Associate Professor Division of Neurosurgery, Department of Surgery Faculty of Medicine Siriraj Hospital, Mahidol University
Original Thai edition: ISBN 974-7445-46-8
This English edition covers Chapters 1–7 and the index, corresponding to pages 1–978 of the Thai original. The original illustrations and reference numbering are retained. This is a draft translation of the author's work, not an English text written by the author. The Thai text remains the reference for checking the translation.
Original printed page (2)
Original publication details
Title
Brain Tumors
Author
Jesada Nimmannitya
First edition
August 1994 (B.E. 2537) · 1,000 copies
ISBN
974-7445-46-8
Statement in the printed edition
All rights reserved · Price: 650 baht
Front cover image
Fronto - temporal meningioma
Cover design
Sathian Saengsalap Graphics Unit, School of Medical Illustration, Faculty of Medicine Siriraj Hospital
Photographic enlargements
Sakda Sukruen Medical Photography Unit, School of Medical Illustration, Faculty of Medicine Siriraj Hospital
Medical students today have greater access to learning materials, as faculty members have compiled or written Thai-language textbooks and study manuals in almost every branch of medicine. Most of these books, however, are translations of foreign-language originals. Some are based on their authors’ own experience, but these are fewer in number.
This textbook on brain tumors by Dr. Jesada Nimmannitya draws on his knowledge and more than 30 years of experience treating neurosurgical patients. It describes in detail the incidence, classification, and pathology of tumors, as well as patients’ symptoms and treatment. Almost all the illustrated examples of brain tumors are from patients treated in Thailand. This is therefore a remarkably comprehensive textbook that will serve medical students, interns, and residents well as both a study manual and a reference.
Professor Vichai Bamrungphol, MD
Original printed pages (5)–(6)
Preface
Brain tumors are an important group of brain diseases that can cause loss of brain function and death. Many patients are diagnosed late, and some reach a neurosurgeon only after their condition has progressed to blindness or unconsciousness. Treatment outcomes are consequently poorer than they should be. Several factors contribute to this situation, but one important factor is that physicians in general still lack basic knowledge of brain anatomy and physiology, the symptoms and signs of brain tumors, and the changes these tumors produce in the brain. It is often apparent that residents in neurosurgery and general surgery, as well as physicians from other specialties rotating through neurosurgery, have limited knowledge of brain tumors.
For more than 20 years I have been responsible for teaching medical students about brain tumors. Throughout my work in neurosurgery, I have taken an interest in collecting a large number of slides showing brain tumor pathology, from brain-cutting examinations and from patients on whom I have operated myself. Believing that this material could be of great benefit to medical students and younger physicians inspired me to write this textbook.
The purpose of this textbook is to provide medical students, residents, and general practitioners with basic knowledge of brain tumors: their pathology, their effects on the brain, symptoms and signs, investigations, methods of treatment, and my own experience. This knowledge should help readers make accurate diagnoses so that patients receive appropriate treatment more promptly. The book therefore does not aim to present a detailed account of the various statistics relating to brain tumors.
New technologies such as C.T. and MRI are indeed excellent aids to the diagnosis of brain tumors. They permit diagnosis at an early stage and have replaced older investigations such as angiography and ventriculography. Nevertheless, I believe that the older methods remain useful for some patients and in settings where C.T. and MRI are unavailable, so they are described briefly here.
The chapter on treatment mainly describes principles and techniques that I have used successfully in many operations for brain tumors, and that physicians may be able to apply after studying this book. Treatment with very expensive new technologies, such as the gamma knife and lasers, is not discussed: I do not yet have expertise in these methods, and they fall outside the purpose of this textbook. Interested readers may consult the relevant journals.
I am deeply grateful to Professor Vichai Bamrungphol, MD, who has continually imparted his knowledge of neurosurgery to me, for kindly writing the foreword to this book. I also thank Professor L. B. Rorke, MD, for her devoted teaching of neuropathology and for providing some of the brain tumor pathology slides specifically for use in this textbook.
Finally, I thank Dr. Suchitra Nimmannitya, former Director of the Children’s Hospital, and Professor Sumalee Nimmannitya, MD, for their tireless help in reviewing and correcting the manuscript.
Jesada Nimmannitya
Original printed pages (7)–(13)
Original contents
Chapter 1 · Introduction Page 1
Causes of brain tumors1
Incidence of brain tumors6
Age of patients with brain tumors8
Preferred locations of brain tumors9
Changes in the brain caused by tumors13
Chapter 2 · Classification of Brain Tumors Page 16
History of brain tumor classification17
WHO Histological Typing of CNS Tumors (1993)45
Chapter 3 · Pathology of Brain Tumors Page 54
Tumors of astrocytic cells55
Astrocytoma56
Fibrillary astrocytoma59
Protoplasmic astrocytoma63
Gemistocytic astrocytoma66
Pilocytic astrocytoma66
Subependymal giant-cell astrocytoma67
Cerebellar astrocytoma69
Optic nerve glioma71
Hypothalamic glioma74
Brain stem glioma76
Anaplastic astrocytoma79
Glioblastoma multiforme82
Tumors of oligodendrocytic cells91
Oligodendroglioma91
Tumors of ependymal cells92
Ependymoma92
Ependymoblastoma98
Tumors of the choroid plexus99
Choroid plexus papilloma99
Malignant choroid plexus papilloma101
Primitive neuroectodermal tumors101
Medulloblastoma101
Desmoplastic medulloblastoma107
Tumors of the pineal gland107
Pineocytoma or pinealocytoma108
Pineoblastoma or pinealoblastoma109
Pinealoma or germinoma109
Teratoma114
Tumors of nerve sheath cells117
Acoustic schwannoma118
Tumors of the meninges122
Meningioma122
Meningotheliomatous type133
Transitional type133
Fibroblastic type135
Angioblastic type136
Malignant meningioma138
Vascular tumors139
Capillary hemangioblastoma140
Maldevelopment tumors146
Craniopharyngioma147
Dermoid and epidermoid tumors151
Colloid cyst155
Lipoma157
Tumors of the pituitary gland158
Pituitary adenoma158
Pituitary adenocarcinoma166
Glomus jugulare tumor167
Chordoma168
Carcinoma of the nasopharynx171
Metastatic brain tumors172
Metastatic melanoma179
Chapter 4 · Pathophysiology of Increased ICP in Brain Tumors Page 184
Intracranial pressure184
Mechanisms regulating intracranial pressure186
Relationship between mass volume and intracranial pressure188
Anatomy of the cranial cavity192
Pathophysiological changes197
Increased intracranial pressure199
Effects of increased ICP on cerebral blood flow (CBF)200
Autoregulation201
Vasomotor response to increased ICP203
Cerebrovascular dysfunction due to increased ICP203
Effects of increased ICP on other systems204
Symptoms and signs of increased intracranial pressure206
Brain displacement and herniation214
Symptoms and signs of brain herniation216
Signs of cingulate herniation216
Signs of central transtentorial herniation217
Signs of uncal and parahippocampal herniation221
Signs of tonsillar herniation228
Signs of upward transtentorial herniation230
Radiological changes in increased intracranial pressure233
Treatment of increased intracranial pressure237
Surgical treatment238
Medical treatment240
Chapter 5 · Symptoms and Signs of Brain Tumors Page 249
General symptoms and signs249
Localizing symptoms and signs of brain tumors250
Frontal lobe250
Parietal lobe259
Occipital lobe263
Temporal lobe268
Thalamus and basal ganglia275
Corpus callosum280
Lateral ventricle283
Hypothalamus284
Third ventricle292
Pituitary gland295
Optic nerve and optic chiasm309
Cavernous sinus309
Superior orbital fissure310
Pineal gland311
Cerebellum317
Fourth ventricle326
Brain stem327
Cerebellopontine angle338
Jugular foramen343
Foramen magnum344
Clivus346
False localizing signs347
Chapter 6 · Investigations Page 353
Changes on skull radiographs caused by brain tumors354
Cerebral angiography374
Normal appearances of carotid angiograms375
Normal appearances of vertebral angiograms382
Angiographic abnormalities in brain tumors393
Angiographic appearances of cerebral herniation393
Local vascular changes caused by brain tumors400
Abnormal circulation in brain tumors430
Computerized tomography (C.T.)442
C.T. appearances of different brain tumors450
Magnetic resonance imaging (MRI)475
MRI appearances of individual brain tumor types483
Advanced investigations507
Chapter 7 · Treatment of Brain Tumors Page 515
General principles of brain tumor treatment515
Preoperative preparation518
Anesthesia in patients with brain tumors522
Postoperative care528
Complications of brain tumor surgery545
Intraoperative complications546
Postoperative complications of brain tumor surgery555
General techniques of brain surgery566
General methods of opening the skull588
Osteoplastic craniotomy586
Opening the posterior fossa600
Ventriculostomy609
Trephination613
Specific treatment for individual brain tumor types615
Surgical treatment of cerebral glioma617
Astrocytoma626
Glioblastoma multiforme641
Oligodendroglioma655
Optic glioma661
Brain stem glioma674
Thalamic glioma683
Ependymoma687
Choroid plexus papilloma694
Medulloblastoma708
Pineal gland tumor716
Acoustic neurinoma725
Meningioma744
Parasagittal meningioma752
Falx meningioma765
Convexity meningioma771
Olfactory groove meningioma782
Tuberculum sellae meningioma789
Sphenoid ridge meningioma794
Tentorial meningioma807
Petrous ridge meningioma817
Foramen magnum meningioma822
Intraventricular meningioma827
Hemangioblastoma835
Craniopharyngioma845
Dermoid and epidermoid tumors869
Colloid cyst874
Pituitary tumor879
Prolactin secreting adenoma905
Growth hormone secreting adenoma911
ACTH secreting adenoma917
Metastatic brain tumor922
Glomus jugulare tumor940
Headings and page numbers follow the original contents, including page 588 appearing before page 586 in Chapter 7.
Original printed pages 1–6
Chapter 1 · Introduction
Brain Tumors
Tumors arising within the brain are an important form of pathology. They are classified as intracranial expanding lesions and cause loss of brain function according to their location. Patients may present with a variety of neurological symptoms. When a tumor becomes large, it raises intracranial pressure and may ultimately cause death. A patient's survival therefore depends in part on the physician's knowledge, experience, and ability to diagnose the disease at an early stage and provide appropriate treatment in time. Most brain tumors arise from cells of the tissues that make up the brain (primary brain tumors), while a smaller proportion spread from cancers of other organs (metastatic brain tumors). Primary tumors may be either malignant or benign. Their nomenclature and classification are discussed in the next chapter.
Brain tumors can, in fact, arise anywhere within the cranial cavity. Experience and reported statistics nevertheless show that many types have characteristic sites of origin. Meningiomas, for example, favor the parasagittal region, the lesser wing of the sphenoid, the olfactory groove, and the tuberculum sellae. Craniopharyngiomas occur in the suprasellar region, and medulloblastomas arise in the cerebellar vermis. Each type also has a characteristic age range and an age at which it occurs most frequently. The relationship between preferred location and age is clinically important because it helps distinguish one tumor type from another.
Causes of Brain Tumors
As with tumors elsewhere in the body, the precise cause of most brain tumors is unknown. However, several factors can contribute to their development:
1. Abnormal development of embryonal cells
This is one cause of tumors, particularly those found in children. Normally, cells develop into parts of the brain with different functions. Some cells may remain as embryonic rests and subsequently grow abnormally to form brain tumors, most of which lie in the midline. Common examples include dermoids, epidermoids, teratomas, craniopharyngiomas, chordomas, and medulloblastomas. Craniopharyngiomas in the pituitary region arise from remnants of the craniopharyngeal duct left during formation of the pituitary gland. Chordomas arise from notochordal remnants. Medulloblastomas were attributed to remnants of the primitive external granular layer of the cerebellum,(1) but are now believed to arise from primitive neuroectodermal tissue.(2)
2. Hereditary factors
Three hereditary disorders associated with brain tumors belong to the phakomatoses, a group of inherited abnormalities affecting the skin, eyes, and nervous system:
von Recklinghausen's neurofibromatosis;
tuberous sclerosis (Bourneville's disease);
von Hippel–Lindau disease.
Von Recklinghausen's neurofibromatosis, known in Thai as “โรคท้าวแสนปม,” is a clear example of an inherited disorder involving tumors of the nervous system. Several members of the same family may be affected. Tumors may occur in the brain, peripheral nerves, and skin. Among intracranial tumors, acoustic neurinoma is the most common; meningiomas and gliomas, including optic nerve gliomas, may also occur. Bilateral acoustic neuroma, or bilateral acoustic neurofibromatosis, is hereditary and has a gene distinct from that associated with peripheral neurofibromatosis.(3) In affected families it is transmitted as an autosomal dominant trait, and affected individuals develop acoustic neuromas on both sides. This differs from nonhereditary acoustic neuroma in that symptoms and signs appear during adolescence, whereas the nonhereditary form usually presents between 40 and 50 years of age.
Tuberous sclerosis is another hereditary disorder that causes abnormalities in the brain and elsewhere in the body. Important diagnostic features are: i) adenoma sebaceum on the face on either side of the nose, in the “butterfly area” (Figure 3.11); and ii) subependymal giant cell astrocytomas along the walls of the lateral and third ventricles. These are usually small nodules, although some may be large (Figure 3.12). The cerebral surface may show nodules (tubers), gliotic cortical plaques, and macro- or microgyria. These abnormalities cause seizures and intellectual disability.
Von Hippel–Lindau disease is an autosomal dominant hereditary disorder(4) involving benign capillary hemangioblastomas together with retinal angiomas. Cerebellar hemangioblastoma is the most common intracranial tumor and may occur as a solitary or multiple lesion. Associated abnormalities in other organs include pancreatic and renal cysts and hypernephroma. The author has encountered this disease in four siblings from the same family.
3. Brain injury
Brain injury has long been suspected as a factor or cause in the development of tumors of the meninges and glial cells, but this has not been clearly proved. Reports describe tumors at sites of previous injury, yet such cases are very rare in relation to the total number of tumors. Cushing and Eisenhardt,(5) however, considered brain injury an important factor in meningioma development. Of their 313 patients, 33% had a history of brain injury; in 24 of these cases the tumor lay at the site of a depressed skull fracture and a scar on the cerebral surface. Other reports have also described tumors at sites of brain injury, chiefly meningiomas. Tumors of neuroepithelial tissue or glial cells are less common in this setting. Most post-traumatic tumors develop many years after the injury. Zülch proposed that, following injury, meningeal or glial cells regenerate abnormally and become a focus of tumor formation.(6)
These tumors may give rise to legal questions. Zülch(7) proposed the following criteria for considering a brain tumor causally related to a brain injury:
The patient must have been normal before the injury.
The head injury must have been severe enough to damage the brain and meninges and initiate chronic regenerative processes.
The tumor's location must correspond to the site of brain injury.
A sufficiently long interval must separate the injury and development of the tumor. The interval may vary, but development within two or three weeks is unlikely; most such tumors arise years after injury.
The tumor must be established histologically. This may be problematic: a cerebral scar, for example, may be histologically indistinguishable from a low-grade astrocytoma.
4. Radiation
It has long been known that irradiation of the central nervous system can later cause brain necrosis at the irradiated site.(8) It may also cause tumors, including fibrosarcoma, meningioma, astrocytoma, and glioblastoma multiforme. Of these, fibrosarcoma has been reported most frequently. The mechanism by which radiation causes brain tumors remains unexplained. To attribute a tumor to radiotherapy, it must occur within the irradiated area after a sufficiently long interval, generally between 5 and 12 years.(9) The latency is related to the radiation dose: the higher the dose, the shorter the interval before tumor development.
Fibrosarcoma has been reported after radiotherapy for pituitary tumors.(10) Russell and Rubinstein also reported a patient with a well-circumscribed giant-cell glioblastoma of the frontal lobe that was completely removed. Six years after radiotherapy, a dural fibrosarcoma developed at the operative site.(11) Zülch(12) found a fibrosarcoma at an irradiated site six years after treatment of a hemispheric ependymoma.
Meningiomas have been reported after radiotherapy for pituitary tumors, glial tumors, and scalp disorders. Iacono and colleagues(13) reported multiple meningiomas following radiotherapy for medulloblastoma.
Modan and colleagues(14) reported a statistically significant study of 10,902 Israeli children treated with radiation for tinea capitis. Comparison with children who had not received radiation, 12–23 years later, showed a fourfold higher occurrence of meningioma in the irradiated group.
In 1988, Ron and colleagues(15) followed 10,834 patients who had received radiotherapy for tinea capitis. Brain tumors were 8.4 times more frequent in the irradiated group than in the unirradiated group. Most were meningiomas, gliomas, or nerve sheath tumors.
5. Immunological disorders
Immunosuppression is now known to play an important role in tumor development after organ transplantation. Some patients who undergo renal transplantation with complete immunosuppression subsequently develop brain tumors, chiefly lymphomas and sarcomas.(16),(17)
Three groups are at risk of developing non-Hodgkin's lymphoma of the central nervous system: i) organ transplant recipients; ii) patients with AIDS; and iii) patients with congenital immunodeficiency syndromes. Among these lymphomas, the proportion occurring in kidney and heart transplant recipients has been reported as high as 30%.(16)
6. Viruses
Viruses can cause brain tumors in experimental animals. Their role in humans remains uncertain, and it has not been proved that viruses cause human brain tumors. However, virus-like particles have been found within brain tumors.
7. Chemicals
No chemical is currently known to be a cause of brain tumors in humans. Nevertheless, several chemicals, including ethyl- and methylnitrosourea, can cause nervous system tumors in experimental animals.(19) Methylcholanthrene, anthracycline, and other anthracene derivatives can also produce nervous system tumors.
Original printed pages 6–9
Incidence of Brain Tumors
The reported incidence of different brain tumor types varies, in part according to whether the figures come from neurosurgical operations or neuropathological autopsies. A surgeon's particular expertise in operating on certain tumor types or locations may affect the statistics. Referral centers receiving patients from other hospitals for surgery will also report higher numbers. Other factors contributing to differences include:
1. Classification of brain tumors. The brain contains various neural elements, including glia, neurons, and cranial nerves, as well as the meninges, pituitary gland, and pineal gland. Cells in these structures can give rise to tumors. Brain tumors have long been classified according to their histopathological characteristics and biological behavior. Several systems have been used, including those of Kernohan and Sayre, WHO (see Chapter 2), and Zülch. They differ in some respects, and the names of certain tumors have also changed. These factors make comparisons of incidence difficult.
2. Heterogeneity within a tumor. Some brain tumors, such as malignant gliomas, show different degrees of malignancy in different areas. One area may resemble a low-grade astrocytoma, while areas showing necrosis and vascular proliferation represent high-grade astrocytoma. Examination of a small biopsy may therefore misrepresent the degree of malignancy and distort incidence figures. The true degree of malignancy must be assessed from the entire tumor or at autopsy.
In some cases a glioma becomes more malignant with time. In the author's experience, this has often been observed at a second or third operation.
3. Autopsy rates. These differ between institutions. A hospital with a high autopsy rate has a greater opportunity to detect brain tumors that have not yet caused symptoms.
4. Tumor location. Tumors in critical locations, such as the brain stem, sometimes cannot be sampled for examination and are diagnosed using CT and MRI. The appearances on these studies are not specific to brain tumors, so the diagnosis may be mistaken. A ring-shaped lesion, for example, may be a brain abscess, metastatic tumor, or glioblastoma.
Despite these variations, a review of published reports(20, 22, 23, 24, 25, 26) indicates that gliomas are the most common brain tumors (40–50%), followed by meningiomas (15–20%), acoustic neurinomas, pituitary adenomas, and metastatic tumors, in that order. The reported incidence of metastatic tumors varies considerably depending on whether the data come from autopsy or surgery. Lung cancer is the most common primary source of brain metastases, followed by cancers of the breast, gastrointestinal tract, and kidney. In 60–80% of metastatic brain tumors, lesions are found at multiple sites within the brain.
The incidence of each tumor type at different ages and locations is important because it contributes to the diagnosis. Some tumors occur only in children and are not found in adults, while others occur in adults but not in children. The patient's sex is less important than age and location.
Age Incidence
The precise age at which a tumor begins cannot be determined, because early tumors do not cause symptoms. Reported age therefore means the patient's age at hospital admission or, for an untreated patient, at death. All types of brain tumor may occur at any age, but most occur from approximately the end of the first decade through middle age. They are less common before age ten and after age seventy. Tumors frequently seen in young children and adolescents include gliomas of the cerebellum, brain stem, optic nerve, and hypothalamus; craniopharyngiomas; pinealomas; teratomas; and medulloblastomas, described here as tumors occurring specifically in children within the first decade of life.
The number of brain tumors occurring in childhood decreases during adolescence, gradually rises again in middle-aged adults, and falls once more in old age.(27)
Common tumors in middle age include meningiomas; gliomas of the cerebral hemisphere, particularly glioblastoma multiforme; acoustic schwannomas and other cerebellopontine angle tumors; and pituitary adenomas. Metastatic tumors tend to occur in later middle age.
In old age, most tumors are glioblastomas, meningiomas, acoustic schwannomas, or metastatic tumors.
Studies show that each tumor type not only occurs across different age ranges but also has a different age of peak incidence, as shown in Table 1.1.
Table 1.1. Age ranges and peak incidence of brain tumors. Black bars: age range in which the tumor occurs. White segments: the most frequent age range. The original chart is retained; the Thai axis label means “Age,” and the two Thai legend labels correspond to the descriptions above.
Original printed pages 9–13
Preferred Locations of Brain Tumors
Tumor location is important for both diagnosis and prognosis. Different locations present different degrees of difficulty, risk, and complications in surgical treatment, with corresponding differences in outcome. A tumor on the cortical surface is easier to remove than one adjacent to the brain stem.
In a study of 510 patients of all ages who underwent surgery for brain tumors, most tumors were supratentorial (66.3%), while 37.7% were infratentorial. Approximately two-thirds of supratentorial tumors lay in the cerebral hemispheres, including the basal ganglia and lateral ventricles. The remaining third occurred in the pituitary fossa, diencephalon, third ventricle, or pineal gland. Within the hemispheres, the frontal lobe was the most common site and the occipital lobe the least common. The parietal and temporal lobes were affected in approximately equal numbers. The higher frequency in the frontal lobe may reflect its larger volume of brain tissue, whereas the smaller occipital lobe offers less opportunity for tumor development.
Of infratentorial tumors, approximately half were in the cerebellum and fourth ventricle, another 20% in the brain stem, and 30% outside the brain stem in the cerebellopontine angle, foramen magnum, clivus, or tentorium.
An important difference between childhood and adult brain tumors concerns their location. Approximately 60–70% of childhood brain tumors are infratentorial and 40% supratentorial. In adults, approximately 60% are supratentorial.
In children within the first decade of life, the most common infratentorial tumor is cerebellar medulloblastoma. It arises in the posterior velum of the fourth ventricle, grows in the cerebellar midline, and extends into the fourth ventricle and cerebellar hemispheres. Next in frequency are ependymoma of the fourth ventricle and cerebellar astrocytoma. During adolescence, however, cerebellar astrocytomas become more frequent, while medulloblastomas and ependymomas become less frequent. Astrocytomas usually lie in the cerebellar hemispheres and are most often benign cystic astrocytomas. Pilocytic astrocytomas also favor the brain stem in children under ten. Cerebellar hemangioblastomas, acoustic neurinomas, and meningiomas are not found in young children and occur predominantly in middle-aged adults.
Other brain tumor types and their preferred locations at different ages in children and adults are summarized in Figures 1.1 and 1.2.
Colour interpretation; refer to the original for anatomical details.Figure 1.1. Types and locations of brain tumors in children.
Meningiomas occur in middle-aged adults and have characteristic preferred locations. They are commonly found along the cerebral convexity, falx and parasagittal region, olfactory groove, tuberculum sellae, tentorium, petrous ridge (Figure 1.3), and foramen magnum. Intraventricular meningiomas and those involving the optic nerve sheath and canal are less common.
Colour interpretation; refer to the original for anatomical details.Figure 1.3. Common intracranial locations of meningiomas.
Original printed pages 12–14
Changes in the Brain Caused by Tumors
A brain tumor produces two important types of change in the brain:
1. Brain edema around the tumor (Figure 1.4). Compression of arteries and veins slows arterial flow and obstructs venous drainage, causing hypoxia in the surrounding brain and disruption of the blood–brain barrier. During surgery, the capillaries can be seen to be compressed and narrowed, while the brain appears pale and swollen.
Edema also depends on the nature, type, size, and location of the tumor. Different tumors have different toxic effects on the brain and therefore cause varying degrees of edema. Malignant tumors, such as metastatic tumors, glioblastoma multiforme, sarcomas, and lymphomas, may cause extensive swelling. A characteristic feature of metastatic tumors is marked edema even when the tumor itself is small (Figure 1.4). In contrast, infiltrating gliomas such as grade I and II astrocytomas and oligodendrogliomas produce very little change in the surrounding brain, and edema is uncommon. Meningiomas likewise generally cause little surrounding edema, except those in the parasagittal region or sphenoid wing, or those that are very large. These frequently produce marked edema, which can be explained by disruption of venous circulation.
Restored colour slide · Numbering follows Figure 1.4.Figure 1.4. Edema of the brain surrounding a tumor. 1. Tumor. 2. Brain edema.
In general, tumor size alone seldom causes a very large rise in intracranial pressure. A marked and rapid rise usually results from the combined effects of four abnormalities: the tumor itself, brain edema, obstruction of cerebrospinal fluid pathways, and venous congestion. If the tumor does not obstruct cerebrospinal fluid flow, peritumoral edema is the most important factor causing focal loss of brain function and symptoms of raised intracranial pressure. The more rapidly edema develops, the more rapidly brain function, including the level of consciousness, deteriorates.
2. Displacement effect. Compression by the tumor and increased intracranial pressure displace brain tissue from areas of higher pressure toward areas of lower pressure, producing herniation at various sites, as discussed in a later chapter. These changes in turn progressively increase edema through ischemia and impair the function of other parts of the brain, particularly the vital structures of the brain stem.
Original printed pages 14–15
References · Chapter 1
Bibliographic entries retain the wording and numbering of the original edition.
Matson D.D.,: Tumors of posterior fossa, in Neurosurgery of infancy and childhood, Charles C. Thomas Pub. p 448-449, 1969.
Rorke L.B.,: The Cerebellar Medulloblastoma and Its Relationship to Primitive Neuroectodermal Tumors. J. of Neuropath. and Experiment. Neurol. Vol. 42, pp 1-15, 1983.
Kanter W.R., Eldrige R., Fabricant R., Allen J.C., Koerber T.: Central neurofibromatosis with bilateral acoustic neuroma : Genetic, clinical and biochemical distinction from peripheral neurofibromatosis. Neurology (N.Y.) 30 : 851-859, 1980.
Horton W.A., Wong V., Eldridge R.,: Von Hippel-Lindau disease. Arch. Internal Med. 136 : 769-777, 1976.
Cushing H., and Eisenhardt, L., : Meningiomas : Their classification, Regional behavior, Life, History, and Surgical end results, Springfield, Ill. Charles C. Thomas, 1938.
Zulch K.J. and Mennel H.D., : Biology of brain tumors in Tumors of the Brain and Skull Ed. by Vinken P.J. and Bruyn G.W. North-Holland Pub. Co., vol. 16 : 1-55, 1974.
Zulch K.J., : The origin of brain tumors. In Brain tumors, their biology and pathology, Springer Verlag pp. 76-77, 1986.
Bouchard, J., Radiation Therapy of Tumors and Diseases of the Nervous System, Lea & Febiger Pub. pp. 31-42, 1966.
Walker J.S., Bigner D.D., Radiation-induced brain tumors in Neurosurgery ed. by Wilkins R.H. and Rengachary, Mc Grawhill Co. pp. 525-527, 1985.
Waltz TA, Brownell B. : Sarcoma : A possible late result of effective radiation therapy for pituitary adenoma : Report of 2 cases J. Neurosurg. 24 : 901-907, 1966.
Russell D.S., and Rubinstein, L.J. : Pathology of Tumors of the Nervous System 2nd Ed. London, Arnold, 1963.
Zulch K.J. : Brain Tumors. Their Biology and Pathology 2nd Ed. N.Y. Springer Verlag, 1965.
Iacono R.P., Apuzzo M L J, Daves RL, Tsai Fy : Multiple meningiomas following radiation therapy for medulloblastoma : Case report. J. Neurosurg. 55 : 282-286, 1981.
Modan, B., Baidatz, D., Mart, H., Steinitz, R., and Levin, S.G., Radiation induced head and neck tumors. Lancet 1 : 277-279, 1974.
Ron, E., Modan B., Boice J.D., Alfandary, E., Stovall, M., Chetrit, A., and Katz, L. Tumors of the brain and nervous system after radiotherapy in childhood N. Engl. J. Med. 319, 1033, 1988.
Varadachari C., Palutke M., Climie ARW., Weise R.W., Chason JL. ; Immunoblastic sarcoma (histeocytic lymphoma) of the brain with B. cell markers J. Neurosurg. 49 : 887-893, 1978.
Hoover R., Fraumeni J.F. : Risk of cancer in renal transplant recipients. Lancet II : 55-57, 1973.
Hochberg F.H., Gabbai A.A., Risk factors in development of glioblastoma and other brain tumors in Neurosurgery Update I by Wilkins RH & Rengachary SS. p. 242-243, 1990.
Wechsler, W., Kleihues, P., Matsumoto, S., Zulch K.J., Ivankovic S., Preussmann, R., and Druckrey H. : Pathology of experimental neurogenic tumors chemically induced during prenatal and postnatal life, Ann. N.Y. Acad. Sci., 159 : 360-408, 1969.
Schoenberg, B.S., Christine, B.W., and Whisnant, J.P., The descriptive epidemiology of primary intracranial neoplasms : The Connecticut experience. Am, J. Epidemiology. 104, 499., 1976.
Walker, A.E., Robins, M., and Weinfeld F.D., Epidemiology of Brain tumors : The National Survey of Intracranial Neoplasms. Neurology, 35 : 219, 1985.
Heshmat, M.Y., Kovi, J., Simpson, C., Kennedy, J., and Fan, K.J., Neoplasms of the central nervous system : incidence and population selectivity in the Washington D.C. Metropolitan area. Cancer. 38, 2135, 1976.
Fan, K.J., Kovi, J., and Earle, K.M., The ethnic distribution of primary central nervous system tumors : AFIP, 1958,1970 J. Neuropathol. Exp. Neurol. 36, 41, 1977.
Cheng, M.K., Brain tumors in the People’s Republic of China : A statistic review. Neurosurgery, 10, 16, 1982.
Wen-Qing, H., Shi Ju. Z., Qing-Sheng, T., Jian-Qing, H., Yu-xia, L., Qing-Zhong, X., Zi-Jun, L., and Wen Cui, Z., Statistical analysis of central nervous system tumors in China J. Neurosurg. 56, 555, 1982.
Kepes, J.J., Chen, W.Y.K., Pang, L.-C., and Kepes, M., Tumors of the central nervous system in Taiwan, Republic of China, Surg. Neural. 22, 149, 1984.
Butler, A.B., Brooks, W.H., and Netsky, M.G., Classification and biology of brain tumors in Neurological Surgery by Youmans J.R., Saunders, W.B.Co. Vol. 5 : 2682-2684, 1982.
Original pages 16–21
Chapter 2 Classification of brain tumors
(Classification of brain tumors)
Tumors arising within the skull or brain originate from the various cells that constitute the brain tissue, blood vessels, and meninges. Each tumor therefore differs in its characteristics and course, including its morphology, biological behavior, and prognosis. Brain tumors must be classified into groups and named to provide a common understanding and allow neuropathologists, neurosurgeons, and neurologists to exchange knowledge for the benefit of treatment and prognostication. Classification nevertheless remains problematic, and no system is universally accepted as the best. Even at present, agreement has not been reached on the names of several brain tumors. The same tumor may have different names, while different tumors sometimes share a name. This confusion occurs among tumors of neuroepithelial tissue. Differences in the names and definitions of individual brain tumors can make statistical comparisons of surgery, radiotherapy, and chemotherapy misleading.
Despite advances in techniques for identifying the specific characteristics of individual cell types by electron microscopy and immunohistochemistry, a complete classification of brain tumors is still not possible. Conventional microscopy and staining techniques remain necessary, including hematoxylin and eosin (H & E), phosphotungstic acid–hematoxylin (PTAH), and silver stains, to identify the tumor type.
Early attempts to classify brain tumors relied solely on gross appearances, using descriptions such as fatty, fleshy, bony, cystic, or spongy. These could not clearly identify the tumor type. Subsequently, following the discovery of the various cells of the nervous system during the first half of the nineteenth century by Schleiden, Schwann, and Virchow, and the introduction of microscopy, a histological classification(1) divided brain tumors into broad groups named after the predominant cell type. For example, a tumor composed mainly of glial cells was called a glioma.
History of brain tumor classification
The most difficult brain tumors to classify are those of the neuroepithelial group (also called neuroectodermal or medullary epithelium). From the earliest attempts until about 1930, at least four classifications of gliomas had been proposed: i) Bailey and Cushing (1926), ii) Roussy and Oberling, iii) Penfield, and iv) Bergstrand. Some tumor names were shared between these classifications and others differed, causing confusion. Of these four systems, Bailey and Cushing’s classification became the most widely known throughout the world.
Bailey and Cushing Classification
In 1926, Bailey and Cushing,(2) neurosurgeons with extensive knowledge of neuropathology, studied patients with gliomas using conventional stains and the metallic impregnation techniques of Roman Y Cajal and Del Rio Hortega. They demonstrated the various tumor cell types and compared them with normal cells from their earliest embryonic stages through maturation (cytogenesis or histogenesis). They believed that the cells of different gliomas arose from cells at different developmental stages, and named the tumors after the corresponding cell type at that stage. Bailey and Cushing divided cells developing from primitive medullary or neural epithelium into five groups: 1) choroid epithelium, 2) pineal parenchymal cells, 3) primitive spongioblasts, 4) medulloblasts, and 5) apolar neuroblasts.
Figure 2.1 Development of cells from medullary epithelium and the types of brain tumors arising at different stages of cell development (Bailey and Cushing, 1926).
The developmental diagram of cells arising from medullary epithelium (Figure 2.1) shows medulloblasts as immature cells capable of giving rise to two further immature cell types: spongioblasts and neuroblasts. Taken together, the tumors arising at the different developmental stages of each group comprise 14 types (Table 2.1).
Table 2.1 Classification of gliomas according to Bailey and Cushing
1. Medulloepithelioma
2. Medulloblastoma
3. Pinealoblastoma
4. Pinealoma
5. Ependymoblastoma
6. Ependymoma
7. Neuroepithelioma
8. Spongioblastoma
a. multiforme
b. unipolare
9. Astroblastoma
10. Astrocytoma
a. protoplasmaticum
b. fibrillary
11. Oligodendroglioma
12. Neuroblastoma
13. Ganglioneuroma
14. Papilloma choroideum
Thus, tumors may arise at either immature or mature cellular stages. Bailey and Cushing also studied the location, age, survival time after surgical treatment, and biological behavior of each tumor type. They found that tumors arising at an undeveloped, immature cellular stage grew rapidly and were associated with short survival, whereas tumors arising at a mature cellular stage grew slowly and patients survived longer. Bailey and Cushing’s classification therefore provided an important foundation for neuropathological and clinical understanding and for prognosis. Most of these tumor names remain in use to the present day; only a few have changed, and new names have been proposed for some.
Medulloepithelioma denotes a malignant tumor arising from primitive cells and occurring in young children. This name remains in use.
Medulloblastoma is a malignant tumor located in the cerebellar vermis. It consists of primitive cells that can develop into undifferentiated (immature) cells along two pathways (bipotential differentiation): i) the unipolar spongioblast pathway, which develops into astroblasts and astrocytes, and ii) the unipolar neuroblast pathway, which subsequently develops into multipolar neuroblasts and ultimately neurons (Figure 2.1). Thus, a medulloblastoma may contain several cell types. Rorke(3,4) proposed renaming medulloblastoma, together with neuroblastoma, pineoblastoma, and ependymoblastoma, under the term primitive or undifferentiated neuroectodermal tumor (PNET), for the following reasons: 1) brain tumors with the same histology as medulloblastoma can occur elsewhere in the CNS—for example, in the pineal gland, where they are called pinealoblastomas, or in the cerebrum or spinal cord, where they are called neuroblastomas. Without knowing their site of origin, one cannot distinguish a medulloblastoma from a neuroblastoma or pinealoblastoma. 2) These tumors have the same biological behavior. 3) Wherever they occur, in addition to undifferentiated cells, they may contain astrocytes, oligodendrocytes, ependymal cells, neuronal cells, or mesenchymal cells such as smooth or striated muscle. Some tumors may contain more than one mature or immature cell type. 4) Cerebellar medulloblastoma is a heterogeneous tumor with various histological patterns.(5)
Pinealoblastoma is a malignant tumor composed of undifferentiated cells of the pineal gland. This name remains in use, although Rorke proposed placing it in the primitive neuroectodermal tumor group, like medulloblastoma. Tumors arising from mature (differentiated) pineal cells are still called “pineocytomas.” “Pinealoma” is a name used for tumors in this region that does not correctly identify their cellular origin.
Ependymoblastoma is also a malignant tumor composed of primitive cells, like medulloblastoma and pinealoblastoma. Its distinguishing diagnostic feature is the presence of ependymal rosettes. It too occurs in children. Ependymoma remains an appropriate, well-defined name that is still in use.
Neuroepithelioma is a confusing name. It has been used for ependymoma(6) and for brain tumors composed of primitive cells that would more appropriately be called medulloepitheliomas. In addition, malignant tumors of the peripheral nervous system composed of primitive cells have also been called neuroepitheliomas.
Spongioblastoma has been renamed “glioblastoma.” It is malignant and contains cells of many forms, hence the name “glioblastoma multiforme.” Astroblastoma, astrocytoma, oligodendroglioma, neuroblastoma, ganglioneuroma, and choroid plexus papilloma have remained in use to the present day.
Original pages 21–24
Classification systems
ROUSSY AND OBERLING CLASSIFICATION
Five years after Bailey and Cushing’s report appeared, Roussy and Oberling(7) (1931) criticized their classification of brain tumors based on cytogenesis as an unproven hypothesis. They suggested that tumors arose through transformation of cells into tumor cells, and divided gliomas into five groups (Table 2.2). The first two groups each contained three subtypes; these tumors arose from glial cells, ependyma, and choroid plexus. The remaining three groups arose from neuronal cells, with neurospongiomas and neuroepitheliomas originating from primitive cells.
Table 2.2 Classification of gliomas according to Roussy and Oberling
Following Bailey and Cushing’s classification, Penfield(8) proposed a new classification of gliomas in 1931, retaining their principles with only minor modifications. Penfield divided gliomas into ten types (Table 2.3).
Table 2.3 Classification of gliomas according to Penfield, 1931
Astrocytoma
Glioblastoma multiforme
Medulloblastoma
Ependymoma
Astroblastoma
Spongioblastoma polare
Oligodendroglioma
Oligodendroblastoma
Neuroepithelioma
Pinealoma
BERGSTRAND’S CLASSIFICATION
In 1932, Bergstrand(9) studied and classified gliomas differently from other investigators. He separated them into “benign” and “malignant” groups according to their biological behavior in relation to clinical findings. Each group contained three subtypes. The remaining two groups were tumors with their own distinctive cellular characteristics (Table 2.4).
Table 2.4 Classification of gliomas according to Bergstrand
Benign group
Astrocytoma fibrillare
Astrocytoma protoplasmaticum
Astrocytoma gigantocellulare
Malignant group
Glioblastoma multiforme
Glioblastoma fusiforme
Glioblastoma protoplasmaticum
Ependymoma
Oligodendroglioma
RIO-HORTEGA’S CLASSIFICATION
In 1934, Rio-Hortega(10) proposed a classification of brain tumors based on cytogenesis, without considering clinical correlations or biological behavior. The important feature of Rio-Hortega’s method was the division of the development of medullary epithelium into two groups: 1) those related to gliomas, and 2) those related to paragliomas (Figure 2.2). Cell types were analyzed and distinguished by metallic impregnation, a technique that frequently produced errors. Because of these shortcomings, Rio-Hortega’s classification represented a step backward and did not gain popularity.
Figure 2.2 Rio-Hortega’s classification of gliomas.
Original pages 25–27
KERNOHAN’S CLASSIFICATION
In 1952, Kernohan and colleagues(11,12) proposed dividing the different types of gliomas into four grades, I to IV, according to malignancy, based on cellular differentiation. Grade I anaplasia corresponded to a benign tumor, grades III and IV to malignant tumors, and grade II was intermediate between the two.
Table 2.5 Classification of gliomas according to Kernohan
1. Astrocytoma
Astrocytoma = astrocytoma grade I
Astroblastoma = astrocytoma grade II
Polar spongioblastoma = (obsolete)
Glioblastoma multiforme = astrocytoma grade III and IV
Neurocytoma, Ganglioneuroma, Gangliocytoma = Neuroastrocytoma grade I
Ganglioglioma, Neuroblastoma, Spongioneuroblastoma, Glioneuroblastoma = Neuroastrocytoma grade II - IV
5. Medulloblastoma
Medulloblastoma
Thus, grading can be applied to astrocytomas, ependymomas, oligodendrogliomas, and neuroastrocytomas. Medulloblastoma, however, is inherently malignant and does not need to be graded.
Kernohan’s method became widely popular among pathologists and neurosurgeons because it was easy to use and also indicated prognosis. Nevertheless, it had several disadvantages:
The grade obtained from a biopsy may not reflect the tumor’s true malignancy. It is well known that different parts of a glioma may differ in malignancy. The surface may show the features of a benign astrocytoma (grade I), while deeper regions show glioblastoma (grades III and IV). Examining only a small tissue specimen may therefore lead to an incorrect assessment of malignancy. The whole tumor must be examined to determine the grade and prognosis accurately. Furthermore, gliomas progressively become more malignant (higher grade) over time. Biopsy or repeat surgery after tumor recurrence demonstrates this increase in malignancy.
Only astrocytoma shows a good correlation between its histological appearance (the various grades) and its clinical course. In practice, grading is therefore used mainly for astrocytomas. Oligodendrogliomas and ependymomas differ. In oligodendroglioma, histological appearances do not correlate with the postoperative clinical course, and experience suggests that histological differences are usually not great enough to require four grades. Similarly, high-grade malignancy is very rare in ependymoma, so attempts to grade it seem to have little practical importance.
In tumors composed of several cell types (mixed-cell tumors), cytological grading makes accurate characterization difficult.(13)
In some patients, the clinical circumstances may be more important for prognosis than the apparent malignancy of the tumor itself. Examples include tumors obstructing the cerebrospinal fluid pathways or involving vital brain centers, described as “malignant in location.” In these cases, grading has no significance.
RUSSELL & RUBINSTEIN CLASSIFICATION(14)
Russell and Rubinstein classified tumors derived from neuroepithelium as shown in Table 2.6.
Table 2.6 Classification of tumors of neuroepithelial tissue according to Russell and Rubinstein
A. Tumors of neuroglial cells
I. Astrocytic group
1. Astrocytoma
2. Astroblastoma
3. Polar spongioblastoma
II. Oligodendroglia
Oligodendroglioma
III. Ependymoma
1. Ependymoma
2. Subependymoma
3. Ependymoblastoma
IV. Anaplastic
Glioblastoma multiforme
B. Tumors of neuronal cells and primitive bipotential precursors
I. Medulloepithelioma
II. Medulloblastoma and cerebellar neuroblastoma
III. Cerebral neuroblastoma
IV. Gangliocytoma and ganglioglioma
C. Tumors of specialized tissue of central neuroepithelial origin
I. Neuroepithelial tumors of the retina
1. Retinoblastoma
2. Medulloepithelioma
3. Adult glioma (astrocytoma)
II. Glioma of the optic nerve and chiasm
III. Tumors of the neurohypophysis
1. Astrocytoma
2. Granular cell tumors
IV. Tumors of the parenchymal and glial cells of the pineal body
1. Pineoblastoma
2. Pineocytoma
3. Glioma
(a) Astrocytoma
(b) Glioblastoma
V. Tumors of the choroid plexus epithelium
1. Papilloma
2. Carcinoma
Original pages 28–32
WORLD HEALTH ORGANIZATION CLASSIFICATION
Although many tumor classifications had been proposed, they remained incomplete, controversial, and not universally accepted, particularly for tumors of the neuroepithelial group. In 1976, the World Health Organization therefore convened neuropathologists from more than 50 countries to develop a globally accepted classification covering all brain tumors. In 1979, the resulting new classification was published as Histological Typing of Tumors of the Central Nervous System,(15) as shown in Table 2.7.
Table 2.7 WHO classification of brain tumors (1979)
I. Tumors of Neuroepithelial tissue
A. Astrocytic tumors
1. Astrocytoma
(a) Fibrillary
(b) Protoplasmic
(c) Gemistocytic
2. Pilocytic astrocytoma
3. Subependymal giant-cell astrocytoma (ventricular tumor of tuberous sclerosis)
A. Haemangioblastoma (capillary haemangioblastoma)
B. Monstrocellular sarcoma
VI. Germ cell tumors
A. Germinoma
B. Embryonal carcinoma
C. Chorio-carcinoma
D. Teratoma
VII. Other malformative tumors and tumor-like lesions
A. Craniopharyngioma
B. Rathke’s cleft cyst
C. Epidermoid cyst
D. Dermoid cyst
E. Colloid cyst of the third ventricle
F. Enterogenous cyst
G. Other cysts
H. Lipoma
I. Choristoma
J. Hypothalamic neuronal hamartoma
K. Nasal glial heterotopia
VIII. Vascular malformations
A. Capillary telangiectasia
B. Cavernous angioma
C. Artereovenous malformation
D. Venous malformation
E. Sturge - Weber disease
IX. Tumors of the anterior pituitary
A. Pituitary adenoma
1. Acidophil
2. Basophil
3. Mixed acidophil-basophil
4. Chromophobe
B. Pituitary adenocarcinoma
X. Local extensions from regional tumors
A. Glomous jugulare tumor
B. Chordoma
C. Chondroma
D. Chondrosarcoma
E. Liposarcoma
F. Olfactory neuroblastoma
G. Adenoid cystic carcinoma
H. Others
1. Osteoma
2. Osteosarcoma
3. Nasopharyngeal tumors
XI. Metastatic tumors
XII. Unclassified tumors
Original pages 33–38
Considerations in brain tumor classification
The WHO classification still follows Bailey and Cushing’s approach. Glioblastoma is placed in the poorly differentiated and embryonal tumor group, together with medulloblastoma and medulloepithelioma. Some have objected that it should belong with anaplastic astrocytoma, as in Russell and Rubinstein’s classification of tumors of neuroepithelial tissue(14) (Table 2.6), which places glioblastoma multiforme among the anaplastic tumors of neuroglial cells. Russell and Rubinstein(14) further divided astrocytomas into eight types according to their cellular characteristics:
Protoplasmic
Fibrillary (a) diffuse (b) circumscribed
Pilocytic
Gemistocytic
Subependymal giant cell
Pleomorphic xanthoastrocytoma
Desmoplastic cerebral astrocytoma of infancy
Anaplastic
The first four types describe the distinctive features of the astrocytic cells. Subependymal giant-cell astrocytoma contains large cells and is frequently associated with tuberous sclerosis. Pleomorphic xanthoastrocytoma contains cells of various shapes (pleomorphism), often with intracellular fat. Desmoplastic cerebral astrocytoma of infancy occurs at the brain surface, is found only in children, and has characteristic dense adhesions (intense desmoplasia).(16) Anaplastic astrocytoma is a malignant glioma commonly found in adults. Its severity approaches that of glioblastoma, although its prognosis is usually better. In a grading system, it would be grade III.
The WHO meeting pointed out that tumors of neuroepithelial tissue may contain more than one cell type. For example, an astrocytoma may contain several types of astrocytic cells, or an oligodendroglioma may also contain astrocytic cells. Naming such a tumor after only one cell type is inaccurate and does not describe its true histology. A mixed name based on the observed cells is therefore necessary. A tumor containing astroblasts and oligodendrocytes is called an astroblast-oligodendroglioma. A tumor containing cells of different tissues, such as glioblastoma and sarcoma, is called a mixed glioblastoma and sarcoma. In their proposed classification of childhood brain tumors, Rorke et al.(3) assigned tumors containing several cell types to a separate mixed-glioma group (Table 2.8), with names reflecting the cells seen microscopically and thus indicating the tumor’s composition. Some contain three cell types, as in oligoastroependymoma. Although these names correctly identify the constituent cells, they become excessively long.
Confusion persists over the names and definitions of pineal tumors. The pineal gland contains parenchymal cells, including i) pineocytes and ii) glial cells or astrocytes, which can become neoplastic. WHO divides pineal tumors into pineocytoma or pinealocytoma, a tumor of mature cells, and pineoblastoma or pinealoblastoma, a tumor of immature cells. Both are very rare. Russell and Rubinstein also include glial tumors of the pineal gland—astrocytoma and glioblastoma (Table 2.6)—which are likewise very rare.
In addition to the pineal parenchymal and glial cells already mentioned, germ cells may be present within or adjacent to the gland. These can give rise to two tumor types: i) germinoma or atypical teratoma,(17) containing two cell types, is the most common tumor in the pineal region, although WHO places it among germ-cell tumors. In practice, it is often called pinealoma, a name that does not correctly reflect its cell of origin. ii) Typical teratoma is a true teratoma containing tissues or organ-like components derived from all three germ layers.
Krabbe(18) introduced the name pinealoma for a pineal tumor whose histology resembled the normal pineal gland of an infant. It contained two cell types: large, mature, lightly staining cells and small, darkly staining, lymphocyte-like cells. The cells formed separate groups with a mosaic appearance. Thus, in Krabbe’s usage, pinealoma meant a pineal tumor composed of two cell types.
In 1947, Friedman(19) concluded that most pineal tumors had the histology of germinoma or testicular seminoma, which, like pinealoma, also contained two cell types. It is now accepted that most tumors called pinealomas are actually germ-cell tumors, or germinomas, and the two names have often been used together or interchangeably.
However, Riverson and Zulch(20) and Sano(21) emphasized that pineal-region tumors containing two cell types could be divided into two kinds: one arising from pineal parenchyma and the other from germ cells. Zulch(22) gave detailed pathological and biological reasons for this distinction.
For ease of understanding, pineal tumors may therefore be classified as follows:
1. Tumors of pineal parenchymal cells
1.1 Pineocytoma (a single mature cell type)
1.2 Pineoblastoma (immature cells)
1.3 Pinealoma (two cell types, as in germinoma)
1.4 glioma :-
1.4.1 astrocytoma
1.4.2 glioblastoma
2. Germ-cell tumors
2.1 Germinoma (two cell types, as in pinealoma), or atypical teratoma
2.2 Teratoma or typical teratoma (cells or organ-like tissues derived from all three germ layers)
WHO divides tumors of nerve-sheath cells into two types, each with benign and malignant forms. Their familiar names have not changed: i) neurilemmoma or schwannoma, indicating the cell of origin, the Schwann cell. Thus, schwannoma is a more appropriate name than neurilemmoma or neurinoma. This tumor lies on the surface of the nerve and consists of densely packed spindle cells, arranged in parallel in some areas. ii) Neurofibroma is found in multiple neurofibromatosis, known in Thai as the “disease of a hundred thousand knots.” The nerve becomes a tumor composed of axons and collagenous fibers.
Among tumors of meningeal tissue, meningiomas are the most common and have distinctive features. Their name derives from their cell of origin, the meningothelial or arachnoidal cell. WHO divides meningiomas into nine subtypes (Table 2.7). The meningotheliomatous, fibrous, transitional, psammomatous, angiomatous, and hemangioblastic types are considered benign. The hemangiopericytic and papillary types tend toward malignant features, but are uncommon. The hemangioblastic type contains vessels indistinguishable from those of cerebellar capillary hemangioblastoma. Hemangioblastic meningioma, however, is attached to the meninges, is well circumscribed, and grows by expansion. The hemangiopericytic type is indistinguishable from hemangiopericytoma elsewhere in the body.
Russell and Rubinstein(14) divided meningiomas into three groups:
Group 1 comprises classical meningiomas:
1.1 Meningothelial (or syncytial) type
1.2 transitional type
1.3 fibroblastic type
This group includes further histological variants named for their appearances: psammomatous, microcystic (or humid), myxomatous, xanthomatous, lipomatous, granular, secretary, chondroblastic, osteoblastic, and melanotic.
All meningiomas in this group are non-malignant.
Group 2 comprises angioblastic meningiomas, subdivided into:
2.1 hemangioblastic type
2.2 hemangiopericytic type
Group 3 comprises malignant meningiomas, including the papillary type.
Primary malignant lymphomas are uncommon but of particular interest because they are often associated with various immunodeficiency states, including AIDS. Tumors often occur around blood vessels and may be multiple. Their cells of origin arise from metalophil microglial cells, reticular tissue within the CNS that is particularly abundant in gray matter, and from primitive reticulum cells in the meninges and perivascular sheaths.(17) Tumors in this group include reticulum-cell sarcoma, adventitial sarcoma, microglioma, Hodglin’s sarcoma, non-Hodgkin sarcoma, plasmocytoma, and others.
WHO divides vascular tumors into two types: i) hemangioblastoma and ii) monstrocellular sarcoma. Capillary hemangioblastoma is the more common type. Most occur in the cerebellum, with smaller numbers in the spinal cord, brainstem, and cerebrum. Although its name might suggest malignancy, it is in fact benign. It may occur as part of Lindau’s syndrome or von Hippel–Lindau disease. Monstrocellular sarcoma consists of reticular stroma and monster cells—large cells with multiple nuclei—and can be distinguished from glioblastoma.(23)
Russell and Rubinstein(24) divided vascular tumors of the brain into i) capillary hemangioblastoma and ii) angiosarcoma, which is malignant.
In 1985, Rorke LB and colleagues(3) reconsidered the WHO classification for childhood brain tumors (Table 2.8). They divided the vascular tumor group into three types: i) capillary hemangioblastoma, ii) hemangiopericytoma, and iii) neoplastic angioendotheliosis–angiosarcoma.
The WHO classification of germ-cell tumors and malformative tumors is appropriate. However, including vascular malformations in the brain-tumor classification is inappropriate because these abnormalities are not tumors and should therefore be excluded.
Adenomas of the anterior pituitary were originally divided into three types according to the staining of intracellular granules under conventional light microscopy: acidophilic, basophilic, and chromophobe adenoma. Immunohistochemical examination now allows pituitary adenomas to be classified according to the hormones produced by the tumor cells.(25,26) They are named after these hormones: prolactin-cell adenoma, growth-hormone-cell adenoma, mixed growth-hormone- and prolactin-cell adenoma, adrenocorticotropic-hormone-cell adenoma, and undifferentiated-cell adenoma.(27)
Brain-tumor classification will not remain static. It will continue to change as new concepts and scientific information emerge. Childhood brain tumors in particular differ somewhat from those in adults and may consequently have different names. Some childhood tumors contain embryonic or poorly differentiated cells with unusual appearances, causing confusion in naming. They also often contain several different cell types (heterogeneity), which creates further nomenclature problems.(28,29) In 1985, a meeting was held to revise the WHO classification for childhood brain tumors, using light microscopy, electron microscopy, and immunocytochemical techniques as guides. The following classification was proposed:
Original pages 39–45
Table 2.8 Classification of Brain Tumors in Children (Rorke, L.B.(3))
I. Tumors of neuroepithelial tissue
A. Glial tumors
1. Astrocytic tumors
a. Astrocytoma (fibrillary, protoplasmic, gemistocytic, pilocytic and xanthomatous)
b. Anaplastic astrocytoma
c. Subependymal giant cell tumors (tuberous sclerosis)
d. Gigantocellular glioma
2. Oligodendroglial tumors
a. Oligodendroglioma
b. Anaplastic oligodendroglioma
3. Ependymal tumors
a. Ependymoma
b. Anaplastic ependymoma
c. Myxopapillary ependymoma
4. Choroid plexus tumors
a. Choroid plexus papilloma
b. Anaplastic choroid plexus tumor (carcinoma)
5. Mixed gliomas
a. Oligoastrocytoma
1. Anaplastic oligoastrocytoma
b. Astroependymoma
1. Anaplastic ependymoastrocytoma
c. Oligoastroependymoma
1. Anaplastic oligoastroependymoma
d. Oligoependymoma
1. Anaplastic oligoependymoma
e. Subependymoma-subependymal glomerate astrocytoma
f. Gliofibroma
6. Glioblastomatous tumors
a. Glioblastoma multiforme
b. Giant cell glioblastoma
c. Gliosarcoma
7. Gliomatosis cerebri
B. Neuronal tumors
1. Gangliocytoma
2. Anaplastic gangliocytoma
3. Ganglioglioma
4. Anaplastic ganglioglioma
C. “Primitive” neuroepithelial tumors
1. Primitive neuroectodermal tumor, not otherwise specified (NOS)
2. “Primitive” neuroectodermal tumor, with:
a. Astrocytes
b. Oligodendrocytes
c. Ependymal cells
D. Neuronal cells
E. Other (melanocytic, mesenchymal)
F. mixed cellular elements
3. Medulloepithelioma
a. Medulloepithelioma, NOS
b. Medulloepithelioma with:
1. Astrocytes
2. Oligodendrocytes
3. Ependymal cells
4. Neuronal cells
5. other (melanotic, mesenchymal)
6. Mixed cellular elements
D. Pineal cell tumors
1. “Primitive” neuroectodermal tumor (see C above) (Pineoblastoma)
2. Pineocytoma
II. Tumor of meningeal and related tissues
A. Meningiomas
1. Meningioma, NOS
2. Papillary meningioma
3. Anaplastic meningioma
B. Meningeal sarcomatous tumors
1. Meningeal sarcoma, NOS
2. Rhabdomyosarcoma or leiomyosarcoma
3. Mesenchymal chondrosarcoma
4. Fibrosarcoma
5. Others
C. Primary melanocytic tumors
1. Malignant melanoma
2. Melanomatosis
3. Melanocytic tumors, miscellaneous
III. Tumors of nerve sheath cells
A. Neurilemmoma (schwannoma, neurinoma)
B. Anaplastic neurilemmoma (schwannoma, neurinoma)
C. Neurofibroma
D. Anaplastic neurofibroma (neurofibrosarcoma, neurogenic sarcoma)
IV. Primary malignant lymphomas
Classify according to local current standards
V. Tumors of blood vessel origin
A. Hemangioblastoma
B. Hemangiopericytoma
C. Neoplastic Angioendotheliosis-angiosarcoma
VI. Germ cell tumors
A. Germinoma
B. Embryonal carcinoma
C. Choriocarcinoma
D. Endodermal sinus tumor
E. Teratomatous tumors
1. Immature teratoma
2. Mature teratoma
3. Teratocarcinoma
F. Mixed
VII. Malformative tumors
A. Craniopharyngioma
B. Rathke’s cleft cyst
C. Epidermoid cyst
D. Dermoid cyst
E. Colloid cyst of third ventricle
F. Enterogenous or bronchial cyst
G. Cyst, NOS
H. Lipoma
I. Granular cell tumor (choristoma)
J. Hamartoma
1. Neuronal
2. Glial
3. Neuronoglial
4. Meningioneurinomatosis
VIII. Tumors of neuroendocrine origin
A. Tumor of anterior pituitary
1. Adenoma
2. Pituitary carcinoma
B. Paraganglioma
IX. Local extensions from regional tumors
type to be specified according to primary diagnosis
X. Metastatic tumors
XI. Unclassified tumors
The classification of childhood brain tumors in Table 2.8 differs from the WHO classification in the following respects.
Gliomas found in children often contain several types of cells. Such tumors are sufficiently common in children to constitute a group termed “mixed glioma,” which includes both malignant and nonmalignant tumors. They are named according to their constituent cell types, for example glioastrocytoma, oligoependymoma, oligoastroependymoma, and astroependymoma. Subependymoma, which the WHO classification places in the ependymoma group, is classified as a mixed glioma in the childhood classification because it actually consists of astrocytes and ependymal cells(30) and is nonmalignant.
In the WHO classification, glioblastoma multiforme is placed among the poorly differentiated and embryonic tumors (Table 2.7), rather than among tumors derived from astrocytic cells. This group is removed in the classification of childhood brain tumors, and a new group termed glioblastomatous tumors is established, comprising glioblastoma multiforme, giant cell glioblastoma, and gliosarcoma.
A new group of childhood tumors is established under the name “primitive neuroectodermal tumor” (PNET), or poorly differentiated neuroepithelial tumors. These are the most common tumors in children and occur chiefly in the midline of the cerebellum, although they may arise elsewhere in the CNS, including the pineal gland. They consist of poorly differentiated neuroepithelial cells: small cells with round, deeply staining nuclei and scant cytoplasm, with numerous mitotic figures. Tumors composed of such primitive cells include medulloblastoma, pinealoblastoma, ependymoblastoma, and central neuroblastoma. Without knowing the site of the tumor, it is impossible to diagnose its type, because all consist of similar primitive cells and have similar biological behavior. They are therefore grouped as primitive neuroectodermal tumors (PNETs). If the location is known, however, the tumor can be named accordingly; for example, a tumor known to arise in the pineal gland is called pinealoblastoma.
In addition, a tumor in this group may contain astrocytes, oligodendrocytes, ependymal cells, neuronal cells, or mesenchymal cells. The name of the accompanying cell type is then added, for example primitive neuroectodermal tumor with astrocytes.
Nevertheless, this group of tumors remains controversial.(31,32)
Tumors arising from immature pineal parenchymal cells are classified as primitive neuroectodermal tumors. When such a tumor arises in the pineal gland, the diagnosis is pinealoblastoma. The name pineocytoma remains unchanged.
The hemangiopericytoma type of meningioma is placed among tumors of blood vessel origin, so that this group comprises hemangioblastoma, hemangiopericytoma, and neoplastic angioendotheliosis–angiosarcoma. All vascular malformations are excluded.
A meeting was held in Houston, Texas, in 1988, prompted by the view that new research findings obtained through immunohistochemistry, electron microscopy, and molecular biology should lead to a revised classification of brain tumors. The results of the meeting were reported in 1989.(33) Many changes can be seen, particularly among poorly differentiated brain tumors. Diagnosis using the techniques described above moves the classification of brain tumors more toward histogenesis, in contrast to the earlier classification according to appearances under the microscope. Another meeting was subsequently held in Zurich, Switzerland, in 1990, and its results were reported as “The New WHO Classification of Brain Tumors” by Kleihues, P., et al.(34) (Table 2.9).
Original pages 45–51
Table 2.9 WHO Histological Typing of CNS Tumours (1993)
This latest classification of brain tumors represents several further advances since the first WHO classification was reported in 1979. Several new groups and types of brain tumors have been added, including pleomorphic xanthoastrocytoma in the astrocytic tumor group, and dysplastic gangliocytoma, desmoplastic infantile ganglioma, dysembryoplastic neuroepithelial tumor, and central neurocytoma in the neuronal and mixed neuronal-glial tumor group. Several variants of certain tumors have also been added. Glioblastoma, formerly classified among poorly differentiated and embryonal tumors, is now included with astrocytic tumors. Astroblastoma, polar spongioblastoma, and gliomatosis cerebri, however, are separated into the group of neuroepithelial tumors of uncertain origin. Mixed gliomas form a new separate subgroup of gliomas. The embryonal tumor group includes neuroblastoma, ependymoblastoma, primitive neuroectodermal tumors (PNETs), and medulloblastoma. The diagnosis primitive neuroectodermal tumor is to be regarded as a designation for cerebellar medulloblastoma and also for tumors with the same histological appearance as medulloblastoma that arise in parts of the brain other than the cerebellum. The classification of childhood brain tumors remains largely unchanged. Hemangioblastoma is placed among tumors of uncertain histogenesis.
Summary. Brain tumors can be classified into 11 major groups on the basis of cell type, morphology, nature, and biological behavior. The classification will continue to change as new scientific evidence accumulates in the future.
Original pages 51–53
Chapter 2 References
Zulch K.J., : Brain tumors-their biology and pathology, 2nd Ed. New York, Springer-Verlag Publ., 1965.
Bailey, P., Cushing, H., : A Classification of the Tumors of the Glioma Group on a Histogenetic Basis. Philadelphia, Lippincott, 1929.
Rorke, L.b., Gilles, F.H., Daves R.L., Becker, L.E., Revision of The World Health Organization Classification of brain tumors for childhood brain tumors. Cancer vol. 56 : 1869-86, 1985.
Rorke L.B., Editorial. Journal of Neuro-oncology 5 : 95-7, 1987.
Zulch K.J., Brain tumors : Their biology and pathology, 3rd Ed., Springer-Verlag publ. p. 270, 1986.
Roussy G., Oberling Ch. : Histologic classification of tumors of the central nervous system. Arch. Neurol. Psychiat. 27 : 1281-89, 1932.
Penfield W. : The classification of gliomas and neuroglia cell types Arch. Neurol. Psychiat. 26 : 745-53, 1931.
Bergstrand H., On gliomas of the cerebral hemisphere : Acta Pathol. Microbiol. Scand. 11 : 100-113, 1932.
Rio-Hortega P Del (1934) Translate as The Microscopic Anatomy of Tumors of The Central and Peripheral Nervous System by Pineda, Russell and Earl. Springfield : Charle C. Thomas, 1962.
Kernohan, J.W., Mabon, R.F., Svien, H.J., And Adson, A.W., : A simplified classification of gliomas. Proc. Staff Meet. Mayo Clinic, 24 : 71-75, 1949.
Kernohan, J.W., and Sayre, G.P., : Tumors of The Central Nervous System. Atlas of Tumor Pathology, Section X, Fascicles 35 and 37. Washington, Armed Forces Institute of Pathology, 1952.
Zulch K.J., Brain tumors : Their biology and pathology 3rd Ed., Springer-Verlag p. 17, 1986.
Russell D.S., Rubinstein L.J., Pathology of Tumors of The Nervous System. 5th Ed. revised by L.J. Rubinstein. London, Edward Arnold, p 88-98 1989.
Zulch K.J., : Histological Typing of Tumors of the Central Nervous System. World Health Organization. Geneva (International histological classification of tumors No. 21), 1979.
VandenBerg S.R., May E.E., Rubinstein L.J., Herman M.M., Perentes E., Vinores S.A., Collin P., Park T.S., : Desmoplastic supratentorial neuroepithelial tumors of infancy with divergent differentiation potential (desmoplastic infantile gangliogliomas) Journal Neurosurgery : 66. 58-71, 1987.
Russell D.S., Rubenstein L.J. Pineal Neoplasms in Pathology of Tumors of the Nervous System 2nd ed. Edward Arnold Pub. p. 173-182, 1963.
Krabbe K.H., The pineal gland, especially in the relation to the problem of its supposed significance in sexual development, Endocrinology 7, 379, 1923.
Friedman N.B., Germinoma of the pineal. Its identity with germinoma (“seminoma”) of the testis, Cancer Res. 7 : 363-368, 1947.
Riverson E.A., and Zulch K.J., : Pineal parenchymal tumors and germinomas (the problem of the socalled pinealomas) Neurosurgery Rev. 1 : 3-11, 1979.
Sano K. Pineal region tumors. Problems in pathology and treatment. Clin. Neurosurg. 30 : 59-91, 1983.
Zulch K.J., Brain Tumors-Their biology and pathology 3rd ed, Springer-Verlag Publ. p. 287, 1986.
Zulch J.J., Brain Tumor-their biology and pathology 3rd ed, Springer Verlag Publ. p. 407-413, 1986.
Russell D.S., Rubinstein L.J., Pathology of Tumors of The Nervous System 5th ed. London, Edward Arnold, p. 639, 1989.
Kovacs K., Horvath E., Ezrin C., : Pituitary adenomas. Pathol. Annu. 12 : 341-382, 1977.
Kovacs K., Horvath E., Ryan N., Immunocytology of the human pituitary. In De Lellis RA. ed. Diagnostic Immunocytochemistry. New York : Masson, 17-35, 1981.
Martinez A.J., Lee A., Moossy J., Maroon J.C., Pituitary adenomas : Clinicopathological and immunohistochemical study, Ann. Neurol. 7 : 24-36, 1980.
Rorke L.B. Classification and grading of childhood brain tumors. Cancer 56 : 1848-1849, 1985.
Vogel F.S., Nomenclature of gliomas. J. Natl Cancer Inst. 46 : 51-56, 1977.
Russell D.S., and Rubenstien L.J., Pathology of tumors of the nervous system 4th ed. Arnold, London, 1977.
Rubinstien L.J., A commentary on the proposed revision of the World Health Organization Classification of the brain tumors Cancer suppl. 56 : pp 1887-1888, 1985.
Rubinstien L.J., : Justification for a cytogenetic scheme of embryonal central neuroepithelial tumors in Primary Brain tumor Ed. by W.S. Fields, Spinger-Verlag, 16-27, 1989.
Fields W.S., Primary Brian Tumors. A Review of Histologic Classification, Springer-Verlag : New York, Berling 1989.
Klihues P., Burger, P.C., and Scheithauer B.W., The New WHO Classification of Brain Tumors, in Brain Pathology 3 : 255-268, 1993.
Original pages 54–56
Chapter 3 · Pathology of Brain Tumors
From the preceding account of the classification of brain tumors, all brain tumors may be summarized in nine groups according to their tissue of origin:
Tumors originating from neuroepithelial tissue or medullary epithelium, which develops into the various glial cells, ependymal cells, and choroid plexus.
Tumors of nerve sheath cells, situated outside the CNS. Acoustic schwannoma is the most common tumor in this group.
Tumors originating from mesoderm. This group includes tumors of the meninges, of which meningioma is the most common. Most are situated outside the brain; only a small proportion are located within the ventricles.
Tumors originating from the blood vessels of the brain.
Tumors originating from germ cells.
Tumors caused by abnormal cellular development (malformative tumors).
Tumors of the pituitary gland.
Tumors metastatic to the brain from cancers in other organs.
The final group consists of tumors arising outside the CNS and extending locally toward the brain tissue.
Of all these brain tumors, the group arising from neuroepithelial tissue is the most common, accounting for approximately 50% of all brain tumors. Its classification is also much more difficult than that of the other groups.
The pathology, including histology, of each group and type of brain tumor will now be described to clarify their classification and biological behavior, thereby helping to explain the clinical features of each tumor type.
Tumors of Neuroglial Cells
The human central nervous system contains several types of neuroglial cells, including astrocytes, oligodendrocytes, and ependymal cells. Each type may give rise to tumors in various parts of the brain, and the tumors are named after their cells of origin. Astrocytes themselves occur in several morphological forms: fibrillary, protoplasmic, gemistocytic, and piloid astrocytes. The tumors that arise from these cells differ in their common sites, malignancy, natural history, and clinical manifestations, as will be discussed in detail for each type.
Tumors of Astrocytic Cells
This is the most common group of tumors arising from neuroglial cells. They are called astrocytomas after their cells of origin and include both benign and malignant types. Bailey and Cushing(1) divided astrocytic cell tumors into astrocytoma, astroblastoma, and spongioblastoma multiforme. Kernohan and Sayre(2) subsequently divided astrocytomas into four grades of increasing malignancy, grade 1 being the most benign and grades 3 and 4 the most malignant. Table 3.1 compares astrocytomas in order of increasing malignancy across different classifications.
Table 3.1 Comparison of astrocytic tumors across different classifications
Pilocytic astrocytoma in the WHO classification is regarded as the most benign tumor, being more benign than Kernohan grade 1 astrocytoma, and patients generally survive longer. Glioblastoma multiforme, equivalent to Kernohan grades 3 and 4 astrocytoma, was placed among poorly differentiated and embryonal tumors in the WHO classification of 1979, which remains a source of confusion. However, the latest WHO classification report (1993) places glioblastoma in the astrocytic tumor group.
Original pages 56–67
ASTROCYTOMA
Astrocytoma is a large group of tumors arising from astrocytic cells. These cells are at different stages of development, giving rise to astrocytomas with different gross appearances, histology, growth patterns, and clinical manifestations.
Astrocytomas can be classified in three ways.
1. By the type of astrocytic cell. Astrocytes include protoplasmic, fibrillary, gemistocytic, and pilocytic forms. Astrocytomas are therefore divided into five subtypes:
1.1 protoplasmic astrocytoma
1.2 fibrillary astrocytoma
1.3 gemistocytic astrocytoma
1.4 pilocytic astrocytoma
1.5 subependymal giant cell astrocytoma
2. By degree of malignancy. Neoplastic astrocytic cells show varying degrees of malignancy, both histologically and clinically. Some tumors are benign and grow slowly; others grow rapidly and cause death within a short time. As already described, Kernohan divided astrocytomas into four grades:
2.1 Astrocytoma grade 1 is the most benign type.
2.2 Astrocytoma grade 2 has an intermediate degree of malignancy, corresponding to anaplastic astrocytoma or astroblastoma.
2.3 Astrocytoma grades 3 and 4 are the most malignant types, equivalent to glioblastoma multiforme.
3. By their specific site in the brain, including cystic or solid cerebellar astrocytoma, juvenile pilocytic astrocytoma of the third ventricle, hypothalamus, or chiasm, and pontine astrocytoma. Tumors at these sites have characteristic clinical features and usually occur in children.
Natural History of Astrocytoma
The astrocytomas discussed here are grades 1 and 2. Grades 3 and 4, or glioblastoma multiforme, will be discussed separately. In general, astrocytoma is a benign tumor that grows slowly by gradual infiltration, taking years to produce clear symptoms. A tumor in a cerebral hemisphere may initially present with seizures, for which the patient continues to receive anticonvulsant treatment. Only later in the disease does loss of cerebral function develop, such as hemiparesis, accompanied by a relatively rapid rise in intracranial pressure. This may indicate malignant transformation of the tumor.
Age. Astrocytoma can occur at any age, but generally occurs between 30 and 40 years. Age at occurrence also depends on the site in the brain. Cerebral hemispheric tumors usually occur at about 30–40 years, whereas astrocytomas of the hypothalamus, cerebellum, pons, and chiasm are common in children.
Some astrocytomas occur in association with von Recklinghausen’s neurofibromatosis (Figure 3.1), usually pilocytic astrocytomas of the chiasm and hypothalamus. Subependymal giant-cell astrocytoma is commonly found in patients with tuberous sclerosis.
Pathology. The pathological appearance of astrocytoma depends on the type of astrocytic cell described above. It may be diffuse or circumscribed. Some tumors undergo cystic degeneration, producing small or large cysts. Large cysts may contain a mural nodule and have a better prognosis than infiltrative tumors. Most astrocytomas are infiltrative, with indistinct boundaries, so that tumor cannot be distinguished from normal brain.
AI-enhanced image · Compare details with the original book image
Figure 3.1 A patient with von Recklinghausen’s neurofibromatosis and an associated astrocytoma.
FIBRILLARY ASTROCYTOMA
This is more common than the other types and usually arises in the white matter of a cerebral hemisphere. Its infiltrative nature gives it an indistinct boundary, hence the descriptive name diffuse cerebral astrocytoma. It may also arise in the brain stem and cerebellum; cerebellar tumors tend to be well circumscribed. On gross inspection during surgery or sectioning of a fresh brain, the tumor is light gray with a pinkish tinge. After fixation, it is pale whitish-yellow (Figure 3.2), sometimes making it difficult to distinguish from white matter. When it extends into the cortex or basal ganglia, their normal color boundaries disappear (see Figure 3.3). The tumor feels firm and harder than normal brain because its cells contain abundant neuroglial fibrils. Some tumors contain cysts of varying sizes.
AI-enhanced image · Compare details with the original book image
Figure 3.2 Fibrillary astrocytoma of the left frontal lobe. The gyri are pale and enlarged, the tumor margins are indistinct, and vessels are sparse. The cingulate gyrus is displaced beneath the falx to the opposite side.Figure 3.3 Infiltrative astrocytoma with indistinct boundaries. The tumor extends into the cortex and basal ganglia, obliterating their normal color.
HISTOLOGY
Fibrillary astrocytoma consists of small, uniformly sized stellate astrocytic cells, more numerous than in normal brain. The nuclei are larger than normal and show slight hyperchromatism. Mitotic figures are very rare. Blood vessels within the tumor are also sparse, and there is no endothelial proliferation such as that seen in glioblastoma multiforme. Special staining of fibrils by silver impregnation reveals numerous fibrils in the cell processes (Figure 3.4 A), a principal diagnostic feature. Fibrillary astrocytoma often undergoes extensive microcystic degeneration (Figure 3.5), which can sometimes create an appearance resembling oligodendroglioma.
A
B
C
AI-enhanced image · Compare details with the original book image
Figure 3.4 A. Fibrillary astrocytic cells stained with Cajal stain to demonstrate fibrils in their processes. B. Grade 1 astrocytoma. Astrocytic cells are more numerous than normal, with enlarged, hyperchromatic nuclei. No mitotic figures or endothelial proliferation are seen. C. Grade 2 astrocytoma, with more astrocytic cells than grade 1 astrocytoma.
A
B
AI-enhanced image · Compare details with the original book image
Figure 3.5 A. Microcystic degeneration in an astrocytoma, showing numerous small white spaces. B. A microcyst in astrocytoma at high power. Cells are compressed to the sides of the microcyst.
PROTOPLASMIC ASTROCYTOMA
This type usually arises in a cerebral hemisphere, often at the brain surface, because protoplasmic astrocytes are abundant in the cortex. The tumor is light gray, soft, and gelatinous, rather than firm like fibrillary astrocytoma, because it lacks glial fibrils (Figure 3.6). It can be readily removed by suction during surgery and bleeds little because its blood supply is limited. Its boundaries are indistinct, and it often contains numerous honeycomb-like cysts. In some cases a large cyst develops (Figure 3.7). This type of astrocytoma may also occur as a component of fibrillary astrocytoma.
HISTOLOGY
Protoplasmic astrocytoma consists of cells resembling protoplasmic astrocytes, but with more swollen cytoplasm and a rounded shape. Their processes are less conspicuous and shorter than normal. A characteristic feature is the consistent presence of microcystic degeneration (Figure 3.8).
AI-enhanced image · Compare details with the original book image
Figure 3.6 Protoplasmic astrocytoma in the cortex. The tumor is light gray-yellow; the cortex is expanded and pale.
AI-enhanced image · Compare details with the original book image
Figure 3.7 Protoplasmic astrocytoma presenting as a large cortical cyst.
AI-enhanced image · Compare details with the original book image
Figure 3.8 Histology of protoplasmic astrocytoma. The cells contain more cytoplasm than normal, and their processes are less conspicuous and shorter than normal.
GEMISTOCYTIC ASTROCYTOMA
This type occurs only in the cerebral hemispheres(3) and is less common than the other types. The tumor is grayish and soft, like protoplasmic astrocytoma. Its boundaries are usually more distinct than those of other types, and it may contain cysts of various sizes.
HISTOLOGY
Gemistocytic astrocytoma consists of large cells with abundant pink-staining cytoplasm. Their nuclei are displaced to the periphery and vary in size. Neuroglial fibrils occur at the cell margins and in the usually short processes (Figure 3.9). Many gemistocytic astrocytomas show cells arranged around blood vessels in pseudorosettes, as seen in astroblastoma. This tumor may therefore be related to glioblastoma.(3)
AI-enhanced image · Compare details with the original book image
Figure 3.9 Mixed gemistocytic astrocytoma. The cells have abundant pink-staining cytoplasm and eccentrically displaced nuclei. Oligodendrocytic cells with small, darkly staining nuclei are also present.
PILOCYTIC ASTROCYTOMA
As its name indicates, this tumor consists of hair-like cells. It is benign and occurs predominantly in children, most often in the cerebellum, brain stem, third ventricle, corpus callosum, and hypothalamus. These cells are actually fibrillary astrocytes, but when they form a tumor in a part of the brain containing fiber tracts, they adapt their shape to the length of those tracts. The tumor thus consists of elongated bipolar cells, with glial fibrils arranged in parallel rows resembling wavy locks of hair. Russell and Rubinstein(3) described two distinguishable forms of pilocytic astrocytoma: an adult type and a juvenile type.
The adult type consists of densely packed, parallel bipolar fibrillated cells without microcystic degeneration. It generally occurs in older adults and tends to become anaplastic.
The juvenile type is very common in children. It consists of slender elongated cells, usually aligned parallel to blood vessels. Special stains clearly demonstrate the neuroglial fibers, and microcystic degeneration tends to occur (Figure 3.10). Cerebellar tumors are usually circumscribed and may form large cysts.
AI-enhanced image · Compare details with the original book image
Figure 3.10 Pilocytic astrocytoma of the cerebellum, composed of slender, hair-like cells. One area is densely cellular near blood vessels; another shows microcystic degeneration.
Original pages 67–79
Astrocytoma: Specific Types and Sites
SUBEPENDYMAL GIANT-CELL ASTROCYTOMA
This astrocytoma occurs in association with tuberous sclerosis, whose principal clinical manifestations are adenoma sebaceum (Figure 3.11), seizures, and intellectual disability. It occurs in children aged approximately 10–12 years. The tumors form small nodules along the wall of the lateral ventricle, usually on its floor near the foramen of Monro, and can therefore obstruct cerebrospinal fluid flow (Figure 3.12). When pneumoencephalography (PEG), involving the introduction of air into the ventricular system, was still performed, these tumors appeared like candle-wax drippings on the ventricular walls; this appearance was used as a basis for diagnosis.
AI-enhanced image · Compare details with the book image
Figure 3.11 Adenoma sebaceum in a patient with tuberous sclerosis.
AI-enhanced image · Compare details with the book image
Figure 3.12 Subependymal giant-cell astrocytoma in the lateral ventricular wall (arrow), associated with tuberous sclerosis.
HISTOLOGY
The tumor consists of large giant cells of varying sizes arranged around blood vessels in perivascular pseudorosettes. The cells have abundant cytoplasm, eccentrically placed nuclei, and few glial fibrils. They resemble gemistocytic astrocytes. Mitotic figures are very rare, and the vessels show no endothelial proliferation (Figure 3.13).
Subependymal giant-cell astrocytoma is a slow-growing tumor and usually has a good prognosis after surgical removal.
AI-enhanced image · Compare details with the book image
Figure 3.13 A. Subependymal giant-cell astrocytoma composed of large cells with abundant cytoplasm and prominent enlarged, eccentrically displaced nuclei. Some cells are multinucleated. B. High-power view showing a large cell with coarse nuclear chromatin (arrow).
CEREBELLAR ASTROCYTOMA
This benign tumor is common in young people, with its peak incidence at 8–15 years of age.(4) Approximately half occur in the vermis and half in a cerebellar hemisphere. There is a tendency to form a large cyst (Figure 3.14), with a clearly demarcated mural nodule projecting from its wall into the cyst cavity. The cyst contains straw-colored fluid with a high protein content that clots on standing. Its yellow wall usually consists of degenerated cells that no longer grow. Complete removal of the mural nodule can therefore cure the patient. In some cases no mural nodule is visible, but tumor surrounds the cyst wall. The tumor is soft, gray with a faint pink tinge, and usually has a discernible boundary. The surrounding cerebellar tissue is necrotic, providing a plane along which the tumor can readily be dissected out. Some tumors have no cyst and can become very large (Figure 3.15). Astrocytomas of the vermis may also contain cysts; these are generally multiple small cysts rather than one large cyst (Figure 3.16). Tumors in this region may extend into the fourth ventricle, cisterna magna, or cerebellar peduncle, or compress the midbrain, causing obstructive hydrocephalus.
Figure 3.14 Cerebellar cystic astrocytoma.
AI-enhanced image · Compare details with the book image
Figure 3.15 Large noncystic astrocytoma of a cerebellar hemisphere (large arrow). Note tonsillar herniation compressing the medulla (small arrow).
AI-enhanced image · Compare details with the book image
Figure 3.16 Astrocytoma of the vermis. One component contains small cysts of varying sizes (arrowhead); another is a solid, lobulated mass extending into the fourth ventricle (arrow), compressing the cerebellum and pons and obstructing cerebrospinal fluid flow.
HISTOLOGY
Cerebellar astrocytoma has the features of pilocytic astrocytoma described earlier.
OPTIC NERVE GLIOMA
This tumor occurs in children. Approximately 50% are associated with neurofibromatosis,(5,6) and approximately 20% with café-au-lait spots.(7) It grows slowly and may arise in one or both optic nerves, or begin at the chiasm. Involvement of an optic nerve causes fusiform enlargement (Figure 3.17). A tumor in the orbital portion of the optic nerve may form a mass, causing proptosis and loss of vision on that side. Some extend through the optic foramen into the intracranial optic nerve, producing a dumbbell shape. The optic foramen becomes enlarged, as can be seen on an optic-foramen radiographic view. Tumors arising in the optic chiasm may extend into both optic nerves (Figure 3.18A), or along the optic tracts into the hypothalamus (Figure 3.18B), causing loss of vision in both eyes and loss of hypothalamic function. Conversely, hypothalamic gliomas may extend into the optic chiasm. Rarely, the tumor extends beyond the optic system. The operative photograph illustrates a large tumor covering the suprasellar region, with no recognizable shape of the optic nerves or optic chiasm remaining (Figure 3.19).
AI-enhanced image · Compare details with the book image
Figure 3.17 Left optic nerve glioma. The optic nerve is fusiform; part of its anterior portion has been removed.
A
B
AI-enhanced image · Compare details with the book image
Figure 3.18 A. Bilateral optic nerve gliomas extending into the hypothalamus. B. Midline section of the brain showing optic nerve glioma extending into the hypothalamus.
AI-enhanced image · Compare details with the book image
Figure 3.19 Operative view of a large optic nerve glioma filling the suprasellar region (long arrow). The normal shape of the optic nerve is completely lost. The internal carotid artery (short arrow) and its branches are displaced laterally.
HISTOLOGY
Most optic nerve gliomas have the features of pilocytic astrocytoma already described, as do those occurring in the hypothalamus (Figure 3.20).
AI-enhanced image · Compare details with the book image
Figure 3.20 Pilocytic astrocytoma of the optic nerve. The cells are slender and hair-like, with microcysts in some areas.
HYPOTHALAMIC GLIOMA
Most of these tumors are pilocytic astrocytomas. They are common in children and grow slowly, but cause manifestations of hypothalamic hormonal dysfunction before symptoms of hydrocephalus. Later in the disease they may compress the foramen of Monro and obstruct cerebrospinal fluid flow. The tumor is gray with a slight pink tinge and may be gelatinous, with internal foci of hemorrhage. A large tumor may spread into the interpeduncular fossa, abut the uncus of the temporal lobe, or invade and destroy the optic chiasm (Figures 3.21A and B).
A
B
AI-enhanced image · Compare details with the book image
Figure 3.21 A. Gelatinous hypothalamic glioma extending into the optic nerves and chiasm, obscuring the shape of these structures. It also extends into the medial temporal lobe. B. Midline section of the brain showing hemorrhage within the hypothalamic glioma.
BRAIN STEM GLIOMA
Most are benign astrocytomas and occur predominantly in children; very few are glioblastomas multiforme. The pons and midbrain are more commonly affected than the medulla. The tumor infiltrates between the fibers of the brain stem, enlarging and firming the pons (Figure 3.22) because of its abundant glial fibers. This appearance is termed a hypertrophic pons, and cystic degeneration is uncommon. The tumor may initially arise on one side of the brain stem or on both sides simultaneously. It subsequently extends into the midbrain and medulla, destroying cranial nerve nuclei at different levels and causing loss of function detectable clinically. In some cases the tumor grows beyond the brain stem on either side of the basilar artery, extending anteriorly to abut the clivus and leaving a groove for the basilar artery between its two sides (Figure 3.23). At the same time the basilar artery is displaced posteriorly. Vertebral angiography demonstrates this appearance, with the basilar artery straightened and displaced backward away from the clivus.
AI-enhanced image · Compare details with the book image
Figure 3.22 Pontine glioma. The enlarged pons displaces the fourth ventricle posteriorly without obstructing cerebrospinal fluid flow. The tumor remains within the pons and contains no cyst.
AI-enhanced image · Compare details with the book image
Figure 3.23 Brain stem glioma growing beyond the brain stem (large arrow) to abut the clivus, separating the basilar artery (small arrow) from the clivus. The normal shapes of the pons and midbrain are completely lost.
Because a pontine glioma grows along fiber tracts, it does not initially obstruct cerebrospinal fluid flow through the fourth ventricle. Patients therefore have no manifestations of raised intracranial pressure early in the disease; long-tract and cranial nerve signs appear first. Obstruction of the fourth ventricle and aqueduct of Sylvius may occur late in the course.
Gliomas of the midbrain tend to obstruct the aqueduct of Sylvius and cause obstructive hydrocephalus relatively early, particularly when they arise near the central gray matter, because the aqueduct is a very narrow CSF passage (Figure 3.24). In some cases a glioma arises on one side and subsequently extends into the thalamus, producing unilateral signs (Figure 3.25).
Figure 3.24 Glioma of the midbrain tegmentum. The aqueduct of Sylvius (arrowhead) is compressed shut, causing obstructive hydrocephalus.
A · Book image
B
AI-enhanced image · Compare details with the book image
Figure 3.25 A. Right-sided midbrain glioma (arrow). B. Transverse section from the same patient showing extension into the right thalamus. Note hemorrhage in the areas of anaplasia.
HISTOLOGY
Most are pilocytic astrocytomas, as described above. Their cells resemble those of fibrillary astrocytoma of the cerebral hemisphere: they are small and contain abundant glial fibrils. Within the fiber tracts of the brain stem, they assume a bipolar shape and align along the tracts, a characteristic of pilocytic astrocytoma.
Tumors in this location may show anaplasia, making them difficult to distinguish from glioblastoma. Anaplastic areas are usually small, soft regions containing necrosis and foci of hemorrhage.(8)
Original pages 79–81
ANAPLASTIC ASTROCYTOMA
Anaplastic astrocytoma, or malignant astrocytoma, is intermediate between benign astrocytoma and glioblastoma multiforme in both histology and the rapidity of symptom development. It corresponds to grade 2 astrocytoma in Kernohan’s classification, or astroblastoma in the classification of Bailey and Cushing. Most occur in people aged 30–40 years and arise more often in the cerebral hemispheres than elsewhere, although they may also occur in the cerebellum and spinal cord. The tumor is usually situated in the cortex and subcortical white matter.
The tumor usually has a discernible boundary. It is soft and gray with a faint pink tinge. Its cut surface is homogeneous and may contain cysts of varying sizes. A large tumor may contain foci of necrosis, but there is no calcification.
HISTOLOGY
Because the tumor is more cellular than benign astrocytoma, its boundary with normal brain can be clearly distinguished. Its cells are small and pleomorphic (Figure 3.26) and are arranged around vessels in perivascular pseudorosettes (Figure 3.27). The spindle-shaped cell bodies lie away from the vessels, with processes extending toward the vessel walls, an appearance resembling ependymoma. Occasional mitotic figures are present. The vessels do not show the endothelial proliferation seen in glioblastoma. In some cases anaplastic astrocytoma grows in the subpial region, producing the characteristic appearance called Scherer’s secondary structure (Figure 3.28).
The diagnosis of anaplastic astrocytoma depends on histological distinctions from both benign astrocytoma (well-differentiated astrocytoma) and glioblastoma. It differs from benign astrocytoma in being more cellular and pleomorphic and in frequently forming pseudorosettes. It is distinguished from glioblastoma multiforme by the necrosis and endothelial proliferation found in glioblastoma. Glioblastoma cells have a variety of shapes, as indicated by the name “multiforme.”
Anaplastic astrocytoma grows more rapidly than benign astrocytoma and may progress to grade 3 astrocytoma, altering the prognosis. The patient’s condition then deteriorates relatively rapidly.
AI-enhanced image · Compare details with the book image
Figure 3.26 A. Anaplastic astrocytoma composed of pleomorphic tumor cells, some undergoing mitosis. A giant cell with a large nucleus and coarse chromatin is visible in the center. B. Anaplastic astrocytoma stained by the immunoperoxidase technique for glial fibrillary acidic protein (GFAP).
AI-enhanced image · Compare details with the book image
Figure 3.27 Perivascular pseudorosette (Scherer’s secondary structure), one of the features of anaplastic astrocytoma.
AI-enhanced image · Compare details with the book image
Figure 3.28 Anaplastic astrocytoma cells growing in the subpial region of the cortex, termed Scherer’s secondary structure.
Original pages 82–90
GLIOBLASTOMA MULTIFORME
Glioblastoma multiforme, or grade 3 and 4 astrocytoma in Kernohan’s classification, is the most malignant type of tumor and may be called a cancer of the brain. It grows rapidly, and patients die within a short time, on average within one year. This tumor accounts for approximately half of all gliomas.(9) It commonly occurs at approximately 45–55 years of age. The frontal lobe is the most frequent site, followed by the temporal and parietal lobes, respectively; the occipital lobe is least often affected.
Pathology
The tumor may arise in white matter near the cortex or at a greater depth, enlarging the affected region of the brain. Because it grows rapidly, it tends to have a macroscopically discernible boundary (Figure 3.29), although its margins always contain cellular infiltration invisible to the naked eye. The surrounding brain is edematous. Consequently, intracranial pressure rises rapidly, and mass effect and brain herniation develop relatively early. Deep tumors may spread from one hemisphere to the other through the corpus callosum, producing a butterfly appearance (Figure 3.30), and then grow into a large mass in the opposite hemisphere (Figure 3.31).
AI-enhanced image · Compare details with the book image
Figure 3.29 Glioblastoma multiforme with a relatively clear boundary and edema of the surrounding brain.
AI-enhanced image · Compare details with the book image
Figure 3.30 Glioblastoma multiforme extending along the corpus callosum on both sides, producing a butterfly appearance.
AI-enhanced image · Compare details with the book image
Figure 3.31 Glioblastoma multiforme extending from one side through the corpus callosum and growing in both cerebral hemispheres. The cut surface has a moth-eaten appearance in necrotic areas and contains foci of hemorrhage.
The cut surface of the tumor is gray-pink and contains numerous cream-colored, moth-eaten cavities representing necrosis. Foci of hemorrhage may also be present (Figure 3.32), particularly in highly vascular areas. A large tumor may contain an extensive area of central necrosis (Figure 3.33). Cysts occasionally form; their fluid is reddish-brown rather than the straw color seen in astrocytoma, because they commonly result from hemorrhage. These findings correspond to the CT appearance: central low density represents necrosis, surrounded by high-density, strongly enhancing tumor. Outside this lies a zone of tumor-cell infiltration and brain edema (Figure 3.34). Both the pathological and CT appearances are important in diagnosing this tumor.
AI-enhanced image · Compare details with the book image
Figure 3.32 Hemorrhage within a glioblastoma multiforme of the frontal lobe.
AI-enhanced image · Compare details with the book image
Figure 3.33 Large glioblastoma with extensive central necrosis.
AI-enhanced image · Compare details with the book image
Figure 3.34 CT appearance of glioblastoma with central necrosis, seen as central low density surrounded by high-density tumor. Low density around the mass represents edematous brain. This appearance is important in diagnosing this tumor.
DISSEMINATION OF GLIOBLASTOMA
Metastasis may occur through the CSF, forming discrete masses rather than the diffuse dissemination seen with medulloblastoma. It usually occurs after surgical removal of the tumor. The author observed dissemination from a glioblastoma multiforme originating in the temporal lobe. At surgery, the superficial portion of the tumor was firmly adherent to the dura mater; separating the dura from the tumor caused profuse bleeding. Its gray color with a faint purple tinge led to an intraoperative diagnosis of meningioma (Figure 3.35), but histological examination showed glioblastoma multiforme. This case demonstrates that localized infiltration of the leptomeninges can occur, causing the dura to adhere firmly to the tumor. This may increase its blood supply from meningeal vessels, and branches of the middle meningeal artery may enlarge, as in meningioma. In the author’s experience, glioblastoma has not been observed to extend through the dura.
AI-enhanced image · Compare details with the book image
Figure 3.35 Operative view of a glioblastoma multiforme at the brain surface. The tumor (arrow) adheres firmly to the dura mater (arrowhead), resembling a meningioma.
Five months after surgery, the patient developed symptoms of spinal cord compression and a mass involving a left rib (Figures 3.36A and B). Spinal surgery and excision of the rib mass revealed glioblastoma at both sites. The patient subsequently died. At autopsy, some tumor remained in the temporal lobe, and another mass was present at the medial aspect of the temporal lobe base (Figure 3.37). The spinal cord showed one large tumor mass and another smaller mass near its surface (Figure 3.38).
A
B · Book image
AI-enhanced image · Compare details with the book image
Figure 3.36 A. Tumor involving a left rib in a patient who underwent surgery for temporal lobe glioblastoma multiforme five months earlier. B. Glioblastoma multiforme in the excised rib specimen.Figure 3.37 Residual temporal lobe glioblastoma (arrowhead) and a disseminated tumor mass growing at the base of the brain (arrow).
AI-enhanced image · Compare details with the book image
Figure 3.38 Two spinal cord glioblastoma deposits in a patient operated on for temporal lobe glioblastoma five months earlier. One mass is large (arrow); the other is small (arrowhead).
This case demonstrates that glioblastoma may disseminate through the CSF and the bloodstream. It is well known that the human brain has no lymphatic drainage, so this is not a route of spread. Glioblastoma presumably destroys blood vessels, as suggested by vascular occlusion with necrosis and by rupture of vessels with intratumoral hemorrhage. Tumor cells may therefore be released into the bloodstream. Nevertheless, metastasis from glioblastoma is very rare.
HISTOLOGY
The tumor comprises cells of various shapes, as indicated by the name “multiforme”: fibrillary astrocytes, gemistocytes, pleomorphic astrocytes, and the most pleomorphic cells, termed large bizarre cells. Cells are especially numerous around the central necrotic region. At the periphery, tumor cells infiltrate the edematous brain, which is often left behind when the tumor mass is surgically removed.
Histological appearances may vary from one area to another. Some areas resemble anaplastic astrocytoma, while others contain densely packed, small, poorly differentiated cells. Around the margins of necrotic regions, cells are arranged in overlapping rows, termed palisading (Figure 3.39A). Around small foci of necrosis, however, the surrounding cells form rosette-like structures. Some areas contain large, unusually shaped, multinucleated cells, called bizarre giant cells (Figure 3.39B). An essential histological feature of glioblastoma is vascular endothelial proliferation: extensive proliferation of vascular endothelial cells produces coiled structures resembling renal glomeruli (Figure 3.39C). This is important in distinguishing glioblastoma from benign astrocytoma and anaplastic astrocytoma.
The diagnosis of glioblastoma multiforme is therefore not difficult. Its principal histological features can be summarized as follows:
i) Cells of varying shapes, appearances, and sizes, including bizarre multinucleated giant cells
ii) Necrosis and cellular palisading
iii) Vascular endothelial proliferation
A
B and C · Book image
AI-enhanced image · Compare details with the book image
Figure 3.39 A. Tumor cells arranged around areas of necrosis (pseudopalisades), a characteristic of glioblastoma multiforme. B. Glioblastoma multiforme composed of anaplastic tumor cells of varying sizes and shapes (pleomorphic), including large, bizarre multinucleated cells (arrow). C. Glomeruloid vessels resulting from endothelial proliferation, a hallmark of glioblastoma multiforme.
Original pages 91–92
TUMORS OF OLIGODENDROCYTIC CELLS
OLIGODENDROGLIOMA
This tumor arises from oligodendrocytes, a type of neuroglial cell. It is benign and the slowest-growing tumor in the glioma group. It accounts for approximately 5% of all gliomas,(10) although Zulch reported a frequency as high as 18.8%.(11) It is most common between 35 and 40 years of age. It may also occur in children, usually in deep structures such as the thalamus.
The cerebral hemispheres are the most frequent location, particularly the frontotemporal region. The cerebellum and spinal cord are very rarely involved.
Pathology
Oligodendroglioma arises in the subcortical white matter and tends to extend into the cortex without a clear boundary, enlarging it and giving it a pale yellow color. In some cases the tumor penetrates locally into the meninges, producing an appearance resembling meningioma. Deep portions usually form a soft, relatively well-demarcated, gray-pink mass. Areas of mucinous change have a gelatinous appearance. The cut surface may show foci of necrosis and cystic degeneration. An important feature is scattered calcification within the tumor, seen histologically in 90% of cases(12) and readily visible on skull radiographs or CT. Most calcification lies toward the tumor margins.
HISTOLOGY
The tumor consists of densely packed, uniform, round cells with absent or very scant cytoplasm. Their round or oval nuclei are centrally placed and stain deeply. The cytoplasm appears clear, with a distinct cell membrane, resembling a fried egg. Large collections of these cells produce a honeycomb appearance (Figure 3.40), characteristic of oligodendroglioma. It must be distinguished from astrocytoma with microcystic degeneration by recognizing these characteristic features and by metallic impregnation staining, in which the nuclei do not stain.
Figure 3.40 Oligodendroglioma composed of cells with a characteristic “fried-egg” or “honeycomb” appearance.
Oligodendroglioma frequently coexists with astrocytoma. If the astrocytoma component is substantial, the tumor may be termed a mixed oligo-astrocytoma. Its blood vessels are capillaries, generally without endothelial proliferation, although they may show calcification. Calcification may also occur throughout the tumor.
Original pages 92–99
TUMORS OF EPENDYMAL CELLS
EPENDYMOMA
Ependymoma arises from ependymal cells. It is slow-growing and benign, but often behaves malignantly because of its location in the ventricular wall, which makes it difficult to approach. This is particularly true of tumors arising in the floor of the fourth ventricle, where important centers include cranial nerve nuclei and the respiratory and cardiac centers. Complete surgical removal is therefore impossible and carries a high risk. Unlike astrocytoma, this tumor does not usually undergo malignant transformation.
Age. Ependymoma occurs predominantly in children and adolescents, with a peak incidence at 8–15 years of age.(13) In children, ependymoma of the cerebral hemisphere is the most common tumor among all gliomas.
Sites. Most ependymomas arise from the ependyma of the ventricular walls. The fourth ventricle is the most common site, followed, in order, by the lateral ventricle, third ventricle, aqueduct of Sylvius, spinal cord, cauda equina, cerebellopontine angle, and extraventricular hemisphere.
Pathology
Ependymoma is gray-pink, soft, and well demarcated. It is sometimes nodular, resembling cauliflower or the human placenta. Because it arises from ependymal cells of the ventricular wall, most ependymomas project into a ventricle and obstruct CSF flow. In some cases, however, the tumor grows into the cerebral tissue; these tumors are also well demarcated (Figure 3.41), homogeneous, and may contain cysts. Ependymomas of the fourth ventricle invariably cause obstructive hydrocephalus. Patients present with manifestations of raised intracranial pressure before other symptoms. The tumor may originate in the floor, roof, or side of the fourth ventricle. Obstruction of CSF flow enlarges the anterior portion of the fourth ventricle, aqueduct, third ventricle, and lateral ventricles (Figure 3.42). The tumor may extend downward to the foramen magnum or the upper cervical subarachnoid space (Figure 3.43), or through the foramen of Luschka to form a mass at the cerebellopontine angle. Foci of hemorrhage may be visible within some tumors (Figure 3.44). An ependymoma arising from the floor of the fourth ventricle cannot be completely removed by the surgeon; a portion adherent to the ventricular floor usually has to be left behind. Attempts to dissect it away may cause the patient’s death.
In some cases, small foci of [a term is missing in the printed source] may be found within the tumor, most often in ependymomas of the cerebral hemisphere.
AI-enhanced image · Compare details with the book image
Figure 3.41 Ependymoma of the lateral ventricle extending into the cerebral tissue. Note the intratumoral foci of hemorrhage, which are frequently seen in ependymoma.
AI-enhanced image · Compare details with the book image
Figure 3.42 Ependymoma of the fourth ventricle compressing the cerebellum and brain stem and obstructing cerebrospinal fluid flow. The proximal fourth ventricle, aqueduct of Sylvius, third ventricle, foramen of Monro, and lateral ventricle are enlarged.Figure 3.43 Ependymoma of the fourth ventricle extending downward to the foramen magnum and upper cervical region.
AI-enhanced image · Compare details with the book image
Figure 3.44 Ependymoma filling the fourth ventricle. The tumor is pinkish and soft, and frequently contains hemorrhage (arrow).
HISTOLOGY
Ependymoma consists of densely packed cells of uniform size. They have scant cytoplasm and oval or round nuclei with distinct nuclear membranes and abundant chromatin networks. The cells form characteristic arrangements that are used to diagnose this tumor: prominent perivascular pseudorosettes are widespread(15) (Figures 3.45A and B). These comprise a pink-staining, anuclear zone around each blood vessel. This zone consists of processes extending from the surrounding nucleated cell bodies toward the vessel wall, without footplates.
A
B
AI-enhanced image · Compare details with the book image
Figure 3.45 A. Ependymoma with cells arranged in pseudorosettes, a characteristic feature of this tumor. Cells with small nuclei surround the vessels. B. High-power view of ependymoma pseudorosettes.
Ependymoma may also show two other patterns of cellular arrangement: ependymal tubules and the papillary type.
Ependymal tubules resemble epithelial tubes, with a lumen like the central canal. This pattern is often found in tumors of the aqueduct of Sylvius.
The papillary type resembles choroid plexus papilloma and may be difficult to distinguish from it. The distinguishing principle is that the papillary stroma in papillary ependymoma consists of neuroglial fibers and lacks the vessels found in choroid plexus papilloma (Figure 3.46). In addition, the cells surrounding the stroma may form several layers.(14) Papillary ependymoma is frequently seen in ependymomas of the cerebellopontine angle.
Figure 3.46 Ependymoma with cells arranged in the papillary pattern.
ANAPLASTIC EPENDYMOMA OR EPENDYMOBLASTOMA
This is a malignant, rapidly growing ependymoma that may arise in either the cerebrum or the posterior fossa. Histology shows increased cellularity and variation in cell shape (polymorphism). The cellular arrangements characteristic of ependymoma are lost, although they remain recognizable in some areas. The nuclei stain more deeply, and mitotic figures are numerous (Figures 3.47A and B). The vessels may show endothelial proliferation.
A
B
AI-enhanced image · Compare details with the book image
Figure 3.47 A. Ependymoblastoma composed of numerous cells of varying shapes (polymorphism) around blood vessels. B. High-power view of ependymoblastoma showing dense cellularity and mitosis.
Dissemination. Because the tumor is closely related to the ventricular system, it often disseminates through the cerebrospinal fluid, particularly after surgery. Nodules may develop in the spinal subarachnoid space or basal cisterns.
Original pages 99–101
CHOROID PLEXUS TUMORS
CHOROID PLEXUS PAPILLOMA
This benign tumor arises from the epithelium of the choroid plexus. It is very rare, accounting for only 0.5–0.6% of all brain tumors.(16) Most occur in children during the first decade of life.
The tumor must arise within a ventricle containing choroid plexus. It is most common in the lateral ventricle, followed by the fourth and third ventricles, respectively. Lateral ventricular papillomas are common in children under two years of age(17) and usually arise in the trigone. Fourth ventricular papillomas are more often found in adults.
Pathology
Choroid plexus papilloma is well demarcated and gray-red because of its abundant blood supply. Its irregular surface resembles cauliflower (Figure 3.48); it is soft to palpation and easily torn. The tumor is attached to normal choroid plexus and invariably receives its blood supply from a choroidal artery. During removal, these vessels must be coagulated and divided to reduce blood loss. Choroid plexus papilloma may obstruct the ventricular system or produce excessive cerebrospinal fluid, causing relatively rapid development of hydrocephalus. Some tumors may contain calcification.
AI-enhanced image · Compare details with the book image
Figure 3.48 Choroid plexus papilloma within a ventricle, causing obstructive hydrocephalus. Note the cauliflower-like surface of the tumor.
HISTOLOGY
The tumor comprises papillae lined by a single row of columnar or cuboidal epithelial cells, with vascular connective-tissue stroma (Figure 3.49). This appearance may resemble papillary ependymoma. The distinction is that the stroma of choroid plexus papilloma consists of connective tissue containing blood vessels, whereas that of papillary ependymoma consists of neuroglial fibers. Mitotic figures are not found in the cells of choroid plexus papilloma.
AI-enhanced image · Compare details with the book image
Figure 3.49 Choroid plexus papilloma showing characteristic branching papillae composed of columnar epithelial cells and connective-tissue stroma containing blood vessels.
Dissemination. Although it is not malignant, its friability allows cells to detach and disseminate through the CSF.
MALIGNANT CHOROID PLEXUS PAPILLOMA
There are no distinctive gross pathological features separating it from the benign type. However, Lewis,(18) and Russell and Rubinstein(19) proposed the following criteria for diagnosing malignant choroid plexus papilloma: 1) extension into adjacent brain with cellular infiltration, making the tumor boundary indistinct; 2) loss of the papillary pattern in infiltrating portions, with malignant cellular change; and 3) cellular pleomorphism, numerous mitoses, and occasional large multinucleated cells.
Dissemination. Malignant choroid plexus papilloma frequently spreads along the cerebrospinal fluid pathways, producing rapidly growing masses in the subarachnoid space that compress the spinal cord and brain stem.
Original pages 101–107
PRIMITIVE NEUROECTODERMAL TUMORS
MEDULLOBLASTOMA
Medulloblastoma is a malignant tumor arising from primitive and poorly differentiated cells in the cerebellum. The origin of cerebellar medulloblastoma remains unsettled, but three possible sources have been proposed:(20)
i) The fetal granular layer of Obersteiner, or external granular cell layer. These embryonic cells are distributed throughout the cerebellar cortex at birth and gradually diminish and disappear during the first year of life. They develop and migrate to become neurons and may also give rise to neuroglial cells. Remnants of these cells may develop into tumors.
ii) Cell rests in the posterior medullary velum. From examinations of cerebella from embryos, fetuses, and infants ranging in age from eight weeks to five years, Raaf and Kernohan(21) hypothesized that the external granular layer originates from a germinal bud in the posterior medullary velum. Normally, this germinal bud disappears one month after birth. In abnormal cases, however, these immature cells persist and microscopically resemble medulloblastoma cells. Primitive cells arising at the roof of the fourth ventricle migrate upward and laterally to form the external granular layer. Medulloblastoma may therefore arise anywhere along this migration pathway. Consequently, childhood medulloblastomas occur in the midline, whereas those in adults are located in a cerebellar hemisphere.
iii) Internal granular neurons. Evidence comes from animal experiments involving local administration of carcinogenic hydrocarbons(23) and injection of oncogenic viruses to induce tumors.(24)
Medulloblastoma is regarded as a malignant cerebellar tumor of children and young adults, occurring most often at approximately 7–12 years of age.(25) It accounts for about 20% of all childhood brain tumors, ranking second after cerebellar astrocytoma.
Pathology
Most tumors arise in the inferior cerebellar vermis, beginning at the roof of the fourth ventricle and extending into the surrounding vermis. They appear relatively well demarcated (Figure 3.50). Nevertheless, cells at the tumor margin infiltrate the surrounding brain. In some cases, tumor is visible on the surface of the cerebellar folia and leptomeninges (Figure 3.51). The medulloblastoma mass is soft and gray with a faint pink tinge, or gray-white. Large tumors develop central necrosis, and small cysts may be present (Figure 3.52). Calcification is usually absent. The tumor extends into the fourth ventricle and posterior portion of the aqueduct of Sylvius, obstructing the CSF pathways (Figure 3.53). In some cases, tumor projects outward and fills the cisterna magna, causing obstructive hydrocephalus. Adult medulloblastomas usually occur in the lateral and superior parts of the cerebellum. They are well circumscribed and firmer than midline tumors. Sometimes they grow onto the surface of a cerebellar hemisphere in an en plaque pattern, covering the cerebellar folia so that neither the folia nor the subarachnoid space remains visible.
AI-enhanced image · Compare details and arrows with the book image
Figure 3.50 Medulloblastoma in the cerebellar vermis. The tumor originates at the roof of the fourth ventricle and is well demarcated. Note that it has not extended into the fourth ventricle.
AI-enhanced image · Compare details and arrows with the book image
Figure 3.51 Spread of medulloblastoma onto the surface of the cerebellar folia and leptomeninges. Note the pale pink-gray color of the tumor.Figure 3.52 Medulloblastoma extending into the fourth ventricle, with central necrosis and a cyst.
AI-enhanced image · Compare details and arrows with the book image
Figure 3.53 Medulloblastoma filling the fourth ventricle (arrow), causing obstructive hydrocephalus. The tumor compresses the cerebellar peduncle (arrowhead) and brain stem.
Dissemination
Tumor cells disseminate through the cerebrospinal fluid. Tumor may therefore be found throughout the subarachnoid space of the brain and spinal cord, forming gray sheets that cover the brain and obscure the normal tissue. This is considered characteristic of medulloblastoma. In some cases, tumor cells spread retrogradely into the third ventricle. Extension into the fourth ventricle produces stagnation of cerebrospinal fluid, permitting this upward retrograde spread.
HISTOLOGY
The tumor consists of very densely packed small cells with scant cytoplasm and indistinct borders. The nuclei are round or oval, vary in size, and stain darkly (Figure 3.54). Mitoses are very frequent. Generally, the cells show no particular arrangement, but in some areas they form rosettes around a space. Homer Wright described these cells as carrot-shaped, with their nuclei toward the outside and their cytoplasm extending toward the center of the rosette (Figure 3.55).
A
B · Book image
AI-enhanced image · Compare details and arrows with the book image
Figure 3.54 A. Medulloblastoma (primitive neuroectodermal tumor) comprising densely packed small cells with scant cytoplasm and no particular arrangement. Mitosis is present. B. The same tumor stained immunocytochemically with a monoclonal antibody to detect neurofilament protein. Pale-staining cells are seen in patches.Figure 3.55 Characteristic Homer Wright rosettes, found in primitive neuroectodermal tumors (medulloblastoma) and neuroblastoma.
DESMOPLASTIC MEDULLOBLASTOMA
This is a variant of medulloblastoma. Tumor cells frequently infiltrate the subarachnoid space(26) and leptomeninges, stimulating a connective-tissue reaction. It is therefore called desmoplastic medulloblastoma (desmoplastic meaning “producing adhesion”). Its distinctive appearance consists of pale-staining islands of reticulin-free tumor adjacent to reticulin-rich cells densely arranged along connective-tissue trabeculae (Figure 3.56).
Figure 3.56 Desmoplastic medulloblastoma, with tumor cells arranged longitudinally along connective-tissue fibers.
Original pages 107–117
Pineal Gland Tumors
Tumors arising in the pineal region may be divided into two groups:
1. Those arising from the parenchymal cells of the pineal gland, which develop and differentiate from neuroepithelial cells. The gland contains two cell types: parenchymal cells, or pinealocytes, and astrocytes. Thus, true tumors of the pineal gland comprise:
1.1 Pineoblastoma, a tumor of primitive pinealocytes
1.2 Pineocytoma, a tumor of well-differentiated pinealocytes
1.3 Astrocytoma and glioblastoma, arising from the astrocytic cells of the pineal gland
2. Those arising from germ cells, including:
2.1 Germinoma (also called atypical teratoma or pinealoma), the most common type
2.2 Teratoma, a true teratoma containing multiple tissue types derived from ectoderm, mesoderm, and endoderm
The nomenclature of pineal tumors has long been confusing. Krabbe introduced the name “pinealoma” in 1923 because the tumor contains two types of cells: large pale-staining cells in groups separated by small dark-staining cells resembling lymphocytes. These cells form a mosaic pattern resembling that of the fetal pineal gland. (The small cells disappear later in the neonatal period, while the remaining cells become pinealocytes.)(25) The term pinealoma continued to be used for tumors of the pineal gland.
Friedman(27) subsequently pointed out that most pineal tumors have histology identical to germinoma or seminoma of the testis. The term germinoma has therefore become accepted for pineal tumors containing these two cell types. Most neurosurgeons, however, still prefer the name pinealoma.
PINEOCYTOMAS (pinealocytoma)
This very rare tumor arises from pinealocytes. Most cases occur in adults and are benign.
Pathology. Pineocytoma is a well-demarcated tumor of the pineal gland. Cystic degeneration and calcification may be present. Like other tumors in this region, it projects into the third ventricle and compresses the quadrigeminal plate and aqueduct of Sylvius, causing obstructive hydrocephalus (Figure 3.57).
Figure 3.57 A well-demarcated pineal tumor compressing the quadrigeminal plate and aqueduct of Sylvius and projecting into the posterior third ventricle, causing obstructive hydrocephalus. Areas of cystic degeneration of varying sizes are visible on the cut surface.
HISTOLOGY
The tumor consists of medium-sized, uniformly shaped (isomorphous) cells. Connective tissue separates groups of cells, as in the normal pineal gland. Importantly, the mosaic arrangement of two cell types characteristic of germinoma is absent.
PINEOBLASTOMAS
This uncommon malignant tumor consists of densely packed, poorly differentiated cells resembling those of medulloblastoma.
Pathology. The tumor is poorly demarcated and extends into surrounding brain. It is soft and gray-pink, with possible foci of hemorrhage or cyst formation. Dissemination of tumor cells to the leptomeninges and CSF has been found in every case examined at autopsy.(28)
PINEALOMA OR GERMINOMA
This tumor arises from germ cells and is the most common of all pineal tumors. Pinealoma accounts for approximately 0.5–0.7% of all intracranial tumors in the Western hemisphere,(29) 4–5% in Japan, and 4.14% in Thailand.(30) Although pinealoma, or germinoma, most often arises in the pineal gland, it may also occur along the midline of the brain, including the suprasellar region, third ventricle, and brain stem (see examples). Such tumors are called ectopic pinealomas (Figures 3.58 and 3.62).
Figure 3.58 Posterior fossa surgery showing a tumor in the pontomedullary region. Examination identified an ectopic pinealoma (germinoma).
Age. Most patients are between 10 and 30 years of age, and males are affected more often than females.
Pathology. The tumor is well circumscribed, with a gray-pink cut surface, and is soft and friable to palpation (Figure 3.59). It can readily be removed by suction during surgery. Intratumoral hemorrhage may occur and cause death from brain-stem compression (Figure 3.60). Large tumors frequently infiltrate adjacent brain, particularly the quadrigeminal plate, aqueduct of Sylvius, posterior wall of the third ventricle, and anterior cerebellar vermis (Figure 3.61). Occasionally, pinealoma in the pineal gland coexists with an ectopic pinealoma in the suprasellar region in the same patient (Figure 3.62 A, B). The suprasellar tumor is well demarcated and compresses the optic chiasm, floor of the third ventricle, and pituitary stalk. In some cases, upward extension obstructs the foramen of Monro, causing hypothalamo-pituitary dysfunction and hydrocephalus.
Figure 3.59 Germinoma of the pineal gland.Figure 3.60 Hemorrhage within a pineal tumor.Figure 3.61 A large pinealoma extending into the third ventricle, vermis, and region anterior to the brain stem.
A
B
AI-enhanced image · Compare details and arrows with the book image
Figure 3.62 A. Pinealoma in the pineal gland accompanied by ectopic pinealoma. B. Ectopic pinealoma at the chiasm and inferior hypothalamus (arrow) in the same patient.
Calcification within pinealoma is regularly encountered and can be seen on skull radiographs and CT in nearly every case.
HISTOLOGY
Pinealoma has a distinctive histological appearance, comprising two clearly different cell types. The large cells are round or polygonal, with distinct cell membranes, clear cytoplasm, central nuclei with vesicular nucleoplasm, and relatively large nucleoli. The other cells are small and dark-staining, presumed to be lymphocytes. They lie within the vascular connective-tissue stroma of the tumor (Figure 3.63). Mitoses may be seen in the large cells.
Figure 3.63 The characteristic appearance of germinoma (pinealoma): two cell types, large pale-staining cells and small dark-staining cells resembling lymphocytes, arranged in a mosaic pattern. Note mitosis in the large cells.
TERATOMAS
These germ-cell tumors contain tissues derived from ectoderm, mesoderm, and endoderm. Pineal-region teratomas may arise within or beside the pineal gland. They are the most common intracranial teratomas. Teratomas may also occur in the suprasellar region, ventricles, and spinal cord.
These tumors commonly occur during the first 20 years of life, with a peak between 10 and 20 years. Most occur in males; females are affected so rarely that pineal-region teratoma may be regarded as a tumor particularly of males.
Pathology. The tumor is usually well demarcated. Its outer surface may be irregular or finely lobulated. The cut surface reveals numerous small cysts of varying sizes containing cloudy white fluid from cellular desquamation. Some areas show old and recent hemorrhage. Cyst contents may be dark brown or green, and necrosis may be present in some areas. The tumor is generally firm to palpation; cartilage, pieces of bone, or hair may be found (Figure 3.64 A, B).
A
B
AI-enhanced image · Compare details and arrows with the book image
Figure 3.64 A. A pineal teratoma extending as a large mass to the base of the brain and displacing the brain stem to the left. The tumor contains patches of hemorrhage. B. The cut surface of the teratoma in the same patient shows numerous small cysts containing cloudy white fluid, with hemorrhage in some areas. The center of the tumor has the color of bone. Note the severe compression of the midbrain.
HISTOLOGY
The histology resembles that of teratomas elsewhere in the body. Groups or cysts of squamous epithelium are common. Cartilage and glandular structures lined by mucus-secreting columnar cells may be interspersed within mesenchymal stroma. Muscle fibers are often present, and glial and neuronal cells may be found in some areas (Figure 3.65 A, B).
B (left) · A (right)
D (left) · C (right)
AI-enhanced image · Compare details and arrows with the book image
Figure 3.65 A. A portion of teratoma showing gland-like structures lined by mucus-secreting columnar cells. B. The squamous epithelial component of the teratoma. C. A portion of the pineal teratoma containing muscle fibers. D. Another portion of the same tumor showing cartilage and mucus-producing glands.
Original pages 117–122
TUMORS OF NERVE SHEATH CELLS
These tumors arise from cells surrounding the axons of peripheral nerves as they leave the central nervous system. Normally, the axons of both cranial and spinal nerve roots are surrounded by 1) Schwann cells, 2) fibroblasts forming part of the epineurium and endoneurium, and 3) perineurial cells. Which of these three cell types gives rise to nerve-sheath tumors was long debated. After electron microscopy became available for examining tumor cells, Schwann cells became generally accepted as the fundamental cells of origin.(31) Nerve-sheath tumors may be divided into schwannomas and neurofibromas; Schwann cells are the essential cellular component underlying both.
SCHWANNOMAS OR NEURINOMAS
These tumors occur in cranial and spinal nerves. The terms neurinoma and neurilemmoma are also used interchangeably. The tumor arises from Schwann cells surrounding the axons of peripheral nerve roots.
Intracranial schwannomas account for 8% of all brain tumors and approximately 80–90% of tumors in the cerebellopontine angle.(32) They commonly occur in middle age. Schwannomas favor sensory rather than motor nerves. Most intracranial tumors involve the acoustic nerve, particularly its vestibular branch. Far fewer involve the trigeminal nerve, and involvement of other cranial nerves is even rarer. Multiple cranial and spinal nerves may be affected in the same patient with von Recklinghausen’s disease (known in Thai as the “hundred-thousand-nodule disease”). In the spine, the lumbar region is most often affected.
ACOUSTIC SCHWANNOMA OR NEURINOMA
Schwannomas are well-circumscribed, slowly growing tumors that impair brain function by compressing adjacent brain tissue. Acoustic neurinomas in the cerebellopontine angle usually begin at the internal auditory meatus, enlarging it visibly on skull radiographs. As the mass grows, it compresses nearby structures: cranial nerves V, VII, IX, X, and XI; the cerebellar peduncle, particularly the middle cerebellar peduncle; the pons (Figure 3.66); the fourth ventricle; and, late in the disease, the CSF outlets (Figure 3.67), causing hydrocephalus. Large tumors often have a posterior arachnoid cyst (Figure 3.68), clearly visible at surgery and often containing vessels supplying the tumor. This structure must be opened to reach the tumor. Small tumors have no visible arachnoid cyst. Patients with von Recklinghausen’s disease may have bilateral acoustic neurinomas. Large tumors push the cerebellar tonsils downward through the foramen magnum, usually farther on the tumor side than on the opposite side.
Figure 3.66 A large acoustic tumor. Note its well-demarcated boundary and compression of the cerebellar peduncle and pons. The internal tissue has a color resembling an omelet.Figure 3.67 An acoustic tumor with a yellow cut surface and numerous small cysts. The tumor compresses the cerebellar peduncle, pons, and fourth ventricle.Figure 3.68 A large acoustic tumor, often covered by an arachnoid cyst that is regularly seen when approaching the tumor during surgery.
Pathology
Fresh tumors appear gray-yellow externally, with a relatively modest blood supply, and are not very firm. Some large tumors are soft because of central degeneration. The cut surface is yellow, resembling an omelet, and the tissue is readily removed by suction during surgery. Numerous small cysts and, in some cases, foci of old hemorrhage may be present.
Some acoustic neurinomas are confined to the intracranial cavity, producing no change in the size of the internal auditory meatus. Others grow within the internal auditory canal or extend into the inner ear.(33) Some occupy both the intracranial cavity and the internal auditory canal, producing a dumbbell shape.
HISTOLOGY
The histological patterns of schwannoma may be divided into Antoni A and Antoni B types.
ANTONI A TYPE
This type consists of densely interlacing, elongated spindle-shaped tumor cells. The nuclei are also spindle-shaped, small, and intensely dark-staining (Figure 3.69). Fine intracellular fibers run parallel to the long axis of the cells and show distinct argyrophilia with silver staining. In some areas, tumor cells form palisades: rows of cells separated by pale-staining spaces (Figure 3.70), considered characteristic of this tumor. In other areas, whorls of varying sizes may occur, resembling the layers of an onion in cross-section, as in transitional meningioma. This appearance is common in schwannomas associated with von Recklinghausen’s neurofibromatosis.(34)
Figure 3.69 Acoustic schwannoma (Antoni A type), consisting of elongated spindle-shaped tumor cells overlapping and arranged along their long axes.Figure 3.70 The characteristic appearance of acoustic schwannoma (Antoni A type): rows of tumor cells separated by pale-staining spaces, called palisading.
ANTONI B TYPE
These areas are intermingled with Antoni A tissue and contain loosely arranged pleomorphic tumor cells. The palisading seen in Antoni A areas is absent. The cells are often stellate. Microcystic degeneration is regularly found in Antoni B tissue (Figure 3.71).
Figure 3.71 Acoustic schwannoma (Antoni B type), with loosely arranged pleomorphic tumor cells and extensive microcystic degeneration.
Original pages 122–125
Tumors of the Meninges
Tumors in this group are second in frequency to glial tumors. Meningiomas are the most common tumors within the group.
MENINGIOMAS
Meningiomas are benign tumors arising from the various cells composing the meninges, including dural fibroblasts, pial cells, and arachnoid cells. It is accepted, however, that most meningiomas arise from arachnoid cells, particularly those in arachnoid granulations or villi and in the root sleeves of nerve roots.
In general, meningiomas can arise wherever arachnoid membrane is present. Because they favor arachnoid granulations near the dural sinuses, most arise in the parasagittal region, accounting for approximately half of all intracranial meningiomas. In the author’s own clinical and operative experience, meningiomas occur more often supratentorially than infratentorially and tend to favor particular sites. In order of frequency, these are as follows.
In the supratentorial compartment: 1) Parasagittal meningiomas are the most common (Figure 3.72). Most arise along the middle third of the sagittal sinus; fewer arise along its anterior third, and very few along its posterior third. Meningiomas in this region frequently extend into and obstruct the sinus. 2) Falx meningiomas arise from the falx cerebri (Figure 3.73) and may grow across to the opposite side, producing a dumbbell shape. They usually lie away from the superior sagittal sinus. 3) Convexity meningiomas arise along the lateral surface of the cerebral hemisphere, away from the sagittal sinus and falx (Figure 3.74).
AI-enhanced image · Compare details and arrows with the book image
Figure 3.72 Parasagittal meningioma.
AI-enhanced image · Compare details and arrows with the book image
Figure 3.73 Falx meningioma in the frontal region. The tumor is attached to the falx and is well demarcated.
AI-enhanced image · Compare details and arrows with the book image
Figure 3.74 Convexity meningioma compressing the cerebral cortex.
Tumors at the skull base often pose problems for surgical removal because access is difficult. These include: 4) Olfactory groove meningiomas, arising at the olfactory groove or cribriform plate and growing in the anterior cranial fossa (Figure 3.75). They may extend posteriorly to the optic nerve and chiasm; some enter the paranasal sinuses. 5) Tuberculum sellae meningiomas, situated in the anterior suprasellar region, anterior to the chiasm (Figure 3.76). 6) Sphenoid ridge meningiomas, arising from the medial third of the lesser wing (Figure 3.77), its lateral third (Figure 3.78), or between these two portions. The tumor may extend along the Sylvian fissure into the anterior cranial fossa or into the temporal fossa.
AI-enhanced image · Compare details and arrows with the book image
Figure 3.75 A large olfactory groove meningioma compressing the prefrontal regions and both olfactory nerves.
AI-enhanced image · Compare details and arrows with the book image
Figure 3.76 Tuberculum sellae meningioma compressing the optic nerves and chiasm.
Original pages 126–132
Meningioma (continued)
Figure 3.77 Right medial lesser-wing meningioma compressing the optic nerve (short arrow), internal carotid artery (not visible), and middle cerebral artery (long arrow).Figure 3.78 Meningiomas at the lateral third of the lesser wing of the sphenoid (large arrow) and at the petrous ridge (small arrow).
In the posterior fossa, meningiomas may occur at the cerebellopontine angle along 7) the petrous ridge, producing symptoms similar to those of an acoustic tumor. They may also arise from 8) the tentorium cerebelli. Tumors arising at its edge may extend into the supratentorial compartment beneath the temporal or occipital lobe. 9) Meningiomas of the foramen magnum and clivus (Figure 3.79). 10) Intraventricular meningiomas, arising from the tela choroidea of the choroid plexus, usually occur in the trigone of the lateral ventricle (Figure 3.80). They may occasionally arise in the third or fourth ventricle, but this is very rare. 11) Optic nerve sheath meningiomas usually arise near the optic foramen (Figure 3.81), then extend into the orbit and displace the globe, causing unilateral exophthalmos (Figure 3.82).
Meningiomas occur in adults aged 20–60 years, with the highest frequency between 45 and 55 years.
Figure 3.79 A large clival meningioma compressing the brain stem and cranial nerves. Note displacement of the brain stem to the left.Figure 3.80 A well-demarcated intraventricular meningioma in the right temporal horn.Figure 3.81 Optic nerve sheath meningioma at the optic foramen.Figure 3.82 Intraorbital meningioma causing unilateral exophthalmos.
Pathology
Meningiomas are very sharply demarcated tumors, usually situated outside the brain. As they grow, they indent its surface, with localized loss of water from the brain in that region and no infiltration into the brain tissue. The tumor may be round or nodular (Figure 3.83) and is generally attached to the dura, as can be seen during surgery; only a few are not attached. Meningiomas tend to infiltrate the dura and dural venous sinuses, particularly the superior sagittal sinus, often causing sinus occlusion. The mass is pink-gray, although fibrous types are pale. Most are firm, elastic, and tough, and are difficult to remove by suction during surgery. The cut surface is smooth and homogeneous. Psammomatous tumors feel gritty, like sand, because of calcified psammoma bodies. Some foci may be soft and pale yellow because of xanthomatous degeneration. Intratumoral hemorrhage is occasionally found (Figure 3.84). Cysts are usually absent.
Figure 3.83 A surgically removed meningioma forming a well-demarcated, multinodular mass. One side of the tumor is invariably attached to the dura mater.
AI-enhanced image · Compare details and arrows with the book image
Figure 3.84 A surgically removed meningioma showing intratumoral hemorrhage. The tumor is attached to a sheet of dura (arrow).
Meningioma en plaque grows along the dural surface as a thick sheet firmly adherent to the dura. It often causes marked hyperostosis of the overlying skull (Figure 3.85). It favors the frontotemporobasal region of the brain and causes exophthalmos.
AI-enhanced image · Compare details and arrows with the book image
Figure 3.85 A skull specimen with extensive outward hyperostosis at the site of a meningioma en plaque. Note the numerous prominent vascular grooves on the inner surface of the skull, a characteristic feature of meningioma.
Intraventricular meningiomas are likewise well demarcated (Figure 3.80). Choroid plexus is often attached to the outer wall of the tumor. The cut surface resembles that of meningiomas elsewhere, as described above. The mass can often become very large before producing localizing symptoms.
Meningiomas at some sites grow into a dumbbell shape. Three such locations have been encountered: 1) At the falx cerebri, the tumor infiltrates through the falx and grows on the opposite side, making surgery more difficult and often leading to postoperative recurrence. 2) At the tentorium cerebelli, a mass on the surface of a cerebellar hemisphere extends directly through the tentorium, or around its edge, into the supratentorial compartment beneath the temporal or occipital lobe. 3) At the optic foramen, one portion may lie within the cranial cavity and another within the orbit.
Hyperostosis of the skull usually occurs where the tumor is attached to the dura. Bone may project deeply into the surface of the tumor (Figure 3.86). This occurs both at the convexity and at the skull base, such as the tuberculum sellae or sphenoid ridge. Hyperostosis results from reactive new bone formation, which may or may not be accompanied by extension of tumor cells into the marrow.
Figure 3.86 Localized hyperostosis where the tumor is attached to the dura. Bone projects deeply into the surface of the tumor.
Original pages 132–137
Meningioma · Histology
Russell and Rubinstein(35) divided meningiomas into three groups.
Group 1 comprises the commonly encountered meningiomas, with cells arranged in three patterns:
1.1 meningothelial or syncytial type
1.2 transitional type
1.3 fibroblastic type
Cellular changes within tumors of this group may produce further variants, including the psammomatous, myxomatous, xanthomatous, and melanotic types.
Group 2 comprises angioblastic meningiomas, which may be divided into two subtypes:
2.1 hemangioblastic meningioma
2.2 hemangiopericytic meningioma
Group 3 is termed malignant meningioma.
Of these three groups, the first is by far the most common; groups 2 and 3 are very rare.
MENINGOTHELIOMATOUS MENINGIOMA
Also termed syncytial or endotheliomatous meningioma, this type consists of uniformly large cells of equal size, with indistinct cell boundaries and round or oval nuclei. The nuclei often have a vesicular appearance, with clear spaces within them. The tumor cells form clusters separated by narrow bands of connective tissue (Figure 3.87).
Figure 3.87 Meningotheliomatous meningioma.
TRANSITIONAL MENINGIOMA
This type is intermediate between the syncytial and fibrous types. Its distinctive feature is the grouping of elongated, curved oval cells into whorls (Figure 3.88 A, B). A small blood vessel may lie at the center of some whorls. Later, these whorls become psammoma bodies; such a meningioma is therefore termed a psammomatous meningioma.
AI-enhanced image · Compare details and arrows with the book image
Figure 3.88 A. Transitional meningioma consisting of elongated, curved oval cells grouped into whorls, the characteristic feature of this type of meningioma (arrow).
AI-enhanced image · Compare details and arrows with the book image
Figure 3.88 B. Higher magnification showing the cells of a whorl.
Psammoma bodies in meningiomas are laminated deposits of calcium in areas of cellular degeneration within a whorl (Figure 3.89).
AI-enhanced image · Compare details and arrows with the book image
Figure 3.89 The characteristic appearance of psammoma bodies in a psammomatous meningioma.
AI-enhanced image · Compare details and arrows with the book image
Figure 3.90 A. Fibroblastic meningioma consisting of spindle-shaped tumor cells arranged longitudinally in bundles.
FIBROBLASTIC MENINGIOMA
Also called the fibrous type, this tumor consists of elongated, spindle-shaped cells arranged longitudinally in bundles (Figure 3.90). The cells contain fibrils. In some areas, nuclear palisading resembling that seen in schwannoma may be found. Whorls and psammoma bodies are regularly present as well. The abundance of reticulin and collagen fibers in the fibrous type helps distinguish fibroblastic meningioma from the meningotheliomatous type.
ANGIOBLASTIC MENINGIOMA
The distinctive features of this type are relatively densely packed cells with indistinct cytoplasmic boundaries and numerous thin-walled capillaries interspersed among the tumor cells (Figure 3.91). Silver staining demonstrates abundant reticulin fibers. Mitotic figures are frequently found.
Figure 3.91 A. Angioblastic meningioma with thin-walled capillaries interspersed among the tumor cells (H & E).Figure 3.91 B. Angioblastic meningioma stained to demonstrate reticulin fibers.
Angioblastic meningioma is much less common than the other types, but tends to be more malignant.(36,37)
As mentioned earlier, this meningioma is subdivided into hemangioblastic and hemangiopericytic types. The hemangioblastic type superficially resembles cerebellar hemangioblastoma, and some pathologists consider them the same tumor. There are, however, reasons to regard them as different: the hemangioblastic type of angioblastic meningioma occurs in the supratentorial compartment, lacks the cyst seen in cerebellar hemangioblastoma, is attached to the dura, and may contain clusters of meningothelial cells. These features are absent in cerebellar hemangioblastoma.(38) Furthermore, manifestations of von Hippel–Lindau disease, such as retinal hemangiomas and adrenal pheochromocytoma, which occur in association with cerebellar hemangioblastoma, are not found with angioblastic meningioma.
The hemangiopericytic type has the same histological appearance as hemangiopericytoma elsewhere in the body. It is malignant and tends to recur or metastasize.
In general, we neurosurgeons more often use the term angiomatous meningioma than angioblastic meningioma. This term describes a meningioma with a rich blood supply. Complete resection can provide a satisfactory cure, as with other meningothelial meningiomas. This usage may therefore cause confusion with angioblastic meningioma.
Original pages 137–139
Meningioma · Spread
Meningioma is a benign, slowly growing, well-demarcated tumor. It does not spread into the brain tissue or cerebrospinal fluid, but compresses the brain. Nevertheless, it may extend into the dura (Figure 3.92), dural sinuses, and skull (Figure 3.93), most commonly at the sagittal sinus and falx. In some cases, it may extend into a paranasal sinus or the temporalis muscle. Extension into the marrow of the skull is also common, stimulating osteoblastic proliferation and causing hyperostosis of the skull (Figure 7.67). Regardless of where it extends, the tumor cells still lack malignant features.
AI-enhanced image · Compare details and arrows with the book image
Figure 3.92 Psammomatous meningioma extending into the dura mater.
AI-enhanced image · Compare details and arrows with the book image
Figure 3.93 Transitional meningioma extending into bone.
MALIGNANT MENINGIOMA
This is a very rare tumor that can spread both locally and to distant sites. It often recurs after surgery. Histologically, it is highly cellular and pleomorphic, lacking the whorled arrangement of benign meningiomas. The cells show numerous mitoses (Figure 3.94 B). Necrosis or pseudopalisading may be present. Infiltration into the brain stimulates gliosis in the tissue adjacent to the tumor.(39) Most malignant meningiomas are of the fibromatous (Figure 3.94 A) or hemangiopericytic type. The malignant cells may sometimes show a papillary arrangement. Dissemination through the cerebrospinal fluid and metastasis to other organs may occur, but are uncommon.
Figure 3.94 A. Malignant meningioma infiltrating the brain. The cellular arrangement resembles that of fibromatous meningioma.Figure 3.94 B. Higher magnification showing malignant features, with numerous mitoses.
Original pages 139–146
Vascular tumors
Two important types of tumors arise from blood vessels in the CNS: capillary hemangioblastoma and angiosarcoma. The former is more common and is benign; angiosarcoma is very rare. Arteriovenous malformation is not considered a tumor because it does not form an expanding mass in the manner of a tumor. Only capillary hemangioblastoma will therefore be discussed here.
CAPILLARY HEMANGIOBLASTOMA
This is a benign tumor with a predilection for the posterior fossa and an association with von Hippel–Lindau disease. Several terms should be clarified.(40) Lindau described hemangioblastoma of the brain in 1926, and the tumor is therefore sometimes called Lindau’s tumor. It may be solitary or multiple. When cysts of the pancreas and kidneys occur in the same patient, the condition is called Lindau’s syndrome. The term Lindau’s disease refers specifically to hereditary cerebellar hemangioblastoma. Von Hippel’s disease is retinal angiomatosis and is also hereditary. Von Hippel–Lindau disease thus comprises retinal angiomas together with cerebellar hemangioblastoma and is inherited.
Cerebellar hemangioblastoma may occur only in the cerebellum or together with tumors elsewhere in the CNS. The author has encountered a patient with both cerebellar and cervical hemangioblastomas (Figure 3.95). In some patients, the tumor may be part of von Hippel–Lindau disease. However, among the patients operated on by the author, none has shown the complete manifestations of von Hippel–Lindau disease, possibly because the number of patients with this tumor is very small. Russell and Rubinstein(41) likewise found the complete manifestations of von Hippel–Lindau disease in only 2 of their 13 patients with hemangioblastoma.
Other diseases or conditions that may accompany cerebellar hemangioblastoma include pheochromocytoma and syringomyelia, especially when the hemangioblastoma occurs in the spinal cord.(42)
Erythrocythemia is another condition frequently associated with cerebellar hemangioblastoma and can aid diagnosis. After removal of the hemangioblastoma, the erythrocythemia resolves, but it returns if the tumor recurs. Erythrocythemia is stimulated by an erythropoietic substance found in the fluid within a hemangioblastoma cyst.(43,44)
Figure 3.95 Cervical hemangioblastoma in a patient with cerebellar hemangioblastoma.
Hemangioblastoma is uncommon, accounting for approximately 1–2.5% of all brain tumors. It may occur at any age, but is most frequent in middle age, around 35–45 years.
The favored sites of hemangioblastoma are the cerebellum, the roof of the fourth ventricle, and the spinal cord, with a small number occurring in the cerebrum.
The cerebellum is the most common site. The tumor tends to occur near the midline in a cerebellar hemisphere (Figure 3.96), and may also arise in the vermis (Figure 3.97), compressing or extending into the fourth ventricle.
The spinal cord is the next most common site after the cerebellum.
Hemangioblastoma of the cerebrum is very rare.
AI-enhanced image · Compare details and arrows with the book image
Figure 3.96 Cerebellar hemangioblastoma near the midline. Note hemorrhage within the tumor.
AI-enhanced image · Compare details and arrows with the book image
Figure 3.97 A well-demarcated hemangioblastoma in the vermis extending into the fourth ventricle. The cut surface shows small, sponge-like spaces representing dilated vessels and cysts. Some vessels are greatly dilated, forming cavernous spaces. Yellow fat is visible between the vessels, a characteristic feature of this tumor.
Pathology
Capillary hemangioblastoma is a well-demarcated tumor. It may be entirely solid, partly cystic, or associated with a large cyst. The last form is the most common in the cerebellum. A small, well-demarcated, reddish-brown mural nodule is present in the cyst wall. The cyst fluid is straw-colored and coagulates on standing (Figure 3.98 A, B, C), or may be reddish-brown, indicating hemorrhage. In the author’s experience, the mural nodule usually lies on the posterior wall of the cyst, which facilitates surgical removal. In some cases, multiple hemangioblastomas may occur within the cerebellum or elsewhere in the CNS.
Figure 3.98 A. Cerebellar hemangioblastoma with a large cyst and a mural nodule. Note the posterior location of the mural nodule.Figure 3.98 B. Operative view showing a large cyst in the right cerebellar hemisphere. The mural nodule has already been removed.
AI-enhanced image · Compare details and arrows with the book image
Figure 3.98 C. Cyst fluid and the mural nodule (arrow) obtained at surgery. Note the red color of the mural nodule and the coagulation of the cyst fluid on standing.
The cut surface of the tumor has a spongy appearance, with small spaces throughout representing dilated blood vessels and small cysts. In some areas, the vessels may be greatly enlarged, forming cavernous spaces, or small foci of hemorrhage may be present (Figure 3.97). Another important characteristic of hemangioblastoma is the presence of golden-yellow foci of sudanophilic lipid scattered between the vessels. When the mass is large, vessels on the surface of the brain become enlarged and tortuous (Figure 3.99).
HISTOLOGY
The distinctive diagnostic histological feature is a dense collection of numerous thin-walled capillaries lined by endothelial cells. Reticulin staining of the vessels makes them more clearly visible. Interspersed between the vessels are large, round, pale-staining stromal cells. Some of these cells have foamy cytoplasm because they contain droplets of sudanophilic lipid (Figure 3.100). Both the endothelial and stromal cells appear benign, and mitoses are not seen.
AI-enhanced image · Compare details and arrows with the book image
Figure 3.99 Enlarged, tortuous vessels on the surface of a hemangioblastoma.Figure 3.100 A. Hemangioblastoma consisting of numerous thin-walled vessels with slender endothelial cells. The stromal cells are large and round, with dark-staining nuclei; some have foamy cytoplasm.
AI-enhanced image · Compare details and arrows with the book image
Figure 3.100 B. High-power view showing cells with foamy cytoplasm.Figure 3.100 C. Staining demonstrates lipid within the cells.
Histologically, hemangioblastoma can be difficult to distinguish from angioblastic meningioma because the two have similar appearances. In general, however, their gross pathology and location differ: angioblastic meningiomas are supratentorial, attached to the dura, and form solid masses without cysts.
Original pages 146–147
MALDEVELOPMENTAL TUMORS
These tumors arise through abnormal changes in cells that would normally disappear or develop into various parts of the body, but instead form tumors. This group includes tumors arising from either neuroepithelial or non-neuroepithelial cells. The types encountered are listed below in order from less to more frequent.
Craniopharyngioma
Dermoid cyst
epidermoid cyst
colloid cyst of the third ventricle
Rathke’s cleft cyst
enterogenous cyst
lipoma
hamartoma
These tumors are considered congenital in origin and are benign. They grow slowly, taking many years to produce symptoms, and patients therefore often present in early adulthood. Most occur outside the brain tissue. Despite being benign, they are not easily removed, because most lie in the midline and beneath the brain.
Original pages 147–151
CRANIOPHARYNGIOMA
This tumor arises from remnants of the epithelium of Rathke’s pouch, an upward projection of the primitive stomodeum toward the neural tube. The cells of Rathke’s pouch develop into the craniopharyngeal duct. The proximal part of the duct disappears, eliminating its connection with the buccal cavity, while the distal part becomes the anterior lobe of the pituitary gland and the pars intermedia. Cells remaining anywhere along the craniopharyngeal duct may give rise to a craniopharyngioma, which may be intrasellar, suprasellar, or occupy both sites. However, because craniopharyngioma tends to occur in adolescence, some have suggested that it arises from metaplasia of adenohypophyseal cells rather than from embryonic cell rests.(45)
Craniopharyngioma accounts for 3% of all intracranial tumors and is the most common supratentorial tumor in children. More than half of craniopharyngiomas occur between the ages of 10 and 20 years.(46)
Pathology
Most tumors are suprasellar; fewer are intrasellar(47) or intraventricular. Craniopharyngioma is well demarcated but is often firmly adherent to the brain because of reactive gliosis. Small tumors lie near the chiasm or tuber cinereum. Larger tumors tend to extend upward into the third ventricle (Figure 3.101), obstructing CSF flow and causing hydrocephalus. In some cases, the mass may expand into the region anterior to the pons or into the temporal lobe (Figure 3.102). A tumor arising within the sella may extend through the diaphragma sellae and enlarge in the suprasellar region, producing a dumbbell shape and symptoms of hypopituitarism.
AI-enhanced image · Compare details and arrows with the book image
Figure 3.101 Suprasellar craniopharyngioma extending into the third ventricle and obstructing the foramen of Monro.Figure 3.102 Craniopharyngioma enlarging in the temporal lobe and clival regions. Note the multiple cysts in the suprasellar portion of the tumor.
On section, the solid portion is pale and irregular because of scattered areas of hard calcification. Other portions form cysts of varying size. The cysts contain yellowish-brown fluid resembling machine oil, with small, golden-yellow cholesterol flakes (Figure 3.103) floating in it. This is an important diagnostic feature of the tumor.
AI-enhanced image · Compare details and arrows with the book image
Figure 3.103 A midline section of the brain showing a large craniopharyngioma. The cut surface is irregular, with scattered areas of calcification. A large cyst contains brown fluid and golden cholesterol flakes.
Viewed from the undersurface of the brain, a craniopharyngioma has an irregular surface with nodules of various sizes. It extends laterally and compresses the internal carotid artery. The mass obscures the optic nerves and chiasm. It also extends into the interpeduncular fossa, compressing cranial nerves and the posterior cerebral artery (Figure 3.104). These anatomical relationships are important in surgery.
HISTOLOGY
Craniopharyngioma consists of stratified squamous epithelium. The epithelium lining the microcysts is composed of columnar cells resting on a collagen basement membrane. Some areas of the stratified squamous epithelium contain pointed cells termed “prickle cells” (Figure 3.105 A, C). Other areas undergo keratinization or calcification (Figure 3.105 B).
AI-enhanced image · Compare details and arrows with the book image
Figure 3.104 Inferior view of the brain showing a craniopharyngioma with an irregular surface. The tumor displaces the internal carotid artery and obscures the optic nerve and chiasm. Note the small collections of white keratin sheets at the posterior aspect of the tumor (arrow).Figure 3.105 A. Characteristic appearance of craniopharyngioma: stratified squamous epithelium covering a connective tissue core. B. Craniopharyngioma showing keratin (arrow) and inflammatory cells intermingled with epithelium and connective tissue.
AI-enhanced image · Compare details and arrows with the book image
Figure 3.105 C. Microcysts lined by columnar cells. Some areas contain pointed cells termed “prickle cells”.
Craniopharyngioma grows very slowly and shows no mitoses.
Original pages 151–155
DERMOID AND EPIDERMOID CYSTS
These cysts arise from non-neuroepithelial cells and occur both intracranially and in the spinal canal. Both types result from heterotopia of ectodermal elements that come together in the midline during closure of the neural groove. Incomplete closure may leave a skin opening called a dermal sinus, often associated with a dermoid cyst along the sinus. This always occurs in the midline of the body. Intracranial dermoid cysts are less common than spinal dermoid cysts. They favor the posterior fossa, particularly the vermis and fourth ventricle, but may also occur in the frontal or occipital regions near the vertex. Spinal cysts are common in the lumbosacral region and may be extramedullary or intramedullary. They are often associated with other congenital abnormalities, such as diastematomyelia, syringomyelia, and Arnold–Chiari malformation.
Intracranial epidermoid cysts are more common than dermoid cysts, whereas spinal epidermoid cysts are less common. Their location is usually away from the midline.
Although epidermoid and dermoid cysts differ clinically and in their sites of occurrence, they are generally grouped together as “pearly tumors”.(48)
DERMOID CYST
Intracranial dermoid cysts are very rare. They tend to occur in the midline of the posterior fossa, especially the vermis and fourth ventricle, causing obstructive hydrocephalus. The most common age at presentation is between 10 and 20 years.
Pathology These are well-demarcated cysts of varying size. Externally, they appear pale pink mixed with opaque white. On section, their characteristic contents are sticky yellowish-white material derived from sebaceous gland secretions and epithelial breakdown. Hair or calcification may also be present (Figure 3.106). The cyst wall is usually firmly adherent to the surrounding brain and has a sparse blood supply.
AI-enhanced image · Compare details and arrows with the book image
Figure 3.106 Operative view of the cerebellum showing a dermoid cyst in the fourth ventricle. The cyst has a wall and contains fat, with a tuft of hair inferiorly (arrow).
Another important diagnostic clue is a dermal sinus in the occipital or lumbosacral region, which often leads to a dermoid cyst of the cerebellum. In some patients, this sinus provides a route for infection, causing meningitis.
HISTOLOGY The cyst is lined by stratified squamous epithelium and contains hair follicles, sebaceous glands, and sweat glands. Bone or cartilage may be seen in some cases.
EPIDERMOID CYST
Also called cholesteatoma, an epidermoid cyst occurs intracranially more often than a dermoid cyst. It usually arises away from the midline of the brain and may also occur in the diploic space of the skull. The most common site is the cerebellopontine angle (Figure 3.107), followed by the parapituitary region, the middle fossa (temporal lobe), and the paratrigeminal region. At the latter site, destruction of the petrous apex is common. Occasionally, an epidermoid cyst may arise within a cerebral hemisphere.
AI-enhanced image · Compare details and arrows with the book image
Figure 3.107 Epidermoid tumor at the cerebellopontine angle (arrow).
Pathology Epidermoid cysts are well demarcated. Their surface consists of small, rounded nodules of varying size, with a smooth, lustrous appearance resembling pearls, hence the name “pearly tumor” (Figure 3.108). Inside is white fatty material containing cholesterol crystals, derived from breakdown of keratin from the epithelium of the cyst wall. Calcification may be found in parts of the wall.
AI-enhanced image · Compare details and arrows with the book image
Figure 3.108 The characteristic pearly appearance of an epidermoid tumor, also known as a “pearly tumor”.Figure 3.109 The cyst wall of an epidermoid tumor, showing epithelium resting on collagenous tissue and laminated keratin.
HISTOLOGY The cyst wall consists of stratified squamous epithelium resting on a layer of collagenous tissue. Laminated keratinous material extends inward into the cyst (Figure 3.109).
Original pages 155–156
COLLOID CYST
This cyst occurs specifically in the anterior part of the third ventricle and is also called a paraphyseal cyst or neuroepithelial cyst. Its origin remains disputed. Those who believe it arises from the paraphysis—an embryonic projection of the telencephalon lying anterior to the diencephalon and subsequently disappearing—call a cyst in this region a paraphyseal cyst.(49) Others believe that a colloid cyst arises from the epithelium of the choroid plexus.(50)
Most colloid cysts are found in people aged 30–40 years.
Pathology The cyst is round and may have a stalk attached to the velum interpositum or choroid plexus of the third ventricle. Because it arises close to the foramen of Monro, it frequently obstructs that foramen and causes obstructive hydrocephalus (Figure 3.110). A large cyst may compress the walls of the third ventricle and the pillars of the fornix. The cyst wall is thin, and the contents are soft, grayish, gelatin-like material characteristic of a colloid cyst.
Figure 3.110 A colloid cyst in the third ventricle obstructing the foramen of Monro and causing hydrocephalus.
Cyst wall From outside inward, there is an outer layer of connective tissue, with lymphocytes and plasma cells in some areas. The inner surface is lined by epithelial cells, mostly cuboidal or low columnar, with cilia in some places. The epithelial cells often contain mucin (Figure 3.111 A). The center of the cyst contains amorphous material derived from mucus. In some cases, the cyst contents have an appearance termed pseudo-actinomycosis (Figure 3.111 B).
A
B
AI-enhanced image · Compare details and arrows with the book image
Figure 3.111 A. Wall of a colloid cyst. B. Pseudo-actinomycosis appearance encountered in a colloid cyst.
Original pages 157–158
LIPOMAS
Lipomas are very rare tumors that may occur both intracranially and in the spinal canal. Intracranial lipomas usually lie in the midline of the brain, most commonly at the corpus callosum, where they are often associated with partial or complete agenesis of the corpus callosum (Figure 3.112). Other sites include the tegmentum of the midbrain (Figure 3.113), infundibulum, choroid plexus, cerebellopontine angle, thoracic cord, and cauda equina.
AI-enhanced image · Compare details and arrows with the book image
Figure 3.112 Lipoma of the corpus callosum associated with agenesis of the corpus callosum.
These tumors may occur at any age, but are most commonly found between 20 and 40 years.
Pathology Lipomas are well demarcated but are often firmly adherent to the surrounding brain. Their characteristic feature is the yellow color of body fat (Figure 3.112). Most have a sparse blood supply, although some are richly vascular and are called angiolipomas. Calcification may occur in the wall of the mass. Lipomas at the cerebellopontine angle often extend between cranial nerves, making dissection difficult and leading to loss of cranial nerve function.
AI-enhanced image · Compare details and arrows with the book image
Figure 3.113 Lipoma on the upper aspect of the midbrain and pons.
HISTOLOGY Lipomas consist of fatty tissue. In angiolipomas, numerous blood vessels are interspersed within the fatty tissue.
Original pages 158–167
TUMORS OF THE PITUITARY GLAND
These tumors belong to the group located outside the brain substance and extending directly into the brain, without hematogenous dissemination. Most arise in the anterior lobe of the pituitary gland, or adenohypophysis. Two tumor types occur there: pituitary adenoma and pituitary adenocarcinoma. The former is by far the most common; the latter is very rare (the author has encountered only one case). Tumors arising from the neurohypophysis, namely gliomas, are even rarer.
PITUITARY ADENOMAS
These are benign tumors arising from the cells of the adenohypophysis, which are divided into three types according to their staining characteristics:
Chromophobe cells are the most numerous cells in the pituitary gland and show no secretory granules with ordinary staining.
Acidophilic cells (eosinophils or alpha cells) are the second most numerous. Their cytoplasmic granules take up acid dyes and appear pink-red with hematoxylin and eosin (H & E).
Basophilic cells (beta cells) are the least numerous. Their cytoplasmic granules take up basic dyes, appearing purple, and stain blue with AF–AB.
For many years, pituitary adenomas were divided into three types according to their staining with H & E and named after the cell type forming the tumor:
Chromophobe adenoma, believed not to produce hormones.
Acidophilic adenoma, secreting growth hormone and prolactin and producing gigantism and acromegaly.
Basophilic adenoma, secreting ACTH and melanin-stimulating hormones and causing Cushing’s disease.
In the author’s surgical experience, chromophobe adenoma is the most common type, accounting for approximately 80–90%, whereas basophilic adenoma is the least common.
The classification described above is now considered outdated because classification by tumor-cell staining does not correlate sufficiently with hormone secretion and cytogenesis. A new classification of pituitary adenoma was therefore developed following the introduction of electron microscopy and immunocytochemistry, which provide information about cellular hormone secretion, ultrastructure, and cytogenesis. Immunocytologic techniques demonstrate the types of hormones produced in the cytoplasm, while electron microscopy demonstrates the ultrastructure of different cell types, whose intracellular details differ and help distinguish adenoma types. Pituitary adenomas are accordingly classified by hormone secretion and function as follows:(51,52)
Plurihormonal adenoma (secreting more than two hormones, usually growth hormone cells together with prolactin cells).
Null cell adenoma (no hormone production).
This new classification can be divided into two groups. The first comprises tumors that do not produce hormones (endocrine-inactive adenomas), namely null cell adenomas, which have no clinical hormonal manifestations. The other group comprises hormone-producing tumors (endocrine-active adenomas), including all the remaining adenoma types. Patients exhibit manifestations corresponding to the hormones produced by the tumor.
Age Pituitary adenoma is a tumor of adults, most frequently encountered between 35 and 45 years. In general, hormone-producing adenomas that cause hormonal manifestations occur at a younger age than non-hormone-producing adenomas. For example, acidophilic adenomas producing growth hormone tend to occur in younger people than chromophobe adenomas and cause gigantism. Pituitary adenocarcinoma also occurs in young people.
Pathology A pituitary adenoma arises within the sella turcica and expands in all directions. The tumor is demarcated but has no capsule. As it enlarges, compressed sellar bone is resorbed and reformed, producing the appearance called ballooning of the sella. With a very large tumor, the bone may disappear entirely and the tumor extends into the sphenoid sinus (Figure 3.114). Lateral expansion pushes the medial wall of the cavernous sinus laterally; the internal carotid siphon becomes elevated and displaced farther from the midline, as seen on carotid angiography. At the same time, the remaining pituitary gland is flattened, with a portion still connected to the pituitary stalk; the surgeon must try to preserve this during surgery. Upward expansion elevates and markedly thins the diaphragma sellae until it resembles a capsule over the upper surface of the tumor. Compressed bone of the anterior clinoid process is resorbed, becoming thin and elevated or disappearing. When the mass extends above the sella turcica, the optic chiasm is compressed (Figure 3.115) and usually displaced backward, because in most cases the optic chiasm lies relatively posteriorly, termed a postfixed chiasm. The adenoma is then seen between the two optic nerves. Both optic nerves and the chiasm become thin and pale. With a prefixed chiasm, the tumor grows upward behind the chiasm, compressing the floor of the third ventricle or enlarging to replace the third ventricle and obstruct both foramina of Monro, causing obstructive hydrocephalus. In some cases, the tumor extends into the interpeduncular fossa, anterior to the pons, and onto the medial aspect of the temporal lobe (Figure 3.116). Such extensive spread usually occurs with chromophobe adenomas. The tumor may also extend beneath the frontal lobe, causing anosmia, confusion, and seizures. Acidophilic and basophilic adenomas seldom grow beyond the sella.
Figure 3.114 Pituitary adenoma destroying the sella turcica and growing into the sphenoid sinus. Note extension of part of the tumor into the suprasellar region.
AI-enhanced image · Compare details and arrows with the book image
Figure 3.115 Pituitary adenoma compressing the optic chiasm.
AI-enhanced image · Compare details and arrows with the book image
Figure 3.116 Pituitary adenoma extending into the interpeduncular fossa, anterior to the midbrain and pons, and to the temporal lobe. This pattern usually occurs with chromophobe adenoma.
In some cases, the tumor extends laterally through the cavernous sinus into the middle cranial fossa (Figure 3.117), causing ophthalmoplegia and facial numbness in the territories of the ophthalmic and maxillary nerves.
Spontaneous hemorrhage into the tumor occurs in a few cases and is fatal in nearly all such patients.
The tumor is gray-pink, demarcated, moderately vascular, and soft, so it can be readily aspirated or excised during surgery. Some tumors undergo necrosis; when the capsule is incised, cream-like tumor material flows out. Some form cysts containing straw-colored or brown fluid, the latter indicating previous hemorrhage.
Figure 3.117 Chromophobe adenoma extending through the cavernous sinus into the middle cranial fossa, causing facial numbness and ophthalmoplegia.
HISTOLOGY As stated above, histologic examination with H & E staining and ordinary light microscopy is insufficient to identify tumor-cell ultrastructure and hormones produced within the cells. Electron microscopy and immunocytochemistry are required. Readers interested in tumor-cell ultrastructure may consult reference (51).
In institutions without these special investigative facilities, ordinary staining and light microscopy remain usable, dividing adenomas into three types according to staining: chromophobe, acidophilic, and basophilic adenomas. These names are still used by most neurosurgeons.
The cellular patterns of each tumor type are as follows:
CHROMOPHOBE ADENOMA
These tumors consist of chromophobe cells in which hormone-secretory granules are not visible. Histologically, the cells are arranged in three patterns.
Type 1, the diffuse pattern, is the most common. It consists of polygonal cells of uniform size with pale-staining cytoplasm. Groups of cells are separated by connective tissue stroma. Sometimes the cytoplasm is clear, producing a space around the nucleus (Figure 3.118).
Figure 3.118 Chromophobe adenoma with uniformly sized cells and pale-staining cytoplasm in a diffuse pattern. Cell groups are separated by connective tissue. Note the resemblance of the cells to oligodendroglioma.
Type 2, the sinusoid pattern, has cells arranged around blood vessels (Figure 3.119), resembling an ependymoma or astroblastoma.
AI-enhanced image · Compare details and arrows with the book image
Figure 3.119 Sinusoid pattern of chromophobe adenoma, with cells arranged around blood vessels.
Type 3, the papillary pattern, has cells arranged around connective tissue cores containing blood vessels (Figure 3.120).
Several cellular patterns may be present within the same tumor.
AI-enhanced image · Compare details and arrows with the book image
Figure 3.120 Papillary pattern of chromophobe adenoma, with cells arranged around connective tissue cores containing blood vessels.
ACIDOPHILIC ADENOMA
The tumor cells are relatively densely packed without a specific pattern. Only a small amount of connective tissue stroma lies between cell groups, and blood vessels are seen in some areas. The important feature is the presence of cytoplasmic granules staining pink-red with H & E (Figure 3.121). Chromophobe cells are usually also present in acidophilic adenomas.
AI-enhanced image · Compare details and arrows with the book image
Figure 3.121 Acidophilic adenoma composed of cells with cytoplasmic granules staining pink-red (H & E).
BASOPHILIC ADENOMA
These consist of cells resembling the beta cells of the pituitary gland, with round, pale nuclei and purple-staining cytoplasm.
PITUITARY ADENOCARCINOMAS
This is a carcinoma of the anterior pituitary cells, occurring more often in chromophobe cells than in other cell types, and is very rare. The tumor has high mitotic activity and malignant features: (1) local infiltration into the dura, bone, brain substance, and sinuses, unlike adenomas, which expand by compressing adjacent structures; (2) dissemination through the CSF; and (3) metastasis to other organs. The author has encountered only one pituitary adenocarcinoma, in a 13-year-old boy who presented with headache and blurred vision for four months. Examination showed bitemporal hemianopia and early optic atrophy. CT demonstrated a sellar tumor extending into the suprasellar region. The tumor was removed, and histology showed pituitary adenocarcinoma. Two months after surgery, the patient developed paraparesis. Investigation revealed compression of the upper thoracic cord by a tumor. Laminectomy disclosed a tumor in the subarachnoid space compressing the spinal cord. It was soft and gray-brown (Figure 3.122). The tumor was dissected out, and histology again showed pituitary adenocarcinoma, identical to the tumor in the sella turcica.
AI-enhanced image · Compare details and arrows with the book image
Figure 3.122 Spinal subarachnoid pituitary adenocarcinoma. Note the gray-brown tumor. The patient underwent removal of a pituitary adenocarcinoma two months earlier.
Original pages 167–168
GLOMUS JUGULARE TUMORS
These tumors arise from small cell clusters (glomus bodies), composed of non-chromaffin paraganglioma cells belonging to the chemoreceptor system, like the carotid and aortic bodies. These cells lie within the petrous portion of the temporal bone, attached to the adventitia of the jugular bulb and adjacent to the floor of the middle ear,(53) or the tympanic branch of the glossopharyngeal nerve. Alternative names include chemodectomas and nonchromaffin paragangliomas. They are very rare, slow-growing tumors, usually occurring in middle age.
Pathology These tumors are highly vascular and reddish. They receive blood from the ascending pharyngeal artery, sometimes supplemented by branches of the posterior auricular, occipital, and internal maxillary arteries. Most begin in the adventitia of the jugular bulb and extend into the middle ear, bulging the tympanic membrane or perforating into the external auditory canal, where they can be seen with an otoscope. Some patients have bleeding from the ear. As the tumor enlarges, it destroys the petrous temporal bone and enters the posterior fossa at the jugular foramen, forming a mass in the cerebellopontine angle and compressing cranial nerves IX, X, and XI. Other manifestations of a cerebellopontine-angle tumor occur as described earlier. In some cases, the mass grows downward to lie beside the pharynx, and it may extend into the internal jugular vein.
The histology is characteristic: clear cells with central nuclei and fine cytoplasmic granules are arranged in clusters separated by thin-walled blood vessels and fibrous tissue (Figure 3.123).
AI-enhanced image · Compare details and arrows with the book image
Figure 3.123 Glomus jugulare tumor. Histology shows cells with fine, pale-staining cytoplasmic granules, arranged in clusters separated by fibrous tissue and blood vessels.
Original pages 168–171
CHORDOMA
This is another tumor arising outside the brain and enlarging to compress the brain and nerves. It arises from remnants of the notochord within midline bones, from the skull base at the sella and clivus down the vertebral column to the coccyx.
Abnormalities of the notochord usually occur at its cranial and caudal ends; chordomas are therefore most frequently found at the clivus and sacrococcygeal region.
Intracranial chordomas accounted for 0.2% of a series of 6,000 intracranial tumors.(54) They occur at all ages, but most commonly at approximately 35–40 years.(55)
The favored sites are the clivus and beneath the sella turcica. As the tumor grows, it destroys bone, enters the epidural space, and then penetrates the dura to lie anterior to the brainstem. It compresses the brainstem, cranial nerves according to the direction of spread, and vessels at the base of the brain.
Pathology Chordomas are soft, gelatinous, gray-white tumors with a nodular surface and foci of hemorrhage. In addition to compressing the pons and medulla, they may extend laterally into the middle fossa (Figure 3.124), cavernous sinus, and cerebellopontine angle. Some extend downward, forming a bulge in the nasopharynx.
AI-enhanced image · Compare details and arrows with the book image
Figure 3.124 Chordoma of the clivus, with a soft, gelatinous consistency and nodular surface, extending into the cavernous sinus and middle cranial fossa.
HISTOLOGY The cells have a characteristic large cytoplasmic vacuole, giving a bubbly appearance termed “physaliphorous.”(56) They are similar in size and appearance and form clusters separated into compartments by fibrous tissue (Figure 3.125 A, B). Abundant mucin lies between the cells,
A
B
AI-enhanced image · Compare details and arrows with the book image
Figure 3.125 A. Chordoma composed of cells with large cytoplasmic vacuoles, giving a sponge-like (physaliphorous) appearance. Cell clusters are separated by fibrous tissue. B. Chordoma cells with a bubbly (physaliphorous) appearance.
which can be demonstrated with a mucin stain. Chordoma is a benign tumor, so mitotic figures are not found. However, because it extends in all directions and lies in a location where complete surgical removal is very difficult, recurrence is frequent.
Original pages 171–172
CARCINOMAS OF THE NASOPHARYNX
In addition to the chordomas and glomus jugulare tumors described above, tumors arising at the skull base and extending intracranially include carcinomas of the nasopharynx and paranasal sinuses. Nasopharyngeal carcinoma is common among Thai people of Chinese ancestry, whereas carcinoma of the paranasal sinuses is less common.
As a nasopharyngeal tumor grows, it extends into the sphenoid and ethmoid sinuses and through the skull-base foramina transmitting cranial nerves, destroying the surrounding bone. Skull radiographs show loss of the air shadow in the sphenoidal sinus, replaced by soft-tissue density, together with loss of portions of bone. Further enlargement destroys the sellar bone and surrounding areas, ultimately forming a mass in the sellar region (Figure 3.126). The nearby optic, oculomotor, trigeminal, trochlear, and abducens nerves are compressed and lose function. Cranial nerves VII through XII are seldom affected unless the mass is very large and extends to the pons and medulla.
Usual manifestations include epistaxis, facial numbness or pain, ophthalmoplegia, and loss of vision. In some cases, in addition to destroying the sellar bone, the tumor extends into the orbit, producing exophthalmos on that side (Figure 3.127).
Transitional cell carcinoma is the most common type of nasopharyngeal tumor extending intracranially. Other types include malignant papilloma and fibroepithelioma.
AI-enhanced image · Compare details and arrows with the book image
Figure 3.126 Nasopharyngeal carcinoma extending into the skull base and destroying the medial sphenoid wing. Note encasement of the right optic nerve, oculomotor nerve, and internal carotid artery by tumor.Figure 3.127 Nasopharyngeal carcinoma destroying the left sellar bone and extending into the orbit, causing unilateral exophthalmos.
Original pages 172–179
METASTATIC BRAIN TUMORS
These brain tumors result from spread of cancer elsewhere in the body. Reported frequencies vary considerably, depending on whether the report comes from a neurosurgeon or a neuropathologist. The most frequent primary is lung cancer, followed by breast cancer. Primaries in the kidney, prostate gland, and gastrointestinal tract are very uncommon. Cutaneous melanoma and chorioepithelioma have a strong tendency to spread to the brain, but fortunately these tumors are rare. The third most common group, after breast cancer, comprises cancers whose primary organ cannot be identified. These patients present with manifestations of a malignant brain tumor, and surgery establishes that the brain lesion is metastatic from another organ. Various investigations fail to locate the primary. Thyroid and prostate cancers tend to metastasize to the skull; the author has never encountered direct metastasis to the brain from either.
Children differ from adults because lung and breast cancers are not encountered in children. Instead, there are other rare tumors, including neuroblastoma, rhabdomyosarcoma, and Wilms tumor. Among these, Wilms tumor metastasizes to the brain two to five times more frequently than neuroblastoma and rhabdomyosarcoma.(57)
Age The age at which these brain tumors occur corresponds to that of the underlying cancer and varies with tumor type. Most patients are approximately 40–60 years old.
Pathogenesis There are two principal routes by which cancer reaches the brain: the bloodstream and direct extension into the cranial cavity, as with nasopharyngeal carcinoma described earlier. This section deals only with hematogenous spread. Spread through lymphatic vessels is not possible because the human brain has no lymphatic vessels.
Most cancer cells detach and reach the brain through arteries. The likelihood of tumor formation differs between brain regions according to their unequal blood flow. Regions supplied by the internal carotid artery receive more blood than those supplied by the vertebrobasilar arteries. Metastatic brain tumors therefore occur more often supratentorially than infratentorially, most commonly in the middle cerebral artery territory.
Pathology
Cancer spreading into the cranial cavity may occur at the following sites:
1) The dura, from which it enlarges into the subdural space and compresses the cortical surface, producing focal manifestations when large. In the author’s experience, these are usually small, round nodules. Tumors may also grow in the epidural space (Figure 3.128). Some may become very large, as in Figure 3.129. This patient was admitted to the psychiatry department with psychiatric symptoms and deterioration in personality. Two months later, the patient died from raised intracranial pressure. Examination of the brain revealed a large extradural mass over the left frontal lobe. Its surface was irregular and its color was green, resembling bile. Histology showed hepatoma. This is the only case of metastatic brain tumor from hepatoma encountered by the author.
AI-enhanced image · Compare details and arrows with the book image
Figure 3.128 Metastatic tumor in the epidural space.Figure 3.129 Large metastatic tumor in the epidural space over the frontoparietal lobe, with an irregular surface and a bile-green color. Histology showed hepatoma.
2) The leptomeninges. Cancer cells disseminate throughout the leptomeninges, subarachnoid space, and Virchow–Robin spaces, usually without a visible mass; thus this should not be termed a tumor mass. Grossly, the arachnoid membrane is thickened, cloudy, and grayish. The ventricles are often enlarged because of hydrocephalus. Histology shows numerous cancer cells in the subarachnoid space (Figure 3.130).
Figure 3.130 Dense dissemination of cancer cells in the subarachnoid space.
3) The brain substance. This is the most common type and forms a distinct mass, usually at the junction of white and gray matter (Figure 3.131). This is because that region is the junction between capillaries and venules, where cancer cells lodge and then grow inward or toward the cortical surface. The vessel containing the cancer cells becomes a feeding vessel for the tumor and enlarges and becomes more tortuous, as seen on angiography. This appearance is used in angiographic diagnosis of the tumor type.
AI-enhanced image · Compare details and arrows with the book image
Figure 3.131 Metastatic brain tumors at the junction of white and gray matter. Note the multiple lesions, an important diagnostic feature.
There may be a solitary mass or multiple masses (Figure 3.131), occurring simultaneously in the cerebral hemispheres, cerebellum, and brainstem of the same patient. When multiple lesions occur, they vary in size (Figure 3.132) because they reach the brain at different times. The masses are well demarcated. Larger masses tend to extend medially into white matter and often show cystic degeneration or necrosis. During surgery, aspiration of a cyst before tumor dissection may yield thick whitish-pale-yellow fluid resembling pus, raising suspicion of a brain abscess. However, the clinical history and a mass on chest radiography should suggest metastasis. Intraoperative frozen section can distinguish the two clearly. A mass close to the cortical surface and dura may cause a dural reaction and adhere to the dura, resembling a meningioma at surgery.
Figure 3.132 Multiple metastatic brain tumors of different sizes, an important diagnostic feature. Note solid, cystic, and hemorrhagic lesions.
An important feature of metastatic brain tumors is cerebral edema, which may be severe and unrelated to the size of the mass. Even a small tumor may cause extensive edema (Figure 3.133), clearly visible on CT. This can cause rapid deterioration through raised intracranial pressure and herniation. The softness of the surrounding brain, however, facilitates dissection and removal of the tumor.
Figure 3.133 Metastatic brain tumor with marked surrounding cerebral edema unrelated to the size of the mass.
The cut surface is gray-pink. Some tumors are solid, whereas others are cystic. Mucin-producing tumors may contain pale-green, gelatinous fluid within the cyst. Cyst fluid may also be brown because of previous hemorrhage.
A metastatic brain tumor may destroy brain substance, dura, and skull at the same site. The patient in Figure 3.134 had breast cancer with multiple brain metastases and metastases in both lungs. Biopsy of a swelling on the forehead showed breast cancer. At surgery, the skull was found to have been destroyed by the tumor. Edema surrounding the frontal-lobe mass suggested a tumor within the brain substance, but it was difficult to determine whether the lesion began in the brain, dura, or skull before extending into and destroying the other structures. Nevertheless, this example demonstrates that a metastatic tumor may destroy the brain, dura, and skull in the same region.
Figure 3.134 Metastatic brain tumor destroying the brain, dura mater, and skull. Note another lesion in the occipital lobe. This patient had breast cancer.
HISTOLOGY
The histology follows that of the cancer in the primary organ and need not be described here.
Original pages 179–181
METASTATIC MELANOMA
Melanoma most often arises in the skin and has a very strong tendency to metastasize to the brain. The primary lesion should therefore receive attention and treatment at an early stage. Fortunately, this tumor is very rare.
Pathology
Like other cancers, melanoma spreads through the bloodstream. It may form a solitary brain lesion or multiple lesions, but usually occurs at multiple sites, both superficially and deep within the brain. Marked edema surrounds the tumors, as with other cancers. The distinctive gross feature of melanoma is its black color (Figure 3.135). The masses are well demarcated (Figure 3.136), with a homogeneous black-brown cut surface and a soft consistency.
Figure 3.135 Metastatic malignant melanoma in the brain. Note the multiple black tumors.Figure 3.136 Surgical specimen showing a well-demarcated black malignant melanoma.
HISTOLOGY
The tumor consists of small melanotic cells with round nuclei and prominent nucleoli. Its characteristic feature is melanin pigment within the cytoplasm (Figure 3.137).
AI-enhanced image · Compare details and arrows with the book image
Figure 3.137 Malignant melanoma. Note cytoplasmic melanin pigment and mitosis.
Additional color images · Chapter 3
Color images from the original collection whose figure numbers have not yet been confirmed. They are displayed by filename to make the complete collection available without assigning them to incorrect places in the textbook.
pathology003 · Additional color image; figure number not yet confirmed
pathology052 · Additional color image; figure number not yet confirmed
pathology059 · Additional color image; figure number not yet confirmed
pathology062 · Additional color image; figure number not yet confirmed
pathology094 · Additional color image; figure number not yet confirmed
pathology110 · Additional color image; figure number not yet confirmed
pathology149 · Additional color image; figure number not yet confirmed
Original pages 181–183
Chapter 3 references
Bailey P., Cushing H.A., : A classification of the tumor of glioma group on a histogenetic basis with a correlated study of prognosis. Philadelphia. Lippincotl, 1926.
Kenohan J.W. and Sayre G.P. Tumor of the Central Nervous System. Fascicle 35, Atlas of tumor pathology. Washington : Armed Force Institute of Pathology, 1952.
Russell D.S., Rubinstein L.J., Pahtology of Tumors of the Nervous System. p.106-112,1989.
Zulch K.J., Brain Tumors, Their Biology and Pathology. p. 223, 1986.
Stern, J., Di. Giacinto, G.V. and Housepain, E.M., Neurofibromatosis and optic gliomas : Clinical and morphologic correlation. Neurosurgery, 4 : 524-528, 1979.
Hoyt, W.R., and Baghdassarian S.A. : Optic glioma of childhood : Natural history and rationale for conservative management Br. J. Ophthalmology, 53 : 793-798, 1969.
Clinterian, A.M., Schwartz, J.F., Evan, R.A., and Corter, S. Neurology, 14, 83, 1964.
Russell D.S., Rubinstein L.J., Pathology of Tumors of The Nervous System 5th ed. p. 150, 1989.
Russell D.S., Rubinstein L.J, Pathology of Tumors of The Nervous System 5th ed., p. 219-220, 1989.
Russell D.S., Rubinstein L.J., Pathology of Tumors of The Nervous System 5th ed. p. 173, 1989.
Zulch K.J., Brain Tumors, Their Biology and Pathology. p. 241, 1986.
Okazaki, H., Scheithauer, B.W., : Neoplasms and Related Lesions, in Atlas of Neuropathology, Gower Medical Publishing P 89, 1988.
Zulch K.J., Brain Tumors, Their Biology and Pathology. p. 260-272, 1986.
Russell D.S., Rubinstein L.J., Pathology of Tumors of The Nervous System 5th ed. p. 195, 1989.
Arendt Alexander : Ependymomas. In Tumor of The Brain and Skull, edit by Vinken P.J., and Bruyn A.W., North-Holland Publishing Co. p. 105-150,1975.
Shuangshoti S., Netsky M.G., Histogenesis of the choroid plexus in man. Am. J. Ant.118 : 283-316,1966.
Laurence, K. M., The biology of choroid plexus pap. in infancy and childhood Acta Neurochirurgica., 50, 79, 1979:
Lewis, P. : Carcinoma of the choroid plexus. Brain, 90 : 177-189, 1967.
Russell D.S., and Rubinstein, L.T., : Pathology of tumors of the nervous system p. 402, 1989:
Russell D.S., Rubinstein L.J., Pathology of Tumors of The Nervous System 5th ed. p. 251, 1989.
Raaf, J and Kernohan, J.W. Relation of abnormal collections of cells in posterior medullary velum of the cerebellum to origin of medulloblastoma Archives of Neurology and Psychiatry. 52, 163, 1944.
Zimmerman, H.M., Brain tumor : Their incidence and classification in man and their experimental production. Annals of the New York Academy of Sciences 159, art 2, 337, 1969.
Zu Rhein, G.M. and Varakis J.N., Perinatal induction of medulloblastomas in Syrian golden hamsters by a human polyoma virus (JC), National Cancer Institute Monographs. 51, 205, 1979.
Nagashima, K., Yasui, K., Kimura, J. Washizu, M., Yamaguchi, K., and Mori W. Induction of brain tumors by a newly isoloted J.C. virus (Tokyo - 1 strain) Am. J. of Patho., 116, 455, 1984.
Zulch K.J., Brain Tumors, Their Biology and Pathology. p. 324, 1986.
Russell D.S., Rubinstein L.J., Pathology of Tumors of the Nervous System. 5th ed. p. 261-263, 1989.
Friedman N.B., Germinoma of the pineal. Its identity with germinoma (“seminoma”) of the testis. Cancer Res. 7 : 363 - 368, 1947.
Russell D.S., Rubinstein L.J., Pathology of Tumors of the Nervous System 5th ed. p. 380-394, 1989.
Zulch K.J., Brain Tumors, Their Biology and Pathology. p. 288, 1986.
Kalumpaheti R., Thumnoon K., Thanaphum U : The pineal tumors in Thailand. J. Neuropathol. Exp. Neurol. 37 : 639, 1978.
Russell D.S., Rubinstein L.J., Pathology of Tumors of The Nervous System. 5th ed. p. 533, 1989.
Slooff, J.L., Pathological anatomical findings in cerebellopontine angle. Advances in Oto. Rhino Laryngology 34, 89, 1984.
Baloh R.W., Honrubia V., : Clinical Neurophysiology of the vestibular system. Philadelphia, F.A., Davis, 1979.
Rubinstein L.J., Tumors of the C.N.S. Armed Forces Institute of Pathoogy p. 209, 1972.
Russell D.S., Rubinstein L.J., Pathology of Tumors of The Nervous System 5th ed. p.465, 1989.
Horten B.C., Urich H, Rubinstein, L.J., Montague SR: The angioblastic meningioma : A reappraisal of a nosological problem. J. Neurol. Sci.,31 : 387-410, 1977.
Pitkethly DT., Hardman J.M., Kempe LG, Earle K.M.,: Angioblastic meningiomas : clinicopathologic study of 81 cases. J. Neurosurg., 32 : 539 - 544. 1970.
Kepes J. J., : Meningiomas : Biology, Pathology, and Differential Diagnosis. New York, Masson, 1982.
Russell D.S., Rubinstein L.J., Pathology of Tumors of The Nervous System p. 56, 1963.
Zulch K.J., Brain Tumors, Their Biology and Pathology. p.400, 1986.
Russell D.S., Rubinstein L.J., Pathology of Tumors of The Nervous System. p.639,1989.
Rubinstein L.J., Tumors of The C.N.S. Armed Froces Institute of Pathology. p. 236, 1972.
Jeffreys, R.V., Napier, J. and Reynolds S.H., Erythropoietin levels in posterior fossa hemangioblastoma., J. of Neurol, Neurosurg. and Psych.45, 264, 1982.
Hennesy, T.G., Stern, W.E. and Herrick, S.E., Cerebellar hemangioblastoma : erythropoietic activity by radioiron assay.,J. of nuclear medicine., 8, 601, 1967.
Luse, S. A., and Kernohan, J. W. : Squamous cell nests of the pituitary gland. Cancer, 8: 623-628, 1955.
Rubinstien, L.J., Tumors of the central nervous system Armed Forces Institute of Pahtology Washington D.C., pp. 292-294. 1972.
Humphreys, R.P., Hoffmans, H.j., and Hendrick, F.B., A long term post-operative follow-up in craniopharyngioma. Childs, Brain, 5 : 530-539, 1979.
Tytus J.S., and Pennybacker, J., Pearly tumors in relation to the central nervous system J. Neurol., Neurosurg. Psychiat., 19 : 241-259,1956.
Ariens xappers, J. A., The development of paraphysis cerebri in man with comments on its relationship to the intercolumnar tubercle and its significance for the origin of cystic tumors in the third ventricle, J. Comp. Neurol.,102 : 425-509, 1955.
Shuangshoti, S., and Netsky M.G., Xanthogranuloma (xanthoma) of choroid plexus. The origin of foamy (xanthoma) cells. Amer. J. Path. 48 : 503-533, 1966.
Horvath, E., and Kovaces, K., Ultrastructural classification of pituitary adenoma. Can. J. Neurol. sci., 3 : 9, 1976.
Kovacs, K., Horvath. E., Asa. S. L., Classification and patholgy of pituitary tumors in Neurosurgery edit by Wilkins R.H., Rengachary S.S., Mc Graw-Hill Book Co. Vol. I : 834-842, 1985.
Kramer, W., Glomus jugulare tumors. In Tumors of The Brain and Skull part III edited by Vinken P.J. and Bruyn G.W. North-Holland Pub. Co.,435 - 452, 1975.
Zulch K.J., Brain Tumors, Their Biology and Pathology. p. 477-479, 1986.
Sassin, J.F., Intracranial chordoma, In Tumors of the Brain and Skull ed. by Vinken P.J., and G.W., Bruyn part III p. 151-163, 1975.
Rubinstein L.J., Tumors of The C.N.S. Armed Forces Institute of Pathology p. 316, 1972.
Vannucci, R.C., and Baten, M. : Cerebral metastatic disease in children. Neurology (minneap), 24 : 981-986, 1974
Original pages 184–192
Chapter 4
PATHOPHYSIOLOGY OF INCREASED INTRACRANIAL PRESSURE IN BRAIN TUMOR
Raised intracranial pressure is extremely important because it is a major cause of death. Diseases affecting the brain—including brain tumors, intracranial hemorrhage, brain abscess, brain injury, cerebral edema, and obstruction of cerebrospinal fluid circulation—are all space-expanding lesions that cause raised intracranial pressure and ultimately death. The brain tumor itself, or the other lesions mentioned above, does not cause death by directly destroying vital brain structures. Rather, death results when the tumor raises intracranial pressure and displaces the brain, compressing the brain stem. Early diagnosis of this condition therefore improves treatment results. Conversely, delayed diagnosis delays treatment, leading to poor recovery or death. Physicians should understand the pathophysiological changes, symptoms, and signs of raised intracranial pressure so that they can recognize the condition early.
Intracranial pressure (ICP)
The human skull consists of rigidly fused plates that cannot expand, except in young children whose skull plates have not yet fused. Its only outlets are the foramen magnum and the openings for the cranial nerves. Intracranial pressure arises from three components within the cranial cavity: (1) brain tissue; (2) cerebrospinal fluid (CSF) in the ventricles, cisterns, and subarachnoid spaces; and (3) blood vessels and the blood circulating within the cranial cavity (Figure 4.1). The Monro–Kellie doctrine (1821) states that the intracranial contents are incompressible. If the volume of any one of these three components increases, or an expanding mass enters the cranial cavity, the volume of the other components must decrease. CSF and blood are the first components whose volumes can decrease most rapidly and readily. Loss of water from brain tissue occurs slowly.
Color added · Anatomical details based on the original imageFigure 4.1. Intracranial components that generate pressure under normal conditions. These components can compensate for rising intracranial pressure and maintain it within normal limits for a time.
Because the skull cannot expand, increasing the volume of its contents progressively raises intracranial pressure. Compensatory mechanisms initially maintain pressure within normal limits, but they can compensate only to a certain extent. Once these mechanisms are fully utilized, continuing progression of the lesion raises intracranial pressure and produces decompensation. Unless the condition is corrected or its cause removed in time, brain herniation and eventual death may occur.
Compensatory mechanisms for intracranial pressure
1. Loss of tissue fluid from the brain. The brain is soft and can undergo localized atrophy through loss of water from the tissue at the site of a tumor or another expanding mass, leaving intracranial pressure unchanged. This phenomenon is often seen with slowly growing benign tumors, such as meningiomas. Removal of the tumor reveals a distinct cavity in the brain (Figure 4.2). In contrast, rapidly growing malignant tumors or other rapidly expanding masses, such as an intracerebral hematoma, cause brain edema (Figure 3.13) and a rapid increase in intracranial pressure, leading to brain herniation within a short time.
Figure 4.2. Localized atrophy forms a cavity in the brain (arrow) at the site of an expanding tumor (arrowhead).
2. Reduction in ventricular, cisternal, and subarachnoid CSF volume. CSF in these spaces is displaced most readily and provides the most important mechanism for compensating intracranial pressure. The ventricles and subarachnoid spaces clearly become smaller or collapse when intracranial pressure is very high (Figure 4.3). The effectiveness of this mechanism depends on the CSF passageways at the tentorial opening and foramen magnum. If downward displacement of brain tissue obstructs these sites, little or no CSF can flow into the spinal canal, limiting pressure reduction. In such cases, lumbar puncture and measurement of CSF pressure in the lumbar subarachnoid space may not reflect the true intracranial pressure. Lumbar puncture is also dangerous because it may increase brain herniation and cause death.
Figure 4.3. A tumor in the right frontal lobe raises intracranial pressure. The right ventricle (arrow) and subarachnoid space (arrowhead) are collapsed, whereas those on the left remain wide and clearly visible.
3. Reduction in intracranial blood volume. It is difficult to determine how important the reduction in blood volume is in compensating intracranial pressure. Nevertheless, changes in blood volume almost certainly occur. Cerebral angiograms in patients with very high ICP show narrowing of the arteries, veins, and sinuses. In some patients no contrast material is seen in the cerebral vessels—the non-filling phenomenon—when ICP exceeds arterial blood pressure (Figure 4.4).
Figure 4.4. Carotid angiogram showing absence of blood flow into the cerebral vessels because intracranial pressure is very high.
4. Separation of the skull sutures. Separation of the cranial sutures occurs in young children whose sutures have not yet fused into bone. This is another important mechanism for compensating intracranial pressure in children. A child with raised intracranial pressure may therefore have an abnormally large head before symptoms of raised pressure become apparent.
Intracranial volume–pressure relationship
Langfitt, T.W.(3) demonstrated an interesting relationship between volume and ICP that is useful in explaining changes in the condition of patients with raised intracranial pressure caused by an expanding intracranial mass. In his experiment, a balloon was placed in the epidural space and gradually inflated with water at 1 cc per hour while ICP was measured continuously. During the early stages of balloon expansion, ICP remained normal without rising. In Figure 4.5, the horizontal portion of the curve shows that the added volume is offset by an equal reduction in the volume of other intracranial contents—CSF, blood, and brain tissue fluid—so pressure remains constant. This is called the compensation period. Further increases in balloon volume raise the pressure. Beyond a certain point, even a small increase in volume causes an immediate, steep rise in ICP, shown by the vertical portion of the curve. This indicates that the intracranial volume available to compensate for the enlarging mass has been exhausted, so pressure rises abruptly.
Color added · Anatomical details based on the original imageFigure 4.5. Relationship between the volume of an expanding intracranial mass and intracranial pressure.
When a mass expands rapidly, the compensatory mechanisms are exhausted sooner and the vertical portion of the curve shifts to the left. Other conditions that reduce the effectiveness of these mechanisms, such as cerebral edema or anoxia, likewise shift the vertical portion to the left. The experiment shows that if a large intracranial volume is available to compensate for an expanding mass, ICP does not increase and the mass can become very large (Figure 4.6). Conversely, if little compensatory volume is available, even slight expansion of a mass can produce a dangerous, marked increase in ICP. In patients who already have expanding lesions, care must therefore be taken to avoid conditions that cause vasodilatation, such as respiratory obstruction, hypercapnia, hypoxia, and the use of volatile anesthetic agents. All increase cerebral blood flow through cerebral vasodilatation and may raise intracranial pressure sufficiently to cause death.
Color added · Anatomical details based on the original imageFigure 4.6. Relationship between the intracranial volume available for pressure compensation, intracranial pressure, and the size of an expanding mass. 1. With little compensatory volume available, even a small mass markedly raises intracranial pressure. 2. Normal intracranial volume available for pressure compensation. 3. With a large compensatory volume available, a mass can become very large before raising intracranial pressure.
The compensatory mechanisms for intracranial pressure do not depend on the type of lesion. Tumors, intracerebral hemorrhage, brain abscesses, cysts, and other lesions provoke the same compensatory response. The speed of compensation, however, depends on the location, size, and rate of development of the mass; the presence of cerebral atrophy; the capacity of the CSF spaces to expand; the expansibility of the skull; and the edema surrounding the tumor.
Tumors within or near the ventricular system can obstruct CSF pathways early, causing obstructive hydrocephalus and generalized increased ICP. Compensatory mechanisms are consequently exhausted rapidly. Tumors in the middle cranial fossa near the tentorial edge readily cause herniation of the medial temporal lobe through their local pressure. This is another cause of obstruction of cisternal CSF flow and rapid elevation of intracranial pressure.
The rate at which a mass develops is an important factor. When a mass develops rapidly, the brain cannot adapt in time and the compensatory mechanisms for intracranial pressure are quickly exhausted. Brain herniation therefore tends to occur early. Malignant tumors, such as metastatic tumors, glioblastoma multiforme, and sarcoma, grow rapidly and are accompanied by considerable cerebral edema. Patients thus show signs of raised intracranial pressure early in the disease. In contrast, benign tumors such as meningiomas grow slowly, giving the brain time to adapt through the mechanisms described above. A conspicuous change is localized atrophy through loss of water at the site compressed by the tumor. This atrophy results from impaired blood flow caused by compression of the vessels.(1) Such tumors can therefore become large before producing symptoms and signs of raised intracranial pressure.
In patients with cerebral atrophy, such as elderly people, there is less brain tissue and the ventricles and subarachnoid spaces are enlarged. The greater available intracranial space allows tumors to become very large. Conversely, younger people have very narrow ventricles and subarachnoid spaces and often develop symptoms of raised intracranial pressure sooner.
Expansion of the skull is another compensatory mechanism. It occurs in young children whose cranial sutures have not yet fused firmly. This change accompanies a gradual rise in pressure, but does not occur when intracranial pressure rises abruptly.
Original pages 192–197
Anatomy
Before studying the symptoms and signs of intracranial pressure, it is helpful to understand the anatomy of the cranial cavity and the pathophysiology of an expanding intracranial mass. This makes the resulting symptoms and signs easier to understand.
As already discussed, the skull is rigid and cannot expand, so its capacity changes very little. The exception is in children whose sutures have not yet fused, allowing the skull to expand. The cranial cavity is divided into compartments by the falx cerebri and tentorium cerebelli. The tentorium is a fold of dura attached to the anterior and posterior clinoid processes, petrous ridge, and occipital bone. It curves inward to join its counterpart on the opposite side, forming a tent that separates the intracranial cavity into the supratentorial compartment and the infratentorial compartment, or posterior fossa. The edges of the two sides of the tentorium form an opening for the brain stem, blood vessels, cranial nerves, and CSF, called the tentorial notch or tentorial opening (Figures 4.7, 4.8, and 4.9). The infratentorial compartment contains the cerebellum, brain stem, cranial nerves, and blood vessels. The brain stem leaves the cranial cavity through the foramen magnum to continue as the spinal cord. The cerebellar tonsils lie at the margins of the foramen magnum (Figure 4.10). These important structures may be displaced downward when posterior fossa pressure rises, compressing the medulla and posterior inferior cerebellar artery and causing immediate respiratory arrest and unconsciousness.
Color added · Anatomical details based on the original imageFigure 4.7. Division of the cranial cavity into compartments by the tentorium cerebelli and falx cerebri.Color added · Anatomical details based on the original imageFigure 4.8. Superior view of the skull base showing the tentorial notch (tentorial incisura), formed by the edges of the tentorium cerebelli. It provides passage for the brain stem, blood vessels, cranial nerves, and CSF.Figure 4.9. Posterior view of the tentorial notch, showing the brain stem passing into the posterior fossa. (From Rohen, J.W., and Yokochi, C., Color Atlas of Anatomy, Igaku-Shoin Medical Publisher, 1988.)Figure 4.10. The cerebellar tonsil (arrow), whose lower margin normally lies at the level of the edge of the foramen magnum (arrowhead).
Within the supratentorial compartment, the falx cerebri is a dural fold in the sagittal plane. It attaches anteriorly to the crista galli, then curves backward to meet both sides of the tentorium in the midline. It divides the supratentorial compartment into right and left halves, each containing a cerebral hemisphere. An important feature of the falx is its narrow anterior portion, which leaves the cingulate gyrus on the medial surface of the frontal lobe uncovered (Figures 4.7 and 4.11). A supratentorial expanding lesion can therefore displace the cingulate gyrus beneath the free edge of the falx to the opposite side.
Color added · Anatomical details based on the original imageFigure 4.11. Midline section showing the narrow anterior portion of the falx cerebri. The cingulate gyrus and anterior cerebral artery are not covered by the falx.
The tentorial notch (Figure 4.8) allows passage of the brain stem at the midbrain level. The midbrain lies close to the edge of the tentorium. The oculomotor nerve (third cranial nerve) emerges from the midbrain in the interpeduncular fossa and courses forward alongside the posterior communicating artery into the cavernous sinus. As it passes forward, the nerve also lies close to the tentorial edge. It is therefore an important cranial nerve for recognizing transtentorial herniation, as discussed below. The posterior surface of the midbrain is farther from the edge of the tentorial notch. Here the cerebellar vermis and superior surface of the cerebellar hemisphere lie close to the tentorial edge. These are other important parts of the brain that can be displaced upward from the infratentorial compartment through the tentorial notch when posterior fossa pressure rises.
In the posterior fossa, the vertebrobasilar arteries supply the brain stem and may be affected during brain herniation. At the junction of the pons and midbrain, the basilar artery gives rise to important branches: the superior cerebellar and posterior cerebral arteries. The superior cerebellar artery remains infratentorial and supplies the superior surface of the cerebellar hemisphere and the vermis. The initial segment of the posterior cerebral artery, after leaving the basilar artery, is also infratentorial. It courses along the midbrain to the edge of the tentorial notch, crosses the tentorial edge into the supratentorial compartment, and supplies the temporal and occipital lobes. The vertebrobasilar vessels supplying the brain stem give rise to two groups of branches: paramedial and circumferential arteries (Figure 4.12). The paramedial arteries enter the brain stem on either side of the midline and pass toward its dorsal surface, supplying the gray matter beneath the floor of the fourth ventricle. The circumferential arteries course around the outer surface of the brain stem and send branches inward from its periphery. Small branches of the anterior inferior cerebellar artery supply the lower pons. These vessels are important in the development of secondary brain stem hemorrhage, as discussed below.
The temporal lobe is important because its medial portions—the uncus and parahippocampal gyrus—lie close to the edge of the tentorial notch. These structures can be displaced downward and compress the brain stem when supratentorial pressure rises.
Figure 4.12. Paramedial and circumferential arterial branches supplying the brain stem, which are important in the development of secondary brain stem hemorrhage.
The ventricular system is another important structure. It includes the right and left lateral ventricles, from which CSF flows through the two foramina of Monro into the third ventricle. It then passes through the aqueduct of Sylvius, a narrow channel in the midbrain tegmentum, into the fourth ventricle. The fourth ventricle opens into the cerebral cisterns through the foramina of Magendie and Luschka. The choroid plexus within the ventricles continuously produces CSF at approximately 20 cc per hour. Thus, if a tumor and brain herniation—for example, tonsillar herniation—obstruct the fourth ventricular outlets, or if transtentorial herniation compresses the aqueduct of Sylvius, CSF cannot leave the ventricles. Intracranial pressure then rises rapidly beyond the pressure caused by the tumor itself. The physician must promptly restore CSF outflow from the ventricles.
Original pages 197–205
Pathophysiological Changes
A brain tumor or another expanding intracranial mass can produce several pathophysiological changes in the brain. The important changes are:
Loss of function in the part of the brain compressed or destroyed by the tumor, producing symptoms and signs of dysfunction of that region.
Increased intracranial pressure (increased ICP).
Brain displacement and herniations.
The lesion may produce only one of these three changes, or all three may develop together as a continuous process. This depends on the type, location, and rate of expansion of the lesion.
This chapter discusses in detail only raised intracranial pressure, brain displacement, and herniation.
Chart 4.1. Changes in the brain caused by a brain tumor or an expanding intracranial mass.
Increased intracranial pressure (increased ICP)
In general, an expanding mass alone does not greatly alter intracranial pressure. Raised pressure usually results from the combined effects of expansion of the mass and secondary changes: brain edema, venous congestion, disturbed intracranial blood circulation, and obstruction of CSF pathways (Chart 4.1).
Chart 4.1 shows that raised intracranial pressure results from the following:
1) Tumor expansion accompanied by brain edema. Malignant tumors are an example. Edema develops through two mechanisms: the primary toxic effect of the malignant tissue on the brain,(2) and abnormal blood circulation around the mass.
2) Abnormal intracranial blood circulation. A tumor can compress local veins and capillaries, impairing circulation and causing congestion and cerebral edema. The author has often observed that benign tumors, such as parasagittal meningiomas, cause considerable surrounding edema that is clearly visible on CT. At operation, the capillaries compressed by the tumor show slowed circulation and local hypoxia, making the cortex at the tumor site appear pale. Thus, the primary toxic effects of malignant tumors, venous congestion, and localized hypoxia all affect the blood–brain barrier and contribute to cerebral edema.
3) CSF obstruction. Obstruction can occur anywhere along the CSF pathways and causes obstructive hydrocephalus. The patient's condition may deteriorate to unconsciousness within a short time. Obstruction may be caused by a small tumor within the ventricular system or by an extraventricular tumor enlarging and compressing a narrow CSF passage, such as the aqueduct of Sylvius or the ventricular foramina. Tumors distant from the ventricles can also obstruct CSF flow through cerebral displacement or herniation. For example, a supratentorial tumor can cause herniation of the uncus and parahippocampal gyrus, compressing the midbrain and its narrow aqueduct of Sylvius, or tonsillar herniation can obstruct the fourth ventricular outlets. Rising intracranial pressure increases brain herniation, which further obstructs CSF flow. This continuing cycle progressively worsens the patient's condition and ultimately causes death.
Unless these three factors are corrected promptly, intracranial pressure continues to rise over time. The most important treatment is directed at the cause. A tumor must be removed to correct venous congestion, cerebral edema, CSF obstruction, and raised intracranial pressure. In some patients, however, the cause cannot be treated and CSF obstruction persists. CSF must then be drained to lower intracranial pressure. If pressure is allowed to rise progressively, two important changes occur: reduced cerebral blood flow and brain herniation compressing the brain stem. Loss of brain stem function ultimately causes death.
Effects of increased ICP on cerebral blood flow (CBF)
Changes in ICP affect CBF because increased ICP invariably affects systemic arterial pressure (SAP) and cerebral perfusion pressure (CPP).(4) CPP is related to carotid arterial pressure, jugular vein pressure, and cerebrovascular resistance by the following equation:
Normally, cerebral venous pressure is approximately equal to intracranial pressure and rises or falls with ICP. As ICP increases, cerebrovascular resistance decreases to maintain normal CBF. At very high ICP, the cerebral veins and sinuses collapse, increasing cerebrovascular resistance and eventually reducing CBF.(6) Zwetnow(5) found that with progressive elevation of ICP, CBF remained normal until CPP fell to 40 mmHg or below, when CBF decreased appreciably. Maintenance of normal CBF indicates cerebral vascular autoregulation adapting to blood pressure changes. Miller(4) likewise concluded that during increased ICP, CBF remains normal as long as the cerebral vessels retain their autoregulatory response to arterial pressure. Once autoregulation is lost through hypoxia or any other cause, increasing ICP immediately reduces CBF.(7)
Clinically, the effect of increased ICP on CBF is clearly demonstrated by cerebral angiography in patients with expanding intracranial lesions and very high ICP. Contrast injected into the internal carotid artery cannot enter the cranial cavity. This indicates that ICP approaches or equals SAP, leaving insufficient pressure to drive the contrast through the cerebrovascular resistance into the brain. This is called the non-filling phenomenon. All such patients subsequently die.
AUTOREGULATION. Autoregulation is related to ICP, SAP, and CBF. CBF delivers O₂ and glucose to the brain, continuously maintaining normal metabolism. Cerebral vascular autoregulation maintains normal CBF by adjusting vessel caliber to changes in blood pressure, ICP, and blood gases. Vasodilatation and vasoconstriction keep CBF constant. When SAP or CPP falls, cerebral vessels dilate to maintain CBF; when SAP rises, they constrict to achieve the same effect. This autoregulatory mechanism depends on the arterial smooth muscle reflex. Adjustment of the arteries to changes in CPP to maintain normal CBF is called “pressure autoregulation.” Its range, from maximal dilatation to maximal constriction, corresponds to a mean SAP of 50–160 Torr.(31) Thus, vessels progressively dilate as SAP and CPP fall, maintaining normal CBF until SAP reaches 50 Torr, when dilatation is maximal. Below 50 Torr, CBF falls with blood pressure, outside autoregulatory control. As blood pressure rises, arteries constrict, reaching maximal constriction at SAP 160 Torr. Above this pressure, the force of the blood pressure dilates the vessels and increases CBF. At this stage the blood–brain barrier is disrupted, water enters the brain tissue, cerebral edema develops, and ICP rises further.
In addition to responding to SAP, cerebral vessels adapt to tissue metabolism, a process called “metabolic autoregulation.” The demand for O₂ and glucose for brain metabolism is normally closely related to CBF. During a seizure, for example, metabolism increases in the affected brain region and vasodilatation increases its blood flow.(3) When metabolism decreases, as during hypothermia, CBF also decreases.(8) Lactic acid or H⁺ generated by metabolism continuously links CBF to metabolism. Hypoxia or increased metabolism raises extracellular lactic acid (H⁺), causing vasodilatation and increased cerebral blood flow. As long as the increased CBF compensates for the fall in blood O₂ and meets the brain's requirements, brain metabolism remains normal. When metabolism returns to its normal level, H⁺ is removed and vessels constrict back to normal.
Hypoxia and hypercarbia greatly influence cerebral vessels, particularly hypercarbia. When arterial PaO₂ falls to approximately 20 mmHg, maximal vasodilatation is stimulated. A further fall in O₂ causes anaerobic glycolysis and reduced oxidative phosphorylation,(9) changes consistently seen in hypoxic metabolism. The mechanism by which hypoxia dilates cerebral vessels is not clearly understood. It is generally considered to be chemical regulation: hypoxia increases lactic acid or H⁺, stimulating chemoreceptors in the aorta and carotid sinus.
Hypercarbia, or elevated arterial PaCO₂, is the most important autoregulatory stimulus for changes in cerebral vessels. High PaCO₂ causes dilatation, whereas low PaCO₂ causes constriction. Vasodilatation raises ICP. Therefore, in patients with brain tumors or other expanding masses who have impaired consciousness, inadequate breathing, or airway obstruction, the airway must promptly be cleared and ventilation supported to relieve hypercarbia. This is one way to lower ICP.
Vasomotor response to increased ICP
Cushing described the vasomotor response to increased ICP as a rise in SAP accompanied by bradycardia. The pressure response results from sympathetic stimulation transmitted through sympathetic outflow. It can be abolished by sectioning the cervical cord or a sympathetic ganglion. Bradycardia results from stimulation of a center in the floor of the fourth ventricle, with impulses transmitted through the vagus nerve; vagotomy abolishes it. The Cushing response increases CBF or maintains normal CBF, depending on how far the rise in SAP exceeds the rise in ICP.
Cerebrovascular dysfunction caused by increased ICP
With intact autoregulation, cerebral vessels dilate when SAP falls and constrict when SAP rises, maintaining normal CBF. They also dilate and constrict in response to changes in PaCO₂. These responses may be altered or lost because of a brain tumor, ischemia, hypoxia, or brain injury. High ICP with severe brain compression abolishes the cerebral vascular vasomotor response. Progressive loss of this response is life-threatening. As ICP rises, CPP falls. Initially, vasodilatation and a rise in SAP maintain normal CBF. Continued elevation of ICP eventually abolishes the mechanisms regulating CBF and causes cerebral ischemia. At this stage, administering CO₂ cannot increase CBF or ICP because the cerebral vessels are already maximally dilated. Similarly, administering O₂ does not cause vasoconstriction. Langfitt(3) called this phenomenon “cerebral vasomotor paralysis.” During this state, if SAP rises through a vasomotor response, ICP rises with it without an increase in CPP or CBF.(3)
Cerebral vasomotor paralysis generally involves the cerebral vessels diffusely. However, by measuring regional CBF at several sites, Langfitt found that localized vasomotor paralysis can occur, particularly near a tumor, and may produce “cerebral steal.” When CO₂ is administered, CBF increases through vasodilatation in normal brain tissue, but in areas with impaired autoregulation it remains unchanged or may even decrease. Conversely, hyperventilation reduces CBF in normal brain through vasoconstriction while increasing flow to the abnormal region.
Effects of increased ICP on other systems
As discussed above, changes in PCO₂ and PO₂ affect cerebral vessels, CBF, and ICP. Increased ICP can in turn affect respiration and blood gases. Respiratory changes may result from brain displacement, increased ICP, or both. Whatever the initial cause, abnormal blood gases initiate further increases in ICP and brain displacement. They must therefore be corrected promptly.
Many patients with expanding masses have relatively low O₂ levels. Two mechanisms explain this. First, increased ICP and brain shift produce pulmonary ventilation–perfusion mismatch and low PO₂. Pulmonary vasoconstriction during the Cushing response lowers blood O₂. Second, increased ICP and brain shift affect the respiratory center in the medulla, depressing respiration and causing low PO₂ and high PCO₂.
Some patients hyperventilate during increased ICP, usually before breathing slows or stops. Hyperpnea at this stage may represent the body's attempt to restore a low PO₂ to normal. In some patients, however, hyperventilation is caused by brain stem pathology.
PULMONARY EDEMA CAUSED BY INCREASED ICP. Pulmonary edema in patients with brain injury or brain tumors is a grave condition. Without timely treatment, all patients die. These patients have no other cause of pulmonary edema, such as lung disease, heart disease, or excessive intravenous fluid administration. They are unconscious and breathless, with pink frothy fluid continuously issuing from the mouth, nose, or endotracheal tube. These manifestations result from markedly increased ICP. The author encountered a patient with a brain tumor and these findings. After the tumor was removed, the pulmonary edema resolved immediately and the patient recovered normally.
Two theories explain pulmonary edema associated with increased ICP:(18)
Theory 1: Increased ICP stimulates greater sympathetic outflow to the pulmonary vessels, causing pulmonary vasoconstriction and edema.
Theory 2: Increased hydrostatic pressure in the pulmonary microvasculature causes fluid to transude from the capillary bed into the alveoli.
Original pages 206–214
Symptoms and Signs of Raised Intracranial Pressure
Every physician should know the symptoms and signs of raised intracranial pressure and its life-threatening consequences, and should be able to diagnose it early enough to provide treatment before the patient dies.
The important general symptoms and signs of raised intracranial pressure are:
Headache
Vomiting
Blurred vision or papilledema (choked disc)
Personality change
Decreased consciousness
Double vision (diplopia)
Head enlargement
Cushing’s reflex
Headache is common in raised intracranial pressure and often brings the patient to a physician. It results from compression or traction on intracranial pain-sensitive structures: the middle meningeal artery and its branches, the large arteries at the base of the brain, the dura mater at the skull base, and the venous sinuses.(10) It usually occurs in the early morning and may awaken the patient. It improves after vomiting. In patients with expanding intracranial masses, reduced ventilation during sleep causes CO₂ retention and vasodilatation, producing brain swelling.(11) Relief of headache after vomiting is explained by subsequent hyperventilation, which lowers ICP.(12) The pain is usually throbbing and progressively worsens until, at very high intracranial pressure, it becomes continuous and unresponsive to analgesics. This pattern is important in distinguishing it from headaches of other causes. Certain positions or activities, such as squatting or straining at stool, can aggravate the pain. For this reason, patients with brain tumors often also have constipation.
Headache associated with raised intracranial pressure does not localize the lesion. Severe frontal headache, for example, does not necessarily indicate a frontal lobe tumor. However, a tumor situated so that it compresses or pulls on pain-sensitive structures may initially cause localized pain before generalized headache develops. A meningioma of the medial lesser wing of the sphenoid may first cause pain around the eye and forehead through traction on V₁ and V₂ of the trigeminal nerve. Posterior fossa tumors, sometimes accompanied by tonsillar herniation, often cause occipital headache and neck tightness through irritation of cranial nerves IX, X, and XI and the dura supplied by them, as well as the upper spinal nerves.
Some patients have such severe headache that they cry out, thrash about, become noisy or agitated, and answer questions inappropriately. These may be manifestations of raised intracranial pressure. If the physician fails to consider this possibility, restrains the patient's limbs, and gives sedating medication, diagnosis and treatment may be delayed until it is too late, with subsequent death.
Vomiting is another symptom accompanying headache, usually appearing later when intracranial pressure is very high. It is projectile and unrelated to meals or nausea. It is more common in children because childhood brain tumors often lie in the posterior fossa and directly stimulate the vomiting center in the medulla. Tumors in or near the fourth ventricle cause vomiting more frequently. Children with brain tumors may therefore be thin, malnourished, and weak, sometimes with head enlargement. Vomiting is less common in adults. When a patient presents with vomiting and raised intracranial pressure is suspected, the cause should be investigated and treated promptly, since vomiting usually indicates that pressure is already very high. Vomiting itself also raises intracranial pressure and can readily precipitate brain herniation when the patient is close to decompensation.
Blurred vision results from papilledema, or choked disc. This is the most important sign and allows reliable diagnosis of raised intracranial pressure. Every physician should learn to recognize papilledema on funduscopic examination so that patients receive prompt diagnosis and treatment.
Papilledema results from congestion of the central retinal vein within the optic nerve. Raised intracranial pressure increases CSF pressure in the arachnoid sheath surrounding the optic nerve, causing the optic disc to swell.
Figure 4.13. Papilledema in a patient with raised intracranial pressure. Note the flame-shaped hemorrhages at the optic disc margin.
Examination of the optic disc with an ophthalmoscope reveals the following features of papilledema(15) (Figure 4.13):
Increased optic disc diameter due to swelling of the optic nerve head.
Indistinct disc margins and loss of the physiological cup due to swelling.
Mushroom-like protrusion of the swollen optic nerve head into the vitreous.
Increasing redness of the optic disc due to venous congestion, an early sign of raised intracranial pressure.
Congested, tortuous veins at the optic disc, with arteries remaining normal in caliber, increasing the vein-to-artery ratio.
Deviation of vessels at the optic disc from their usual course because of displacement by swelling.
Flame-shaped hemorrhages at the disc margin or within the disc, usually surrounding it close to its edge. Hemorrhage elsewhere is attributed to another cause, such as retinal vein thrombosis, rather than raised intracranial pressure.
Grayish-white exudate on the surface and margins of the optic disc.
The earliest optic disc signs of raised intracranial pressure are venous congestion, disappearance of central retinal venous pulsation, and increasing redness of the disc. The other changes indicate more advanced papilledema.
Papilledema may be unilateral or bilateral, or may be absent despite raised intracranial pressure. This may reflect anatomical variation in the extension of the subarachnoid space along the optic nerve. If this space extends a shorter distance than normal, the central retinal vein lies outside it and is not subjected to its pressure, so papilledema does not develop. In some cases, such as a meningioma near the medial lesser wing of the sphenoid, the optic nerve and its subarachnoid space are compressed without obstruction of the central retinal vein. Primary optic atrophy occurs instead of papilledema. If the large mass raises intracranial pressure, papilledema may develop on the opposite side (Foster–Kennedy syndrome). With a subfrontal tumor, frontal lobe tissue may likewise be pushed against the optic nerve and subarachnoid space, preventing papilledema. Thus, absence of papilledema does not exclude a brain tumor. When a tumor is suspected, other findings must help establish the diagnosis. The presence of papilledema is not a localizing sign.
Papilledema takes time to develop and is therefore absent when intracranial pressure rises abruptly, as with an epidural hematoma. Once papilledema has developed, failure to treat the cause of raised pressure promptly can eventually result in blindness from secondary optic atrophy (Figure 4.14). At that stage, blindness will not improve regardless of how quickly the cause is removed. Prompt treatment upon detection of papilledema is therefore essential. In general, visual acuity does not deteriorate rapidly as it does in papillitis; it declines gradually over months or years, depending on tumor type and location. Vision is usually lost late in the disease. Infratentorial tumors and tumors within or near the ventricles produce papilledema sooner than supratentorial tumors, because they commonly obstruct CSF pathways and rapidly raise intracranial pressure. Rapidly growing tumors, such as malignant gliomas and metastatic brain tumors, also cause early papilledema. Slowly growing tumors such as meningiomas are less often associated with it.
Figure 4.14. Secondary optic atrophy: the optic disc is pale white, with distinct margins and narrowed vessels.
Personality and behavior. Changes in personality and habits are common accompanying manifestations. Patients are often fatigued, lack enthusiasm for work, become slower and less active, lose interest in their surroundings, and tend to sleep. Schoolchildren show progressively declining academic performance. If intracranial pressure becomes sufficiently high and remains elevated long enough, memory impairment and dementia may develop. However, these manifestations may also be localizing symptoms of tumors in particular brain regions.
Decreased consciousness is the most important manifestation. It indicates very high intracranial pressure and progression toward the terminal stage. Pressure must be restored to normal as quickly as possible; otherwise, the patient becomes unconscious and dies. Unconsciousness results from two factors: reduced cerebral blood flow and brain herniation causing cessation of brain stem function. As pressure rises gradually, the patient becomes progressively more drowsy. When recording the level of consciousness, physicians should describe what the patient can do—for example, speak, move, and understand commands—rather than use terms such as stupor, semicoma, or coma. Such terms may be interpreted differently by different caregivers and obscure the actual changes.
Changes in consciousness depend on the rate of development and location of the mass. A brain tumor growing slowly over months or years may cause drowsiness for several days before unconsciousness develops. With a rapidly developing mass, the patient may progress from full alertness with headache to drowsiness and unconsciousness within minutes or hours. An epidural hematoma is a clear example.
Double vision results from dysfunction of the cranial nerves supplying the extraocular muscles. The nerves commonly affected by raised intracranial pressure are the sixth (abducens) and third (oculomotor) nerves. The sixth nerve is most commonly affected before uncal herniation occurs. Once uncal herniation develops, the third nerve loses function in every case.
Figure 4.15. Internal squint due to abducens nerve dysfunction in a patient with raised intracranial pressure caused by a brain tumor.
The abducens nerve supplies the lateral rectus muscle, which abducts the eye. Loss of nerve function prevents outward eye movement and causes an internal squint (Figure 4.15). The patient experiences horizontal diplopia and walks with the face turned toward the affected side to avoid double vision. Sixth nerve palsy is not a localizing tumor sign and does not help identify the tumor's location. It is simply a general manifestation of raised intracranial pressure.
Sixth nerve palsy occurs because this long nerve runs from the lower border of the pons along the skull base, crosses the petrous ridge, and enters the cavernous sinus. When intracranial pressure rises and the brain stem moves downward, the sixth nerve is pulled against the petrous ridge and loses function.
Head enlargement occurs in young children whose skull plates have not yet fused. Raised intracranial pressure, whether from a brain tumor or another cause, enlarges the head. The sutures may separate and become palpable, especially at the coronal suture and anterior fontanelle. Percussion produces a “cracked pot” sound. Congested scalp veins become prominent. Both eyes may look downward (the sunset sign) because of pressure on the roofs of the orbits. Head enlargement is not seen in older children or adults.
CUSHING’S REFLEX. When intracranial pressure becomes very high, Cushing's reflex raises blood pressure and slows the pulse, increasing cerebral blood flow to compensate for the reduction caused by elevated ICP. These changes in blood pressure and pulse rate are important signs that intracranial pressure is rising. A progressive rise in blood pressure and slowing of the pulse, accompanied by a change in consciousness, make raised intracranial pressure particularly certain.
Original pages 214–217
BRAIN DISPLACEMENT AND HERNIATION
As a tumor or expanding mass enlarges, the surrounding brain tissue is displaced to accommodate its growth. Because the cranial cavity is divided into compartments by the falx cerebri and tentorium cerebelli, the pattern of displacement varies with the location of the tumor.
A frontal lobe tumor readily displaces frontal brain tissue beneath the falx cerebri to the opposite side. The falx is narrow anteriorly and covers or separates relatively little of the medial frontal surface. In the parietal region it is broad and covers the medial hemispheric surface, limiting displacement across the midline. Cerebral angiography demonstrates this displacement as a “proximal shift” of the anterior cerebral artery on the anteroposterior view. The falx cerebri itself may also be displaced to the opposite side. Because the frontal lobe lies close to the central axis of the brain, a frontal mass can also cause downward displacement of the brain stem. In addition, the posterior part of the frontal base may be pushed into the middle cranial fossa and compressed by the lesser wing of the sphenoid, leaving an indentation on the frontal base (Figure 4.16).
A parietal lobe tumor produces less displacement beneath the falx because the falx is very broad here and covers almost the entire medial parietal surface. Its lower border lies close to the corpus callosum and is firmly attached to the tentorium on both sides. Increasing mass pressure must first compress the corpus callosum before the cingulate gyrus can move to the opposite side. As the mass enlarges, part of the cingulate gyrus passes beneath the falx, producing a “distal shift” of the anterior cerebral artery on the anteroposterior carotid angiogram. Further enlargement pushes the frontal lobe so that its medial surface also passes beneath the falx, producing a “square shift” on this view. The dorsal surface of the third ventricle is compressed by the tissue displaced across the midline.
Figure 4.16. The posterior part of the frontal lobe base is compressed by the edge of the lesser wing of the sphenoid (arrows).
A temporal lobe tumor displaces adjacent brain upward, forward, and downward. The Sylvian fissure and its vessels are elevated, while the brain stem and third ventricle are pushed to the opposite side. Temporal lobe tumors readily cause transtentorial herniation because the uncus and parahippocampal gyrus lie close to the tentorial edge.
An occipital lobe tumor lies in a region bounded by the falx and tentorium cerebelli. Increasing pressure displaces brain tissue forward toward the parietal and temporal lobes.
A posterior fossa tumor displaces the brain in two directions: upward through the tentorial notch and downward through the foramen magnum, as described below.
Regardless of its location, an enlarging tumor or other expanding mass transmits pressure to other parts of the brain until the compensatory mechanisms are exhausted. Brain tissue is then shifted or displaced into compartments with lower pressure. This produces cerebral or brain herniation, which compresses the brain stem and can cause unconsciousness and death.
Supratentorial tumors or other expanding masses can cause three forms of brain herniation:
Cingulate or subfalcine herniation
Central transtentorial herniation
Uncal and/or parahippocampal herniation
Infratentorial tumors or other expanding masses can cause two forms of brain herniation:
Tonsillar herniation
Upward transtentorial herniation
These forms of brain herniation represent a continuing process as long as ICP continues to rise. Even when the original cause of increased ICP is supratentorial, pressure eventually spreads to the posterior fossa, producing all forms of herniation and ultimately death.
Symptoms and Signs of Brain Herniation
The manifestations of brain herniation may be classified by the site involved, as follows.
1. Manifestations of cingulate or subfalcine herniation
The cingulate gyrus herniates beneath the falx across the midline from the higher-pressure side to the lower-pressure side. This depresses the roof of the ipsilateral lateral ventricle and displaces the pericallosal arteries to the opposite side. Cerebral angiography demonstrates shifting of the anterior cerebral arteries across the midline. As the cingulate gyrus and anterior cerebral arteries pass beneath the falx, the falcine edge compresses branches of these arteries (Figure 4.17). Hemorrhagic pressure necrosis may develop in the cingulate cortex, or ischemia or infarction may occur on the medial frontal and parietal surfaces supplied by the anterior cerebral arteries. This causes weakness of the leg opposite the original lesion. The infarcted brain swells, further increasing intracranial pressure.
Figure 4.17. The right cingulate gyrus has herniated beneath the falx to the left. Note the indentation of the cingulate gyrus and branches of the anterior cerebral artery (arrow).
Original pages 217–221
2. Symptoms and Signs of Transtentorial Herniation
2.1 Central transtentorial or diencephalic herniation(13)
A supratentorial tumor displaces the diencephalon downward through the tentorial notch, in turn pushing on the midbrain. This often accompanies uncal herniation (Figure 4.18). Perforating arteries supplying the diencephalon and brain stem are displaced by these forces (Figure 4.19), causing ischemia or hemorrhage within the diencephalon and upper midbrain.
Figure 4.18. A. Normal midbrain position: its anterior border lies at the level of a line drawn between the optic chiasm and the posterior border of the splenium of the corpus callosum. B. Multiple supratentorial tumors displace the diencephalon and brain stem downward. (From Plum F. and Posner J. B., The Diagnosis of Stupor and Coma.)Color added · Anatomical details based on the original illustrationFigure 4.19. A brain tumor causes central displacement and central transtentorial herniation. The perforating arteries supplying the diencephalon (short arrows) are displaced and stretched taut, resulting in ischemia.
Early manifestations begin with changes in consciousness and progressively increasing drowsiness. Breathing often includes sighing, yawning, or occasional pauses; some patients develop Cheyne–Stokes respiration. The pupils are small but still constrict well to light. The small pupils at this stage are not clearly explained but may result from hypothalamic sympathetic dysfunction. Opening both eyes reveals conjugate or divergent roving movements—wandering, inconsistently directed movements resembling those of a person who is half asleep, indicating preserved brain stem function. The doll’s eye maneuver and caloric testing remain normal. Motor examination begins to show bilateral corticospinal tract signs. Patients whose hemispheric tumor has already caused contralateral hemiparesis develop further weakness.
If the supratentorial tumor continues to enlarge or intracranial pressure continues to rise, the diencephalon and midbrain are compressed more severely.
In the later phase of central transtentorial herniation, the patient therefore becomes unconscious and develops Cheyne–Stokes respiration. The pupils remain small but constrict less to light. Responses to the doll’s eye maneuver and caloric testing are unchanged from the early stage. The patient may lie motionless without stimulation. Strong pressure at the medial eyebrow or over the sternum, however, produces rigid extension of the legs and flexion of the arms, known as “decorticate rigidity” (Figure 4.20). If hemiparesis or hemiplegia was already present, decorticate rigidity always appears first on that side and may later become bilateral. In some patients with a hemispheric lesion and subsequent herniation, stimulation produces rigidity in the previously hemiplegic limbs and decorticate rigidity in the limbs on the same side as the lesion. This difference cannot yet be explained physiologically.(13)
Figure 4.20. Decorticate rigidity in an unconscious patient. The clenched hands rest on the chest, the wrists and elbows are flexed, and both legs are rigidly extended.
Some patients also develop hypersecretion from the tracheobronchial tree and increased gastric secretion. Secretions may be so copious that froth appears at the nose and mouth, or through the tracheostomy tube, as in pulmonary congestion. Hyperthermia may also occur. These phenomena may reflect hypothalamic disturbance.
Manifestations in the “diencephalic stage” are critically important: they warn that a reversible condition will soon become irreversible. If treatment is not provided promptly and herniation is allowed to destroy the midbrain, recovery becomes difficult or impossible, however rapidly the mass is subsequently removed.
When intracranial pressure continues to rise after the compensatory mechanisms have been exhausted, pressure from a supratentorial expanding mass causes uncal herniation into the lower-pressure posterior fossa. The uncus, the medial portion of the anterior temporal lobe resting on the tentorial edge, is displaced medially and downward through the tentorial notch. The parahippocampal gyrus may follow it (Figures 4.21 and 4.22). The relative extent of uncal and parahippocampal displacement varies with the location of the mass. An anterior mass, such as one in the frontal lobe or anterior temporal lobe, produces more prominent uncal herniation. A posterior temporal or occipital mass produces greater parahippocampal herniation.
Figure 4.21. Left uncal and parahippocampal transtentorial herniation, with indentation by the tentorial edge (arrows). Lateral compression lengthens the midbrain anteroposteriorly and occludes the aqueduct of Sylvius. The left third cranial nerve is compressed by the uncus.Figure 4.22. Uncal transtentorial herniation viewed from above with the frontal lobe retracted upward. The herniated uncus compresses the third nerve (arrow), and the tentorial edge has indented the uncus (arrowhead).
The manifestations of uncal and parahippocampal herniation are as follows.
oculomotor nerve palsy The oculomotor nerve is compressed during uncal herniation. Early on, before the uncus has fully descended through the tentorial notch, the pupil on the side of the expanding mass begins to constrict but remains reactive to light. The opposite pupil remains normal in size and reactivity. A physician may therefore mistakenly identify the side with the larger pupil as abnormal and perform cerebral angiography on that normal side, although the lesion lies on the side with the smaller pupil. Initial constriction before dilatation is explained by stimulation of the parasympathetic fibers on the surface of the oculomotor nerve during early herniation. This stage is important because full uncal herniation will soon follow, compressing the nerve until it loses function and causing oculomotor palsy. The ipsilateral pupil then enlarges and becomes less reactive, eventually becoming fully dilated and fixed. The pupils are unequal, a condition called anisocoria (Figure 4.23A). The patient becomes unconscious as compression disables the brain stem reticular activating system. External oculomotor ophthalmoplegia is also found: the eye does not move, and the doll’s eye response is lost on the side of the dilated pupil. If the cause is not removed, contralateral herniation develops, leaving both pupils dilated and unreactive (Figure 4.23B). Most patients die at this stage.
Thus, the expanding intracranial mass lies on the side of the dilated, unreactive pupil. If carotid angiography is necessary, it must be performed on that side to demonstrate the lesion.
Unconsciousness and decerebrate rigidity In addition to a dilated, unreactive pupil, uncal herniation produces manifestations of midbrain compression and ischemia. The patient becomes unconscious and develops decerebrate rigidity: both arms and legs are rigidly extended, the arms are internally rotated, the hands are clenched, and the wrists are flexed (Figure 4.24). Midbrain dysfunction also abolishes the oculocephalic reflex.
Figure 4.23. A. Unequal pupils (anisocoria), with the left pupil larger than the right. B. Both pupils are dilated and unreactive to light. Markedly raised intracranial pressure has caused bilateral uncal herniation, ultimately resulting in death.Figure 4.24. Decerebrate rigidity in an unconscious patient. Both arms and legs are rigidly extended, the arms internally rotated, the hands clenched, and the wrists flexed.Color added · Anatomical details based on the original illustrationFigure 4.25. Kernohan’s phenomenon. The uncus herniates through the tentorial notch and displaces the midbrain, pressing the opposite cerebral peduncle against the tentorial edge.
hemiparesis, and Kernohan’s phenomenon Compression of the lateral midbrain by the uncus and parahippocampal gyrus displaces it to the opposite side. The opposite cerebral peduncle is pressed against the tentorial edge, causing ischemia and necrosis. Hemiplegia may therefore occur on the same side as the expanding mass and the dilated pupil. This is called Kernohan’s phenomenon (Figure 4.25), reported in fewer than 10% of cases by Finney and Walker(14) Hemiplegia may be either ipsilateral or contralateral to the lesion. Contralateral hemiplegia, however, usually reflects a hemispheric lesion rather than midbrain compression.
Manifestations of secondary brain stem hemorrhage Lateral compression reduces the transverse diameter of the midbrain and lengthens its anteroposterior diameter. Together with downward displacement of the brain stem by a supratentorial mass, this stretches vessels supplying the midbrain and upper pons. The paramedial arteries are particularly affected. Ischemia and hemorrhage may develop in the posterior diencephalon, midbrain, and upper pons. The hemorrhage is usually paramedial in the brain stem and destroys the reticular activating system, leaving the patient unconscious with no prospect of returning to normal (Figure 4.26).
visual field defect These result from occlusion of the posterior cerebral artery and its branches. During uncal and parahippocampal herniation, the tentorial edge compresses the posterior cerebral artery, causing temporo-occipital infarction and visual field loss. The lesion is usually a red infarction (Figure 4.27) and may be unilateral or bilateral. Slowly developing herniation may allow homonymous hemianopsia to be detected. It is rarely identified, however, because visual fields are often not examined and herniation usually develops rapidly, with impaired consciousness making examination difficult. A visual field defect may nevertheless be detected in a survivor.
Figure 4.26. Brain stem hemorrhage (arrowhead) caused by uncal and parahippocampal herniation (arrows).Figure 4.27. Bilateral temporo-occipital red infarction (arrows) caused by compression of the posterior cerebral arteries against the tentorial edge during uncal and parahippocampal herniation (arrowheads).
diabetes insipidus Pituitary involvement may occur when anterior transtentorial herniation descends into the basal cistern and compresses the pituitary stalk. Ischemia of the pituitary gland or hypothalamus then causes diabetes insipidus.
obstructive hydrocephalus Brain stem compression narrows or occludes the aqueduct of Sylvius within the midbrain (Figure 4.21). The cisterns around the midbrain are also effaced, obstructing CSF flow and producing obstructive hydrocephalus. This is particularly harmful because the rise in CSF pressure rapidly increases the already elevated intracranial pressure. Herniation worsens, further compressing the aqueduct and obstructing CSF circulation, with progressive deterioration of the manifestations described above.
Original pages 228–230
3. Symptoms and Signs of Tonsillar Herniation
Tonsillar herniation, or a tonsillar pressure cone, occurs when the cerebellar tonsils descend through the foramen magnum into the cervical spinal canal, where pressure is lower. An expanding mass and raised pressure in the posterior fossa may cause this, or very high supratentorial pressure may be transmitted to the posterior fossa. Herniation may be bilateral, but is usually greater on the side of the mass. The tonsils become tightly impacted in the foramen magnum, compressing the medulla and the posterior inferior cerebellar arteries supplying it, and producing the following manifestations.
Respiratory and cardiac arrest Compression of the medulla by the cerebellar tonsils disables its vital respiratory center. Depending on the rate at which pressure rises, this may occur rapidly or gradually. Respiration becomes slower and shallower until it stops. Respiratory arrest always precedes cardiac arrest. Without treatment, the initially slow heart rate becomes rapid and irregular, and the previously elevated blood pressure progressively falls until death occurs.
Figure 4.28. Tonsillar herniation. The cerebellar tonsils compress the medulla and show indentations made by the margins of the foramen magnum (arrows).
In a patient with a posterior fossa mass and increased intracranial pressure, lumbar puncture to obtain CSF is contraindicated. Removing spinal CSF lowers pressure in the spinal canal, increasing the relative pressure above the foramen magnum and precipitating tonsillar herniation.
Gross examination of the brain shows indentations on the cerebellar tonsils where they have been compressed by the margins of the foramen magnum (Figure 4.28).
Unconsciousness Loss of consciousness may occur rapidly, or the condition may develop gradually before sudden unconsciousness. Slowing of respiration usually accompanies it. When tonsillar herniation is complete, respiration stops and the patient immediately becomes unconscious. Transtentorial and tonsillar herniation may occur together.
Neck stiffness (stiff neck) may occur when tonsillar herniation develops slowly. Pain and tightness in the neck result from irritation of the cranial and spinal nerves around the foramen magnum and upper cervical region. Movement aggravates the pain. Marked neck flexion may produce an electric-shock sensation traveling down the body, known as Lhermitte’s sign.
Paresthesia may accompany neck pain and stiffness when the cerebellar tonsils compress the posterior columns near the foramen magnum.
Original pages 230–232
4. Manifestations of Upward Transtentorial Herniation
A tumor or expanding mass in the posterior fossa may also cause upward, ascending, or reversed transtentorial herniation. The anterior vermis, superior cerebellar hemispheres, and midbrain are displaced through the posterior part of the tentorial notch into the supratentorial compartment, where pressure is lower. Compression of the quadrigeminal plate and aqueduct of Sylvius (Figure 4.29) produces Parinaud’s, or quadrigeminal, syndrome and obstructive hydrocephalus. Manifestations may be unilateral or bilateral, depending on whether the mass lies in the midline or in a cerebellar hemisphere. Tonsillar herniation almost always accompanies this condition. Compression of the vein of Galen and veins of Rosenthal impedes venous drainage and increases supratentorial venous pressure. Gross examination shows grooves on the superior cerebellar surface caused by the tentorial edge (Figure 4.30), and infarction in the territory of the superior cerebellar artery.
Color added · Anatomical details based on the original illustrationFigure 4.29. Upward transtentorial and tonsillar herniation. A large tumor pushes the vermis through the tentorial notch, compressing the quadrigeminal plate and aqueduct of Sylvius.Figure 4.30. Upward transtentorial herniation. The vermis and cerebellar hemispheres have been displaced upward and compressed by the tentorial edge (arrows).
In a patient with a large posterior fossa tumor, ventricular puncture for diagnosis or treatment may dangerously precipitate ascending herniation. Removal of ventricular CSF lowers supratentorial pressure, thereby increasing the relative infratentorial pressure and worsening upward herniation.
Quadrigeminal plate or Parinaud’s syndrome consists of paralysis of vertical eye movements. Initially, the vermis compresses the inferior colliculus, damaging the centers for downward gaze and convergence. The patient cannot look downward or converge the eyes on a near object, and the eyes deviate upward. Subsequent compression of the superior colliculus damages the upward-gaze center, so the patient can no longer look upward. The pupils become unreactive because of pretectal dysfunction. These ocular findings are usually difficult to elicit because unconsciousness develops rapidly.
cerebellar fit Upward herniation, or a large tumor in the anterior cerebellum, may severely compress the midbrain. Both arms and legs become rigidly extended, with opisthotonos, clenched hands, and flexed wrists. The patient is usually unconscious (Figure 4.31). The term “cerebellar fit” is misleading: the cerebellum itself does not produce this convulsive rigidity. Rather, a large cerebellar tumor compresses the midbrain.
Figure 4.31. “Cerebellar fit” in a child with a large cerebellar tumor compressing the brain stem.
Original pages 233–236
Radiological Signs of Increased Intracranial Pressure
Prolonged elevation of intracranial pressure, whatever its cause, produces changes visible on skull radiographs. These may be generalized, localized, or both, depending on the degree and duration of pressure elevation and the patient’s age. In young children, sutures may separate early. I have seen this within two or three days after a head injury producing an acute subdural hematoma. In adults with brain tumors, it is difficult to determine how long the changes take to appear, since the onset of increased pressure is unknown. The radiological manifestations are as follows.
1. Skull enlargement occurs only in young children whose sutures have not fused. The ratio of the skull to the facial bones exceeds 3:1. Localized bulging from focal pressure may accompany generalized enlargement.
2. Sutural separation is illustrated in Figure 4.32. The posterior fontanelle closes soon after birth. By one and a half years, the anterior fontanelle is about fingertip-sized, and by two years it is closed on radiographs. The coronal suture separates first and is the last to fuse, followed by the sagittal and lambdoid sutures. Separation is greatest near the fontanelles and is an important sign. It may occur up to the age of twelve, but is rare after sixteen. In an adult, sutural separation should suggest a diastatic fracture.
Figure 4.32. Separation of the coronal suture (arrowhead) due to increased intracranial pressure.Figure 4.33. Convolution markings, or digital impressions, indenting the inner skull surface.
3. Convolution markings or digital impressions (Figure 4.33) appear as radiolucent indentations in the inner table, resembling finger impressions in clay. They reflect thinning caused by pressure and pulsation of the cerebral gyri. Such markings are normally seen in the frontal and occipital bones; those in the parietal bones are more significant for diagnosing raised intracranial pressure. They should not, however, be used as the sole diagnostic criterion.
4. Changes in the sella turcica occur mainly in adults. They are uncommon in children because sutural separation and skull expansion relieve pressure. The first change is cortical erosion along the anterior surface of the dorsum sellae, extending downward toward the inferior sellar margin. On lateral radiographs, the cortex becomes indistinct or discontinuous (Figure 4.34). Subsequently the dorsum sellae and posterior clinoid processes disappear, and the cortex of the sellar floor thins, particularly posteriorly. With persistent pressure elevation, the floor may also disappear. The sella enlarges and loses mineral as pressure acts on its floor and posterior wall; the contents of the pituitary fossa bulge into the sphenoid sinus. Longstanding pressure elevation also causes atrophy of the tuberculum sellae.
Figure 4.34. Destruction of the dorsum sellae and posterior clinoid processes due to increased intracranial pressure.
Similar changes may result from osteoporosis or from local compression and destruction by a tumor in the sellar region.
5. Increased vascularity The vascular grooves on the inner skull surface enlarge in tumors such as meningioma. In some patients with raised intracranial pressure, the grooves of draining or emissary veins and the impressions of Pacchionian granulations also become larger.
6. Skull thinning occurs with chronically raised intracranial pressure in childhood, as in hydrocephalus. It is less common in adults and is generally diffuse.
7. cerebral angiography The cerebral vascular changes associated with raised intracranial pressure are described in Chapter 6.
CT and MRI have greatly improved neurological diagnosis, reducing the use of skull radiography and cerebral angiography. They provide more accurate information about a lesion’s location, type, size, and effect on the brain. Knowledge of plain radiographic findings nevertheless remains useful when CT or MRI is unavailable, and can guide further investigation. These findings should therefore still be learned.
Original pages 237–246
Treatment of Increased Intracranial Pressure
As discussed above, a brain tumor or other expanding intracranial mass raises intracranial pressure and alters cerebral blood flow (CBF). When decompensation occurs, brain herniation produces unconsciousness. These changes progressively worsen for as long as the expanding mass remains. Urgent diagnosis and treatment are therefore essential to restore normal intracranial pressure; otherwise, the patient may never regain consciousness and may eventually die.
Treatment has three objectives:
To reduce intracranial pressure and increase CBF by surgically removing the tumor or expanding mass.
To treat the effects of the expanding mass, such as cerebral edema, obstruction of CSF pathways, and neurovegetative disorders involving temperature, respiration, and circulation; and
To prevent herniation or reverse it.
Methods of treating increased intracranial pressure are as follows.
2.2.3 Administer an osmotic solution, such as mannitol
2.2.4 Administer a diuretic, such as furosemide
2.2.5 Administer corticosteroids
2.2.6 Induce hyperventilation
2.2.7 Administer barbiturates
2.2.8 Lower body temperature: hypothermia
2.2.9 Correct hyponatremia
Surgical Treatment
Removal of the mass Complete removal of the tumor or expanding mass is the best treatment because it removes the cause and lowers intracranial pressure. The changes caused by the mass, such as cerebral edema and abnormal CBF, gradually return toward normal. If the tumor compresses or obstructs CSF pathways, removal also reopens those pathways and lowers CSF pressure.
VENTRICULOSTOMY When a tumor obstructs CSF pathways and causes obstructive hydrocephalus, but cannot be removed immediately, CSF must be drained from the cranial cavity. A small burr hole is made anterior to the coronal suture, approximately 2–3 cm from the midline. The dura mater is opened and a catheter inserted into the frontal horn of the lateral ventricle, then connected to a sterile bottle in a closed drainage system. Intracranial pressure falls immediately and the patient progressively improves. Ventriculostomy provides only temporary CSF drainage or pressure reduction, however, and the underlying cause should subsequently be removed. Besides treatment, ventriculostomy may be used to locate a tumor: radiopaque contrast is injected into the ventricle and skull radiographs are obtained to demonstrate the site of obstruction.
In a patient with a cerebral hemispheric tumor, ventriculostomy may worsen the condition. Draining CSF from the ventricle opposite the tumor increases displacement of the brain toward that side. Ventriculostomy should therefore be performed on the side of the tumor, although catheter placement is often difficult because the tumor has compressed and displaced that ventricle. The catheter may also enter the tumor, causing hemorrhage within the tumor and ventricle and further deterioration.
VENTRICULO-ATRIAL, VENTRICULO-PERITONEAL SHUNT When a tumor lies in a vital location and cannot be removed, or can only be partly removed with persistent obstructive hydrocephalus, a shunt provides long-term CSF drainage and reduction of intracranial pressure. It may be combined with other treatment, such as radiotherapy.
A ventriculoatrial shunt drains CSF from the lateral ventricle into the atrium of the heart through a device implanted beneath the skin. The system consists of a ventricular catheter, reservoir, and cardiac or peritoneal catheter, and regulates CSF pressure. A ventriculoperitoneal shunt instead drains CSF into the peritoneal cavity.
RADICAL DECOMPRESSIVE CRANIECTOMY A very large portion of the skull is removed on the side of increased pressure. The dura mater is opened and sutured to the temporalis muscle, allowing the brain to expand outward and reducing intracranial pressure. This procedure remains effective in some patients and can save lives. The opening must be genuinely large. If it is too small, the skull edge compresses the extruding brain and its veins and arteries, causing venous congestion, ischemia, and progressively increasing edema (Figure 4.35). The result is harmful, with a further rise in intracranial pressure. For this reason, subtemporal craniectomy, which creates only a narrow opening, is ineffective and is no longer performed, as it cannot reduce intracranial pressure. Internal decompression by removing nonessential brain tissue, such as the anterior temporal lobe, is also relatively ineffective. When edema or pressure is severe, swollen brain rapidly fills the space created by resection, and intracranial pressure rises again.
Figure 4.35. Brain protruding through a small craniectomy opening. Note the indentations caused by the skull edge (arrows). The protruding brain is swollen and dark from venous congestion.
Medical Treatment
Medical treatment aims to reduce cerebral edema and correct disturbances of cerebral circulation. Cerebral edema is a major complication responsible for many deaths, so prompt treatment must accompany treatment of the underlying cause. Medical therapy should always proceed alongside surgery. Besides the tumor or expanding mass itself, other factors may aggravate edema; these must be eliminated or prevented. Medical treatment consists of the following.
Respiratory care The first step is for the physician or caregiver to observe whether breathing is normal. Airway obstruction produces anoxia and CO₂ retention, leading to vasodilatation, cerebral edema, and increased intracranial pressure. Patients whose consciousness is impaired by raised intracranial pressure may breathe abnormally, and the tongue or vomitus may obstruct the airway. Endotracheal intubation is then necessary to clear the airway and provide adequate oxygen. Slow, shallow breathing requires mechanical ventilation.
Circulation Cerebral circulation must be maintained adequately to deliver sufficient oxygen for brain metabolism. Blood loss or hypotension in the presence of raised intracranial pressure further reduces cerebral perfusion. The cause of inadequate circulation must therefore be found and corrected promptly.
Body temperature A rapid rise in intracranial pressure may produce marked hyperthermia. This endangers the brain because cerebral metabolism and oxygen demand increase. Temperature should therefore be returned to normal with antipyretics, sponging, or a cooling device. Induced hypothermia is not necessary.
Elevation of the head and trunk This improves venous return to the heart. The head should be elevated approximately 30° and kept straight. Excessive rotation of the neck compresses the neck veins and increases intracranial pressure.
Fluid restriction Fluid intake should be restricted to less than daily fluid losses. Intravenous fluid is given as 5% dextrose in half-strength saline, with added K⁺ when necessary. For adults, a rate of 60 cc/hour produces mild dehydration. Intake must be adjusted to losses to avoid excessive water and salt depletion. Physical examination, urine output, and blood sodium measurements guide adjustments to maintain normal values. Excessive fluid administration or a hypotonic solution with a Na⁺ concentration below 75 mEq/L (half-strength saline) may cause cerebral edema and increase intracranial pressure.
HYPERTONIC OR OSMOTIC SOLUTIONS A hypertonic solution, such as 20% mannitol or glycerol, reduces cerebral swelling and temporarily lowers intracranial pressure. It draws water out of the brain into blood with a higher osmolarity, while increasing urine output. The effect is temporary because plasma osmolarity returns to normal after two or three hours. Intracranial pressure then rises again, producing the rebound phenomenon. This is explained by penetration of some solute into brain tissue while the hypertonic solution is circulating; when blood osmolarity returns to normal, that solute draws water back into the brain. In a patient with a tumor or expanding mass, the mass must therefore be removed promptly after mannitol, before rebound occurs. Otherwise, pressure may exceed its previous level and the patient may deteriorate. A common example is an epidural hematoma: after mannitol, urgent evacuation and hemostasis are essential. Mannitol reduces brain volume and thus the tamponade effect, allowing further bleeding and enlargement of the hematoma. Intracranial pressure rises, and subsequent rebound raises it further, causing rapid deterioration. Intracranial hemorrhage must therefore be excluded before administering a hypertonic solution, or, when such a solution is used to reduce pressure in a patient with known intracranial bleeding, the hematoma must be evacuated urgently.
The advantage of hypertonic solutions is their rapid reduction of intracranial pressure, providing time for radiological investigation or preparation for surgery. Their disadvantages include an effect lasting only two or three hours followed by rebound. Excessive or frequent administration causes severe water and salt depletion, and the resulting electrolyte imbalance may damage neurons.
At present, 20% mannitol is the most commonly used agent; our neurosurgical unit does not use glycerol. The dose used for cerebral edema is 1.0–2.0 g/kg, which is relatively high, infused intravenously over approximately 15–20 minutes. Intracranial pressure begins to fall within 20–30 minutes of starting the infusion. More recently, however, Marshall, L. F., and colleagues(17) found that 0.25 g/kg mannitol produces an osmotic gradient of up to 10 mOsm and reduces intracranial pressure as satisfactorily as a high dose of 1 g/kg. The reduction likewise lasts approximately three hours. A dose of 0.25–0.5 g/kg does not cause hyperosmolarity harmful to renal function, electrolyte imbalance, rebound, hemoconcentration, or hypotension. Mannitol should not be administered to patients with renal failure or congestive heart failure.
Diuretics Furosemide is a diuretic acting on the kidneys, unlike mannitol, which is an osmotic solution. Furosemide reduces intracranial pressure without the initial pressure increase associated with mannitol(16) Furosemide reduces edema in both diseased and normal brain, whereas mannitol acts effectively only where the blood–brain barrier remains normal. This property of furosemide may be therapeutically useful. Furosemide also reduces CSF production, so CSF pressure does not rise as rapidly.
STEROIDS Dexamethasone is the steroid most often used in neurological and brain disease. It reduces cerebral edema and improves the patient’s condition, particularly in metastatic brain tumors and malignant gliomas. After dexamethasone, patients with headache, drowsiness, vomiting, or hemiplegia may become free of headache, regain alertness, and recover limb movement. Repeat cerebral angiography or CT generally shows that clinical improvement accompanies reduced mass effect and improved circulation around the tumor. The mechanism by which dexamethasone reduces cerebral edema remains uncertain, but corticosteroids are believed to restore the function of cell membranes forming part of the blood–brain barrier.
Dexamethasone is started at 10 mg intravenously, followed by 5 mg intravenously or intramuscularly every six hours for five to seven days, then gradually tapered. Its antiedema effect begins approximately 18–24 hours after administration. It is therefore not useful for urgently reducing cerebral edema and intracranial pressure. Mannitol should be given initially for rapid pressure reduction, together with dexamethasone, which reduces edema later.
Contraindications: dexamethasone should not be given in patients with peptic ulcer, tuberculosis, fungal infection, diabetes, or psychological disorders.
When dexamethasone is used for cerebral edema, phenytoin (Dilantin) should be avoided because it increases dexamethasone metabolism and elimination.
HYPERVENTILATION This is another relatively rapid method of reducing intracranial pressure. During brain surgery, hyperventilation causes the brain to shrink within two or three minutes. It produces hypocapnia and cerebral vasoconstriction, reducing the amount of blood circulating in the brain. To lower pressure without causing oxygen deficiency, PCO₂ should be maintained at 25–30 mmHg. If PCO₂ falls to 20 mmHg or below, oxygen becomes insufficient for normal metabolism, with harmful subsequent effects.
BARBITURATES Barbiturates are increasingly used to lower intracranial pressure in patients with brain injury. When steroids, hyperventilation, and hypertonic solutions fail, barbiturates such as thiopental and pentobarbital reduce pressure in 70% of treated patients. Pressure consistently falls rapidly, making barbiturates useful when intracranial pressure rises abruptly.
Treatment should begin with phenobarbital 3–5 mg/kg body weight. Repeated doses are then given to maintain a blood phenobarbital level of 2.5–3.5 mg/100 cc, which effectively lowers intracranial pressure. Thiopental has a short duration of action and requires frequent repeat injections. Intravenous administration is preferable to maintain a steady reduction in pressure. Barbiturates may be combined with steroids, hypertonic solutions, and hypothermia.
The mechanism of pressure reduction is unknown. Barbiturates have long been known to reduce cerebral metabolic requirements, but this does not explain their pressure-lowering mechanism.
In patients with brain injury, barbiturates should not be used without continuous direct intracranial pressure monitoring. They induce sleep, preventing neurological examination. Continuous pressure measurement is therefore necessary to identify complications such as hemorrhage or cerebral edema.
HYPONATREMIA Hyponatremia caused by water retention is known to produce cerebral edema, drowsiness, and seizures. It must be corrected promptly by restricting fluid intake. The patient improves when blood sodium returns to normal.
HYPOTHERMIA This protects injured brain from further hypoxic damage by reducing cerebral metabolism. Its effect on intracranial pressure varies between patients and is less pronounced than that of hypertonic solutions or barbiturates. At present, neurosurgeons generally do not use hypothermia during or after brain surgery because it is cumbersome and its effects on cerebral edema and intracranial pressure are not clear. Instead, antipyretics are used to maintain normal temperature, together with other pressure-lowering treatments.
Original pages 246–248
Chapter 4 References
Weinstein J.D., Langfitt T.W., Bruno L., Zaren H.A., and Jackson J.L.F., : Experimental study of patterns of brain distortion and ischemia produced by an intracranial mass. J. Neurosurgery 28 : 513-521, 1968.
Koos W.T., Miller M.H., Pathological and clinical evaluation of increased intracranial pressure. in Intracranial Tumors of Infants and Children. C.V. Mosby Company pp. 28-59, 1971.
Langfitt T.W. : Intracranial pressure, Clinical Neurosurg. The Williams & Wilkins Co. Vol. 16 : 417-436, 1969.
Miller D. and Adam H. : Physiopathology and management of increased intracranial pressure. In Scientific Foundation of Neurol. William Heineman Med. Books Ltd. 308-324, 1972.
Zwetnow N.N. : Effect of increased cerebrospinal fluid pressure on the blood flow and on energy metabolism of the brain. Acta Physiol. Scand., Suppl. 339 : 1-31, 1970.
Shapiro H.M., Langfitt T.W., Weinstein J.D. : Compression of cerebral vessels by intracranial hypertension : II. Morphological evidence for collapse of vessels. Acta Neurochir. (Wien) 15 : 223-233, 1966.
Miller I.D., Becker D.P., Ward J.D., Sullivan H.G., Adam W.E., and Rosner M.J. : Significance of intracranial hypertension in severe head injury. J. Neurosurgery, 47 : 503-516, 1977.
Meyer J.S., and Hunler J., : Effect of hypothermia on local blood flow and metabolism during cerebral ischemia and hypoxia. J. Neurosurg. 14 : 210-227, 1957.
Siesjo B.K., and Plum F. : The brain in normoxia and in hypoxia. Acta Anesthes. Scand. Suppl. 45 : 81-101, 1972.
Wolff H.G. : Headache and other head pain. New York, Oxford University Press, 1963.
Cooper R., and Hulme A. : Intracranial pressure and related phenomena during sleep J. Neurol. Neurosurg. Psychiat, 29 : 564-570, 1966.
Lundberg N. : Continuous recording and control of ventricular fluid pressure in neurosurgical practice. Acta Psychiat. Scand., 36 : suppl. 149 : 1-193, 1960.
Plum F., Posner J.B. : Diagnosis of Stupor and Coma, 3rd edition. F.A. Davis Company, Philadelphia : 87-172, 1980.
Finney L.A., Walker A.E. : Transtentorial herniation, Charles C. Thomas Publisher, 1962.
Huber A. : Eye symptoms in brain tumor, The C.V. Mosby Company, 2nd edit, pp 94-100, 1971.
Cottrell J.E., Robustelli A., Post K., Turndof H. : Furosemide and mannitol induced changes in intracranial pressure and severe osmolarity and electrolytes. Anesthesiology 47 : 28-30, 1977.
Marshall L. F., Smith R.W., Rauscher L. A., Shapiro HM : Mannitol dose requirements in brain injured patient. J. Neurosurgery 48 : 169-172, 1978.
Langfitt T.W., Increased intracranial pressure and the cerebral circulation. In Neurological Surgery, edited by Youmans J.R., W.B. Saunders Co., vol. 2 p. 846-917, 1982.
Mc Graw C.P., Howard G. : Effect of mannitol on intracranial pressure. Neurosurgery 13 : 269-271, 1983
Ravussin P, Abou-Madi M, Archer D., Chiolero R., Freeman J., Trop D., de Tribolet N., : Changes in CSF pressure after mannitol in patients with and without elevated CSF pressure J. Neurosurg. 69 : 869-876, 1988
Robert P.A., Pollay M., Eagles C., Pendleton B., Reynolds E., Stevens F.A., : Effect on intracranial pressure of furosemide combined with varying doses and administration rates of mannitol. J. Neurosurg. 66 : 440-446, 1987
Kosteljanetz, M. : Acute head injury : Pressure-volume relations and cerebrospinal fluid dynamics. Neurosurgery, 18 : 17-24, 1986
Yoshino, E., Yamaki, T., Higuchi, T., Harikawa, Y., and Kirakawa, K. : Acute brain edema in fatal head injury : Analysis by dynamic CT scanning. J. Neurosurg., 63 : 830-839, 1985
Quest D.O. : Increased intracranial pressure, brain herniation, and their control in Neurosurgery, edit. by Wilkins, R.H., and Rengachary, S.S., Mc Graw-Hill Book Co. vol 1 : 332-342, 1985
Silverberg, G.D. : Intracranial pressure monitoring. in Neurosurgery, edit by Wilkins, R.H., and Rengrachary S.S., Mc Graw-Hill Book Co. vol 1 : 156-160, 1985
Wilkinson, H.A., : Diagnosis and therapy of intracranial hypertension. In Rippe, J.M., Irwin, R.S., Alpert, J.S., and Dalen J.E., eds. : Intensive Care medicine. Boston, Little, Brown & Co. 1985
Tans, J.T., and Poortvliet, D.C.J. : Intracranial volume-pressure relationship in man Part 1 : Calculation of the pressure-volume index. J. Neurosurgery, 56 : 524-528, 1982
Tans, J.T., and Poortvliet, D.C.J. : Intracranial volume-pressure relationship in man. Part 2 Clinical significance of the pressure-volume index J. Neurosurgery, 59 : 945-950, 1983
Miller J.D., Piper, I.R. : Raised intracranial pressure and its effect on brain function. In Neurosurgery edited by Crockard L., Hayward, R., Hoff, J.T. Blackwell Scientific Publications p. 373-390, 1992
Chapman P.W., Cosman E.R., Arnold M.A., : The relationship between ventricular fluid pressure and body positon in normal subjects and subjects with shunts : telemetric study. Neurosurgery 26 : 181-189, 1990
Miller, J.D. Intracranial pressure monitoring. In : Bihari, C. & Holaday, J.W. (eds) Update in Intensive Care and Emergency Medicine. Vol.9 - Brain Failure, PP 223-38, 1989 Springer-Verlag. Berlin.
Piper I.R., Miller J.D. Whittle I.R. Lawson A. : Measurement of craniospinal compliance - an improved method. Journal of neurology, Neurosurgery, and Psychiatry 53 : 445, 1990
Rosner M.J., Coley I.B., : Cerebral perfusion pressure, intracranial pressure and head elevation. J. of Neurosurgery 65 : 636-641, 1986
Jafar J.J., Johns L.M. Mullan S.F. : The effect of mannitol on cerebral blood flow. J. of Neurosurgery 64 : 754-759, 1986
Robertson, C.S. Narayan, R.K., Contant, C.F., et al. : Clinical experience with continuous monitor of intracranial compliance. J. Neurosurgery 71 : 673-80, 1989
Original pages 249–250
Chapter 5
Symptoms and Signs of Brain Tumors
Tumors arising in the brain continue to grow, producing two major groups of symptoms and signs:
1. General symptoms. These result from raised intracranial pressure. The three principal symptoms (the symptom triad) are headache, vomiting, and blurred vision due to papilledema (choked disc). As the tumor enlarges, other manifestations appear: personality change, a reduced level of consciousness, double vision (diplopia) or strabismus due to abducens nerve palsy, enlargement of the head in young children, dizziness, generalized epilepsy, and the Cushing reflex. These manifestations have been discussed in detail in the chapter on raised intracranial pressure. They are not, in fact, specific to brain tumors; they are manifestations of raised intracranial pressure, which may have many other causes, including an intracerebral hematoma, brain abscess, and cerebral edema.
2. Focal symptoms. These reflect loss of the specific functions of the part of the brain destroyed or compressed by the tumor. Focal manifestations are important diagnostic clues because they indicate the location of the tumor. Physicians should therefore understand the anatomy and function of each part of the brain in order to recognize abnormalities. In general, patients do not present with purely focal symptoms; their symptoms often also reflect impaired function in the brain surrounding the tumor. Because a brain tumor continues to enlarge, it compresses adjacent brain tissue, progressively impairing its function. Thus, a history of progressively increasing loss of brain function is important in diagnosing a brain tumor. Careful history-taking can identify the first focal functional deficit.
In addition to manifestations of brain destruction, a brain tumor may produce manifestations of cerebral irritation in the form of various types of seizures. A focal seizure can be just as important as a deficit caused by brain destruction, because it helps locate the tumor, as discussed in detail below.
Focal Symptoms and Signs of Brain Tumors
The brain is divided into regions, each with specific functions and connections to other regions. A tumor causes loss of brain function, but this loss may not be conspicuous because of several modifying factors, including the patient’s age, whether the tumor is benign or malignant, the rate of tumor development, and the occurrence of herniation. Frequently, no focal manifestations are evident; the patient has only symptoms of raised intracranial pressure, and the tumor can be localized only by radiological investigation.
Original pages 250–259
FRONTAL LOBE
The frontal lobe is the largest part of the brain. It lies anterior to the central sulcus (of Rolando), which separates it from the parietal lobe. Laterally, the frontal lobe is separated from the temporal lobe by the lateral or Sylvian fissure. This fissure begins at the temporal pole and runs posteriorly and slightly upward. The cortex forming the fissure is called the operculum and comprises parts of the frontal, parietal, and temporal lobes. Large sulci divide the frontal lobe into four gyri. On the lateral surface of its anterior portion are the superior, middle, and inferior frontal convolutions, separated by the superior and inferior horizontal sulci (Figure 5.1). The inferior frontal gyrus is further divided into orbital, triangular, and opercular parts. The gyrus immediately anterior to the central sulcus is the precentral gyrus, which forms the motor cortex; this also includes the part of the paracentral lobule anterior to the central sulcus on the medial surface of the hemisphere. Anterior to the motor cortex is the premotor sulcus. The cortex anterior to this sulcus and posterior to the superior, middle, and inferior frontal convolutions is the premotor area, corresponding to Brodmann area 6, also called the extrapyramidal cortex. The premotor area helps control the muscles on the opposite side of the body and has a distribution of centers similar to that of the motor area.(1) The posterior portion of the middle frontal convolution contains the frontal eye field, which controls movement of both eyes in the same direction (conjugate gaze). The posterior portion of the inferior frontal convolution, corresponding to its opercular and triangular parts in the dominant hemisphere, is the motor speech area or Broca’s area and is concerned with speech. The frontal lobe anterior to the premotor and motor speech areas is the frontal association or prefrontal area. It is concerned with higher intellectual function and is particularly well developed in humans. On the basal or orbital surface, the olfactory sulcus divides the frontal lobe into the rectus gyrus medially and the orbital gyrus lateral to the sulcus.
Color added while retaining the original linework and letteringFigure 5.1. The left cerebral hemisphere and the locations of its various functional centers. Loss of function in these centers indicates the location of a lesion.
The functional deficits associated with the individual regions of the frontal lobe are discussed separately below.
The motor area produces voluntary movement on the opposite side of the body. It is divided into centers, each controlling the muscles of a particular body part. The center for the larynx and throat lies lowest, adjacent to the Sylvian fissure. Successively higher are the centers for the jaw, tongue, face, eyes, fingers, hand, arm, shoulder, trunk, hip, and leg. The leg area lies medially in the motor area (Figure 5.2). The shoulder center is near the vertex. This anatomy explains shoulder weakness following surgery for a parasagittal meningioma in this part of the motor cortex. The cortical representations of the tongue, face, and fingers are particularly large because these structures perform extensive and complex movements. Fibers from the motor area form the corticobulbar and corticospinal tracts, descending through the corona radiata, the genu and anterior two-thirds of the posterior limb of the internal capsule, and the cerebral peduncle. The corticobulbar tract terminates in nuclei in the pons and medulla. The corticospinal tract continues toward the spinal cord and decussates in the lower medulla: approximately 70–90% of its fibers cross to the opposite side and descend as the lateral corticospinal tract, ending on anterior horn cells in the spinal cord.(2) The remaining minority descend without crossing as the ventral corticospinal tract.
Color added while retaining the original linework and letteringFigure 5.2. The motor cortex. A tumor in the cortex or subcortex (1) causes monoplegia. A small tumor in the internal capsule (2) causes hemiplegia.
The symptoms and signs of frontal lobe tumors are as follows:
1) MONOPLEGIA, HEMIPLEGIA
Tumors in the motor area often bring patients to medical attention relatively early because they cause weakness of a body part or seizures. A tumor on the surface or in the subcortex causes a focal deficit in the compressed region, described as monoplegia (Figure 5.2). Compression of the arm and hand area causes weakness of the opposite arm and hand; a tumor in the medial motor area causes weakness of the opposite leg. Tumors in these locations do not usually cause hemiplegia. A tumor of the falx in the region of the paracentral lobules, such as a falx meningioma, causes weakness of both legs (Figure 5.3). One leg is usually weaker than the other, and the foot is weaker than the proximal thigh. Some patients also have difficulty passing urine because the micturition center is compressed. These manifestations must be distinguished from those of a spinal cord lesion. The distinction is not difficult: a parasagittal brain tumor causes raised intracranial pressure and seizures, without a sensory level. A spinal cord lesion causes neither raised intracranial pressure nor seizures, but produces a level of sensory loss and motor dysfunction.
Color added while retaining the original linework and letteringFigure 5.3. A tumor of the falx cerebri at the medial motor cortex compresses the motor fibers to the legs, producing paraparesis.
A unilateral lesion in the motor representation of the larynx, throat, palate, upper face, diaphragm, anus, or bladder seldom produces an obvious deficit, because these structures receive bilateral innervation.
A tumor in the lower frontal lobe of the dominant hemisphere, at the facial muscle center and Broca’s area, causes difficulty speaking (dysphasia) or inability to speak (aphasia), together with facial weakness. In right-handed people this speech center is in the left hemisphere; in left-handed people it is in the right hemisphere. If a tumor in this region causes seizures, the patient cannot speak during the seizure and for a time afterward.
A tumor in the deep white matter, where the corticospinal fibers converge, causes hemiplegia (Figure 5.2), even if it is small.
The history is one of gradually developing weakness that progressively spreads to other parts of the body. This is a very important history in diagnosing a brain tumor.
2. Seizures (epilepsy, convulsion, seizure, fit)
Seizures are important, particularly when they first occur in an adult who has never previously had one. Focal seizures and marching seizures (Jacksonian epilepsy or marching epilepsy) are especially significant because they provide clues to the cause and location of the lesion. Tumors in the motor and premotor areas cause seizures more frequently than tumors elsewhere. A focal seizure begins in the body part corresponding to the tumor’s location. It is clonic, with rhythmic jerking that may stop or continue for a prolonged period. In some patients, the jerking spreads to other parts of the same side of the body; this is called marching or Jacksonian epilepsy. For example, jerking may begin in the hand and spread to the arm, mouth, and eyelid. If the tumor is in the dominant hemisphere, the patient becomes unable to speak. The seizure then stops. Consciousness is retained in such cases, but the body parts that jerked remain temporarily weak afterward. This is Todd’s paralysis, attributed to temporary exhaustion of the neurons responsible for the seizure. Within a few hours, the weakness resolves and function returns to its pre-seizure state. The body part in which jerking began regains strength last. In this example, the hand, arm, and face are weak after the seizure, with the hand showing the greatest and longest-lasting weakness. A history identifying the site of onset of the jerking and the distribution of Todd’s paralysis therefore helps localize the tumor.
In some cases, a seizure involves an entire side of the body before spreading to the opposite side. At that stage the patient loses consciousness, and the seizure is called a generalized or grand mal seizure. It takes the form of a clonic-tonic convulsion, which stops after a time. The patient commonly sleeps for a while before awakening.
Jacksonian epilepsy may affect a single body part continuously without loss of consciousness; this is called “epilepsia partialis continua.” In some cases, there are pauses between attacks or many dozens of attacks a day, termed serial Jacksonian epilepsy. Recurrent attacks without recovery of consciousness between them are called Jacksonian status epilepticus.
3) FRONTAL ATAXIA
The premotor and motor areas of the frontal lobe are connected to other brain regions, particularly the pons and cerebellum. Frontopontine fibers arise from the middle frontal convolution anterior to areas 6 and 8 and form an important part of the corticopontocerebellar tract.(1) Impulses descend from the cortex to the pons; after synapsing there, they pass through the middle cerebellar peduncle (brachium pontis) to the opposite cerebellar hemisphere. Destruction of these fibers by a frontal lobe tumor causes frontal ataxia. It may be difficult to distinguish this from cerebellar ataxia. The guiding distinction is that destruction of the frontal cortex or frontopontine fibers causes contralateral ataxia without dysmetria, whereas destruction of a cerebellar hemisphere causes ipsilateral ataxia with dysmetria, usually accompanied by nystagmus.
4) ABNORMAL CONJUGATE GAZE
The frontal eye field (Brodmann area 8), in the posterior middle frontal gyrus anterior to the premotor area, controls voluntary movement of both eyes together in the same direction (conjugate gaze). Stimulation produces conjugate deviation of both eyes to the opposite side and may also turn the head and trunk in the same direction. Eye movements elicited by visual stimulation require impulses to pass from area 17 in the occipital lobe through the inferior occipitofrontal fasciculus to the frontal eye field (Figure 5.40). Destruction of this center causes paresis of conjugate gaze toward the opposite side, so both eyes look toward the side of the lesion.(6) This is temporary in a conscious person because adaptation can occur; in an unconscious person the deviation persists.
In general, frontal lobe tumors in this region do not cause gaze palsy, conjugate ocular deviation, or nystagmus. If the tumor causes an adversive seizure, however, the attack begins with the eyes and face turning toward the side of the convulsing limbs. Thus, deviation of the eyes and face to the left while the left arm and leg are convulsing indicates an irritative lesion in the right frontal eye field and motor areas.
5) PERSONALITY CHANGE
The prefrontal or frontal association area is the part of the frontal lobe anterior to the premotor area and motor speech center, including its orbital surface. It is connected to the visual, auditory, and other sensory centers through association fibers and also sends fibers to the thalamus and hypothalamus. The prefrontal area is highly developed in humans and is responsible for higher intellectual functions, including memory, judgment, reasoning, emotional restraint, mental activity, and personality. Tumors here therefore cause changes in personality and thinking.(3,4) Generally, they cause no clearly recognizable focal symptoms until very large, because neither patients nor their families notice the early changes. Patients may complain of deteriorating memory, difficulty concentrating on work, progressively poorer work performance, neglect of their usual duties, and impaired thinking. These changes gradually progress to dementia. Later personality changes include loss of initiative, lack of interest, untidiness, and neglect of habitual personal hygiene such as brushing the teeth, shaving, and bathing. Some patients use coarse language or become irritable; they eat slowly and messily. In later stages they pass urine and stool without awareness, in inappropriate places and without embarrassment, and may sometimes handle their feces. They become lethargic, expressionless, and unresponsive to stimulation.
Intrinsic frontal lobe tumors, such as gliomas and metastases, cause these manifestations earlier and more severely than extracerebral tumors such as meningiomas. With benign gliomas, such as astrocytoma or oligodendroglioma, symptoms develop more slowly and are less severe than with glioblastoma multiforme, which grows rapidly and destroys fibers. Meningiomas grow from outside the brain and compress it before destroying it, so symptoms develop slowly and gradually.
A common orbital-surface tumor is the olfactory groove meningioma. It causes loss of smell (anosmia) by compressing and damaging the olfactory bulb or tract. Depending on tumor size, anosmia may be unilateral or bilateral. Gliomas at the base of the frontal lobe may likewise abolish smell by destroying the olfactory pathway. A large olfactory groove meningioma may also cause personality change, although this is usually not marked. Posterior growth may compress the ipsilateral optic nerve, causing primary optic atrophy. Funduscopic examination shows a distinctly pale optic disc and narrowed vessels. The opposite disc shows papilledema because the large tumor raises intracranial pressure. This combination is called Foster-Kennedy syndrome.
6) TREMOR
Tremor may occur with a large, deep frontal lobe tumor. It may be contralateral or bilateral. It resembles the tremor of parkinsonism but is less severe and lacks the pill-rolling movement seen in parkinsonism. There is no satisfactory explanation for this tremor resembling extrapyramidal motor dysfunction.
7) GRASPING AND GROPING REFLEXES
A grasping reflex on examination is an important finding, regarded as a pathognomonic sign of a frontal lobe lesion. It occurs in the hand opposite the lesion and may also occur in the foot if the tumor is in the superior frontal lobe.(7)
The grasping reflex is flexion of the fingers and thumb in response to an object stimulating the palmar surfaces of the fingers, particularly between the index finger and thumb. The patient grasps the object and does not release it; attempts to pull it away make the grip tighter. In some patients, with both eyes closed, a light touch to the palm or fingers produces grasping and searching or fumbling movements, called the groping reflex. Grasping and groping are infantile reflexes. A frontal lobe lesion causes a return to this infantile pattern, allowing a grasping reflex to appear on the opposite side. A unilateral grasping and groping reflex in a conscious patient is therefore a valuable localizing sign. It is much less significant in a patient with impaired consciousness or when present bilaterally. If the tumor causes progressively increasing hemiparesis, the grasping reflex disappears once complete hemiplegia develops.
Original pages 259–263
PARIETAL LOBE
The parietal lobe lies posterior to the central sulcus (Rolandic fissure), superior to the temporal lobe or Sylvian fissure, and anterior to the occipital lobe. Anteriorly, the postcentral sulcus runs parallel to the central sulcus, separating the postcentral gyrus from the remainder of the parietal lobe. In the middle of the lobe, a transverse sulcus runs from the postcentral sulcus to the transverse occipital sulcus, dividing the posterior parietal lobe into superior and inferior parietal lobules. These include the supramarginal gyrus, which curves around the end of the Sylvian fissure, and the angular gyrus, which curves around the end of the superior temporal sulcus. In the dominant hemisphere, the supramarginal and angular gyri serve as the sensory or perceptive speech center, also called Wernicke’s center (Figure 5.1).
The postcentral gyrus is concerned with somatosensation. Most of its fibers come from the lateral nuclei of the thalamus, which relay impulses from the spinothalamic tract, medial lemniscus, and secondary trigeminal tract. Fibers from the thalamus pass through one-third of the posterior limb of the internal capsule to the postcentral gyrus. Sensations from different body parts are represented in the postcentral gyrus in an arrangement similar to that of the motor area (Figure 5.2). The superior and inferior parietal lobules constitute the psychosensory area, concerned with the perception and interpretation of sensation, or sensory association area. They connect to the postcentral gyrus through association pathways and also receive fibers from the lateral dorsal and posterior thalamic nuclei. The precise functions of the individual subdivisions of this part of the parietal lobe are not clearly known.
The parietal lobe receives and interprets sensations from the thalamus, particularly touch, pressure, and position sensation.
Focal Symptoms and Signs of Parietal Lobe Tumors
A tumor that destroys the postcentral gyrus causes loss of several somatosensory or cortical sensory functions, including touch, pressure, and position sensation on the opposite side of the body, while pain sensation is retained. Joint position sense, vibration sense, tactile localization, light touch, two-point discrimination, and stereognosis are impaired.(8) Common sensory deficits include the following:
1. ASTEREOGNOSIS
Astereognosis, or tactile agnosia, is the most common cortical sensory deficit. It occurs opposite the tumor. The patient cannot identify a familiar, frequently used object by touch. For example, with the eyes closed, a key placed in the affected hand cannot be recognized as a key, even though tactile and pressure-touch perception remain intact, because the patient does not recognize the object’s size, weight, shape, and composition.
2. IMPAIRED TWO-POINT DISCRIMINATION
The patient cannot distinguish two simultaneous stimuli. This indicates combined impairment of touch and pressure sensation and occurs on the side opposite the lesion.
3. SENSORY INATTENTION
This is another important finding in a patient with a tumor or other parietal lobe lesion. When corresponding sites on both sides are stimulated simultaneously, the patient does not perceive the stimulus opposite the lesion. For example, a patient with right-sided sensory inattention does not perceive right-palm stimulation when both palms are stimulated together, but perceives stimulation on either side when they are tested separately.
4. SENSORY EPILEPSY
The attack begins with a sensation that is difficult to describe and may take various forms, such as numbness, tingling, an electric-shock-like sensation, or paresthesia. It begins in one body part and spreads to others, a pattern called a sensory Jacksonian fit. For example, numbness may begin in the right hand and subsequently involve the arm and right side of the face. Sensory epilepsy may remain localized and then cease, or spread to the motor area and produce jerking. The motor seizure may be focal or generalized, with loss of consciousness (generalized convulsion). The sensory symptoms may sometimes be interpreted as the aura of motor epilepsy. As with motor epilepsy, the site of onset of sensory symptoms helps locate the tumor in the postcentral gyrus. Deep parietal lobe tumors seldom cause seizures.
5. PSEUDO-ATHETOSIS
A tumor or other lesion in the postcentral gyrus causes hypotonia and wasting of the muscles of the affected body part, with ataxia both at rest and during movement. Involuntary limb movements may occur at rest, termed pseudo-athetosis. Ataxia is evident on finger-nose testing and is called sensory ataxia.(7)
This occurs when a large posterior parietal tumor extends deeply into the white matter near the lateral wall of the lateral ventricle, compressing or destroying the upper optic radiation and producing this pattern of visual field loss (Figure 5.4). Here the optic radiation passes upward near the posterior limb of the internal capsule; its fibers then spread along the lateral aspect of the lateral ventricle at the beginning of the occipital horn and terminate at the calcarine fissure of the occipital lobe. A visual field defect is an important sign that requires careful examination to detect.
Color added while retaining the original linework and letteringFigure 5.4. A parietal lobe tumor destroys the upper optic radiation, producing inferior homonymous quadrantanopia.
7. GERSTMANN’S SYNDROME
A tumor or other lesion in the posterior parietal lobe, at the angular gyrus of the dominant hemisphere, produces finger agnosia (inability to identify the fingers), dysgraphia (inability to write), dyscalculia (inability to calculate), and right-left disorientation.(6,8) Of these manifestations, finger agnosia is the most important.
8. SENSORY APHASIA OR DYSPHASIA
This results from a tumor in the posteroinferior parietal lobe corresponding to Wernicke’s center in the dominant hemisphere. The patient has impaired comprehension of spoken language (dysphasia), written language (dysgraphia), and meaning, as well as impaired reading (dyslexia) and calculation (dyscalculia). As the tumor enlarges, the deficits become more severe, producing global dysphasia: speech becomes meaningless and incomprehensible, and verbal communication is impossible.
9. AGNOSIA AND APRAXIA
These occur with tumors in the posterior parietal lobe near the temporal and occipital lobes. Agnosia is the inability to understand the meaning of, or recognize, objects presented visually or by touch because of a receptive defect. Apraxia is the inability to perform a desired action, such as unfastening a pin, despite understanding the task and having no motor paralysis, sensory loss, or ataxia of the arm or hand.
Original pages 263–268
OCCIPITAL LOBE
The occipital lobe is the most posterior part of the cerebral hemisphere, lying behind the parieto-occipital fissure. Anteriorly it adjoins the parietal and temporal lobes. On its medial surface, the calcarine fissure runs from front to back. The portion above the fissure is the cuneus, and that below it is the lingual gyrus. The optic radiation from the lateral geniculate body terminates in the primary visual cortex (the striate area or Brodmann area 17) (Figure 5.5), which lies on both sides of the calcarine fissure and extends onto the lateral aspect of the occipital pole. Fibers carrying impulses from each half-retina divide into two groups: those from its lower half terminate below the calcarine fissure, and those from its upper half terminate above it. Macular fibers terminate in the most posterior part of the calcarine fissure bilaterally (bilateral representation), accounting clinically for macular sparing with a unilateral lesion. A distinctive feature of the visual cortex on a transverse section through the occipital lobe is a white band of fibers, the stripe of Gennari, comprising optic radiation fibers and secondary association fibers.(9) The visual cortex is concerned only with the reception of visual information, not its interpretation.
Color added while retaining the original linework and letteringFigure 5.5. The calcarine fissure, visual cortex (area 17), and visual association areas (18 and 19). A. Medial view of the right cerebral hemisphere. B. Lateral view of the left cerebral hemisphere.
Beyond the visual cortex lie the visual association areas (Brodmann areas 18 and 19) (Figure 5.5). Area 18 connects with areas 17 and 19 and interprets impulses received from area 17. Its important function is to recognize and distinguish the objects seen. Area 18 also exchanges fibers with the prefrontal, sensory, motor, and auditory association areas. Of particular importance are fibers forming the superior longitudinal and inferior fronto-occipital bundles to the frontal lobe, providing the pathway for voluntary conjugate eye deviation in response to visual stimulation (Figure 5.40). Area 18 also sends internal corticotectal or corticomesencephalic fibers to the superior colliculi, providing a pathway for vertical eye movements.(9) Area 19, the peristriate area, extends from area 18 to the boundary of the occipital lobe and connects with areas 17 and 18 and other cortical regions. It serves as the visual psychic area, with complex functions involving visual recognition and perception. Together with area 18, it is also a cortical center for eye movements and the optic fixation reflex in response to vision.
Focal Symptoms and Signs of Occipital Lobe Tumors
Tumors are uncommon in the occipital lobe. It is considered a silent area because symptoms usually do not appear early, but only after the tumor has become very large. The large size produces raised intracranial pressure, with headache, papilledema, and vomiting; papilledema is common. Focal manifestations may result either from destruction or from irritation (epilepsy), as follows:
1. CONTRALATERAL HOMONYMOUS HEMIANOPIA
The patient cannot see the same half of the visual field of each eye (Figure 5.6) because of destruction of the optic radiation or the region of the calcarine fissure. Homonymous hemianopia may be complete or incomplete, depending on the tumor’s position and size. Compression of the upper or lower part of the calcarine fissure produces homonymous inferior or superior quadrantanopia, respectively. Such tumors are small and are often falx meningiomas compressing the calcarine fissure. Intrinsic tumors, such as an occipital glioblastoma, usually cause complete homonymous hemianopia because they destroy the entire optic radiation as it approaches the calcarine fissure. A tumor at the occipital pole destroys fibers from the retinal macula, producing a hemianopic scotoma.
Color added while retaining the original linework and letteringFigure 5.6. Visual field loss resulting from lesions at different sites along the visual pathway.
Optic nerve = ipsilateral amaurosis
Chiasm = bitemporal hemianopsia
Optic nerve-chiasm junction = ipsilateral amaurosis and contralateral temporal hemianopsia
Anterior (Meyer’s) loop of the optic radiation in the temporal lobe = incongruous contralateral homonymous superior quadrantanopsia
Optic radiation in the parietal lobe = incongruous contralateral homonymous inferior quadrantanopsia
Optic radiation in the anterior occipital lobe = contralateral homonymous hemianopsia
Occipital pole = contralateral congruous homonymous hemianoptic central scotoma
Occipital horn. intraventricular tumor extending into the ventricular wall = contralateral homonymous hemianopsia
Homonymous hemianopia is an important manifestation of an occipital lobe tumor, but some patients are unaware that vision on one side is lost. Others give a suggestive history, such as repeatedly walking into a door frame. One of the author’s patients reported grazing a three-wheeled vehicle while cycling three times in four months, always on the patient’s right side. When reading, some patients see only half a word or sentence; when writing, they continue to the far right edge of the page, a manifestation of right hemianopia.
2. CORTICAL BLINDNESS
This is blindness caused by a tumor destroying both occipital lobes at the calcarine fissures. It may occur with a large falx meningioma extending to both sides and compressing the calcarine fissures. Cortical blindness is complete bilateral blindness with preserved pupillary light responses.(10) Convergence when viewing a near object and ocular movements remain normal.
3. SEIZURES
Seizures from an occipital lobe tumor take the form of unformed visual experiences or sudden visual hallucinations, such as flashing lights. These differ from hallucinations due to temporal lobe tumors, which are formed images. Visual hallucinations may be accompanied by eye deviation to the opposite side and are an important localizing manifestation of an occipital lobe tumor.
4. VISUAL AGNOSIA, ALEXIA, AGRAPHIA
A large occipital lobe tumor extending into the peristriate area (area 19) or the parietotemporal region of the dominant hemisphere causes alexia (word blindness), or visual receptive aphasia. Despite intact vision, the patient cannot understand the meaning or significance of written words. Some degree of agraphia, the inability to express thoughts in writing, is also usually present.(12) These manifestations also occur with parietal or temporal lobe tumors, so they alone cannot readily distinguish an occipital tumor from a parietotemporal tumor.
Original pages 268–275
TEMPORAL LOBE
The temporal lobe lies below the Sylvian fissure and rests in the middle cranial fossa. Laterally, the superior, middle, and inferior sulci divide it into the superior, middle, and inferior gyri, respectively. The inferior temporal gyrus lies on the undersurface and is therefore not visible. The superior temporal gyrus forms the operculum of the insula (island of Reil). On the upper surface of its posterior portion is the transverse or Heschl’s gyrus, which serves as the auditory receptive center(15) (Figure 5.1). This center receives the auditory radiation from the medial geniculate body and auditory fibers from both sides (bilateral representation) (Figure 5.7). Destruction of the center on one side therefore does not cause deafness, but impairs sound localization. Bilateral destruction causes deafness. This center connects with other cerebral centers concerned with speech, memory, eye movements, body movements, and so forth. For example, a loud sound causes the eyes and face to turn toward its source.
Color added while retaining the original linework and letteringFigure 5.7. The auditory pathway.
The posterior third of the superior temporal gyrus in the dominant hemisphere is Wernicke’s area (the perceptive speech center) (Figure 5.1). It is concerned with perceiving speech, recognizing words, and understanding and interpreting spoken language. The posterior portions of the middle and inferior temporal convolutions connect with the opposite cerebellum through the temporopontocerebellar pathway. Destruction of this region or pathway produces contralateral ataxia.
The optic radiation passes through the temporal lobe to the occipital lobe (Figures 5.4 and 5.6). On leaving the lateral geniculate body, its fibers run closely together behind the sensory fibers of the internal capsule, forming the optic peduncle, before spreading out. Fibers from the upper retinal quadrant pass upward into the white matter of the parieto-occipital lobe and terminate above the calcarine fissure. Fibers from the lower retinal quadrant pass downward into the temporal lobe and loop anteriorly around the temporal horn of the lateral ventricle, forming Meyer’s temporal loop. They then run posteriorly along the lateral side of the temporal horn, pass the occipital horn, and terminate below the calcarine fissure (Figure 5.8). Destruction of the optic radiation in the temporal lobe produces contralateral homonymous superior quadrantanopia. Irritation produces visual hallucinations with more clearly formed images than those arising from the occipital lobe.
Color added while retaining the original linework and letteringFigure 5.8. The optic radiation terminates in the visual cortex. Fibers from the upper retinal quadrant end above the calcarine fissure, and fibers from the lower retinal quadrant end below it.
Inferomedially, the temporal lobe contains the parahippocampal gyrus, uncus, and amygdala, which projects into the anterior temporal horn. These structures are concerned with learning, recent memory, smell, taste, emotion, and sexual feeling.
Focal Symptoms and Signs of Temporal Lobe Tumors
Patients with temporal lobe tumors usually present when the tumor is large because changes in this region produce few conspicuous signs, particularly in the anterior temporal lobe and the nondominant hemisphere. A tumor in the dominant hemisphere may lead to earlier consultation because speech disturbance often appears first. The focal manifestations are as follows:
1. VISUAL FIELD DEFECT
This is an important manifestation of a temporal lobe tumor. As noted above, fibers from the lower retina loop around the temporal horn as Meyer’s loop. An anterior temporal lobe tumor therefore damages this loop, producing homonymous superior quadrantanopia, a characteristic visual sign of a temporal lobe tumor. As the tumor enlarges posteriorly, it destroys fibers from the upper retina and produces homonymous hemianopia. This is more common than superior quadrantanopia because most patients present with a large tumor. Unlike hemianopia caused by an occipital lobe tumor, the defects in the two eyes differ in a temporal lobe lesion (incongruous homonymous hemianopia). For example, one eye may lose half its field while the other loses only a quadrant. An occipital lobe tumor, by contrast, usually causes complete homonymous hemianopia(13) (Figure 5.6).
2. DYSPHASIA, APHASIA
A tumor in the posterior temporal lobe of the dominant hemisphere, at or near Wernicke’s center, causes sensory dysphasia or aphasia: the patient cannot understand spoken language. An anterior tumor near Broca’s area causes motor dysphasia. A very large tumor may cause global aphasia.
3. UNCINATE FITS AND TEMPORAL LOBE EPILEPSY
A tumor in the medial temporal lobe, at the uncus and parahippocampal gyrus, which are concerned with smell and taste, produces the syndrome called uncinate fits. An attack begins with an unusual smell or taste, usually unpleasant, followed by tasting movements and lip licking. At the same time, the patient stares blankly and appears disconnected from the surroundings. Afterward, the patient describes a dreamlike experience.(14)
Temporal lobe epilepsy, or psychomotor seizure, occurs with a lesion in the medial temporal lobe, involving the uncus, parahippocampal gyrus, amygdala, or their subcortical connections. The patient shows automatisms: unusual movements with an appearance of partial awareness. Some patients abruptly stop their current activity and stare in bewilderment, without jerking or collapsing unconscious. Others may walk a considerable distance without remembering where they went or what they did (amnesia). Some experience illusions or hallucinations involving hearing, smell, or taste, sometimes with chewing or swallowing movements. Some describe a dreamlike state with the feeling that they have seen or experienced the present situation before, termed déjà vu. After a psychomotor seizure, confusion may persist for a time, and some patients fall asleep.(1)
4. MEMORY IMPAIRMENT
A deep medial temporal lobe tumor destroys the hippocampus or its connections, impairing recent memory. With progression, the manifestations may resemble dementia.
5. HALLUCINATIONS
Both visual and auditory hallucinations may occur. Visual hallucinations are relatively clearly formed images, unlike the unformed hallucinations of an occipital lobe tumor, such as flashing lights. With auditory hallucinations, the patient reports a sound in the ear, such as ringing resembling a bell or a whistle.
6. HEMIPARESIS
A large medial temporal lobe tumor displaces the corticospinal tract fibers supplying the opposite facial muscles, which lie laterally, producing contralateral weakness. Compression extending to the internal capsule may cause contralateral hemiparesis (Figure 5.9). A large tumor may also displace the brain stem to the opposite side, pressing the contralateral cerebral peduncle against the edge of the tentorium cerebelli. Hemiparesis may therefore occur on the same side as the tumor. The combination of homonymous hemianopia and hemiparesis is very important in localizing a temporal lobe tumor (Figure 5.10).
Color added while retaining the original linework and letteringFigure 5.9. A large temporal lobe tumor displaces the corticospinal tract and Broca’s center, causing hemiparesis and dysphasia.Color added while retaining the original linework and letteringFigure 5.10. A temporal lobe tumor compresses the corticospinal tract and optic radiation, producing contralateral hemiparesis and homonymous hemianopsia.
7. TRIGEMINAL & OCULOMOTOR NERVE PALSY
The Gasserian ganglion of the trigeminal nerve lies medially in the middle cranial fossa and may be compressed by the tumor, causing ipsilateral facial numbness and loss of the corneal reflex. A tumor may also descend past the tentorial edge and compress the oculomotor nerve adjacent to the uncus, causing ptosis and a dilated pupil unresponsive to light on the same side as the tumor.
8. UNILATERAL EXOPHTHALMOS
This occurs with tumors anterior to the temporal lobe, such as meningiomas of the lesser wing of the sphenoid. They may impair venous drainage from the eye, cause reactive thickening of the orbital wall and narrowing of the orbit, or extend into the orbit. These changes cause proptosis. A more lateral meningioma in this region may cause thickening of the temporal bone, making that temple appear fuller than the opposite one (Figure 6.17).
9. ATAXIA
This is uncommon. It resembles frontal ataxia, with swaying or falling toward the side opposite the tumor. It occurs with tumors in the posterior portions of the middle and inferior temporal gyri that destroy the temporopontocerebellar pathway.(5,16)
Original pages 275–280
THALAMUS AND BASAL GANGLIA
The thalamus is an ovoid nuclear mass near the midline of the brain, at the upper end of the cerebral peduncle. Its anterior medial surface forms the wall of the third ventricle. Its enlarged posterior portion, the pulvinar, lies close to the quadrigeminal plate, pineal gland, and medial and lateral geniculate bodies and serves as a visual association area of the cortex. Together with the caudate nucleus, its superior surface forms the floor of the lateral ventricle. Laterally it adjoins the internal capsule, containing the corticospinal tract connecting the cerebral motor area with lower levels of the central nervous system. Inferiorly, the thalamus rests on the subthalamus and mesencephalic tegmentum. Here fibers ascending from lower levels of the central nervous system enter the thalamus: the spinothalamic tract (pain and temperature), medial lemniscus (touch, vibration, and proprioception), and brachium conjunctivum from the cerebellum.
The thalamic nuclei are divided into midline, anterior, medial, lateral, and posterior groups. The lateral nuclei are further divided into a large ventral and a smaller dorsal group. An important nucleus in the posterior ventral group is the nucleus ventralis posterior, where sensory pathways terminate. The secondary trigeminal sensory pathway carries facial sensation to the nucleus ventralis posteromedialis, while spinothalamic and medial lemniscal fibers terminate in the nucleus ventralis posterolateralis. Cells in these two nuclei send fibers to the postcentral gyrus.(17) A lesion of the lateral thalamic nucleus causes contralateral sensory loss. In some patients, intractable pain also occurs in the affected body parts, termed thalamic syndrome. Even a slight stimulus in the region of sensory loss produces severe pain, often with an emotional response. This phenomenon is not yet satisfactorily explained.(17)
The internal capsule is another clinically important structure. It consists of fibers entering and leaving the cerebral cortex, with the thalamus and caudate nucleus medially and the lenticular nucleus (globus pallidus and putamen) laterally. Most of the internal capsule consists of the thalamic radiation, fibers passing from the thalamus to the cerebral cortex.(18) The remainder consists of efferent cortical fibers descending to the brain stem and spinal cord: the corticospinal, corticobulbar, and corticopontine tracts, together with small groups of fibers to the hypothalamus, substantia nigra, and red nucleus. Below the thalamic level, the internal capsule becomes the crus cerebri or cerebral peduncle of the midbrain.
On horizontal section (Figure 5.11), the internal capsule has anterior and posterior limbs meeting at an angle at the genu. The anterior limb contains the anterior thalamic radiation and prefrontal corticopontine tract. The genu contains corticobulbar and corticoreticular fibers. The posterior limb contains the corticospinal tract, frontopontine fibers, and superior thalamic radiation carrying somatic sensation to the postcentral gyrus. The superior thalamic radiation lies posterior to the corticospinal tract.(18)
Color added while retaining the original linework and letteringFigure 5.11. Components of the internal capsule.
In this region, the geniculocalcarine tract leaves the lateral geniculate body, passes posteriorly and inferior to the internal capsule, and spreads out as the optic radiation to the calcarine (striate) cortex, area 17, of the occipital lobe. The medial geniculate body gives rise to the auditory radiation, which runs near the geniculocalcarine tract behind the internal capsule to the temporal auditory cortex. These two groups of fibers are important in localizing lesions, as discussed below.
The BASAL GANGLIA comprise gray matter in the caudate nucleus, lenticular nucleus (globus pallidus and putamen), amygdaloid nuclei, and claustrum. The lenticular nucleus is separated from the caudate nucleus by the anterior limb of the internal capsule and from the thalamus by the posterior limb. The basal ganglia connect with many other structures and perform several functions, summarized as follows:(19)
i) They are important in voluntary movement. Together with the precentral motor cortex, the basal ganglia can produce useful muscular activity even when the corticospinal fibers from this cortex are lost.
ii) They participate in many automatic and associated movements.
iii) They inhibit postural reflexes, as demonstrated by the muscular rigidity produced by basal ganglia lesions.
iv) They inhibit motor centers. Destruction of the basal ganglia produces abnormal involuntary movements: choreoathetosis with damage to the caudate nucleus and putamen; intention tremor with damage to the dentorubrothalamic pathway; resting tremor with damage to the globus pallidus and substantia nigra; and hemiballismus with damage to the subthalamic nucleus of Luys.
Focal Symptoms and Signs of Tumors of the Thalamus and Basal Ganglia
Because the thalamus and basal ganglia lie very close together, lesions in these regions produce similar manifestations and are discussed together. Tumors are uncommon here, but symptoms often appear relatively early because of the proximity of motor structures (the corticospinal tract) and sensory pathways (Figure 5.12). A tumor arising in one of these regions may extend into the other.
Color added while retaining the original linework and letteringFigure 5.12. A thalamic tumor destroys the thalamus, internal capsule, sensory pathway, optic radiation, and superior colliculus.
Thalamus
Internal capsule
Superior colliculus
Medial geniculate body
Lateral geniculate body
Optic radiation
Auditory radiation
The manifestations of tumors in this region are as follows:
1. HEMIHYPESTHESIA OR HEMIANESTHESIA
There is numbness on the side opposite the tumor, with impairment of all sensory modalities, due to destruction of thalamic nuclei and all types of sensory fibers entering the thalamus. With a tumor originating in the thalamus, sensory symptoms precede weakness. With a basal ganglia tumor, hemiplegia usually precedes numbness because the sensory fibers lie posterior to the basal ganglia. The author has not encountered thalamic syndrome caused by a tumor.
2. HEMIPLEGIA
This is common in tumors of the thalamus and basal ganglia and usually appears early. Because of its proximity, the corticospinal tract in the internal capsule is destroyed relatively early. A basal ganglia tumor usually presents first with hemiplegia, which is spastic.
3. HOMONYMOUS HEMIANOPIA
This occurs when the tumor compresses the lateral geniculate body or the optic radiation passing below and behind the thalamus and internal capsule.
4. UPWARD CONJUGATE GAZE PALSY AND ANISOCORIA
The tumor grows to compress the upper midbrain, including the quadrigeminal plate (superior and inferior colliculi) and pretectal area. As the superior colliculus is the upward gaze center, the patient cannot look upward. The pretectal area is where pupillary fibers from the optic nerve synapse; compression causes unequal pupils with poor light responses.
5. ATAXIA
Contralateral incoordination may result from destruction of the nucleus ventralis lateralis, where fibers from the cerebellum through the brachium conjunctivum (superior cerebellar peduncle) terminate, together with loss of proprioceptive sensation in the thalamus. This ataxia is uncommon and usually appears late in the disease.
Tremor and abnormal involuntary movements, such as choreoathetosis or hemiballismus, are very rarely caused by a tumor.
6. MENTAL SYMPTOMS
Although not specific to this region, mental symptoms may occur with a thalamic tumor. Destruction of the thalamus and subthalamus produces drowsiness, excessive sleep, mental dullness, and memory impairment.(7) These may also reflect associated raised intracranial pressure. Because the thalamus lies next to the third ventricle, a tumor here may obstruct cerebrospinal fluid circulation relatively early.
Original pages 280–283
CORPUS CALLOSUM
The corpus callosum is the largest commissural fiber bundle connecting different regions of the two cerebral hemispheres. It has four parts: the rostrum, genu, body, and splenium (Figure 5.13). It forms the roof of the anterior horn and body of the lateral ventricle. Fibers passing anteriorly through the genu to the two frontal poles are called the anterior forceps; those passing through the splenium to the two occipital lobes are the posterior forceps. Other fibers passing through the body connect cortical centers in the frontal, parietal, and temporal lobes (Figure 5.14). The corpus callosum enables functional communication between the hemispheres, allowing the various cortical centers to function fully. Its destruction causes different disconnection syndromes according to the part damaged.(20) If the splenium is destroyed, for example, only visual communication is lost. A clear example is occlusion of the left posterior cerebral artery, causing infarction of the occipital lobe and splenium. The patient has right homonymous hemianopia and cannot read. Because the left occipital lobe is damaged, the speech center must receive visual information from the right occipital lobe, but this information cannot reach the left angular gyrus. Destruction of the corpus callosum anterior to the splenium, as with anterior cerebral artery occlusion, disconnects tactile perception and language between the hemispheres. With the eyes closed, the patient cannot compare objects held in the two hands. On verbal command, the right hand performs a task correctly but the left hand cannot. For example, writing to dictation with the left hand produces unformed, illegible writing, while the right hand writes normally.(20)
Color added while retaining the original linework and letteringFigure 5.13. Medial view of the right cerebral hemisphere, showing the parts of the corpus callosum and their relationships to adjacent structures.Color added while retaining the original linework and letteringFigure 5.14. Fibers in the corpus callosum (from Correlative Anatomy of the Nervous System by Crosby, Humphrey, and Luer).
Along the midline, the cingulate gyrus and anterior cerebral arteries lie above the corpus callosum throughout its length. Below it, the septum pellucidum adjoins the corpus callosum at the level of the anterior horn of the lateral ventricle, and the fornix lies below its body.
Several important structures lie below the splenium: the internal cerebral vein, great vein of Galen, pineal gland, quadrigeminal plate, and midbrain aqueduct of Sylvius. These structures account for the syndromes discussed below.
Symptoms and Signs of Corpus Callosum Tumors
Tumors in this region are very uncommon, and clearly defined focal manifestations are difficult to identify. They usually present with dysfunction of neighboring brain invaded by the tumor, or arise in nearby brain and extend into the corpus callosum and then the opposite hemisphere. Thus, manifestations of a corpus callosum tumor are essentially those of dysfunction in neighboring brain and depend on the adjacent hemispheric region. A tumor of the body produces weakness and numbness of both legs because the leg motor cortex lies medially in the frontal lobe. A tumor of the splenium (Figure 5.15) compresses the quadrigeminal plate, pretectal area, and aqueduct of Sylvius, producing manifestations resembling a pineal tumor or Parinaud’s phenomenon. The patient cannot look upward (upward conjugate gaze palsy) because the upward gaze center in the superior colliculus is impaired. Both pupils are dilated and respond poorly to light. Raised intracranial pressure also develops early because the aqueduct is compressed. A tumor of the genu or rostrum may extend into both frontal lobes, producing the previously described manifestations of a prefrontal tumor: personality change and progressive dementia. A corpus callosum tumor should therefore always be considered when dementia is prominent.
Color added while retaining the original linework and letteringFigure 5.15. A tumor of the splenium of the corpus callosum compresses the superior colliculus, pretectal area, and aqueduct of Sylvius.
Original pages 283–284
LATERAL VENTRICLE
Lateral ventricular tumors are uncommon. Symptoms and signs generally do not appear until the tumor is very large, because the ventricle is a cerebrospinal fluid-filled cavity in which a tumor can grow without compressing brain tissue or producing a focal deficit. The lateral ventricle is therefore another silent area. When the tumor becomes large, the conspicuous symptoms are those of raised intracranial pressure—headache, blurred vision, and vomiting—which bring the patient to medical attention. In cases where the tumor obstructs cerebrospinal fluid circulation or produces cerebrospinal fluid, as with a choroid plexus papilloma, presentation with raised intracranial pressure occurs relatively early. Some patients have intermittent severe headaches due to a ball-valve action of the tumor. In certain head positions, the tumor blocks cerebrospinal fluid flow, greatly increasing intracranial pressure and causing severe headache. In another position, the tumor may move and allow fluid to pass, relieving the raised pressure and headache; the symptoms may recur. This pattern is important in diagnosing an intraventricular tumor. If the tumor causes hydrocephalus and enlargement of the lateral ventricles, the patient may also present with bilateral leg weakness because corticospinal fibers from the leg motor cortex run close to the lateral ventricular wall and are compressed (Figure 5.20).
A tumor arising from the lateral ventricular wall may grow into the ventricle and also extend into adjacent brain tissue, causing focal deficits determined by its location. A tumor in the body of the lateral ventricle may cause contralateral hemiparesis and hemihypesthesia by compressing the corticospinal and sensory tracts. A tumor in the occipital horn may cause homonymous hemianopia by destroying the optic radiation, which runs close to the wall of the lateral ventricular occipital horn.
Original pages 284–292
HYPOTHALAMUS
The hypothalamus lies in the wall of the third ventricle below the hypothalamic sulcus. Its anteroinferior aspect adjoins the optic chiasm and optic tract. Behind the optic chiasm, the infundibulum on the inferior surface of the hypothalamus extends downward to join the hypophysis as the pituitary stalk (Figure 5.16). The portion forming the floor of the third ventricle is called the median eminence and is divided into two parts. The portion anterior to the infundibulum is the anterior median eminence, and the portion posterior to it is the posterior median eminence. The median eminence is the final important part of the hypothalamus that converts the pathway of the central venous system into the peripheral endocrine system. The arterial capillaries of the hypophyseal portal vessels, beginning at the median eminence, collect blood from this area containing both releasing and inhibitory hormones from the hypothalamus and convey it to the target cells of the anterior pituitary gland.(21)
Color added while retaining the original linework and letteringFigure 5.16 Medial aspect of the right cerebral hemisphere, showing the hypothalamus and its relationship to neighboring structures.
Within the hypothalamus, groups of cells form several hypothalamic nuclei. The supraoptic region contains the paraventricular, supraoptic, anterior hypothalamic, and suprachiasmatic nuclei. The paraventricular and supraoptic nuclei are readily distinguishable; both send fibers to the posterior lobe of the hypophysis. The tuberal region also contains several nuclei: the ventromedial, dorsomedial, arcuate, posterior hypothalamic, and mamilloinfundibular nuclei.
The hypothalamus exerts most of its influence on the pituitary gland through the supraopticohypophyseal and tuberohypophyseal tracts. The supraopticohypophyseal tract consists of fibers from the supraoptic and paraventricular nuclei passing to the posterior lobe of the pituitary gland, where oxytocin and antidiuretic hormone are released. This region is important because it is concerned with the body’s fluid balance. Its destruction causes diabetes insipidus; therefore, great care must be taken to avoid damaging it during surgery for tumors in this region. The tuberohypophyseal tract begins in the tuberal area and passes to the median eminence and infundibular system. Together with the hypophyseal portal system, it links the nervous and hormonal systems, connecting the hypothalamus with the anterior pituitary gland. Destruction of the tuberal area causes abnormalities of carbohydrate and fat metabolism, resulting in hyperglycemia and adiposogenital syndrome.(22)
Lesions destroying the anterior hypothalamic nuclei cause hyperthermia accompanied by sweating, vasodilatation, and rapid, deep breathing—mechanisms that lower body temperature—as well as emaciation. Lesions destroying the posterior hypothalamic nuclei cause hypothermia accompanied by mechanisms attempting to conserve body temperature, including vasoconstriction and shivering to generate heat. Abnormalities of the posterior hypothalamic nuclei also cause excessive sleep (hypersomnia).
Color added while retaining the original linework and letteringFigure 5.17 Coronal section of the brain showing the hypothalamus.
The medial hypothalamus controls satiety, whereas the lateral hypothalamus controls the desire to eat. Abnormalities of the medial hypothalamus cause marked obesity, while abnormalities of the lateral hypothalamus cause loss of appetite.
Although the hypothalamus is very small compared with other parts of the brain, its functions are essential to survival. It continually regulates and adjusts the body’s internal balance in response to changes both inside and outside the body through three important systems:(23)
1. The endocrine system. The hypothalamus directly controls the pituitary gland and indirectly controls the body’s other endocrine glands. It secretes various releasing hormones (factors) that stimulate the pituitary gland to release the corresponding hormones, or secretes inhibitory hormones (factors) to suppress excessive production of pituitary hormones. In this way, it maintains the hormonal balance required for normal life. The hypothalamus thus plays an important role in controlling all the endocrine glands, including the pituitary, thyroid, pancreas, adrenal glands, and gonads.
2. The autonomic nervous system (ANS). The hypothalamus keeps the functions of all the body’s visceral organs within normal limits through reflexes passing to parasympathetic and sympathetic cells in the brainstem and at various levels of the spinal cord. It therefore regulates the cardiovascular, respiratory, and gastrointestinal systems, body temperature, sweat glands, sexual organs, and other functions.
The anterior and medial hypothalamic nuclei, together with the tuber cinereum, control parasympathetic activity. The posterior and lateral hypothalamic nuclei are concerned with sympathetic activity.(24)
3. The limbic system. This system is important in emotion, protective responses, and memory, through connections with the hippocampus, uncus, anteromedial thalamus, and amygdala.
The hypothalamus also communicates with the tegmentum of the midbrain, an important region concerned with consciousness.
The hypothalamus therefore controls the anterior and posterior pituitary glands, body temperature, water balance, food intake, consciousness, sleep, emotion, behavior, and the autonomic nervous system. Abnormalities or tumors of the hypothalamus may produce the following manifestations:(25)
1.3 Body temperature varying with the external temperature (poikilothermia)
2. Abnormalities of food intake
2.1 Reduced or absent appetite (anorexia)
2.2 Reduced food intake (hypophagia)
2.3 Absence of food intake (aphagia)
3. Abnormalities of drinking
3.1 Persistent excessive drinking
3.2 No drinking or reduced drinking
3.3 Essential hypernatremia
4. Abnormalities of sleep and consciousness
4.1 Excessive sleepiness (hypersomnia)
4.2 Insomnia
4.3 Absence of movement and speech (akinetic mutism)
4.4 Unconsciousness (coma)
5. Autonomic nervous system abnormalities
5.1 Pulmonary edema
5.2 Cardiac arrhythmia
5.3 Gastrointestinal disturbance
5.4 Sphincter disturbance
6. Abnormalities of caloric balance
6.1 Obesity
6.2 Emaciation
7. Emotional abnormalities
7.1 Anger
7.2 Fear
7.3 Emotional indifference or listlessness (apathy)
8. Sexual abnormalities
8.1 Hypogonadotropic hypogonadism
8.2 Precocious puberty
9. Memory impairment
Symptoms and signs of hypothalamic tumors
As described above, the hypothalamus is very small and contains many closely adjacent groups of nuclei with different functions. It is therefore difficult to identify the precise point at which a tumor originated. Most patients seek medical attention only after the tumor has become large. The findings then represent a combination of hormonal abnormalities, metabolic abnormalities, and loss of function of neural structures neighboring the hypothalamus, including the optic nerves and chiasm, other cranial nerves, cerebral peduncle, pituitary gland, and cerebrospinal fluid pathways. The manifestations vary according to the tumor’s location within the hypothalamus and the patient’s age.
With respect to age, experience has shown different manifestations in younger and older children even when tumors occupy the same location. For example, an anterior hypothalamic tumor may cause emaciation in a young child but abnormal obesity in an older child. This difference remains unexplained.
Anterior hypothalamic tumors cause failure to thrive or the diencephalic syndrome(26,27) in young children. The patient is emaciated (Figure 5.18), has no subcutaneous fat, and fails to gain weight despite eating well. Some have nausea and vomiting. The child is usually alert and cheerful despite a sickly appearance. These manifestations are generally absent in older children, for reasons that remain unexplained. Visual abnormalities are common, with optic atrophy resulting from compression of the nearby optic chiasm. Impaired vision produces searching nystagmus as the patient moves the eyes in an attempt to find an object to look at. In older children, tumors in this region commonly cause obesity together with diabetes insipidus and visual field defects. Excessive urination and impaired thirst mechanisms may cause dehydration, serum hyperosmolarity, and hypernatremia.(28) Some patients also have persistently elevated body temperature.
Figure 5.18 Emaciation in a child with an anterior hypothalamic tumor.
Tumors in the posterior hypothalamic region, including the tuber cinereum and median eminence, produce precocious puberty (Figure 5.19). The child’s body and bones grow rapidly, the penis becomes adult-sized, pubic hair appears, and both testes enlarge. These changes occur because the tumor destroys the part of the hypothalamus that suppresses secretion of gonadotropic substance,(29) resulting in excessive gonadotropin secretion. Upward extension of the tumor causes excessive sleeping or, in some cases, impaired consciousness.
Some hypothalamic tumors also produce several of the other abnormalities described above. Downward extension into the interpeduncular fossa may impair the oculomotor and abducens nerves and produce corticospinal tract signs. Some patients develop raised intracranial pressure because the tumor obstructs cerebrospinal fluid pathways in the third ventricle and foramen of Monro.
Figure 5.19 Precocious puberty in a patient with a posterior hypothalamic tumor.
In summary, a hypothalamic tumor should be suspected in patients with diencephalic syndrome or precocious puberty accompanied by visual field defects and optic atrophy. Radiological investigation with CT or MRI should be undertaken.
Original pages 292–295
THIRD VENTRICLE
The third ventricle lies in the midline of the brain (Figures 5.16 and 5.17). The anterior portions of its lateral walls are formed by the hypothalamus and the posterior portions by the thalamus. Its anterior boundary consists of the lamina terminalis and anterior commissure. Inferiorly, the pituitary stalk connects the base of the third ventricle with the pituitary gland, with the optic chiasm anterior to the stalk. Behind the third ventricle lie the midbrain and the pineal gland, which rests above the superior colliculus. Above the third ventricle are the tela choroidea, fornix, and internal cerebral veins. The third ventricle communicates with both lateral ventricles through the foramina of Monro. Cerebrospinal fluid leaves it through the aqueduct of Sylvius, beneath the quadrigeminal plate of the midbrain. The third ventricle is an important region because it is surrounded by vital structures, including the hypothalamus, pituitary gland, optic chiasm and other cranial nerves, and cerebral blood vessels. It is also small and deeply situated, making surgical access to tumors difficult. As in other ventricles, tumors in this region may arise within the ventricular cavity itself (intraventricular), or arise in the ventricular wall or neighboring region and grow into the third ventricle (paraventricular). The latter produce manifestations attributable to those structures and will not be discussed here; only tumors within the ventricle are considered.
Localizing manifestations of third ventricular tumors
Tumors in this region do not produce specific localizing symptoms. Most manifestations result from raised intracranial pressure. Tumors in the anterior third ventricle commonly obstruct CSF flow at the foramen of Monro, causing obstructive hydrocephalus. Patients have severe headache, vomiting, blurred vision, and papilledema. A colloid cyst originating near the foramen of Monro often produces a distinctive presentation: intermittent severe headache, vomiting, weakness of both legs, inability to stand, and possible collapse to the ground. Some patients become drowsy or unconscious. When the head assumes another position, however, the symptoms disappear immediately. This is explained by the cyst obstructing CSF flow in one position, causing acute obstructive hydrocephalus. A change in head position displaces the cyst, opening the foramen of Monro and allowing CSF to pass; the headache and other symptoms then disappear. Some patients develop dementia, possibly from compression and destruction of the fornix, septum pellucidum, hypothalamus, and memory pathways, or from raised intracranial pressure. Some also present with weakness of both legs because the enlarged lateral ventricles compress the corticospinal tract fibers to the legs, which lie close to their lateral walls (Figure 5.20).
Color added while retaining the original linework and letteringFigure 5.20 A tumor within the third ventricle obstructs the foramen of Monro, producing hydrocephalus and compression of the corticospinal tract, resulting in paraparesis.
Large tumors in the anterior third ventricle (Figure 5.21) compress the hypothalamus and the base of the third ventricle. Patients develop the manifestations of hypothalamic dysfunction described above, including marked obesity, excessive sleep, drowsiness, diabetes insipidus, failure to thrive, and autonomic and endocrine abnormalities. Large tumors extending downward compress the optic chiasm and cause visual field defects.
Tumors in the posterior third ventricle (Figure 5.21) compress the quadrigeminal plate and obstruct CSF flow at the aqueduct of Sylvius, producing Parinaud’s phenomenon. The patient cannot look upward; both pupils are dilated, with absent or diminished light reactions. This occurs because the superior collicular region is the center for upward conjugate gaze, while the pretectal area just anterior to the superior colliculus is the center for the pupillary light reflex. Tumor compression impairs these functions. Raised intracranial pressure from obstruction of CSF flow is regularly associated, producing headache, papilledema, and vomiting. At this stage, tumors in this part of the ventricle are difficult to distinguish from tumors of the pineal gland or quadrigeminal plate itself. In some patients, marked enlargement of the third ventricle from aqueductal obstruction impairs hypothalamic function and causes bitemporal hemianopia through compression of the optic chiasm.
Color added while retaining the original linework and letteringFigure 5.21 Tumors within the third ventricle.
An anterior third ventricular tumor causes hypothalamic dysfunction, visual field defects, and hydrocephalus.
A posterior third ventricular tumor causes Parinaud’s phenomenon and obstructive hydrocephalus.
Original pages 295–309
PITUITARY GLAND
The pituitary gland lies in the sella turcica and is connected to the hypothalamus above by the pituitary or infundibular stalk. The stalk passes through an opening in the diaphragma sellae, a sheet of dura mater stretched between the clinoid processes that separates the pituitary gland from CSF in the basal cistern. In some individuals, this opening is large enough to allow the suprasellar arachnoid and CSF to protrude into the pituitary fossa, producing the abnormality known as empty sella syndrome.
Color added while retaining the original linework and letteringFigure 5.22 Parts of the pituitary gland and the hypothalamic–hypophyseal tract.
The pituitary gland (Figure 5.22) comprises the adenohypophysis and neurohypophysis. The adenohypophysis, or anterior lobe of the pituitary gland, also called the pars distalis, develops from Rathke’s pouch, an upward extension of the primitive stomodeum toward the neural tube. Cells of Rathke’s pouch form the craniopharyngeal duct. At about 12 weeks of gestation, the proximal part of this duct disappears, eliminating its connection with the buccal cavity. Subsequently, the distal portion of the anterior wall of Rathke’s pouch becomes the pars distalis; 90–95% of this portion becomes the adult anterior pituitary gland. The posterior wall becomes the pars intermedia, adjacent to the posterior lobe of the pituitary gland. A group of anterior lobe cells also extends upward in front of the pituitary stalk to form the pars tuberalis.
The neurohypophysis, or posterior lobe of the pituitary gland, develops from the diencephalic portion of the neural tube at the floor of the third ventricle. A pouch grows downward to form the infundibulum. Its upper portion fuses to become the pituitary stalk, while its distal portion enlarges to form the posterior pituitary lobe, or neurohypophysis.
Two principal arteries supply the hypophysis: the superior and inferior hypophyseal arteries. The superior hypophyseal artery arises from the internal carotid artery. After crossing the diaphragma sellae, it passes toward the pituitary stalk and divides into anterior and posterior branches supplying the median eminence and upper infundibulum. A large branch, the trabecular artery, runs along the anterior aspect of the pituitary stalk and enters the pars distalis superiorly. Within the pars distalis, it does not supply the glandular tissue of the anterior lobe but passes through connective-tissue trabeculae to supply the infundibular stem.(29) The inferior hypophyseal artery arises from the intracavernous internal carotid artery. On reaching the hypophysis, it divides into medial and lateral branches that join their counterparts on the opposite side to form a ring around the pars nervosa (posterior lobe). It supplies the pars nervosa and infundibulum.
The arteries supplying the median eminence and infundibular stem terminate in capillary tufts. In humans, blood from these capillary plexuses enters larger vessels on the anterosuperior surface of the pituitary stalk and then reaches sinusoids in the pars distalis of the adenohypophysis. The vessels carrying blood from the capillaries of the median eminence and infundibulum to the sinusoids in the pars distalis are collectively called the hypophyseal portal vessels.(29)
Many important structures surround the sella turcica. A large pituitary tumor may damage them and produce detectable manifestations, so they warrant description here. These structures include the optic nerves, optic chiasm, and hypothalamus above the sella turcica, and the cavernous sinuses, third, fourth, fifth, and sixth cranial nerves, internal carotid arteries, and temporal lobes lateral to the sella (Figure 5.23).
Color added while retaining the original linework and letteringFigure 5.23 Superior view showing the pituitary gland and its relationship to parasellar structures.
Optic nerves and optic chiasm. The right and left optic nerves pass through the optic foramina medial to the anterior clinoid processes, run backward, and unite in the midline to form the optic chiasm. The chiasm lies above the pituitary gland and diaphragma sellae, with the pituitary stalk behind it. From the chiasm, the optic tracts pass below and lateral to the cerebral peduncles toward the lateral geniculate bodies. The optic chiasm forms the anteroinferior wall of the third ventricle. Above it lie the lamina terminalis, anterior commissure, and third ventricle; behind it lie the pituitary stalk, tuber cinereum, mammillary bodies, and oculomotor nerves. Because the optic nerves and chiasm are closely related to other structures in this region, most patients with tumors here present with visual abnormalities. Pituitary tumors in particular produce characteristic visual field defects, discussed below.
Color added while retaining the original linework and letteringFigure 5.24 Cross-section of the cavernous sinus showing cranial nerves III, IV, V₁, and V₂, all within a sheath in its lateral wall. Cranial nerve VI lies close to the internal carotid artery.
Cavernous sinus. The cavernous sinus lies lateral to the sphenoid sinus, sella, and pituitary gland, extending from the superior orbital fissure to the apex of the petrous temporal bone. It communicates with and receives blood from the orbit through the superior and inferior ophthalmic veins, and communicates with the cerebral hemisphere through the sphenoparietal sinus and middle cerebral veins. The two cavernous sinuses communicate through anterior and posterior intercavernous sinuses. Blood drains through the superior petrosal sinus into the transverse sinus, through the inferior petrosal sinus into the jugular bulb, and also through the basilar and pterygoid plexuses.
The lateral wall of the cavernous sinus contains several cranial nerves. From superior to inferior, these are the oculomotor nerve (III), trochlear nerve (IV), and ophthalmic (V₁) and maxillary (V₂) divisions of the trigeminal nerve. Within the trabeculae of the cavernous sinus lies the internal carotid artery, closely accompanied by the abducens nerve (VI), with sympathetic fibers surrounding the artery (Figure 5.24).
The cavernous sinus is important to surgeons operating on the pituitary gland or tumors in this region because its medial wall may tear and bleed. Furthermore, some tumors extend into the cavernous sinus, making surgical removal of that portion impossible.
Internal carotid artery. The artery passes through the foramen lacerum and enters the cavernous sinus, running forward and upward before emerging from its superior aspect near the anterior clinoid process. Immediately after leaving the cavernous sinus, it gives off the ophthalmic artery to supply the optic nerve, retina, and orbital structures. The internal carotid artery lies inferolateral to the optic nerve and chiasm and runs obliquely laterally. At the beginning of the Sylvian fissure, it divides into the anterior and middle cerebral arteries. The middle cerebral artery follows the Sylvian fissure, while the anterior cerebral artery passes medially above the optic nerve and chiasm and joins its counterpart through the anterior communicating artery. As the anterior cerebral artery crosses the optic nerve and chiasm, it gives off small branches supplying their superior surfaces; their inferior surfaces receive blood from the posterior communicating artery. The anterior cerebral artery is therefore closely related to the optic nerve, chiasm, diaphragma sellae, pituitary gland, pituitary stalk, and hypothalamus, and its position changes when tumors arise in these structures.
Temporal lobe. The anterior medial portion of the temporal lobe, called the uncus, lies close to the cavernous sinus and cranial nerves. A sellar tumor may extend to compress this part of the temporal lobe and produce temporal lobe epilepsy.
Frontal lobe. The posterior basal portion of the frontal lobe lies above the anterior cerebral artery, optic nerve, chiasm, and pituitary gland. A sellar or parasellar tumor extending upward may compress the frontal lobe and olfactory nerve, producing frontal lobe manifestations and anosmia (loss of smell). Seizures may occur in some patients.
Symptoms and signs of tumors in the pituitary region
Based on the anatomy described above, the manifestations of tumors in this region may be divided into two groups.
General manifestations caused by tumor extension and compression of the brain and cranial nerves in this region (mass effect).
Specific manifestations of pituitary tumors consist of various hormonal abnormalities (endocrinopathies) caused by tumors of pituitary cells. Both hyperpituitarism and hypopituitarism may occur.
A. General symptoms and signs
Most manifestations result from tumor compression of structures surrounding the sella: the optic nerve, chiasm, optic tract, hypothalamus, third, fourth, fifth, and sixth cranial nerves, cavernous sinus, pituitary gland, brain tissue, and ventricular system. Not all manifestations of dysfunction in these structures necessarily occur. They depend on the tumor’s size, location, and direction of extension, which determine the structures compressed. Those nearest the tumor lose function first, and other symptoms gradually develop. In the author’s experience, visual abnormalities are the most common presentation of lesions in this region.
1. Visual abnormalities. Pituitary tumors and other tumors, such as craniopharyngiomas, arising in the sella and extending upward compress the optic nerves and chiasm, causing loss of visual acuity and visual fields. Fundoscopy reveals primary optic atrophy, and the visual field defect is bitemporal hemianopia, a localizing manifestation of tumors in this region and an important diagnostic feature. Some patients presenting early have bitemporal superior quadrantanopia; with time, the inferior temporal quadrants are also lost. This results from compression of the fibers crossing at the optic chiasm (Figure 5.6.2). Later, the tumor also destroys the uncrossed fibers, causing loss of the inferior nasal fields followed by the superior nasal fields. Eventually, both eyes become blind. In some patients, the tumor grows toward the junction of one optic nerve with the chiasm and causes a junctional scotoma (Figure 5.6.3), comprising an ipsilateral central scotoma from compression of that optic nerve and contralateral superior temporal quadrantanopia from compression of inferior nasal fibers arriving from the opposite optic nerve.(31)
Many other patterns of visual loss may occur, depending on the part of the visual pathway damaged. Blindness in one eye with temporal hemianopia in the other indicates extension from the chiasm to damage the optic nerve or optic tract on the blind side. The blind eye is always on the side toward which the tumor has extended. This pattern may also occur with extrasellar tumors, such as meningiomas of the tuberculum sellae or medial sphenoidal ridge.
2. Hypothalamic and pituitary dysfunction. Sellar tumors, whether arising within the pituitary gland or from other tissues in the sella, grow to compress the gland, pituitary stalk, and suprasellar hypothalamus, producing various hormonal abnormalities. In addition to controlling both anterior and posterior pituitary lobes, the hypothalamus regulates fluid balance, temperature, emotion, sleep, behavior, consciousness, and autonomic function. Its manifestations have been described in detail in the section on hypothalamic tumors. Destruction of the pituitary gland and stalk produces hypopituitarism of varying severity, depending on how much of the gland is lost and which hormones are deficient. Large nonfunctioning pituitary tumors, whose cells do not secrete hormones, or large intrasellar craniopharyngiomas commonly destroy the functions of the various pituitary cells, causing panhypopituitarism with reduced pituitary trophic hormones, including growth hormone, gonadotropin, TSH, ACTH, and ADH. Patients lose weight and appear pale. Gonadotropic hormone deficiency causes loss of sexual desire. Women have absent milk secretion and menstruation, with uterine and vaginal atrophy. Men develop testicular atrophy and absence of sperm, with absent or diminished erections and loss of axillary and pubic hair. Thyrotropic hormone deficiency causes hypothyroidism resembling myxedema: swollen eyelids, dry wrinkled skin, dry brittle nails and hair, bradycardia, constipation, hoarseness, mental changes, and cold intolerance.
Loss of adrenocortical function causes weakness, a tendency to hypoglycemia, nausea and vomiting, and hypotension. Complete loss of adrenal function produces shock and unconsciousness.
Growth hormone deficiency before puberty causes dwarfism and hypoglycemia.
The manifestations of functioning pituitary tumors are discussed below.
3. Cranial nerve abnormalities. The cranial nerves involved in this region are II, III, IV, VI, and V. Most patients with pituitary tumors have visual abnormalities from compression of the optic nerves and chiasm, which are the principal symptoms prompting medical consultation. Most present before the tumor extends to compress other cranial nerves. Consequently, pituitary tumors only rarely produce dysfunction of cranial nerves III, IV, VI, and V. When a large tumor extends beyond the sella into the parasellar region, it may impair these nerves, producing strabismus, diplopia, pupillary dilatation, ptosis, facial pain, and related manifestations.
4. Obstructive hydrocephalus and raised intracranial pressure. These result from suprasellar tumor extension compressing the hypothalamus and obstructing the foramen of Monro at the third ventricle. Late in the disease, patients develop manifestations of raised intracranial pressure, including headache and vomiting. Blurred vision due to papilledema is absent because tumor compression has already caused primary optic atrophy and visual loss. Eventually, consciousness progressively deteriorates. The obstruction must be relieved by tumor removal or CSF diversion with a shunt.
Headache may result from raised intracranial pressure, compression of pain-sensitive structures in this region, or both. Pituitary tumor patients commonly have retro-orbital pain due to pressure on the diaphragma sellae, which is supplied by the ophthalmic division of the trigeminal nerve.
Vomiting is uncommon with tumors in this region unless hydrocephalus is severe.
5. Compression of surrounding brain tissue. A large tumor may extend to compress the frontal lobe, temporal lobe, or brainstem (Figure 3.116). Frontal extension produces personality changes, memory impairment, and anosmia from olfactory nerve compression. Irritation of either the frontal or temporal lobe may cause seizures.
6. Rarely, downward tumor extension produces a nasopharyngeal mass and CSF rhinorrhea.
B. Specific symptoms and signs of pituitary tumors
Pituitary tumors produce manifestations of excessive hormone secretion (endocrinopathy), according to the type of tumor cell. The pituitary gland contains three cell types: chromophobe, acidophilic, and basophilic cells, each secreting different hormones. A tumor of a particular cell type therefore produces manifestations of excess hormone from those cells, while compressing the other cell types and reducing their hormone secretion.
Historically, pituitary tumors were classified by cytoplasmic staining as chromophobe, acidophilic, or basophilic adenomas. Chromophobe adenomas were considered nonsecretory and therefore not responsible for hormonal abnormalities; acidophilic adenomas were considered growth hormone-producing, and basophilic adenomas ACTH-producing. Because staining characteristics do not correlate with hormone-secretory capacity, this classification has been abandoned in favor of classification by the endocrine function of the tumor cells.(32) This approach is appropriate because circulating hormone levels can be measured.
Classification of pituitary adenomas by endocrine function is as follows:
Growth hormone - secreting adenoma
Prolactin - secreting adenoma
ACTH - secreting adenoma
TSH - secreting adenoma
FSH- and LH-secreting adenoma
Plurihormonal adenoma
Adenoma with no apparent hormonal function
1. Growth hormone-secreting adenoma. This tumor of acidophilic cells secretes growth hormone, causing gigantism (Figure 5.25) when it develops in a child before epiphyseal closure, or acromegaly when it develops in an adult. The patient becomes large in all parts of the body (Figure 5.26). Associated abnormalities include hypertension, heart disease, diabetes mellitus, pulmonary disease, and back and joint pain due to peripheral nerve compression.
Figure 5.25 Gigantism in a 14-year-old patient with a pituitary acidophilic adenoma, compared with a child of the same age.Figure 5.26 Acromegaly in a patient with a pituitary acidophilic adenoma (growth hormone-secreting adenoma).
2. Prolactin-secreting adenoma (prolactinoma). This is the most common pituitary tumor. Its manifestations result from excessive prolactin secretion by tumor cells, producing hyperprolactinemia. In women, this causes galactorrhea, amenorrhea, and infertility. Galactorrhea is the discharge of whitish, milk-like fluid from the nipple (Figure 5.27), either spontaneously or after stimulation by squeezing the nipple. Galactorrhea occurs in 30% of prolactinoma cases,(33) whereas amenorrhea or oligomenorrhea is the most common manifestation, occurring in up to 95%.(34)
Figure 5.27 Galactorrhea in a patient with a pituitary prolactinoma.
In men, prolactinomas cause diminished sexual desire, impotence, low sperm counts, and galactorrhea. Galactorrhea is less common in men than in women.(35, 36) Prolactinomas in men are generally larger than those in women and therefore commonly produce hypopituitarism and mass-effect symptoms. In women, they are detected earlier because the endocrine manifestations are more conspicuous.
3. Adrenocorticotropic hormone-secreting adenoma. Its manifestations result from elevated blood ACTH and constitute Cushing’s syndrome. This syndrome can also arise from other causes, including corticosteroid administration, adrenal adenoma, and lung cancer. When caused by a pituitary adenoma, it is called “Cushing’s disease.” Characteristic features include increased appetite; a rounded, red moon face; double chin; truncal obesity; facial acne; long sideburns and a slight mustache, sometimes a beard (hirsutism); a buffalo hump; purple abdominal striae, sometimes extending to the thighs; thin skin, easy bleeding, and slow wound healing; diabetes; weakness; osteoporosis; and amenorrhea or oligomenorrhea. Hypertension and left ventricular enlargement commonly coexist.
An ACTH-secreting adenoma may develop after bilateral adrenalectomy for hypercortisolism. This is called Nelson’s syndrome. Patients develop progressively increased skin pigmentation and elevated blood ACTH. CT and physical examination reveal evidence of a pituitary adenoma.
4. TSH-secreting adenoma. This produces hyperthyroidism.
5. FSH- and LH-secreting adenoma. Composed of gonadotropic cells, this has no specific clinical symptoms or signs, but blood FSH and LH levels are elevated.
6. Plurihormonal adenoma. This adenoma secretes two or more adenohypophyseal hormones. Growth hormone and prolactin are the usual combination. These two hormones are secreted by three types of pituitary adenoma: mixed growth hormone cell–prolactin cell adenoma, acidophil stem cell adenoma, and mammosomatotropic cell adenoma.(32)
Original page 309
OPTIC NERVE AND OPTIC CHIASM
Tumors arising in the optic nerve or chiasm impair vision. When one optic nerve is involved, vision in that eye gradually deteriorates and ultimately is lost. An intraorbital optic nerve tumor may push the globe forward, producing nonpulsatile unilateral exophthalmos and restricted eye movements. Fundoscopy reveals primary optic atrophy on the affected side.
A tumor extending into or originating in the chiasm impairs visual fields and visual acuity in both eyes. The pattern of field loss varies according to the fibers destroyed and may be similar or different in the two eyes. Some patients have bitemporal hemianopia, with bilateral optic atrophy on fundoscopy. Children often do not recognize their visual loss, but searching nystagmus may be noticed and may be the first sign prompting medical consultation.
A chiasmal tumor may extend into the hypothalamus, causing hypothalamic dysfunction. Further growth obstructing the CSF pathway at the foramen of Monro produces raised intracranial pressure.
As noted above, tumors of the pituitary gland, hypothalamus, or parasellar region can also impair the optic nerves and chiasm, producing visual field loss, diminished visual acuity, and optic atrophy. These must be considered in the differential diagnosis, although differentiation is sometimes difficult.
Original pages 309–310
CAVERNOUS SINUS
As described in the anatomy section, cranial nerves III, IV, VI, and V pass through the cavernous sinus. Three supply the extraocular muscles, while the trigeminal nerve supplies facial sensation. These cranial nerves lie very close together in the cavernous sinus. A tumor here impairs their function, producing “cavernous sinus syndrome.” Patients have orbital and temporal pain, followed by numbness in the trigeminal distribution and diplopia from compression of the ocular motor nerves, causing ophthalmoplegia. Third nerve palsy is most common: the upper eyelid droops on the tumor side (ptosis), and the pupil is dilated and unreactive to light. When the eyelid closes completely, diplopia disappears because the affected eye cannot see; reopening the eye restores the diplopia. Upward tumor extension may impair the ipsilateral optic nerve and cause blindness. Malignancies such as nasopharyngeal carcinoma extending upward to the skull base may cause bilateral manifestations.
Original pages 310–311
SUPERIOR ORBITAL FISSURE
The superior orbital fissure lies anterior to the cavernous sinus, near the orbital apex and at the medial border of the greater wing of the sphenoid bone. It transmits the oculomotor, trochlear, and abducens nerves and the ophthalmic division of the trigeminal nerve into the orbit to supply the ocular muscles. The fissure is closely related to the optic canal and nerve.
A tumor in this region produces superior orbital fissure syndrome: loss of eye movements, a dilated pupil unreactive to light, and ptosis from compression of the oculomotor, trochlear, and abducens nerves (Figure 5.28). Pain or numbness occurs in the forehead within the ophthalmic division of the trigeminal nerve, and the corneal reflex on the tumor side is lost. Vision on that side may deteriorate to complete blindness while the opposite eye remains normal. Some patients have temporal or nasal visual field loss in the affected eye, depending on the site of optic nerve compression. Fundoscopy shows optic atrophy.
Some tumors also cause unilateral exophthalmos on the affected side.
Color added while retaining the original linework and letteringFigure 5.28 A tumor at the superior orbital fissure compressing the oculomotor, trochlear, and abducens nerves, the ophthalmic division of the trigeminal nerve, and the optic nerve.
Original pages 311–317
PINEAL GLAND
The pineal gland is a small gland attached to the posterior roof of the third ventricle near the posterior commissure. It is closely related to the quadrigeminal plate and aqueduct of Sylvius in the midbrain, resting on the superior colliculi (Figure 5.29). Above it lie the internal cerebral veins and splenium of the corpus callosum; behind it lie the great vein of Galen and anterior vermis. The pulvinar of the thalamus lies laterally, and the posterior third ventricle lies anteriorly. The function of the pineal gland remains uncertain, so the true localizing manifestations of pineal tumors cannot yet be specified. Clinical findings suggest a direct or indirect relationship with gonadotropin, although this remains unproven: some children with pineal tumors have precocious puberty, while others do not, and the difference remains unexplained.
Figure 5.29 The pineal gland and its relationship to neighboring structures. A. Lateral view. B. Superior view.
Localizing symptoms and signs result from tumor compression of the quadrigeminal plate, aqueduct of Sylvius, and oculomotor nucleus. Pineal tumors therefore resemble tumors arising within the upper midbrain, or tectum, and the two are difficult to distinguish clinically.
The important manifestations of pineal tumors are as follows:
1. Ocular manifestations. These are important localizing signs, resulting from compression and destruction of the quadrigeminal plate and producing “Parinaud’s syndrome.” This comprises loss of conjugate vertical eye movements (vertical gaze palsy), usually beginning with inability to look upward (upward vertical gaze palsy), and dilated pupils with absent or, in some cases, minimal light reactions (Figure 5.30). The pupils still constrict during near viewing (accommodation).
In this region, corticotectal fibers from the lower part of area 18 and upper part of area 19 in the occipital lobe pass to the upward vertical gaze center at the rostromedial aspect of the superior colliculi.(37) Tecto-oculomotor fibers then pass to the portions of the oculomotor nuclei (Figure 5.31) responsible for upward movement of the eyes and eyelids. Pineal tumor compression of the superior colliculi therefore prevents upward eye movements. Corticotectal fibers from the middle of area 19 and upper part of area 18 pass to the downward vertical gaze center caudolateral to the superior colliculi.(37) A large pineal tumor compresses this center and prevents downward gaze. Fibers passing to the horizontal gaze center in the pons lie deep in the midbrain tegmentum and escape compression. Horizontal gaze palsy is therefore not seen in patients with pineal tumors.
Figure 5.30 Upward vertical gaze palsy and dilated pupils unreactive to light (Parinaud’s phenomenon).Color added while retaining the original linework and letteringFigure 5.31 Pathways for conjugate vertical gaze.
The pupillary light reflex pathway begins in the retina and passes through the optic nerve, chiasm, and optic tract to the pretectal nucleus without synapsing in the lateral geniculate body. The pretectal nuclei lie immediately anterior to the superior colliculi and communicate across the posterior commissure. Fibers then pass to both Edinger–Westphal nuclei, whose parasympathetic fibers accompany the oculomotor nerves to the iris (Figure 5.32), causing pupillary constriction. Shining light into one eye causes both pupils to constrict simultaneously and equally. A pineal tumor compressing the pretectal area produces dilated pupils unreactive to light.
Color added while retaining the original linework and letteringFigure 5.32 The pupillary light reflex pathway, controlled by the parasympathetic nervous system.
Both eyes can still turn medially to view a near object (convergence) because the convergence center, or nucleus of Perlia, lies deep in the midline between the posterior parts of the two oculomotor nuclei. It is therefore usually spared by a pineal tumor unless the tumor is large. At that stage, upward gaze, downward gaze, and convergence are all lost.
Diplopia may initially be experienced as blurred or indistinct vision because vertical gaze impairment is unequal between the eyes and pupillary dilatation prevents good focus. The double images are vertically separated. Alternatively, diplopia may result from abducens nerve dysfunction due to raised intracranial pressure, in which case the images are horizontally separated (horizontal diplopia). Compression of the oculomotor nucleus can also cause diplopia, but this is uncommon because the nucleus lies deep.
Some patients have upward vertical nystagmus early in the loss of vertical gaze; it disappears once upward gaze paralysis is complete. Pineal tumors may also cause convergence spasm and nystagmus retractorius.(38) Both globes retract rapidly and return slowly to their normal position. Greater activity of the medial recti also produces convergence.
2. Raised intracranial pressure. Tumor compression of the aqueduct of Sylvius beneath the quadrigeminal plate causes obstructive hydrocephalus. Patients develop headache, vomiting, blurred vision, papilledema, and diplopia from abducens nerve palsy, with drowsiness late in the disease. Raised intracranial pressure often occurs early and precedes other manifestations because the aqueduct is a very narrow CSF passage closely adjacent to the pineal gland. Some patients have bitemporal hemianopia caused by compression of the optic chiasm by an enlarged third ventricle (Figure 3.57).
3. Deafness. This occurs when a very large pineal tumor extends downward to compress the inferior colliculi, auditory relay stations in the midbrain. Auditory signals pass along the cochlear nerves to the dorsal and ventral cochlear nuclei on both sides, then through the lateral lemnisci to the inferior colliculi, onward to the medial geniculate bodies, and finally to the temporal cortex. The inferior colliculi thus have bilateral innervation (Figure 5.7), and their compression causes bilateral deafness. Some patients have tinnitus before becoming deaf, sometimes with dizziness.
4. Gait ataxia. A large pineal tumor extending downward and backward may compress the cerebellar vermis and superior cerebellar peduncle, causing an unsteady gait. This generally occurs late, when intracranial pressure is markedly elevated. If gait ataxia occurs without prominent Parinaud’s syndrome, a posterior fossa tumor may be suspected instead.
5. Endocrine changes. As noted above, some patients have precocious puberty: the genitalia develop earlier than expected for age and acquire an adult appearance, pubic and axillary hair develops, and the voice breaks (Figure 5.19). These changes do not occur in every patient and remain inadequately explained.
A pineal tumor may grow or seed into the third ventricle, or an ectopic pinealoma may occur there. Compression of the hypothalamus, optic chiasm, and infundibulum then produces the hypothalamic manifestations described above and bitemporal hemianopia.
Original pages 317–326
CEREBELLUM
The cerebellum lies in the posterior fossa behind the fourth ventricle and brainstem, covered superiorly by the tentorium cerebelli. Its two main components are the midline vermis and the two cerebellar hemispheres. The primary fissure divides it into anterior and posterior lobes. Behind the posterior lobes on both sides lies the flocculonodular lobe.
The flocculonodular lobe is also called the vestibulocerebellum (archicerebellum) because it communicates with the vestibular system, which is concerned with balance. It also receives impulses from brain regions involved in eye movements.(39, 40)
The vermis (paleocerebellum) is sometimes called the spinocerebellum because it receives most of its input from the spinal cord through spinocerebellar afferents. It is concerned with equilibrium and posture.
The cerebellar hemisphere (neocerebellum) is sometimes called the pontocerebellum because most of its fibers arrive from the pons. It sends fibers to the thalamus and cerebral cortex and is concerned with motor coordination.
Within the cerebellar white matter are groups of gray-matter cells forming the dentate, fastigial, globose, and emboliform nuclei. The dentate nucleus is the largest and lies near the midline. The fastigial nucleus lies close to the midline beneath the vermis, or on the roof of the fourth ventricle. The globose and emboliform nuclei, collectively called the nucleus interpositus, lie between these two nuclei.
The cerebellum connects with the brainstem through three cerebellar peduncles (Figure 5.33): the inferior cerebellar peduncle (restiform body), middle cerebellar peduncle (brachium pontis), and superior cerebellar peduncle (brachium conjunctivum). Afferent fibers from various parts of the CNS enter through these peduncles. Most efferent fibers leave through the superior cerebellar peduncle; a smaller number leave through the juxtarestiform body, the medial part of the restiform body.
Color added while retaining the original linework and letteringFigure 5.33 Cerebellar peduncles. A. Lateral view. B. Superior view, showing only the right cerebellar hemisphere.
Inferior cerebellar peduncle. This connects the cerebellum with the spinal cord and medullary centers, carrying the following afferent fibers:
The dorsal spinocerebellar tract begins in the dorsal nucleus of Clarke in spinal cord segments L₃–C₈ and enters the cerebellum to terminate in the vermis.(41) It carries impulses from stretch, touch, and pressure receptors, providing proprioceptive and exteroceptive information for coordination of standing and individual limb muscle movements.
The cuneocerebellar tract. Because the column of Clarke is absent above C8, cervical spinal nerve fibers entering the cord ascend ipsilaterally in the fasciculus cuneatus. Impulses then reach the accessory cuneate nucleus in the medulla, analogous to the dorsal nucleus of Clarke. Its cells give rise to the cuneocerebellar tract, which carries proprioceptive information from the arm and neck to the cerebellum.
The vestibulocerebellar tract begins in the vestibular nerve root and vestibular nuclei, sending fibers to the flocculonodulus, uvula, and paraflocculus. It conveys information from vestibular receptors on both sides to the cerebellum for balance.
The olivocerebellar tract begins in the inferior olivary nucleus and sends fibers to all parts of the opposite cerebellar cortex, conveying somatosensory information from the contralateral inferior olivary nucleus to the cerebellum.
The reticulocerebellar tract begins in the lateral reticular nucleus of the medulla and terminates in the vermis.
The important efferent fibers passing through the restiform body are cerebellovestibular, fastigiobulbar, and cerebello-olivary fibers, located in the juxtarestiform body.
Middle cerebellar peduncle, or brachium pontis. The largest of the three peduncles, it connects the cerebellum with the pons and cerebral cortex. Most afferent fibers belong to the pontocerebellar tract, arising from pontine cells. The cerebellum communicates with the cerebral cortex through the cerebropontocerebellar pathway. This begins in the frontal, temporal, parietal, and occipital cortices, conveys impulses to the pons, and then relays them through the pontocerebellar tract to the opposite cerebellar hemisphere.
Superior cerebellar peduncle, or brachium conjunctivum. This consists mainly of cerebellar efferent fibers. Fibers from the cerebellar cortex pass to the cerebellar nuclei, chiefly the dentate nucleus. Dentate efferents then pass through the superior cerebellar peduncle to the contralateral red nucleus and ventrolateral thalamic nucleus through the dentorubral and dentothalamic tracts, respectively.
The cerebellum is therefore concerned not only with equilibrium and muscle tone but also with integrating and coordinating muscular activity to produce smooth, accurate intended movements. Cerebellar dysfunction from any cause produces the following manifestations:
Asynergy: muscle groups fail to act in coordination, preventing smooth, accurate movement, particularly fine tasks. Examination reveals dysmetria (inaccurate judgment of movement range) and dysdiadochokinesia (inability to alternate pronation and supination of the hand).
Hypotonia: reduced muscle tone and rapid fatigability.
Intention tremor: the hand trembles during an intended action but not at rest.
Unsteady gait and leaning. Destruction of one cerebellar hemisphere causes the head and body to lean toward the affected side when standing, with veering and falling toward that side when walking. A vermian lesion prevents stable sitting or standing, causing forward or backward falls or a staggering, broad-based gait.
5. Nystagmus and ocular deviation. Nystagmus is the most frequent finding in cerebellar lesions and indicates damage to the vestibulocerebellar pathway. The cerebellar hemisphere and nuclei are important in maintaining conjugate gaze toward the ipsilateral side, while the vermis helps maintain vertical gaze. Destruction of one hemisphere prevents sustained conjugate gaze toward that side. The eyes drift slowly back toward the midline, then rapidly return to the intended target, producing jerky nystagmus. Clinically, most cases are horizontal nystagmus, with the fast component toward the lesion.
A unilateral cerebellar hemispheric lesion also causes the eyes at rest, or during attempted straight-ahead gaze, to deviate approximately 10–30° toward the unaffected side because conjugate gaze toward the affected side is impaired.(42)
6. Speech abnormalities. Speech becomes slow and irregular because the muscles involved in articulation do not act in coordination.
Localizing symptoms and signs of cerebellar tumors
The manifestations may be divided into two groups:
1. Midline tumors. These destroy the vermis and flocculonodular lobe, where vestibular fibers terminate, and therefore resemble vestibular system disease. The midline vermis is important in controlling the head, neck, and trunk. A tumor here impairs their coordination, producing characteristic truncal ataxia (Figure 5.34). Patients cannot sit or stand upright, fall forward or backward, and cannot hold the neck and head upright. They stagger like an intoxicated person when walking and, if severely affected, cannot sit up at all. Dizziness is common, but nystagmus is uncommon unless the tumor extends into a cerebellar hemisphere, in which case ipsilateral cerebellar signs also occur.
Figure 5.34 Truncal ataxia in a patient with a vermian tumor. The patient cannot sit upright and falls backward.
A large vermian tumor may compress the brainstem, particularly the midbrain, producing a cerebellar fit: opisthotonos, rigid extension of both arms and legs, and backward arching of the head. Some patients remain conscious while others do not (Figure 4.31). The term “cerebellar fit” is actually inaccurate because the cerebellum itself does not cause seizures; the phenomenon is more likely due to brainstem dysfunction. Some tumors in this region compress the posterior midbrain at the quadrigeminal plate, causing vertical gaze palsy resembling Parinaud’s syndrome, as described above. This is a false localizing sign.
Vermian tumors commonly produce raised intracranial pressure relatively early because they lie very close to the fourth ventricle and can readily obstruct its inlet and outlets. Headache, vomiting, blurred vision, and papilledema are prominent. Young children develop enlargement of the head and separation of the cranial sutures.
2. Cerebellar hemispheric tumors. These produce cerebellar dysfunction in the ipsilateral limbs. Use of the arm and hand is clumsy, with hypotonia and drift toward the tumor side when the arm is extended. Dysmetria, intention tremor, and dysdiadochokinesia occur. The patient walks with the legs spread apart and veers or falls toward the tumor side (Figure 5.35). Unsteadiness is particularly evident when standing with the eyes closed or walking heel-to-toe in a straight line.
Figure 5.35 Broad-based gait adopted to maintain balance in a patient with a left cerebellar hemispheric tumor. Note the veering to the left.Figure 5.36 A 5-year-old patient with a large cerebellar cystic tumor and tonsillar herniation, causing arching of the back and backward bending of the neck (A). B shows the normal posture after tumor removal.
Nystagmus is present in nearly every case and is horizontal, with the quick phase toward the affected side and the slow phase toward the midline.
Sometimes a cerebellar hemispheric tumor produces relatively few signs despite its size, particularly when slowly growing, presumably because adaptation has occurred.
In addition to cerebellar signs, a cerebellar tumor may extend to compress ipsilateral cranial nerves V–XII. Involvement of V, VI, VII, and VIII is more common than involvement of IX, X, XI, and XII, although cranial nerve manifestations are uncommon with cerebellar tumors.
Some children develop meningism with neck and occipital pain because the tumor and cerebellar tonsils herniate through the foramen magnum, irritating the cervical nerve-supplied dura of the posterior fossa. The neck becomes stiff, the head tilts backward and may rotate slightly to one side, and opisthotonic arching of the back is frequent (Figure 5.36).
Original pages 326–327
Fourth ventricle
Tumors arising within the fourth ventricle itself produce raised intracranial pressure relatively early because they obstruct CSF flow. Patients have headache, vomiting, blurred vision, and papilledema. Vomiting is more frequent than with tumors elsewhere because the vomiting center in the medulla is affected. Headache usually begins early in the occipital and neck regions, sometimes with neck stiffness, and later becomes generalized as intracranial pressure rises markedly. Abducens nerve palsy may accompany the raised pressure. A large tumor compressing the vermis causes truncal ataxia, with inability to maintain balance and forward or backward falls; cerebellar hemispheric manifestations may be slight. Compression of the fourth ventricular floor, formed by the posterior pons, may impair cranial nerve function. The sixth and seventh nerves have been affected in cases encountered by the author.
Some tumors originate in the floor of the fourth ventricle or the vermis above and then grow into the ventricle. Manifestations of the site of origin appear first; for example, a vermian tumor produces truncal ataxia followed by raised intracranial pressure.
Original pages 327–338
BRAINSTEM
Anatomically, the brainstem comprises the midbrain, pons, and medulla. These three regions have similar components: four important groups of nuclei and five important groups of fibers (Figures 5.37 and 5.38).
Color added while retaining the original linework and letteringFigure 5.37 Important brainstem structures whose destruction by a brainstem tumor produces detectable symptoms and signs.Color added while retaining the original linework and letteringFigure 5.38 Important brainstem structures whose destruction by a tumor produces detectable symptoms and signs (superior view).
The important nuclei are as follows:
1. Cranial nerve nuclei. These are the sensory and motor nuclei of cranial nerves III–XII. The midbrain contains nuclei III and IV; the pons contains V, VI, VII, and VIII; and the medulla contains IX, X, XI, and XII. Their locations are important for tumor localization, as discussed below.
2. Sensory tract relay nuclei. The cuneate and gracile nuclei in the medulla are concerned with somatic sensation. The inferior colliculus and medial geniculate body in the midbrain are concerned with hearing, as are the superior olivary and trapezoid nuclei in the pons. The superior colliculus is concerned with vision and eye movements.
3. Motor tract relay nuclei. These include the pretectal area, concerned with the pupil and oculomotor system; the red nucleus, connected with the cerebral cortex and cerebellum; the reticular formation nuclei, similarly connected with the cortex and cerebellum; and the vestibular nuclei, concerned with the cerebellum and equilibrium.
4. Cerebellar relay nuclei. These include the inferior olivary, pontine, and red nuclei.
The important fibers are as follows:
1. Cranial nerves. These emerge from their nuclei. Most cranial nerves—V, VII, VIII, IX, X, XI, and XII—leave the brainstem inferolaterally. Nerves III and VI emerge inferiorly. Nerve IV is unusual in emerging superiorly and crossing to the opposite side.
The oculomotor nerve (III) supplies all extraocular and intrinsic ocular muscles except the superior oblique and lateral rectus.
The trochlear nerve (IV) supplies the superior oblique muscle.
The abducens nerve (VI) supplies the lateral rectus muscle.
The sensory root of the trigeminal nerve (V) receives sensation from the face and head. Its motor root supplies the muscles of mastication. The mesencephalic tract receives proprioceptive input from the jaw and ocular muscles; the spinal descending tract receives sensation from the face and head.
The motor root of the facial nerve (VII) supplies facial muscles, and its intermediate root provides parasympathetic innervation to facial glands.
The acoustic nerve (VIII) comprises the vestibular nerve for balance and the cochlear nerve for hearing.
The glossopharyngeal nerve (IX) receives sensation from the pharynx.
The vagus nerve (X) supplies the pharyngeal and laryngeal muscles and provides parasympathetic innervation to thoracic and abdominal organs.
The accessory nerve (XI) supplies the trapezius and sternocleidomastoid muscles, with a small contribution to the pharyngeal muscles.
The hypoglossal nerve (XII) supplies the tongue muscles.
2. Important sensory tracts
The spinothalamic tract conveys pain and temperature sensation from the spinal cord to the thalamus.
The medial lemniscus conveys somatic sensation to the thalamus and parietal cortex.
The trapezoid body, lateral lemniscus, and brachium of the inferior colliculus are concerned with hearing.
3. Clinically important motor tracts
The corticopontine tract runs from the cerebral cortex to the pons. The corticospinal tract consists of fibers from the motor cortex to the spinal cord and controls movement of the body’s muscles.
The rubrospinal tract is associated with the red nucleus and regulates muscle tone.(41)
The vestibulospinal tract is concerned with vestibular function.
4. Cerebellar projections. Clinically important projections include the middle cerebellar peduncle, or brachium pontis, associated with the cerebral cortex.
The restiform body, or inferior cerebellar peduncle, is associated with spinal cord function.
The superior cerebellar peduncle, or brachium conjunctivum, carries efferent fibers from the cerebellum to the red nucleus and thalamus.
The juxtarestiform body, the medial portion of the restiform body, connects the cerebellum with the brainstem.
5. Intrinsic fiber systems. The clinically important medial longitudinal fasciculus connects the oculomotor and vestibular nuclei.
Symptoms and signs of brainstem tumors
Based on the anatomy described above, the manifestations of an intrinsic brainstem tumor can be divided into five groups according to the structures destroyed:
Dysfunction of one or more cranial nerves from III to XII, depending on tumor location.
Corticospinal tract dysfunction, causing hemiparesis with unilateral damage or quadriparesis with bilateral damage.
Long sensory tract dysfunction, causing hemianesthesia or hemihypesthesia.
Dysfunction of internuclear or supranuclear tracts within or entering the brainstem.
Dysfunction of cerebellar pathways entering the pons and medulla or leaving the cerebellum for the midbrain and thalamus.
The key diagnostic pattern is progressively worsening contralateral spastic hemiparesis, with hemianesthesia or hemihypesthesia, accompanied by ipsilateral cranial nerve dysfunction. One or several cranial nerves may be affected. This crossed paralysis is an important diagnostic sign of a brainstem lesion, and the nerves involved indicate tumor location: III and IV indicate the midbrain; V, VI, VII, and VIII indicate the pons; IX, X, XI, and XII indicate the medulla. As the tumor enlarges and crosses the midline, it destroys corresponding structures on the opposite side, producing bilateral cranial nerve and long tract deficits. In the author’s experience, however, the manifestations are not equal or identical on the two sides. Large tumors may produce rigid extension of both arms and legs (Figure 7.39), resembling decerebrate rigidity, while consciousness may remain unchanged until late in the disease.
Brainstem tumors usually do not cause raised intracranial pressure, except for midbrain tumors, which can cause it early because the narrow aqueduct of Sylvius is easily obstructed. Pontine and medullary tumors generally grow along the brainstem fibers rather than into the ventricle; furthermore, brainstem dysfunction prompts patients to seek medical attention early. Nevertheless, raised intracranial pressure may develop late.
Tumors in different parts of the brainstem produce different manifestations, described separately below.
Midbrain. The midbrain comprises the tectum, tegmentum, and basis pedunculi. The tectum, or quadrigeminal plate, lies above the aqueduct of Sylvius and includes the superior colliculus, concerned with eye movements and containing the upward conjugate gaze center, and the inferior colliculus with its adjacent brachium, concerned with hearing. The pretectal area anterior to the superior colliculus is concerned with pupillary function.
On the inferior surface of the midbrain are the two cerebral peduncles, containing corticospinal, corticobulbar, and frontopontine tracts. Between them lies the interpeduncular fossa, where the oculomotor nerves emerge. Above the peduncles, within the tegmentum, lie the substantia nigra and red nucleus. Oculomotor fibers pass through this region, and fibers of the brachium conjunctivum terminate here. Laterally within the tegmentum lie the medial lemniscus and lateral spinothalamic tract, conveying sensation to the thalamus.
At the level of the superior colliculus, beneath the periaqueductal gray, lie the oculomotor nuclei and medial longitudinal fasciculus (MLF). Oculomotor fibers pass through the red nucleus to emerge in the interpeduncular fossa. At the inferior collicular level lies the trochlear nucleus. Its fibers curve around to emerge from the posterior brainstem on the side opposite their nucleus, behind the inferior colliculus, and supply the superior oblique muscle. Near the inferior colliculus are the downward conjugate gaze and convergence centers, controlling downward gaze and inward gaze respectively.
Symptoms and signs of midbrain tumors
Tumors of the tectum or quadrigeminal plate produce Parinaud’s phenomenon, as do pineal tumors: loss of upward conjugate gaze and dilated pupils unreactive to light, due to dysfunction of the superior colliculi and pretectal area (Figures 5.39 and 5.30). Extension destroying the inferior colliculi and lateral lemnisci causes tinnitus and bilateral deafness, together with loss of downward gaze and convergence, so the patient cannot look down or focus on a near object. Destruction of the oculomotor and trochlear nuclei produces diplopia, ptosis, and complete ophthalmoplegia except for the lateral rectus muscles supplied by the abducens nerves. Raised intracranial pressure occurs relatively early because the aqueduct becomes obstructed (Figure 5.39.1).
A tegmental tumor destroying the red nucleus, oculomotor fibers, medial lemniscus, and superior cerebellar peduncle produces contralateral limb tremor and ataxia together with ipsilateral oculomotor palsy. Contralateral sensory loss may occur from medial lemniscal damage (Benedikt’s syndrome; Figure 5.39.2).
A tumor originating in the cerebral peduncle produces contralateral spastic hemiparesis with ipsilateral oculomotor palsy (Weber’s syndrome; Figure 5.39.3).
Color added while retaining the original linework and letteringFigure 5.39 Tumors in different parts of the midbrain.
A tectal tumor produces Parinaud’s syndrome.
A tegmental tumor produces Benedikt’s syndrome.
A tumor of the basis pedunculi produces Weber’s syndrome (see text for details).
Midbrain tumors may extend to both sides, producing bilateral long tract and cranial nerve manifestations, usually of unequal severity.
PONS AND MEDULLA. The pons contains cranial nerves V, VI, VII, and VIII; the medulla contains IX, X, XI, and XII. Clinically important fibers include the corticospinal and corticobulbar tracts; pontocerebellar fibers through the brachium pontis; the medial longitudinal fasciculus (MLF) for eye movements; the medial lemniscus and spinothalamic tract for sensation; the lateral lemniscus for hearing; and the restiform body, or inferior cerebellar peduncle.
In addition to these cranial nerve nuclei, the pons contains a horizontal gaze center on each side near the abducens nucleus. Each center coordinates lateral movement of both eyes toward its own side. It sends fibers directly to the ipsilateral abducens nucleus and through the MLF to the medial rectus portion of the contralateral oculomotor nucleus. Each pontine center receives impulses from the opposite cerebral hemisphere and relays them to the ipsilateral lateral rectus nucleus and contralateral medial rectus nucleus (Figure 5.40). Destruction of one center prevents both eyes from turning toward the lesion; the eyes deviate to the opposite side. If the corticospinal tract is also destroyed, the eyes look toward the side of hemiparesis.
Color added while retaining the original linework and letteringFigure 5.40 Connections between the frontal eye field and lateral pontine gaze center for conjugate lateral gaze, with the medial longitudinal fasciculus connecting the abducens and oculomotor nuclei.
The medial longitudinal fasciculus (MLF) is another structure whose dysfunction produces detectable signs. It lies beside the midline and, at the midbrain level, close to the oculomotor nucleus. It is clearly identifiable from the oculomotor to the vestibular nuclear region. Most MLF fibers originate in the vestibular nuclei. This tract links cranial nerves III, IV, and VI with one another and with the vestibular nuclei, and also connects the pontine lateral conjugate gaze center to the oculomotor nucleus. Tumor destruction of the MLF causes internuclear ophthalmoplegia, discussed below.
Symptoms and signs of pontine and medullary tumors
Most tumors in this region originate in the pons and extend into the medulla; primary medullary tumors are very rare. Common early manifestations are diplopia and lower motor neuron facial weakness because the closely adjacent abducens and facial nerves and nuclei are destroyed. Later, horizontal conjugate gaze toward the tumor is lost and the eyes look away from it, an important localizing finding for a pontine tumor. In the author’s experience, this contralateral eye deviation persists and does not subsequently return to normal as may occur with frontal eye field lesions. Pontine tumors impair horizontal but not vertical conjugate gaze because the vertical gaze center lies in the midbrain. However, extension into the midbrain (Figure 3.23) can also impair vertical gaze.
Tumor damage to the MLF produces internuclear ophthalmoplegia. The characteristic findings are failure of the ipsilateral medial rectus during gaze toward the opposite side and horizontal nystagmus in the contralateral abducting eye.(43, 44) For example, on attempted rightward gaze, the right lateral rectus functions normally and the right eye turns right, but the left medial rectus fails to act despite no actual palsy of that muscle. The left eye remains in the primary position, yet convergence is preserved. Horizontal nystagmus is greater in the right eye than in the left; this asymmetry is another indication of an MLF or brainstem lesion. With progression, both horizontal and vertical nystagmus occur and internuclear ophthalmoplegia becomes bilateral. Vertical nystagmus is an important sign indicating a lesion within the brainstem; it is not found with lesions outside it and may therefore help distinguish these locations.
Failure of the medial rectus in internuclear ophthalmoplegia may be accompanied by other findings, depending on the location of MLF damage. Cogan(44) divided MLF lesions into three locations:
Posterior MLF lesions (medullary portion): convergence remains normal. Attempted lateral gaze produces nystagmus and sometimes paresis of the lateral rectus as well as the medial rectus.
Anterior MLF lesions (midbrain portion): convergence is absent or diminished in both eyes, without lateral rectus dysfunction. Nystagmus persists on lateral gaze but is less conspicuous than with posterior MLF lesions.
MLF lesions intermediate between sites i and ii produce the characteristic internuclear ophthalmoplegia described above. Thus, finding internuclear ophthalmoplegia indicates a tumor or lesion within the brainstem.
When the tumor enlarges to destroy the trigeminal and acoustic nerves and their nuclei, patients develop facial numbness, loss of the corneal reflex (V), and hearing loss (VIII), which may be unilateral or bilateral.
Medullary tumors impair cranial nerves IX, X, XI, and XII, causing vomiting, hiccups, progressive hoarseness, and choking when swallowing food or liquids, often resulting in aspiration pneumonia. Examination shows abnormal gag reflex, uvular movement, and vocal cord function. The tongue is paralyzed and atrophic, with fasciculations, and deviates toward the affected side on protrusion. Medullary tumors generally do not weaken the sternocleidomastoid and trapezius because these muscles receive most of their innervation from cervical nerves.
Spastic hemiparesis is commonly encountered with pontine and medullary tumors because the corticospinal tract in the lower pons is destroyed. Pontocerebellar fibers are also damaged, so gait ataxia may accompany limb weakness. Some patients have bilateral limb weakness, but its severity is unequal. Late in the disease, both sides may show rigid extension. Hemisensory loss accompanies the hemiparesis.
Original pages 338–343
CEREBELLOPONTINE ANGLE
The cerebellopontine angle is another common site of tumors. It contains several important structures whose involvement produces localizing symptoms and signs.
The C-P angle is bounded superiorly by the cerebellar hemisphere, medially by the pons, and anteriorly and laterally by the dura over the temporal bone.
Important structures in this region include the cerebellum, middle cerebellar peduncle, brainstem, cranial nerves IV–XI, and arteries and veins: the vertebrobasilar artery, superior cerebellar artery, anterior inferior cerebellar artery, posterior inferior cerebellar artery, petrosal sinus, cerebellar and pontine veins, and sigmoid sinus. The cerebrospinal fluid pathways include the aqueduct of Sylvius, fourth ventricle, and basal cistern.
The trochlear nerve (N IV) emerges from the dorsal midbrain behind the inferior colliculus and runs beneath the tentorium to supply the superior oblique muscle of the eye. During a transtentorial approach, every effort must be made to identify N IV.
The trigeminal nerve (N V) emerges from the lateral pons anterior to the facial and acoustic nerves and passes to Meckel’s cave at the middle of the petrous ridge. Meckel’s cave contains the Gasserian ganglion of the sensory root. Three divisions arise from this ganglion: i) the ophthalmic division receives sensation from the forehead, upper eyelid, and cornea; ii) the maxillary division receives sensation from the cheek, nose, and upper lip; iii) the mandibular division receives sensation from the chin, the inside of the mouth and tongue, and part of the ear.
The motor root runs beneath the sensory root and joins the mandibular division to supply the muscles of mastication (masseter, pterygoids, and temporalis).
The sensory nucleus and descending tract in the pons lie near its lateral surface and may be compressed by a C-P angle tumor.
The abducens nerve (N VI) emerges ventrally at the pontomedullary junction and runs along the underside of the pons into the cavernous sinus and superior orbital fissure to supply the lateral rectus muscle.
The facial nerve (N VII) emerges from the lateral pons close to the acoustic nerve and passes to the internal auditory canal. It lies anterior and inferior to the acoustic nerve and supplies the facial muscles and platysma.
The nervus intermedius is the part of the facial nerve that runs between the facial and acoustic nerves. It has two functions: sensory and parasympathetic. It carries pain and touch sensation from the ear, particularly the external auditory canal, and taste from the anterior two-thirds of the tongue via the chorda tympani. The ganglion of its sensory root is the geniculate ganglion. Its parasympathetic function controls secretion from the lacrimal and submaxillary glands.
The acoustic nerve (N VIII) has two components: the cochlear component for hearing and the vestibular component for balance. The vestibular nerve begins at Scarpa’s ganglion, which receives impulses from the hair cells of the semicircular canals, saccule, and utricle. It then enters the vestibular nuclei at the pontomedullary junction. These nuclei connect with many structures, including the MLF, cerebellum, spinal cord, and contralateral vestibular nuclei. These connections provide balance, changes in posture, and movements of the eyes, head, and neck. The cochlear nerve begins at the spiral ganglion and runs alongside the vestibular nerve to the cochlear nuclei in the brainstem, serving hearing.
The glossopharyngeal (N IX) and vagus (N X) nerves are related cranial nerves with similar functions. Both have motor and autonomic nuclei in the medulla and carry exteroceptive, general, and visceral sensations into the brainstem. They emerge from the medulla slightly below N VIII and pass into the jugular foramen together with the accessory nerve (N XI).
The motor component of N IX supplies the pharyngeal, soft-palate, and stylopharyngeus muscles involved in swallowing. Autonomic efferent fibers arise from the inferior salivatory nucleus and pass as preganglionic fibers to the otic ganglion. Postganglionic fibers then supply the parotid gland and stimulate salivary secretion. The sensory branch carries pain and temperature sensation from the posterior part of the tympanic membrane and the external auditory canal. General visceral sensory fibers receive sensation from the mucosa of the pharyngeal wall, uvula, tonsil, and posterior third of the tongue. It also carries special visceral sensation—taste—from the posterior third of the tongue. The fibers terminate in the nucleus of the fasciculus solitarius.
The vagus nerve (N X) has motor fibers from the nucleus ambiguus supplying the muscles of the soft palate, pharynx, and larynx (vocal cords). Its parasympathetic or visceromotor component begins at the dorsal efferent nucleus and sends postganglionic fibers to control the heart, gastrointestinal tract, and respiratory tract. The sensory fibers have cell bodies in the jugular ganglion and ganglion nodosum below the jugular foramen. They carry visceral sensation from the pharynx, larynx, bronchi, and abdominal viscera into the tractus solitarius in the medulla. There is also a component carrying sensation from the external ear.
The spinal accessory nerve (N XI) is a motor cranial nerve with two origins, one in the medulla and the other in the spinal cord. The medullary component arises from the nucleus ambiguus. After emerging from the medulla, it joins the spinal component, whose fibers arise from motor cells in the anterior horn from the fifth cervical segment upward to the medulla. N XI then enters the jugular foramen with N IX and N X to supply the sternocleidomastoid and trapezius muscles.
The hypoglossal nerve (N XII) arises from the hypoglossal nucleus in the medulla. It is a motor nerve supplying the muscles of the tongue on the same side.
Symptoms and signs of cerebellopontine angle tumors
The anatomy described above shows that tumors in this region produce signs of cranial nerve, brainstem, and cerebellar dysfunction, as well as obstruction of cerebrospinal fluid flow (Figure 5.41).
Color added while retaining the original linework and letteringFigure 5.41 Structures compressed and displaced by a tumor in the cerebellopontine angle.
1. Symptoms of cranial nerve dysfunction are important from the earliest stage because most tumors in this region are extra-axial. They compress the portions of the cranial nerves outside the brain, which therefore produce the first symptoms. Additional cranial nerves become involved as the tumor enlarges. Brainstem and cerebellar symptoms develop later, when the mass is very large. Whatever the tumor type, the nerve from which it arises or the nerve nearest it will produce symptoms first. The most common C-P angle tumor is acoustic neurinoma, followed by meningioma, trigeminal neurilemmoma, and others.
Tumors of the acoustic nerve begin in the vestibular nerve. The initial symptom is therefore dizziness related to balance, followed by tinnitus and progressively diminishing hearing on the side of the tumor until deafness develops. These are important early symptoms of acoustic nerve tumors, and the physician must make a particular effort to elicit them in the history. Dizziness is usually mild and does not cause severe spinning vertigo. The tinnitus varies: some patients describe buzzing, while others hear a bell-like sound. It is intermittent rather than continuous, and in most cases its timing is irregular. Patients describe progressively declining hearing until they can hear nothing on the affected side. Some do not realize they have lost hearing until they use the telephone.
As the tumor subsequently enlarges, it compresses adjacent cranial nerves, including N V, VII, IX, X, and XI. N V and N VII are most commonly affected. In some patients, N V symptoms occur before those of N VII. There is numbness or paresthesia on the side of the face ipsilateral to the tumor. A few patients report pain in the distribution of N V and may be mistaken for cases of trigeminal neuralgia. When N V is compressed, the corneal reflex is diminished or absent. Although N VII lies close to the acoustic nerve, facial weakness is uncommon unless the tumor is very large. A few patients present with facial twitching. The earliest sign of N VII dysfunction is loss of taste over the anterior two-thirds of the tongue, indicating compression of the nervus intermedius of N VII(45). N IX and N X dysfunction is uncommon unless a large mass extends downward and compresses both nerves, causing dysphagia and hoarse, indistinct speech.
2. Symptoms caused by cerebellar and brainstem dysfunction. A large tumor compresses the cerebellar hemisphere, nuclei, and peduncle, causing an unsteady gait and incoordination. Cerebellar signs are found in the ipsilateral limbs, together with nystagmus. At the same time, compression of the corticospinal tract in the pons causes contralateral spastic hemiparesis.
3. In the final stage, raised intracranial pressure results from obstruction of cerebrospinal fluid flow at the fourth ventricle and basal cistern. The patient develops headache, blurred vision, vomiting, and progressively worsening consciousness, eventually leading to death.
When a tumor arises from another cranial nerve, loss of that nerve’s function occurs first. For example, an N V tumor causes facial numbness or paresthesia, impairment of the corneal reflex, and dysfunction of the muscles of mastication early in its course. Other cranial nerves become affected later. The history is therefore important in identifying the original site of the tumor. As the mass enlarges, it compresses the brainstem, cerebellum, and other cranial nerves, just as an acoustic nerve tumor does.
Original pages 343–344
JUGULAR FORAMEN
As noted above, the jugular foramen is the exit for N IX, X, and XI. A tumor here therefore impairs all three cranial nerves. The patient has difficulty swallowing, hoarse and indistinct speech, vocal cord paralysis, and loss of taste and general sensation in the posterior third of the tongue. Sensation is also lost in the soft palate, uvula, pharynx, and larynx. The sternocleidomastoid and trapezius muscles on the side of the tumor become weak and atrophic.
Original pages 344–346
FORAMEN MAGNUM
The foramen magnum is the opening through which the medulla continues into the cervical cord. Two cranial nerves pass through this region: i) the spinal component of the accessory nerve arises from spinal cord levels C1–5 and ascends through the foramen magnum to join the component emerging from the medulla. It then leaves the skull through the jugular foramen to supply the sternocleidomastoid and trapezius muscles. ii) The hypoglossal nerve emerges from the medulla and enters the hypoglossal foramen at the margin of the foramen magnum to supply the ipsilateral tongue muscles. In the lower medulla, the corticospinal tract (pyramid) crosses to the opposite side (decussation). Fibers destined for the arm cross before those destined for the leg and lie lateral to the leg fibers (Figure 5.42). The lateral medulla contains important structures whose dysfunction can be detected clinically: the spinal tract and nucleus of the trigeminal nerve and the spinothalamic tract, which carries pain sensation from the lower body. Posteriorly, the medulla contains the fasciculus cuneatus and fasciculus gracilis, which carry proprioception, vibration, and touch.
Color added while retaining the original linework and letteringFigure 5.42 Pyramidal decussation and a foramen magnum tumor causing hemiplegia cruciata and lower cranial nerve dysfunction.
Symptoms and signs of foramen magnum tumors
Most tumors in this region lie outside the medulla and grow to compress it, the cranial nerves, and the upper spinal cord and spinal nerves. Patients present with the following symptoms.
1. Occipital and neck pain is a common initial symptom. It is explained by compression of the C2 spinal nerve, which gives rise to the greater occipital nerve. The pain worsens with changes in head position and movements of the neck. Patients therefore tense their neck and keep their head still.
2. Numbness. As the mass enlarges, contralateral hemihypesthesia or hemianesthesia develops because of compression of the lateral spinothalamic tract. Sensation is also lost on the side of the face ipsilateral to the tumor because the descending spinal tract of the trigeminal nerve is compressed. Paresthesia usually affects the arms more than the legs because the tumor commonly arises lateral or anterolateral to the medulla and displaces the fasciculus cuneatus. Some patients have Lhermitte’s sign: flexion of the head produces an electric-shock sensation extending into the lower body.
3. Spastic weakness. Muscle weakness may take several forms, depending on the tumor’s location. As noted above, motor fibers to the arm and leg do not decussate at the same level. A tumor lateral to the medulla compresses fibers to the ipsilateral arm and contralateral leg, causing weakness of an arm on one side and a leg on the other. This is called hemiplegia cruciata. Some patients describe weakness beginning in an arm and spreading to the leg on the same side, followed by the opposite leg and finally the opposite arm, producing quadriparesis. This pattern is explained by the arrangement of the pyramidal decussation (Figure 5.42).
Atrophy of the hand muscles, particularly the intrinsic muscles, is common. It may suggest a lesion in the part of the cervical cord supplying the arm and hand. The explanation remains uncertain, but ischemia caused by compression of the anterior spinal artery may be responsible(46).
4. Dysfunction of N XI and N XII causes weakness and atrophy of the ipsilateral sternocleidomastoid, trapezius, and tongue muscles. Upward extension of the tumor may compress N IX and N X, causing dysphagia and hoarseness later in the course.
5. Difficulty breathing occurs when a large tumor compresses the respiratory center in the medulla. Associated quadriparesis makes breathing still more difficult.
6. Horizontal nystagmus is found in 25% of patients(47).
7. In the late stage, patients develop raised intracranial pressure because cerebrospinal fluid pathways around the fourth ventricle are obstructed.
Original pages 346–347
CLIVUS
The clivus is the part of the skull base anterior to the brainstem. It extends from the posterior wall of the sella turcica to the anterior margin of the foramen magnum. It is closely related to cranial nerves II–XII, the basilar artery, cerebral peduncle, pons, and medulla.
Symptoms and signs of clival tumors
A tumor in this region compresses several cranial nerves and the corticospinal tract. A tumor in the upper clivus, anterior to the midbrain, causes headache and blurred vision. Compression of the optic chiasm and optic tract produces visual field defects. Compression of the oculomotor, trochlear, and abducens nerves causes extraocular muscle palsy and diplopia. In some cases, extension above the sella causes hypopituitarism. Extension to Meckel’s cave causes ipsilateral facial numbness or pain. Simultaneous compression of the cerebral peduncle in the midbrain causes associated limb weakness.
With a tumor arising in the lower clivus, or extending there from above, headache becomes more severe and is invariably accompanied by neck and occipital pain. Cranial nerves VI–XII may be affected unilaterally or bilaterally. N VI is affected most often because it runs from the lower border of the pons along its underside to the cavernous sinus(48).
Original pages 347–350
FALSE LOCALIZING SIGNS
In patients with brain tumors, false localizing signs arise from dysfunction of brain regions distant from the tumor rather than from the tissue at its actual location. They therefore cause confusion in determining the true site. Even careful history-taking and repeated examinations may lead to incorrect localization. These signs should be recognized. Those encountered include the following.
1. Dementia. Patients show deterioration in memory, reasoning, judgment, emotion, and personality, resembling a frontal lobe tumor. This dementia results from raised intracranial pressure or hydrocephalus.
2. Frontal lobe sign. The grasp reflex, a frontal lobe sign, may occur with raised intracranial pressure. In these cases it is bilateral and has no localizing value. A unilateral grasp reflex, however, is highly significant for localization.
3. Cranial nerve signs
3.1 Visual field defect. Compression of the optic chiasm by a markedly enlarged third ventricle may occur when a posterior fossa tumor obstructs cerebrospinal fluid flow and causes hydrocephalus. Bitemporal hemianopia may be found.
A supratentorial tumor unrelated to the optic pathways may cause homonymous hemianopia because raised intracranial pressure produces tentorial herniation. The tentorial edge compresses the posterior cerebral artery, causing occipital infarction (Figure 4.27). If the brain tissue has not infarcted, the homonymous hemianopia may disappear after removal of the tumor.
3.2 Oculomotor nerve signs. Ptosis, pupillary dilatation, and extraocular muscle paresis may result from uncal herniation compressing N III. These are important signs requiring prompt removal of the causative tumor before brainstem dysfunction develops.
3.3 Abducens nerve palsy is the most common false localizing sign. Raised intracranial pressure displaces the brainstem downward, stretching the abducens nerve against the petrous ridge. Lateral rectus dysfunction causes inward deviation of the eye. It may be unilateral or bilateral and has no value in localizing the lesion.
3.4 Trigeminal nerve palsy. A tumor outside the brainstem may push it to the opposite side. The contralateral trigeminal nerve is stretched and kinked where it enters Meckel’s cave, causing pain or numbness on the side of the face opposite the tumor(9).
4. Cerebellar signs may occur with supratentorial tumors, such as frontal or temporal lobe tumors, because of damage to frontopontocerebellar or temporopontocerebellar fibers projecting to the cerebellum.
5. Pyramidal tract signs. A supratentorial tumor, particularly in the temporal lobe, displaces the brainstem to the opposite side. The opposite cerebral peduncle is compressed against the tentorial edge, producing hemiparesis ipsilateral to the tumor. This is called Kernohan’s phenomenon.
A tumor causing hydrocephalus may produce paraparesis. Markedly enlarged lateral ventricles compress corticospinal fibers from the leg area of the motor cortex that run close to the lateral ventricular walls. The resulting spastic paraparesis resembles a spinal cord lesion.
6. Conjugate gaze palsy. The quadrigeminal plate may be compressed by the posterior portion of the third ventricle in hydrocephalus, or by the vermis during upward transtentorial herniation caused by a posterior fossa tumor. This produces Parinaud’s phenomenon, resembling the signs of a pineal tumor.
7. Endocrine dysfunction. A tumor elsewhere, unrelated to the pituitary gland, may cause hydrocephalus with marked third ventricular enlargement and produce hypopituitarism. The floor of the enlarged third ventricle presses down on the pituitary gland. At the same time, displacement or ischemia of the hypothalamus causes diabetes insipidus. In longstanding cases, marked enlargement of the pituitary fossa may be visible on X-rays.
8. Neck stiffness may suggest subarachnoid hemorrhage or meningitis. It is frequently found with posterior fossa tumors that cause tonsillar herniation and irritate the dura mater and upper spinal sensory nerves. Some patients experience an electric-shock sensation extending elsewhere in the body when the neck is strongly flexed (Lhermitte’s sign).
9. Paraparesis. Bilateral frontal parasagittal meningiomas cause paraparesis, which is a true localizing sign. It is included here because such patients have sometimes been misdiagnosed as having spinal cord lesions. The distinction is actually straightforward: a brain tumor is associated with raised intracranial pressure, seizures (if present), and absence of a sensory level, unlike a spinal cord lesion.
10. Cerebellar fits consist of arching of the back and neck (opisthotonos) with extensor rigidity of the limbs. They are not localizing signs of the cerebellum, because the cerebellum does not cause seizures. Rather, they indicate brainstem involvement due to a large cerebellar tumor with upward transtentorial herniation of the vermis, compressing the brainstem, particularly the midbrain.
Original pages 350–352
Chapter 5 References
De Jong R.N.: Functions and Disorders of Function of the cerebral cortex. In The Neurologic Examination. Harper & Row, Publishers 3rd edition, p 837-856, 1967.
De Jong R.N.: The Pyramidal Level. In The Neurologic Examination, p 410-426, 1967.
Andy O.J., Webster J.S., and Carranza J.: Frontal lobe lesions and behavior. South Med. J. 74: 968-972, 1981.
Boetz M.I.: Frontal lobe tumors. In Vinken, P.J., and Bruyn, G.W. eds: Handbook of Clinical Neurology. Vol. 17 Tumor of The Brain and Skull. Part II Amsterdam, North Holland Publishing Co., p 234-280, 1974.
De Jong R.N.: The Neurologic Examination, New York, Harper & Row, 1979.
Schneider R.C., Crosby E.C., and Calhoun, H.D.: Surgery of convulsive seizures and allied disorders. In Schneider R.C. Kahn E.A., Crosby E.C., Taren J.A., eds.: Correlative Neurosurgery 3rd edition, Springfield Ill., Charles C. Thomas Publisher pp 559-701, 1982.
Walton J. Intracranial tumor in Brain’s Diseases of The Nervous System, 9th edition, Oxford University Press. pp 143-173, 1985.
Schenwirth R.M.: Parietal lobe tumors. In Vinken, P.J. and Bruyn.: Handbook of Clinical Neurology. Vol. 16 Tumors of The Brain and Skull, Part II. Amsterdam, North-Holland Publishing Co. pp 296-309, 1974.
Crosby E.C., Humphrey T., Lauer E.W.: The occipital lobe. In Correlative Anatomy of The Nervous System. The Macmillan Co., p 456, 1962.
Gassel, M.M.: Occipital lobe tumors. In Vinken, P.J. and Bruyn, G.W., eds.: Handbook of Clinical Neurology, Vol. 17 Tumors of The Brain and Skull Part II. Amsterdam, North Holland Publishing Co., pp 310-349, 1974.
Adams R.D., Victor Maurice. The Principles of Neurology. Mc Graw-Hill Book Co. p 296-302, 1977.
Grinker R.R., Sahs A.L., The cerebrum. In Neurology. Charles C. Thomas Publisher 6th edition p 754-758, 1966.
Huber: Local symptoms of brain tumors. In Eye Symptoms in Brain Tumors 2nd ed. The C.V. Mosby Co., p 156-281, 1971.
Grinker R.R., Sahs A.L., Intracranial tumor. In Neurology. Charles C. Thomas Publisher 6th ed. p 759-879, 1966.
Kahn E.A., and Crosby E.C.: Glioma of the cerebral hemispheres. In Schneider, R.C., Kahn, E.A., Crosby E.C., and Taren J.A., eds.: Correlative Neurosurgery. Springfield Ill. Charles C. Thomas. Publisher pp 151-152, 1982.
Harsh G.R. and Wilson C.B. Neuroepithelial tumors of the adult brain. In Youmans J.R., eds. Neurological Surgery 3rd edition, W.B. Saunders Co. p 3040-3121, 1990.
Grinker R.R., Sahs A.L.: The cerebrum. In Neurology. Charles C. Thomas Publisher 6th edit. p 737-754, 1966.
Carpenter M.B., Truex R.C.: Diencephalon. In Neuroanatomy 6th edit. The Williams & Wilkins Co., p 458-497, 1970.
Grinker R.R., Sahs A.L.: The motor system. In Neurology. Charles C. Thomas Publisher 6th ed., p 608-694, 1966.
Adams R.D., Victor Maurice: The Principles of Neurology Mc Graw-Hill Book Co., p 312-314, 1977.
Tindall G.T., Barrow D.L., Disorders of The Pituitary Gland. The C.V. Mosby Co., p 1-22, 1986.
De Jong R.N.: The hypothalamus. In The Neurologic Examination 3rd edit. Harper & Row Publisher p 687-693, 1967.
Masdeu J.C.: The localization of lesions of the hypothalamus and pituitary gland. In Localization in Clinical Neurology. Brozis P.W., Madeu J.C., Biller Jose eds. Little, Brown and Co., p 249-265, 1985.
De Jong, R.N.: Autonomic nervous system. In The Neurologic Examination. Hoeber & Row Publishers 3rd ed. pp 687-693, 1967.
Martin J.B., Reichlin S. Neurological manifestations of hypothalamic disease. In Clinical Neuroendocrinology 2nd ed. F.A. Davis Co., p 379, 1984.
Burr I.M., Slonim A.E., Danish, R.K. et al. Diencephalic syndrome J. Pediatric 88: 429-436, 1976.
Cohen M.E., and Duffner P.K.: The tumors of brain and spinal cord including leukemic involvement. In Swaiman K.F., ed. Pediatric Neurology. The C.V. Mosby Co. pp 661-714, 1989.
Bell N.E., Mc Cormick W.F., Hypothalamic tumors. In Increased Intracranial Pressure in Children. W.B. Saunder Co., p 214-218, 1972.
Martin J.B., Reichlin S. Neuroendocrinology of reproduction. In Clinical Neuroendocrinology 2nd edit. F.A. Davis Co. p 331-334, 1987.
Plum F., and Van Uitert R.: Nonendocrine Diseases and Disorders of the Hypothalamus. In Reichlin, S., Baldessarini R.T. and Martin J.B., The Hypothalamus. New York, Raven Press. p 415-473, 1978.
Tindall G.T., Barrow D.L., Clinical and endocrinologic evaluation of patients with pituitary tumors. In Disorders of the Pituitary. The C.V. Mosby Co. p 123-143, 1986.
Kovaces K., Horvath E., Asa S.L.: Classification and pathology of pituitary tumors. In Neurosurgery. Wilkins R.H., Rengachary S.S. eds. Mc Graw-Hill Book Co. p 834-842, 1985.
Frank S., Nabarro JDN., Jacobs H.S.: Prevalence and presentation of hyperprolactinemia in patients with “functionless” pituitary tumors. Lancet 1: 778, 1977.
Faria M.A., Jr., Tindall G.T.: Transphenoidal microsurgery for prolactin-secreting pituitary adenomas. J. Neurosurgery 56: 33, 1982.
Carter J.N., Tyson J.E., Tolis G. et al: Prolactin-secreting tumors and hypogonadism in 22 men N. Engl J. Med 299: 847, 1978.
Finn J.E., Mount L.A.: Galactorrhea in males with tumors in the region of pituitary gland. J. Neurosurg. 35: 723, 1971.
Kahn E.A., Crosby E.C.: Lesions of the posterior ventricle and the midbrain. In Correlative Neurosurgery, 3rd edition. Charles C. Thomas Publisher p 283, 1982.
Huber A.: Tumors of the pineal body and the midbrain. In Eye Symptoms in Brain Tumors 2nd edition. The C.V. Mosby Co. p 259-264, 1971.
Selhorst J.B., et al: Disorders in cerebellar ocular motor control. I Saccadic overshoot dysmetria. An oculographic, control system, and clinico-anatomical analysis. Brain 99: 497, 1976.
Selhorst, J.B., et al: Disorders in cerebellar ocular motor control II Macrosaccadic oscillation. Brain 99. 509, 1976.
Truex R.C., Carpenter M.B.: The fiber tracts of the spinal cord. In Human Neuroanatomy, The Williams & Wilkins Co. 6th edition p 269, 1970.
De Jong R.N., The cerebellum In The Neurologic Examination 3rd edit. Harper and Row Publisher p 438, 1967.
Huber A., Eye Symptoms in Brain Tumors 2nd edit. The C.V. Mosby Co. p 48-49, 1971.
Cogan D.G. Neurology of the Ocular Muscles, 2nd ed. Charles C. Thomas Publ. P 84-91, 1966.
Pool, J.L., Pava, A.A. Acoustic Nerve Tumors 2nd edit Charles C. Thomas Publ. P 47, 1970.
Yasuoka S., Okazaki H., Daube J.R., et al.: Foramen magnum tumor. Analysis of 57 cases of benign extramedullary tumor J. Neurosurg. 49: 828-838, 1978.
Meyer F.B., Ebersold, M.J., Ruse D.F.: Benign tumors of the foramen magnum. J. Neurosurgery 67: 136-142, 1984.
Gutin P.H. Clivus chordoma. In Current Therapy in Neurological Surgery The C.V. Mosby Co. p 20, 1985.
O’connell J.E.A.: The trigeminal false localizing signs and their causation. Brain 10: 119-142, 1978.
Original pages 353–354
Chapter 6: text and illustrations from original pages 353–514
Chapter 6
INVESTIGATION
When a patient presents with neurological symptoms suggesting a brain tumor, the physician should take a detailed history and perform thorough neurological and general physical examinations. The resulting symptoms and signs help identify the tumor’s location and the extent of neurological dysfunction. The surgeon must carefully consider the various aspects of treatment in order to restore as much lost function as possible, or achieve a cure, while avoiding further deterioration. Before surgery, radiological investigations are therefore needed to support the clinical diagnosis. The images help determine the site, size, and type of tumor, as well as the many changes it has caused in the brain and blood vessels. This information guides surgical planning: where to operate, the extent of the procedure, and whether to remove the entire tumor or only part of it.
Several radiological investigations are available for tumors. The physician should choose methods that provide an accurate diagnosis, offer the greatest benefit for treatment, and do not endanger the patient, while also considering appropriate costs. The investigations used for brain tumors are as follows:
Skull X-rays
Cerebral angiography
C.T. (Computerized tomography)
MRI (magnetic resonance imaging)
Ventriculography
Pneumoencephalography (PEG), radioisotope brain scanning, echoencephalography, and EEG are now obsolete investigations because they do not clearly demonstrate the pathological lesion, and some carry risks.
Original pages 354–374
SKULL X-RAYS
Before C.T. became available, skull radiography was a useful initial investigation that provided certain information about brain tumors without endangering the patient. Routine views were anteroposterior (A-P), lateral, and Towne’s views. Additional views could examine particular sites, such as the optic foramen or sella turcica. A posteroanterior (P-A) view showed changes in the frontal bone, orbit, and lesser wing of the sphenoid; Stenvers’ view examined the auditory canal; and the submentovertical view examined the skull base.
The changes in skull radiographs caused by brain tumors are as follows:
1. Changes due to raised intracranial pressure. Tumors are among the many causes of raised intracranial pressure. The pressure must remain elevated for a prolonged period before skull changes develop. Pulsations of the cortex, CSF, and blood vessels with the heartbeat cause bone resorption, producing the following abnormalities.
1.1 Convolutional markings appear as indentations in the skull because its inner surface has become thinner. These are sometimes called digital impressions because they resemble indentations made by pressing fingers into modeling clay (Figure 6.1). This change is seen in adults. Prominent markings in the parietal region have particular diagnostic significance, because some digital impressions may normally occur in the occipital and frontal regions.
1.2 Erosion of the dorsum sellae is a frequent abnormality. The dorsum sellae and posterior clinoid become thin and fade from view (Figure 6.2). This is common in adults but uncommon in children, who can accommodate raised intracranial pressure by separation of the cranial sutures. With prolonged and progressively increasing pressure, the sellar floor becomes thinner, and the sella enlarges. In some cases, it disappears completely, together with atrophy of the tuberculum sellae (Figure 6.3).
Figure 6.1 Indentations on the inner surface of the skull (digital impressions or convolutional markings) caused by raised intracranial pressure.Figure 6.2 Destruction of the dorsum sellae and posterior clinoid process of the sella turcica.Figure 6.3 Complete destruction of the sella turcica and tuberculum sellae.
1.3 Suture separation. The sutures between the skull bones separate. This occurs in children whose skull bones have not yet fused with bone, but not in adults, whose sutures are firmly joined. The coronal suture is the first to separate because it is the last to fuse (Figure 6.4, A and B).
1.4 Enlargement of the head results from separation of the cranial sutures and occurs in young children (Figure 6.4).
Figure 6.4 A. Separation of the coronal and lambdoid sutures. Note the abnormally enlarged skull. B. Separation of the sagittal suture.
1.5 Localized skull bulging occurs in children with a slowly growing tumor at the brain surface. The bulging bone is thinner than the surrounding skull (Figure 6.5).
Figure 6.5 Localized bulging and thinning of the skull over a brain tumor.
2. ABNORMAL VASCULAR GROOVES. Normal skull radiographs show grooves for the middle meningeal artery and its branches, diploic venous channels, and emissary veins. Tumors arising at the brain surface in contact with the dura and skull, such as meningiomas, usually receive their blood supply from the middle meningeal artery. Two changes may be seen: i) neovascularity, and ii) enlargement of arterial and venous grooves on the inner skull surface (Figure 6.6).
Figure 6.6 Enlargement of a middle meningeal arterial branch (arrow) and a diploic venous channel (arrowhead) in a patient with a parietal parasagittal meningioma.
Neovascularity consists of new vessels around the tumor that supply it. It is an important sign for tumor localization (Figure 6.7).
Enlargement of vascular grooves and vessels is more common than neovascularity and usually occurs with tumors of the cerebral convexity and parasagittal region. Tumors at the brain base usually do not show this change. Three changes in the middle meningeal arterial grooves are significant: i) enlargement on only one side; ii) enlargement of a single branch; and iii) tortuosity. Unilateral enlargement suggests that the vessel supplies a tumor on that side. Enlargement may occasionally be bilateral, as when a falcine meningioma grows to both sides. Enlargement of one branch of the middle meningeal artery likewise raises suspicion that it supplies a tumor.
Figure 6.7 Markings of newly formed vessels (neovascularity) in the frontal skull in a patient with a frontal lobe meningioma.Figure 6.8 Enlargement of the groove and skull opening of the occipital emissary vein due to increased pressure in the posterior fossa.
Enlargement of emissary venous grooves and their skull openings may occur with tumors causing raised intracranial pressure, or when the vein drains a tumor. Sites include the occipital emissary vein (Figure 6.8) and the region of the Pacchionian granulations.
3. CALCIFICATION. Calcium deposits in intracranial structures, including pathological lesions, can assist diagnosis. Several brain tumor types calcify, particularly slowly growing (benign) tumors such as meningioma, craniopharyngioma, and oligodendroglioma. Recognizing the pattern and location of calcification helps distinguish tumor types.
Physiological calcification may occur in the pineal gland, choroid plexus, falx cerebri, tentorium cerebelli, and diaphragma sellae. Pineal and choroid plexus calcification are particularly important in relation to tumors. On an A-P view, the calcified pineal gland normally lies in the midline of the skull. A tumor or other expansile mass may displace it to the opposite side (Figure 6.9, B), indicating a supratentorial mass. It may also be displaced anteriorly, posteriorly, superiorly, or inferiorly, depending on the tumor’s position. Pineal calcification is found in approximately 55% of people over 20 years of age(1), although it is less common in Thai people. Pineal calcification in a child, unusually large calcification, or calcification unlike the normal gland should always be regarded as suspicious for pineal pathology. A detailed neurological examination and further investigations are required.
Choroid plexus calcification usually occurs in its glomus. It may be unilateral or bilateral and is less common than pineal calcification. Calcified glomera normally lie midway between the midline and the lateral skull margins and are symmetrical. A tumor may displace them from their normal positions, producing asymmetry (Figure 6.10, A and B). A choroid plexus papilloma may occasionally produce a large calcified mass on one side.
Figure 6.9 A. Calcified pineal gland on a lateral view. B. Calcified pineal gland on a frontal view. Note its displacement to the right of the midline because the patient has a left-sided brain tumor.Figure 6.10 A. Frontal skull view showing calcification in both choroid plexus glomera. B. Calcified glomera on both sides. Note that one lies lower than the other because it is compressed by a parietal lobe tumor.
Tumor calcification varies with the tumor type. Gliomas, including oligodendroglioma, astrocytoma, and ependymoma, show clusters of small and large calcific fragments or curved lines scattered throughout the tumor (Figure 6.11). Oligodendroglioma calcifies more commonly than the other types. In some cases, extensive calcification merges into an appearance resembling cigarette smoke.
Figure 6.11 Clusters of calcification in gliomas, commonly found in oligodendroglioma and low-grade astrocytoma.
Craniopharyngioma frequently calcifies and can show several patterns. Curved lines indicate calcification of a tumor cyst wall (eggshell calcification); small and large fragments may also coalesce into a mass. The important feature is its suprasellar location (Figure 6.12, A, B, and C), although some lesions lie within the sella.
Slowly growing meningiomas, especially psammomatous meningiomas, develop numerous calcified psammoma bodies. Their radiographic calcification is therefore uniformly white (homogeneous) (Figure 6.13), allowing the size and shape of the mass to be seen without angiography. In addition to calcification, two other radiographic abnormalities may coexist: i) hyperostosis and ii) increased vascularity, described earlier. Hyperostosis (Figure 6.14) develops in the skull adjacent to the tumor. This new bone formation is a reaction to the tumor, although the precise mechanism is unknown. Some cases show no tumor cells in the thickened bone or in the dura against the tumor surface; in others, tumor cells extend through the dura into the skull. Hyperostosis is usually accompanied by hypervascularity. Changes in the outer table produce a visible bony prominence on the head (Figure 6.15). A tuberculum sellae tumor may produce brushlike hyperostosis(1) (Figure 6.16). Another diagnostically important finding is upward bulging of the cortical bone above the ethmoid and sphenoid sinuses, enlarging the air sinus beneath the tumor upward. This is termed blistering(1) (Figure 6.16). With a sphenoid tumor, particularly meningioma en plaque, hyperostosis may cause exophthalmos and temporal bony prominence (Figure 6.17).
Figure 6.12 A. Suprasellar eggshell calcification (arrow) in a patient with craniopharyngioma. B. Lateral view of the same patient, also showing a calcified sellar mass. C. A calcified craniopharyngioma mass in the sellar region.Figure 6.13 Calcified temporal lobe meningioma. Note its homogeneous white appearance.Figure 6.14 Frontal bone hyperostosis in a patient with frontal meningioma. Note the hypervascular grooves around the hyperostotic region.Figure 6.15 A bony prominence of the skull in a patient with meningioma.Figure 6.16 Brushlike hyperostosis at the tuberculum sellae (arrow in A) and upward bulging (blistering) of the cortical roof of the air sinus (arrow in B) in a patient with tuberculum sellae meningioma.Figure 6.17 Unilateral exophthalmos and left temporal bony prominence in a patient with meningioma en plaque of the left sphenoid bone.
4. Local bone erosion. Bone at the site of a tumor consistently shows destruction or a reactive change. Rapidly growing tumors, such as skull metastases, destroy bone rapidly and extensively. Slowly growing tumors, such as meningioma, neurilemmoma, and pituitary adenoma, cause slow, localized destruction. Most tumors that erode bone lie at the skull base. Common examples include pituitary tumors, optic nerve glioma, acoustic nerve tumors, and glomus jugulare tumors. The changes are visible on skull radiographs.
4.1 Changes in the sella turcica. An intrasellar tumor, such as a pituitary adenoma, enlarges the sella into a rounded shape extending beneath the tuberculum sellae and anterior clinoid. This is called ballooning of the sella (Figure 6.18). A double sellar floor may be seen, indicating greater growth on one side than the other (Figure 6.19). This appearance may also occur with a medial lesser-wing meningioma or an intracavernous aneurysm.
Figure 6.18 Ballooning of the sella in a patient with a pituitary tumor.Figure 6.19 A double floor of the sella turcica.
An early intrasellar tumor erodes the junction of the dorsum sellae and sellar floor. The bone gradually thins and ultimately disappears. With a slowly growing tumor, reossification may produce a thin bony outline, creating the ballooned appearance.
4.2 Changes in the internal auditory canal are demonstrated by Towne’s and Stenvers’ skull views. They are important in diagnosing acoustic nerve tumors, most of which arise near the meatus of the internal auditory canal. As the mass enlarges, the following canal changes occur (Figure 6.20, A, B, and C): i) the internal meatus enlarges to more than 8 mm vertically; ii) the canal becomes funnel-shaped, with the wider end medially; iii) its upper margin becomes indistinct; iv) one canal exceeds the other in size by more than 2 mm; and v) a large tumor may destroy the petrous apex.
Figure 6.20 Internal auditory canal changes in a patient with an acoustic tumor. Note the funnel-shaped enlargement on the side of the tumor. A. Frontal view. B. Stenvers’ view. C. Towne’s view.
4.3 Changes in the jugular foramen. Enlargement occurs with glomus jugulare tumors. Some also destroy the posterior petrous bone (Figure 6.21).
Figure 6.21 Skull-base view showing enlargement of the jugular foramen in a patient with a glomus jugulare tumor.
4.4 Changes in the optic foramen. Both sides must be imaged and compared. Normally they should be equal or differ by no more than 2 mm. With optic nerve glioma, the optic foramen enlarges and has a thin, sharply defined margin (Figure 6.22) because the tumor grows slowly. A lateral skull radiograph shows a J-shaped sella (Figure 6.23), named for its shape. The tumor presses on and flattens the anterior sella and tuberculum sellae. The combination of an enlarged optic foramen and a J-shaped sella is important in diagnosing optic nerve glioma.
Figure 6.22 Enlarged optic foramen with a thin, sharply defined margin in a patient with optic nerve glioma.Figure 6.23 Lateral skull view during pneumoencephalography showing an optic nerve glioma (T) and a J-shaped sella.
Optic nerve meningiomas may produce hyperostosis or erosion of the foramen. Nasopharyngeal carcinoma extending upward destroys the optic foramen together with the adjacent skull base (Figure 6.24).
Figure 6.24 Destruction of the skull base and a soft-tissue shadow from nasopharyngeal carcinoma within the sphenoid air sinus (arrow).
4.5 Changes in the clivus. A clival chordoma may extend into the middle cranial fossa, C-P angle, and foramen magnum, causing destruction of the petrous bone together with the clivus.
Nasopharyngeal carcinoma extending into the base of the brain can likewise destroy bone in this region.
Original pages 374–375
CEREBRAL ANGIOGRAPHY
Before C.T. and MRI became available, this was an important investigation performed alongside skull radiography. It provided a high rate of accurate diagnosis, but was invasive and potentially hazardous, with several possible complications that could be severe enough to cause paralysis. A physician performing this investigation therefore required adequate training. In experienced hands, important complications would not occur. The introduction of C.T. and MRI (around 1973 and 1987, respectively) greatly reduced the use of angiography to diagnose brain tumors and other expanding masses. It continued to be performed in selected cases to determine the location of important vessels and the vascularity of a tumor, information useful in planning surgery for maximum patient safety, and in vascular disorders such as aneurysms and AVMs. Nevertheless, where C.T. is unavailable, angiography remains a very useful investigation and should therefore be learned.
When angiography is used to investigate a tumor, three types of change in the cerebral vessels must be examined:
Local stretching of cerebral vessels at the site of the tumor
Vessels affected by herniation or displacement of midline structures toward a region of lower pressure; and
Abnormal circulation within the tumor
Before discussing abnormalities on an angiogram, the normal appearances of carotid and vertebral angiograms will be described to provide a basis for understanding. The technique of cerebral angiography will not be discussed.
Original pages 375–382
Normal appearance of the carotid angiogram
The internal carotid artery branches from the common carotid artery at the level of the upper part of the thyroid cartilage and enters the carotid canal in the petrous bone. Its cervical portion has no branches. The artery runs through the carotid canal into the cavernous sinus; this is called the cavernous sinus portion. On a lateral skull radiograph it runs horizontally at approximately the level of the floor of the sella turcica. It then emerges from the cavernous sinus medial to the anterior clinoid process and enters the subarachnoid space. The artery passes upward and backward between the optic and oculomotor nerves. This is called the supraclinoid portion. On the lateral view, the cavernous and supraclinoid portions form a curved, pipe-like configuration called the carotid siphon. On the AP view, its shape is less clear because the vessels overlap, but the supraclinoid portion can be seen passing upward and slightly laterally before dividing into the anterior and middle cerebral arteries (Figure 6.25).
As the internal carotid artery passes through the carotid canal and cavernous sinus, it gives off small branches that are normally invisible on an angiogram. A branch may enlarge and become visible when it supplies a tumor or other lesion in that region.
Branches of the internal carotid artery
1. Ophthalmic artery. This is the first branch visible on the angiogram. It arises immediately after the internal carotid artery emerges from the cavernous sinus and enters the orbit through the optic foramen. On a lateral angiogram it is seen running forward from the internal carotid artery (Figure 6.27).
2. Posterior communicating artery. This arises from the posterior aspect of the internal carotid artery and passes backward and medially to join the posterior cerebral artery approximately 1 cm from the basilar bifurcation. These two arteries form part of the circle of Willis. On a lateral view, the posterior communicating artery runs horizontally or curves slightly downward and is about 1.5 cm long. Its origin may be enlarged, a feature called junctional dilatation that can sometimes be confused with an aneurysm. If this enlargement does not exceed 3 mm and the posterior communicating artery arises from its apex, it is considered normal rather than an aneurysm. On the AP view, the proximal posterior communicating artery is hidden by the internal carotid artery, while its posterior portion lies medial to the internal carotid artery (Figure 6.26). This relationship is important: a change in position should be regarded as abnormal.
3. Anterior choroidal artery. This arises from the internal carotid artery slightly behind the posterior communicating artery. It is a small vessel that runs backward and laterally into the choroidal fissure of the anterior temporal lobe to supply the choroid plexus, hippocampus, and basal ganglia.
On a lateral angiogram, this artery passes backward and slightly downward before curving upward (Figure 6.26b). On the frontal (AP) view, it passes upward and slightly medially for a short distance before turning laterally into the temporal horn (Figure 6.25).
In tumors of the choroid plexus or basal ganglia, this artery may be enlarged and form a visibly elongated curve.
4. Anterior cerebral artery. This is one of the two terminal branches of the internal carotid artery. It runs forward and toward the midline, passes over the anterior perforated substance above the optic nerve and optic chiasm, and connects with the opposite anterior cerebral artery through the anterior communicating artery. It then runs backward along the corpus callosum as far as the parieto-occipital fissure. Because it lies close to the midline of the cerebral hemispheres, it is an important vessel for demonstrating midline shift (herniation) of the brain.
Figure 6.26 Carotid angiogram showing the posterior communicating artery (long arrow), posterior cerebral artery (short arrow), and anterior choroidal artery (arrowhead). a. Frontal view. b. Lateral view.
The important branches of the anterior cerebral artery visible on angiography are:
4.1 The frontopolar artery arises before the anterior cerebral artery reaches the genu of the corpus callosum and runs forward to supply the anterior frontal lobe (Figure 6.27).
4.2 The callosomarginal artery is a large branch arising behind the frontopolar artery. It follows the callosomarginal sulcus and divides into anterior, middle, and posterior internal frontal branches, supplying the medial frontal lobe as far as the paracentral lobule (Figure 6.27).
4.3 The pericallosal artery is the distal continuation of the anterior cerebral artery and runs backward to the parieto-occipital fissure (Figure 6.27).
5. Middle cerebral artery. After arising from the internal carotid artery, it runs laterally and slightly forward into the beginning of the Sylvian fissure, where it divides into three branches (trifurcation). The major branches pass upward and backward over the surface of the insula (island of Reil), giving off further branches while on the insula. There are about 5–8 branches from front to back. These ascend to the cleft between the insula and operculum, then turn downward to emerge on the surface of the Sylvian fissure and supply the frontal, parietal, and temporal cortex.
On a lateral angiogram, these branches are arranged from front to back. Three lines—one joining the points where the branches turn back toward the Sylvian fissure, one along the middle cerebral artery, and one along the first (most anterior) insular branch—form a triangle called the Sylvian triangle (Figure 6.27). This is very important for localizing tumors and other expanding masses.
Figure 6.27 The Sylvian triangle and branches of the anterior cerebral artery. 1. = frontopolar artery 2. = callosomarginal artery 3. = pericallosal artery 4. = ophthalmic artery
Tumors at different sites produce characteristic changes in the shape of this triangle. Its most posterior point is called the angiographic Sylvian point.
On the frontal view, the middle cerebral artery branch over the anterior insula lies lowest and most medially. Successive branches lie progressively higher and farther laterally, so that the most posterior branch is highest and most lateral. This arrangement reflects the fact that the anterior insula is nearer the cerebral midline than the posterior insula (Figure 6.28). The middle cerebral artery itself lies approximately 20–30 mm from the inner skull, while the angiographic Sylvian point lies about 30–43 mm away. The latter point is approximately halfway along a line drawn from the upper border of the petrous bone to a horizontal line along the inner skull at the vertex(1) (Figure 6.29). Changes in these relationships indicate the location of a tumor, as described below.
Figure 6.28 Arrangement of the middle cerebral artery branches on the insular cortex, from anterior to posterior.Color added while retaining the original linework and letteringFigure 6.29 Position of the angiographic point in the frontal view.
The small branches arising from the horizontal segment of the middle cerebral artery are the medial and lateral lenticulostriate arteries. Approximately 2–6 can be seen on an angiogram. They ascend into the anterior perforating substance. The medial lenticulostriate arteries supply the medial ganglia, including the lentiform nuclei, internal capsule, thalamus, and caudate nucleus. The lateral lenticulostriate arteries supply the putamen, lateral part of the globus pallidus, and internal capsule. On a frontal angiogram, the lenticulostriate arteries form an S-shaped curve (Figure 6.25). They are usually not visible on the lateral view because the internal carotid bifurcation obscures them. With tumors of the basal ganglia, these vessels become enlarged and their position and shape are abnormal.
Original pages 382–387
Normal appearance of the vertebral angiogram
VERTEBRAL ARTERY arises from the subclavian artery and enters the foramina transversaria from C6 to C1. It then pierces the dura at the foramen magnum, enters the posterior fossa, and joins the opposite vertebral artery at the pontomedullary junction to form the basilar artery. The basilar artery lies in the midline anterior to the pons. At the upper border of the pons, or the level of the dorsum sellae, it divides into the two posterior cerebral arteries. The important vertebrobasilar branches that should be recognized and are visible on angiography are (Figure 6.30):
posterior inferior cerebellar a.
anterior inferior cerebellar a.
superior cerebellar a.
posterior cerebral a.
posterior choroidal a.
Figure 6.30 Vertebral angiogram in the frontal view. 1. Vertebral artery. 2. Basilar artery. 3. Superior cerebellar artery. 4. Posterior cerebral artery.
Posterior inferior cerebellar artery. This arises from the vertebral artery approximately 1–2 cm before the latter joins to form the basilar artery. It runs backward along the side of the medulla and divides into medial and lateral branches. The lateral branch supplies the inferior cerebellum. The medial branch lies along the medial aspect of the tonsil and curves around its lower border, forming the caudal loop. It then ascends to the upper tonsil, corresponding to the posterior aspect of the fourth ventricle, and forms the rostral loop. Beyond this, it supplies the medial cerebellar hemisphere and vermis. A choroidal branch arising at the rostral loop supplies the fourth ventricular choroid plexus and can sometimes be seen. On the lateral view, the posterior inferior cerebellar artery and its caudal loop are clearly visible as described (Figure 6.31). On the AP view, the vessel is initially some distance from the midline at its origin from the vertebral artery, then approaches the midline. The arteries on the two sides are approximately 3 mm apart. Their separation indicates a tumor developing between them.
Figure 6.31 Vertebral angiogram in the lateral view. 1. = caudal loop 2. = rostral loop 3. = choroidal point 4. = superior cerebellar artery 5. = posterior cerebral artery
The caudal and rostral loops are important landmarks for posterior fossa lesions because they indicate the positions of the tonsil and posterior fourth ventricle, respectively. A posterior fossa tumor causes tonsillar herniation, with the caudal loop displaced through the foramen magnum into the cervical canal (Figure 6.32), visible on the lateral skull view. Normally, the caudal loop is at the lower border of the tonsil and lies no lower than the margin of the foramen magnum. In some patients it may descend as far as C2–3. The rostral loop may also change position: a tumor within the fourth ventricle displaces it backward (Figure 6.69).
Figure 6.32 Tonsillar herniation: the caudal loop of the posterior inferior cerebellar artery is displaced below the margin of the foramen magnum.
Anterior inferior cerebellar artery. This small vessel arises from the proximal basilar artery and runs laterally toward the internal auditory meatus. It can be seen on a frontal vertebral angiogram. On the lateral view it is obscured by bone, and in some patients it is not visible on angiography.
Superior cerebellar artery. This arises from the basilar artery just before its termination and runs laterally and slightly downward around the lateral midbrain to the side of the quadrigeminal plate. It then curves upward to supply the superior cerebellum. On a lateral vertebral angiogram, it lies below the posterior cerebral artery. Over the cerebellum it forms a dome with its apex superiorly, but below the medial branch of the posterior cerebral artery (Figure 6.31). If this dome lies above the posterior cerebral artery, a cerebellar tumor should be suspected. On the frontal view, the superior cerebellar artery initially lies below the posterior cerebral artery. After passing around the midbrain, it lies more medially than the posterior cerebral artery (Figure 6.30). The superior cerebellar arteries on the two sides have matching configurations and relationships to the posterior cerebral arteries.
Posterior cerebral artery. This is a terminal branch of the basilar artery. The portion that curves around the midbrain is infratentorial. At the tentorial edge, it ascends into the supratentorial compartment to supply the temporal and occipital lobes.
Posterior choroidal artery. This arises from the proximal posterior cerebral artery and curves around the midbrain alongside it. This portion is not visible on the vertebral angiogram because it is obscured by the posterior cerebral artery. There are two posterior choroidal branches, medial and lateral (Figure 6.33). The medial posterior choroidal artery passes to the back of the midbrain. On reaching the side of the pineal gland, it enters the tela choroidea of the third ventricle to supply its choroid plexus. The lateral posterior choroidal artery passes around the posterior border of the thalamus to supply the choroid plexus of the lateral ventricle.
Figure 6.33 Lateral vertebral angiogram showing the posterior choroidal arteries, branches of the posterior cerebral artery. The lateral posterior choroidal artery (long arrow) lies posterior to the medial posterior choroidal artery (short arrow).
On a frontal vertebral angiogram, the posterior cerebral artery lies above the superior cerebellar artery, then passes lateral to it (Figure 6.30). In the supratentorial compartment, it gives off temporal and occipital branches whose positions vary. The posterior choroidal arteries are usually not visible. On the lateral vertebral angiogram, the posterior cerebral artery lies above the superior cerebellar artery throughout; any change in this relationship is abnormal. The posterior choroidal arteries are usually visible on the lateral view. Both curve backward and upward, with the lateral posterior choroidal artery forming a wider arc and lying posterior to the medial posterior choroidal artery. Changes in the configuration or size of these vessels indicate lesions of the thalamus, ventricle, or pineal gland.
Original pages 387–393
Normal appearance of the cerebral veins
The cerebral veins are divided into superficial and deep cerebral veins. Venous blood drains into the superior sagittal, inferior sagittal, and transverse sinuses and then into the internal jugular vein.
SUPERFICIAL CEREBRAL VEINS
1. SUPERIOR SUPERFICIAL CEREBRAL VEINS lie on the cortex of the cerebral hemispheres and run upward and backward. Before emptying into the superior sagittal sinus, they turn forward and then enter the sinus. At the central sulcus, a large vein called the superior anastomotic vein of Trolard (Figure 6.34) marks the position of the motor cortex. In the anterior frontal lobe, the superficial cerebral veins are less conspicuous than posteriorly.
2. MIDDLE CEREBRAL VEIN lies in the Sylvian fissure and receives blood from the lower frontal lobe and upper temporal lobe. It descends along the Sylvian fissure into the sphenoparietal sinus at the medial sphenoid ridge. Blood then drains into the cavernous sinus (Figure 6.34).
Figure 6.34 Lateral view of the superficial and deep cerebral veins. 1. Superior anastomotic vein of Trolard. 2. Middle cerebral vein. 3. Inferior anastomotic vein of Labbé. 4. Internal cerebral vein. 5. Great vein of Galen. 6. Thalamostriate vein. 7. Basal vein of Rosenthal.
3. INFERIOR ANASTOMOTIC VEIN OF LABBÉ communicates with the superior anastomotic vein of Trolard and the middle cerebral vein. It runs downward and backward over the posterior temporal lobe to enter the transverse sinus (Figure 6.34).
Important DEEP CEREBRAL VEINS
1) INTERNAL CEREBRAL VEIN begins at the foramen of Monro through the union of the thalamostriate and septal veins. It runs in the roof of the third ventricle close to the midline, parallel to the internal cerebral vein on the opposite side. The veins curve upward and then downward to unite above the suprapineal recess, forming the great vein of Galen (Figure 6.34).
2) GREAT VEIN OF GALEN passes into the quadrigeminal cistern and then curves upward into the straight sinus, which joins the transverse sinus at the torcular Herophili. In some patients, the posterior callosal vein is visible as a small vessel running along the posterior border of the splenium to join the anterior part of the great vein of Galen. This vessel helps identify the position of the splenium.
3) THALAMOSTRIATE VEIN lies between the thalamus and caudate nucleus and receives blood from the wall of the lateral ventricle. It therefore indicates the size of the lateral ventricle. On the lateral carotid angiogram it lies above and parallel to the internal cerebral vein (Figure 6.34). On the frontal view, the two thalamostriate veins form curves on either side of the internal cerebral veins, resembling buffalo horns (Figure 6.35). If the ventricles are enlarged, these curves extend farther from the midline. This is a more reliable sign of ventricular enlargement than changes in the anterior cerebral artery. Conversely, a vein lying unusually close to the midline indicates a smaller ventricle or one compressed by a tumor lateral to it.
Figure 6.35 Frontal view of the superficial and deep cerebral veins. 1. Thalamostriate vein. 2. Basal vein of Rosenthal.
The junction of the thalamostriate vein with the internal cerebral vein and the septal vein from the septum pellucidum is called the “venous angle.” It corresponds to the foramen of Monro and normally lies directly above the dorsum sellae or slightly posterior to this line. Displacement of the venous angle indicates pressure from an expanding mass. In some patients, the thalamostriate vein joins the internal cerebral vein behind the foramen of Monro, placing the venous angle farther posteriorly than usual. This is called a “false venous angle” (Figure 6.36), and caution is required in interpretation. If a frontal lobe tumor truly displaces the venous angle backward, the internal cerebral vein must also be displaced into an upward arch.
Color added while retaining the original linework and letteringFigure 6.36 False venous angle. 1. Internal cerebral vein. 2. Thalamostriate vein. 3. Septal vein. 4. Venous angle corresponding to the foramen of Monro.
4) BASAL VEIN OF ROSENTHAL originates in the anteromedial temporal lobe, the interpeduncular fossa of the midbrain, and the anterior perforated substance. It passes backward and upward around the midbrain to join the internal cerebral vein on each side before these unite as the great vein of Galen. Its appearance in the lateral and AP views is shown in Figures 6.34 and 6.35.
5) VEINS OF THE POSTERIOR FOSSA are seen on vertebral angiography and are divided into three groups(1): i) the superior group drains the superior cerebellum into the vein of Galen; ii) the anterior group drains the anterior cerebellum into the petrosal sinus; and iii) the posterior group drains the posterior cerebellum into the torcular, straight sinus, and transverse sinus. Two other important veins are the anterior pontomesencephalic vein, lying anterior to the pons, and the precentral cerebellar vein, running in the precentral cerebellar fissure (Figure 6.37a, b). Visualization of these two veins helps localize tumors.
DURAL SINUSES
These are important because they receive venous blood from the brain. Obstruction causes cerebral venous congestion and brain swelling and may be fatal. The important dural sinuses are:
1) SUPERIOR SAGITTAL SINUS lies beneath the superior sagittal suture. It begins at the nasion and passes backward, progressively increasing in size, to join the transverse sinus at the torcular Herophili; drainage then continues into the internal jugular vein. Most blood passes into the right transverse sinus. This sinus receives blood from cortical veins, which enter in a direction opposed to the flow within the superior sagittal sinus.
2) INFERIOR SAGITTAL SINUS lies along the lower edge of the falx cerebri and is visible on some carotid angiograms. At the junction of the falx and tentorium, the great vein of Galen joins it to form the straight sinus, which runs backward in the midline to the torcular.
3) TRANSVERSE SINUS begins at the torcular, receiving blood from the superior and inferior sagittal sinuses and the straight sinus. It extends to either side along the junction of the supratentorial and infratentorial compartments, continuing into the sigmoid sinus and internal jugular vein. The right transverse sinus is usually larger than the left.
Figure 6.37 a. Lateral view showing important posterior fossa veins: the anterior pontomesencephalic vein (arrow) and precentral cerebellar vein (arrowhead). b. Frontal view of the posterior fossa veins.
Original page 393
Angiographic abnormalities in brain tumors
A brain tumor is an expanding lesion that compresses brain tissue, vessels, and cerebrospinal fluid pathways. Adverse consequences include cerebral edema, hydrocephalus, increased intracranial pressure, and herniation of brain tissue and vessels. Angiography can demonstrate the following changes:
Herniation of vessels and brain tissue across the midline toward the side with lower intracranial pressure.
The location and size of the tumor, indicated by displacement of vessels at the tumor site from their normal positions.
The tumor type, judged from its blood supply, the rate of blood flow, and the pattern of vascular abnormalities within it.
Original pages 393–400
Angiographic appearances of cerebral herniation
A tumor may produce four important forms of herniation: i) midline shift, ii) transtentorial herniation, iii) tonsillar herniation, and iv) upward cerebellar herniation. These can be demonstrated by angiography, with the characteristic appearances described below.
MIDLINE SHIFT is displacement of the brain across the midline toward the side with lower intracranial pressure, passing beneath the falx. It is called subfalcine or cingulate herniation because the displaced structure is the cingulate gyrus, accompanied by the anterior cerebral artery. The inferomedial frontal lobe and anterior portion of the anterior cerebral artery are not covered by the falx, so they are displaced to the opposite side more readily than posterior structures, which are almost completely covered by the broader posterior falx. The pericallosal artery on the corpus callosum is not covered by the falx along its course, although its branches are. On a frontal carotid angiogram, the anterior cerebral arteries run parallel on either side of the midline. When an anterior cerebral artery and its branches are displaced to the opposite side, the lower edge of the falx forces them back toward the midline, creating an angular, step-like appearance (Figures 6.39–6.41).
Midline shift also affects the internal cerebral vein, septal vein, and vein of Galen. In deep-seated brain tumors, displacement of these deep veins is more conspicuous than displacement of the anterior cerebral artery (Figure 6.38).
Figure 6.38 Midline shift of the deep veins.
Displacement of the anterior cerebral artery from the midline takes several forms that also help localize the tumor. The appearances on carotid angiography are as follows:
1. PROXIMAL SHIFT is displacement of the anterior portion of the anterior cerebral artery beneath the falx to the opposite side, with its distal portion gradually returning to the midline without an angular bend (Figure 6.39). It is clearly seen on the frontal view and indicates a tumor in the anterior and inferior frontal lobe.
Figure 6.39 Proximal shift of the anterior cerebral artery.Figure 6.40 Rounded shift of the anterior cerebral artery.Figure 6.41 Square shift of the anterior cerebral artery.
2. ROUNDED SHIFT is a bowing of both the anterior and posterior portions of the anterior cerebral artery to the opposite side (Figure 6.40). It indicates a large frontal lobe tumor at or near the origin of the pericallosal artery.
3. SQUARE SHIFT is equal displacement of the anterior and posterior portions of the anterior cerebral artery to the opposite side (Figure 6.41). It indicates a tumor in the posterior frontal lobe. Although pressure from the tumor is greater posteriorly, the broader posterior falx limits displacement of the posterior anterior cerebral artery; consequently, the brain and vessels are displaced by equal amounts.
4. DISTAL SHIFT shows displacement of the posterior anterior cerebral artery to the opposite side, followed by an abrupt return to the midline where it is restrained by the falcine edge. The anterior portion remains in the midline (Figure 6.42). This indicates a parietal lobe tumor, especially in the parasagittal area. The anterior portion remains central because the pressure does not reach it. A very large mass may displace it somewhat, but less than the posterior portion.
The internal cerebral vein lies at the midline in the center of the brain, making it an important vessel in which contralateral displacement may be seen. Displacement of the internal cerebral vein without a corresponding change in the anterior cerebral artery indicates a deep tumor in the posterior frontal lobe or thalamic region. Changes in its shape may also localize a tumor, as discussed later.
Figure 6.42 Distal shift of the anterior cerebral artery.
TRANSTENTORIAL HERNIATION changes the configuration of the posterior communicating and posterior cerebral arteries. On the lateral carotid angiogram, uncal herniation produces increased downward bowing of the posterior communicating artery because the uncus presses on it from above (Figure 6.43a). If the parahippocampal gyrus also herniates, both the posterior communicating and posterior cerebral arteries sag in a broad downward curve. At the tentorial edge, the vessel makes an angular upward turn into the supratentorial compartment (Figure 6.43b). The anterior choroidal artery is stretched horizontally. On the AP view, both the posterior cerebral and anterior choroidal arteries shift toward the midline (Figure 6.44), an important diagnostic feature. The anterior choroidal artery also forms a wider arc.
Figure 6.43 a. Uncal herniation: note the downward displacement of the posterior communicating artery. b. Uncal and parahippocampal herniation: note the downward displacement of the posterior communicating and posterior cerebral arteries.Figure 6.44 Frontal carotid angiogram showing transtentorial herniation. Note displacement of the posterior communicating and posterior cerebral arteries toward the midline.
TONSILLAR HERNIATION is demonstrated by the caudal loop of the posterior inferior cerebellar artery lying below the margin of the foramen magnum, clearly visible on a lateral vertebral angiogram (Figure 6.32). The tonsil may descend as far as C2–3. In posterior fossa tumors, the tonsil on the tumor side usually herniates farther downward than the opposite tonsil.
UPWARD CEREBELLAR HERNIATION displaces the basilar artery forward on the lateral vertebral angiogram because the upward-herniating tissue lies behind the brainstem. The superior cerebellar artery rises above the posterior cerebral artery (Figure 6.45), on one or both sides. The most important venous-phase finding is elevation of the great vein of Galen and the posterior basal vein of Rosenthal by the upward-herniating cerebellar tissue.
Figure 6.45 Lateral vertebral angiogram showing upward cerebellar herniation. Note the superior cerebellar artery branch (arrow) displaced above the posterior cerebral artery by the tumor (T).
Original pages 400–430
Local vascular changes caused by brain tumors
Wherever a tumor develops, it compresses nearby vessels and alters their configuration and position. Arteries and veins adjacent to it may be stretched in an arc around its margin, sometimes outlining the mass. The tortuosity of vessels following the gyri disappears; the vessels become narrower and straighter. An infiltrative tumor without cerebral edema may cause relatively little vascular change. When a tumor produces local cerebral edema, vessels in the sulci are compressed into curves by the mass and swelling. On the lateral carotid angiogram, groups of vessels form concentric curved layers resembling an onion cut across (Figure 6.46). With a subcortical tumor, pressure from the mass and edema spreads the cortex, stretching and separating the vessels (Figure 6.47).
Figure 6.46 Cortical vessels displaced by a tumor and cerebral edema into a pattern resembling the layers of a cross-sectioned onion (onion peel).Figure 6.47 Local vascular changes at a tumor site. Note the separation of middle cerebral artery branches.
In the posterior fossa, tumors can alter the positions of the superior cerebellar, basilar, and posterior inferior cerebellar arteries, just as supratentorial tumors alter vessels in that compartment.
Deep cerebral hemisphere tumors can alter the size and shape of the septal vein, internal cerebral vein, thalamostriate vein, great vein of Galen, and basal vein of Rosenthal (Figure 6.50).
Taveras used the Sylvian fissure as a reference(1) for angiographic localization of tumors (Figure 6.48), as follows:
a. SUPRATENTORIAL TUMORS at the following sites:
anterior frontal lobe
supra-Sylvian (posterior frontal and anterior parietal)
infra-Sylvian (temporal lobe)
retro-Sylvian (temporo-occipital, parieto-occipital, and occipital lobe)
latero-Sylvian (lateral to the Sylvian fissure, extracerebral)
intra-Sylvian (within the Sylvian fissure)
centro-Sylvian (thalamus, basal ganglia, deep posterior frontal)
hydrocephalus
intraventricular, periventricular structures
suprasellar and parasellar
b. INFRATENTORIAL TUMORS
c. INCISURAL TUMORS
Dividing the brain into regions related to the Sylvian fissure and Sylvian triangle is useful for tumor localization. Physicians should therefore observe and remember the normal Sylvian triangle. Tumors at different sites alter its shape in different ways, as described below.
Color added while retaining the original linework and letteringFigure 6.48 Brain tumor locations in relation to the Sylvian fissure. 1. Anterior Sylvian (anterior frontal lobe). 2. Supra-Sylvian. 3. Infra-Sylvian. 4. Retro-Sylvian.
ANTERIOR FRONTAL LOBE TUMORS produce changes in three vascular structures: the anterior cerebral artery, the distal internal carotid artery, and the Sylvian triangle vessels. The anterior cerebral artery changes are particularly important. A tumor causes proximal shift, or rounded shift if large. A frontobasal tumor elevates the frontopolar and anterior cerebral arteries (Figure 6.49). An olfactory groove meningioma arches the anterior cerebral artery upward with little or no contralateral displacement, although a predominantly unilateral tumor also displaces it to the opposite side. A frontal lobe tumor bows the anterior cerebral and frontopolar arteries backward. The Sylvian triangle may be unaffected, but a large tumor or one extending posteriorly pushes the anterior insular branches backward, compressing the triangle posteriorly (Figure 6.49). The carotid siphon narrows as the internal carotid artery is depressed and its bifurcation displaced backward. The internal cerebral vein becomes more arched upward, and the venous angle is displaced backward (Figure 6.50).
Figure 6.49 Tumor at the base of the anterior frontal lobe. The frontopolar and anterior cerebral arteries are displaced upward and backward. The anterior middle cerebral artery branches of the Sylvian triangle are pushed backward by the anteriorly situated tumor.Figure 6.50 Frontal lobe tumor arching the septal vein upward (arrow) and displacing the venous angle backward.
An anterior parasagittal tumor may depress the anterior portions of the pericallosal and callosomarginal arteries.
Supra-Sylvian tumors lie in the posterior frontal or anterior parietal lobe. They cause square or distal shift of the anterior cerebral artery, depending on location, and depress the supraclinoid internal carotid artery. A tumor on the frontoparietal convexity stretches and separates the middle cerebral artery branches supplying that region. The upper border of the Sylvian triangle is depressed (Figure 6.51a), best seen on the lateral view. A large tumor or extensive edema spreading into the parietal lobe also depresses the angiographic Sylvian point and shifts the internal cerebral vein to the opposite side.
Parietal lobe tumors depress the angiographic Sylvian point and move it toward the midline, changes visible on both frontal and lateral carotid angiograms (Figure 6.52). The posterior cerebral artery is often displaced downward and medially. The internal cerebral vein is flattened and displaced contralaterally, increasing its distance from the thalamostriate vein. Tumors here generally shift the internal cerebral vein more than the anterior cerebral artery because the broad falx restricts arterial displacement. This relationship is important in localization.
A parasagittal parietal tumor produces important changes in the pericallosal and callosomarginal arteries: both are depressed and deflected to the opposite side. The upper (distal) middle cerebral artery branches are stretched, separated, and distorted. A large parietal parasagittal tumor invariably depresses the angiographic Sylvian point. The internal cerebral vein is flattened and may not shift contralaterally. A parasagittal meningioma may extend into the superior sagittal sinus, narrowing or occluding it. A surface tumor can stretch cortical veins around its border (Figure 6.53).
Figure 6.51 a. Supra-Sylvian tumor depressing the upper border of the Sylvian triangle and separating the cortical middle cerebral artery branches. b. Frontal view of the same patient, showing depression of the angiographic point and midline shift of the anterior cerebral artery.Figure 6.52 Parietal lobe tumor depressing the angiographic point (posterior end of the Sylvian triangle).Figure 6.53 Parietal parasagittal tumor stretching a cortical vein (arrow) and flattening the internal cerebral vein (arrowhead).
Temporal lobe tumors are infra-Sylvian tumors. Their characteristic carotid angiographic changes vary somewhat with the site and size of the mass in the middle cranial fossa, but generally include (Figure 6.54a, b): i) elevation of the middle cerebral artery and its branches, clearly seen laterally; ii) medial displacement of the middle cerebral artery; iii) medial displacement of the supraclinoid internal carotid artery with elevation of its bifurcation; iv) medial displacement of the anterior choroidal artery, which may also move upward or downward; v) medial displacement of the basal vein of Rosenthal; vi) midline shift of the anterior cerebral artery and internal cerebral vein, usually a proximal shift; and vii) when parahippocampal herniation occurs, downward and medial displacement of the posterior communicating and posterior cerebral arteries.
Tumors in different parts of the temporal lobe have the following angiographic appearances:
An anterior temporal lobe tumor elevates the horizontal middle cerebral artery. The anterior choroidal artery is also displaced upward and medially. The anterior Sylvian triangle is elevated while the angiographic Sylvian point remains unchanged (Figure 6.55).
With a posterior temporal lobe tumor, the lateral carotid angiogram shows elevation of the middle cerebral artery branches, with only slight change in the proximal horizontal segment. The angiographic Sylvian point is displaced upward and forward. The frontal view likewise shows elevation and medial displacement of this point (Figure 6.56).
An intraparenchymal temporal lobe tumor not only arches the middle cerebral artery branches within and outside the Sylvian fissure upward, but also stretches the branches on the affected temporal cortex around the tumor margin. This is called the “draping sign” (Figure 6.57). It may also occur with a large extracerebral tumor at the floor of the middle cranial fossa, which pushes the temporal lobe and its vessels into a draped configuration.
Figure 6.54 Infra-Sylvian or temporal lobe tumor. a. Frontal carotid angiogram: the middle cerebral artery and its branches are elevated and displaced medially, and the internal carotid artery is deflected inward. b. Lateral carotid angiogram: the middle cerebral artery and its branches are elevated, and the carotid siphon is stretched open.Figure 6.55 Anterior temporal lobe tumor. a. Frontal carotid angiogram showing elevation of the proximal (horizontal) middle cerebral artery. b. Lateral carotid angiogram showing elevation of the proximal middle cerebral artery and anterior Sylvian triangle.Figure 6.56 Posterior temporal lobe tumor displacing the angiographic Sylvian point upward and forward.Figure 6.57 “Draping sign” in a temporal lobe tumor. Note the stretched middle cerebral artery branches on the temporal cortex (arrow).Figure 6.58 a. Retro-Sylvian (parieto-occipital) tumor: the angiographic point is displaced forward and downward, and the Sylvian triangle is compressed forward. b. Frontal carotid angiogram showing depression and medial displacement of the angiographic point by a parieto-occipital tumor.
Retro-Sylvian tumors lie behind the angiographic point and include occipital, parieto-occipital, and temporo-occipital tumors (Figure 6.58). The prominent feature on the lateral carotid angiogram is forward displacement of the angiographic Sylvian point, accompanied by upward or downward displacement depending on the tumor site. An occipitoparietal tumor moves the point forward and downward, whereas an occipitotemporal tumor moves it forward and upward. On the frontal view, the point appears lower because forward displacement projects as downward displacement in the AP view. An occipital tumor pushes the brain forward, so the distal cortical middle cerebral artery branches are invariably bowed as well. The posterior cerebral artery supplying the occipital lobe is stretched and displaced.
INTRA-SYLVIAN TUMORS arise within the Sylvian fissure. On the lateral carotid angiogram, middle cerebral artery branches within the fissure are stretched and separated, some lying above the tumor and others below—a characteristic appearance (Figure 6.59a, b). A tumor extending to the brain surface may displace the middle cerebral artery medially (Figure 6.59b).
LATERAL SYLVIAN TUMORS lie outside the Sylvian fissure and displace the middle cerebral artery branches and angiographic Sylvian point medially. If the tumor lies toward the anterior Sylvian fissure, however, the point may remain unchanged, with displacement confined to the insular middle cerebral artery branches.
Thalamic tumors. Because the thalamus is deep, the important changes involve the deep veins, particularly the thalamostriate and internal cerebral veins. Anatomically, the thalamostriate vein follows the groove between the caudate nucleus and thalamus, which form the lateral wall and floor of the lateral ventricle. In a thalamic tumor, the venous angiographic phase is important for localization: the thalamostriate vein is elevated, widening the venous angle. On the lateral angiogram, the thalamostriate vein lies unusually high above the internal cerebral vein, which itself becomes more curved. On the frontal carotid angiogram, the thalamostriate vein is elevated and deflected medially, while the internal cerebral vein shifts to the opposite side (Figure 6.60a, b). In the arterial phase, the anterior cerebral artery generally remains at the midline, although hydrocephalus may arch it upward. The middle cerebral artery branches and angiographic Sylvian point move farther laterally. This pattern occurs with deep intracerebral tumors generally, is not specific to thalamic tumors, and may also occur with hydrocephalus. The lenticulostriate arteries supplying the basal ganglia are displaced laterally and obliquely downward. The anterior choroidal artery enlarges and is stretched around the posterior thalamus, visible on both lateral and frontal carotid angiograms (Figure 6.61a, b). The posterior cerebral artery may be depressed. The lateral posterior choroidal artery enlarges and forms a wider arc.
Figure 6.59 Intra-Sylvian tumor. a. Lateral carotid angiogram showing separation of the middle cerebral artery branches within the Sylvian fissure. b. Frontal carotid angiogram showing medial displacement of the middle cerebral artery and bowing of its branches.
The key carotid angiographic findings in a thalamic tumor are displacement of the internal cerebral and thalamostriate veins without displacement of the anterior cerebral artery, together with enlargement and widening of the arc of the anterior choroidal artery.
Pineal gland tumors elevate the posterior internal cerebral vein, separating it from the basal vein of Rosenthal (Figure 6.62). A large tumor may make the internal cerebral vein meet the great vein of Galen at an angle rather than an S-shaped curve, and may depress the great vein of Galen. Changes in the internal cerebral vein are important for diagnosing pineal tumors. Backward displacement of the posterior choroidal artery on the lateral view provides further support for this location (Figure 6.63).
Figure 6.60 a. Frontal venous-phase carotid angiogram showing a thalamic tumor elevating the thalamostriate vein and displacing the internal cerebral vein contralaterally. b. Lateral view showing upward arching of the thalamostriate and internal cerebral veins by a thalamic tumor.Figure 6.61 Arterial-phase carotid angiogram in a patient with a thalamic tumor. a. Frontal view: the lenticulostriate arteries bow outward (arrow); the anterior choroidal artery is enlarged and stretched into an arc (arrowhead); the anterior cerebral artery is stretched at the midline without deviation. b. Lateral view: the anterior choroidal artery is enlarged and stretched into an arc by the thalamic tumor.Figure 6.62 Internal cerebral vein narrowed and arched upward by a pineal gland tumor.Figure 6.63 Pineal gland tumor displacing the posterior choroidal artery backward.
Suprasellar tumors. The important related vessels are the internal carotid and anterior cerebral arteries. The intracavernous and supraclinoid internal carotid artery lie beside the sella, while the anterior cerebral artery lies above it. Any sellar tumor expanding upward arches the anterior cerebral artery upward and stretches the carotid siphon and supraclinoid segment upward and laterally, best seen on the frontal view. The lateral carotid angiogram shows widening of the siphon, called opening of the siphon (Figure 6.64a, b). Intrasellar tumors displace the intracavernous internal carotid artery laterally more conspicuously than extrasellar tumors. If a suprasellar tumor extends high enough to obstruct the foramen of Monro, hydrocephalus develops, with increased arching of the anterior cerebral artery and elevation of the septal and internal cerebral veins. This pattern may be difficult to distinguish from a third ventricular tumor.
A tumor arising at the tuberculum sellae or planum sphenoidale, such as a meningioma, displaces the anterior cerebral artery upward and backward while depressing the supraclinoid internal carotid artery. This narrows the carotid siphon, a pattern called closing of the siphon (Figure 6.65a, b).
A posteriorly situated suprasellar tumor elevates the internal carotid bifurcation and moves it forward. The anterior choroidal and posterior communicating arteries are displaced laterally, visible on the frontal carotid angiogram.
A tumor lateral to the sella turcica, such as a medial lesser wing meningioma, displaces the supraclinoid internal carotid artery medially. The internal carotid bifurcation and horizontal middle cerebral artery are elevated, best seen in the AP view. The anterior choroidal and posterior communicating arteries are simultaneously displaced medially and downward (Figure 6.66a, b).
Figure 6.64 a. Suprasellar tumor arching the anterior cerebral artery upward (small arrow) and stretching and deflecting the internal carotid artery outward (large arrow). b. Carotid siphon stretched open by a suprasellar tumor.Figure 6.65 a. Tuberculum sellae tumor displacing the anterior cerebral artery backward and upward (small arrow) and depressing the supraclinoid internal carotid artery (large arrow). b. Elevation of the anterior cerebral artery and lateral displacement of the internal carotid artery.Figure 6.66 Medial lesser wing meningioma. a. Frontal carotid angiogram: the proximal middle cerebral artery is elevated and deflected medially (long arrow); the internal carotid artery is likewise stretched and displaced medially (short arrow). Tumor stain is conspicuous. b. Lateral carotid angiogram: the internal carotid artery is stretched upward and the carotid siphon is widened.
Hydrocephalus. Tumors near or within the ventricular system, especially posterior fossa tumors, cause obstructive hydrocephalus. Carotid angiography shows: i) an anterior cerebral artery that is straight at the midline without shift on the AP view and arched upward like a bow on the lateral view; ii) elevation of the angiographic Sylvian triangle when the temporal horn is enlarged, resembling a temporal lobe tumor; iii) lateral displacement of the middle cerebral artery and its branches by the enlarged ventricle, increasing separation between the anterior and middle cerebral arteries on the frontal view; iv) outward bowing of the lenticulostriate arteries; and v) outward bowing of the thalamostriate vein with increased separation from the internal cerebral vein, indicating lateral ventricular size (Figure 6.67a, b, c).
Figure 6.67 Hydrocephalus on carotid angiography. a. Frontal view: both lenticulostriate and middle cerebral arteries are displaced laterally, while the anterior cerebral artery is stretched at the midline. b. Lateral view: the anterior cerebral artery is arched like a bow, and the middle cerebral artery is slightly elevated by the enlarged temporal horn. c. Frontal venogram showing outward bowing of the thalamostriate veins.
Posterior fossa tumors. The vessels affected are the posterior inferior cerebellar, superior cerebellar, and basilar arteries. A tumor in one cerebellar hemisphere stretches and displaces the normally midline vermian branches of the posterior inferior cerebellar artery contralaterally. The superior cerebellar artery is usually elevated above the posterior cerebral artery by upward cerebellar herniation (Figure 6.68). The posterior inferior cerebellar artery descends below the foramen magnum because of tonsillar herniation, with the tumor side usually descending farther than the normal side. The basilar artery is pushed forward against the clivus (Figure 6.68). An inferior vermian tumor stretches the vermian arterial branches backward and displaces the rostral loop of the posterior inferior cerebellar artery downward and backward, best seen laterally (Figure 6.69). The frontal view shows separation of the posterior inferior cerebellar arteries. A superior vermian tumor separates the superior cerebellar arteries and their branches; the lateral view shows upward bowing of the superior cerebellar artery.
Figure 6.68 Cerebellar hemisphere tumor arching the superior cerebellar artery upward to the level of the posterior cerebral artery.
Fourth ventricular tumors displace the rostral loop backward and move the basilar artery against the clivus. A large mass also displaces the vermian branches of the posterior inferior cerebellar artery backward (Figure 6.69).
Brainstem tumors push the basilar artery against the clivus and separate the posterior cerebral and superior cerebellar arteries on the two sides as they pass around the brainstem (Figure 6.70a, b). These changes usually occur in advanced cases. Occasionally, a brainstem tumor grows anteriorly against the clivus, paradoxically placing the basilar artery farther posteriorly away from the clivus (Figure 6.71).
Figure 6.69 Tumor of the vermis and fourth ventricle displacing the cephalad loop of the posterior inferior cerebellar artery backward. The posterior portion of the basilar artery is pushed against the clivus.
Clival tumors displace the brainstem and basilar artery backward away from the clivus, curving them around the tumor margin. A laterally situated tumor may also deflect them to the opposite side (Figure 6.72).
Cerebellopontine angle tumors elevate and medially displace the superior cerebellar artery alongside the brainstem (Figure 6.73). A large tumor displaces the rostral loop of the posterior inferior cerebellar artery and its vermian branches backward and contralaterally. The anterior inferior cerebellar artery may be displaced upward or downward and straightened.
The petrosal vein, if visible in the venous phase, is an important diagnostic landmark. This short vein lies superior and lateral to the internal auditory canal and receives the transverse pontine, mesencephalic, and cerebellar veins. A cerebellopontine angle tumor stretches the petrosal vein or makes it disappear entirely, an important angiographic sign of a lesion in this region.
Figure 6.70 Brainstem tumor. a. Frontal vertebral angiogram: the posterior cerebral and superior cerebellar arteries bow outward, separating the vessels on the two sides. b. Lateral view: the basilar artery is pushed against the clivus.Figure 6.71 Brainstem tumor growing outside the brainstem against the clivus, displacing the basilar artery away from the clivus.Figure 6.72 Clival tumor displacing the basilar artery backward.Figure 6.73 Cerebellopontine angle tumor. a. Frontal view: the superior cerebellar artery is elevated and deflected medially, and the basilar artery bows slightly to the opposite side. b. Lateral view: the superior cerebellar artery on the tumor side is elevated, and the basilar artery is stretched against the clivus.
Tumors at the tentorial edge are commonly meningiomas and may grow supratentorially, infratentorially, or in both compartments. They displace the posterior cerebral, superior cerebellar, and basilar arteries. An anterior tentorial tumor depresses the still-infratentorial portions of the posterior cerebral and superior cerebellar arteries downward and medially (Figure 6.74a, b, c, d). A more posterior tumor, where the posterior cerebral artery crosses into the supratentorial compartment, elevates that artery while depressing and medially displacing the superior cerebellar artery, increasing their separation (Figure 6.75a, b). A posterior midline tentorial tumor displaces the great vein of Galen forward. Upward extension may also displace the posterior internal cerebral vein. Infratentorial extension depresses superior cerebellar artery branches, visible on the lateral view. A large mass displaces the basilar artery contralaterally.
Figure 6.74 Tumor at the tentorial edge. a. Frontal vertebral angiogram: the superior cerebellar artery (arrow) and posterior cerebral artery (arrowhead) are displaced upward and medially. b. Lateral view: the superior cerebellar and posterior cerebral arteries are depressed. c. Carotid angiogram showing a tentorial branch supplying the tumor and tumor stain at the tentorium. d. C.T. showing an anterior tentorial meningioma.Figure 6.75 Posterior tentorial tumor. a. Lateral vertebral angiogram: the posterior cerebral artery is elevated and the superior cerebellar artery depressed. b. C.T. showing the tumor at the posterior tentorium.
Original pages 430–431
Abnormal Tumor Circulation
Studying the vessels supplying a brain tumor and the circulation within it may reveal the type of tumor. Angiography therefore requires serial images showing the arterial, capillary, and venous phases to permit more reliable interpretation. Some tumors contain abnormally formed vessels and rapid blood flow, features of malignancy, whereas others have slow blood flow, and in some no intratumoral vessels are visible at all. These findings can indicate both the type and the malignancy of the tumor. The important angiographic features to observe are: i) the vessels supplying the tumor, which become enlarged and tortuous; ii) abnormalities of newly formed intratumoral vessels, which may be large, show arteriovenous shunting, or have a beaded appearance characteristic of malignancy; iii) tumor stain, also called tumor capillary blush, produced by an increased number and size of intratumoral vessels and thus increased blood flow. On the angiogram this appears as a whitish mass. The duration of tumor staining can also indicate malignancy. Prolonged staining favors a benign tumor, whereas rapid disappearance of staining favors malignancy, except in angioblastic meningioma and hemangioblastoma, which have rapid blood flow but are not malignant; iv) the appearance of veins draining the tumor or the surrounding area. Early visualization of veins in the arterial phase suggests malignancy. This can be distinguished from an AVM because an AVM does not form an expanding mass like a tumor.
Only a few tumors have circulatory abnormalities that allow them to be distinguished by angiography using the principles described above: meningioma, hemangioblastoma, malignant glioma, metastatic tumors, and glomus jugulare tumor.
Original pages 431–438
Meningioma
This tumor arises from arachnoid cells and receives blood from two systems, the external and internal carotid arteries. Its sites are relatively characteristic, most commonly the parasagittal region; other locations include the convexity, olfactory groove, lesser wing of the sphenoid, tuberculum sellae, petrous ridge, tentorium, foramen magnum, and ventricles. Displacement of vessels near the tumor is similar to that described under local vascular changes caused by tumors in general. The characteristic angiographic features of meningioma, however, are as follows:
1. Supply from the external carotid system: branches of the middle meningeal artery or meningeal arteries at other tumor sites are enlarged, sometimes tortuous, and appear relatively earlier than other vessels in the arterial phase because of their increased flow. These feeding arteries become progressively larger as they approach the tumor, an important sign that they supply it (Figure 6.76). Branches of the middle meningeal artery are more clearly seen on external carotid angiography.
External carotid angiograms show the characteristic sunburst or sunray appearance of meningioma, with capillaries radiating from a central point where the meningeal artery enters the tumor from its outer surface (Figure 6.76).
The internal carotid artery supplies the inner aspect of the tumor, and its branches near the tumor are enlarged. In intraventricular meningioma of the lateral ventricle, the anterior choroidal artery is enlarged and more tortuous, clearly visible on both lateral and frontal angiograms (Figure 6.77). Intraventricular meningiomas receive no blood supply from the middle meningeal artery.
2. Meningioma produces a well-defined, uniformly opaque white mass of homogeneous staining. Its intratumoral vessels resemble normal capillaries, but are numerous and do not have a beaded appearance. The white tumor stain remains visible for approximately 8–10 seconds, beginning in the arterial phase and continuing through the capillary and venous phases. Such prolonged staining is characteristic of meningioma (Figure 6.78), unlike malignant glioma or metastatic tumor, in which staining lasts for a shorter period. This principle is therefore used in diagnosing the tumor.
3. Early venous drainage is usually absent in meningioma. An exception is angioblastic meningioma, in which several large early draining veins may be seen because circulation is relatively rapid, as in malignant glioma. Nevertheless, staining remains prolonged, as in ordinary meningioma (Figure 6.79).
Figure 6.76 Carotid angiogram of a frontal lobe meningioma. a. An enlarged middle meningeal artery supplies the tumor (arrow), with a sunray appearance. b. Lateral carotid angiogram of the same patient.Figure 6.77 Intraventricular meningioma supplied by an enlarged, tortuous anterior choroidal artery.
4. Meningiomas near the superior sagittal sinus often extend into it and cause partial or complete occlusion, clearly seen in the venous phase of the angiogram. Other tumors do not show this feature (Figure 6.80).
5. Even without tumor staining, the pattern of local vascular displacement in a falx meningioma may suggest the diagnosis. As an extracerebral tumor, a falx meningioma pushes the callosomarginal artery away from the falx toward the side of the tumor, because this artery lies lateral to the falx. The pericallosal artery, however, is pushed to the opposite side because it lies below the falx(3) (Figure 6.81a, b). A tentorial meningioma may elevate the posterior cerebral artery because part of it is supratentorial, while depressing the superior cerebellar artery, which lies in the infratentorial compartment.
Figure 6.78 Tumor staining characteristic of meningioma. a. Homogeneous staining begins in the arterial phase. b. Homogeneous staining persists into the venous phase.Figure 6.79 Meningioma with early venous drainage, an uncommon finding.Figure 6.80 Occlusion of the posterior superior sagittal sinus (arrows) by a parasagittal meningioma.Figure 6.81 Falx meningioma displaces the callosomarginal artery (arrow) away from the falx to the tumor side, while the pericallosal artery is pushed to the opposite side. a. Frontal carotid angiogram. b. Lateral carotid angiogram.
Original pages 438–439
Malignant Glioma
Glioblastoma multiforme is a brain tumor with abundant, rapid intratumoral blood flow because numerous new vessels of varying sizes form within it. These vessels are abnormal, with proliferation of intimal cells in their walls, a beaded appearance, and shunting between arteries and veins, causing rapid flow into the veins. The angiographic features of malignant glioma are as follows (Figure 6.82a, b):
Figure 6.82 Angiogram of malignant glioma. a. Beaded tumor vessels, patchy tumor staining, and early venous drainage (arrow). b. Early venous drainage into both superficial veins (short arrowhead) and deep veins (long arrowhead). Staining disappears rapidly.
1. The vessels supplying this tumor vary in size and have a beaded appearance.
2. Tumor staining begins in the arterial phase and disappears before the venous phase, sooner than in meningioma.
3. Abnormal intratumoral vessels are usually numerous at the tumor periphery but sparse centrally. They may appear as patches of vascular clusters surrounding central tumor necrosis, resulting in uneven staining.
4. Early venous drainage is visible late in the arterial phase. There may be one or several draining veins, or drainage into the deep cerebral veins. These are important signs of the malignant nature of this tumor.
Original pages 439–441
Metastatic Tumors
These tumors spread from cancer in other organs, most commonly the lung and breast. Their principal angiographic features are as follows (Figure 6.83):
1. Finding more than one tumor mass is the most important diagnostic feature. Cancer cells reach the brain through the bloodstream and may spread to several sites at different times, producing multiple brain metastases of varying sizes. A solitary lesion may be difficult to distinguish from glioblastoma because the intratumoral vessels, tumor staining, and early venous drainage are similar. However, finding a primary cancer elsewhere, such as in the lung or breast, favors metastatic tumor over glioblastoma.
2. There is usually a single enlarged feeding vessel, because the cancer cells enter that vessel as an embolus. As the tumor grows, the vessel containing the embolus becomes its feeding artery, so only one vessel is enlarged. The angiogram shows this feeder directed toward a pole of the tumor (Figure 6.83).
Figure 6.83 Angiogram of a metastatic brain tumor. a. The feeding vessel, which carried cancer-cell emboli, is enlarged and tortuous (arrow). Tumor staining is irregular. b. Early venous drainage (arrow). This patient had lung cancer.
3. Tumor staining is not homogeneous as in meningioma, and circulation is faster. Central tumor necrosis leaves fewer vessels in the center than at the periphery. Newly formed vessels resemble those in glioblastoma.
4. Early venous drainage appears as rapidly as in glioblastoma and cannot distinguish the two.
Original pages 441–442
Cerebellar Hemangioblastoma
This is a highly vascular tumor consisting of a solid tumor component, the mural nodule, and a surrounding cyst, although some cases have no cyst. The solid component has a rich vascular supply, so tumor staining is prominent and sometimes homogeneous (Figure 6.84). The cyst contains no vessels, but vessels are present in its wall. Early venous drainage occurs at the mural nodule. In cases without a cyst, the entire tumor contains numerous abnormal vessels. Intratumoral circulation is relatively rapid, like that of malignant tumors in general, sometimes making the distinction difficult. Clinical findings and other investigations must assist the diagnosis.
Figure 6.84 Two cerebellar hemangioblastomas. Tumor staining is very prominent from the early arterial phase because of their rich blood supply.
Original page 442
Glomus Jugulare Tumor
This is another highly vascular tumor. It lies at the jugular foramen and destroys the petrous bone. It receives blood from the external carotid system. Carotid angiography shows large feeding branches, staining resembling an AVM, and prominent early venous drainage. Circulation is also relatively rapid. The important angiographic diagnostic feature is its supply from the external carotid artery. Subtraction films clearly show both the feeding vessels and the tumor (Figure 6.85).
Figure 6.85 Glomus jugulare tumor at the jugular foramen. Note its supply from the external carotid artery and prominent tumor staining.
Original pages 442–449
Computed Tomography (C.T.)
Since 1972 (B.E. 2515), CT has been introduced for diagnosing diseases of the brain and spinal cord, greatly reducing the use of older investigations such as skull radiographs, angiography, ventriculography, and pneumoencephalography. Some, including ventriculography and pneumoencephalography, are now hardly performed because they carry substantial risks and cause considerable pain and distress. Skull radiographs and angiography are still used in selected patients and where CT is unavailable. Skull radiographs can provide direct or indirect evidence of a brain tumor. Direct signs include tumor calcification and tumor-induced blastic or lytic skull changes or ballooning of the sella. Indirect signs include displacement of a calcified pineal gland and changes in the sella turcica or cranial sutures resulting from tumor-related intracranial hypertension. However, these radiographic findings are insufficiently detailed to characterize the tumor, so further investigation is necessary. Before CT, angiography was the next investigation; ventriculography and pneumoencephalography were used when angiography was nondiagnostic or a tumor within or near a ventricle was suspected. At present, when physical examination suggests a brain tumor, CT is requested directly without skull radiographs, saving time and money. Angiography is also used much less often to diagnose brain tumors. It is reserved for selected cases in which the major feeding vessels and tumor vascularity must be assessed to plan surgery with the least possible risk. For example, in meningioma of the medial lesser sphenoid wing, the positions of the internal carotid artery and its branches must be known.
CT is a safe, painless examination that causes no suffering and depicts tumor location, size, and shape very well; sometimes it can also suggest the tumor type. It shows tumor-related changes in the skull, soft tissues, brain parenchyma, and ventricular system. CT should be performed before and after contrast administration, with standard axial sections. Tumors in the sellar, parasellar, tentorial, and posterior fossa regions may be better seen in coronal sections. Computer reconstruction can also provide sagittal images, but these are not particularly clear and are inferior to MRI (magnetic resonance imaging), as discussed later.
For brain tumors, noncontrast CT is less useful than contrast-enhanced CT, but it reveals calcification and intratumoral hemorrhage, which help identify the tumor type.
A brain tumor at any site produces mass effect on brain tissue, ventricles, subarachnoid spaces, cisterns, and blood vessels. CT assessment should consider the following changes to guide treatment planning and determine how urgently treatment should begin:
1. Tumor location. Enhanced CT usually shows tumor location and size very well. The neurosurgeon must determine whether the tumor is intra- or extracerebral, infratentorial or supratentorial, superficial or deep, and solitary or multiple. These findings inform the decision whether to operate, which approach will permit complete and safe removal, or whether only palliative treatment is appropriate. CT provides considerable guidance in these decisions.
2. Enhancement pattern. Different tumor types have different patterns. Irregular peripheral enhancement, appearing hyperdense or very white on the film, with a hypodense or dark center favors malignancy. Rapid tumor growth causes central necrosis because of inadequate blood supply.
3. Calcification, visible on nonenhanced CT, favors a benign rather than malignant tumor (Figure 6.86).
4. Brain edema. Edema is usually visible around brain tumors. CT clearly demonstrates it, an advantage over cerebral angiography. Malignant glioma, glioblastoma multiforme, and metastatic brain tumors may cause extensive surrounding edema. Metastatic tumors in particular can cause marked edema even when the tumor itself is small (Figure 6.87). Nevertheless, extensive edema is also observed around benign parasagittal meningiomas, possibly because the tumor compresses cortical veins entering the superior sagittal sinus and impedes venous drainage (Figure 6.88). It may also occur around large meningiomas of the lesser sphenoid wing and olfactory groove (Figures 6.89, 6.90). Intraventricular and other midline tumors usually do not cause brain edema. Marked edema on CT is important because the patient may deteriorate rapidly. Thus, whether extensive or limited, edema on CT helps indicate the need for prompt, appropriate treatment.
Figure 6.86 Intratumoral calcification is clearly visible on nonenhanced CT.Figure 6.87 Extensive peritumoral edema (dark area) around a small ring-shaped metastatic brain tumor.Figure 6.88 Parasagittal meningioma can also produce extensive surrounding edema. Both CT images are from the same patient.Figure 6.89 Brain edema in a lesser sphenoid wing meningioma.Figure 6.90 Brain edema in an olfactory groove meningioma.
5. Brain herniation. CT is a very useful radiological investigation for identifying the sites and extent of brain herniation. These findings prompt the surgeon to treat the patient urgently before brainstem function is lost. As discussed earlier, subfalcine, transtentorial, tonsillar, and upward cerebellar herniations occur at different sites and can be demonstrated on CT.
Subfalcine herniation occurs with supratentorial tumors. Important CT findings are as follows (Figure 6.93): i) the falx is displaced to the opposite side; ii) the lateral ventricle is compressed and displaced to the opposite side; iii) the anterior cerebral artery and cingulate gyrus pass beneath the falx to the opposite side, clearly seen in the coronal plane; iv) the anterior suprasellar cistern is distorted and narrowed; v) a relatively small superficial tumor may cause only local loss of the subarachnoid space over the tumor.
Transtentorial herniation has the following CT features: i) the lateral suprasellar cistern disappears because the uncus herniates downward into it; ii) further downward displacement of the uncus and parahippocampal gyrus pushes the brainstem to the opposite side. The ambient cistern on the herniation side widens, while the opposite cistern narrows or disappears; iii) marked brainstem compression elongates its anteroposterior diameter, and associated hydrocephalus also obliterates the interpeduncular and suprasellar cisterns(5); iv) if the herniating tissue occludes the posterior cerebral artery, occipital infarction appears as a low-density area; v) severe, rapidly developing transtentorial herniation with marked brain edema compresses the ventricles until they are no longer visible. The suprasellar, interpeduncular, and ambient cisterns also become invisible.
Tonsillar herniation. A posterior fossa tumor can cause the cerebellar tonsils to herniate downward through the foramen magnum and compress the medulla. Neither nonenhanced nor enhanced CT can show this unless opaque contrast medium has been injected into the spinal subarachnoid space. However, a posterior fossa tumor is a contraindication to lumbar puncture because it may increase herniation. Vertebral angiography shows tonsillar herniation better.
Upward cerebellar herniation. A posterior fossa tumor pushes the upper cerebellum upward through the posterior margin of the tentorial notch. CT shows: i) obliteration of the quadrigeminal cistern; ii) disappearance of the superior cerebellar cistern; iii) truncation of the posterior third ventricle, with hydrocephalus involving the third and lateral ventricles; iv) with a large mass, anterior displacement of the brainstem and loss of the prepontine and cerebellopontine angle cisterns; v) altered shape and size of the fourth ventricle, depending on tumor location and size (Figure 6.91).
Figure 6.91 Upward cerebellar herniation with obliteration of the quadrigeminal cistern.
Original pages 449–450
Metrizamide Cisternography and CT
This consists of CT after intrathecal injection of metrizamide, a water-soluble contrast medium. The patient is placed in the Trendelenburg position so that the opaque medium enters the posterior fossa cisterns and fourth ventricle. This demonstrates the cisterna magna, cerebellopontine and chiasmatic cisterns, as well as the medulla, pons, midbrain, and cerebellar tonsils. The technique is suitable for detecting small posterior fossa tumors, such as acoustic tumors, and tumors at the foramen magnum. Small tumors in these areas are generally difficult to see with conventional CT alone because of extensive artifacts.
In some cases, 4–5 cc of air may be injected intrathecally instead of metrizamide, a technique called air cisternography. The patient is positioned to let the air rise into the cerebellopontine angle, followed by CT. This can clearly demonstrate acoustic tumors smaller than 1 cm (Figure 6.92).
Metrizamide and air cisternography are now rarely used to detect tumors, because current CT scanners provide better image quality and higher resolution, and MRI offers better diagnosis than CT.
Figure 6.92 CT with air cisternography clearly demonstrates a 1-cm acoustic neurinoma.
Original page 450
CT Features of Different Tumor Types
It is generally accepted that CT is much better than angiography for diagnosing brain tumors. It shows tumor location, size, and effects on adjacent brain, including edema and herniation. Combining these findings with the tumor’s enhanced and nonenhanced CT appearances may identify its type. Although determining tumor type by CT is difficult, it can improve treatment planning. In practice, neurosurgeons correctly identify the tumor type before surgery in most cases; only a few prove to be something else.
The principal CT features of commonly encountered tumor types are described below.
Original pages 450–453
Malignant Glioma
This tumor arises from astrocytic cells and is classified as astrocytoma grade III–IV, also called glioblastoma multiforme. It grows rapidly and contains numerous new abnormal vessels. Rapid growth invariably causes central necrosis. Nonenhanced CT shows a tumor margin slightly denser than brain tissue (Figure 6.93a). The tumor center and surrounding brain are low-density areas, darker than normal brain, due to necrosis and edema respectively. Enhanced CT shows tumor hyperdensity in every case. Most commonly, an irregular hyperdense ring of uneven thickness surrounds a low-density center. There may be several low-density areas. Low-density edematous brain surrounds the mass (Figure 6.93b). Two other appearances may occur: homogeneous enhancement of the entire mass, sometimes containing small low-density spots (Figure 6.94), or an entirely cystic lesion with a small hyperdense solid mural tumor component in the cyst wall (Figure 6.95a, b).
Figure 6.93 a. Nonenhanced CT of glioblastoma multiforme. The tumor is slightly denser than normal brain, with surrounding low-density edema and central low-density necrosis. b. Enhanced CT of the same patient. The tumor is hyperdense, and low-density edema and necrosis are clearly visible.Figure 6.94 Glioblastoma that is almost entirely hyperdense, containing small low-density areas.Figure 6.95 a and b. Glioblastoma appearing as an entirely cystic lesion. Note the irregular cyst wall and a small mural nodule in the wall.
The pattern of peritumoral edema may also suggest malignancy. Malignant gliomas and metastatic tumors can have extensive surrounding low density, unlike grade 1–2 astrocytomas or other benign tumors, which have little surrounding low density.
These CT appearances of glioblastoma multiforme must be distinguished from metastatic brain tumors, brain abscesses, and intracerebral hematomas several weeks old. The history is needed to distinguish these conditions. A primary cancer in the lung or breast favors metastasis, and multiple brain lesions make this more certain. For brain abscess, both the history and CT help: its ring is smoother and more uniform than that of glioblastoma.
Original pages 453–455
Astrocytoma
Grade 1 and 2 astrocytomas are classified as low-grade, benign astrocytomas. They grow slowly, infiltrate tissue without clear margins, and are less vascular than glioblastoma multiforme. They occur in the cerebral hemispheres, cerebellum, brainstem, optic nerve and chiasm, and hypothalamus. Nonenhanced CT (Figure 6.96) shows irregular low density without clear margins. Some are isodense with brain tissue. Any calcification is clearly visible on nonenhanced CT. Astrocytomas may contain cystic components, particularly in the cerebellum. Enhanced CT usually shows little increase in density(7); when present, it is less marked than in glioblastoma and occurs in the solid tumor, while the cyst does not increase in density. Other causes of this low-density CT appearance include other tumors, cerebral infarction, traumatic brain edema, demyelination, and focal cerebritis.
Figure 6.96 Low-grade frontal lobe astrocytoma with ill-defined low density (arrow) and hyperdense calcification (arrowhead). Note the absence of mass effect.
In brainstem astrocytoma, nonenhanced CT shows an enlarged pons and flattening and posterior displacement of the fourth ventricle. Most tumors are low density (Figure 6.97). Enhanced CT appearances vary: some show only a slight increase in density, while others become hyperdense.
Figure 6.97 Brainstem glioma appears low density on nonenhanced CT. Note enlargement of the brainstem.
Cerebellar astrocytomas differ from those in the cerebral hemispheres in having well-defined margins. They may be solid, cystic, or mixed; most consist of a cyst with a mural nodule. Nonenhanced CT may show slightly increased density or mixed low- and high-density areas. Enhanced CT clearly defines the tumor, showing a cyst with a hyperdense mural nodule (Figure 6.98a, b). If the cyst wall also contains tumor, a high-density ring may be visible. In such cases, the neurosurgeon must try to remove the cyst wall as well, otherwise the tumor may recur.
Original pages 455–457
Oligodendroglioma
This is a benign, slowly growing tumor, usually in the cerebral hemispheres and commonly in the frontal lobe. Nonenhanced CT shows hypodensity with mass effect and relatively little surrounding edema. This resembles astrocytoma and is difficult to distinguish from it. Calcification is common in oligodendroglioma (Figure 6.99). Enhanced CT shows high density at the tumor periphery, while its center may be low density.
Figure 6.98 Cerebellar astrocytoma. a. A well-defined solid mass with a small cystic focus. b. A large cyst with a hyperdense solid mural nodule in its wall.Figure 6.99 Frontotemporal oligodendroglioma with ill-defined low density and, commonly, calcific granules in the brain tissue.
Original page 457
Ependymoma
This tumor arises from ependymal cells lining the ventricles. Its location in the ventricular wall or within a ventricle is therefore a diagnostic clue. Ependymoma can occur anywhere in the ventricular system, most commonly in the fourth ventricle, where it causes obstructive hydrocephalus. Nonenhanced CT shows an isodense or slightly hyperdense fourth ventricular mass, sometimes with calcification. Enhanced CT may show homogeneous or heterogeneous enhancement (Figure 6.100). Supratentorial ependymomas often contain cysts and calcification. The differential diagnosis includes medulloblastoma and choroid plexus papilloma.
Original pages 457–459
Choroid Plexus Papilloma
This highly vascular choroid plexus tumor commonly occurs in the trigone of the lateral ventricle and in the fourth ventricle. CT shows a well-defined hyperdense intraventricular mass, invariably with hydrocephalus because the tumor produces CSF or because it may bleed (Figure 6.101). Some cases contain calcification. The differential diagnosis includes intraventricular meningioma, ependymoma, medulloblastoma, and hemangioblastoma.
Figure 6.100 Lateral ventricular ependymoma with heterogeneous enhancement on enhanced CT. Note the marked hydrocephalus.Figure 6.101 Choroid plexus papilloma appears as a hyperdense intraventricular mass on enhanced CT, with cauliflower-like margins and invariably associated hydrocephalus.
Original page 459
Medulloblastoma
This tumor is common in children and lies in the cerebellar midline, extending into the fourth ventricle or foramen magnum, or spreading through CSF into the subarachnoid space. CT shows a hyperdense mass in the vermis extending toward the fourth ventricle, displacing it anteriorly or obstructing it and causing obstructive hydrocephalus (Figure 6.102a). Cysts are generally absent, although very large tumors may develop small cysts (Figure 6.102b).
Figure 6.102 Medulloblastoma in the vermis causing hydrocephalus. a. Enhanced CT shows hyperdensity without cysts. b. A very large medulloblastoma, often containing several cystic areas.
Original pages 459–460
Colloid Cyst
A mucoid-containing cyst situated in the third ventricle near the foramen of Monro. This characteristic location is a diagnostic clue. CT shows a small, round, smooth-margined mass of homogeneous high density(6).
Original page 460
Hemangioblastoma
This benign vascular tumor most commonly lies in a cerebellar hemisphere near the midline and may contain a cyst. CT shows a hyperdense solid component. When a cyst is present, it is low density, with solid tumor in its wall, usually adjacent to the pia mater on the superior or posterior cerebellar surface (Figure 6.103). This is difficult to distinguish from cystic astrocytoma, but angiography can differentiate them by the numerous intratumoral vessels of hemangioblastoma.
Figure 6.103 Cerebellar hemangioblastoma on enhanced CT. The solid component is markedly hyperdense and abuts the pia mater; a low-density cyst is visible deeper in the tumor.
Original pages 460–464
Meningioma
Meningioma is not difficult to diagnose on CT because of its characteristic sites, including the parasagittal region, falx, olfactory groove, lesser sphenoid wing, tentorium, and convexity, and associated skull changes. It is a benign, well-defined tumor. Psammomatous meningiomas often contain calcification. Nonenhanced CT shows increased density due to densely packed cells and calcification, with no hypodense areas within the tumor. Some tumors are extensively calcified throughout and clearly visible on nonenhanced CT (Figure 6.104). Enhanced CT shows a well-defined hyperdense mass, sometimes with its surface attached to the falx (Figure 6.105) or hyperostotic bone. The broad surface of attachment to the dura also aids diagnosis. Since meningioma is an extracerebral tumor, surrounding low-density edema is often visible. Parasagittal meningiomas in particular may have extensive surrounding low density because compression of cortical veins impairs venous return and causes edema (Figure 6.88), as observed during surgery at this site. In other locations, such as the olfactory groove, tuberculum sellae, and tentorium, surrounding low density may be absent or slight.
Figure 6.104 An entirely calcified meningioma, clearly visible on nonenhanced CT.
Another CT feature suggesting meningioma is mass effect that is disproportionately small for tumor size, such as only slight midline shift despite a large mass. Because meningioma grows slowly, adjacent brain atrophies through local water loss, allowing the tumor to expand without raising intracranial pressure.
Figure 6.105 Falx meningioma on enhanced CT appears as a well-defined hyperdense mass attached to the falx on one side.
Intraventricular meningioma shows homogeneous isodensity or slight hyperdensity on nonenhanced CT. It is well defined within the ventricle, commonly at the glomus of the lateral ventricle, and becomes hyperdense on enhanced CT (Figure 6.106), making it difficult to distinguish from choroid plexus papilloma.
A cerebellopontine angle meningioma is difficult to distinguish from an acoustic tumor. Bone CT may help: in meningioma, the internal auditory canal is not enlarged, and adjacent bone may be hyperostotic, whereas acoustic tumors usually enlarge the internal auditory canal. Sellar meningioma must be distinguished from pituitary adenoma and craniopharyngioma, both of which alter the sella turcica; craniopharyngioma also contains cysts.
Figure 6.106 A large intraventricular meningioma on enhanced CT is hyperdense like a choroid plexus papilloma, but lacks a cauliflower-like appearance.Figure 6.107 Meningioma en plaque (a) and hyperostosis (b).
Meningioma en plaque appears on enhanced CT as hyperdensity spreading along the brain surface, sometimes with associated hyperostosis (Figure 6.107).
Original pages 464–467
Metastatic Brain Tumors
Most spread from lung or breast cancer. They can occur anywhere in the brain, commonly in the frontal lobe, and may be solitary or multiple. Growth often begins at the gray–white matter junction, where capillaries supply the tissue. CT is very useful for brain metastases because it shows their number, location, and associated edema in greater detail than other methods. Generally, CT shows well-defined homogeneous hyperdensity. Another important feature is extensive surrounding low-density edema, even when the tumor is small (Figure 6.108a). The tumor center may be hypodense. These appearances, together with multiple masses (Figure 6.108b), are the main diagnostic criteria for brain metastases. A solitary metastasis is difficult to distinguish from malignant glioma, and a history of the primary cancer is needed. Ring-shaped lesions must be distinguished from brain abscesses, which may also be solitary or multiple. A very thick, irregular wall on CT favors metastasis. Four types of metastatic tumors commonly hemorrhage: choriocarcinoma, melanoma, and lung and renal carcinomas(8). Nonenhanced CT shows a hyperdense hematoma within the tumor.
Figure 6.108 CT of metastatic brain tumors. a. Homogeneously hyperdense tumor with extensive surrounding hypodense edema. b. Multiple ring-shaped masses of varying sizes with brain edema.Figure 6.109 CT of pituitary adenoma. a. Enhanced CT shows hyperdensity and tumor extension into the left middle cranial fossa. b. Pituitary adenoma with an associated cyst.
Original page 467
Pituitary Adenoma
This tumor grows in the pituitary fossa, enlarging the sella turcica. It usually extends upward, but may also grow laterally, posteriorly, or anteriorly. A small intrasellar tumor is called a microadenoma; a large tumor is a macroadenoma. CT shows enlargement of the sella turcica in macroadenoma, but no sellar change in microadenoma. Nonenhanced CT shows increased tumor density, and enhanced CT shows well-defined hyperdensity (Figure 6.109a). Occasionally, a low-density cyst is present within the tumor (Figure 6.109b). Suprasellar or parasellar extension is best seen in coronal sections (Figure 6.110a, b), which clearly show the tumor’s relationships to the sphenoid sinus, sellar floor, pituitary gland and stalk, suprasellar cistern, optic chiasm, and third ventricle. These sections also reveal microadenomas, usually as low-density areas within the pituitary gland. The pituitary stalk may deviate away from the tumor. Marked suprasellar extension can obliterate the third ventricle and obstruct the foramen of Monro, producing obstructive hydrocephalus.
Original pages 467–470
Craniopharyngioma
This tumor arises above the sella turcica and does not cause sellar ballooning unless it originates within the sella. It usually consists of solid and cystic components. The cyst fluid contains cholesterol, and calcification is common. Nonenhanced CT therefore shows hyperdense calcification (Figure 6.111), which may be eggshell-like or form scattered small clumps, together with low-density cystic areas measuring below 0 because they contain fat. This combination with calcification is an important diagnostic criterion(9). Enhanced CT shows hyperdensity of the solid component. Without a cyst, the tumor may be difficult to distinguish from pituitary adenoma. As with pituitary adenoma, coronal imaging demonstrates suprasellar hyperdense tumor and calcification and low-density cysts (Figure 6.112). Some cases show parasellar extension.
Figure 6.110 a. Pituitary adenoma extending above the sella into the suprasellar region, clearly seen on coronal CT. b. Parasellar extension of pituitary adenoma is also well demonstrated on coronal CT.Figure 6.111 Nonenhanced CT of craniopharyngioma. a. Hyperdense calcification and isodense tumor. b. Coronal CT shows hyperdense calcification extending into the third ventricle.Figure 6.112 Craniopharyngioma on enhanced CT shows hyperdense areas (bone and tumor) and hypodense cysts, with suprasellar and parasellar extension.
Original page 470
Dermoid and Epidermoid
These ectodermal tumors are cystic and may have calcification in the cyst wall. Enhanced CT shows low-density cysts (Figure 6.113a, b) and hyperdense wall calcification. The two types are difficult to distinguish by CT.
Original page 470
Pineal Gland Tumors
These tumors arise from two cell groups(10). Pineal parenchymal cells give rise to pineocytoma and pineoblastoma, while germ cells give rise to germinoma, teratoma, and embryonal carcinoma. The tumor compresses the quadrigeminal plate, aqueduct of Sylvius, and posterior third ventricle. Pineal tumors generally contain both calcification and cysts, and distinguishing their types by CT is very difficult. Nonenhanced CT shows isodensity or slight hyperdensity, with obliteration of the posterior third ventricle and quadrigeminal cistern. There may be hyperdense calcification or hemorrhage, or small low-density cysts. Enhanced CT shows hyperdensity (Figure 6.114). Some patients have a pineal tumor together with a tumor near the anterior third ventricle or optic chiasm, called an ectopic pinealoma (Figure 6.115).
Original pages 470–474
Acoustic Neurinoma (Schwannoma or Neurilemmoma)
This tumor arises from the vestibular division of the acoustic nerve, either within the internal auditory canal or intracranially, most commonly beginning at the internal auditory meatus. It enlarges the surrounding bone and extends into the cerebellopontine angle cistern. A large tumor compresses cranial nerves, the brainstem, cerebellar peduncle, and ventricle, obstructing CSF flow. Nonenhanced bone CT shows clear enlargement of the internal auditory canal on the tumor side compared with the normal side (Figure 6.116a). If the tumor arises outside the auditory canal, the canal may remain normal in size. Bilateral acoustic neurinomas may enlarge both canals (Figure 6.116b). Acoustic neurinomas generally contain no calcification visible on CT, unlike meningiomas, which may be calcified. Enhanced CT shows homogeneous hyperdensity. Large tumors may contain low-density degenerative areas, with compression of the brainstem, middle cerebellar peduncle, and fourth ventricle (Figure 6.116c).
Figure 6.113 a. Cerebellopontine angle dermoid tumor with a low-density cyst on enhanced CT. b. Lateral ventricular epidermoid with a low-density cyst on enhanced CT.Figure 6.114 Pineal germinoma is hyperdense on enhanced CT (arrow). Note obliteration of the posterior third ventricle and quadrigeminal cistern, with hydrocephalus. Tumor seeding is present along both lateral ventricular walls (arrowheads).Figure 6.115 Pineal germinoma (long arrow) and suprasellar germinoma, or ectopic pinealoma (short arrow).Figure 6.116 Acoustic neurinoma. a. Enlargement of the internal auditory canal on the tumor side. b. Bilateral enlargement of the internal auditory canals due to tumors. c. A large acoustic neurinoma compresses the brainstem, cerebellum, and fourth ventricle.
An acoustic neurinoma smaller than 1.5 cm may not be clearly visible on CT alone because hyperdense petrous bone obscures it. It can be demonstrated more clearly by introducing air or water-soluble contrast medium in conjunction with CT (Figure 6.92).
Petrous ridge meningioma is also hyperdense, like an acoustic neurinoma, but does not enlarge the internal auditory canal. Some cases cause hyperostosis or contain visible calcification.
Original pages 474–475
CT in Treatment Follow-up
CT is useful for monitoring tumors both after surgery and when they have not been operated on. Some tumors are difficult to reach or still small; surgical exploration may cause further loss of brain function. CT should therefore be used to monitor their changes because it is harmless to the patient. A benign, slow-growing tumor may show little change over many years. If neurological symptoms do not worsen, surgery is not yet necessary.
Some tumors, such as pineal germinoma, are radiosensitive and can disappear after radiotherapy. CT is useful for assessing the response.
Postoperative complications, including hemorrhage or herniation, may cause death. CT demonstrates these complications very well.
For cystic tumors, CT can guide aspiration of cyst fluid to improve the patient’s symptoms. It can also guide stereotactic needle biopsy in some cases.
Original pages 475–477
MRI (MAGNETIC RESONANCE IMAGING)
MRI, also called NMR (nuclear magnetic resonance), is the newest investigation. It differs from C.T. in that it does not use ionizing radiation. MR imaging results from the interaction between the body’s hydrogen nuclei, placed in a strong external magnetic field generated by the MRI scanner, and radiofrequency waves. The patient is therefore not exposed to radiation, and being within the magnetic field is highly safe. Like C.T., MRI uses a digital computer to display tomographic images of the desired thickness. Because MR data are stored as MR signals, MRI has the advantage of producing clear axial, coronal, sagittal, oblique, and curved images as required. C.T. cannot do this as well; in particular, it cannot produce oblique or curved images.
The appearance of an MR image depends on the density of mobile hydrogen nuclei and their physical changes, expressed by T1 and T2 magnetic relaxation times (also referred to as T1- and T2-weighted images). Different MR sequence parameters produce tissue signals of varying brightness according to the tissue type. In routine clinical practice, T1-, T2-, or proton-density-weighted images are obtained to distinguish diseased tissue from normal brain.
On T1-weighted brain images, gray matter appears gray, white matter white, and CSF black. Skull bone produces no signal, whereas bone marrow fat produces a very bright signal. On T2-weighted images, gray matter appears white, white matter is less bright, and CSF is white. The degree of brightness depends on the degree of T2 weighting.
MRI diagnoses many diseases of the brain and spinal cord better than C.T. and clearly demonstrates lesions in different planes. It is particularly useful to neurosurgeons because it shows the relationship between a lesion and nearby structures before surgery, thus facilitating operative planning. The physics of MRI may be studied in general MRI textbooks and will not be discussed here.
Although MRI offers many advantages in diagnosing brain lesions, it also has shortcomings and is inferior to C.T. for some conditions. For example, C.T. provides excellent, detailed diagnosis of acute hemorrhage, whether outside the brain, within the brain substance, in the ventricles, or in the subarachnoid space. C.T. also demonstrates calcification and bony details well. MRI does not show bone because its low mobile-hydrogen content produces no signal (a signal void). This characteristic is also an advantage, however: MRI does not produce the bone artifacts commonly encountered on C.T. at the skull base or foramen magnum. MRI is therefore particularly suitable for investigating skull-base lesions, showing them more clearly and in greater detail than C.T. It also better demonstrates several other conditions, including hemorrhage at different stages, multiple sclerosis plaques, intracanalicular acoustic neuromas, occult brainstem abnormalities, cavities within the spinal cord, and normal and abnormal cerebral vessels, such as AVMs. All these are well demonstrated by MRI without contrast injection and without bone artifacts, even when a lesion lies immediately adjacent to bone.
MRI is routinely performed in three planes: axial, coronal, and sagittal. Coronal sections clearly demonstrate lesions of the pituitary gland, orbits, petrous pyramids, skull base, and regions near the vertex. Sagittal sections show the details and relationships of midline tumors to adjacent structures particularly well, more clearly than C.T. They are therefore suitable for investigating lesions of the pituitary gland, diencephalon, brainstem, and spinal cord. In practice, when the clinical examination suggests a lesion in one of these locations, MRI should be performed because it provides better results and greater benefit than C.T.
Original pages 477–478
CONTRAST INJECTION
The intravenous contrast material currently accepted as safe for MRI is Gd-DTPA (gadolinium-labeled diethylenetriamine pentaacetic acid, also known as gadopentetate dimeglumine). It enhances T1 and T2 relaxation, producing T1 hyperintensity (Figure 6.126c) and T2 hypointensity. The indications for contrast injection are similar to those for contrast-enhanced C.T.: extra-axial brain tumors, tumors at the skull base, and intra-axial tumors, particularly metastatic brain tumors.
Contrast enhancement in MRI is especially useful for demonstrating the relationship between a brain tumor and surrounding cerebral edema(15) and for better defining the tumor’s characteristics. In general, tumors with a high malignancy grade enhance more than low-grade tumors.(16) However, the intensity of enhancement does not necessarily correlate with tumor grade. Extra-axial tumors consistently show marked enhancement.
MRI detects and localizes brain tumors much more clearly than C.T., but it still cannot unequivocally demonstrate the specific features of every tumor type. Accurate diagnosis requires consideration of differences in signal intensity. Most brain tumors have a high proton density, with prolonged T1 and T2 on spin-echo sequences. Tumors therefore appear hypointense on T1-weighted images and hyperintense on T2-weighted images. Studies show that T1 hyperintensity occurs with subacute and chronic hemorrhage (methemoglobin), melanin, fat, high protein concentration, slowly flowing blood, iodinated or paramagnetic intravenous contrast enhancement, and paramagnetic cations such as manganese, iron, and copper. T2 hypointensity occurs with low proton density (for example, calcification, dense cellularity, and fibrocartilage), paramagnetic effects (iron, hemosiderin, deoxyhemoglobin, melanin, and intracellular methemoglobin), macromolecular content (high protein concentration), and signal void caused by rapidly flowing blood.(17,18) Knowledge of these signal intensities, considered together with the characteristic features of each lesion and the clinical history, enables more accurate and definite MRI diagnosis of brain tumor types.
The MRI characteristics of a brain tumor depend mainly on its water content, particularly extracellular water. Occasionally, other components develop within a tumor, including calcium, fat, blood, necrosis, edema, and cysts. These alter its MRI appearance according to their composition. Considered together with other features, they improve the accuracy of tumor diagnosis. The MRI appearances of tumors containing these various components are briefly described below.
Original pages 478–479
Cerebral Edema
As discussed in earlier chapters, brain tumors can cause cerebral edema. This occurs with metastatic and malignant brain tumors, as well as with benign tumors such as meningiomas. MRI demonstrates edema very well. On T1-weighted images, edematous tissue has lower intensity than brain tissue and appears darker; on T2-weighted images, it has higher intensity and appears white (Figure 6.126b). This high intensity sometimes makes it difficult to distinguish the tumor margin from surrounding edema, because the extracellular spaces in both the tumor and white matter contain water. Low-grade astrocytomas have relatively little vascular permeability to contrast material and therefore show no enhancement on contrast C.T., despite increased water within the tumor. In such cases, MRI demonstrates tissue abnormalities and their extent better than C.T. MRI often shows a different signal in the tumor from that in the surrounding edematous brain. On T2-weighted images, edema has higher intensity (appears whiter) than the tumor, indicating more extracellular water in white matter than in the densely cellular tumor region.(19) Necrotic or cystic portions of a tumor appear markedly hypointense (darker) on T1-weighted images, whereas edema is better demonstrated on T2-weighted images.
Original pages 479–480
Cyst
Many brain tumors contain cysts, including craniopharyngiomas, colloid cysts, and various malignant tumors. Some are cystic from the outset, such as colloid and epidermoid cysts. Others develop cysts from tumor-cell necrosis or hemorrhage in the center of the tumor, producing a high-protein cyst with a variable MRI appearance. In general, cysts in malignant tumors have irregular walls and may show fluid levels. Their fluid signal differs from CSF, with a shorter T1 relaxation time and a brighter appearance on film. MRI’s ability to characterize cyst fluid allows better assessment of cystic brain tumors than C.T.(20) For example, C.T. cannot distinguish the density of fluid in a cystic astrocytoma from that of CSF, whereas MRI clearly distinguishes a CSF-containing cyst from a high-protein cyst such as a cystic astrocytoma or a hemorrhagic cyst. High-protein fluid has a shorter T1 relaxation time than CSF, so the cyst appears brighter than CSF on MRI (Figure 6.120a). When cyst fluid separates into two layers, the layers have different MRI appearances. The upper, lower-protein layer has a longer T1 relaxation time than the lower, higher-protein layer. On T1-weighted images, the upper layer consequently appears darker than the lower layer, though not as dark as CSF.
Original page 480
TUMOR HEMORRHAGE
Intratumoral hemorrhage generally involves only part of a tumor. MRI demonstrates characteristic blood appearances well in subacute and chronic hemorrhage. On T1-weighted images, an acute hematoma (0–2 days) is isointense to brain tissue, while surrounding vasogenic edema is less intense (darker) because of its longer T1. In the subacute stage, the periphery of the hematoma changes to methemoglobin, which has a very short T1. T1-weighted images therefore show increased intensity,(21) or a whiter appearance (Figure 6.117a, b). In the chronic stage, all deoxyhemoglobin in the center of the hematoma has changed to methemoglobin, and the surrounding vasogenic edema disappears. The hematoma is hyperintense,(22) with surrounding isointense hemosiderin. With further passage of time, the former hematoma becomes hypointense.
Original page 480
Calcification
Calcification in a tumor is important in diagnosing its type. C.T. demonstrates calcification better than MRI.(14) Calcification produces no MRI signal (a signal void) and therefore appears dark (Figure 6.118).
Original pages 480–483
Fat
Fat-containing tumors such as lipomas and teratomas appear bright on T1-weighted MRI and fade on T2-weighted images.
Figure 6.117. MRI appearances in a patient with subacute intratumoral hemorrhage. a. Non-contrast C.T. clearly demonstrates the hematoma. b. On T1-weighted MRI, the hematoma is hyperintense and surrounded by hypointense cerebral edema. c. On T2-weighted MRI, both the hematoma and surrounding edema are hyperintense.Figure 6.118. a. Calcification produces no MRI signal (signal void) and appears dark (hypointense). b. C.T. clearly demonstrates the calcification.
Original page 483
MRI Characteristics of Individual Brain Tumors
Different intra-axial and extra-axial brain tumors have different MRI appearances, depending on their internal components as described above. Knowledge of the pathological and MRI characteristics of each type permits more accurate and definite diagnosis. The MRI appearances of individual brain tumors are briefly described below.
Original page 483
Glial Tumors
These tumors arise within the brain substance. Common members of this group include astrocytoma, oligodendroglioma, and ependymoma, with further variation according to malignancy. Abnormal signals produced by glial tumors can be divided into five categories:(17) signals from the tumor itself, cystic change, necrosis, edema, and neovascularity with loss of the blood–brain barrier, clearly demonstrated by contrast enhancement. All these changes increase brain water content and thus prolong T1 and T2 relaxation times. Consequently, MRI shows hypointensity on T1-weighted images and hyperintensity on T2-weighted images. Gliomas with central cystic change and necrosis show hypointensity on T1-weighted images.
Original pages 483–484
Astrocytoma
Astrocytomas may be divided into low-grade (benign) astrocytoma, anaplastic astrocytoma, and glioblastoma multiforme (malignant). MRI improves localization of these tumors. For example, a low-grade astrocytoma has almost the same density as brain tissue on C.T., making its location and extent indistinct. Even contrast C.T. shows no enhancement. MRI defines its margins more clearly (Figure 6.119) because it distinguishes water within the tumor from water in the surrounding edematous brain. Nevertheless, MRI remains no better than C.T. at identifying the tumor type. Tumors in this group are more conspicuous after Gd-DTPA contrast injection.
Figure 6.119. Low-grade astrocytoma of the frontal lobe. a. Contrast C.T. shows no enhancement. b. T1-weighted imaging shows slight hypointensity. c. T2-weighted imaging shows hyperintensity.
Original pages 484–486
Glioblastoma Multiforme
MRI demonstrates differences among the components of this tumor (Figure 6.120a, b, c). i) Central necrosis is hypointense on T1-weighted images and hyperintense on T2-weighted images. ii) Densely cellular, highly vascular tumor often forms an irregular ring around the central necrosis. It is hypointense on T1-weighted images and hyperintense on T2-weighted images, but the T2 hyperintensity is relatively modest (not very white on film) because of the glial cells, vascular proliferation, and abundant blood flow characteristic of glioblastoma multiforme. Contrast MRI shows marked enhancement of this component. iii) Abnormal vessels supplying the tumor and large draining veins produce signal voids and appear dark. iv) Edematous brain is hypointense on T1-weighted images and hyperintense on T2-weighted images. v) Areas of intratumoral hemorrhage appear hyperintense on both T1- and T2-weighted images.
Figure 6.120. MRI appearances of glioblastoma multiforme. a. Central necrosis is hypointense on T1-weighted imaging, surrounded by less hypointense cerebral edema. Cyst fluid appears brighter than CSF. b. Necrotic and edematous regions show increased intensity (appear whiter) on proton-density imaging. c. Contrast T1-weighted MRI clearly defines the tumor margins.
Original page 486
Oligodendroglioma
This is a slowly growing glioma, usually containing calcification. Intratumoral hemorrhage may occur, so MRI can show several different appearances. Calcified areas are hypointense, whereas areas of previous hemorrhage are hyperintense on T1-weighted images.
Original page 486
Brainstem Glioma
MRI is very useful for brainstem glioma. It shows the tumor more clearly than C.T., without interference from bone artifacts, and produces excellent sagittal images. The brainstem tumor is hypointense on T1-weighted images and hyperintense on T2-weighted images (Figure 6.121a, b, c). The pons is enlarged and the fourth ventricle compressed. Intravenous contrast produces conspicuous enhancement.
Original page 486
Cerebellar Astrocytoma
This is a common childhood tumor, second to medulloblastoma, and includes benign pilocytic and fibrillary astrocytomas. The tumor may be solid without a cavity, or cystic with a mural nodule in the cyst wall. On MRI, the solid tumor is hypointense on T1-weighted images and hyperintense on T2-weighted images. The cystic portion has lower intensity than the solid portion on T1-weighted images and higher intensity on T2-weighted images. Cyst fluid has higher intensity (is whiter) than water on T1-weighted images and may form fluid levels. Intravenous contrast produces very clear enhancement.
Original pages 486–488
Ependymoma
On MRI, this tumor is hypointense on T1-weighted images and hyperintense on T2-weighted images. Patches of T1 hyperintensity may indicate previous intratumoral hemorrhage. Some tumors contain scattered signal voids caused by calcification. Important diagnostic features are an intraventricular location, clearly defined margins, and obstruction of CSF flow causing hydrocephalus. Contrast MRI may show tumor seeding along the ventricular ependyma and in the subarachnoid space.
Figure 6.121. MRI appearances of brainstem glioma. a. Sagittal T1-weighted image shows a clearly defined hypointense tumor. b. T2-weighted image shows hyperintensity. c. Axial proton-density image shows a hyperintense tumor.
Original page 488
Choroid Plexus Papilloma
This intraventricular tumor commonly occurs in the trigone of the lateral ventricle and in the fourth ventricle. It has a cauliflower-like appearance and is always associated with hydrocephalus, because the tumor produces excessive CSF and may occasionally bleed into it. A fourth-ventricular tumor can rapidly obstruct CSF flow. The intraventricular location, together with these features, helps establish the diagnosis. Choroid plexus papilloma is highly vascular and may contain calcification. It is hypointense or isointense to brain on T1-weighted images, and hypointense to CSF on T2-weighted and proton-density-weighted images. Contrast MRI shows very marked enhancement.
Original pages 488–489
Medulloblastoma
This tumor consists of densely packed primitive cells and is usually located in the cerebellar vermis. Obstruction of the fourth ventricle causes hydrocephalus. Most tumors are solid without cysts, although large tumors may contain cysts or necrosis. MRI shows hypointensity on T1-weighted images and isointensity or slight hyperintensity on T2-weighted images (Figure 6.122). The isointensity or limited hyperintensity on T2-weighted images reflects the high cellular density and low interstitial water content.(24) This distinguishes medulloblastoma from cerebellar astrocytoma on MRI. Intravenous gadolinium produces conspicuous tumor enhancement and can also demonstrate tumor cells disseminated through the subarachnoid space.(25)
These signal characteristics, together with a vermian location and subarachnoid dissemination, are important in diagnosing this tumor.
Figure 6.122. Sagittal MRI of a medulloblastoma in the cerebellar vermis. a. On T1-weighted imaging, the tumor is isointense and its cystic portion hypointense. b. On proton-density and T2-weighted imaging, the tumor is slightly hyperintense.
Original pages 489–491
Colloid Cyst
This is a round, smooth-walled cyst containing mucinous fluid, located in the third ventricle near the foramen of Monro. MRI shows hyperintensity on both T1- and T2-weighted images. However, the signal varies with the amounts of mucin, iron, and hemosiderin in the cyst, so its appearance is not constant.(26,27,28,29) The key diagnostic feature is therefore a smoothly marginated mass in the third ventricle close to the foramen of Monro.
Figure 6.123. MRI of hemangioblastoma. a. Sagittal T1-weighted image shows a heterogeneously hypointense cerebellar tumor. b. Axial image shows vessels within and on the surface of the tumor (arrows). They are hypointense on both T1- and T2-weighted images because the vessels produce no MR signal (signal void).
Original page 491
Hemangioblastoma
This benign vascular tumor commonly occurs in the posterior fossa, especially the cerebellum. It contains numerous small and large sinusoidal vessels, so intratumoral hemorrhage is common. The tumor may be solid or a cyst with a mural nodule; the cystic form is less common. Multiple hemangioblastomas may occur in one patient. MRI shows a mixture of T1 and T2 intensities reflecting solid tumor, cyst, vessels, intratumoral hemorrhage, and fat. The following appearances may therefore be seen:(30) i) A cyst, or a cyst with a mural nodule; the cyst is hypointense on T1-weighted images and hyperintense on T2-weighted images. ii) Areas of T1 hyperintensity within the tumor indicate previous hemorrhage or fat within the tumor stroma, which shortens T1. iii) Previous hemorrhage produces hemosiderin within and around the hemangioblastoma, appearing as curved hypointense areas. iv) Vascular signal voids appear as hypointense structures within or around the tumor. Their size varies with the vessels supplying or draining the tumor (Figure 6.123a, b).
Important diagnostic features of hemangioblastoma are a cyst with a mural nodule and vascular signal voids. Contrast MRI clearly demonstrates the mural nodule.
Original pages 491–492
Meningioma
This is an extra-axial tumor, usually attached to the dura and clearly circumscribed. When large, it compresses the cortex, subarachnoid CSF, and cortical vessels; some cases also have cerebral edema. MRI demonstration of these changes is important for diagnosis. Meningiomas are generally isointense to brain or slightly hypointense on both T1- and T2-weighted images, although some may be slightly hyperintense on T2-weighted images. After contrast injection, there is marked enhancement and a “dural tail sign”: thickened, enhancing dura adjacent to the tumor margin resembles a tail extending from the meningioma (Figure 6.124b). Enhancement is often heterogeneous because the tumor may contain calcification, varying vascularity, and sometimes small cysts. A hypointense band of subarachnoid CSF and vessels separates the meningioma from the compressed gyri (Figure 6.124a). Some cases show surrounding edema, with T1 hypointensity and T2 hyperintensity. MRI demonstrates extension into a dural venous sinus better than C.T.(31) MRI may also show skull thickening from hyperostosis as a signal void.
Figure 6.124. MRI of meningioma. a. The tumor is hypointense on T1-weighted imaging. Note the hypointense band of subarachnoid CSF and vessels between the tumor and gyri (arrows), an important diagnostic feature. b. Contrast MRI shows the characteristic “dural tail sign” (arrow).
Original pages 493–494
Schwannomas
The most common tumor in this group is an acoustic nerve schwannoma. It is a well-circumscribed extra-axial tumor surrounded by CSF in the basal cistern. It may lie within the internal auditory canal (intracanalicular) or extend outside the canal into the intracranial cerebellopontine angle (extracanalicular). MRI is the best method for diagnosing acoustic neurinoma. It does not require intrathecal air or metrizamide contrast as C.T. does, and there is no artifact from adjacent bone, even with a small tumor. It clearly shows the details of both intracanalicular and extracanalicular tumors. The tumor is hypointense on T1-weighted images and hyperintense on T2-weighted images, more so than meningioma. The cistern on the affected side is enlarged; occasionally a cyst lies over the posterior surface of the tumor. Contrast injection produces marked enhancement, particularly of the intracanalicular component.(32,33,54) (Figure 6.125a, b, c)
Figure 6.125. MRI of acoustic neurinoma. a. Axial T1-weighted image shows a hypointense tumor compressing the cerebellar peduncle, pons, and fourth ventricle. b. The tumor is hyperintense on T2-weighted imaging. c. Coronal contrast image shows marked enhancement within the internal auditory canal (arrow) and intracranially, with multiple intratumoral cysts.
Original pages 494–497
Metastatic Tumors
The pathological characteristics of metastatic brain tumors are: i) They are commonly located at the junction of gray and white matter. ii) They may be solitary or multiple. iii) Marked edema always surrounds the tumor. iv) Some tumors contain hemorrhage. v) They show marked contrast enhancement, which may be homogeneous, heterogeneous, or ring-like when there is central necrosis. vi) Tumor cells may spread into the ventricles and subarachnoid space. MRI clearly demonstrates all these features. Contrast MRI is the best examination for metastatic tumors in the brain, ventricles, subependymal and ependymal regions, cisterns, and subarachnoid space. Bone produces no signal, so an enhancing tumor adjacent to bone is clearly visible (Figure 6.126c). This is particularly useful in the posterior fossa. Metastatic tumors are hypointense on T1-weighted images and hyperintense on T2-weighted images. On T2-weighted images the surrounding edema is hyperintense (Figure 6.126a, b, c), and is more readily distinguished from the tumor than in primary brain tumors.(19)
Figure 6.126. MRI of a metastatic tumor. a. T1-weighted image shows hypointensity of the tumor and surrounding edema. b. On T2-weighted imaging, the tumor is hyperintense but less intense than the edema, allowing the two to be distinguished (arrows). c. Contrast T1-weighted image clearly demonstrates the tumor.
Two types of metastatic tumor have characteristic appearances: mucinous adenocarcinoma and malignant melanoma. Both are hypointense on T2-weighted images.
MRI best demonstrates hemorrhage within metastatic tumors because it is sensitive to blood and hemoglobin breakdown products, helping to distinguish these lesions from ordinary hemorrhage.(34) The distinguishing features are: i) Reduced T2 signal persists longer because deoxyhemoglobin continues to be produced.(34,35) ii) Hypointensity may persist for weeks or months. iii) Repeated hemorrhage produces a heterogeneous appearance, with blood of different ages in different locations: recent hemorrhage is hypointense, subacute hemorrhage hyperintense, and old hemorrhage has a hypointense hemosiderin rim. iv) There is marked contrast enhancement.
Malignant melanoma contains melanin, a paramagnetic substance,(36) and tends to bleed. Its appearance depends chiefly on whether hemorrhage is present. Without hemorrhage, it is hyperintense on T1-weighted images and slightly hypointense or isointense on T2-weighted images. When hemorrhage is present, the appearance varies with its age. Contrast enhancement is homogeneous.
Mucinous adenocarcinoma is hypointense or isointense on T1-weighted images and hypointense on T2-weighted images, probably because of its high protein content.(37)
Original page 497
Leptomeningeal Metastasis
Tumor cells spread to the leptomeninges and through the CSF in the subarachnoid space, involving the basal cisterns, Sylvian fissures, cortical sulci, and ventricles and causing hydrocephalus. Primary CNS tumors that commonly spread in this way include medulloblastoma, ependymoma, pinealoblastoma, and retinoblastoma.(38,39) Lymphoma, leukemia, and melanoma can also do so. Noncontrast MRI generally cannot demonstrate this dissemination at all. Contrast injection produces marked enhancement, and MRI demonstrates it better than C.T.(40) Enhancement in the basal cisterns, Sylvian fissures, cortical sulci, and tentorium is usually nodular, rather than the smooth diffuse enhancement seen with inflammation.(41)
Original pages 497–499
Pituitary Adenoma
MRI clearly demonstrates tumor margins, particularly in coronal and sagittal sections, showing its size, extent, and relationship to nearby important structures and thus helping the surgeon plan treatment. Pituitary adenomas are classified as microadenomas, smaller than 1 cm, and macroadenomas. MRI is better than C.T. for microadenomas. Most are hypointense relative to the normal gland on T1-weighted images, with variable T2 signal. They enhance less than normal pituitary tissue (Figure 6.127a, b). Most lie laterally, causing bulging of the gland and displacement of the stalk to the opposite side.(42) (Figure 6.127c) Most prolactin-secreting microadenomas do not enhance.(43,44) ACTH-secreting microadenomas enhance late after Gd-DTPA injection.
Figure 6.127. Pituitary microadenoma. a. T1-weighted image shows an isointense lesion. The internal carotid arteries on both sides appear as hypointense signal voids (arrows). b. The microadenoma enhances less than the normal gland (arrow). c. The pituitary stalk is displaced away from the adenoma.
For macroadenomas, MRI clearly shows the size, extent, and relationships, as well as cysts, necrosis, and hemorrhage. Solid tumor is hypointense or nearly isointense on T1- and T2-weighted images and enhances homogeneously (Figure 6.128a, b, c). Cystic and necrotic areas have T1 intensity between that of CSF and solid tumor and are hyperintense on T2-weighted images. Hemorrhage is clearly demonstrated; in the subacute stage, methemoglobin causes hyperintensity on both T1- and T2-weighted images.(45) Coronal and sagittal images excellently demonstrate compression of the optic chiasm, cavernous sinus, and internal carotid artery, and extension into the interpeduncular fossa.
Original pages 499–502
Craniopharyngioma
This tumor occurs in the region of the sella turcica. It may be intrasellar, suprasellar—the most common location—or, less commonly, intraventricular in the third ventricle. The tumor usually contains cysts and calcification. The cyst fluid is brown, with a high protein content and numerous cholesterol crystals. In children, craniopharyngioma is the most common tumor in the sellar region with these characteristics. MRI is the best investigation because it differentiates tissue types and clearly demonstrates the relationship of the tumor to adjacent structures in coronal and sagittal planes. C.T., however, demonstrates calcification better. In general, the cystic component of a craniopharyngioma is hyperintense on T1-weighted images because of cholesterol crystals within it; a cyst without cholesterol is slightly hypointense. On T2-weighted images it is hyperintense (Figure 6.129a, b). Noncalcified solid tumor is isointense on T1-weighted images and hyperintense on T2-weighted images. Calcification is hypointense on both T1- and T2-weighted images because bone produces no signal (signal void). After contrast injection, the solid tumor and cyst wall enhance clearly on T1-weighted images.
Figure 6.128. Pituitary macroadenoma. a. Coronal T1-weighted image shows an isointense tumor. Note its upward expansion, compressing the optic chiasm and third ventricle. b. Proton-density-weighted image shows homogeneous hyperintensity. c. Sagittal image clearly demonstrates extension of the pituitary tumor into other regions.Figure 6.129. MRI of craniopharyngioma. a. Sagittal T1-weighted image shows a craniopharyngioma that is not as hypointense as CSF. The tumor has suprasellar and retrosellar extension. b. Coronal T2-weighted image shows hyperintensity.
Original page 502
Pineal Tumors
Tumors in this region fall into three groups.
Tumors arising from germ cells: germinoma and teratoma
Tumors arising from pineal cells: pineocytoma and pineoblastoma
Tumors arising from glial cells, such as gliomas, and others
The most common tumor in this region is germinoma, followed in descending order of frequency by teratoma, pineoblastoma, and pineocytoma.
On MRI, germinomas are isointense to gray matter on T1-weighted images and isointense or slightly hyperintense on T2-weighted images.(49,50) (Figure 6.130) Germinomas generally do not contain calcification, although they may coexist with pineal gland calcification. Contrast MRI shows hyperintensity. These tumors tend to extend into the third ventricle and disseminate through the CSF; consequently, deposits on the ventricular walls and in the subarachnoid space may be demonstrated on contrast MRI.
Original page 502
Teratoma
This tumor contains several types of tissue, including bone and fat, and often contains cysts. On MRI, fat produces hyperintensity on T1-weighted images, whereas bone or calcium and cysts are hypointense.
Original pages 502–503
Pineocytoma & Pineoblastoma
Both are tumors of pineal cells. Pineoblastoma is malignant and more common than pineocytoma. It consists of densely packed immature cells and is currently classified in the primitive neuroectodermal tumor (PNET) group. Both tumors are hypointense on T1-weighted MRI and hyperintense on T2-weighted MRI. Because these tumors contain calcification, hypointense areas of bone may be seen on both T1- and T2-weighted images.
Figure 6.130. MRI of germinoma. a. Axial T1-weighted image shows an isointense germinoma. b. T2-weighted image shows slight hyperintensity. c. Sagittal postcontrast image shows clear enhancement of the germinoma (short arrow). Note a second, ectopic germinoma in the suprasellar region (long arrow).
Original pages 503–504
Epidermoid Tumors (Pearly Tumors)
These are the most common congenital intracranial tumors, followed by dermoids, lipomas, and teratomas, in that order. They commonly occur in the cerebellopontine angle and parasellar region. The tumor consists of an epithelial cyst wall and fluid containing keratin. Calcification is uncommon. Epidermoids generally appear hypointense on T1-weighted MRI and hyperintense on T2-weighted MRI,(51) (Figure 6.131a, b) without enhancement after Gd-DTPA injection. Horowitz et al.(52) described two MRI types: black epidermoids and white epidermoids. The former are solid masses of pearly keratin without triglycerides, and therefore appear hypointense on T1-weighted images. The latter are cystic lesions containing triglycerides and consequently have a higher signal intensity (a whiter appearance) on T1-weighted images.
Original page 504
Dermoid Tumors
These thick-walled cysts occur along the midline of the brain, commonly in the posterior fossa, and often have calcification in their walls and contents. The cyst contents have two components: the lighter, fat-containing component lies above, while the keratin protein component lies below. A dermoid therefore has a heterogeneous MRI appearance (Figure 6.132). The fatty component is hyperintense on T1-weighted images; the lower component is hypointense or dark, although not as dark as CSF. On T2-weighted images, all the contents are hyperintense.(53) Calcified areas produce signal voids and appear dark. If a dermoid ruptures, fat droplets disseminate to multiple sites in the subarachnoid space. On T1-weighted MRI they appear as hyperintense foci in the basal cisterns and throughout the subarachnoid space.
Original pages 504–506
Lipomas
These commonly occur in midline structures such as the corpus callosum and quadrigeminal plate. Some have eggshell-like calcification. MRI clearly demonstrates the characteristic fat within the lipoma: hyperintensity on T1-weighted images and isointensity or hyperintensity on T2-weighted images. A lipoma of the corpus callosum may be associated with a visible abnormality of the corpus callosum.
Figure 6.131. MRI of epidermoid tumor. a. T1-weighted image shows hypointensity without definite enhancement of the wall. b. T2-weighted image shows hyperintensity.Figure 6.132. MRI of dermoid tumor. a. Coronal T1-weighted image shows heterogeneous hypointensity. b. Axial T2-weighted image shows hyperintensity. c. The tumor does not enhance with contrast.
Original pages 506–507
Chordoma
This tumor arises from notochordal remnants. Within the skull it commonly occurs at the clivus and sphenoid bone. It is a locally destructive tumor, appearing as a mass anterior to the brainstem and displacing it posteriorly. MRI shows hypointensity or isointensity on T1-weighted images and hyperintensity on T2-weighted images. Some tumors contain hemorrhagic foci that are hyperintense on both T1- and T2-weighted images. In others, fragments of bone and bone marrow within the tumor produce mixed intensities on both sequences. Clival chordomas are well demonstrated in the sagittal plane.
Original page 507
Obsolete Investigations
Before C.T. and MRI were introduced for detecting brain tumors, several other examinations could establish the diagnosis, including:
ventriculography
pneumoencephalography
radioisotope brain scan
echoencephalography
EEG
These examinations have now been discontinued because they do not provide the detail obtained with C.T. Some cause distress and pain, and occasionally serious complications. C.T. is far superior: it is reliable and clearly demonstrates the location, size, sometimes the type of tumor, and its effects, such as cerebral edema, hydrocephalus, and herniation, without pain or danger to the patient.
Nevertheless, these examinations will be described briefly to provide an understanding of investigations that have become historical. If necessary, they may still be used to investigate tumors on certain occasions and in particular circumstances.
Original pages 507–509
Ventriculography
Air or radiopaque contrast is injected to replace CSF in the ventricles, to demonstrate hydrocephalus, the site of CSF pathway obstruction, and tumors within or adjacent to the walls of the lateral, third, and fourth ventricles. Examination using air is called air ventriculography; that using radiopaque material is called positive-contrast ventriculography. Ventriculography is performed when angiography does not clearly demonstrate an intracranial abnormality. The surgeon must always be prepared to operate immediately if necessary, because complications may be fatal.
Technique: Under local anesthesia, a frontal burr hole is made over the nondominant hemisphere, anterior to the coronal suture and approximately 2–2.5 cm from the midline. The dura is opened and a catheter containing a stylet is passed toward the ventricle, almost perpendicular to the surface and angled slightly medially toward the ipsilateral inner canthus. At a depth of approximately 5 cm, the catheter tip enters the frontal horn of the lateral ventricle and CSF is obtained. Alternatively, the burr hole may be placed in the posterior temporal region, 3 cm above and 3 cm behind the ear, or in the posterior parietal region, just above the lambdoid suture and 3–3.5 cm from the midline.
For air ventriculography, before air is injected the opposite side of the head is placed uppermost, or the patient is positioned prone, to prevent air escaping through the catheter. The volume of CSF removed must balance the volume of air injected; otherwise, air pressure may dangerously increase intracranial pressure. After the required amount of air has been introduced, the head is repositioned to direct it to the desired site and reveal the abnormality, and skull radiographs are obtained. If the foramina of Monro are unobstructed, air enters both lateral ventricles and the third ventricle (Figure 6.133).
Figure 6.133. Air ventriculogram showing air within the lateral ventricle.
For positive-contrast ventriculography, the radiopaque agents used include Myodil, Pantopaque, and Conray 60. Only 3–4 c.c. of Myodil or Pantopaque is required; the head is then repositioned to allow Myodil to enter the third ventricle, aqueduct, and fourth ventricle (Figure 6.134). When Conray 60 is used, 6 c.c. is mixed with 6 c.c. of CSF and injected back into the ventricle. Conray flows through the ventricular system, allowing the whole system to be seen on radiographs.
Figure 6.134. Conray ventriculogram showing the lateral ventricle, posterior third ventricle, aqueduct of Sylvius, and fourth ventricle displaced posteriorly by a brainstem tumor.
Original pages 509–511
Pneumoencephalography
Air is injected into the ventricular system through a lumbar puncture. This examination causes headache, distress, sweating, and faintness, and is hazardous, particularly in patients with raised intracranial pressure or a posterior fossa tumor, because it may cause tonsillar herniation, respiratory arrest, and loss of consciousness. In the author’s opinion, this should be the last investigation considered.
Technique: The patient sits with the head slightly flexed so that air can readily rise into the fourth ventricle. A lumbar puncture is performed, and air is injected in a volume equal to the CSF removed, approximately 5 c.c. at a time. Skull radiographs are obtained in the sitting position after each additional injection. If air does not enter the ventricles, the head must be repositioned. To show the third ventricle, aqueduct, and fourth ventricle clearly, tomography is performed by having the patient turn the head from side to side while remaining seated and obtaining a lateral image (Figure 6.135). This method clearly depicts only the midline structures. The patient may then be repositioned to move the air into other desired locations, followed by radiographs to demonstrate abnormalities.
Figure 6.135. Pneumoencephalogram during tomography. Air in the basal cistern outlines a suprasellar mass (arrow). Note the third ventricle (3), aqueduct of Sylvius (AS), and fourth ventricle (4).Figure 6.136. Tc99 brain scan showing a frontal lobe tumor (arrows).
If a tumor is suspected at the base of the brain, such as in the suprasellar region or cerebellopontine angle, it may be demonstrated by injecting air with the patient seated and the head extended. Air then enters the basal cisterns and subarachnoid space (Figure 6.135).
Original page 511
Brain Scan
A radioisotope is injected intravenously, and a scanning detector records an image on paper or X-ray film, demonstrating intracranial pathology. This is suitable as a screening examination to identify patients with brain lesions and may be performed on outpatients. The isotope used is technetium (Tc 99m). When an abnormality is found, further investigations are performed to establish the diagnosis, using angiography or ventriculography according to the individual case (Figure 6.136).
Original pages 511–512
Echoencephalography
Ultrasound is used to locate the brain’s midline and intracerebral masses. When ultrasound strikes the skull, midline structures, or a mass, reflected echoes allow their positions to be identified. A mass on one side of the skull shifts the midline to the opposite side. The ultrasound reflections have no features specific to tumors, so this method is insufficient for preoperative diagnosis and must always be supplemented by angiography or another investigation. Echoencephalography is therefore used only for screening.
Original page 512
EEG
This records the electrical activity of the brain and is appropriate only for patients with epilepsy. It is not useful for determining whether a patient has a brain tumor, because the changes in brain electrical activity are not specific to tumors. EEG indicates only the location of abnormal electrical activity; other investigations are required to determine the cause.
Original pages 512–514
References · Chapter 6
Taveras J.M., Wood E.H., Diagnostic Neuroradiology. William and Wilkins Co., Baltimore.
Huang, V.P., and Wolf B.S., The veins of the posterior fossa-superior galenic draining group. Amer. J. Roentgen, 95 : 808-821, 1965.
Schechter M.M., Cerebral angiography in Youmans Neurological Surgery, Vol. 1, W.B. Sounders Co., p. 321-350, 1982.
Schechter M.M., Zingesser, L.H., and Rosenbraum, A.E.; Tentorial meningioma. Amer. J. Roentgen. 104 : 123-131, 1968.
Lee, S.H., Rao K.C.V.G. Primary tumors in adults. In Cranial Computed Tomography, Mc Graw-Hill Book Co., pp. 241-293, 1983.
Krischeff I.J., Pinto R.S., Bergeron R.T., et al : Air C.T. cisternography and canalography for small acoustic neuromas. AJNR 1 : 57-63, 1980.
Butler AR, Horri S.C., Krischeff I.I., et al : computed tomography in astrocytoma. Radiology 129 : 443-439, 1978.
Robertson W.D., : Neoplasms of the brain, cranial nerves and meninges. In Text-book of Diagnostic Imaging. W.B. Saunders Co., pp. 218-243, 1988.
Russell D.S., Rubenstein L.J., Pathology of Tumors of C.N.S. Williams & Wilkins Co., Baltimore, 1977.
Huk W., Baer, U : A new targeting device for stereotaxic procedures within the C.T. scanner. Neuroradiology. 19:13-17, 1980.
Brown RA, Roberts T., Osborn A.G., : Simplified C.T. guide stereotaxic biopsy AJNR 2 : 181-184, 1981.
Darwin R.H., Drayer B.P., Riederer S.J., et al: T2 estimates in healthy and diseased brain tissue: a comparison using various MR pulse sequences Radiology 160 : 375-381, 1986.
Oot, R.F., New P.F.J., Pile-Spellman J. et al : The detection of intracranial calcification by MR. AJNR 7 : 801-809, 1986.
Felix R., Schorner W., Liniado M. et al : Brain tumors : MR imaging with gadolinium DTPA, Radiology 156 : 681,1985.
Graif M., Bydder G.M., Steiner R.E., et al: Contrast MR imaging of malignant tumors AJNR 6 : 855-862, 1985.
Smirniotopoulos J.G., Lee SH : Primary tumors in adults, in Cranial MRI and C.T. ed. by Lee S.H., Rao K.C.V.G. Zimmerman R.A., Mc Graw-Hill Inc. p. 307, 1992.
Atlas S.W.: Magnetic resonance imaging of the brain and spine, New York, Raven Press, 1991.
Zawadzki M.B., Kelly W., : Brain tumors in Magnetic Rosonance Imaging of Central Nervous System ed. by Zawadzki M.B., Norman D., Raven Press, p. 151-185, 1987.
Kjos B.O., Brant-Zawadzki M. Kucharczyk W., Kelly W.M., Norman D., Newton T., : Cystic intracranial lesions : magnetic resonance imaging. Radiology 155 : 363-369, 1985.
Bradley W.G., Schmidt P.C., Effect of methemoglobin formation on the MRI appearance of subarachnoid hemorrhage. Radiology, 156 : 99-103, 1985.
Gomori J.M., Grossman R.I., Goldberg H.I., et al : Intracranial hematomas : imaging by high field MR. Radiology 156, 1985.
Lee B.C.P., Kneeland J.B., Walker R.W., et al MR imaging of brain stem tumors. AJNR 6 : 159-163, 1985.
Zimmerman R.A., : Pediatric brain tumors. In Cranial MRI and C.T. ed. by Lee H, Rao, K.C.V.G. Zimmerman R.A. 3rd ed. Mc Graw-Hill Inc. p. 389. 1992.
Heideman R.L., Packer R.J., Albright, L.A., et al: Tumors of the central nervous system in Pizzo PA, Poplack D.G. (eds), Principles and Practice of Pediatric Oncology, Philadelphia, Lippicott, pp. 505-553, 1989.
Maeder P.P., Holtas S.L., Basibuyuk L.N., : Colloid cyst of the third ventricle : Correlation of MRI & C.T. findings with histology and chemical analysis AJNR 11 : 575-581, 1990.
Wilms G., Marchal G., Van Hecke P., et al colloid cysts of the third ventricle : MR findings J. comput. Assist. Tomogr. 14 : 527-531, 1990.
Roosen N., Gahlen D., Stork W., et al: Magnetic resonance imaging of colloid cysts of the 3rd ventricle. Neuroradiology 29 : 10-14, 1987.
Scotti G., Scialfa G., Colombo N., Landoni, L. : MR in the diagnosis of colloid cysts of the 3rd ventricle. AJNR 8: 370-372, 1987.
Lee S.R., Sanches J., Mark A.S., et al : Posterior fossa hemangioblastomas : MR imaging. Radiology 171 : 463-468, 1989.
Destian S., Sze G., Krol G., et al : MR imaging of hemorrhagic intracranial neoplasms. AJNR 9 : 1115-1122, 1988.
Wooddruff W.W. Jr., Djang W.T., Mc Lendon R.E., et al : Intracranial malignant melanoma : High-field strength MR imaging. Radiology 165 : 209-213, 1987.
Egelhoff J., Ross, J.S., Modic M.T., et al: Finding of MR imaging of adenocarcinoma metastatic to the brain, presented at the radiological society of North America annual meeting, Chicago, November. p. 25-30, 1990.
Rippe D.J., Boyko O.B., Friedman H.S., et al : Gd-DTPA enhanced MR imaging of leptomeningeal spread of primary intracranial CNS tumors in children AJNR 11: 329-332, 1990.
Sge G., Soletsky. S., Bronen R. et al : MR. imaging of the cranial meninges with emphasis on contrast enhancement and meningeal carcinomatosis AJNR 10 : 965-975, 1989, AJR 153 : 1039-1049, 1989.
Phillips M.E., Ryals T.J., Kambhu S., et al : Neoplastic V.S. inflammatory meningeal enhancement with Gd-DTPA. J. Comput. Assist. Tomogr. 14(4) : 536-541, 1990.
Kucharczyk W., Davis D.O., Kelly W.M., Pituitary adenomas : High resolution MR imaging at 1.5 T. Radiology 161 : 761-765, 1986.
Dwyer A.J., Frank J.A., Doppman J.L., et al : Pituitary adenomas with Cushing’s disease : Initial experiences with Gd-DTPA-enhanced MR imaging. Radiology 163 : 421-426, 1987.
Davis P.C., Hoffman J.C., Malko J.A., : Gadoliniun-DTPA and MR imaging of pituitary adenoma : a preliminary report AJNR 8 817-823, 1987.
Chakeres D.W., Curtin A., Ford G., : magnetic resonance imaging of pituitary and parasellar abnormalities. Radio. Clin. North Am. 27 (2) : 265-281, 1989.
Kyle C.L., Laster R.A., Burton E.M., et al : subacute pituitary apoplexy : MR. and C.T. appearance. J. Comput. Assist. Tomogr. 14 (1) : 40-44, 1990.
Karnaze M.G., Sartor K., Winthrop J.D., et al: Suprasellar lesion : Evaluation with MR imaging. Radiology 161 : 77-82, 1986.
Pusey E., Kortman K.E., Flannigan B.D., et al : MR of craniopharyngiomas tumor delineation and characterization. AJNR 8 : 439-444, 1987.
Tien R.D., Barkovich A.J., Edwards M.S.B., MR imaging of pineal tumors. AJNR 11: 557-565, 1990.
Zee C.S., Segall H., Apuzzo M., et al: MR. imaging of pineal region neoplasm. J. comput. Assist. Tomogr., 15 : 56-63, 1991.
Tampieri D., Malanson D., Ethier R. : MR imaging of epidermoid cysts AJNR 10 : 351-356, 1989.
Horowitz B.L., Chari M.V., James R., et al : MR of intracranial epidermoid tumors : Correlation of in vivo imaging with in vitro C. spectroscopy. AJNR 11 : 299-302, 1990.
Howard Lee Primary tumors in adults in Cranial MRI and C.T. p. 295-280, 1992.
Damoefs D.L., Miller S.J. Meyes G.A., : MR detection of tumor in the internal auditory canal AJNR 8: 249-252, 1987.
Original page 515
Chapter 7 · Treatment of Brain Tumors
As discussed earlier, a brain tumor impairs the function of the region in which it arises and, as it enlarges, adjacent regions. It also causes cerebral edema, obstruction of CSF pathways, and raised intracranial pressure. Various medical illnesses may further worsen the patient’s condition or compromise the results of surgery. All these factors must be considered when treating patients with brain tumors. The aim of treatment is complete removal without increasing the neurological deficit present before surgery, with the greatest possible recovery of lost function. Once the tumor has been completely removed, its effects—cerebral edema, obstruction of CSF pathways, and raised intracranial pressure—resolve toward normal. However, tumors in some locations cannot be completely removed, and some cannot be treated surgically at all, such as those in the brainstem, thalamus, and hypothalamus. These are vital brain regions, and surgery may cause death. Other methods must therefore be used to provide palliation for a period of time.
The treatment of brain tumors may be discussed in two parts:
General principles of treatment
Specific management of individual tumors according to their type and location
Original pages 515–518
General Principles of Brain Tumor Treatment
Brain tumors grow, and allowing time to pass permits them to enlarge, with progressive loss of neurological function. Once examination and investigation establish that a brain tumor is present, treatment must be carefully planned. Considerations include its location, size, and probable type based on imaging, cerebral edema, hydrocephalus, midline shift, and the patient’s condition. The general treatment plan is as follows:
1. Completely remove the brain tumor if its location permits this without loss of neurological function or life. This can cure the disease and is usually possible with well-circumscribed benign tumors. Malignant or infiltrative tumors are difficult to remove completely; even with an operating microscope, all tumor cells infiltrating brain tissue cannot be dissected away. When the tumor is completely removed, intracranial pressure, cerebral edema, tumor-related hydrocephalus, and midline shift may return to normal.
2. Perform subtotal excision, removing as much as possible without increasing neurological deficit. This relieves compression of the brain and is appropriate when complete removal is impossible. During surgery, the surgeon must exercise judgment as to whether removal is worth the risk, how much should be removed, and when an attempt at complete excision should be abandoned in the face of difficulty. The patient’s neurological function and life must always take priority. If complete removal of a benign tumor in a critical location might cause death or major disability, it should not be attempted; as much as safely possible should be removed instead. The patient may then improve for a period and continue living, but may eventually face a second operation. At that point, the question of reoperation must be reconsidered through a fresh neurological examination and imaging, such as C.T., comparing the findings with those before the first operation and carefully weighing the benefits and disadvantages. If a second operation would offer no benefit, other treatments should be sought. In general, the period of improvement after a second operation is shorter than after the first unless additional treatments are used. Lost neurological functions often do not recover, particularly with infiltrative tumors.
New, highly effective instruments now assist brain tumor surgery, including bipolar coagulating forceps, microscopes, microinstruments, ultrasonic aspirators, and lasers. These make removal easier and less hazardous. Tumors in some locations that previously could not be completely removed can now be treated more successfully, with higher success rates.
3. Divert CSF through a shunt or ventriculostomy when its pathways are obstructed and the causative tumor cannot be completely removed. This improves the patient’s condition by lowering intracranial pressure and is often combined with radiotherapy for radiosensitive tumors. Shunts are frequently used in children, whose tumors commonly occur in the posterior fossa or midline and obstruct CSF flow.
CSF drainage before tumor removal has several benefits. It lowers intracranial pressure, potentially saving the patient’s life and improving neurological function. It also provides time to correct malnutrition and electrolyte abnormalities before major surgery. With posterior fossa tumors, however, a shunt or ventriculostomy may cause upward cerebellar herniation. Conversely, posterior fossa craniectomy for tumor removal without first draining CSF by ventriculostomy may worsen downward herniation, with similarly harmful consequences.
4. Obtain tumor tissue for pathological examination to determine its type, helping to plan surgery and subsequent additional treatment. Biopsy is indicated: i) when the tumor is deep or in a critical location where complete removal might endanger the patient; and ii) for malignant tumors that may require radiation and chemotherapy, so that the tumor type should be established. Tissue may be obtained by three methods: i) craniotomy and open biopsy; ii) needle biopsy; and iii) stereotactic biopsy. Open biopsy allows the surgeon to see the tumor, identify and avoid major vessels, and obtain additional tissue for diagnosis. It also allows bleeding points to be seen and controlled. Needle biopsy often yields a small sample that may be insufficient for diagnosis or may come from nontumorous tissue. More importantly, it may cause internal hemorrhage that cannot be controlled.
5. For radiosensitive tumors, follow surgery with radiotherapy, possibly combined with chemotherapy, according to the individual case.
Original pages 518–519
Preoperative Preparation
Before surgery, the surgeon must perform a thorough general and neurological examination to identify abnormalities in the various body systems. Unless urgent surgery is necessary, medical illnesses should first be treated and stabilized. This helps ensure successful surgery without intraoperative or postoperative complications. Once examination and investigations establish a brain tumor diagnosis, the surgeon must weigh the expected outcome and risks, considering the tumor’s location and type and the degree of cerebral edema. A reasoned plan must be made before operating: the approach to the tumor, the extent of removal, and whether surgery should be replaced by another treatment because of pre-existing medical illness. It is essential always to consider what additional loss of brain or cranial nerve function removal might cause. For example, acoustic neuroma surgery may cause facial palsy, while tentorial meningioma surgery may cause third, fourth, or sixth nerve palsy.
Psychological preparation and the relationship between the doctor, patient, and family are also important. The surgeon should explain the disease, indications for surgery, operative method, benefits, disadvantages, risks, and possible complications so that the patient and family understand them. At the same time, encouragement and confidence should be fostered to obtain cooperation and prepare the patient to face surgical risks.
The following important factors relating to brain surgery should be assessed and corrected before the operation.
Original page 519
1. The Cardiovascular System
This is particularly important because the brain requires an adequate blood supply at all times, both during and after surgery. Surgery may cause blood loss and hypotension, and pre-existing cardiac disease increases the risk. A history of angina pectoris, chest pain, easy fatigue on exertion, myocardial infarction, or arrhythmia indicates risks during anesthesia. EKG and chest X-rays should therefore be obtained, particularly in patients over 40 years old, to detect abnormalities. A cardiologist should be consulted and treatment provided until surgery is considered safe.
In elderly patients, blood pressure should be measured both supine and sitting to assess whether brain surgery in the sitting position would compromise cardiac function. If cardiac function is inadequate, surgery should be performed in a recumbent position.
Original pages 519–520
2. The Respiratory System
This is another important system that ensures adequate O2 delivery to the brain. The preoperative history should cover chronic lung diseases such as asthma, emphysema, and bronchiectasis, chronic productive cough, noisy breathing, difficulty breathing, and tuberculosis. These conditions can cause CO2 retention and inadequate oxygenation. Excess CO2 causes cerebral vasodilatation, raising intracranial pressure and making surgery difficult and hazardous to the brain. Chest radiographs should be obtained to detect abnormalities. If pulmonary function is suspected to be inadequate, pulmonary function tests and blood gas analysis should be performed, and treatment continued until lung function improves satisfactorily before surgery.
In patients with markedly elevated intracranial pressure, positive-pressure breathing should not be used, because it raises venous pressure and consequently increases intracranial pressure further, creating a potential danger.
Original page 520
3. Blood Tests
Obtain a complete blood count, including hemoglobin, hematocrit, and platelet count. Anemia and a low platelet count should first be corrected by transfusion of blood and platelets. If a disorder causing a coagulation defect, such as liver disease, is suspected, measure the prothrombin time and partial thromboplastin time, and correct the abnormality with intravenous vitamin K1 (Mephyton) and fresh frozen plasma.(1)
Other hematological problems that must be sought in the preoperative history include ecchymoses, prolonged bleeding, petechial rashes, purpura, epistaxis, and current aspirin use. These abnormalities endanger the patient during and after surgery; their causes must be identified and corrected.
Original pages 520–521
4. Fluids and Electrolytes
Tumors in certain locations may cause fluid and electrolyte disturbances. For example, hypothalamic tumors may cause diabetes insipidus or impair the thirst mechanism. Children with posterior fossa tumors may vomit excessively and eat poorly. Administration of osmotic diuretic solutions and furosemide can also cause dehydration and hypovolemia. At induction of anesthesia, blood pressure may fall, reducing cerebral blood flow and causing cerebral ischemia. Furosemide causes greater losses of Na+ and K+ than mannitol.(2) These disturbances must be corrected before anesthesia.
Several brain diseases, including tumors, may cause the syndrome of inappropriate antidiuretic hormone secretion (SIADH). Excessive water retention results in hyponatremia and water intoxication,(3) which can cause cerebral edema and seizures, making surgery difficult and dangerous. Fluid restriction should therefore first restore Na+ to normal.
K+ abnormalities are also important in surgery. Patients receiving diuretics for hypertension may develop hypokalemia, which can cause cardiac arrhythmias during surgery. It must therefore be corrected before the operation.
Original page 521
5. The Endocrine System
Two important diseases affect surgery: diabetes insipidus and diabetes mellitus. Blood glucose must therefore be measured in every patient. If diabetes mellitus is found, it must be treated until blood glucose is within the normal range, because diabetes impairs wound healing and increases susceptibility to infection. Moreover, the stress of anesthesia and surgery, or steroids given before and after surgery, may greatly increase blood glucose and endanger the patient.
Corticosteroids must sometimes be given before surgery. In patients with a tumor and cerebral edema, they are used to reduce swelling:(4) dexamethasone 10 mg I.V., followed by 5 mg I.V. every 6 hours, beginning 1–2 days before surgery. Patients with pituitary gland or hypothalamic tumors often have hypopituitarism and require hydrocortisone 100–200 mg by intravenous drip before surgery to prevent an Addisonian crisis.
Original page 521
6. Anticonvulsants
Preoperative anticonvulsants remain controversial for patients with brain tumors who have never had seizures. Some neurosurgeons give agents such as Dilantin and phenobarbital before and after every supratentorial tumor operation, although seizures during or immediately after surgery are uncommon. The author considers routine preoperative anticonvulsants unnecessary for all supratentorial tumors and selects only patients undergoing surgery in areas readily provoking seizures, such as the motor area, and those with a history of seizures. Dilantin or phenobarbital must be given for several days before surgery to control seizures, and should be continued for a time afterward. If no seizures occur, medication is discontinued.
Original page 521
7. Antibiotics
The administration of antibiotics before and during surgery remains controversial. However, intraoperative antibiotics in clean cases have now been found effective in preventing postoperative neurosurgical infection.(5)
Original pages 521–522
8. Head Shaving and Hair Washing
Before the day of surgery, the hair should be washed thoroughly to reduce staphylococcal organisms. The head is then shaved on the day of surgery, cleaned with antiseptic, and covered with a clean cloth. The entire head should be shaved rather than only part, since partial shaving provides inadequate cleanliness and makes wound dressing difficult. After anesthesia and positioning, before surgery begins, the operative scalp area must be scrubbed twice with antiseptic soap for approximately 5–10 minutes, followed by sterile draping of the surrounding unclean areas.
Original page 522
9. Enemas
An enema should not be given to a patient with a large tumor and raised intracranial pressure. It may induce forceful straining at defecation, abruptly raising intracranial pressure enough to cause brain herniation. The patient may lose consciousness and deteriorate, requiring emergency surgery.
Original page 522
10. Urinary Catheterization
Brain tumor operations often take a long time, and some patients require diuretics to lower intracranial pressure. A Foley catheter should therefore be inserted in every patient with raised intracranial pressure who is expected to undergo a prolonged operation. Generally it is inserted after induction of anesthesia and removed postoperatively once the patient has recovered well and frequent timed measurements of urine output are no longer necessary.
Original pages 522–523
Anesthesia for Patients with Brain Tumors
Besides providing smooth anesthesia, the anesthesiologist must understand the various changes that may occur in the brain during anesthesia, particularly changes in intracranial pressure and cerebral circulation. These must be recognized immediately and corrected urgently during anesthesia; otherwise brain surgery cannot continue.
Before anesthesia, the anesthesiologist should assess the patient and consult the operating surgeon about the disease, operation, patient position, risks, and precautions, to prevent intraoperative complications and ensure a good result. The anesthesiologist must know the patient’s history regarding illness, level of consciousness, drug allergies, and seizures. The respiratory and circulatory systems must be examined for respiratory disease that could interfere with anesthesia or obstruct the airway. Cardiac and blood pressure abnormalities, such as myocardial infarction and hypertension, should be treated before anesthesia. Abnormalities in the laboratory and other investigations—CBC, electrolytes, blood glucose, blood gases, coagulation profile, urinalysis, EKG, and chest X-rays—must also be corrected to prevent complications.
Original pages 523–528
Considerations in Anesthesia for Patients with Brain Tumors
The surgeon and anesthesiologist must always take three interrelated factors into account: intracranial pressure, cerebral blood flow, and respiration. Changes must be recognized and corrected promptly. Raised intracranial pressure is a major obstacle to brain tumor surgery, making removal difficult and dangerous.
Changes in intracranial pressure depend on several factors that must be understood so that an increase during anesthesia can be prevented:
1. Premedication. This is important in patients whose tumor has already produced very high intracranial pressure, approaching decompensation (see Chapter 4). Drugs should not increase cerebral blood flow or intracranial pressure. Respiratory depressants should be avoided because they cause carbon dioxide retention and reduced oxygen; carbon dioxide dilates cerebral blood vessels and raises intracranial pressure. Narcotics, particularly morphine, should be avoided: they depress respiration, constrict the pupils, reduce consciousness, delay postoperative awakening, and interfere with assessment of consciousness. They may also cause vomiting, raising intracranial pressure to a dangerous level. The anesthesiologist may give atropine alone. Drowsy or unconscious patients do not require premedication.
2. Coughing and straining during induction. In patients with a large tumor or very high intracranial pressure, the surgeon must warn the anesthesiologist to avoid provoking coughing. Coughing and straining during intubation abruptly raise intracranial pressure and may cause uncal or tonsillar herniation, compressing the brainstem during anesthesia. Patients with raised intracranial pressure also tolerate poorly the hypoxia caused by coughing or prolonged intubation. Induction should therefore be smooth, with adequate oxygenation and rapid intubation without coughing.
3. Airway obstruction. This is the most important cause of an abrupt rise in intracranial pressure. Hypercapnia and hypoxemia cause cerebral vasodilatation and engorgement. Unless the airway is cleared promptly, diffuse cerebral edema may lead to brain herniation and brainstem compression, preventing recovery of consciousness. Brain cells cannot tolerate prolonged oxygen deprivation; obstruction must therefore be diagnosed promptly.
When the skull and dura have been opened, obstruction of the endotracheal tube by secretions or kinking causes the brain to bulge progressively beyond the craniotomy, without pulsation. Capillaries rupture, producing subarachnoid hemorrhage over the protruding brain. Surgery cannot continue. The airway must be cleared and the patient hyperventilated to correct hypercapnia; the brain then visibly subsides and begins to pulsate. Thus, when sudden intraoperative brain swelling occurs and hemorrhage into the tumor or brain and obstruction of the ventricles have been excluded, the airway should be checked first. Restoring its patency allows the brain to subside.
During tumor removal, intracranial pressure should be lowered by hyperventilation to a PCO2 of 25–30 mmHg. This provides the desired reduction in pressure without the cerebral ischemia caused by excessive vasoconstriction at a very low PCO2. Its advantages are: (1) cerebral vasoconstriction lowers intracranial pressure and relaxes the brain, facilitating tumor removal; (2) it counteracts the vasodilating effect of halothane; (3) it reduces the amount of anesthetic required; and (4) it permits control of PCO2. The disadvantage is that vasoconstriction at a PCO2 of 20 mmHg may cause cerebral hypoxia and infarction.
Spontaneous respiration during anesthesia is inappropriate in patients with a tumor and high intracranial pressure, since respiration is already depressed, especially with posterior fossa tumors near the respiratory center. Inadequate ventilation prevents brain relaxation and makes surgery difficult. Controlled respiration offers the following advantages: (1) adequate oxygen delivery and carbon dioxide elimination when the heart and lungs are normal; (2) less cerebral venous congestion and bleeding; (3) a smaller anesthetic requirement; (4) lighter anesthesia and more rapid awakening; (5) improved ventilation in the prone position; and (6) the use of muscle relaxants to prevent coughing and straining, which benefits the brain. Some surgeons prefer spontaneous respiration during posterior fossa surgery to monitor the respiratory center while manipulating the medulla. Even during controlled respiration, however, cardiac arrhythmias on the EKG can indicate disturbance of the medulla.(6)
A patent airway must be maintained at all times, including after surgery, when surgical edema and poor respiration may aggravate the problem. If the patient remains unconscious after the operation, the endotracheal tube should remain in place to prevent obstruction by the tongue and permit suction of secretions.
4. Anesthetic agents. Several injectable and inhaled anesthetics, including ketamine and halothane, dilate cerebral vessels, increasing cerebral blood flow and intracranial pressure.
KETAMINE is not favored in patients with tumors or other brain disorders associated with raised intracranial pressure, because it increases cerebral blood flow by more than 50%(7,8) and markedly increases intracranial pressure.
HALOTHANE is widely used in general surgery because it provides smooth anesthesia and allows rapid awakening.(9,10) It is nonexplosive and can be used with electrocautery. However, it dilates cerebral vessels and increases cerebral blood flow and intracranial pressure. It should therefore be used at a concentration below 0.75%, together with hyperventilation.(11)
5. Patient position. Position affects intracranial pressure, particularly the prone position and the supine position with excessive head rotation. Breathing is more difficult prone than supine; increased intrathoracic pressure raises cerebral venous pressure and intracranial pressure. Compression of the abdomen and thorax should be avoided, and the head should be slightly above the heart to improve venous drainage and prevent a rise in pressure. In the supine position, excessive head rotation may obstruct the neck veins. A pillow should elevate the shoulder on the operative side above the other shoulder, reducing the amount of head rotation and preventing venous obstruction. If intracranial pressure is already very high and cerebral perfusion is maintained only by elevated blood pressure, venous obstruction may raise intracranial pressure to a life-threatening level.
6. Blood pressure. Marked hypertension should be avoided after the dura has been opened. It is dangerous because blood pressure is no longer opposed by intracranial pressure; cerebral blood flow increases, and the brain swells to fill the craniotomy opening. Touching or retracting it causes extravasation of blood and fluid, increasing the swelling.(12) Conversely, lowering blood pressure relaxes the brain.
Hypertension. The main cause is painful stimulation during excessively light anesthesia, particularly during dissection around the trigeminal nerve.(13) Interference with vessels of the brainstem, such as the anterior inferior cerebellar artery, or basal branches of the anterior cerebral artery supplying the anterior hypothalamus,(13) may also raise blood pressure. At the start of surgery, injection of local anesthetic containing adrenaline to reduce bleeding may cause hypertension. Hypertension before craniotomy or after completion of the operation should suggest raised intracranial pressure.
Hypotension. Initially, thiopentone, muscle relaxants, and controlled ventilation may cause a temporary fall in blood pressure, followed by recovery. During posterior fossa surgery, such as removal of an acoustic neuroma, traction on the adjacent vagus nerve or traction on a medullary tumor may produce hypotension with a slow, irregular pulse. Stopping the stimulus restores normal values. The sitting position for posterior fossa surgery lowers blood pressure and intracranial pressure. Air embolism causes an abrupt fall in blood pressure and is a life-threatening complication, discussed in detail in the section on surgery.
The cerebral circulation has already been discussed in the chapter on intracranial pressure.
Original page 528
Postoperative Care
If the patient was alert before surgery, the operation was smooth without injury to important areas of the brain, and consciousness returns well, postoperative care resembles that following other operations. With smooth care and no complications, recovery proceeds normally. Nevertheless, many technically successful operations are followed by complications caused by errors in postoperative care. Close and correct care must continue until the patient is safe. Postoperative hematoma and cerebral edema can be fatal and require prompt diagnosis and treatment.
Important aspects of postoperative care for patients with brain tumors are as follows:
Original pages 528–529
1. Immediate Postoperative Care
Emergence from anesthesia is a critical period. Before removing the endotracheal tube, adequate respiration, blood pressure, and consciousness must be assured. Premature extubation may cause carbon dioxide retention and hypoxemia, resulting in cerebral edema, raised intracranial pressure, and poor recovery of consciousness. If awakening or respiration remains poor, ventilation should be continued with frequent reassessment. If the condition does not improve, its cause must be investigated. The tube can be removed later, when the patient is alert and breathing normally.
After anesthesia has been discontinued, the endotracheal tube may provoke coughing, causing hypertension, intracranial bleeding, and raised intracranial pressure. Once the patient is adequately awake, extubation should be smooth, preventing or minimizing coughing.
An intensive care unit is essential after brain surgery, providing close care by doctors and nurses trained in neurological observation. They must recognize changes in consciousness, vital signs, weakness, and pupils. The earlier a complication is diagnosed, the better. Nurses are especially important because they remain continuously with the patient, and require extensive training to provide effective care. Untrained nurses may be unable to interpret changes and may miss the opportunity for prompt treatment.
Original pages 529–535
2. Four Standard Observations
Immediately on arrival in the intensive care unit, four important observations must be made to establish the baseline for monitoring changes. Everyone must use the same criteria so that subsequent observations can be compared:
Vital signs: pulse, blood pressure, and respiration
Consciousness
Limb movement
Pupil size and reactions
These four observations reveal intracranial complications, namely postoperative hemorrhage (postoperative clot) and cerebral edema. Both raise intracranial pressure and require urgent treatment.
Vital signs should be checked frequently, every 15–30 minutes during the first 1–2 hours. If the condition is then stable, observations should continue hourly for another 2–3 days.
Blood pressure and pulse. When a cause of raised intracranial pressure develops, the pulse progressively slows while blood pressure progressively rises: Cushing’s reflex. An accompanying deterioration in consciousness, with increasing drowsiness, further supports the diagnosis. The author consistently follows this principle in practice.
Generally, after brain tumor surgery without major blood loss, or with major blood loss adequately replaced by transfusion, hypotension does not occur even if intracerebral hemorrhage develops. The amount of postoperative intracranial bleeding is insufficient to lower blood pressure, although it can impair consciousness. If postoperative hypotension occurs, extracranial causes should therefore be considered, such as cardiac disease, diabetes insipidus with excessive urine output causing hypovolemia, and hypopituitarism. These require appropriate treatment. In some patients, inadequate hemostasis during closure of the skull and scalp results in 400–500 cc of blood collecting in the suction bottle within 10–15 minutes, potentially causing hypotension. The patient must be returned urgently to the operating room for hemostasis.
Respiration. This is extremely important in caring for patients after brain surgery. The airway must remain patent at all times to provide adequate O2. Patients who are fully conscious after surgery have no respiratory difficulty, but this may change if postoperative hemorrhage or cerebral edema raises intracranial pressure. A posterior fossa hematoma produces conspicuous respiratory changes: breathing becomes progressively slower and shallower, followed shortly by respiratory arrest. This is an important sign requiring diagnosis and intervention before respiration ceases. After supratentorial tumor surgery, respiratory changes may be less obvious. Breathing may slow somewhat, and some patients develop Cheyne–Stokes respiration. These are important signs requiring investigation of the cause.
To determine whether respiration is adequate, assess the breathing pattern, cough, and blood gases. Shallow, slow breathing or dyspnea indicates abnormal ventilation. A patient able to cough strongly has sufficient vital capacity to maintain normal oxygenation. Blood gases provide a good indication of pulmonary function. Since inspired air contains no CO2, an increased blood PaCO2 indicates hypoventilation and the need for mechanical ventilation. Normally, while breathing room air, PaCO2 is 35–45 torr and PaO2 80–100 torr. This PaCO2 range maintains blood pH within the normal range of 7.35–7.45. A reduced PaCO2 indicates hyperventilation. Generally, if the brain is not compressed after surgery, patients mildly hyperventilate. This is beneficial, avoiding CO2 retention and providing adequate O2, and does not require correction.
Maintaining a patent airway. In patients who remain drowsy or poorly conscious after brain tumor surgery, whatever the cause, the first concern and intervention must be to maintain a patent airway. This permits good lung expansion without hypoxia or hypercarbia, saves life, and prevents intracranial complications.
Methods of maintaining a patent airway are as follows:
i) Position the patient with the head extended. This draws the relaxed jaw forward and lifts the tongue that has fallen back to obstruct the pharynx, opening the airway. Preferably, the patient should lie on either side with the head extended, allowing sputum, saliva, and vomitus to drain out.
ii) Insert an oropharyngeal or nasopharyngeal airway, placing its inner end between the posterior pharynx and the base of the tongue. The oropharyngeal airway is inserted through the mouth; the nasopharyngeal tube through one nostril. Besides opening the airway, both allow suction of sputum and saliva. An oropharyngeal tube also prevents an unconscious patient from biting the endotracheal tube. Conscious patients, however, usually tolerate it poorly because it provokes vomiting and laryngospasm. A nasopharyngeal tube is well tolerated by both conscious and unconscious patients. Neither type prevents aspiration into the trachea, which may cause pneumonia, so caution is required. In a drowsy patient who vomits, an endotracheal tube is preferable because it provides good protection against aspiration.
The airway must be appropriately sized for the patient. If too long, it may push the epiglottis over the airway; if too short, it may push the tongue backward and worsen obstruction.
iii) Insert an endotracheal tube. For poorly conscious or unconscious patients, this is the best way to maintain a patent airway. It can be passed through the nose (nasoendotracheal tube) or mouth (oroendotracheal tube). These tubes have cuffs to prevent aspiration and can be connected to a ventilator. Adequate training is necessary for smooth insertion without complications. In a patient with raised intracranial pressure, an inexperienced operator may provoke struggling and resistance, raising pressure dangerously. If possible, a muscle relaxant and Pentothal facilitate insertion without resistance, but a ventilator must be immediately available for safety.
After intubation, always check that air enters both lungs equally. Insertion into one bronchus ventilates only one lung, with serious effects on the brain: hypercarbia, cerebral vasodilatation, and raised intracranial pressure. Leaving an excessively long external portion of the tube can also cause problems. The author has often encountered a tube displaced inward into one bronchus while its outer end still appeared long, obscuring recognition of the displacement. The patient breathes with only one lung and becomes breathless. Withdrawing the tube to the correct position restores normal breathing. The author therefore makes it a rule to take the following steps after intubation:
i) Auscultate both sides; air entry must always be equal in both lungs.
ii) Once the tube’s correct position has been verified, mark it at the nostril or lip and secure it so that it remains in position.
iii) Cut the tube so that approximately 2 inches remain outside. If less than this protrudes later, inward displacement will be apparent.
iv) Tracheostomy is performed when unconsciousness persists for a long time after brain tumor surgery. An endotracheal tube should not remain in place for more than 10 days because nasal necrosis may develop, or dried secretions may narrow its lumen and cause inadequate ventilation. For an unconscious patient, a tracheostomy tube with a low-pressure cuff and an inner tube should be used. The cuff can be inflated to fill the trachea, preventing aspiration and allowing connection to a ventilator without leakage. The inner tube can also be removed and inspected for obstruction. A metal tube is unsuitable for an unconscious patient because it does not prevent aspiration and cannot be connected to a ventilator. It should be used when consciousness has recovered and removal of the tracheostomy tube is planned. A metal tube must not be too long, because it may injure a major blood vessel, causing fatal hemorrhage as blood obstructs the trachea and bronchi.
Tracheostomy must be performed by an experienced operator; otherwise complications may occur, sometimes rapidly fatal. The author has encountered tension pneumothorax in a child after injury to the pleural dome, which lies close to the trachea; the patient subsequently died.
Consciousness. This is the most important observation in postoperative care because it indicates changes in the brain. Immediately after recovery from anesthesia, assess consciousness by asking questions and giving commands, then record what the patient can actually do—for example, correctly stating the day, month, year, and location, and recounting the history of illness. Terms such as conscious, drowsy, stupor, semicoma, and coma may be interpreted differently by the next person taking over care. This can lead to misinterpretation of changes: consciousness may be judged unchanged when it has in fact deteriorated. Treatment is then delayed, and the patient may eventually become unconscious.
In some cases, postoperative hemorrhage develops early. A patient approaching full recovery from anesthesia deteriorates again and must be returned to the operating room for reopening of the skull and evacuation of the blood. In others, consciousness begins to deteriorate around the third or fourth day, possibly because of cerebral edema, a slowly developing hematoma, or hyponatremia. Imaging investigations are required to identify the cause, followed by urgent treatment.
Limb movement. This is another sign requiring repeated assessment after surgery. As soon as the patient awakens from anesthesia, record any weakness and which limbs are affected. In principle, monoparesis or hemiparesis already present on leaving the operating room suggests injury to some part of the corticospinal tract during surgery. If there is no weakness on awakening, but hemiparesis develops later, consider a postoperative complication: hemorrhage, cerebral edema, or infarction. If this is the cause, changes in consciousness and signs of raised intracranial pressure will also be present. The cause must be investigated and treated immediately.
If weakness was present before surgery and persists afterward, subsequent progressive worsening should likewise suggest a postoperative complication.
After posterior fossa tumor surgery, complications may produce increasing incoordination and relatively rapid deterioration of consciousness, together with progressively slower respiration.
Pupil size and reactions. Pupillary changes occur with brain herniation, as discussed in detail under raised intracranial pressure. It is wrong to wait until one pupil has dilated (anisocoria), because treatment is then delayed and recovery is less satisfactory than when treatment precedes herniation. As already mentioned, actual pupillary dilatation is often preceded by constriction, due to stimulation of the parasympathetic constrictor fibers on the surface of the oculomotor nerve or interference with the hypothalamus. Such changes, together with deteriorating consciousness, require urgent investigation so that the cause can be corrected early. After posterior fossa surgery, anisocoria does not occur as it does after supratentorial surgery; both pupils remain equal and continue to react to light.
Original pages 535–536
3. Patient Position
Generally, the patient is positioned with the head elevated approximately 30° to improve cerebral venous return and prevent cerebral edema and raised intracranial pressure. The disadvantage is possible aspiration of vomitus, making this position less suitable for patients who remain unconscious after surgery. If an endotracheal tube is present, however, it is safe. Lying flat with the head low provides poorer venous drainage than head elevation, promoting cerebral edema and raised intracranial pressure, which may facilitate bleeding at the operative site. Its advantage is a lower likelihood of aspiration.
Removal of a large tumor on one side leaves a large cavity. Placing the operative side downward may shift the brain toward this space, tearing cortical bridging veins and causing an acute postoperative subdural hematoma. The patient should therefore lie on the side with the operative hemisphere uppermost for several hours, allowing the brain in the operative area to swell and narrow the cavity, while CSF also accumulates to support the brain. Turning to other positions then becomes less dangerous. Similarly, turning a patient after removal of a large posterior fossa tumor may cause complications; the author has encountered respiratory arrest and hypotension.
Elderly and unconscious patients must be turned every 2 hours to prevent pneumonia.
Original pages 536–538
4. Fluids and Electrolytes
The brain is very sensitive to water retention and edema. In the early period after brain tumor surgery, cerebral edema remains a concern and excessive fluid should be avoided. Generally, during the first 3–4 days, mild dehydration should be maintained by giving approximately two-thirds of the daily requirement, about 1500 cc per day for an adult. Fluid is given as 5% dextrose in half-normal saline (0.5 NSS), with K+ added as required. It is generally accepted that 5% dextrose in water should not be given when postoperative cerebral edema is anticipated, because it may worsen swelling. If the patient is fully conscious after surgery, does not vomit, and does not aspirate because of ninth- or tenth-cranial-nerve dysfunction, oral feeding can begin on the second postoperative day. Intravenous fluids are unnecessary if intravenous medication is not needed. Patients who are not fully conscious should not yet be fed orally, because vomiting and aspiration may occur. Intravenous fluids should continue as required, and tube feeding should begin once vomiting has ceased.
During the first 1–2 postoperative days, urine output may be reduced as a normal response to surgery. Increasing fluid intake to restore urine output to normal is unnecessary and may aggravate cerebral edema.
Hyponatremia. A low blood Na+ concentration may result from excessive water retention due to the syndrome of inappropriate ADH secretion (SIADH). This is frequently encountered after brain surgery or with brain disease, particularly tumors near the third ventricle and hypothalamus. The syndrome may also occur after traumatic intracranial hemorrhage, with oat cell carcinoma of the lung, or with pulmonary tuberculosis. Diagnosis rests on the history and blood Na+ measurement. Its features are: (i) weight gain; (ii) progressive drowsiness around the end of the first postoperative week, after intracranial hematoma has been excluded; (iii) possible seizures; (iv) low serum Na+; (v) low serum osmolarity; (vi) increased urinary Na+; (vii) increased urine osmolarity; and (viii) absence of renal or adrenal disease. The principal treatment is restriction of fluid intake to no more than 500–1000 cc daily. In mild cases, Na+ returns to normal within 1–2 days, with restoration of consciousness. In severe cases, with Na+ below 120 mEq/L, hypertonic saline, such as 3% or 5% solution, 200–300 cc daily, may be required in addition to fluid restriction. The author has found that this improves consciousness and raises Na+ more rapidly than fluid restriction alone. Nevertheless, hyponatremia may recur intermittently after correction. The patient must therefore be monitored and blood Na+ measured periodically until normality is maintained.
Diabetes insipidus (DI). This occurs after surgery for tumors in the pituitary and hypothalamic regions. Most postoperative cases last approximately 2–3 weeks before gradually improving. Characteristic diagnostic features are polyuria, polydipsia (excessive thirst and drinking), very low urine specific gravity, and signs of dehydration.
Treatment depends on severity. With mild polyuria and polydipsia, the patient may drink enough water to replace losses as required, and the condition usually improves. If urine output is excessive and the patient becomes markedly dehydrated, drowsy, and unable to retain water, intravenous replacement and Pitressin injections are required. There are two preparations. Aqueous Pitressin is given intramuscularly at 0.1 unit/kg, or approximately 5 units for an adult. Its action lasts approximately 4–6 hours, so it may need repeating every 4–6 hours to keep urine output below 200 cc per hour. The other preparation, Pitressin tannate in oil, is given to adults as 5 units intramuscularly and acts for 16–24 hours. One daily injection can therefore reduce urine output as required. Preparation before injection is extremely important because the drug settles as particles at the bottom of the ampoule. The ampoule must be warmed for approximately 10 minutes and then shaken vigorously for another 10–15 minutes before the contents are drawn into a syringe and immediately injected intramuscularly. This ensures delivery of the intended dose. Otherwise only oil may be drawn up and injected, providing inadequate Pitressin. A Foley catheter must be inserted, and fluid intake and output carefully measured and recorded to prevent dehydration. Electrolytes must also be checked regularly and abnormalities corrected.
If diabetes insipidus persists, intranasal treatment is more convenient: DDAVP (1-desamino-9-D-arginine vasopressin [chemical name as printed in the original]), 0.05 cc intranasally once or twice daily as required.(14)
Original pages 538–540
5. Fever
Elevated body temperature harms the brain by increasing metabolism and the cerebral blood flow needed to supply sufficient O2, thereby raising intracranial pressure. Postoperative care must therefore maintain temperature within the normal range at all times, using antipyretics, cold-water sponging, or a hypothermia blanket.
Fever usually occurs on the first postoperative day and lasts approximately one day as a bodily response to surgical injury. It resolves spontaneously without medication. If high fever recurs on subsequent days, consider postoperative hematoma and infection. A postoperative hematoma always causes accompanying signs of raised intracranial pressure. Investigate with CT, MRI, or angiography; if a hematoma is found, evacuate it surgically, after which the fever subsides. Infection generally causes fever around postoperative days 4–5. Uncovering the wound reveals inflammation, swelling, and redness, with an increased white blood cell count and polymorphonuclear cells.
Blood in the CSF may also cause fever, particularly after posterior fossa tumor surgery. Fever may persist for several days, sometimes accompanied by meningism and Kernig’s sign. Meningism can be difficult to identify because neck stiffness may also result from the operative wound. In such cases, lumbar puncture may be necessary in addition to antipyretics. If the CSF is heavily bloodstained, approximately 20–30 cc or more should be removed. Repeated punctures over several days help clear the blood from the CSF and reduce the raised intracranial pressure caused by hydrocephalus resulting from blood in the CSF.
Another important cause of high fever is surgery near the third ventricle and hypothalamus, disrupting the temperature-regulating mechanism. Characteristically, the temperature rises abruptly and remains high without returning to normal, sometimes reaching 40°C. Treatment is often ineffective even when several measures are combined: oral and rectal antipyretics, a hypothermia blanket, and sponging with ice water or alcohol. Temperature may remain uncontrollably high and the patient may die.
Original pages 540–541
6. Steroids
Postoperative steroids serve two purposes: (i) hormone replacement in patients with tumors of the pituitary and hypothalamic regions; and (ii) reduction of edema in the operated portion of the brain.
Patients undergoing tumor surgery in the pituitary and hypothalamic regions must always receive adequate steroid replacement before and after surgery. They frequently lack ACTH and cannot tolerate the operation and postoperative stress. Steroid deficiency causes a shock-like state and deterioration of consciousness.(15) Patients develop hypotension, tachycardia, fever, abdominal pain, nausea, vomiting, and oliguria. Blood tests show low or absent plasma cortisol, as well as hyponatremia and hypoglycemia—important laboratory findings.(15)
Steroids should begin one day before surgery for sellar and parasellar tumors. Options are dexamethasone 5 mg I.V. every 6 hours, hydrocortisone 100–200 mg by intravenous drip over 24 hours, or cortisone acetate 100 mg I.M. daily.(16)
Treatment must continue postoperatively, with gradual reduction of the dose. If there was no preoperative hormone deficiency and surgery did not damage the pituitary or hypothalamus, tapering may be rapid, with discontinuation within 3–4 days. If hormone deficiency existed preoperatively, the initial postoperative dose should gradually be reduced to an adequate maintenance dose within 7 days. Once the patient can eat, oral prednisolone or dexamethasone may be given according to the patient’s requirements.
The edema-reducing benefit of steroids is particularly apparent in metastatic brain tumors or malignant gliomas with marked vasogenic edema. Steroids reduce swelling and improve the patient’s condition. Dexamethasone 5 mg I.V. every 6 hours is generally given before surgery for these tumors and continued afterward. If the tumor has been satisfactorily removed, postoperative dexamethasone should continue for 5 days, followed by tapering and discontinuation over 2–3 days. Prolonged dexamethasone treatment causes complications such as gastric bleeding, hyperglycemia, and hypertension.
Original pages 541–542
7. Anticonvulsants
Patients with brain tumors who have previously had seizures, or whose tumors occupy seizure-prone areas such as the motor area, require anticonvulsants before and after surgery. Each seizure increases cerebral metabolism, oxygen requirements, cerebral blood flow, and venous engorgement, raising intracranial pressure. For this reason some neurosurgeons give anticonvulsants to every patient undergoing supratentorial tumor surgery. The author, however, selects only patients with previous seizures or tumors in seizure-prone regions such as the motor area, because postoperative seizures have been very uncommon in the author’s patients without a previous history.
Postoperative seizures require urgent and effective control. Diazepam 10 mg in adults, given slowly intravenously over 1 minute, can stop a seizure immediately. Intravenous diazepam may impair respiration; a ventilator should always be ready. Inadequate respiration is particularly important after tumor removal because it can raise intracranial pressure and cause hemorrhage. Once diazepam has stopped the seizure, longer-acting anticonvulsants—Dilantin and phenobarbital—must follow. Dilantin may be started with 400 mg, or 5–7 mg/kg, intravenously at a very slow rate, no more than 50 mg per minute; thus 400 mg should take 8–10 minutes. Cardiac activity must be monitored because arrhythmias may occur. Thereafter, Dilantin 100 mg and phenobarbital 30 mg are given orally or through a nasogastric tube three or four times daily.
Whenever seizures occur, remember that the operative site may have developed a complication, such as postoperative hemorrhage, cerebral edema, or infarction; metabolic disorders are another possible cause. These require investigation with CT and treatment directed at the cause.
Original page 542
8. Headache
Headache after brain tumor surgery has two possible causes: (i) pain from the operative wound, and (ii) a change in intracranial pressure. Wound pain is localized to the incision and responds to analgesics such as paracetamol or aspirin. Headache from raised intracranial pressure—for example, due to hemorrhage, cerebral edema, or hydrocephalus—is generalized and does not respond to analgesics alone. Its cause must be removed or intracranial pressure restored to normal before the headache resolves. A hematoma requires evacuation, for example, while elevated CSF pressure requires drainage of CSF from the brain.
Morphine and other analgesics with narcotic or sedative effects should not be used because they cause drowsiness and mask deterioration due to raised intracranial pressure. Morphine also depresses the respiratory center and should not be used when intracranial pressure is already elevated.
Original pages 542–543
9. Urinary and Bowel Care
Brain tumor operations generally take a long time, and some patients need diuretics to lower intracranial pressure. A Foley catheter must therefore be inserted before surgery and left in place during the postoperative period. If consciousness is normal, remove it as soon as possible and allow spontaneous urination, reducing bladder infection. If recovery is poor, or surgery involved the pituitary region where diabetes insipidus often develops, retain the catheter to measure hourly urine output. After removal of a frontal lobe tumor, patients may have poor urinary control despite being conscious, wetting the bed without awareness. Their voiding mechanism remains normal. A condom catheter connected to a collecting bottle prevents bedwetting and can be removed once frontal lobe function improves.
Bowel care is not difficult, but is often overlooked. Patients may go 4–5 days without defecating, particularly those who are poorly conscious after surgery, and may strain or develop hypertension. A laxative or enema should therefore be given within the first 2 postoperative days and repeated as appropriate. If hard impacted stool is found and cannot be expelled with an enema, manual evacuation is required. The author has seen fecal impaction cause multiple rectal ulcers, bleeding, rectal perforation, generalized peritonitis, and death. The attending physician must give this matter attention.
Original pages 543–544
10. Eye Protection
Eyelid swelling may follow frontal lobe surgery. The lids often swell shut, usually more severely on the operative side. A bifrontal bone flap may cause bilateral swelling, sometimes preventing inspection of the pupils. Swelling begins on the second postoperative day, lasts approximately 4–5 days, and gradually subsides. The physician should explain to the patient and family that this is usual after surgery in this region. Head elevation accelerates its resolution.
Corneal drying and abrasion are important problems in unconscious patients. If both eyes remain open, the corneas dry and become abraded; the patient may be unable to see after otherwise recovering from brain tumor surgery. The physician must attend to this, using narrow strips of adhesive tape at the lateral and medial portions of the upper lid and drawing the lid downward to close the eye. Ensure that the tape does not touch the cornea, and inspect regularly. Apply ophthalmic ointment three times daily to coat the cornea. A fan should not blow directly into the eyes because it introduces dust and accelerates drying. Most importantly, do not use an eye pad: its underside may directly contact the cornea and cause an ulcer.
Keratitis may follow acoustic neuroma surgery when loss of the corneal reflex and facial nerve palsy leave the cornea insensitive and the eye widely open. Keratitis and corneal ulceration develop readily. Initially the eye becomes red, followed by a whitish opacity at the ulcer, and eventually loss of vision. Prevention must therefore begin immediately after surgery. An effective measure is temporary tarsorrhaphy, suturing together the lateral third of the upper and lower eyelids. If corneal sensation remains and facial nerve function is expected to recover soon, an eye shield to exclude wind and dust may suffice, with artificial tears every 2–3 hours.
Original pages 544–545
11. Operative Wound Care
Brain tumor surgery produces a clean wound after proper preoperative skin preparation. Nevertheless, infection may occur in 1%(17,18) despite prophylactic antibiotics. Contributing factors include an operation lasting more than 3 hours, entry into a paranasal sinus or mastoid air cells, diabetes, anemia, wasting or malnutrition from vomiting, CSF leakage, and a drain left in place too long. A blood-soaked dressing must be replaced promptly because blood supports bacterial growth.
At present, a vacuum drain is routinely used after craniotomy. It must be removed after 24–48 hours; leaving it longer increases infection risk. The author usually inspects the wound when removing the drain. After removal, compress the scalp opening until it closes completely. If it remains open, suture it to prevent bacterial entry. If the sutured edge is dusky, remove the offending stitch to improve circulation and healing. Redress the wound properly. Sutures are removed on days 6–7, although an inflamed stitch should be removed earlier and antibiotics given.
Sutures in posterior fossa wounds must be removed later than those in supratentorial wounds, around postoperative days 8–9, because this region moves. If the dura was left open for decompression, or was not closed watertight, CSF may leak through the wound. This must be corrected urgently by lumbar puncture or another method of CSF drainage to lower CSF pressure, stop leakage, and permit sound wound healing.
Original page 545
12. Skin Care
In patients who remain unconscious after surgery, caregivers must prevent pressure sores caused by prolonged immobility in one position. These usually develop over bony prominences such as the femoral greater trochanter, shoulders, heels, and head. Turn the patient every 2 hours and support these areas with soft, jelly-like pads to reduce pressure. If the patient is soiled with stool or urine, clean and dry the skin promptly to reduce rashes.
Original pages 545–546
Complications of Brain Tumor Surgery
Complications are a major reason why surgery and its outcome may fall short of expectations, and may be severe enough to cause death. Surgeons must understand them thoroughly in order to plan prevention, diagnose them rapidly, and correct them appropriately. They arise from two sources. The first is the disease itself—for example, intratumoral hemorrhage, cerebral edema, or obstruction of CSF pathways. The second is the physician’s actions, of which several examples follow. These complications are less frequent in experienced hands. Nevertheless, they still occur despite newer and more effective equipment, including the microscope, microinstruments, laser, ultrasonic aspirator, and bipolar coagulator.
Complications may occur during two periods:
The intraoperative period
The postoperative period
Original page 546
Intraoperative Complications
These are extremely important. Complications such as brain swelling or air embolism may prevent any further surgery and force abandonment of the operation if they cannot be corrected in time.
Possible intraoperative complications are as follows:
Original page 546
1. A Craniotomy That Does Not Correspond to the Tumor’s Position
This makes access difficult and requires greater brain retraction, potentially tearing brain tissue and vessels. Before making the incision, the surgeon should carefully study the tumor’s location on imaging and correlate it as accurately as possible with the surface anatomy of the patient’s head. Before CT and MRI, correct placement based on angiography, brain scanning, or ventriculography was sometimes difficult, particularly for tumors in the posterior cerebral hemisphere. CT now accurately shows tumor location and size, permitting more precise placement of the craniotomy and sometimes a smaller opening, with fewer complications. Nevertheless, errors remain possible if variations in the angle of the orbitomeatal line used for CT slices are overlooked; this angle may differ between patients.
Original pages 546–547
2. Complications of the Incision
When making the scalp incision, the following must be considered:
i) The blood supply to the scalp flap.
ii) The nerves supplying the muscles and skin.
iii) Cosmetic appearance.
The surgeon must therefore know the vascular and neural anatomy of the scalp; otherwise the following complications may occur.
Original page 547
2.1 Scalp Ischemia
This is an important cause of poor wound healing and dehiscence. The scalp may become dusky or gangrenous. Causes include: (i) a scalp flap with an excessively narrow base or pedicle; (ii) an incision across a major scalp artery; (iii) spring scalp clips applied to the wound edges for hemostasis, particularly when the scalp is thin or already poorly supplied; and (iv) prolonged sharp folding of the reflected flap, impairing flow through its base. A rolled cloth should therefore be placed beneath the flap’s base before reflection to prevent kinking and maintain its blood supply.
Original page 547
2.2 Frontalis Muscle Paralysis
In a frontotemporal craniotomy, a temporal incision extending down to the zygomatic margin and more than 2 cm anterior to the tragus often divides the frontal branch of the facial nerve.(19) The ipsilateral frontalis muscle then loses function, preventing eyebrow elevation. This may cause psychological distress, especially in women.
Original page 547
3. Hemorrhage
Hemorrhage may occur at any stage, from opening the skull to dissecting out the tumor.
Original pages 547–548
3.1 Hemorrhage from the Middle Meningeal Artery
With a meningioma on the cerebral convexity, especially in the frontotemporal or parasagittal region, bleeding during opening of the skull may be profuse. In some patients, this alone causes enough blood loss to produce hypotension. The tumor is supplied by a markedly enlarged middle meningeal artery. This vessel should therefore always be ligated with a suture before opening the skull to reduce blood loss.
Original page 548
3.2 Hemorrhage from the Superior Sagittal Sinus and Arachnoid Granulations
For a parasagittal tumor, the craniotomy must approach the midline, where the superior sagittal sinus lies, and may extend across it. Profuse bleeding may arise from the sinus and arachnoid granulations. Although venous, it can be difficult to control without familiarity with hemostatic techniques in this region and may cause hypotension. Preventing sinus tears is therefore important. Place burr holes a little away from the superior sagittal sinus; never drill directly over it. If a tear occurs, cover it with muscle or Gelfoam, suture the dura across the muscle patch, and apply pressure briefly to stop bleeding. Bleeding from an arachnoid granulation can be controlled by covering it with Gelfoam and pressing with cotton briefly.
Original pages 548–549
3.3 Bleeding from the Tumor
Dissection of highly vascular tumors, such as angioblastic meningioma, glioblastoma multiforme, metastatic tumors, and hemangioblastoma, may cause blood loss severe enough to produce shock and require massive transfusion, with its harmful consequences. The author has encountered this several times. In one patient, a temporal lobe meningioma the size of a small orange received a substantial supply from the middle meningeal and internal carotid arteries. Attempted removal required 15 bottles of blood. After approximately 10 bottles, clotting became delayed, and the blood subsequently appeared very dilute. Hemostasis was unsuccessful because massive transfusion caused dilutional coagulopathy, thrombocytopenia, and hypocalcemia.(20) Bleeding stopped only after the decision to clip the internal carotid artery. The patient survived without hemiplegia.
Large glioblastomas and metastatic brain tumors similarly present difficult hemostasis because their numerous abnormal, fragile vessels often bleed profusely.
In brain tumor surgery, complete hemostasis is achieved only after the entire tumor has been removed. Residual tumor may bleed again at any time. The physician must remain alert for a postoperative hematoma causing deterioration.
Original page 549
4. Acute Brain Swelling
During an otherwise smooth operation, the brain may suddenly bulge beyond the craniotomy margin, with patches of subarachnoid hemorrhage on its exposed surface. The brain may even split. The abrupt rise in intracranial pressure prevents access to the tumor and makes further surgery impossible. Its cause must be removed promptly; otherwise brainstem dysfunction and death follow. Causes of acute intraoperative brain swelling include:
Original page 549
4.1 Airway Obstruction
Secretions may obstruct the endotracheal tube, the tube may kink, or a connector may become detached. Oxygen deprivation and carbon dioxide retention cause cerebral vasodilatation and venous engorgement, abruptly raising intracranial pressure. If the anesthesiologist corrects the problem promptly and hyperventilates briefly, the brain subsides well. This is the most frequent complication and is usually easy to correct.
Original pages 549–552
4.2 Intracranial Hemorrhage
4.2.1 Intraventricular and subarachnoid hemorrhage. During dissection of a tumor near or within a ventricle, blood may enter the ventricular system and obstruct CSF pathways, causing the brain to bulge. Prevent this by securely covering any opening in the ventricular wall with cotton so that blood cannot enter. Blood may also spread through the subarachnoid space, another cause of CSF obstruction.
4.2.2 Intracerebral hematoma. When dissection moves from one part of the tumor to another, bleeding may develop in adjacent brain at a previously dissected site because initial hemostasis was incomplete. The resulting hematoma pushes the brain outward. Excessive retraction can also cause intracerebral bleeding.
4.2.3 Subdural hematoma. This important complication may occur when a tumor causes hydrocephalus with enlarged lateral ventricles, as with posterior fossa or supratentorial intraventricular tumors. Before tumor removal, ventriculostomy is needed to drain CSF and lower intracranial pressure, facilitating dural opening and access. Ventricular collapse after drainage may tear cortical bridging veins, producing a unilateral or bilateral acute subdural hematoma. This is common in children, whose tumors often arise in the posterior fossa and enlarge the head, further predisposing bridging veins to tearing. The sitting position aggravates the risk because the brain sags downward, as illustrated by the following cases.
First case. A 5-year-old child had a medulloblastoma obstructing the fourth ventricle, markedly enlarged third and lateral ventricles, and an enlarged head. Surgery was performed sitting. A ventriculostomy was placed before opening the posterior fossa, ready for CSF drainage. When the dura was exposed, it was tense and bulging. The ventriculostomy was opened to drain CSF into a bottle until the tension subsided, then the dura was opened and tumor dissection begun. The cerebellum bulged during dissection, but inspection found no posterior fossa hemorrhage, and the CSF in the ventriculostomy tube was not bloodstained. The pulse accelerated and blood pressure fell. The wound was rapidly closed and the patient laid down. Pallor suggested an acute subdural hematoma. An exploratory burr hole disclosed one on the right; craniotomy revealed a very large clot. In such a young child, this amount of bleeding can cause pallor and hypotension. The hematoma could become so large because the lateral ventricle and cortex collapsed markedly. The patient recovered well after surgery.
Second case. A 7-year-old child had a fourth-ventricular choroid plexus papilloma and hydrocephalus with very large lateral ventricles. Posterior fossa surgery and ventriculostomy were performed sitting. The tumor was removed satisfactorily, the wound closed, and the patient regained consciousness. Approximately half an hour later, drowsiness returned with signs of raised intracranial pressure. Investigation revealed an acute subdural hematoma over the left cerebral hemisphere. The patient returned to the operating room for craniotomy and evacuation, after which the symptoms resolved and consciousness returned. The author believes no subdural hematoma was present during the posterior fossa operation, since there had been no signs of raised pressure, surgery was successful, and the patient awakened. The hematoma probably arose during repositioning, when brain displacement tore a bridging vein, causing renewed unconsciousness after initial recovery.
Third case. A 17-year-old patient with a fourth-ventricular tumor underwent posterior fossa surgery and ventriculostomy in the sitting position. The tumor was removed satisfactorily. After wound closure, before the patient was laid flat, several bouts of coughing occurred. Once the patient was laid down and the anesthesiologist prepared for extubation, the right pupil was found larger than the left and unreactive to light. A burr hole and craniotomy were required to evacuate a subdural clot. The patient recovered well.
Fourth case. A 2-year-old child with a lateral-ventricular choroid plexus papilloma had an enlarged head and ventricular system. Craniotomy was performed supine. After the ventricle was opened and the tumor completely removed, the ventricle and cortex collapsed. Profuse subdural bleeding occurred at multiple sites, not all of which could be visualized. The patient ultimately developed shock and died.
These cases teach the following lessons: (1) When ventriculostomy is used to lower pressure in patients with large ventricles, CSF should not drain continuously; open the drain intermittently as needed. (2) Patients with markedly enlarged lateral ventricles should be operated on lying down rather than sitting, reducing the risk of acute subdural hematoma. (3) Coughing while sitting, with the ventricles still collapsed, jolts the brain and may tear bridging veins. (4) Repositioning or transferring a patient immediately after surgery must always be gentle and careful, avoiding blows to the head. (5) In children, subdural hemorrhage may cause pallor, tachycardia, and hypotension, which are useful diagnostic signs.
Original pages 552–553
4.3 Venous Obstruction
Impaired venous return to the heart causes cerebral venous congestion and marked swelling, which may be fatal. During surgery, this may result from the following:
4.3.1 Tearing of a cerebral vein. A large cortical vein may be torn during tumor dissection, such as a superior cortical vein draining into the superior sagittal sinus, the Sylvian vein, or the vein of Labbé. The brain drained by that vein then swells, making further dissection impossible. Sometimes the swollen brain must be removed unnecessarily, with additional loss of function. Cortical veins must therefore be carefully preserved; tearing them may prove fatal.
For example, a 50-year-old man had a parasagittal meningioma at the postcentral gyrus. The tumor lay adjacent to the cortex and displaced a superior cortical vein anteriorly. During dissection the vein was torn and coagulated. The adjacent brain rapidly swelled and protruded through the craniotomy, with patchy subarachnoid hemorrhage. Surgery could not proceed, and some brain tissue had to be removed. Further removal was difficult because the brain continued to swell and venous bleeding constantly obscured the field. The patient developed postoperative hemiplegia and died on the second day from brain swelling leading to brain stem dysfunction.
This example illustrates the harm caused by injury to a major cortical vein. The surgeon must learn to prevent such injury during dissection and to use the techniques of venous hemostasis described later.
4.3.2 Compression of a vein by a retractor. Strong, prolonged brain retraction impairs circulation. Retractors should not be placed over large cortical veins and should be released periodically. Retraction that presses a vein against the craniotomy margin likewise obstructs venous return and causes brain swelling.
Original page 553
4.4 Other Causes
Excessive fluid administration, administration of hypo-osmolar fluids, or irrigation of the exposed brain with a hypo-osmolar solution may cause brain swelling.
Original pages 553–554
5. AIR EMBOLISM
Air embolism is an important complication of surgery in the sitting position. Air enters the right atrium because venous pressure at the operative site is lower than that within the right atrium. When a vein is opened, air is sucked into the right atrium. Diagnostic manifestations include: 1) hyperventilation preceding air hunger, cyanosis, or apnea; 2) a fall in blood pressure without another explanation; 3) tachycardia and dysrhythmia; 4) increased central venous pressure; 5) EKG changes with atrial and ventricular extrasystoles; 6) a mill-wheel murmur, audible with an esophageal stethoscope or ultrasonic Doppler; 7) a fall in expired CO2; 8) occasionally, visible air bubbles in cerebral vessels; and 9) cardiac arrest when a large volume of air in the heart produces severe effects.
Several devices are available for detecting air embolism, including ultrasonic Doppler and the capnographic technique for measuring expired CO2.(21) Two newer devices are the transesophageal Doppler probe(22) and the transesophageal echocardiographic unit.(23) Both are sensitive and can detect abnormalities on both sides of the heart. They are not yet in use in the Neurosurgical Unit at Siriraj Hospital.
Ultrasonic Doppler is a very sensitive means of detecting air embolism. Both the anesthetist and the surgeon can hear and recognize the embolism simultaneously, allowing the surgeon to act immediately to prevent further air entry. Sometimes, however, the opening in the vein is difficult to locate quickly.
Original pages 554–555
Treatment of Air Embolism
Prevention is most important. If the sitting position is unnecessary, operating with the patient lying down reduces the risk. When the sitting position is used, a catheter should be introduced by venous cutdown at the antecubital fossa, with its tip in the right atrium. Bunegin and colleagues(24) described the appropriate position for maximum air aspiration using a catheter with multiple holes near its tip. A chest X-ray must always confirm that the tip lies in the right atrium; sometimes it remains in the superior vena cava or turns upward into the common jugular vein. If surgery in the sitting position proceeds without verification of the catheter tip, air embolism cannot be adequately managed.
The principles of treatment are as follows:
1) The surgeon must immediately close any visible opening in a vein, using a clamp, ligature, or suture as appropriate. If the opening cannot be seen, cover the operative wound with wet gauze and keep the field flooded with fluid to prevent air entry. To locate the opening, temporarily apply positive end-expiratory pressure or compress both common jugular veins. The resulting rise in central venous pressure causes bleeding from the opening and makes it visible.
2) Aspirate air from the right atrium through the catheter. Blood withdrawn into the syringe should be reinjected through another venous line to prevent blood loss.
3) Stop N2O and administer 100% O2 with positive-pressure ventilation.
4) If the venous opening cannot be closed and air embolism increases, close the wound rapidly, turn the patient into the left lateral position, and continue aspiration until no air remains.
5) If blood pressure falls, administer a vasopressor, such as ephedrine 10–30 mg intravenously.
Once the condition has returned to normal, surgery may be continued with the patient lying down if tumor removal must be completed that day. If the patient’s condition is unfavorable, the operation should be postponed.
Original pages 555–556
Postoperative Complications of Brain Tumor Surgery
Complications can occur after any operation, and most cause increased intracranial pressure. Early, accurate diagnosis and timely, appropriate treatment preserve life and function. Delay may result in poor recovery or death. Close, continuous observation is particularly important during the first 48 hours. When a complication is suspected, urgent investigation should begin before all its manifestations have appeared; this can make a substantial difference to the outcome.
The surgeon must take meticulous preventive measures, perform the operation properly, secure complete hemostasis, and avoid factors that cause brain swelling. Complications are closely related to the surgeon’s experience and skill; experienced surgeons encounter fewer complications.
1.1.2 Bleeding outside the dura (epidural hematoma)
1.1.3 Bleeding beneath the dura (subdural hematoma)
1.1.4 Bleeding within the brain (intracerebral and intracerebellar hematoma)
1.2 Brain edema
1.3 Necrotic brain tissue
1.4 Hydrocephalus
1.5 Air within the ventricle
2) Cerebrospinal fluid leakage
3) Infections
4) Fluid and electrolyte imbalance
4.1 Hyponatremia
4.2 Hypernatremia
5) Hormonal Disturbance
5.1 SIADH
5.2 DI
6) Seizures
7) Hyperthermia
Original pages 556–557
1) Hemorrhage
Hemorrhage is a major cause of raised intracranial pressure and many rapid postoperative deaths. Intraoperative blood loss is usually not fatal because adequate transfusion can be given. After surgery, however, a hematoma of only 40–50 cc may cause unconsciousness, death, or loss of functions that the surgeon took great care to preserve during the operation. It is regrettable when successful tumor removal is followed by destruction of function from this complication.
Postoperative hemorrhage may occur at the following sites:
Original page 557
1.1 Bleeding from Residual Tumor
Every surgeon fears and is troubled by incomplete tumor removal, because the residual surface may bleed after surgery from its numerous abnormal, fragile vessels. After the bulk of the tumor has been removed, a fall in blood pressure may allow arterial bleeding from the tumor to stop with pressure or coagulation. When blood pressure rises after wound closure, bleeding may recur. Before closure, the anesthetist should be asked to raise the blood pressure so that bleeding points can be identified and hemostasis secured as an additional precaution. Complete removal is the best prevention of recurrent bleeding. Surgeons often find that, however profuse the hemorrhage during the operation, it stops once the entire tumor has been removed.
Original page 557
1.2 SUBDURAL HEMATOMA
This most commonly results from tearing of bridging veins. After removal of a large tumor, collapse of the brain stretches these veins. Coughing, jolting of the head during transfer onto or off the bed, or positioning the patient with the operative side downward may tear them and cause an acute subdural hematoma, as discussed earlier.
After removal of a falx meningioma, the attachment contains many dural vessels that supplied the tumor. If hemostasis is inadequate, these may bleed into the subdural space later.
Original pages 557–558
1.3 EPIDURAL HEMATOMA
An epidural hematoma may arise from three sources [Translator’s note: the original enumerates four sources below and subsequently refers to all four]: i) the middle meningeal artery and its branches; ii) venous tributaries in the dura and arachnoid granulations; iii) the diploic space at the skull margins and in the bone flap; and iv) the temporalis muscle. Prevention requires secure hemostasis at all four sites. Bleeding from the middle meningeal artery may be controlled by suture ligation. When cutting the dural flap, begin below and pass across the frontal, temporal, and parietal regions, leaving its base at the superior sagittal sinus; this divides the arterial supply to the dura. Small bleeding points on the dura should be controlled with bipolar coagulation. The dura near the craniotomy margin should then be tacked to the galea and muscle to prevent an epidural hematoma beneath the adjacent skull. Bleeding from the diploic space at the skull margins can be stopped by plugging the openings with bone wax. Bleeding openings in the bone flap may likewise be plugged with bone wax. Alternatively, separate the temporalis muscle from the outer table of the bone flap, leaving only its terminal attachment to the bone; this divides the vessels supplying the flap from the muscle. Bleeding from the temporalis must also be stopped. If all these measures are completed properly, an epidural hematoma should not occur.
Original page 558
1.4 INTRACEREBRAL AND INTRACEREBELLAR HEMATOMA
These arise from two causes: i) forceful retraction and operative manipulation contuse and swell the brain, making small vessels liable to rupture both during and after surgery; and ii) venous obstruction, which may occur when retraction compresses a cortical vein against the craniotomy margin or when a vein is torn during surgery. Venous return from that vein’s tributaries is impaired, producing swelling and necrotic brain tissue that bleeds readily.
An intracerebral or intracerebellar hematoma may be solitary or multiple. The clots are usually not large, but associated brain swelling causes rapid deterioration.
Original pages 558–559
Symptoms and Signs of Postoperative Hemorrhage
Whatever its location, hemorrhage causes increased intracranial pressure. Changes are generally evident in the first 24–48 hours, although in some patients they occur within 1–2 hours after surgery. The timing depends on the rate of bleeding and the size and location of the hematoma. As the hematoma develops, headache progressively increases and vomiting occurs. Consciousness gradually deteriorates, the pulse progressively slows, and blood pressure rises. Respiration may become shallow or show a Cheyne–Stokes pattern. With a posterior fossa hematoma, respiration slows and apnea develops rapidly. Some patients with supratentorial hemorrhage develop weakness of one side, usually contralateral to the side from which the tumor was removed. An intracerebral hematoma may also cause seizures. Without timely investigation and treatment, the patient becomes unconscious, the pupil on the side of the hematoma dilates and loses its light reaction, decerebration occurs, and death follows from brain stem dysfunction.
Original pages 559–560
Treatment
As soon as the patient recovers from anesthesia, consciousness, vital signs, limb movements, and pupillary size and reactions must always be assessed, followed by close observation. If consciousness begins to change and Cushing’s reflex appears, urgent angiography or C.T. is required to determine the cause. A hematoma may require reopening the craniotomy for evacuation. Whether to reoperate must, however, be considered individually, according to the speed of deterioration, the size and location of the clot, and other factors contributing to impaired consciousness. In the author’s opinion, progressive deterioration in consciousness with a mass effect on C.T. requires reopening, evacuation of the hematoma, and secure hemostasis; medical treatment alone is insufficient.
Evacuation of blood from the epidural and subdural spaces generally presents little difficulty, and hemostasis is readily achieved. With an intracerebral or intracerebellar hematoma, however, reaching the clot reveals swollen, soft, friable, necrotic brain tissue resulting from the first operation and the postoperative clot. Hemostasis is difficult in this tissue even when the bleeding is capillary. Sometimes portions of this friable brain must be aspirated back to healthy tissue before bleeding can be stopped. This is another cause of additional loss of brain function. When bleeding arises from residual tumor, some patients require an attempt at complete tumor removal to prevent a second hemorrhage.
Original printed page 560
2) Brain swelling
This is another complication responsible for many deaths after tumor removal, and the surgeon must try to prevent it during surgery. The principal causes of intraoperative and postoperative brain swelling are: i) trauma to the brain during tumor dissection. Retraction by an assistant is often unstable, with frequent changes in position and traction force, occasionally tearing the brain. A self-retaining retractor is preferable and causes less injury. In principle, the less the brain is injured, the less it swells. During tumor dissection, therefore, the surgeon should handle the brain as gently and as little as possible. ii) Venous obstruction caused by retraction or control of venous bleeding is an important cause of swelling. iii) Hyponatremia and water intoxication.
In postoperative brain swelling, symptoms of raised intracranial pressure appear about 48–72 hours after surgery. Consciousness gradually deteriorates, with increasing drowsiness and Cushing’s reflex. These changes develop less rapidly than with hemorrhage, although the two may sometimes be difficult to distinguish clinically. CT or MRI is needed for a definite distinction. Hemiparesis or seizures may also occur.
For treatment, see Chapter 4.
Original printed pages 560–561
3) NECROTIC BRAIN TISSUE
This is another cause of raised intracranial pressure. It occurs where the cortex has been incised for tumor dissection, damaging brain tissue and occluding arteries and veins. The brain tissue at this site and farther away in the territory supplied by those vessels becomes infarcted and swollen. If extensive, this raises intracranial pressure. Occasionally the affected tissue must be removed before the condition resolves.
Original printed page 561
4) HYDROCEPHALUS
This occurs postoperatively for two reasons. i) During surgery for tumors within or near the third and lateral ventricles, small clots or tissue fragments may enter and obstruct the narrow aqueduct of Sylvius, blocking CSF flow and raising intracranial pressure. Prevent this during surgery by packing the ventricular space beyond the tumor with moist cotton. ii) During posterior fossa surgery, blood commonly enters the subarachnoid space, obstructing CSF circulation and impairing absorption at the arachnoid granulations, thus producing communicating hydrocephalus. This is an important cause of tense bulging at the craniectomy wound and CSF leakage through it, followed by postoperative meningitis or ventriculitis.
CT readily demonstrates hydrocephalus. Treatment requires CSF drainage by lumbar puncture, ventriculostomy or a shunt to lower CSF pressure and stop leakage. Select the appropriate method individually.
Original printed pages 561–562
5) PNEUMOCEPHALUS
Whenever the skull is opened, some air remains intracranially, in the epidural or subdural space or in the ventricles. This air exerts pressure but is slowly absorbed. Together with brain swelling and hydrocephalus, it may further increase intracranial pressure. Therefore irrigate these cavities to expel all air before closing the dura.
When nitrous oxide anesthesia is used for posterior fossa surgery in the sitting position, air may rise into the ventricular system and form a closed gas-containing space. Nitrous oxide in the blood exchanges with nitrogen in this closed space. Nitrous oxide is generally 34 times more soluble in blood than nitrogen(25). Consequently, nitrous oxide accumulates in the closed space and expands its gas volume, increasing intraventricular pressure. The gas can be removed through a ventriculostomy tube.
Original printed page 562
6) CSF LEAKAGE
This commonly occurs after surgery for tumors at the base of the frontal lobe or in the pituitary fossa. A low skull opening is needed for adequate tumor exposure but may open the frontal air sinus. Dissection of a frontal tumor such as an olfactory groove meningioma may leave a defect in the cribriform plate. These defects cause CSF rhinorrhea. In posterior fossa surgery, craniectomy may open the mastoid air cells, producing CSF otorrhea if the tympanic membrane is perforated. Watertight dural closure helps prevent leakage. Mastoid air-cell openings may additionally be sealed with a thin sheet of bone wax or covered with a muscle patch.
Hydrocephalus or raised CSF pressure is an important cause of leakage. Prevention therefore requires maintaining low CSF pressure, using repeated lumbar punctures, ventriculostomy or a shunt as appropriate for the individual patient.
Original printed pages 562–563
pseudomeningocoele
This may occur after posterior fossa tumor surgery by craniotomy when the dura is not sutured closed as before, but its edges are attached to muscle and galea. CSF then collects between the cerebellum, muscle and dura. Several months after surgery, a bulging fluid-filled sac resembling a meningocele develops. Hydrocephalus makes it particularly tense. It can be resolved by lowering CSF pressure.
Treatment of CSF leakage follows these principles: i) Position the patient to reduce hydrodynamic pressure at the leak, for example with the head elevated. ii) Suture the skin-wound opening closed. iii) Correct the cause of raised CSF pressure, for example by complete tumor removal, lumbar puncture, ventriculostomy or a shunt. Remember that some patients may become drowsier after leakage stops if an expanding mass remains: the leak had lowered intracranial pressure, but when it stops, CSF accumulates and pressure rises. iv) Give antibiotics as appropriate for the individual patient.
Original printed pages 563–564
7) Infection
Most postoperative infections involve the scalp wound. Acute epidural, subdural or brain abscesses are very rare, particularly after clean operations such as brain tumor surgery, in which they are now almost never seen because of good technique and antibiotics. Three forms of infection may occur: skin-wound infection, osteomyelitis, and meningitis or ventriculitis resulting from CSF leakage. Predisposing factors for infection and poor wound healing include advanced age, poorly controlled diabetes, a poorly vascularized scalp flap, necrosis of skin edges, prolonged surgery, steroid and immunosuppressive therapy, and repeat craniotomy. Wound inflammation generally becomes evident toward the end of the first week, with fever, leukocytosis, red and warm skin, or palpable abscesses at suture sites. Remove the sutures and give appropriate antibiotics for an adequate duration. Open the wound to drain any pus. In some patients infection appears weeks or months after surgery as protruding infected granulation tissue along the wound, sometimes discharging pus. This usually accompanies infection of the bone flap and epidural infected granulation tissue. Open the scalp flap, remove the bone flap, curette all infected granulation tissue, excise unhealthy wound edges and close the wound to allow healing. The bone flap must be removed because its poor blood supply makes it behave like a foreign body.
During craniotomy closure, the surgeon must achieve a watertight dural closure to prevent infection from spreading into the subdural space or the operated brain region. If this occurs, the patient often dies.
Infection from CSF leakage or intraoperative contamination causes meningitis or ventriculitis, with high fever, drowsiness, neck stiffness, a positive Kernig’s sign and possible death. Stop the CSF leak promptly and give high doses of antibiotics appropriate to the organism, with good CSF penetration, for 3–4 weeks.
Original printed pages 564–565
8) Fluid and electrolyte imbalance
Hyponatremia is a complication of brain tumor surgery and craniotomy for other cerebral diseases. Causes include excessive hypotonic fluid, such as 5% dextrose in water, and SIADH (syndrome of inappropriate antidiuretic hormone). Both cause dilutional hyponatremia and water intoxication. Patients develop vomiting, nausea, deteriorating consciousness and progressively increasing drowsiness, sometimes with seizures or hemiparesis. These findings may be difficult to distinguish from postoperative hemorrhage or brain swelling. They improve when the sodium level returns to normal.
The main treatment is fluid restriction, which works well when hyponatremia and symptoms are mild. In severe hyponatremia, the author has found that an initial 300 cc of 3% or 5% NaCl, together with fluid restriction, hastens recovery. Subsequent administration is determined by the patient’s symptoms and sodium level.
Hypernatremia or hyperosmolarity is less common. The principal causes are dehydration and excessive sodium administration. It occurs in patients with brain disease who are unconscious or drowsy, lack thirst, have difficulty swallowing, vomit, have high fever or rapid breathing, or lose excessive water in the urine (polyuria). Following surgery for tumors around the pituitary gland and hypothalamus, destruction of the source of ADH may cause diabetes insipidus. It may also occur with osmotic diuresis, such as mannitol used to reduce intracranial pressure.
Signs and symptoms of hypernatremia include increasing drowsiness, confusion or unconsciousness, fever, dry mouth and oliguria, except when diabetes insipidus or osmotic diuresis is responsible. Some patients have seizures and weight loss.
Treatment principally consists of electrolyte-free water in amounts exceeding ongoing water losses, with repeated electrolyte measurements until normal values are restored. At the same time, correct the cause of polyuria, for example by treating diabetes insipidus as described earlier, and stop diuretics.
Original printed page 565
9) HORMONAL DISTURBANCES
These may occur after surgery for tumors around the pituitary gland and hypothalamus. Common examples are SIADH (syndrome of inappropriate antidiuretic hormone) and diabetes insipidus, discussed earlier in this chapter.
Original printed page 565
10) Seizures
Postoperative seizures may be motor or nonmotor. They are most common after surgery in or near the motor area. A preoperative history of seizures increases the likelihood of postoperative seizures. If a seizure occurs, promptly give anticonvulsants until it stops, as discussed earlier, and investigate the cause with CT. During the first 2–3 postoperative days, common causes are postoperative hemorrhage, brain swelling and infarction. Metabolic abnormalities can also cause seizures. Once the cause is identified, treat it accordingly.
Original printed pages 565–566
11) HYPERTHERMIA
A persistently elevated temperature from the first postoperative day, without returning to baseline, usually indicates dysfunction of the hypothalamic temperature-regulating center, termed central hyperthermia. Blood in the subarachnoid space, ventricles or brain may also cause fever, but it is usually less marked than central hyperthermia. When the patient has a high fever, lower the temperature by the methods described earlier in the chapter, to reduce cerebral metabolism, CBF and intracranial pressure.
Original printed page 566
General techniques of brain surgery
Many new instruments and techniques for diagnosing and operating on cerebral disease have made brain surgery easier and more successful. These include CT, MRI, bipolar forceps coagulators, microinstruments, microscopes, microneurosurgical techniques, ultrasonic aspirators and lasers. CT and MRI accurately locate tumors, allowing the surgeon to make a small skull opening precisely over the tumor. This shortens the operation and reduces complications.
Bipolar forceps coagulation provides effective hemostasis even where unipolar coagulation would be dangerous, such as the brainstem. For tumors at important sites such as the third ventricle, pituitary gland and cerebellopontine angle, with vital structures including the brainstem, cranial nerves and vessels, microscopes and microinstruments allow more confident removal while preserving cranial nerves and important vessels. The newest and very useful developments at present are the ultrasonic aspirator and laser. Ultrasonic aspiration facilitates removal of large tumors or those at important sites by aspirating tissue fragmented by ultrasound, reducing tumor size. Advances in laser technology for neurological surgery also allow surgery without blood loss and shorten operating time.
Before discussing operative techniques, the following basic principles should be understood.
Original printed pages 566–567
1. Patient positioning
Before surgery, the surgeon must carefully assess tumor location, side, size, vascularity and feeding vessels on CT, MRI or cerebral angiography. Before anesthesia, display the images that best show the tumor, as they will be needed throughout the operation. Relate them to the surface anatomy of the head and brain to place the skull opening directly over the tumor.
Good positioning must achieve these important objectives:
i) Provide the easiest and most complete exposure of the lesion.
ii) Avoid intraoperative and postoperative complications, such as venous obstruction or compression of spinal nerves.
iii) Allow the anesthetist to correct cardiovascular and respiratory abnormalities during surgery without disturbing the operative field.
iv) Keep the surgeon comfortable during a prolonged operation.
v) Allow convenient placement of the anesthetic machine, surgical instruments, scrub nurse, assistant and microscope.
In general, the operating surgeon should personally position the patient and mark the skull opening to ensure correct tumor exposure and avoid potential injury.
The following positions are used in brain surgery:
Original printed pages 567–568
1.1 Supine position
The patient may face directly upward or be turned slightly toward the opposite side, depending on tumor location. This position is suitable for frontal lobe and sellar tumors. No support beneath the shoulder on the operative side is needed because the neck is not rotated. Avoid compression of either ulnar nerve. A horseshoe headrest may be used for a short operation without causing pressure sores. A pin-type head holder avoids pressure sores even in prolonged operations, leaving only scalp puncture sites. Choose pin sites away from vessels to prevent bleeding when the pins are removed. Place the pins below the frontal and parietal prominences to prevent upward slippage, and avoid the thin temporal squamous bone.
Keep the head slightly above the chest to improve venous drainage. Air embolism is possible, although the author has not encountered it. Moderately extend the head so that gravity allows the frontal lobe to fall toward the vertex, reducing the retraction needed to reach subfrontal and sellar tumors.
Temporal and parietal tumors require substantial rotation of the face and neck toward the opposite side. This may obstruct venous drainage and overstretch neck muscles, increasing intracranial pressure and making surgery difficult and dangerous. Elevate the shoulder on the operative side with a sandbag to reduce neck rotation.
After positioning, always verify the endotracheal tube position and adequate ventilation, then arrange the gas tubing and anesthetic machine appropriately. Apply ophthalmic ointment over the entire cornea and tape the eyelids fully closed to prevent dryness and corneal ulceration from contact with the drapes.
Original printed page 568
1.2 Lateral position
This position is used for posterior fossa and occipital lobe tumors. Place a soft pillow beneath the dependent side of the chest. Extend the lower arm forward to reduce pressure on axillary nerves and vessels, and support the upper arm. Always flex the lower hip and knee to provide a stable base and prevent the patient from rolling backward. Keep the upper leg straight, with a pillow between the legs. Secure the iliac crest and chest to both sides of the operating table with broad adhesive straps. Avoid compression of the peroneal and ulnar nerves. Once the trunk is positioned, secure the head in a pin-type holder with the neck tilted slightly downward. Tape the upper shoulder downward to enlarge the operative space. Rotate the head moderately downward as required by tumor location (Figure 7.1)
Original printed pages 568–569
1.3 Prone position
This position is used for tumors in the posterior fossa, occipital lobe and cervical spine. It is important to avoid pressure on the chest and abdomen, which would increase intrathoracic pressure and impair venous return from the brain. Place the patient prone on a Wilson frame with an open center, or use cylindrical cushions under the pelvis and upper chest. Keep both arms beside the body and both feet against the foot support. Raise the head of the operating table so the head does not hang downward, improving cerebral venous return. Moderately flex the head and neck to facilitate posterior fossa access and secure the head in a pin-type holder, avoiding pressure sores on the forehead and cheekbones. For an occipital lobe tumor, keep the head straight without flexion to expose the occipital region. After positioning, check that the endotracheal tube remains correctly positioned, because flexing the head and neck may advance it into one bronchus, ventilating only one lung and adversely affecting the brain.
Figure 7.1 Lateral positioning, suitable for posterior fossa and occipital lobe surgery.
If a horseshoe headrest is used, protect the forehead and cheekbones from pressure sores with soft cotton padding. Ensure that neither eye is compressed by the edge of the headrest.
Original printed pages 569–570
1.4 Semiprone position
Position the patient as for the lateral position, then rotate approximately another 45° forward. Extend the lower arm backward and place a pillow anteriorly to support the trunk in the semiprone position. Secure the trunk with adhesive straps and position the head appropriately for the tumor site within the posterior fossa.
Original printed pages 570–571
1.5 Sitting position
This position provides good posterior fossa exposure but carries several possible hazards, including air embolism, hypotension, supratentorial subdural hematoma and pneumocephalus, as discussed under complications. These require particular attention. After anesthesia, gradually raise the head of the table, checking blood pressure at intervals. If it falls, wait for the patient to adapt and the pressure to normalize before proceeding to the sitting position. If blood pressure does not recover, do not operate in this position. Wrap the legs with elastic bandages from feet to groins to limit dependent pooling of blood while sitting. Flex the hips and knees and elevate the legs above the horizontal. Flex the head, leaving at least about two fingerbreadths between the chin and sternum. This provides good posterior fossa access. Flexion until the chin touches the sternum may kink the endotracheal tube and impair ventilation. For a cerebellopontine angle tumor, turning the face toward the tumor side may improve exposure. Finally, secure the head in a pin-type holder (Figure 7.2)
Figure 7.2 Sitting position, suitable for posterior fossa and cervical spine surgery.
Original printed page 571
2. Preparation of the operative skin
Correct skin preparation is important in preventing wound infection. Shave the entire head closely; partial shaving may allow contamination. After positioning, scrub the scalp with Betadine or Hibitane soap for about 10 minutes to remove skin bacteria. Once dry, mark the incision with sterile dye or a light superficial scratch with a knife. Place sterile drapes around the marked incision. Do not omit this marking, since draping obscures surface landmarks and the skull opening may otherwise miss the tumor site. A Steri-Drape, a plastic sheet adhesive on one side, placed over the scalp and upper drapes prevents fluid from soaking the drapes and spreading bacteria along with it.
Original printed page 571
3. Hemostasis
Several sites may bleed profusely during brain surgery. The surgeon must know the appropriate hemostatic technique for each. Unless bleeding is completely controlled, brain surgery becomes difficult. Potential sources include the scalp, skull, dura mater, middle meningeal artery, superior longitudinal sinus, transverse sinus, arachnoid granulations, cerebral vessels and tumor vessels.
Original printed pages 571–574
3.1 Scalp bleeding
The scalp is highly vascular, and opening and closing it can cause substantial blood loss. Most scalp vessels lie between the skin and galea. Individually clamping and ligating cut vessels, as in general surgery, is ineffective and slow. Methods of scalp hemostasis are as follows:
3.1.1 Have the assistant press firmly with the fingertips along both sides of the planned incision, compressing vessels against the skull to prevent bleeding. Incise a length of about 6–7 cm at a time (Figure 7.3)
3.1.2 Grasp the galea and undersurface of the skin together with arterial clamps about 1 cm apart along both wound edges. Tie the clamps together in groups of approximately 5–6 (Figure 7.4). Continue along the entire planned scalp incision. The clamps fall under gravity and exert traction on the scalp, stopping bleeding.
Figure 7.3 Scalp hemostasis by finger pressure along both wound edges.
3.1.3 Clips may be applied to both wound edges, including both skin and galea to stop bleeding. Michel clips (Figure 7.5), Raney clips or Kölner clips may be used. Michel clips come in long, medium and short sizes. The medium size is generally used for an ordinary adult scalp and the short size for the thinner scalp of a child. Place Michel clips about 1 cm apart. They cannot be reused and are therefore costly, but they keep the field tidy and do not obstruct the operation. Raney clips are broad spring clips that indent and darken the scalp edges, potentially impairing healing. Place cloth beneath them on the scalp before application (Figure 7.4). Raney clips can be reused and are therefore economical.
3.1.4 Use bipolar or unipolar coagulation at individual points where vessels remain open. Coagulate only the vessel, avoiding the skin, to promote good healing.
3.1.5 Inject a solution of adrenaline, 1 mg in 200 cc of water, beneath the scalp along the planned incision. Vasoconstriction reduces wound bleeding. Disadvantages include elevated blood pressure from systemic absorption of adrenaline and, in some patients, skin necrosis with failure of wound healing.
Figure 7.4 Hemostasis with arterial clamps grasping the galea and underside of the scalp. Kölner clips control bleeding on the opposite wound edge.Figure 7.5 Scalp hemostasis using Michel clips.
3.1.6 Scalp closure is another stage when substantial bleeding may occur. Correct suturing also provides hemostasis. Before closure, thoroughly irrigate all bone fragments from the wound edges, because bone acts as a foreign body and prevents healing. Begin closure proximally along the arterial supply to the scalp, controlling inflow and reducing distal bleeding. Also work from the higher part of the wound toward the lower part so that bleeding does not obscure suturing. Starting below allows blood from above to pool where sutures are being placed. Remove arterial clamps or clips in groups of 5–6 at a time, and approximate the subcutaneous tissue together with the galea at intervals of about 1.5 cm. Then approximate the full thickness of the skin. The author prefers alternating one subcutaneous suture with two skin sutures, with the subcutaneous stitch lying between the two skin stitches. This improves hemostasis because the skin sutures reinforce vessel compression. After completing one group, remove the next group of clamps and repeat until finished. Do not space skin sutures too widely, as bleeding may occur; intervals should not exceed 1.5 cm. Inadequate scalp hemostasis during closure can cause a large hematoma or rapid drainage of hundreds of cc of blood, requiring reopening for hemostasis. This wastes time and provides an opportunity for infection. The surgeon must therefore always secure complete hemostasis during closure.
Original printed page 574
3.2 Muscle bleeding
Muscle bleeds along its cut edges and where it has been detached from the skull. This most often involves the temporalis during supratentorial craniotomy, or the occipital muscles during posterior fossa exposure. Coagulation usually stops the bleeding easily. If it persists, use suture ligation.
Original printed pages 574–575
3.3 Bone bleeding
Since Victor Horsley invented bone wax(26) and successfully used it to control bone bleeding, this hemostatic problem has been resolved. Bone wax remains in use today. Without it, brain surgery would be difficult, and even with modern operative techniques, postoperative hemorrhage could still be dangerous. Press bone wax into the bone openings to plug them. If the middle meningeal artery is torn while the bone flap is being elevated, bleeding may emerge from a bony canal containing the retracted arterial end. Do not simply plug it with bone wax: postoperative hypertension may dislodge the wax and cause an acute epidural hematoma. A better method is to remove bone until the artery is visible, then suture-ligate or coagulate it until bleeding stops. Besides using bone wax, bleeding from the bone flap may be stopped by detaching the temporalis from the skull, leaving only its end attached. This interrupts the muscular blood supply to the bone. Bleeding from the muscle must also be controlled.
When applying bone wax along the skull edge, do not push large pieces beneath the skull. They may separate the dura from the inner skull surface and cause bleeding on the dural surface.
Original printed pages 575–576
3.4 Dural bleeding
Dural bleeding comes from the middle meningeal artery, superior sagittal sinus and arachnoid granulations (Pacchionian bodies). It may be profuse and difficult to control, making prevention important. The middle meningeal artery is often torn by a sharp inferior temporal bone edge when the bone flap is turned away from the dura, producing heavy arterial bleeding. Prevent this by slightly lifting the bone flap and inserting a periosteal elevator to separate the skull from the dura all around. After fracturing the temporal bone attachment, do not turn the flap directly downward; first lift it, then turn it downward. This prevents the fractured edge from injuring vessels. The author has often seen simultaneous tears of the middle meningeal artery, dura and cortical vessels caused by incorrectly turning the flap.
Bleeding from the superior sagittal sinus and arachnoid granulations can be avoided by keeping the skull opening at least 3–4 cm from the midline. If midline exposure is necessary, for example for a tumor near the midline, make burr holes about 2 cm from the midline on both sides and join them by removing the intervening bone with a rongeur. This avoids injury to the superior sagittal sinus.
Control a torn middle meningeal artery with a silver clip across its open end or by passing a suture through the dura around the artery and tying it. If the arterial end lies deep to the skull edge, remove a little more bone until it is visible, then suture-ligate, clip or coagulate it. Suspend the dura from muscle or galea with sutures. If these methods fail, it may be necessary to approach the artery at the foramen spinosum. Separate the dura from the inner skull surface in the middle fossa and follow the middle meningeal branches from distal to proximal. At the floor of the middle fossa, identify the foramen spinosum. If the arterial segment between dura and foramen is long enough, apply a silver clip and divide the artery, or simply clip it, to stop bleeding. If the segment is too short to clip, pack a piece of cotton approximately 3 × 5 mm into the foramen spinosum to occlude the artery. The cotton may be left there without harm. Small middle meningeal branches on the dural surface are readily controlled with bipolar coagulation. Avoid unipolar coagulation because it causes marked dural contraction. Finally, suspend the dura along the skull edge from the galea all around to prevent epidural bleeding beneath the skull.
Original printed pages 576–577
3.5 Bleeding from arachnoid granulations
Small bleeding points may be controlled with bipolar coagulation. This is ineffective for larger areas. Cover the bleeding site with an adequately sized piece of Gelfoam, place moist cotton over it and apply pressure for 2–3 minutes to stop bleeding. If the bleeding granulation is at the skull edge, cover it with Gelfoam and suspend the dura from the galea with sutures.
Original printed pages 577–578
3.6 Bleeding from a dural venous sinus
Although the blood is venous, a tear can cause substantial blood loss. The taut sinus walls cannot be approximated to close the defect, and coagulation is ineffective. A good method is to cover the opening with a muscle patch, pass a suture through the dura on either side and tie it so that the thread presses down on the patch. Apply cotton briefly until bleeding stops, then remove the cotton (Figure 7.6)
AI-enhanced and colorized image · Switch to view the originalFigure 7.6 Hemostasis of a dural sinus with a muscle patch or Gelfoam.
If the superior sagittal sinus must be divided, its anterior one-quarter to one-third may be divided without harm. Occlusion farther posteriorly may impair venous return, cause brain swelling and lead to death. To divide the sinus, make small dural openings on both sides, apply two clamps, divide the sinus and securely suture-ligate its ends. Simple ligation alone should be avoided because the ligature may slip.
Original printed pages 578–579
3.7 Bleeding from cerebral and tumor vessels
Bleeding from either arteries or veins on the cerebral or cerebellar cortex is readily controlled with bipolar coagulation for small vessels and silver clips for larger vessels. Before occluding a vessel, always consider the function of the brain territory it supplies. Avoid proximal occlusion of a torn vessel; occlude it at the bleeding site to minimize brain injury.
The author considers bleeding from cortical or bridging veins particularly important. Although bleeding may be easily stopped, swelling in the territory drained by the vein may be fatal. Sometimes the swollen brain must be resected to save the patient, leaving a disability. Therefore, if a large vein has a defect but is not completely divided, wrap Gelfoam around it and apply pressure for 2–3 minutes. Bleeding will stop, and the Gelfoam is unlikely to dislodge because venous pressure is low. This preserves normal venous flow. The author has seen a Sylvian vein torn during craniotomy by bone penetrating through the dura into the vein. The surgeon attempted bipolar hemostasis, but the entire hemisphere eventually swelled and the patient died. Small veins may be coagulated, except those draining important regions such as the brainstem and hypothalamus.
Bleeding during tumor dissection can be controlled with coagulation, silver clips and cotton packing. The best method of controlling tumor bleeding is prompt complete removal of the tumor, which stops the bleeding and leaves the field in good order. There may be slight bleeding from cerebral vessels supplying the tumor, but it is easily controlled. During dissection, systematically occluding and dividing the feeding vessels along the capsule margins minimizes blood loss during removal.
Original printed pages 579–581
4. Suction apparatus (sucker)
This is essential in every brain operation. Two suction units may sometimes be needed when substantial bleeding is anticipated. Suction serves the following purposes:
i) It keeps the operative field clean and dry, removing blood, cerebrospinal fluid and saline used to irrigate the brain, so that the surgeon can clearly see the lesion and important structures.
ii) It removes soft tumor gradually, reducing its size so that the remainder can be removed easily. For firm tumors, suction may be combined with a cutting loop.
iii) It identifies bleeding points. Sometimes the severed vessel can be lifted into view by suction and coagulated to stop the bleeding easily. When the bleeding point is unclear, I usually flood the operative cavity with saline and apply suction away from the bleeding site. The jet of blood and its stream through the water toward the suction tube reveal the point that needs coagulation.
iv) For firm tumors, the suction tube can help lift the tumor and facilitate its separation from the brain.
v) It removes necrotic brain tissue or substitutes for a knife during lobectomy. Suction exposes vessels running between the tissue to be removed and the healthy tissue, allowing convenient coagulation or clipping without causing bleeding.
Suction technique is important because improper use may impair brain and cranial nerve function. Suction tubes are available in several sizes. The choice depends on the operation: microsurgery requires a small tube, whereas tumor aspiration calls for a large one. Most tubes are metal and have a vent at the handgrip to regulate suction. Closing the vent completely with the thumb applies the full suction set on the machine; opening it reduces suction. Fukushima devised a tube with a teardrop-shaped oval vent that allows finer thumb control.
When suction is applied near brain tissue, cranial nerves or blood vessels, a thin cotton pledget should first cover the area, and suction should be applied through it to prevent injury. Gentle pressure while suctioning through the pledget also controls bleeding and dries the field. Gradually lifting the pledget reveals bleeding points for easy coagulation.
A large tube aspirates tumor quickly and removes more tissue. Begin in the least vascular area and gradually work outward. As the tumor shrinks, its margins and feeding vessels become more visible. Coagulating and dividing these vessels reduces its blood supply. If a tumor vessel is drawn onto the suction tip, coagulate it with bipolar forceps; with unipolar coagulation, apply the electrode to the metal suction tube to stop the bleeding.
Hazards of suction Suction may damage cranial nerves, blood vessels and important brain tissue. If these structures are not protected, a nerve or vessel may be drawn onto the tip, causing contusion or transection and loss of function. For example, the facial nerve may be injured during suction dissection of an acoustic neuroma. If the nerve becomes caught on the tip, an alarmed surgeon may pull the tube away and sever it. The correct method is to reduce suction when approaching the nerve. If the nerve adheres to the tip, open the vent or pinch the rubber tubing to interrupt suction, then gently push the nerve off the tip to preserve it. The optic and olfactory nerves are not true peripheral nerves but extensions of the brain and lack toughness. Suction can easily sever them, so they should be completely covered with cotton pledgets.
Striking, pulling or aspirating a vessel with the suction tube may tear it. Cerebral veins are particularly fragile and should remain carefully covered with cotton pledgets throughout tumor dissection.
Original printed page 581
5. Coagulator
An electrical coagulator controls bleeding from small vessels. There are two types: i) unipolar and ii) bipolar. Bipolar coagulation is now used for most neurosurgical operations.
Original printed page 581
5.1 Unipolar coagulation
Unipolar coagulation can be used for cutting and hemostasis. Its disadvantage is that current passes from the active electrode through the patient to a grounding plate placed against the leg. It therefore cannot be used in vital areas such as the brainstem, because the patient may fail to regain consciousness. Burns may also occur if the grounding plate is absent.
The operative field must be dry for effective unipolar coagulation, so suction is always required. The electrical setting must be appropriate. Besides coagulation, a loop electrode can cut firm tumors that cannot be aspirated, such as fibrous meningiomas. Cutting pieces from the center outward reduces the tumor to its capsule, allowing complete removal. However, using a loop on tumors near the medial part of the lesser sphenoid wing may be dangerous: in some patients the internal carotid artery runs through the tumor and could be cut. This possibility must always be borne in mind.
Original printed pages 581–582
5.2 Bipolar coagulation
Current flows only between the two electrode tips of the forceps, rather than through the patient to ground. If the tips touch, a short circuit occurs and no coagulation takes place. The bleeding point or tissue to be coagulated must therefore lie between the tips, which should remain approximately 2–3 mm apart. Unlike unipolar coagulation, bipolar coagulation can work in a pool of saline. Irrigating the tips during use improves coagulation, protects tissue from heat, reduces tissue shrinkage and prevents the tips from drying and sticking. Without saline, the tips adhere to dry, burned tissue. Tips coated with charred tissue will not coagulate effectively again until the coating has been scraped off.
An advantage of bipolar coagulation in neurosurgery is that it can control vessels in areas where unipolar coagulation would be dangerous, such as the brainstem(27). Small bleeding points on the wall of a large vessel may also be controlled with low current and saline irrigation, without vessel contraction or thrombosis. Unipolar coagulation would sacrifice such a vessel through contraction and thrombosis.
Original printed pages 582–584
6. Retractor
Retractors are another essential instrument in brain surgery because they expose the lesion. They include ordinary hand-held brain spatulas used to retract a brain tumor and self-retaining retractors that hold the brain without manual support. These useful devices come in many forms (Figure 7.7). They are generally divided into those attached directly to the skull edge and those attached to the operating table. Self-retaining retractors maintain steady traction, avoiding contusion, and their position and tension can be adjusted as needed. They free both of the surgeon’s hands for other tasks. A hand-held spatula tends to shift during prolonged retraction, readily bruising the brain and interrupting the operation.
Figure 7.7 Examples of self-retaining brain retractors. a. The De Martel type, attached to the skull edge. b. The Gilsbach type, attached to the operating table.
Principles of retractor use:
i) Use a self-retaining retractor.
ii) Lower intracranial pressure before applying a retractor; otherwise traction may tear the brain and make tumor exposure difficult.
iii) Choose a suitably small spatula that provides the required tumor exposure.
iv) Apply only enough traction to expose part of the tumor. There is no need to retract the brain until the entire tumor is visible; doing so damages brain tissue.
v) First cover the brain to be retracted with a cotton pledget to protect it from the blade edges.
vi) Whenever possible, position the spatula away from cortical veins to prevent venous occlusion and brain edema.
If hypotension develops, reduce retraction to maintain adequate brain perfusion.
Original printed pages 584–585
7. COTTONOID
Cottonoids are thin cotton pads cut into various sizes. A long black thread is sewn to one side to indicate the pad’s location, with the thread remaining outside the skull. They have the following uses:
i) Covering the brain to prevent drying. The pad retains water and keeps the cortical surface continuously moist.
ii) Covering cranial nerves and vessels near the tumor to protect them during dissection.
iii) Providing a protective layer when suctioning fluid and blood, preventing direct contact between the suction tube and brain, cranial nerves or vessels. Place the pad over the area and apply suction to the pad until dry.
iv) Packing a bleeding site to apply pressure. Wait approximately 3–4 minutes for bleeding to stop, then irrigate the packing with saline. The cotton expands and can be gently removed one piece at a time. If bleeding persists, use another method.
v) Covering Gelfoam while suction is applied to the cotton, drying the Gelfoam and helping it adhere to the bleeding surface.
Care is required when removing cottonoids covering nerves, vessels or brain, because these structures may tear. During suction, they can adhere to the fibers on the underside of the pad; repeated suction and prolonged placement increase this adherence. Lifting the cottonoid may then avulse them. I encountered this during acoustic neuroma surgery, in which cottonoids are routinely placed over cranial nerves IX, X and XI at the jugular foramen. Careless removal before wound closure tore one nerve filament; fortunately, the entire nerve was not severed. The correct method is to keep irrigating the pad while lifting it gradually. At any point of adherence, gently free the nerve, vessel or cortex from the cotton with a nerve root retractor to avoid injury.
Original printed pages 585–586
General methods of opening the skull
There are two methods, classified according to how the skull is opened:
i) Osteoplastic craniotomy creates a bone flap of the required size, depending on the size, location and type of tumor or lesion. Particular techniques for each location will be discussed later. After the brain operation, the bone flap is replaced, leaving no large skull defect. This method is used for supratentorial openings.
ii) Craniectomy removes bone to create an opening of the required size. Usually a burr hole is made first, then enlarged by cutting away surrounding bone. This is suitable for the posterior fossa. It may also be used supratentorially when only a small opening is needed. No bone flap is replaced after the brain operation, and a skull defect remains.
Original printed page 586
Osteoplastic craniotomy technique
The following principles apply to craniotomy at any location:
i) Center the opening over the tumor and make it as small as permits convenient removal. CT and MRI are particularly helpful. Limiting the opening to the necessary size saves time and reduces blood loss. It also limits the cortical area exposed to air, which may be damaged by drying during prolonged exposure.
ii) Always preserve the muscle attachment to the bone flap to maintain its blood supply. Otherwise the flap dies and behaves like a foreign body.
iii) For this reason, fracture the bone with the muscular pedicle of the flap always directed toward the skull base.
iv) Fracture the skull at a thin, narrow site where it breaks easily.
v) Avoid injury to the superior sagittal and transverse sinuses and to the proximal middle meningeal artery.
vi) Whatever the shape of the scalp incision, preserve the major vessels supplying the scalp flap.
vii) Always consider cosmetic results, particularly in frontal operations, without compromising access to the brain tumor.
Original printed pages 586–587
Scalp incision
A scalp incision for craniotomy is generally horseshoe-shaped, with its open end directed inferiorly toward the skull base to maintain a good blood supply to the flap. The pedicle must be sufficiently wide: the narrower it is, the greater the risk of ischemia. A straight or slightly curved incision may be suitable for a relatively small craniotomy.
AI-enhanced and colorized image · Switch to view the originalFigure 7.8 Major arteries supplying the scalp, which must be preserved when raising a scalp flap.
i) The superficial temporal artery, supplying the temporal and parietal regions and part of the frontal region.
ii) The supraorbital and supratrochlear arteries, supplying the frontal region.
iii) The greater occipital artery, supplying the occipital and posterior parietal regions.
A scalp flap must receive blood from at least one of these arteries; preserving two supplies is preferable whenever possible.
Original printed pages 587–590
Examples of scalp incisions (Figure 7.9)
Panel a shows an incision suitable for tumors of the temporal lobe, Sylvian fissure, middle cranial fossa and tentorium. Begin in front of the ear, behind the superficial temporal artery, to preserve the flap’s blood supply. The incision may need to extend to the upper border of the zygoma, but should not lie more than 2 cm anterior to the tragus, as this may sever the frontal branch of the facial nerve and impair frontalis function. Curve the incision posteriorly through the temporal region above the ear, then forward around the temple, ending behind the frontotemporal hairline.
AI-enhanced and colorized image · Switch to view the originalFigure 7.9 Examples of scalp incisions for craniotomy at different locations (a–g).AI-enhanced and colorized image · Switch to view the originalFigure 7.9 Examples of scalp incisions for craniotomy at different locations (h–i).
Panel b shows a horseshoe incision with its open end toward the skull base. It is suitable for tumors on the cerebral convexity and in paramedian regions, as in panel f. Note the good blood supply from the superficial temporal artery.
Panel c is suitable for tumors of the occipital lobe and tentorium. It may be extended inferiorly to expose both supratentorial and infratentorial compartments, using a craniotomy above and a craniectomy below the tentorium. The occipital artery provides a good blood supply to this flap.
In panel d, the anterior limb of the horseshoe lies in front of the ear. This incision is suitable for tumors of the posterior temporal region, lateral tentorium or posterior petrous bone.
Panel e shows a transcoronal incision along the coronal suture, extending from in front of one ear to the other. Keep it behind the frontal hairline for cosmetic reasons. In some cases it need only extend slightly across the midline, rather than all the way to the opposite ear—for example, with a narrow forehead or when subfrontal access is unnecessary. The flap remains supplied by the supraorbital, supratrochlear and superficial temporal arteries.
A transcoronal incision is suitable for a bifrontal bone flap, as shown in panel g.
Panel f shows a horseshoe incision crossing the midline, with its open end still directed toward the skull base. This is suitable for parasagittal tumors such as meningiomas, or midline tumors such as third ventricular tumors.
Panels h and i show straight scalp incisions, which bleed relatively little because they run parallel to the vessels. I prefer this approach when a large bone flap is unnecessary, since CT and MRI now show tumor location and size clearly enough to permit accurate incision placement.
Original printed pages 590–596
Opening the skull
After incising the scalp and controlling bleeding with arterial clamps or clips as described earlier in this chapter, separate the scalp in the loose areolar plane between the galea and pericranium and reflect it inferiorly. Place a rolled cloth beneath the flap to prevent folding and ischemia, and hold it in this position throughout the operation. A frontotemporoparietal craniotomy exposes the temporalis muscle and pericranium; an occipital craniotomy does not expose temporalis.
The steps are as follows:
Step 1. Divide the temporalis muscle with electrocautery along its fibers at both lower wound margins. Strip enough muscle from the skull to permit convenient burr-hole placement (Figure 7.10b). Control bleeding from muscle and bone, and remove the pericranium at each intended burr-hole site.
Step 2. Use a perforator to make approximately 4–6 holes, depending on the required flap size, spaced about 5–6 cm apart (Figure 7.10b). Usually five holes suffice: three superiorly and two inferiorly in the prepared temporalis regions over the temporal squama. When the perforator reaches the dura, it feels caught and becomes difficult to turn. Stop immediately, remove it and move to another site. Forcing it farther may penetrate the dura or brain, particularly through the thin temporal squama. Control bony bleeding with bone wax. Then enlarge each initial opening with a burr. Remove any inward-projecting bone at the lower rim with a rongeur. In a thin skull, this opening is sufficient to pass a dural guide between holes. A thick skull may require slightly wider holes to facilitate passage.
Burr holes can also be made with an electric or pneumatic drill (craniotome) (Figure 7.10). Its shoulder prevents penetration that could injure the brain. When the drill passes the inner table and reaches the dura, loss of resistance stops its rotation. The skull is then divided with a dural guide and Gigli saw, as described below.
Step 3. Use a rongeur to enlarge the two lowest temporal burr holes toward each other, leaving a narrow bridge of bone beneath temporalis that can be fractured easily. Cutting here may cause bleeding from branches of the middle meningeal artery. Use bipolar coagulation or temporarily pack with bone wax or a cottonoid. Definitive hemostasis is achieved after the skull is opened and the bleeding point is visible.
AI-enhanced and colorized image · Switch to view the originalFigure 7.10 Steps of osteoplastic craniotomy (a–e).AI-enhanced and colorized image · Switch to view the originalFigure 7.10 Steps of osteoplastic craniotomy. a. The incision line. b. Making burr holes with a perforator and burr. c. Enlarging the two temporal burr holes toward each other and inserting the dural guide with the Gigli saw. d. Sawing around the bone flap with the Gigli saw. e. Relationships of the dural guide, Gigli saw, dura and brain. f. Elevating the bone flap to fracture the temporal bone bridge. g. The dural incision line. h. Opening the dura with its hinge superiorly toward the vertex.
Step 4. Pass the dural guide with the Gigli saw from one hole to the next (Figure 7.10). The guide must lie between the dural surface and the inner table. Precautions are: i) If the perforator has torn the dura, the guide may enter the subdural space and injure brain or vessels. First separate the dura from bone with a curved dissector, then insert the guide. ii) In elderly patients or those with hyperostosis frontalis interna, frontal dura may adhere firmly to the inner table and tear during guide insertion. If passage from one hole is obstructed, try from the other or first separate the dura with a curved dissector. iii) Large arachnoid granulations often occur near the midline in the parietal parasagittal region. The guide may perforate the dura there and cause venous bleeding. If this happens, withdraw it and reinsert it obliquely downward, passing beyond the granulation before turning the tip toward the intended exit hole. This separates the dura and arachnoid granulation from the inner table. iv) When cutting across the midline, do not pass a dural guide from one side of the superior sagittal sinus to the other, because the sinus may tear.
Step 5. Detach the Gigli saw from the dural guide and saw the skull at an angle of approximately 45° to produce a beveled edge. This allows the replaced flap to rest securely against the skull margin without easily falling inward. After sawing around the flap, except at its base beneath temporalis, use a periosteal elevator to raise the upper edge (Figure 7.10f). Insert a dissector beneath the flap and separate the dura from its inner table. Fold the flap downward until the remaining bone bridge breaks. Before reflecting it downward, lift the bone flap first, then turn it down. Lift the bone flap first, then turn it down. This prevents the sharp fractured edge from pressing on and tearing the middle meningeal artery, dura or cortex. The temporalis muscle remains attached. Smooth the fractured edge, wrap the flap in cloth and secure it to the drapes.
A craniotome can create a flap of the required size and shape. First drill a burr hole in the prepared temporalis region, then replace the burr with a cutting head, consisting of a vertically rotating metal cutter with a dural guard beneath it. Insert the head into the hole and control the switch with the foot. Advance parallel to the skull while keeping the cutter perpendicular to it, continuing to the opposite burr hole. Then fracture the bone beneath temporalis. Where no muscle is attached, one burr hole may suffice: cut a circle of the required size, returning to the initial hole to free the flap.
The craniotome may tear the dura as it passes, particularly over hyperostotic frontal bone where the dura adheres firmly.
Step 6. Control bony bleeding with bone wax. Bleeding from the middle meningeal artery is controlled with bipolar coagulation or a suture ligature. Coagulate bleeding arachnoid granulations or cover them with Gelfoam and briefly apply a cotton pad until bleeding stops.
Step 7. Place dural hitch sutures around the skull margin, securing the dura to the surrounding galea or muscle to control epidural bleeding. Achieve hemostasis before opening the dura so that blood does not interfere with the brain operation.
Step 8. Before opening the dura, always assess whether intracranial pressure remains elevated. If so, lower it, for example by hyperventilation or by administering 200–300 cc of 20% mannitol over 10–15 minutes, then waiting until the dura becomes soft. When hydrocephalus is responsible, ventricular puncture and CSF removal immediately relax the brain. Open the dura only after pressure has been relieved. Opening it while pressure remains high causes brain protrusion and tearing, subarachnoid hemorrhage and further swelling, and should be avoided. Begin the incision frontally or temporally, about 1 cm from the skull edge. Lift the dura away from the cortex with a dural hook and make an approximately 0.5-cm incision with a pointed knife. Insert a dural groove beneath it and cut along the groove, which protects the cortex while the opening is enlarged. If this instrument is unavailable, place a small cotton pledget beneath the dura to protect the cortex and cut with scissors. Continue around the opening, leaving a hinge toward the superior sagittal sinus. Take particular care near the Sylvian fissure, where the dura is thicker and pushed inward by the lesser sphenoid wing. Inserting scissors may tear the Sylvian vein, with serious consequences; protect it carefully with cotton before cutting. Control middle meningeal arterial bleeding with a silver clip or suture ligature, and small bleeding points at the dural edge with bipolar coagulation. Leaving a 1-cm dural margin facilitates closure. If the dura is cut flush with the skull edge, subsequent shrinkage draws its margin beneath the bone and makes suturing difficult.
Original printed pages 596–598
Bifrontal craniotomy
A bifrontal craniotomy opens both frontal bones. It is used for a large midline frontal tumor extending into both frontal lobes, since a unilateral opening makes dissection on the opposite side difficult and dangerous. The general principles of craniotomy apply, with the following differences:
Step 1. Position the patient facing directly upward, with the head moderately extended so that gravity allows the frontal lobes to fall away and exposes the anterior cranial fossa. Make a transcoronal incision from one temple to the other behind the hairline. Reflect the scalp inferiorly until the superior orbital ridge can be seen or palpated. Opening as low as possible improves the view of a subfrontal tumor. Preserve the supraorbital nerve within the scalp flap, although accidental division has no adverse effect. Place a rolled cloth beneath the flap base to prevent folding and ischemia.
Step 2. Divide the right temporalis along its fibers near the junction of the zygoma, orbital rim and temporal fossa. On the left, if the opening does not reach the temporalis insertion, the muscle need not be divided. If the opening must extend to temporalis, divide it close to its fascial insertion at the frontotemporal ridge, leaving enough length for resuturing. Strip the muscle over the width required for the bone flap.
Incise the pericranium 2–3 cm from the orbital ridge so that it can later cover an opened frontal sinus.
Step 3. Make eight burr holes as shown in Figure 7.9g. Cut the bone above the orbital ridge as low as possible. A large frontal sinus may have to be crossed, but avoid it if possible. Remove the bridge between the holes on either side of the superior sagittal sinus with a rongeur to protect the sinus. Never pass a dural guide or Gigli saw between these two holes.
At the frontal sinus, the perforator first passes through the anterior wall. Use a fine-tipped rongeur or laminectomy rongeur to enlarge the anterior opening to the width of the perforator. The sinus mucosa may still be intact. The author prefers to separate it from the sinus wall and push it inferiorly with a cottonoid. Keeping it intact prevents infection from the nose. Then perforate the posterior wall and proceed as for the anterior wall.
Step 4. Divide the bone with a Gigli saw and lift the flap. Always dissect the superior sagittal sinus away from the inner table before lifting it. Fracture the temporal bone bridge, using temporalis as the hinge. Control bleeding from bone, dura and muscle as described above.
Step 5. If the frontal sinus has been opened, cut an appropriately sized piece of temporalis to cover the entire opening. Suture the prepared galea to the dura over the muscle as an additional layer, then close the skull.
Original printed pages 598–600
Closing the skull
After removing the tumor or lesion and securing hemostasis, proper closure is important. Some postoperative complications result from improper closure. Follow these steps (Figure 7.11)
Step 1. Close the dura. Place three or four initial sutures to restore its original shape. If it is taut, cut the initial hitch sutures to prevent tearing during approximation, and replace them after dural closure. Once the dura is adequately relaxed and can be tied without tearing, close it with closely spaced continuous sutures to obtain a watertight seal. Closely spaced interrupted sutures may also be used, but take longer.
If the dura has contracted so that its edges cannot be approximated, or if the brain is swollen, insert a temporalis fascia graft between the edges to reduce tension and cover the brain.
Step 2. Replace the bone flap. If bleeding persists despite bone wax, partially detach temporalis, leaving a small vascular attachment. This reduces blood flow from the muscle into the flap and helps prevent a postoperative epidural hematoma. Use a 2–3-mm drill to make corresponding holes in the skull and flap at three or four positions for secure fixation. The skull holes may pass through its full thickness, but protect the underlying brain. Limit the protruding drill bit to slightly more than the bone thickness to avoid penetrating the dura. The author prefers to drill a horizontal hole almost 1 cm deep into the diploic space, then drill through the outer table about 0.5 cm from the edge to intersect the first hole. Stop at the intersection to avoid penetration toward the brain. Drill full-thickness holes in the flap, together with two central holes for suspending the dura, reducing the epidural space and preventing expansion of a hematoma. Pass fine silver wire through each pair of corresponding holes. Pass a central dural suture through the two central flap holes. An epidural vacuum drain may be placed through a burr hole before closure. Replace the flap and twist the wires tightly. Trim their ends and tuck them into the holes to prevent skin puncture and late infection. Securely tie the central dural hitch suture. Resuture temporalis, replace the pericranium over the bone and close the scalp as described at the beginning of this chapter.
AI-enhanced and colorized image · Switch to view the originalFigure 7.11 Steps in closing the skull. a. Watertight continuous dural closure. b. Drill corresponding holes and pass the wire; suspend the dura at the center to secure it to the bone flap. c. Pass the wires through the prepared holes. d. Tighten each wire and tuck its ends into the holes, then close the scalp.
Original printed pages 600–609
Opening the posterior fossa
Suboccipital craniectomy provides access to tumors or lesions in the cerebellar hemisphere, vermis, fourth ventricle, brainstem, foramen magnum and cerebellopontine angle. The opening may be unilateral or bilateral, depending on the tumor site and size. The steps are as follows.
Step 1. Positioning is important, because the occipital bone is difficult to reach if the patient is incorrectly positioned, making posterior fossa exposure difficult.
Sitting position is the position the author most often prefers. Positioning is described at the beginning of this chapter. In particular, the head must be sufficiently flexed without kinking the endotracheal tube or causing venous obstruction. For a midline or cerebellar hemisphere tumor, flex the head directly forward without rotation. For a cerebellopontine angle tumor, slight rotation toward the tumor side may be necessary. Advantages of posterior fossa surgery in the sitting position are: i) the tumor is clearly visible at eye level, and table height can be adjusted as required; ii) venous bleeding is reduced because venous pressure is low; and iii) blood flows downward rather than pooling in the operative field. Disadvantages are: i) air embolism may occur; ii) hypotension; and iii) downward sagging of the cerebellum necessitates greater retraction.
Recumbent position is suitable for cerebellopontine angle tumors. Its advantages are: i) there is no need to fear air embolism or hypotension; and ii) less cerebellar hemisphere retraction is needed, since the cerebellum falls downward and facilitates access to the cerebellopontine angle. Disadvantages are: i) the surgeon must look downward unless using a microscope; and ii) blood pools in the operative field.
Step 2. Scalp incision. Usually make a midline incision from about 3–4 cm above the external occipital protuberance down to the C3–C4 spinous processes. Use electrocautery in the midline to divide connective tissue between the muscles on both sides and the fascia until the occipital bone and C1–C2 are visible. Detach the muscular attachments from each side of the occipital bone with electrocautery and a periosteal elevator, extending to both occipitomastoid sutures and the foramen magnum margin. A large mastoid emissary vein is present in the mastoid region; if divided, coagulate it and plug its bony opening with bone wax. During muscular dissection, bleeding may occur at individual points. Secure hemostasis before proceeding. Detach the muscle from the posterior arch of C1 no more than 1.5 cm laterally from the midline on each side; extending farther may injure the vertebral artery. After dissection, separate the muscles with a self-retaining retractor to expose the occipital bone and the entire atlas arch.
Hockey-stick and paramedial incisions are suitable for unilateral posterior fossa exposure, such as a cerebellar hemisphere or cerebellopontine angle tumor. As its name suggests, the hockey-stick incision resembles a hockey stick. Begin in the midline as described above, then extend obliquely laterally for about 5 cm at the level of the external occipital protuberance (Figure 7.12). Detach muscle from the ipsilateral occipital bone and posterior arch of C1 as described above.
AI-enhanced and colorized image · Switch to view the originalFigure 7.12 Incision lines for posterior fossa exposure. 1. midline incision 2. hockey stick incision 3. paramedial incision 4. paramedial hockey stick incision 5. external occipital protuberanceFigure 7.13 Suboccipital craniectomy. a. Making a skull opening with a perforator. b. Removing bone with a rongeur.
Step 3. Removing the skull bone. Make a burr hole on each side of the occipital bone (Figure 7.13). Enlarge each opening circumferentially until they meet in the midline. Extend laterally to the occipitomastoid sutures and superiorly until the transverse sinus is visible. In some patients, the bone near the external occipital protuberance and transverse sinus is too thick for a rongeur. If skull radiographs and CT show marked thickness here, before making burr holes and removing the occipital bone, use a perforator to make multiple closely spaced holes in the protuberance and other thickened areas to a depth of approximately two-thirds of the bone thickness. Removing the intervening bone leaves a thinner plate that can be removed with a rongeur. Do not drill these thick areas after craniectomy, because the perforator could slip and penetrate the brain. Inferiorly, remove the posterior margin of the foramen magnum to almost its full width. If removal of the posterior atlas arch is necessary, remove no more than 1.5 cm on each side, since extending farther could injure the vertebral artery. In a unilateral occipital opening, only the ipsilateral atlas arch may need removal. Alternatively, the occipital bone may be removed without opening the foramen magnum margin. Decide individually.
For a midline tumor, a large craniectomy is unnecessary. Determine the required dimensions from CT or MRI. CT is particularly useful in this respect. Previously, ventriculography and vertebral angiography localized a tumor but did not clearly show its shape and size, so a broad opening was necessary.
After removing the bone, apply bone wax to bleeding bone and coagulate all bleeding points on the dural surface.
Step 4. Opening the dura. Before every dural opening, assess whether the dura is bulging and tense from raised intracranial pressure. If so, remove CSF first. There are two methods. The first is ventriculostomy immediately above the lambdoid suture, 3–4 cm from the midline. Mark and prepare this incision site beforehand so it is ready for use. Inserting a tube into the occipital horn of the lateral ventricle allows CSF to drain. Continue drainage until the dura softens and the brain moves with respiration, then clamp the tube and open the dura safely. The author prefers frontal-horn ventriculostomy before positioning the patient, because it is easier to perform and manage postoperatively, and the head does not compress and kink the tube. The second method is to make a small opening in the dura and arachnoid over the cisterna magna, allowing CSF to drain until posterior fossa pressure decreases.
AI-enhanced and colorized image · Switch to view the originalFigure 7.14 a. Dural incision lines for posterior fossa surgery. The atlas arch may be removed. b. Exposure of both cerebellar hemispheres by ligating the lower dural corner and reflecting the dura upward. c. Exposure of one cerebellar hemisphere.
Always open the dura only when intracranial pressure is not elevated. The dura must be soft and relaxed, not tense, to avoid injury to the cerebellum and its vessels. Make a Y-shaped incision (Figure 7.14), beginning just below the transverse sinus at the two upper corners of the craniectomy and converging in the midline at the foramen magnum. An occipital dural sinus runs along the midline and may be large, causing bleeding when divided. Therefore, always suture-ligate this sinus at the lower dural corner (Figure 7.14b), then reflect the dural flap upward to expose the cerebellum. Continue the midline incision down to C1 and suture the lateral dura to muscle. In some cases, a transverse incision in this dural margin is needed before securing it to muscle, providing wider cerebellar exposure. Control dural sinus bleeding at the foramen magnum with a silver clip; bipolar coagulation may suffice elsewhere.
After a unilateral craniectomy, a single oblique dural incision followed by a transverse incision, with the dura retracted and sutured to muscle, exposes the ipsilateral cerebellar hemisphere and cerebellopontine angle.
Step 5. Locating the tumor. After opening the dura, always inspect the cerebellar hemispheres, vermis, tonsils, fourth ventricle, brainstem and cerebellopontine angle, because a tumor may lie outside the cerebellum and the cerebellum could otherwise be incised at the wrong site. The author witnessed such an error abroad when the surgeon carelessly omitted a complete posterior fossa inspection before incising the cerebellum. Clinical and radiological examination had shown a lime-sized tumor in the right posterior fossa. Exposure revealed an enlarged right cerebellar hemisphere and tonsillar herniation. Palpation of the cerebellar surface met resistance suggesting an underlying tumor, as did probing with a cannula. The surgeon incised the cerebellar hemisphere to a depth of about 3–4 cm and encountered a well-demarcated tumor. Attempted removal through the cerebellar hemisphere could not achieve complete excision and caused marked cerebellar swelling. The patient died postoperatively from brain swelling and hemorrhage around the residual tumor. Examination of the brain and tumor histology revealed a petrous ridge meningioma. The surgeon had omitted inspection of the cerebellopontine angle before incising the cerebellum and had improperly approached an extracerebellar tumor through the cerebellum. Inspection of the cerebellopontine angle would have allowed better planning.
With the remarkable ability of CT and MRI to show tumor site and size, such an error should now be rare, except when the surgeon truly lacks knowledge.
When a cerebellar hemisphere tumor is not visible on the surface, its site may be indicated by changes in the overlying folia, which become broader and paler. Abnormal vessels may be visible. Palpation may reveal resistance, or a cystic tumor may feel softer than the surrounding tissue. Probing with a cannula is another method. A vermian tumor may similarly broaden and pale the vermian folia and separate the supplying branches of the posterior inferior cerebellar artery.
Incise the cerebellar hemisphere horizontally, parallel to its folia. Always incise the vermis vertically in the midline. A horizontal incision may divide branches of the posterior inferior cerebellar artery and veins and gives poor exposure of the fourth ventricle. Coagulate small vermian vessels first, then divide and separate the vermis. The larger posterior inferior cerebellar artery branches at the junction of the vermis and cerebellar hemispheres remain intact.
For a fourth ventricular tumor or a vermian tumor projecting into that ventricle, separate the tonsils with a spatula to expose the lower fourth ventricle. To expose its upper part, divide the vermis vertically from posterior to anterior for the required distance.
Wider cerebellopontine angle exposure can be obtained by removing the lateral third of the cerebellar hemisphere, which does not add functional loss. Removing more may impair cerebellar function. Techniques for removing individual tumor types are described later.
Step 6. Closing the posterior fossa. This is an important step. Before closure, completely control bleeding from the tumor bed, dura and muscle surfaces dissected from bone. The posterior fossa contains the brainstem, and even a small hematoma may cause unconsciousness and respiratory arrest. A vacuum drain is generally not left in the posterior fossa.
There are two methods of closure: leaving the dura open, or suturing it closed as before.
For closure with the dura left open, approximate the muscles in the midline up to just above the foramen magnum. Suture the lower corner of the V-shaped dural flap, previously reflected upward, to the muscles on both sides in the midline. Secure its lateral edges to the undersurface of the muscles with interrupted sutures so that the flap continues to cover the cerebellum. Leave the dura at the craniectomy margin and atlas attached to muscle as previously sutured. Continue approximating the muscles throughout, then suture the fascia and galea and close the skin. A disadvantage is formation of a CSF collection beneath the muscles, termed a pseudomeningocele. It may bulge posteriorly when hydrocephalus develops. Over time, the uncovered cerebellar hemisphere adheres firmly to muscle, making separation difficult at another operation. Blood from muscle surfaces may also enter the subarachnoid space. A vacuum drain cannot be used because the cerebellar surface is not covered by dura. The advantage is decompression of the posterior fossa and relief of medullary compression in patients with tonsillar herniation.
Closure with the dura sutured is suitable when, after the operative work, there is no evidence of raised posterior fossa pressure or cerebellar swelling, or after a small or unilateral craniectomy. Cut the sutures securing the dura to muscle around the craniectomy, then reapproximate the original dural incision. Sometimes the dura can be closed without tearing or excessive tension. If it is tight, harvest a neck muscle fascia or galeal graft and close the dura with a watertight continuous suture. The graft relieves tension. Then suspend the dural margins from muscle around the craniectomy. Place a central dural suture and secure it to muscle to eliminate the epidural space and prevent a large epidural hematoma. Close muscle and fascia in the midline, then close the skin in two layers. This preserves dural coverage of the cerebellum, prevents pseudomeningocele and permits placement of an epidural vacuum drain if desired.
Original printed pages 609–610
Ventriculostomy
Ventriculostomy creates a communication with a ventricle so that CSF can flow elsewhere or outside the body, reducing CSF pressure. It is used in patients with obstructive hydrocephalus, or to introduce radiopaque media or air to investigate lesions within or near a ventricle. Injection of radiopaque media is no longer performed, since CT and MRI are more useful.
Ventriculostomy is generally performed through a frontal or occipital site. Occasionally a parietal site, as used for a ventriculoatrial shunt, may be necessary.
Original printed pages 610–612
Frontal ventriculostomy
The procedure may be performed under local or general anesthesia. Position the patient supine, facing directly upward, and secure the head with adhesive tape. Even slight rotation may cause an inaccurate ventricular puncture. After preparing the scalp, mark an approximately 3-cm incision just anterior to the coronal suture, which is palpable in some patients, about 2–2.5 cm from the skull midline. Ventricular cannulation is easier here than farther laterally. After sterile draping, incise along the mark and separate the scalp with a mastoid self-retaining retractor. Strip the pericranium with a periosteal elevator and make an exploratory burr hole. Control skull and dural bleeding with bone wax and bipolar coagulation. Make a cruciate dural incision with a pointed knife to expose the cortex. Incise an area without large vessels, making the opening only as wide as the cannula. Insert the cannula with its stylet toward the ventricle, perpendicular to the skull when the ventricle is large, or inclined slightly medially when it is not markedly enlarged (Figure 7.15). When the tip penetrates the ventricular wall, loss of resistance and CSF return are felt and seen. Stop advancing the cannula. Do not allow CSF to spurt out rapidly under pressure; let it drip slowly. Rapid reduction of intracranial pressure may shift the brain, causing upward cerebellar herniation and brainstem dysfunction. A No. 8 stomach tube may be used for CSF drainage. Tie a thread around it 10 cm from its tip as a depth marker during intracerebral placement. After sufficient CSF has drained and its pressure has returned to normal, withdraw the cannula and introduce the prepared tube along the cannula tract until CSF flows through it. Do not insert the tube through brain into the ventricle while intracranial pressure is high: its end and side openings may cut off pieces of brain that block the tube and prevent CSF flow. Once the tip is correctly positioned, cover the dura with Gelfoam, close the wound and secure the tube. It may be tunneled beneath the scalp to exit away from the incision. Connect it to a sterile bottle. Crucially, position the bottle so that the open end of the tube within it is about 10–12 cm above the foramen of Monro, corresponding to normal ventricular pressure. CSF drains into the bottle when pressure exceeds 10–12 cm CSF and stops when it falls to 10–12 cm. Drainage starts and stops automatically as long as the tube remains patent. Once the bottle and head levels are set, avoid changing either, to maintain the desired intracranial pressure. Reset the level whenever their positions change. Never lower the bottle below the head, because continuous drainage would cause intracranial hypotension. Always clamp the tube temporarily when moving the patient, then reset its level and reopen it.
AI-enhanced and colorized image · Switch to view the originalFigure 7.15 Frontal ventriculostomy. a. Burr-hole site. b and c. Trajectory into the frontal horn.
A ventriculostomy may be maintained for no more than seven days. If it remains necessary, change to a new site on the opposite side. Leaving it longer risks wound and CSF infection. In general, a ventriculoatrial or ventriculoperitoneal shunt is preferable for prolonged CSF drainage.
Original printed pages 612–613
Occipital ventriculostomy
This may be performed with the patient sitting or prone, but is most often done in the sitting position during posterior fossa exposure. Place the burr hole adjacent to the palpable lambdoid suture, 3–4 cm from the midline. Alternatively, place it 7–8 cm above the external occipital protuberance (Figure 7.16). Make the burr hole and open the dura as described above. Direct the cannula toward the ipsilateral medial canthus to enter the occipital horn of the lateral ventricle. Once the ventricle is entered, proceed as for frontal ventriculostomy.
AI-enhanced and colorized image · Switch to view the originalFigure 7.16 Occipital ventriculostomy. a. Burr-hole site. b and c. Trajectory into the posterior horn.
Original printed pages 613–615
Trephination
This is another method of opening the skull, using a rotating circular saw to remove a bone disk corresponding to the trephine diameter, which ranges from 3 to 5 cm. It is therefore suitable for a small skull opening when extensive brain exposure is unnecessary. A central pin holds the trephine in position as it rotates through the skull.
Figure 7.17 Trephination. a. Trephine with its central pin and saw teeth. b. Rotating the trephine to cut the skull. c. Elevating the bone disk. d. Opening the dura.
Open the scalp sufficiently for the selected trephine, and retract the scalp and pericranium with a self-retaining retractor. Attach the trephine to a Hudson brace. Adjust the central pin to project about 2–3 mm beyond the saw teeth and set the guard to limit the cutting depth. Rock and press the trephine until the pin grips the bone, stabilizing it. Then rotate the trephine (Figure 7.17). The teeth gradually cut down to the inner table. Since skull thickness may not be uniform, observe whether one side has been cut more deeply and tilt the trephine to deepen the cut where required. Avoid cutting deeply enough to tear the dura. The external guard, set to the skull thickness, prevents the trephine from plunging inward. Once the bone has been divided, use a periosteal elevator to lift the disk (Figure 7.17). Secure hemostasis in bone and dura before proceeding with brain surgery. For closure, replace the disk, secure it with silver wire and close the scalp in layers.
Original printed pages 615–616
Treatment of individual brain tumor types (Specific management of individual brain tumors)
As discussed in the pathology chapter, many types of tumor occur in the brain, including primary tumors and metastases from elsewhere. Each has a different natural history. Some are malignant, growing and impairing brain function rapidly; others are benign and grow slowly. Treatment therefore differs among tumor types. Tumor site and size are also important considerations in surgical treatment. Even benign tumors require different treatments and operative approaches when they involve vital brain centers.
Surgical treatment has three main objectives:
i) Complete removal when the tumor is accessible and removal will not cause loss of brain function or life.
ii) Obtaining tumor tissue for histological identification to guide the choice of other treatments in conjunction with surgery.
iii) When complete removal is impossible, reducing tumor size to relieve local and generalized intracranial pressure and improve symptoms for a time.
When tissue cannot be obtained to identify the tumor, whether radiotherapy should be given may be debated. The author believes that the tumor site and appearance on skull radiographs, CT and MRI, together with the patient’s age and clinical syndrome, should be considered. Previous experience with the characteristic age distribution, location, CT appearance and radiosensitivity of each tumor type can support radiotherapy in selected cases. Nevertheless, if the tumor can be approached without a major risk of loss of brain function, or the patient is fit enough for surgery, tissue should be obtained for identification in every case, for three reasons:
i) To support the clinical and radiological diagnosis.
ii) To compile accurate statistics on tumor types.
iii) To provide a sound basis for radiotherapy when the tumor is known to be radiosensitive, with benefit through shrinkage or disappearance.
The surgical approach must take account of the tumor’s site, size, extent, vascularity, histology and radiosensitivity, as well as the patient’s neurological and general condition.
Individual tumor types at their various sites and the corresponding operative techniques are described in detail below.
Original printed pages 616–617
Tumors of neuroglial cells
Tumors arising from the various neuroglial cells—astrocytes, oligodendrocytes, microglia and ependymal cells—are collectively called gliomas. They are the most common brain tumors, accounting for 40–45% of all brain tumors(28). Because they arise within brain tissue and infiltrate without clear boundaries, complete surgical removal is difficult. Although modern techniques and instruments permit earlier diagnosis and easier removal, they still cannot cure the disease; surgery only prolongs postoperative survival. No method can distinguish the full extent of these tumor cells from normal brain, even with an operating microscope. Gliomas can therefore be treated but are usually not cured.
Surgical treatment of gliomas generally offers three alternatives:
Original printed pages 617–618
Method 1: Craniotomy with removal of the tumor alone
The tumor is excised or aspirated without lobectomy. Success depends on removing it without adding to the patient’s pre-existing neurological deficits, which is difficult for the surgeon. New instruments, including the operating microscope, carbon dioxide laser, ultrasonic aspirator and bipolar coagulator, make removal easier, even for large tumors, while reducing injury to healthy brain. The surgeon should always stop resection on reaching functionally important brain tissue. In addition to removing as much tumor as possible, this operation immediately reduces intracranial pressure, as shown by relaxation of the brain after removal. The patient may then experience a further period without focal symptoms or symptoms of raised intracranial pressure. In general, prolonged survival after glioma surgery correlates with the extent of resection. This method usually leaves some tumor behind, which later gives rise to recurrence.
There are two reasons for attempting the most complete removal possible. i) In some patients and locations, a glioma is not markedly infiltrative and its boundary can be identified. Hemiparesis or dysphasia may result from compression and associated local edema. Radical removal should therefore permit functional recovery and longer survival than limited removal. ii) If the tumor has infiltrated functionally important brain tissue, that tissue has already been destroyed and rendered nonfunctional. Resection within the visible tumor boundary should therefore not add neurological deficits, while reducing local pressure and intracranial pressure. Nevertheless, radical resection remains impossible in some patients.
The removal technique is described in the illustrative cases that follow.
Original printed page 618
Method 2: Lobectomy
This removes the tumor together with a margin of healthy brain beyond its boundary, in the hope of complete excision. It is suitable for gliomas at the frontal, temporal and occipital poles, which can be removed without loss of brain functions important for daily living. Some sites may incur functional loss, but not disabling impairment; for example, occipital lobe removal causes homonymous hemianopia.
From experience with this method, gliomas can still recur. Some tumors are not truly confined to the pole but infiltrate widely toward important areas, such as Broca’s and motor areas, or, in the temporal lobe, toward the Sylvian fissure or insula. These extensions limit resection. Even when CT shows a well-defined mass, histology reveals tumor cells extending beyond its macroscopic margin into surrounding brain, where they subsequently grow into another mass. This operation prolongs survival.
Original printed pages 618–622
2.1 Frontal lobectomy
This procedure is suitable for gliomas in the frontal pole, particularly unilateral tumors in the non-dominant hemisphere. It can also be performed in the dominant hemisphere.
Technique. Place the patient supine, with the face turned approximately 15–20° away from the side of the tumor. Make a transcoronal incision behind the anterior hairline to conceal the scar. On the side of the craniotomy, extend the incision down to the superior border of the zygoma, no more than 2 cm anterior to the tragus, to avoid injuring the frontal branch of the facial nerve. Dissect and reflect the scalp flap anteriorly to expose the frontal bone, orbital ridge, and temporalis muscle. Make a craniotomy with its anterior edge close to the orbital ridge to provide easy access to the frontal pole. Place its medial edge approximately 1–1.5 cm from the midline, its posterior edge slightly behind the coronal suture (approximately 1 cm), and its inferior edge at the level of the squamosal suture of the temporal bone. This exposes the anterior Sylvian fissure, which helps identify the positions and relationships of the various structures.
After opening the skull, if the dura is tense, institute hyperventilation or administer 300 cc of 20% mannitol intravenously over 10–15 minutes. Once intracranial pressure has decreased and the dura is relaxed, open the dura with its flap based adjacent to the superior sagittal sinus. This opening exposes the superior, middle, and inferior frontal gyri. In the dominant hemisphere, the posterior third of the inferior frontal gyrus contains Broca's motor speech center, which must be preserved and not injured. The anterior temporal lobe, Sylvian fissure, and lesser wing of the sphenoid are also visible.
Resection of brain tissue. In a normal brain without hydrocephalus, resection of the frontal lobe along a vertical line extending upward from the anterior tip of the temporal lobe, or from the edge of the lesser wing of the sphenoid, generally does not enter the anterior horn of the lateral ventricle (Figure 7.18). Frontal lobectomy should therefore be performed transversely along this line or anterior to it, as appropriate. Resection may begin in the cortex of the inferior frontal gyrus, using bipolar cautery to coagulate the vessels and scissors to divide them. Then use suction to remove the brain tissue transversely, proceeding from the inferior to the middle and superior frontal gyri and deepening the resection uniformly to maintain a broad view. Use a spatula to retract the part of the frontal lobe to be removed. Avoid touching or retracting the brain that is to be preserved, as this may cause further damage. During suction resection, vessels may be drawn up with the tissue; coagulate and divide them. Preserve the major branches of the cortical veins draining into the sagittal sinus with the brain that is to remain, to avoid cerebral swelling. Divide cortical veins close to the cortex, rather than near the superior sagittal sinus. As suction resection proceeds deeper, direct it toward the base of the frontal lobe. If the anterior part of the frontal horn is entered, cover the opening carefully with a cottonoid to prevent blood entering the ventricle. Remove the cottonoid at the end of the operation and plug the opening with Gelfoam. Medially, keep the frontal lobe resection anterior to the genu of the corpus callosum and the anterior cerebral artery. Coagulate or clip and divide the ipsilateral frontopolar artery running along the medial frontal lobe. When resecting the inferior frontal gyrus, avoid injuring the Sylvian vessels by keeping the resection anterior to the Sylvian fissure throughout. At the base of the frontal lobe, the olfactory nerve and bulb and the vessels running along the nerve will be seen. Try to preserve these structures, both to prevent CSF leakage through the cribriform plate and to preserve the sense of smell. Coagulate and divide the veins and arteries adjacent to the pia-arachnoid at the frontal base; the frontal pole can then be removed. If the tumor extends posterior to the resection plane, remove as much as possible with suction without damaging functionally important brain tissue. Before closing the dura, irrigate and secure complete hemostasis. Cover the cut surface of the remaining frontal lobe with Gelfoam and close the dura tightly. Before placing the final stitch, fill the cavity with saline to expel all air, to prevent postoperative headache.
Image enhanced and colorized with AI · Switch to view the original imageFigure 7.18 Left frontal lobectomy for a glioma in the prefrontal area. Note preservation of Broca's center, the anterior cerebral artery, the genu of the corpus callosum, and the anterior part of the frontal horn.
Disadvantages of frontal lobectomy. Generally, this procedure does not cause an obvious loss of cerebral function such as hemiparesis or dysphasia, because the motor speech area and motor area are not damaged. However, patients may become slow in thinking, lack interest in activities, or tend to remain inactive. These changes are especially noticeable after surgery on the dominant hemisphere. Some patients may have impaired recent memory.(29)
Original printed pages 622–624
2.2 Temporal lobectomy
This procedure is suitable for gliomas in the temporal pole and may be performed in either the dominant or non-dominant hemisphere.
Technique. Place the patient supine with the face turned to the opposite side. Elevate the shoulder on the operative side with a sandbag to avoid excessive neck rotation, which may cause venous obstruction in the neck. After skin preparation and draping, make a question-mark incision starting 1.5 cm anterior to the tragus, above the superior border of the zygoma, curving posteriorly above the ear and then forward (Figure 7.9). This incision preserves the frontal branch of the facial nerve and the superficial temporal artery. Make the craniotomy as low in the temporal fossa as possible, leaving the temporalis muscle attached to the bone flap. After opening the skull, remove the squamous temporal bone down to the floor of the temporal fossa. If bleeding occurs from the middle meningeal artery, control it by suture ligation. Then open the dura, beginning in the temporal region, with the dural flap based toward the vertex.
Resection of brain tissue. After opening the dura, the Sylvian fissure, superior and middle temporal gyri, and part of the inferior temporal gyrus are visible. Most of the inferior temporal gyrus lies on the inferior surface of the temporal lobe. The tip of the temporal lobe is hidden beneath the lesser wing of the sphenoid. The temporal lobe may be resected to a maximum of approximately 5–6 cm posterior to its anterior edge without loss of functions essential to daily living. Remember that approximately 2 cm of the anterior temporal tip lies beneath the lesser wing and must be included in this measurement. In addition to measuring distance, a reliable anatomical landmark can guide the resection: the junction of the Rolandic and Sylvian fissures. Temporal lobe resection must always remain anterior to this point. Resection of the superior and middle temporal gyri posterior to it in the dominant hemisphere would remove part of Wernicke's sensory speech center. The inferior anastomotic vein of Labbé can be an unreliable landmark because its position varies.
Use suction and a bipolar coagulator for the resection. Begin along the length of the superior temporal gyrus, from anterior to posterior, stopping just anterior to the junction of the Rolandic and Sylvian fissures and remaining approximately 1 cm from the Sylvian fissure. Throughout the resection, avoid entering the Sylvian fissure or insular cortex (Figure 7.19). Do not cut through the pia-arachnoid separating the insula and middle cerebral artery, as injury to the artery or its branches may cause postoperative hemiparesis. Coagulate and divide the branches of the middle cerebral artery crossing to supply the temporal lobe. When the superior temporal gyrus has been resected to the planned posterior limit, continue transversely downward through the middle and inferior temporal gyri, again using suction and bipolar coagulation, toward the floor of the middle fossa. Near the temporal horn, avoid opening it because this may lead to postoperative complications such as a tension cyst. If the temporal horn is entered, plug the opening securely with Gelfoam. If a large draining vein is encountered, preserve it until the final stage before dividing it, to avoid cerebral swelling during surgery. The uncus and parahippocampal gyrus on the medial side of the temporal lobe may also be resected if infiltrated by tumor. Leave some of the medial surface of the uncus to protect the optic tract. During surgery in this region, avoid injury to the oculomotor nerve and posterior cerebral artery, which lie medial to the uncus and parahippocampal gyrus.
Image enhanced and colorized with AI · Switch to view the original imageFigure 7.19 Temporal lobectomy for a glioma in the anterior temporal lobe, showing the resection line.
Sequelae of temporal lobectomy. Homonymous superior quadrantanopia is commonly encountered. It may involve part or all of the quadrant, depending on the extent of resection. In patients with temporal lobe gliomas, this deficit may already be present before surgery.
Original printed pages 624–625
2.3 Occipital lobectomy
This procedure is suitable for gliomas in the occipital lobe. It may be performed with the patient sitting or recumbent. In the recumbent position, place the patient semiprone or on the side, with the operative side uppermost, the face directed toward the floor, and the occiput uppermost. After skin preparation, make an inverted U-shaped incision to preserve the occipital artery and nerve. Make a craniotomy with its medial edge approximately 1.5 cm from the midline. At its lower edge, make 2 burr holes approximately 1.5 cm above the transverse sinus, then cut the bone obliquely downward toward each other, crossing the transverse sinus. The remaining bone is fractured when the bone flap is elevated. Open the dura approximately 1.5 cm above the transverse sinus, with the flap based beside the superior sagittal sinus.
In the non-dominant hemisphere, occipital lobe resection may begin approximately 6 cm from the occipital pole. In the dominant hemisphere, no more than 4 cm should be removed to avoid damaging the angular gyrus, which forms part of the sensory speech center. Resect the brain in the same manner as for frontal lobectomy, using suction and bipolar coagulation. Medially, branches of the posterior cerebral artery supplying the occipital lobe will be encountered; coagulate or clip and divide them. After completing the parenchymal resection, coagulate or clip the cortical veins draining into the transverse sinus, torcula Herophili, and superior sagittal sinus. The occipital pole can then be removed. As with lobectomy elsewhere, take care not to enter the occipital horn.
Functional loss after occipital lobectomy. If occipital lobectomy is performed correctly, the only visual field loss will be contralateral homonymous hemianopia. However, if resection in the dominant hemisphere extends too far anteriorly, nearly to the junction of the occipital, parietal, and temporal lobes, it will impair reading (dyslexia), writing (dysgraphia), and calculation (dyscalculia). If Wernicke's area is resected, the patient will have sensory dysphasia.
Original printed pages 625–626
Method 3: Biopsy
Biopsy obtains tumor tissue for identification of its type, helping guide the use of additional treatments such as radiotherapy. It is suitable for deep tumors in critical locations, such as the thalamus, basal ganglia, or near the third ventricle. Attempting to remove an entire tumor in these areas would be dangerous and cause further functional loss. Either needle biopsy or open biopsy may be used. CT and stereotaxis are now used to guide the needle accurately into the tumor(30,31) A needle biopsy from only one site may not reliably establish the nature of the tumor, because different parts of a glioma may show different degrees of malignancy. The periphery is usually less malignant than the central region. CT guidance overcomes this problem by allowing samples to be taken from several sites. Nevertheless, the procedure can cause intratumoral hemorrhage that cannot be controlled immediately, and the patient may deteriorate.
Open biopsy involves craniotomy and exposure of the tumor, followed by removal of a portion large enough for histological examination. This allows the surgeon to inspect the tumor directly and, in some cases, recognize its type. It also permits control of bleeding caused by the biopsy.
None of the 3 surgical methods for gliomas described above is ideal, because they cannot yet cure the disease. Additional treatment, including radiotherapy and chemotherapy, which remains experimental, is still needed to prolong survival. Treatment of gliomas must therefore be individualized to determine the best method for each patient, considering the location and natural history of the particular tumor type, as discussed below. An account of the natural history of each tumor is consequently needed to explain its treatment.
Original printed pages 626–629
ASTROCYTOMA
Astrocytoma is a brain tumor arising from astrocytic cells. It grows by infiltration and lacks a clearly defined boundary. It accounts for approximately half of all gliomas. Within the cerebral hemispheres, astrocytomas occur most frequently in the frontal lobe, followed by the temporal and parietal lobes; the occipital lobe is rarely affected. Most occur in middle age, with a peak incidence at approximately 34–45 years(32)
Astrocytomas may also arise in the thalamus, hypothalamus, optic nerve, chiasm, brain stem, and cerebellum. Tumors at the last 5 sites are common in children and will be discussed separately by location. Cerebellar astrocytoma has a better prognosis than cerebral hemispheric astrocytoma because it often consists of a large cyst with a small mural nodule in its wall. Removal of the mural nodule may cure the patient.
Some astrocytomas arise near the genu of the corpus callosum and extend into the frontal lobe and cingulate gyrus on the same side or on both sides. Psychiatric symptoms may be the initial presentation.
Astrocytomas may be subdivided according to the predominant tumor cell type into fibrillary, protoplasmic, and gemistocytic astrocytomas. Each has characteristic cell shape, cytoplasm, and astrocytic fibrils (see the pathology chapter). They have also been classified by degree of malignancy. Kernohan(33) divided astrocytomas into 4 grades: grade 1 is the most benign; grade 2 corresponds to anaplastic astrocytoma in the WHO classification(34) and has greater malignancy; grades 3 and 4 are the most malignant, termed glioblastoma multiforme or poorly differentiated glioma.
Fibrillary astrocytoma is the most common benign form among tumors of the various astrocytic cell types. In the cerebral hemispheres, however, it is less common than glioblastoma multiforme(35) Hemispheric astrocytomas may sometimes develop a cyst (Figure 7.23). The cyst contains straw-colored fluid and contributes substantially to raised intracranial pressure and focal neurological deficits. Surgical drainage of the cyst can greatly improve neurological symptoms. It is a palliative treatment for tumors in locations where complete removal is not possible.
Because astrocytoma is a benign tumor, metastasis or spread through the cerebrospinal fluid pathways has not been observed. Recurrence after the first operation is nevertheless common because the tumor infiltrates critical brain regions, such as the motor area, thalamus, and hypothalamus. Extensive resection along this infiltration is not possible without loss of brain function or life. The tumor may therefore be considered malignant by location, since it cannot be completely removed.
Symptoms and signs. Regardless of its cell type, astrocytoma produces the 2 main groups of symptoms described above: general symptoms of raised intracranial pressure and focal symptoms corresponding to its location in the brain. These symptoms do not identify the tumor type. However, the speed with which symptoms and signs develop may help indicate whether the tumor is malignant or benign.
Focal symptoms may be irritative, destructive, or a combination of both. Astrocytoma most often presents with seizures, which may be focal, Jacksonian, or generalized. Temporal lobe tumors may cause uncinate fits or psychomotor epilepsy. Seizures are common when the tumor is in or near the motor cortex, and a history of seizures often precedes diagnosis by years, generally 1–2 years. Diagnosis is now made earlier because CT and MRI are highly effective investigations, prompting physicians to refer patients with these symptoms for imaging at an early stage. Deficits such as limb weakness do not develop as rapidly as in glioblastoma multiforme, because the benign tumor grows slowly by infiltration. In some cases CT clearly shows an extensive area of low density due to astrocytoma, yet with very little mass effect.
Symptoms of raised intracranial pressure—headache, vomiting, and blurred vision—are less common than in malignant glioma or glioblastoma multiforme. This is illustrated by CT showing a large low-density astrocytoma without midline shift (Figure 6.96).
Cerebellar astrocytoma is benign, occurs predominantly in children, and commonly involves a cerebellar hemisphere. Patients therefore have ipsilateral cerebellar signs: ipsilateral ataxia, dysmetria, dysdiadochokinesia, hypotonia, and nystagmus. Symptoms of raised intracranial pressure subsequently develop as the fourth ventricle is compressed and obstructed.
Astrocytomas of the brain stem, hypothalamus, optic nerve, and chiasm will be discussed under their respective headings.
Original printed page 629
Diagnosis
In addition to taking the history and examining for the signs described above, special radiological investigations help establish an accurate diagnosis.
1. MRI is currently the best investigation, clearly demonstrating the extent of the tumor even when it is poorly visualized on CT. For example, if the tumor is only slightly hypodense or nearly isodense with brain tissue on CT, MRI demonstrates it better.
2. CT scanning is another accurate diagnostic method, but is inferior to MRI for low-grade astrocytoma. The tumor appears as a low-density area and is not better visualized after contrast enhancement, whereas MRI shows it more clearly.
3. Skull radiographs may show small clusters of calcification scattered throughout the tumor. Raised intracranial pressure may cause changes in the sella turcica or separation of the cranial sutures; these latter changes are not specific to astrocytoma.
4. Cerebral angiography shows an avascular region at the tumor site, without a tumor blood supply; only displacement of nearby vessels is seen. This differs from glioblastoma multiforme, which has numerous newly formed, abnormal vessels supplying the tumor.
Original printed pages 629–630
Treatment
As already stated, astrocytomas or gliomas are treatable, but most cannot be cured because there is still no ideal method of removing all the tumor without destroying function in the brain it has infiltrated. Treatment is therefore directed toward relieving symptoms and providing a period of better quality of life or minimal disability. Attempts at complete removal are generally difficult to accomplish and often cause immediate deficits such as hemiplegia, aphasia, or hemianesthesia, imposing suffering on both the patient and family. The surgeon should bear this in mind and exercise judgment during the operation about when to stop, so as to avoid further loss of brain function, and then use other treatments.
Original printed pages 630–639
Surgical treatment of cerebral hemispheric astrocytoma
The method of tumor removal must be planned according to its location, size, and characteristics (solid, cystic, anaplastic, and vascularity). In general, the 3 surgical options for glioma are those described above. At present, the author prefers direct tumor resection because excellent surgical instruments are available. Lobectomy is now very rarely performed, except when the tumor lies at the pole of a lobe, cannot be completely removed, and raised intracranial pressure persists. In that situation, a lobectomy is needed to reduce intracranial pressure and prolong survival.
Osteoplastic craniotomy for this tumor is performed in the usual manner described at the beginning of the chapter. The opening should be wide enough to show the cortical anatomy. Before opening the dura, assess whether it is tense from raised intracranial pressure. If so, first reduce the pressure by hyperventilation or 20% mannitol at 1 g/kg body weight, approximately 200–300 cc for an adult. Wait until the dura relaxes before opening it. Opening the dura while the pressure is high causes cerebral herniation and may rupture or tear the brain.
After opening the dura, inspect the cortex for changes. In some cases the tumor is clearly visible at the surface (Figure 7.21). The affected gyri are enlarged and pale yellowish, unlike normal cortex. Displacement of vessels and normal cortex is readily apparent. In some cases a cyst containing straw-colored fluid is visible at the brain surface (Figure 7.23)
When a glioma lies beneath the cortex (subcortically), cortical changes may or may not be apparent, depending on the size and depth of the tumor. A superficial tumor broadens and pales the overlying cortex. Also inspect the cortical veins. In glioblastoma multiforme or malignant glioma, some cortical veins may be enlarged and contain arterialized blood (Figure 7.28A). This indicates shunting of arterial blood within the malignant tumor. Gently palpating the cortex with a wet index finger (never a dry finger, which may cause subpial hemorrhage), together with reviewing the CT and angiogram, helps localize the tumor. A non-cystic tumor may feel firm, whereas a cystic tumor feels soft. Seek the softest area, corresponding to the part of the cyst nearest the brain surface. Make a small cortical incision of approximately 2–3 mm and pass a cannula through the cortex toward the tumor. Resistance will be felt when the cannula enters solid tumor. If it enters a cyst, resistance disappears and straw-colored fluid is obtained.
Real-time ultrasonography is now used during brain surgery to identify the location and extent of a tumor(36,37,38), enabling accurate access to subcortical tumors and increasing the surgeon's confidence.
When opening the cortex to reach the tumor, choose the point where it lies closest to the surface, guided by cortical changes and the feel of the cannula as it reaches the tumor. Avoid incising clinically important cortex, such as the motor and speech areas. However, if the tumor is at the surface of the motor cortex and that cortex is very thin, an incision may be made there because its function has already been lost. The important point is to make the incision transverse to the length of the precentral gyrus or motor cortex. Do not incise longitudinally along the motor cortex, as this would extend the loss of motor function (Figure 7.20)
Since the introduction of loupes and microscopes for brain tumor surgery, a long cortical incision has become unnecessary; 2–3 cm is sufficient. Illumination from a coaxial headlight and the microscope gives a clear, broad view at depth and permits tumor removal. Once the cortex has been opened to the tumor, use a self-retaining brain retractor on both sides to improve the view and free both of the surgeon's hands. Resect only tissue that looks different from normal brain: tumor is grayish with a pink tinge and is usually easily removed by suction. The following cases illustrate the method of removal.
Image enhanced and colorized with AI · Switch to view the original imageFigure 7.20 Cortical incision for a tumor beneath the motor cortex. A. An incision transverse to the motor cortex, preserving major branches of the middle cerebral artery, sacrifices less motor cortex. B. An incision along the length of the motor cortex sacrifices more motor cortex.
Case 1: Parasagittal glioma of the posterior frontal lobe adjacent to the motor cortex. A 36-year-old patient first had clonic seizures of the left leg approximately 1 year earlier and received anticonvulsants at a provincial hospital. There were another 3–4 seizures over the next 6 months. Six months before admission, the patient began to have headaches without vomiting or blurred vision; analgesics relieved the pain. Three months before admission, mild left leg weakness appeared and gradually progressed. On the day of admission, a seizure began in the left leg and became generalized. Afterwards, the patient could not move the left leg for several hours. Examination showed mild spastic monoparesis of the left leg. A brain tumor in the leg area of the right motor cortex was diagnosed. Right carotid angiography showed an avascular parasagittal tumor in the posterior frontal lobe. At surgery, opening the dura revealed a tumor on the surface of the posterior superior frontal convolution, adjacent to the motor cortex (Figure 7.21). The cortex was widened and pale yellowish. The tumor had a very sparse blood supply compared with the vessels of the normal cortex, a characteristic appearance of astrocytoma. Displacement of the cortical vein was obvious. From its surface the tumor appeared circumscribed, but its deep portion might lack a defined boundary. The motor cortex was clearly infiltrated in some areas and compressed in others, explaining the seizures and weakness of the left leg.
Figure 7.21 Operative photograph of a glioma in the superior frontal convolution adjacent to the right motor cortex.
In this patient, surgery had to be planned to remove only the tumor and protect 3 structures: 1) the motor cortex; 2) the cortical vein, which is particularly important in this region, as tearing it may cause cerebral swelling and death; and 3) the anterior cerebral artery and its branches above the corpus callosum and cingulate gyrus, which also supply the tumor.
Tumor resection. This portion of the superior frontal gyrus had been destroyed by the tumor and had lost all function; its removal would therefore cause no further deficit. Begin by coagulating and dividing small vessels at the tumor margin. Then use suction and bipolar coagulating forceps to remove the tumor, working outward from its center. Send a large specimen for histological identification. Coagulate or clip and divide branches of the anterior cerebral artery supplying the tumor, taking care not to injure the callosomarginal or pericallosal arteries. Initially use a large suction tube, working from anterior to posterior. Near normal brain, change to a smaller tube and reduce suction to avoid injury. Removing the tumor over a broad area provides a view in all directions without a retractor (Figure 7.22). Do not retract the motor cortex, as this may cause ischemia or tearing with hemorrhage. Once part of the tumor has been removed, the cortical vein relaxes. Cut the arachnoid membrane beside and parallel to the vein to separate it from the tumor. Cover the vein completely with cotton to protect it, then remove the adjacent tumor with a small suction tube at low pressure. In this location, the tumor can be removed widely anteriorly, laterally, and medially. Posteriorly, however, some tumor attached to the motor cortex may have to remain; attempting complete removal could increase motor deficits.
After tumor removal, obtain meticulous hemostasis, especially where residual tumor remains, since it may bleed later. Close the dura tightly, followed by the skull and skin in layers.
Histological examination in this case showed a grade 2 protoplasmic astrocytoma. This tumor is soft and gelatinous and can be aspirated more easily than fibrillary astrocytoma. The patient received postoperative radiotherapy.
Image enhanced and colorized with AI · Switch to view the original imageFigure 7.22 Resection of a glioma in the posterior superior frontal convolution (from Figure 7.21). Note preservation of the important large cortical vein and anterior cerebral artery.
Case 2: Temporal lobe cystic astrocytoma. A 26-year-old Thai man had intermittent headaches for more than 1 year, relieved by analgesics. In the 2–3 months before admission the headaches progressively worsened and no longer responded to analgesics. Vision in both eyes became blurred, with occasional diplopia. The left arm and leg became progressively weaker, without numbness. He sometimes felt slightly unsteady when walking. One day before admission, clonic seizures began in the left side of the face and the left arm and then became generalized. Initial examination showed papilledema, left homonymous quadrantanopia, and mild weakness of the left arm and leg.
Right carotid angiography demonstrated a large avascular temporal lobe tumor with a patch of small vessels supplied by the middle cerebral artery. Exploratory craniotomy and opening of the dura revealed a cystic tumor at the surface of the posterior half of the temporal lobe, containing straw-colored fluid (Figure 7.23). The posterior portions of the superior and middle temporal gyri had been completely destroyed. Arterialized blood in the cortical vein over the cyst suggested malignancy, although the presence of such a large cyst made malignancy less likely.
Figure 7.23 Operative photograph of a cystic astrocytoma in the posterior temporal lobe, containing straw-colored fluid and a mural nodule.
Tumor resection. In this case the tumor was in the right hemisphere, so the sensory speech center was not a concern; only the distal middle cerebral artery required particular care. Such cystic tumors often contain a solid component, or mural nodule, with a relatively clear boundary. This appearance is common in cerebellar astrocytoma. In some cases, however, there is no discrete mural nodule, and the solid component usually lies on the inner side, deep to the brain surface. First open and drain the cyst to reduce intracranial pressure. Coagulate and divide the vessels and cyst wall around its margin to expose the interior. In this case a distinct pinkish-gray mural nodule projected into the cavity. A branch of the middle cerebral artery supplied it from above and medially. Begin separating the tumor by incising the cyst wall at a distance of approximately 1–2 cm around the nodule (Figure 7.24). In fact, there is no fixed rule for how close to or far from the nodule the incision should be. Observe how far tumor-like tissue extends around it and incise slightly beyond that area. Dissect along the tumor margin, trying to remain outside its boundary. When a branch of the middle cerebral artery is seen, follow it to the small branches supplying the tumor, then coagulate and divide them to disconnect its blood supply. Use suction and bipolar coagulating forceps to separate the tumor from the surrounding normal brain; the nodule should then come away easily. When the dissection reaches the temporal horn of the lateral ventricle, try to avoid entering it. If it is entered, prevent blood from falling inside by covering the opening with cotton. Remove the cotton once tumor resection and hemostasis are complete, then plug and cover the opening with Gelfoam. Finally, close the dura tightly.
Image enhanced and colorized with AI · Switch to view the original imageFigure 7.24 Resection lines for a cystic glioma with a mural nodule.
In this case, the clearly demarcated solid tumor was completely removed (Figure 7.25). Histology showed fibrillary astrocytoma. The cyst wall need not be removed if it shows degeneration and gliosis and is therefore not growing. This can be recognized while incising the wall at the cyst margin away from the mural nodule: it is yellowish-white, without the pinkish-gray areas characteristic of glioma. At 13 years of follow-up, this patient remained well, without symptoms of recurrence. This case illustrates a cystic astrocytoma of the cerebral hemisphere in which, fortunately, the tumor formed a discrete mass, unlike most other cases, which are infiltrative. Complete removal of the mass cured the patient. Thus, a cystic astrocytoma of the cerebral hemisphere with a mural nodule can have a favorable prognosis, like a cystic astrocytoma of the cerebellar hemisphere. A degenerated cyst wall does not cause tumor recurrence. However, if tumor spreads within the cyst wall without forming a nodule, it must be carefully aspirated, resected, and separated from normal brain. The principle is always to remain within the tumor boundary and avoid damage to normal brain, especially clinically important areas. Meticulous hemostasis is essential because residual tumor may cause postoperative hemorrhage.
Figure 7.25 A completely resected glioma. Note the surrounding normal brain tissue.
Original pages 639–640
Case 3: Cystic astrocytoma in the motor area of the dominant hemisphere
A 43-year-old man employed by the electricity authority had seizures involving the right arm and right side of the face, with inability to speak during the seizures. He subsequently developed headache, difficulty speaking, and weakness of the right arm and leg. Examination showed motor dysphasia and mild weakness of the facial muscles and right arm; the arm was weaker than the leg. C.T. demonstrated a cystic tumor in the left frontal lobe adjacent to the motor and speech areas.
A craniotomy was performed. After the dura was opened, the premotor and motor gyri appeared pale and broadened, and felt cystic on palpation. A cannula inserted only 1 cm through the cortex entered the cyst and yielded straw-colored fluid. The brain subsided as the fluid was aspirated. A cortical opening approximately 2 cm long exposed a tumor spreading along the cyst wall and infiltrating toward the motor area and Broca's speech area. It was therefore decided to perform only a biopsy and marsupialization to provide an opening for drainage. Histological examination showed a grade 2 astrocytoma.
The tumor was not dissected out because removing a lesion of this kind often immediately worsens speech impairment and hemiparesis through additional surgical damage to the brain, while still failing to remove the entire tumor. The patient should therefore be given a period of life without disability together with radiotherapy. This patient completed a course of irradiation. Immediately after surgery he could speak fluently and had good strength in the right arm, indicating that the preoperative speech difficulty and limb weakness had resulted from compression by the enlarging cyst. He returned to a normal working life for 1 1/2 years before the same symptoms recurred. Repeat C.T. showed a recurrent cyst and a slight increase in tumor size. A second craniotomy revealed adhesions at the opening that had obstructed drainage from the cyst. The cyst fluid was removed as before, and a wider marsupialization was performed. The tissue removed on this occasion was a grade 3 astrocytoma. This operation relieved headache and vomiting only temporarily. The hemiparesis subsequently progressed, and the patient died 6 months later.
Original pages 640–641
Results of treatment of astrocytoma
In general, patients with astrocytoma survive an average of approximately 3–5 years after surgery. The prognosis is much better than for glioblastoma multiforme, in which average survival is approximately 5–12 months. Among the cases described, cystic astrocytomas with a mural nodule have the best prognosis, with a long period free of tumor recurrence. Astrocytomas commonly recur after surgery, especially when they are near or within clinically important areas of the brain, a major obstacle to extensive excision. After the first operation, clinical and radiological examinations must be repeated periodically. Renewed tumor growth indicates failure of the first operation, and repeat surgery is necessary to determine the tumor histology and reduce the mass effect and intracranial pressure. In general, indications for reoperation for recurrent gliomas include a young patient in good health, no loss of brain function, and a tumor location accessible to surgery without causing functional loss. A further indication is a long interval between the first operation and the return of tumor symptoms. From experience with recurrent gliomas, the results of a second operation are often poor, as the period of improvement is usually shorter than after the first. Astrocytoma is frequently found to have changed into malignant astrocytoma. Nevertheless, surgery combined with radiotherapy has been found to prolong survival compared with surgery alone. In grade 1 and 2 astrocytomas treated by incomplete excision, the 5-year survival rate is 19%; adding postoperative irradiation increases 5-year survival to 45%.(40) Efforts at radical excision nevertheless prolong survival more than partial excision or biopsy alone. The use of an operating microscope, CO2 laser, and ultrasonic aspirator to assist tumor removal has now increased surgical success and reduced neurological morbidity and mortality.(39)
Original pages 641–642
GLIOBLASTOMA MULTIFORME
This is the most highly malignant tumor of neuroglial cells, corresponding to astrocytoma grades 3 and 4 in Kernohan's classification. It grows rapidly and infiltrates and destroys brain tissue, producing symptoms and signs within 1–2 months. In addition to rapid tumor growth, there is extensive surrounding cerebral edema. Together these two factors cause signs of raised intracranial pressure in almost every patient.
This tumor usually occurs in a cerebral hemisphere and is uncommon in the posterior fossa. The frontal lobe is the most frequent site and the occipital lobe the least frequent. In some cases it spreads through the corpus callosum to the opposite hemisphere, producing the so-called butterfly appearance (Figure 3.30).
Most of these tumors are poorly demarcated, although portions of the mass may be clearly defined in some cases. At surgery the tumor is usually gray-pink or gray-red because of its rich blood supply, an important cause of operative blood loss. Newly formed tumor vessels are abnormal, with endothelial proliferation (Figure 3.39) and shunting, as demonstrated on angiograms and during surgery by arterial blood in cortical veins draining the tumor. These new vessels are fragile and bleed easily, and hemostasis during surgery is often difficult. Rapid tumor growth can cause central necrosis and hemorrhage because the blood supply is inadequate. Endothelial proliferation causes vascular occlusion and necrosis, which can lead to hemorrhage. At surgery or in the specimen, patches of necrosis and hemorrhage can be seen (Figures 3.31 and 3.33).
The surrounding cerebral edema may give the impression that the tumor can be separated from the edematous brain. In reality, the swollen tissue adjacent to the tumor is usually infiltrated by tumor cells that can subsequently proliferate. When a glioblastoma reaches the cortical surface, gray-pink tissue can be seen spreading along the cortex. Dissemination into the subarachnoid space may be visible. In some cases the tumor reaches and adheres to the dura, with increased vascularity in this region and possible bleeding when the dura is opened. The author, however, has never found tumor cells within the dura itself.
Original pages 642
Symptoms and signs
Patients develop focal symptoms and signs according to the tumor location, together with general symptoms of raised intracranial pressure, as in astrocytoma and other tumors discussed in Chapter 5. The important distinction is that symptoms and signs develop more rapidly than in astrocytoma. Within approximately 1–2 months, patients become severely symptomatic even if the tumor is not particularly large, because extensive edema spreads into the surrounding brain. Headache due to raised intracranial pressure is therefore commonly the presenting symptom. Seizures and hemiplegia depend on the location of the tumor. Extension into the corpus callosum causes relatively rapid development of dementia, followed by progressively deteriorating consciousness. In a small minority of cases, symptoms begin suddenly, usually because of intratumoral hemorrhage, necessitating urgent surgery.
Original pages 642–644
Diagnosis
A history of symptoms and signs developing and deteriorating relatively rapidly first suggests malignancy, such as glioblastoma. Radiological investigation helps establish the correct diagnosis, especially C.T. or MRI combined with angiography.
1. Skull radiographs. Changes due to raised intracranial pressure, such as demineralization of the dorsum sellae, are uncommon because glioblastoma grows rapidly and causes symptoms within a short time, before skull changes develop. Most skull radiographs are therefore normal. If the pineal gland is calcified, it may be seen displaced to the opposite side. As these changes are not specific to brain tumors, this method has now been abandoned in favor of C.T. and MRI, which give more reliable results.
2. Computerized tomography (C.T.). This investigation provides a definite diagnosis. On C.T., glioblastoma appears as a high-density lesion that enhances well with contrast medium. The center may contain low-density areas of necrosis. Another important finding is low-density cerebral edema surrounding the mass, extending over a wide area even when the glioblastoma itself is not large. This is an important cause of relatively rapid deterioration, reflected by the mass effect on C.T. (Figure 6.93).
3. Magnetic resonance imaging (MRI). This is the newest investigative method and demonstrates tumors very clearly, particularly neuroepithelial tumors. MRI has high sensitivity and specificity, is free from bone-related artifacts, distinguishes the brain's white and gray matter, and clearly delineates tumor margins. Most of these tumors, together with the edematous brain, show high intensity on T2-weighted images (Figure 6.120).
4. Cerebral angiography. Before C.T. became available, angiography was the best investigation for identifying glioblastoma multiforme. The important features are (Figure 6.82): i) tumor vessels of varying caliber with a beaded appearance, caused by newly formed vessels and endothelial cell proliferation; ii) staining beginning in the arterial phase and disappearing before the venous phase, with an uneven pattern because parts of the tumor are necrotic; and iii) early venous drainage.
The abnormal vessels in glioblastoma multiforme sometimes need to be distinguished from those of an arteriovenous malformation (AVM) or meningioma. The distinction is not difficult, because an AVM produces no mass effect or vascular displacement unless it has ruptured and formed a hematoma. Glioblastoma, in contrast, produces mass effect and displaces cerebral vessels. Venous drainage in an AVM appears early in the arterial phase and disappears earlier than in glioblastoma, because the shunts are larger and there is no raised intracranial pressure. Glioblastoma is a mass that raises intracranial pressure and slows blood flow; early venous drainage begins in the late arterial or early capillary phase. In the author's observations, most AVMs consistently have several large draining veins, whereas glioblastomas usually have only one large vein, or at most two, one large and one small. To distinguish a meningioma, examine its feeding vessels and tumor staining. Meningiomas receive blood from both the external and internal carotid systems and show homogeneous staining that persists into the venous phase. Early venous drainage is uncommon except in angiomatous meningiomas. Glioblastoma receives blood only from the internal carotid artery, lacks homogeneous staining, and loses its staining earlier than meningioma. The clinical course is also important in differentiation: meningioma progresses slowly, whereas glioblastoma causes rapid deterioration.
Original pages 644–645
Treatment
Glioblastoma multiforme is accepted as an incurable tumor that causes death in every case within a short period. In general, survival is approximately 5–8 months after diagnosis. This is because the tumor grows rapidly and provokes a reaction in the surrounding brain, with extensive cerebral edema. These changes lead to brain herniation and progressive deterioration. If a patient survives more than a year and a half or two years, this tumor is unlikely, and the histology should be reviewed. Nevertheless, treatment should be attempted to prolong life and reduce suffering.
Steroid therapy. From experience using steroids or dexamethasone at 20 mg/day in patients with glioblastoma and metastatic brain tumors, improvement begins on the second day of treatment and is most marked around days 3–4. Headache, drowsiness, and limb weakness diminish. The precise mechanism is unknown, but steroids are generally believed to reduce cerebral edema and intracranial pressure.(41) Steroids should therefore be given before and after surgery in every case to help lower intracranial pressure during surgery and facilitate access to the tumor.
Treatment of glioblastoma consists of removing as much tumor as possible without increasing disability, followed by irradiation. Chemotherapy remains under investigation.
Original pages 645–646
Surgical treatment of glioblastoma multiforme
The surgical principles are the same as those for astrocytoma: remove as much tumor as possible without increasing disability, and achieve internal decompression to lower intracranial pressure and provide a period of symptomatic improvement. During this interval the patient can receive irradiation without severe neurological symptoms. For tumors in the frontal, temporal, or occipital lobe of the nondominant hemisphere, normal brain may be removed together with the tumor, or a lobectomy may be performed, to increase decompression. For tumors in the parietal lobe or in areas of the dominant hemisphere concerned with speech, limb movement, or other important functions, removal should be confined to the tumor. Brain tissue should not be excised, to avoid disability. If tumor extending into an important brain region is necrotic, cautious aspiration may be attempted. If it is infiltrative and the brain retains its structure, however, it should be left untouched.
At some institutions, when C.T. or angiography suggests glioblastoma multiforme, only a biopsy is performed to establish the diagnosis, followed directly by irradiation. The rationale is that tumor excision and biopsy alone, each combined with irradiation, do not differ in survival.
External decompression by craniotomy with removal of the bone flap is strongly discouraged. Although it can immediately improve neurological symptoms, the benefit is brief. As the tumor enlarges and expands outward, further problems arise. The scalp over the surgical site becomes tense and bulges outward (Figure 7.26), distressing the patient, and the wound may sometimes break down.
Figure 7.26 Outward bulging of the brain and wound dehiscence after external decompression in a patient with glioblastoma.
The following cases illustrate tumor removal techniques.
Original pages 646–648
Case 1: Frontal pole glioblastoma multiforme
A 45-year-old soldier had developed headache 4 months before admission, followed by blurred vision and vomiting. Two months later he became inactive and poorly responsive to his surroundings, neglected personal hygiene, and no longer dressed as neatly as he previously had in uniform. His memory became confused and his intellectual ability declined markedly. One week before admission he became slightly unsteady on standing and walking. On admission he was slow, seldom answered questions, and showed impaired intellectual function. Fundoscopy revealed papilledema, and a grasp reflex was present in the left hand. A frontal lobe tumor was diagnosed. Right carotid angiography demonstrated a large, anteriorly situated frontal lobe tumor, richly supplied by the anterior cerebral artery and to a lesser extent by the middle cerebral artery (Figure 7.27). The AP view showed considerable midline displacement of the anterior cerebral artery, with early venous drainage in the late arterial phase. These angiographic features, together with the relatively rapid clinical deterioration, suggested malignancy, particularly glioblastoma multiforme.
Figure 7.27 Carotid angiogram showing an anterior frontal lobe glioblastoma with a rich supply from the anterior cerebral artery.
Operative technique. For such a highly vascular tumor in the frontal pole, planned removal by frontal lobectomy is safer than cutting directly into the tumor, which would certainly cause substantial blood loss. The feeding vessels should therefore be divided before the tumor is removed. The frontal craniotomy must be large enough, with its anterior edge next to the orbital ridge, its posterior edge approximately 1 cm behind the coronal suture, its medial edge approximately 1–1.5 cm from the midline, and its inferior edge extending down to the pterion. Intracranial pressure must always be lowered before opening the dura, using hyperventilation or mannitol. After dural opening, frontal lobe resection begins at the superior frontal gyrus, with the line of section behind the tumor margin but anterior to the genu of the corpus callosum and the anterior cerebral artery coursing around the genu and over the corpus callosum. Beware of displacement of the anterior cerebral artery by midline shift, which can cause disorientation or misidentification. Brain section should proceed both deeply and inferiorly through the middle and inferior frontal gyri together, creating a broad exposure rather than working in a narrow channel. As the brain is aspirated, branches of the anterior cerebral artery supplying the tumor will be seen medially in the frontal lobe; these are coagulated or clipped and divided. Cortical veins on the surface draining into the superior sagittal sinus are initially preserved and divided last, when the tumor is to be removed. During section through the inferior and middle frontal gyri, tumor-feeding branches of the middle cerebral artery are likewise encountered, coagulated or clipped, and divided. In this way the section gradually deepens toward the base of the frontal lobe, allowing the frontal lobe and tumor to be removed together. If the olfactory nerve has already been destroyed, it may be divided while leaving the olfactory bulb in place to prevent CSF rhinorrhea. The dura, skull, and scalp are then closed in layers.
Original pages 648–651
Case 2: Glioblastoma multiforme in the motor area
A 40-year-old woman had a 3-month history of headache. Two months before admission she developed right-sided limb weakness, greater in the arm than the leg, but could still walk. Two weeks before admission she had one generalized convulsion, beginning in the face, spreading to the limbs, and then involving the whole body. Thereafter, the right-sided weakness became so severe that she could no longer walk unaided and needed support. She also developed diplopia. On the day of admission she vomited and became drowsy. Examination showed drowsiness; she could still answer questions but was reluctant to do so, and appeared to have a continuous headache. Fundoscopy showed papilledema. There was a left sixth nerve palsy, definite right upper motor neuron facial weakness, and right hemiplegia affecting the arm more than the leg. Pinprick sensation was normal, with bilateral positive Babinski signs. Left-sided angiography demonstrated a frontoparietal tumor.
Operative technique. The angiographic appearance together with complete hemiplegia indicated that the motor cortex and fibers had already been destroyed. Removing the tumor was therefore unlikely to cause much additional loss of limb motor function. The tumor was also distant from Broca's and Wernicke's centers. Direct removal of the tumor alone was undertaken to provide a period of improvement during which irradiation could be given.
After dural opening, the tumor was visible on the brain surface in the face and arm regions of the motor cortex. It was gray-pink, and had destroyed the cortex. The cortical vein draining the tumor was enlarged and contained arterialized blood (Figure 7.28 A). Palpation showed the inferior part of the tumor to be cystic. Puncture with a cannula yielded pale, blood-stained fluid, resembling water used to wash meat (Figure 7.28 B). Aspiration allowed the brain to subside slightly. Tumor removal began at the margin facing the Sylvian fissure, followed by dissection along the anterior and posterior borders toward the superior part, initially preserving the large cortical draining vein. Dividing this vein too early could cause hemorrhage and brain swelling. Deeper dissection exposed branches of the middle cerebral artery entering the tumor from below; these were coagulated or clipped and divided, interrupting its blood supply and reducing bleeding during subsequent dissection. The cystic component made it easier to identify tumor margins without much brain retraction. Once enough feeding vessels had been divided, as indicated by the cortical vein becoming less red or turning dark, the tumor was aspirated and excised from within toward its periphery. This reduced the chance of injuring surrounding normal brain. Eventually all visible tumor was removed. The brain relaxed well, indicating relief of pressure (Figure 7.28 C). The ultrasonic aspirator now greatly facilitates tumor aspiration.
Postoperatively the patient recovered well, without symptoms of raised intracranial pressure. Right leg strength gradually improved and she could walk, although right arm and facial weakness remained unchanged. Speech was unaffected, and she completed irradiation.
Figure 7.28 A. Operative view of glioblastoma multiforme in the motor cortex. Note the large cortical draining vein containing arterialized blood. B. Aspiration of blood-stained fluid from the tumor allows the brain to subside. C. Operative view after tumor removal. Note the well-relaxed brain and dark cortical vein.
Surgery thus improved neurological function without increasing deficits and allowed a period of comfortable life. Correct surgical technique enabled effective tumor removal with little blood loss. Histology confirmed glioblastoma multiforme. Eight months after surgery the tumor recurred, and the patient eventually died.
Original pages 651–653
Case 3: Glioblastoma multiforme of the parieto-occipital lobe
A 35-year-old patient had begun to experience mild headaches approximately 5 months before admission, relieved by analgesics. Two months later the headaches gradually increased and were sometimes accompanied by vomiting. Vision became blurred, and the patient occasionally walked into furniture on the left, without arm or leg weakness. Neurological examination revealed bilateral papilledema with retinal hemorrhages, left inferior homonymous quadrantanopia, left astereognosia, and a left Babinski sign and ankle clonus. A right parietal lobe tumor was diagnosed. Right carotid angiography showed a large parieto-occipital tumor with extensive abnormal intratumoral vessels supplied by terminal branches of the middle cerebral artery (Figure 7.29 A, B). Parts of the tumor were avascular, indicating necrosis or hemorrhage. Later films showed early venous drainage. This angiographic appearance strongly suggested either glioblastoma multiforme or a metastatic brain tumor.
Tumor removal. Two large vessels from the middle cerebral artery supplied the tumor in this case; any contribution from the posterior cerebral artery was not visible. The first principle of removal was to interrupt the tumor's blood supply. The cortex was first incised along the anterior tumor margin to approach the terminal middle cerebral artery branches. Once identified, they were coagulated and divided from the tumor. The tumor was then reduced by aspiration and excision from within toward its margins, beginning in the necrotic or avascular area identified on the angiogram. If aspiration and excision reached a vascular region without bleeding, this indicated that the blood supply had been completely interrupted. Removal was continued in this way to the normal brain. If the tumor was difficult to aspirate, it could instead be dissected along its external boundary with normal brain. At this stage, the reduced mass could readily be retracted to expose the operative space. Dissection was continued posteriorly and medially around the entire lesion, allowing complete removal. The deep portion might lie against the occipital horn, which should not be opened. If an opening occurred, it was plugged with Gelfoam and carefully sealed.
Figure 7.29 A. Right carotid angiogram showing a parieto-occipital tumor richly supplied by the middle cerebral artery. This tumor was a glioblastoma multiforme. B. Operative view of the parieto-occipital tumor.
Postoperatively, homonymous quadrantanopia persisted, but symptoms of raised intracranial pressure disappeared. Histology showed glioblastoma multiforme. The key to successful surgery in this case was complete interruption of the blood supply before removing the tumor from its center toward its periphery.
Original pages 653–655
Case 4: Parietotemporal glioblastoma multiforme in the dominant hemisphere
A 52-year-old patient presented with progressively increasing headache for 6 months. Ten days before admission the headache became severe, with vomiting and inability to understand speech and reading. On admission the patient was drowsy and slept continuously. Examination showed mild sensory dysphasia, papilledema, right homonymous hemianopia, and parietal lobe signs: astereognosis, acalculia, finger agnosia, inability to identify parts of the right side of the body, inability to read or write, and inability to draw simple figures. A left parietotemporal tumor was diagnosed.
C.T. showed a mass in the posterior parietotemporal region, extending deep from the lateral cortex toward the midline. Marked cerebral edema was visible lateral to the tumor (Figure 7.30) and was thought likely to account for the speech disturbance.
Tumor removal. Because the tumor was in the dominant hemisphere containing Wernicke's sensory speech center, care was required to avoid damaging this area with a cortical incision and causing a permanent, physician-induced deficit. In this patient, impaired speech might have been due solely to edema extending into the speech center and could be expected to improve as edema subsided after tumor removal. The cortical incision should therefore be made in the posterior parietal parasagittal region to avoid injury to the speech center.
Figure 7.30 C.T. showing a parietotemporal tumor in the dominant hemisphere.
The principles of tumor removal were as described above. In this case the blood supply had to be considered from three directions: branches of the anterior, middle, and posterior cerebral arteries. These feeding vessels were to be interrupted before aspirating and excising the tumor. Complete removal was not possible because of its depth and proximity to the cerebral midline; attempts to remove it all might have endangered the patient, so the deep portion was left. Nevertheless, the tumor was greatly reduced and the brain relaxed. Postoperatively the patient recovered well, and speech and the various parietal lobe signs returned almost to normal. This showed that some symptoms had arisen from compression by the mass and edema; after mass removal and resolution of edema, brain function could return. This example also illustrates an approach to tumor removal that avoids damaging important brain regions.
Original pages 655
OLIGODENDROGLIOMA
Oligodendroglioma arises from oligodendrocytes and is a relatively benign, very slowly growing tumor found in adults approximately 30–50 years of age. It occurs most commonly in the cerebral hemispheres, particularly the frontotemporal region rather than other lobes. Growth is infiltrative, although a distinct margin may sometimes be visible, and multiple areas of cystic degeneration may occur. Calcification is frequent, occurring in 40–50% of oligodendrogliomas, and can be seen radiologically and histologically. The characteristic microscopic appearance consists of uniformly sized cells with dark-staining central nuclei, absent or scant cytoplasm, and sharply defined cell borders, giving a fried-egg appearance. The cells are tightly packed in a honeycomb pattern (Figure 3.40).
Original pages 655–656
Symptoms and signs
Because oligodendroglioma grows very slowly, symptoms usually develop gradually over a long period before correct diagnosis and treatment, generally approximately 3–5 years. When raised intracranial pressure develops, the symptomatic interval is shorter. Seizures are the most common initial symptom and may be the only symptom, so patients may receive anticonvulsant medication for a long time. Other accompanying symptoms may include headache, psychiatric symptoms, limb weakness, and unclear speech, depending on the brain region damaged by the tumor (see Chapter 5). In the past, diagnosis was often made only after loss of brain function and raised intracranial pressure had developed. The author now believes that earlier diagnosis should be possible because C.T. and MRI are excellent diagnostic aids. In an adult presenting with a first seizure, an organic lesion must always be considered. Brain tumors are a common such lesion, so C.T. or MRI should be obtained directly, as these are safe and painless. Some oligodendrogliomas can nevertheless cause rapid deterioration if the tumor extends toward a ventricle and causes hydrocephalus, or if intratumoral hemorrhage occurs.
Original pages 656
Diagnosis
Several radiological investigations can suggest oligodendroglioma.
1. Skull radiographs. The important finding on plain skull films is calcification in small fragments of varying sizes scattered throughout the tumor. It occurs in approximately 50% of oligodendrogliomas(42) (Figure 7.31 D).
2. C.T. Oligodendroglioma generally has two components. One is hypodense or isodense and may or may not enhance after contrast injection. The other consists of calcification, appearing as scattered bone-density hyperdensities, especially near the tumor margins. There is usually no visible surrounding cerebral edema, or very little (Figure 7.32).
3. MRI. The tumor may appear hypointense on T1-weighted images and hyperintense on T2-weighted images, but MRI does not show calcification as C.T. does.
4. Cerebral angiography shows an avascular mass.
Original pages 656–657
Treatment
The principles of treating oligodendroglioma are the same as for other gliomas: craniotomy and complete tumor removal without damaging important brain functions. Some tumors form a clearly demarcated mass that can be completely removed as judged by the naked eye, particularly when located at a lobar pole. Others lack a distinct mass and infiltrate the insula, basal ganglia, motor or speech areas, or a ventricle. In these cases only as much partial removal as is feasible should be attempted. Complete excision should not be pursued at the cost of function in important brain regions. This consideration is always essential because oligodendroglioma grows very slowly and the patient may live for many years; disability should therefore not be inflicted.
Indications for surgery. Because oligodendroglioma grows very slowly, a frequent question is whether a patient whose only symptom is seizures well controlled by anticonvulsants, with no other neurological symptoms or raised intracranial pressure, should undergo immediate surgery or wait until neurological deficits or raised pressure develop. There are two schools of thought: operate immediately, or wait. Surgeons favoring delay believe that several years may elapse before this slow-growing tumor causes functional deterioration, and fear that surgery might immediately cause limb weakness or other disability. The author favors immediate surgery, without waiting for further loss of function. Operating while the tumor is small and has not yet damaged important structures is easier and less dangerous than operating on a large tumor that has already caused neurological deficits. Furthermore, radiological diagnosis can be mistaken. Tissue should therefore be removed and examined to establish the exact diagnosis and guide subsequent treatment. C.T. and MRI now assist diagnosis and clearly show the tumor's location and extent, allowing surgeons to operate more confidently while avoiding important brain structures.
Radiotherapy. Because oligodendroglioma is a benign tumor, postoperative irradiation has been considered ineffective.(43,44) Some institutions nevertheless administer it and report a higher proportion of patients surviving beyond 5 years. Sheline G.F. et al.(45) studied postoperative irradiation and found an increase in 5-year survival from 31% to 85%, in 10-year survival from 25% to 55%, and in median survival from 2.8 to 8 years. Chin, H.W. et al. reported 24 patients treated with surgery and irradiation, with a 5-year survival rate of 100%.(43)
Original pages 657–658
Results of treatment
Gross total removal leads to longer survival than partial excision. Most patients survive more than 5 years. The prognosis is particularly good for a clearly defined mass that can be completely removed. In Case 1, follow-up has continued for 8 years without recurrent symptoms.
Original pages 658–660
Case 1: A discrete frontal lobe oligodendroglioma
A 40-year-old patient presented with generalized seizures and a change in personality. Previously active and talkative, the patient had become slow at work and less communicative. More recently there were headaches, impaired memory, and occasional confusion. The patient appeared indifferent and reluctant to answer questions, spoke slowly, had impaired recent memory, right-sided anosmia, bilateral papilledema, and frontal lobe signs. Skull radiographs showed calcification in the right frontal lobe. Carotid angiography demonstrated a mass at the base of the right frontal lobe (Figure 7.31 A, B).
Operative removal. A transcoronal incision and right frontal craniotomy are performed. The anterior edge of the craniotomy is placed close to the orbital ridge to expose the frontal pole readily; the posterior edge lies just behind the coronal suture, the superior edge 1.5 cm from the midline, and the inferior edge as low as possible to facilitate exposure of the frontal base. Because intracranial pressure is raised, hyperventilation and mannitol are used to lower it before dural opening. A lateral approach gives easier access to this tumor than a frontal pole approach or a cortical incision through the middle frontal convolution. From the side, the posterior and inferior portions of the tumor can be lifted away from the internal carotid and anterior cerebral arteries. As this is the nondominant hemisphere, part of the inferior frontal convolution can be excised to expose the tumor without excessive retraction (Figure 7.31 C). Once the tumor is reached, dissection follows its posterior and inferior margins toward the midline. Some tumor in this region is removed to open a corridor to the anterior cerebral artery and its anteriorly directed tumor-feeding branches. These branches are coagulated and divided. The entire tumor can then be dissected out easily and without blood loss.
AI-enhanced and colorized image · Switch to view the originalFigure 7.31 Right frontal lobe oligodendroglioma. A. Lateral carotid angiogram showing a large tumor at the frontal base. Note the calcification. B. Anteroposterior carotid angiogram. C. Resection of the inferior frontal convolution to approach the tumor (applicable only in the nondominant hemisphere). D. Radiograph of the surgically removed tumor, showing numerous scattered calcifications.
In this case the tumor was removed as a whole. Radiography of the specimen clearly showed the intratumoral calcifications commonly seen in oligodendroglioma (Figure 7.31 D). Histology confirmed oligodendroglioma. Nowadays, gradual aspiration from the center toward the margins with an ultrasonic aspirator greatly facilitates removal.
Original pages 660–661
Case 2: Infiltrative oligodendroglioma
A 36-year-old male bank employee had a 1-year history of generalized seizures and progressively slower work performance. Neurological examination revealed no other abnormalities.
C.T. showed a hypodense frontotemporal lesion infiltrating toward the basal ganglia. Calcified portions appeared hyperdense (Figure 7.32).
Figure 7.32 C.T. of a low-grade glioma with calcification. Histology showed oligodendroglioma.
Surgery. Complete removal in such a case would be impossible without damaging the basal ganglia. The aim should be partial resection of tumor in the temporal and frontal lobes while leaving the part near the basal ganglia. A frontotemporal craniotomy is performed, followed by cortical incisions in the anterior superior temporal gyrus and inferior frontal convolution at the sites of visible cortical abnormality. Suction and coagulation are used to remove tumor progressively inward as extensively as feasible, without damaging the insula, middle cerebral artery, or Sylvian fissure with its veins and arteries. Resection must stop at the basal ganglia. This reduces tumor size and intracranial pressure and establishes the tumor type.
After surgery, no additional neurological deficit was present. Histology showed oligodendroglioma, and irradiation was not given. The patient returned to his previous bank work. Three years later symptoms recurred: slow speech, inactivity, loss of sexual desire, and mild headache, but still no limb weakness. Repeat C.T. showed expansion of the hypodense region, and further tumor removal was undertaken. As after the first operation, he initially recovered well without limb weakness. Twenty-four hours later, however, he developed left-sided limb weakness and drowsiness. Repeat C.T. showed hemorrhage extending into the basal ganglia. It was decided not to reopen and evacuate the hematoma, because surgery might further damage the basal ganglia; the hemorrhage had already destroyed part of the basal ganglia and tumor. Medical treatment would be continued provided consciousness did not progressively deteriorate. Fortunately, the patient recovered with medical treatment, although left hemiparesis persisted.
This case shows that infiltration into important brain structures such as the basal ganglia limits complete tumor removal. Residual tumor can regrow sooner than a discrete mass such as that in Case 1. Postoperative hemorrhage also occurs more readily, a risk that should always be remembered.
Original pages 661–662
OPTIC GLIOMAS
These gliomas arise in the anterior visual pathway: the optic nerve, chiasm, and optic tract. Most are benign, very slowly growing astrocytomas composed of elongated, hair-like astrocytic cells, hence the name pilocytic astrocytoma.(46,47) The author has never personally encountered malignant optic gliomas, although they have been reported in both children and adults.(48,49)
Reports indicate that 75% of optic gliomas occur in children under 12 years and are more frequent in patients with von Recklinghausen's disease, or neurofibromatosis. Some occur in patients with café-au-lait spots. Thus, when optic glioma is suspected, cutaneous abnormalities support the diagnosis. Conversely, deteriorating vision in a patient with von Recklinghausen's disease requires thorough investigation for an optic pathway glioma.
The tumor may arise at different sites. In the optic nerve it is termed optic nerve glioma and may be unilateral or bilateral. Optic chiasmal glioma refers to a tumor arising in the chiasm. These two entities differ somewhat in symptoms and signs, treatment, and prognosis. An optic nerve tumor may extend into the chiasm; conversely, a chiasmal tumor may extend into an optic nerve, the optic tract, hypothalamus, or interpeduncular fossa.
Original pages 662–665
Symptoms and signs
The principal symptom is visual loss, the pattern depending on tumor location.
OPTIC NERVE GLIOMA. This causes progressively worsening vision in the affected eye. Visual field loss usually begins as a central or paracentral scotoma, followed by peripheral visual loss. Because most patients are children and the tumor grows slowly, a history of visual deterioration is often difficult to obtain. Fundoscopy shows a pale optic disc (optic atrophy). Optic nerve gliomas commonly arise within the orbit; later enlargement therefore produces forward protrusion of the eye (proptosis) (Figure 7.33 A). This is nonpulsatile, and ocular movement is generally preserved unless the mass becomes very large, when motility is impaired and strabismus develops. Tumor may grow through the optic foramen and form a mass on the intracranial optic nerve, giving a dumbbell configuration with enlargement of the optic foramen. Extension into the chiasm causes bilateral visual field loss without a consistent specific pattern.
Figure 7.33 Optic nerve glioma in the left orbit. A. Unilateral proptosis or exophthalmos. B. C.T. showing an intraorbital optic nerve glioma.
CHIASMAL GLIOMA. Vision deteriorates progressively in both eyes. Bilateral visual field defects have no characteristic pattern; their borders may be regular or irregular depending on tumor infiltration. A chiasmal glioma may extend into one or both optic nerves. The eye whose optic nerve is destroyed becomes blind first. Fundoscopy shows primary optic atrophy. Nystagmus in the absence of cerebellar signs is an important indicator of chiasmal disease,(50) arising as the eyes search for objects. In some cases the tumor enlarges to compress the anterior third ventricle and hypothalamus and obstruct the foramen of Monro, causing hydrocephalus and raised intracranial pressure with papilledema. Thus, either optic atrophy or papilledema may be found in chiasmal glioma. Hypothalamic dysfunction may manifest as diabetes insipidus, diencephalic syndrome, or precocious puberty.(51,52,53)
The author has also encountered a patient with an intraorbital optic nerve glioma, chiasmal glioma, and large frontal lobe astrocytoma, without hypothalamic dysfunction. This 24-year-old woman had developed blurred vision at age 12, with bilateral visual field loss and optic atrophy. Angiography at that time showed a suprasellar mass. Frontal craniotomy revealed a large chiasmal tumor (Figure 7.34); biopsy showed pilocytic astrocytoma. Twelve years later, the left eye was proptotic and blind, the right eye had visual field loss, and headache and personality changes had developed. C.T. demonstrated tumor in the left intraorbital optic nerve, chiasm, and frontal lobe (Figure 7.35 A, B). The frontal tumor was removed and was found to have grown from the optic chiasm. At the same operation, the intraorbital optic nerve glioma on the left side was excised from behind the globe to its junction with the chiasm. Histology showed astrocytoma in all specimens.
Figure 7.34 Operative view of chiasmatic and optic nerve glioma. 1. Tumor. 2. Right optic nerve. 3. Internal carotid artery.Figure 7.35 Optic nerve glioma associated with frontal lobe glioma. A. Left proptosis. B. C.T. showing tumor in the left orbit and left frontal lobe.
Original pages 665–666
Investigations
Before C.T. and MRI became available, skull radiography was an important investigation for diagnosing optic nerve glioma.
Skull radiographs. In optic nerve glioma, lateral skull films often show a change in the sella turcica termed a J-shaped or pear-shaped sella (Figure 6.23), caused by tumor pressure eroding the anterior clinoid process and tuberculum sellae. This change, however, is not specific to optic nerve glioma. The optic foramen view is also very important.(54) It shows enlargement of the foramen on the affected side (Figure 6.22). Normally the optic foramen is oval, with an average diameter of 5 mm. A round foramen wider than 6 mm, or a difference of more than 1 mm between sides, is abnormal. Both foramina may be enlarged if a chiasmal glioma extends into both optic nerves. A normal-sized foramen does not exclude optic nerve glioma, however, because some tumors do not grow through the optic canal.
C.T. and MRI. These are the best methods and have replaced the other radiological investigations. They clearly demonstrate the optic nerve and intraorbital tumor. Low-density orbital fat provides good contrast with the isodense optic nerve. They also show the location, size, shape, and extension into neighboring structures. Because optic nerve glioma is isodense, intravenous contrast does not make the tumor more clearly visible.(55) The optic canal is clearly seen on C.T. sections through it. For an intracranial tumor at the sella turcica, MRI depicts the lesion more clearly than C.T., in axial, sagittal, and coronal views. The midsagittal view best shows a chiasmal tumor.
PNEUMOENCEPHALOGRAPHY, VENTRICULOGRAPHY, CAROTID ANGIOGRAPHY. These demonstrate a suprasellar mass when it is fairly large but cannot determine its type. They are no longer used for this investigation. In some cases, however, carotid angiography may be necessary to exclude vascular disease and assist surgical planning.
Original pages 666–667
Diagnosis
Optic gliomas can be diagnosed from the clinical signs described above: a child, usually under 12 years, with progressively deteriorating vision leading to blindness and proptosis on the affected side, sometimes accompanied by strabismus, with optic atrophy on fundoscopy. Chiasmal gliomas impair acuity and visual fields in both eyes, with no fixed pattern of field loss. Hypothalamic dysfunction, including diabetes insipidus, diencephalic syndrome, or precocious puberty, or symptoms of raised intracranial pressure such as headache and vomiting, may accompany the visual changes. If features of von Recklinghausen's disease are also present and skull radiographs show an abnormally enlarged optic foramen and a J-shaped sella, the diagnosis of optic glioma is fairly certain. C.T. and MRI best support the diagnosis and demonstrate compression of neighboring structures.
Original pages 667–669
Treatment
There are two methods of treating optic glioma: surgery and radiotherapy. The choice depends principally on the patient's vision and the tumor's location, according to the following principles.
1. When an intraorbital optic nerve glioma causes severe loss of vision or blindness in that eye together with proptosis, the best treatment is excision of the optic nerve and tumor from behind the globe to close to the optic nerve–chiasm junction. If the proximal optic nerve is free of tumor, postoperative radiation is unnecessary. Removal of only the intraorbital tumor should be avoided because it may extend into the intracranial optic nerve. The globe need not be removed, thereby preserving appearance, unless tumor is also present within it.
2. When an optic nerve tumor extends into the chiasm but both eyes retain vision, even if vision on the affected side is worse, and there is no proptosis, the involved optic nerve should not be divided. Biopsy followed by radiotherapy is preferable. For example, a 3-year-old girl presented with oscillation of both eyes when looking at objects. Examination showed searching nystagmus. Both eyes retained vision, but detailed acuity and field testing was impossible because she did not cooperate. C.T. showed sausage-shaped enlargement of the right optic nerve (Figure 7.36A). Frontal craniotomy and orbital exploration disclosed an optic nerve tumor extending into the chiasm. Biopsy of the proximal optic nerve showed glioma. Postoperative radiotherapy gave a good result: she retained vision in both eyes without deterioration and performed well at school. C.T. 10 years after treatment showed that the optic nerve glioma had become slightly smaller rather than enlarged (Figure 7.36B), indicating that radiotherapy could arrest its growth. At follow-up 10 years after surgery, visual acuity, visual fields, and optic nerve size remained unchanged. Menstruation was normal. Continued follow-up is necessary to determine whether the tumor will grow again. Had the involved optic nerve been excised, she would immediately have lost vision in one eye.
Figure 7.36 Results of radiotherapy for optic nerve glioma. A. C.T. before radiotherapy. B. C.T. 10 years after radiotherapy.
3. In chiasmal glioma, tumor excision should not be attempted because it would further impair vision in both eyes and could cause blindness. Moreover, because the tumor infiltrates, there is no way to determine whether removal from the chiasm is complete. Biopsy followed by radiotherapy is appropriate.
2. Lateral orbital wall resection is an unsatisfactory approach. It requires division of the zygomatic arch to reach and resect the lateral orbital wall, and may damage the frontal branch of the facial nerve. The author therefore usually uses frontal craniotomy.
TRANSFRONTAL APPROACH. This is a good approach and the only one that exposes both the intraorbital optic nerve glioma and its intracranial extension, including the optic chiasm and the opposite optic nerve.
Technique. Position the patient supine with the face turned approximately 15° to the opposite side. Make a transcoronal incision and frontal craniotomy on the tumor side. The craniotomy resembles that used for pituitary-region tumors: its anteroinferior edge must lie close to the orbital ridge and its medial edge at the midline.
C.T. and MRI now show the location and extent of these tumors fairly clearly. Previously, pneumoencephalography and angiography gave less precise localization, making it necessary always to open the dura and inspect the intracranial optic pathway before opening the orbit. Although this remains a sound practice, it is unnecessary in some cases, in which extradural orbitotomy alone suffices. For example, when an optic nerve glioma lies at the distal end of the nerve beside the globe and the proximal nerve is normal in appearance and size, extradural orbitotomy avoids the frontal lobe and olfactory nerve damage from retraction that often accompanies an intradural approach. Frozen section of the proximal intraorbital optic nerve also helps determine whether the dura must be opened. If no tumor is present in the nerve near the orbital apex, opening the dura is unnecessary.
For extradural orbitotomy, gently separate the dura from the orbital roof posteriorly to the anterior clinoid process, and retract the dura and frontal lobe with a spatula. Open the orbit using a small chisel on its thin roof, which is easily penetrated, then enlarge the bony opening with rongeurs. Unroof the optic canal to expose the dural sheath. The orbital fascia, which is the orbital periosteum and joins the dura at the optic foramen, will bulge through the opening. Incise it along the optic nerve and transversely, then place retraction sutures to expose the orbital structures. Use a microscope at this stage: the nerves and other structures are small in children and still harder to recognize when flattened by the tumor. From above, the frontal branch of the ophthalmic division of the trigeminal nerve can be seen on the levator palpebrae superioris and superior rectus muscles. The small trochlear nerve crosses the levator tendon from lateral to medial to supply the superior oblique. All these nerves and muscles must be identified and preserved. To approach the optic nerve, divide the tendon at the origin of the levator near the annulus of Zinn (Figure 7.37) and reflect it anterolaterally with its supplying nerves. Open the annulus of Zinn and optic canal dura by a transverse incision parallel to the superior rectus margin. Retract the superior rectus laterally with the levator and separate the fat to expose the whole optic nerve and tumor. Protect the oculomotor nerve, which lies lateral to the optic nerve and sends branches beneath it to the inferior rectus and medial rectus muscles. The small trochlear nerve is sometimes difficult to find and may be divided during dissection. Loss of superior oblique function is not considered particularly important here because that eye is blind and the abnormal eye movement is difficult to notice.
AI-enhanced and colorized image · Switch to view the originalFigure 7.37 Structures within the orbit. 1. Ophthalmic nerve. 2. Optic nerve. 3. Trochlear nerve. 4. Superior oblique muscle. 5. Levator palpebrae muscle. 6. Superior rectus muscle. 7. Lateral rectus muscle. 8. Abducens nerve. 9. Ophthalmic artery. (From Sobotta Atlas of Human Anatomy, edited by H. Ferner and J. Straubesand.)
Divide the optic nerve near the globe first, where the other nerves are farther apart because they have already branched to their destinations. Lift and reflect it posteriorly to separate it from posterior and lateral structures. Divide its proximal end at the optic canal.
After removing the tumor and securing hemostasis with bipolar coagulation, close the orbital fascia. To prevent postoperative pulsation of the globe, the author covers the orbital roof defect with a thin acrylic sheet. It need not be sutured to the skull: projections engaging the bony margin hold it in place.
TRANSFRONTAL INTRADURAL APPROACH. Perform frontal craniotomy, open the dura, and retract the frontal lobe from the orbital roof to expose the optic nerve, chiasm, and internal carotid artery. This approach suits tumors extending intracranially or arising in the chiasm. Incise the arachnoid around the chiasm and internal carotid artery to allow greater frontal lobe retraction and better visualization of the chiasm. If only one optic nerve contains tumor and vision is already lost, divide that nerve close to the chiasm. Leave no optic nerve remnant, even if it appears normal, because tumor cells may remain. If vision persists in that eye, however, do not divide the optic nerve; perform biopsy alone followed by radiotherapy.
For a tumor arising in the chiasm, with or without extension into the optic nerve or hypothalamus, take a biopsy from the region most evidently occupied by tumor, where the nerve fibers have already been destroyed. Do not attempt complete removal. A mass projecting beyond the chiasm may be excised while avoiding further chiasmal damage, as in the example above. Attempting to remove tumor from within the chiasm only increases visual loss.
TRANSFRONTAL COMBINED APPROACH. There are two methods:
1. After transfrontal craniotomy, separate the dura from the orbital roof and perform extradural orbitotomy as described above to expose the optic nerve and tumor. If inspection of the chiasm and optic nerve is necessary, open the dura and retract the frontal lobe. The nerve can then be divided both within the orbit and at its proximal end.
2. After transfrontal craniotomy, open the dura and retract the frontal lobe to expose the chiasm and optic nerve. Incise the dura over the orbital roof along the orbital margin and lift it from the bone. Then perform orbitotomy and unroof the optic canal to expose the entire optic nerve (Figure 7.38).
AI-enhanced and colorized image · Switch to view the originalFigure 7.38 Surgery for optic glioma using a combined intradural and extradural approach.
Radiotherapy. Optic glioma responds to radiotherapy. In the example above, 10 years after irradiation the tumor had become slightly smaller rather than enlarged. The author therefore considers radiotherapy suitable for optic nerve glioma when vision remains and proptosis is not marked, and also for chiasmal glioma.
Original pages 674
Treatment Results and Prognosis
Surgery gives very good results only for optic nerve glioma confined to the orbit without extension into the chiasm. Excision of the optic nerve and tumor cures the disease. Prognosis depends on whether the tumor extends into the chiasm or originates there. Surgery is ineffective in these cases; radiotherapy is the best treatment, arresting or slowing growth and sometimes shrinking the tumor. The patient's condition may remain unchanged for nearly 10 years. Nevertheless, renewed growth remains possible over long follow-up. Most patients survive for a long time because these tumors grow very slowly.
Original pages 674–675
Brain Stem Gliomas
Brain stem gliomas are the third most common tumors in children, after cerebellar astrocytoma and medulloblastoma.(56,57,58) They occur most often between 3 and 10 years of age.(59,60) Most are benign gliomas, with very few malignant gliomas. Even a benign glioma must, however, be regarded as malignant because its location prevents surgical removal. The tumor usually starts in the pons and extends into the medulla, midbrain, or both. The true incidence is difficult to establish because histology is often unknown. In many patients the symptoms, signs, and radiological investigations such as C.T. and MRI establish the diagnosis clearly; surgery to obtain tissue is therefore not performed, given the poor prognosis and risk of further functional loss.
These patients consequently receive radiotherapy without a tissue diagnosis, and the brain may not be examined after death. Furthermore, a small biopsy specimen may not establish the tumor type and malignancy reliably; taking a larger specimen risks further brain stem dysfunction. Reported incidence therefore does not accurately reflect the true frequency.
The pathological changes in the brain stem and histological features are described in Chapter 3.
Original pages 675–676
Symptoms and Signs
These tumors occur predominantly in children and do not produce raised intracranial pressure until late in the disease. Diagnosis is therefore often delayed until symptoms are advanced.
Symptoms generally develop gradually and reflect dysfunction of the following important structures: i) cranial nerves, their nuclei, and other special nuclei; ii) corticospinal and sensory tracts; iii) cerebellar peduncles; iv) the reticular activating system; and v) the ventricular system, late in the disease. Details appear in Chapter 5.
In summary, cranial nerve dysfunction accompanied by long tract signs and cerebellar dysfunction indicates a brain stem lesion. The affected cranial nerve level localizes the tumor. Several nerves may be involved unilaterally or bilaterally, depending on its extension. Because brain stem gliomas occur most often in the pons and next in the medulla, manifestations include diplopia, convergent squint, unilateral or bilateral lower motor neuron facial weakness, facial numbness, choking on swallowing, altered voice, and vomiting from compression of the medullary vomiting center. Horizontal or vertical nystagmus is commonly found. Lateral gaze palsy may also result from damage to the pontine lateral gaze center.
Abnormal walking is also common. Truncal or gait ataxia may result from damage to the cerebellar peduncles. Spastic hemiparesis or quadriparesis with extensor plantar responses is frequently found. Advanced disease produces decerebration (Figure 7.39) and declining alertness. Most patients have no symptoms or signs of raised intracranial pressure early because the tumor does not obstruct cerebrospinal fluid pathways. Late in the disease, a large brain stem tumor may obstruct the fourth ventricle, basal cistern, and tentorial notch. Tumors originating in the midbrain or extending there from the pons may produce raised intracranial pressure from hydrocephalus relatively early by obstructing the aqueduct of Sylvius (Figure 3.24). Patients then develop headache, vomiting, papilledema, and drowsiness.
Reported mental and personality changes in children with brain stem glioma commonly include apathy, emotional unrest, declining school performance, and deterioration in writing and speech (see Case 1).
Original pages 676
Diagnosis
The diagnosis can be made with considerable certainty from age, history, and examination. Most patients are children in their first decade, with progressively increasing brain stem dysfunction involving several cranial nerves, corticospinal and sensory tracts, cerebellar peduncles, and the reticular activating system, as described above. Raised intracranial pressure is absent except late in the disease. Radiological investigations provide strong support for the diagnosis.
Original pages 676–678
Investigations
C.T. and MRI are currently the best methods. C.T. shows enlargement of the brain stem with obliteration of the posterior fossa cisterns. The tumor is hypodense or isodense; after contrast injection its density may remain unchanged or become hyperdense. Extension into the cerebellar peduncle and the floor of the fourth ventricle may flatten and displace the fourth ventricle posteriorly (Figure 6.97). C.T. may also show hydrocephalus, an exophytic mass extending from the brain stem into the fourth ventricle or cerebellopontine angle, and intratumoral cysts. These findings guide the choice between partial tumor resection and shunting alone. Its limitations are poor depiction of medullary tumors and poor sagittal visualization. Before MRI, C.T. combined with metrizamide cisternography depicted exophytic and medullary tumors very well. This method has been used very little since MRI became available.
MRI excellently demonstrates the location, size, shape, and extent of brain stem tumors, both intrinsic and exophytic. Unlike C.T., it clearly shows tumors in the medulla and those extending into the upper spinal cord, making it especially useful in these locations. Axial, coronal, and sagittal views are available. These tumors show decreased signal intensity on T1-weighted images and increased signal intensity on T2-weighted images (Figure 6.121).
Previously, pneumoencephalography (PEG), ventriculography, and vertebral angiography were useful diagnostic investigations. All were invasive and hazardous, and demonstrated a mass without clearly defining its extent. PEG and ventriculography showed posterior bowing of the fourth ventricle and aqueduct of Sylvius, with greater separation from the clivus, and no hydrocephalus (Figure 6.134). On anteroposterior vertebral angiography, both posterior cerebral and superior cerebellar arteries bowed laterally. Lateral views showed the basilar artery displaced against the clivus. In some tumors growing anteriorly out of the brain stem against the clivus, however, the basilar artery could be displaced posteriorly away from the clivus. These had to be distinguished from other lesions arising near the clivus outside the brain stem. The posterior cerebral artery was elevated.
Original pages 678–679
Treatment
Because these tumors arise within the brain stem, a vital part of the brain, complete surgical removal is impossible. Treatment usually consists of biopsy to determine tumor type, followed by radiotherapy. Brain stem tumor biopsy presents two problems: i) obtaining tissue sufficient for histological diagnosis is difficult because surgeons fear that a large biopsy will worsen brain stem function and therefore take only a small specimen. Diffuse enlargement may make selection of the biopsy site difficult. C.T. and MRI now localize the tumor precisely, facilitating biopsy and definite tissue sampling.(61) ii) Histology may differ within different parts of a tumor; a biopsy from one site may not reveal its true malignancy,(62) making prognosis less reliable.
Whether to biopsy patients whose clinical and radiological findings clearly indicate brain stem glioma remains controversial. Some give radiotherapy without biopsy, arguing that biopsy risks further brain stem damage and may not establish the precise tumor type or malignancy. The author believes that biopsy should be performed whenever possible in every patient to determine the tumor type first. However detailed C.T. or MRI may be about appearance and location, they cannot establish the type with certainty. Biopsy identifies benign or malignant tumor type, helps predict its course, and guides further treatment. This not only helps parents understand the prognosis but also improves knowledge of incidence and treatment results for each tumor type with radiotherapy or effective chemotherapy currently under investigation. Such knowledge will help improve future treatment of brain stem glioma.
C.T. and MRI distinguish tumors outside the brain stem from intrinsic tumors fairly clearly. They greatly improve surgical planning by showing tumor characteristics and location, cerebrospinal fluid obstruction or hydrocephalus, and extension outside the brain stem or into the fourth ventricle. The indications for surgery are as follows:
1. If diagnosis remains uncertain after C.T. or MRI and histology is needed for further treatment, perform surgical exploration and biopsy.
2. If C.T. and MRI show an intratumoral cyst close to the brain stem surface, open and evacuate the cyst and obtain tissue. Precise imaging localization makes this relatively straightforward, and surgery generally causes no further brain stem damage. Although not curative, it can produce temporary improvement and prolong survival. Before C.T. and MRI, diagnosis relied on pneumoencephalography (PEG), ventriculography, and angiography, which could not identify an intratumoral cyst. Exploration was needed to look for a surface suggesting a cyst within the brain stem tumor. Finding one was fortunate because draining it improved the patient's condition. If none was evident, searching further was inadvisable because it would damage the brain stem; biopsy of an evident tumor area was sufficient. The following example illustrates the effect of draining a cyst in a brain stem glioma.
Original pages 679–683
Case 1: Brain Stem Glioma with a Cyst
A 6-year-old boy had experienced frequent near-fainting episodes for a year before admission. He subsequently bumped into objects, fell frequently, and often dropped things. His speech and school performance deteriorated. He sometimes cried, became easily angry, and behaved aggressively. Two months before admission, he developed incomplete eyelid closure and weakness of both sides, worse on the left. Increasing unsteadiness left him unable to walk or sit unaided. His speech became indistinct, with projectile vomiting and drowsiness. On examination he answered questions poorly, was irritable, and spoke slowly with a drawl. There were sixth nerve palsy, bilateral facial palsy, bilateral extensor rigidity with occasional flexion of the left arm, increased deep tendon reflexes, and bilateral positive Babinski signs (Figure 7.39). The history and examination suggested a brain stem tumor. Vertebral angiography and ventriculography showed posterior bowing of the fourth ventricle and aqueduct of Sylvius without hydrocephalus (Figure 7.40), characteristic of a brain stem tumor. Exploratory suboccipital craniectomy was performed.
Figure 7.39 Extensor rigidity in a patient with brain stem glioma.Figure 7.40 Ventriculogram showing a brain stem glioma displacing the fourth ventricle and aqueduct of Sylvius posteriorly without obstructing cerebrospinal fluid flow.
Operative technique. Open the posterior fossa as described for other tumors. After opening the dura, before inspecting the fourth ventricle, elevate each cerebellar tonsil and hemisphere to inspect the outside of the brain stem and the cerebellopontine angles, ensuring that there is no extrinsic lesion. Then separate the tonsils to inspect the floor and cavity of the fourth ventricle. To expose its anterior portion, divide the inferior vermis in the midline, preserving the vessels on either side, and separate the vermis and tonsils. A pale or light-yellow area on the ventricular floor indicates the cyst wall, which can be opened to drain the cyst without further functional loss. In this case the wall lay in the midline anterior to the striae medullares. Before opening it, a needle inserted in the midline of the ventricular floor aspirated pale tea-colored fluid (Figure 7.41A). The wall was then opened in the midline or at its thinnest point to expose the tumor and establish drainage, or marsupialization (Figure 7.41B). A microscope or loupe should be used at this stage to visualize the tumor clearly and remove a small portion safely for histology. Extensive or complete removal should not be attempted because it would damage the brain stem.
Histology showed astrocytoma. The patient was very drowsy for the first 2 postoperative days and became alert on the third. The striking change was almost complete disappearance of bilateral limb extensor rigidity. Only bilateral hyperreflexia remained, greater on the left. He was discharged on postoperative day 17 and returned for radiotherapy.
3. When tumor projects into the fourth ventricle or outside the brain stem and obstructs cerebrospinal fluid pathways, remove the extrinsic portion without damaging the brain stem. This reopens cerebrospinal fluid pathways, relieves brain stem compression, lowers raised intracranial pressure, and prolongs survival.(63,64) There is now increasing support for resecting such tumors, whereas these patients were formerly considered beyond surgical help.(65,66)
Figure 7.41 Surgery for brain stem glioma through a midline split in the vermis. A. Tea-colored fluid from the cystic part of the tumor. B. The cyst wall has been opened and part of the tumor removed.
4. In a tumor with intratumoral hemorrhage, evacuation of the hematoma may allow recovery.
5. In hydrocephalus, a ventriculoperitoneal or ventriculoatrial shunt relieves raised intracranial pressure.
Radiotherapy. Because these tumors arise within the brain stem and cannot be removed completely, radiotherapy is necessary. The accepted dose is 5000–5500 rad, divided over 5–6 weeks. Improvement is generally apparent early during irradiation, with little further change later. Results depend on several factors, including location, tumor type, and early response. Patients who improve early during radiotherapy survive longer than those who show no change afterward.(67) After irradiation, patients with low-grade astrocytoma survive approximately 2–4 years, whereas those with glioblastoma survive no longer than 1 year.
Original pages 683–684
Thalamic Gliomas
Thalamic tumors are uncommon, accounting for approximately 3% of childhood brain tumors.(68) Most are astrocytomas, either benign or malignant, and usually arise in childhood or young adulthood. Oligodendroglioma and ependymoma are still less common.
Symptoms and signs. Manifestations vary with extension into structures adjacent to the thalamus: the basal ganglia, internal capsule, third ventricle, midbrain, corpus callosum, and hypothalamus. Details appear in Chapter 5. The commonest presentation is raised intracranial pressure with unilateral weakness and sensory loss, caused by damage to sensory fibers, thalamic nuclei, and internal capsule, together with tumor compression of the posterior third ventricle producing obstructive hydrocephalus. Headache, vomiting, blurred vision, and papilledema result. Experience shows that hemiparesis or hemiplegia is generally more prominent than sensory loss, although anatomically one might expect sensory disturbance first because the thalamus is a sensory center. Limb weakness results from internal capsule compression and progressively becomes hemiplegia when the capsule is destroyed. Patients complain of numbness in the weak limbs; this progresses to loss of every sensory modality when the tumor destroys the ventral posterolateral thalamic nucleus.(69)
Homonymous hemianopsia may result from compression of the lateral geniculate body, optic tract, or optic radiation. Some patients develop upward conjugate gaze palsy and anisocoria when the quadrigeminal plate and pretectal midbrain are compressed from above. Large tumors may produce cerebellar dysfunction—ataxia, incoordination, and nystagmus—through damage to the cerebellorubrothalamic system.(70) Confusion, memory impairment, excessive sleep, and emotional lability may also occur through destruction of the dorsomedial thalamic nucleus and its fibers to the frontal cortex.(71)
In summary, a child with progressive hemiparesis and hemisensory deficit together with raised intracranial pressure should be suspected of having a thalamic tumor, usually a thalamic glioma.
Original pages 684–685
Investigations
C.T. or MRI currently demonstrates thalamic tumors best, showing their characteristics and extension into neighboring brain structures and thus better explaining the patient's symptoms and signs. They also show hydrocephalus and other mass effects, aiding treatment planning. The tumor may be hypodense, isodense, or hyperdense, with or without calcification. When calcification is present, the tumor is a benign glioma. Most tumors become hyperdense after contrast injection.
Previously, the main investigations were carotid angiography and PEG or ventriculography. Angiographic changes usually appeared late, when the mass was large, whereas PEG or ventriculography showed the tumor while still relatively small because the thalamus adjoins the ventricles. Important angiographic changes involve the lenticulostriate, anterior choroidal, and lateral posterior choroidal arteries and the internal cerebral and thalamostriate veins. The anterior and middle cerebral arteries show no changes specific to tumors in this region. On anteroposterior views, the lenticulostriate arteries are displaced laterally and downward (Figure 6.61). The anterior cerebral artery generally remains in the midline. Upward tumor expansion may separate the pericallosal arteries. Middle cerebral branches and the angiographic point are stretched laterally. Venous changes indicating a thalamic tumor are elevation and medial inclination of the thalamostriate vein and displacement of the internal cerebral vein across the midline, while the anterior cerebral artery remains central. On lateral views, the anterior choroidal artery enlarges; its proximal part is compressed and straightened and its distal part bows posteriorly (Figures 6.60, 6.61). The lateral posterior choroidal artery forms a wider arch, and elevation of the thalamostriate vein widens the venous angle.
PEG and ventriculography are reliable investigations. A characteristic, consistently observed feature is elevation of the central and posterior floor of the lateral ventricle on the tumor side, outlining the mass. The third ventricle bows toward the opposite side, especially posteriorly. This curvature indicates a deep tumor extending into the third ventricle. Its anterior part and the lateral ventricle enlarge because of obstruction in the posterior third ventricle.
Original pages 685–687
Treatment
The thalamus is a vital, deep brain structure, and these tumors infiltrate without a clear boundary. Resection in this region is therefore considered contraindicated: it increases functional loss without allowing complete removal or cure. Most treatment consequently relies on radiotherapy. Surgery chiefly aims to obtain tissue for diagnosis and establish a ventriculoatrial or ventriculoperitoneal shunt to lower intracranial pressure from cerebrospinal fluid obstruction at the posterior third ventricle. Radiotherapy without biopsy to establish tumor type is inappropriate because the lesion may not respond, exposing the patient to irradiation without benefit. Treatment results would also be impossible to interpret. Biopsy methods are:
1. Craniotomy: transcallosal approach or transventricular approach.
2. C.T.-guided stereotactic biopsy.
The transcallosal approach enters the lateral ventricle through the corpus callosum and exposes the thalamus well whether the ventricle is small or large. Perform a posterior parietal craniotomy near the midline and separate the medial parietal surface from the falx cerebri, as in pineal tumor surgery. Incise the corpus callosum anteroposteriorly to enter the lateral ventricle and expose the thalamic tumor for straightforward biopsy.
For the transventricular approach, make a cortical incision in the posterior parietal lobe approximately 4 cm from the midline. Separate the white matter deeply toward the lateral ventricle, expose the thalamus, and take a biopsy. Hydrocephalus makes ventricular access easier.
The author has not performed C.T.-guided stereotactic biopsy but considers it suitable for deep thalamic tumors. Caution is necessary because vascular injury may cause intrathalamic hemorrhage, which cannot be controlled immediately as it can during open biopsy.
In summary, thalamic glioma is treated with radiotherapy and, when obstructive hydrocephalus is present, a shunt. Improvement may last months or years, depending on tumor malignancy.
Original pages 687–688
Ependymoma
Ependymoma is a benign tumor arising from ependymal cells, which belong to the neuroglial group. It occurs mainly in children and adolescents and originates in the ventricular walls, most often in the fourth ventricle, followed by the lateral ventricles, third ventricle, and aqueduct of Sylvius. It may grow into the ventricle or brain substance, producing symptoms according to location. It can occur in either the cerebrum or posterior fossa.
Cerebral ependymomas commonly occur in the parietal lobe and expand into the brain. Some grow to the cortical surface and extend into several lobes, as in Figure 7.42.
Figure 7.42 Ependymoma extending from the lateral ventricular wall to the brain surface in the frontoparietotemporal region.
Fourth ventricular ependymomas usually adhere to the posterior ventricular floor near the obex and extend anteriorly within the ventricle or posteriorly into the cisterna magna. They may pass through the foramen magnum into the spinal canal. At surgery, opening the dura reveals tumor filling the cisterna magna. This portion is usually well defined and easily removed. Adherence to the fourth ventricular floor is the main obstacle to complete excision because this region contains vital respiratory and cardiac centers and cranial nerve nuclei. Attempted dissection may be fatal, while the residual attachment allows tumor regrowth.
Original pages 688
Symptoms and Signs
Most manifestations are those of raised intracranial pressure because the tumor obstructs cerebrospinal fluid flow before producing localizing signs. Tumors arising in the cerebrum and expanding within brain tissue produce focal symptoms according to their location.
Fourth ventricular tumors likewise present first with raised intracranial pressure, often early because cerebrospinal fluid pathways are readily obstructed. In young children, the head frequently becomes abnormally large. Cerebellar and brain stem signs usually appear later. Extension into the spinal canal may also cause neck stiffness and spasm of the neck and shoulder muscles, producing a tilted neck with limited movement.
Original pages 688–689
Diagnosis
Before C.T. and MRI, carotid angiography was used for suspected supratentorial lesions and vertebral angiography for suspected posterior fossa tumors. If localization remained unclear, air ventriculography (Figure 6.133) or contrast ventriculography (Figure 7.43) was performed.
C.T. and MRI now provide excellent investigation, clearly showing tumor boundaries, location, size, and hydrocephalus. Angiography and ventriculography are therefore no longer performed for this purpose.
Original pages 689–690
Treatment
Because the tumor is benign, surgery aims at complete removal to prevent recurrence. Its location and size must nevertheless be considered. Sites such as the fourth ventricular floor, aqueduct of Sylvius, and third ventricle are dangerous: attempting complete removal may cause postoperative death. Establishing the diagnosis, inserting a cerebrospinal fluid shunt, and giving radiotherapy is preferable. Cerebral tumors may be very large and involve several lobes, likewise making attempted total removal highly dangerous.
Figure 7.43 Contrast ventriculogram showing a fourth ventricular tumor obstructing cerebrospinal fluid flow and producing hydrocephalus. Histology showed ependymoma. A. Lateral radiograph. B. Anteroposterior radiograph.
The following example illustrates successful surgery for a fourth ventricular ependymoma.
Original pages 690–692
Case 1: Ependymoma of the Posterior Fourth Ventricle
A 21-year-old woman presented with headache, vomiting, and blurred vision for 3 months. More recently she had slight unsteadiness to either side but could still work. Two weeks before admission she developed diplopia and worsening headache. Examination showed bilateral papilledema, right sixth nerve palsy, good limb strength, a slightly ataxic gait without consistent deviation to either side, and bilateral corticospinal tract signs. A posterior fossa tumor was diagnosed. Angiography showed hydrocephalus, and contrast ventriculography demonstrated a mass in the posterior fourth ventricle obstructing cerebrospinal fluid flow and causing marked ventricular enlargement (Figure 7.43A, B).
Tumor removal. Suboccipital craniectomy was performed. Opening the dura revealed a well-defined grayish-pink tumor filling the cisterna magna, with part extending into the spinal canal and part spreading alongside the medulla (Figure 7.44A). Structures requiring protection were i) the medulla; ii) lower cranial nerves; iii) the posterior inferior cerebellar artery; and iv) the fourth ventricular floor. Starting dissection from below was inconvenient because the mass had to be elevated with a spatula to expose the spinal cord and medulla; removing the spatula allowed it to fall back and obscure the field. Suction within the tumor was particularly inadvisable because deeper aspiration could injure the spinal cord, medulla, or ventricular floor. The author considered removal from above easier: with the patient sitting, the tumor's weight drew it downward and clearly exposed its upper margin. Complete removal was achieved without damage to the medulla or fourth ventricle (Figure 7.44B). The ventriculogram showed enlargement of the anterior half of the fourth ventricle and a clear tumor boundary. Dissection therefore began along the tumor margin adjacent to the posterior vermis to enter the ventricle. This clearly exposed the tumor boundary and ventricular floor, which was completely covered with cotton for protection. The covering was extended progressively downward as dissection proceeded inferiorly. The tumor descended under its own weight, revealing its origin at the side of the fourth ventricle. Dividing this attachment freed the mass without dissection near the spinal cord or beside the medulla (Figure 7.45).
Figure 7.44 Ependymoma of the fourth ventricle and cisterna magna. A. Before removal, showing the pinkish tumor. B. After complete removal, showing the intact fourth ventricle and brain stem.AI-enhanced and colorized image · Switch to view the originalFigure 7.45 Approach for removing an ependymoma from the fourth ventricle.
When the tumor lies high in the fourth ventricle, removal requires the method illustrated in Case 2.
Original pages 692–694
Case 2
The patient presented with raised intracranial pressure. Investigation disclosed a fourth ventricular tumor. Opening the posterior fossa revealed tonsillar herniation down to C2–3 (Figure 7.46), with no tumor visible on the cerebellar surface. Separating the tonsils exposed tumor at the foramen of Magendie. Because this opening was too small for easy access to the tumor's sides and anterior portion, the posterior vermis was divided in the midline while preserving vessels on either side (Figure 7.47). Retraction improved anterior and lateral exposure, allowing access to the anterior fourth ventricle and identification of its floor. After separating tumor from the floor, the floor must always be protected with cottonoid before suction and cutting. Proceeding gradually inferiorly and laterally permits complete removal. Tumor adherent to the ventricular floor must not be stripped off, because doing so endangers cranial nerve nuclei and the respiratory and cardiac centers. A thin adherent layer should be left in place (Figure 7.48).
Figure 7.46 Tonsillar herniation caused by a fourth ventricular tumor.Figure 7.47 Splitting the vermis exposes the fourth ventricular tumor.Figure 7.48 After tumor removal, a thin layer remains adherent to the fourth ventricular floor (short arrow). The aqueduct of Sylvius is markedly enlarged (long arrow).
Tumor extending into the cerebellar hemisphere should also be removed. Extension through the foramen of Luschka into the cerebellopontine angle should not be removed because it commonly adheres to the brain stem and cranial nerves. Tumor extending into the aqueduct of Sylvius and obstructing cerebrospinal fluid flow may, however, be removed because it does not infiltrate the aqueductal gray matter. In this second case, removal exposed a large aqueduct through which the third ventricle could be seen.
Original pages 694–695
Choroid Plexus Papilloma
Choroid plexus papilloma is a benign, slowly growing tumor arising in the choroid plexus. It is therefore intraventricular and well circumscribed, and complete surgical removal cures the disease. Its ventricular location commonly causes hydrocephalus. Despite being benign, it can be fatal if diagnosis and removal do not precede complications such as severe hydrocephalus or intraventricular hemorrhage.
Hydrocephalus may result from three factors: I) excessive cerebrospinal fluid production by the tumor; II) obstruction of cerebrospinal fluid pathways by the tumor; and III) repeated bleeding into the cerebrospinal fluid, increasing protein and causing adhesions.
Excess cerebrospinal fluid production is supported by resolution of hydrocephalus after removal of a nonobstructing intraventricular tumor.(72,73,74,75) Obstruction occurs early in the narrow third and fourth ventricles. A tumor at the lateral ventricular trigone may enlarge the temporal or occipital horn disproportionately to the rest of the ventricle. Removal restores normal cerebrospinal fluid pathways and resolves the hydrocephalus.
Some patients present with subarachnoid and intraventricular hemorrhage. If they survive the bleeding, increased cerebrospinal fluid protein, adhesions, or leptomeningeal fibrosis impair circulation and absorption, producing hydrocephalus.
Choroid plexus papilloma accounts for approximately 0.5–0.6% of all brain tumors. Most occur in children within the first 2 years of life, predominantly in the lateral ventricle. In adults they usually occur in the fourth or third ventricle.
Some lateral ventricular papillomas contain calcification, making the highly vascular mass firmer. At surgery they may resemble intraventricular meningiomas; both have a choroid plexus pedicle and receive blood from choroidal arteries. They may nevertheless be distinguished because a meningioma has a smooth rather than papillary or cauliflower-like surface, although it may be nodular, and is firmer.
Original pages 695–696
Symptoms and Signs
The commonest initial manifestation is raised intracranial pressure or hydrocephalus. Because the tumor occurs in young children, an infant may initially develop normally and later develop an enlarged head, possibly with vomiting, restlessness, or drowsiness. Older children may complain of headache. In the author's experience, all children presented with head enlargement and no focal signs. A large papilloma in one lateral ventricle may cause hemiparesis through marked enlargement of that ventricle or direct compression of the corticospinal tract. Fourth ventricular papillomas likewise present with raised intracranial pressure; cerebellar signs are uncommon until the mass is large enough to produce cerebellar and cranial nerve signs.
Intraventricular or subarachnoid hemorrhage from the tumor may cause sudden severe deterioration, followed by drowsiness or death from very high intracranial pressure.
Original pages 696–697
Diagnosis
Raised intracranial pressure, an enlarged head in a child, absence of focal neurological deficits, and increased cerebrospinal fluid protein or xanthochromia should always suggest an intraventricular tumor.
Sampling cerebrospinal fluid in choroid plexus papilloma is hazardous by either lumbar or ventricular puncture; neither is now necessary for this purpose. Lumbar puncture in raised intracranial pressure may cause tonsillar herniation. Another observed phenomenon is a rapid rise in cerebrospinal fluid pressure after fluid removal for examination or pressure relief, even when hydrocephalus had previously progressed slowly. The patient may become unconscious or die rapidly. Lowering cerebrospinal fluid pressure stimulates massive new fluid production and often causes subependymal and paraventricular petechial hemorrhages.(76)
C.T. and MRI now clearly demonstrate intraventricular tumors, displacing older investigations. Before C.T., the investigative sequence was as follows:
1. Skull radiographs show changes from raised intracranial pressure: sutural separation, head enlargement, and sometimes calcification. These are not specific to choroid plexus papilloma.
2. AIR CONTRAST STUDIES. Air introduced into the ventricle outlines the white tumor against the dark air. This demonstrates its boundaries fairly clearly (Figure 6.133) and was considered a specific investigation for intraventricular tumors, but is now rarely performed.
3. CEREBRAL ANGIOGRAPHY. This is not particularly helpful for precise tumor boundaries or localization. It shows hydrocephalus and the feeding vessels, helping surgical removal with less blood loss. Tumor staining may be visible. Angiography is difficult and hazardous in small children and is therefore seldom performed.
4. C.T. The tumor is clearly seen both before and after contrast because its intraventricular density differs from cerebrospinal fluid. It is isodense on unenhanced C.T. and becomes strikingly hyperdense with enhancement.(77) (Figure 7.52.) C.T. shows the boundaries, size, location, and hydrocephalus and is therefore the best diagnostic method.
5. MRI demonstrates location, boundaries, size, and hydrocephalus as well as C.T.
Original pages 697–698
Treatment
The best treatment for choroid plexus papilloma is complete surgical removal with minimal injury to neighboring brain tissue. Because the tumor is benign, complete removal is curative. Partial removal followed by radiotherapy is ineffective.
Tumor removal. Operative techniques and complications differ somewhat with the tumor's location, as follows.
Original pages 698–699
1) Choroid Plexus Papilloma of the Fourth Ventricle
For a fourth ventricular choroid plexus papilloma, perform suboccipital craniectomy without extensive lateral exposure because the tumor is within the ventricle. Before opening the dura, release cerebrospinal fluid through a ventriculostomy to lower intracranial pressure. Tumor seldom protrudes externally when the dura is opened because it obstructs cerebrospinal fluid pathways before becoming very large. The key to removal without major blood loss is division of the vessels supplying the choroid plexus. These arise from the posterior inferior cerebellar artery (PICA). The choroid plexus lies at the posterior velum of the fourth ventricle. Separate and elevate the cerebellar tonsils to expose PICA medially between the tonsil and medulla. Following the arteries distally brings the two PICAs close together. Divide the uvula and nodulus of the vermis in the midline to expose the posterior velum. Here the choroidal artery branches from PICA before PICA turns laterally to supply the vermis and cerebellar hemisphere (Figure 7.49); PICA must be preserved during surgery. In choroid plexus papilloma, the choroidal arteries are enlarged and prominent and form the tumor pedicle. Coagulate them with bipolar forceps and divide them on both sides. The tumor immediately shrinks. It can then be removed easily without blood loss. This method permits complete removal in every case because the papilloma has a choroid plexus pedicle and a clearly defined boundary all around. Direct suction and cutting to debulk the tumor before dividing its feeding vessels is particularly inadvisable: it causes substantial bleeding and obscures vital structures, including the medulla, cranial nerves, and fourth ventricular floor.
Figure 7.49 Choroid plexus of the fourth ventricle (long arrow) and its arterial supply (short arrow).
Original pages 699
2. Choroid Plexus Papilloma of the Lateral Ventricle
Tumors in this ventricle can be subdivided by location: the frontal horn adjacent to the foramen of Monro, the body of the lateral ventricle, and the trigone. The trigone is the most frequent site. Each location requires knowledge of the relevant cerebral anatomy and a somewhat different operative technique. The approaches may therefore be classified by tumor location as follows.
Original pages 699–700
2.1 Papilloma of the Trigone
The two common tumors in the trigone are choroid plexus papilloma and meningioma. Other tumors, including ependymoma, astrocytoma, and epidermoid tumors, may also occur here. Meningioma is more common than papilloma. These tumors are supplied chiefly by the anterior choroidal artery and sometimes also by the posterior choroidal artery, as demonstrated by carotid and vertebral angiography. These vessels are usually not greatly enlarged and are tortuous.
Important anatomical structures that must always be considered when operating here are the sensory speech center (Wernicke's or perceptive speech center) in the dominant hemisphere, the optic radiation, the tail of the caudate nucleus, and the pulvinar of the thalamus. Any approach must account for their functions and minimize functional loss. Several routes are available. However, these tumors are often large because the ventricular location is a silent area, producing no focal symptoms, and surgery is therefore difficult. Except for small tumors, no approach is completely satisfactory for exposing every part of the tumor and its feeding vessels through a single cortical incision.
Operative technique. Three approaches to trigonal tumors are commonly used (Figure 7.50).
AI-enhanced and colorized image · Switch to view the originalFigure 7.50 Cortical incisions for approaching the choroid plexus at the trigone of the lateral ventricle. 1. Lateral parietotemporal incision. 2. Posterior middle temporal gyrus incision. 3. Posterior parieto-occipital paramedial incision.
Original pages 700–701
2.1.1 Lateral Parietotemporal Approach
This provides easy access to a trigonal tumor because only a thin layer of brain separates the cortex from the tumor. It has three disadvantages.
First, in the dominant hemisphere it causes postoperative dysphasia through damage to the angular and supramarginal gyri of the temporoparietal lobe, the location of the sensory speech center.
Second, part of the optic radiation is damaged because the incision crosses its fibers perpendicularly as they run toward the occipital lobe, causing a homonymous quadrantanopia.
Third, a large tumor obscures the anterior and posterior choroidal arteries. Early division of these vessels to reduce the tumor's blood supply is difficult. Piecemeal removal may therefore cause heavy, uncontrollable, and potentially fatal blood loss.
Original pages 701–702
2.1.2 Posterior Middle Temporal Gyrus Incision
The incision is made in the posterior portion of the middle temporal gyrus (Figures 7.50 and 7.51). This gives good access to the tumor and anterior choroidal artery, allowing easy interruption of the tumor's blood supply. Removal is therefore safe, with little blood loss and no injury to neighboring structures. Possible disadvantages include postoperative homonymous quadrantanopia, probably less extensive than with the first approach because the incision runs parallel to the optic radiation fibers. In the dominant hemisphere, some speech disturbance may still occur.
Figure 7.51 A cross-section of the brain showing the choroid plexus at the trigone and the approaches. 1. Posterior middle temporal gyrus incision. 2. Posterior parieto-occipital paramedial incision.
Original pages 702–704
2.1.3 Parieto-occipital Paramedial Incision
This is the safest approach, particularly for a tumor in the dominant hemisphere, because it avoids the optic radiation, which runs inferolaterally in the parietal lobe, and the sensory speech center. The cortical incision is made at the level of the parieto-occipital fissure, approximately 3–4 cm from the midline, and extends about 4 cm anteriorly (Figures 7.50 and 7.51). It provides access to feeding vessels, especially the posterior choroidal artery approaching medially. However, the anterior choroidal artery is less accessible than with the first two approaches because it lies lateral and inferior to the tumor. Ventricular enlargement from hydrocephalus permits the tumor to be turned to expose the vessels.
Thus, no single approach is best for removing a trigonal papilloma. The surgeon should be skilled in all the approaches described and thoroughly understand the anatomy and functions of this region. The operation must be individualized according to tumor location, size, feeding vessels, and vascularization demonstrated by C.T. and angiography. If necessary, more than one approach may be combined to interrupt both the anterior and posterior choroidal arterial supply completely. Complete, safe removal without blood loss is then possible. Nevertheless, even an easily removed tumor may be followed by fatal complications, which require careful attention and prevention, as the following case illustrates.
Case example. An 18-month-old child had progressive head enlargement for approximately six months and a right squint for one month. Examination showed hydrocephalus and a right sixth nerve palsy, without other focal signs. C.T. showed a mass at the trigone of the left lateral ventricle and marked hydrocephalus (Figure 7.52).
Figure 7.52 C.T. showing a choroid plexus papilloma at the trigone in an 18-month-old child.
The tumor was within the left lateral ventricle of the dominant hemisphere, clearly circumscribed, and extended into the occipital horn. The images suggested that the glomus of the choroid plexus, or tumor pedicle, would be readily visible through a parieto-occipital paramedial incision. A parieto-occipital craniotomy was therefore performed, and the dura was opened after partial cerebrospinal fluid drainage. The cortical incision was placed as described above. On entering the ventricle, a pink-red tumor was seen. Slight rotation exposed the choroid plexus and feeding vessels. Cottonoids covered the ventricular passage toward the frontal horn to prevent blood entering the horn and obstructing the foramen of Monro. The vessels passing from the choroid plexus into the tumor were coagulated with bipolar forceps and divided. The tumor immediately shrank and was removed without any blood loss. After complete removal and partial suction of cerebrospinal fluid, the brain collapsed markedly because the ventricle was very large. Multiple bridging veins tore, causing sudden, widespread subdural hemorrhage. The bleeding sites could not be found. The child went into shock and died.
This case shows that selecting the correct approach can make tumor removal straightforward. However, choroid plexus papilloma may cause hydrocephalus with extreme ventricular enlargement, as in this child. Excessive cerebrospinal fluid drainage should therefore be avoided. Saline should be maintained within the ventricle to prevent excessive collapse. This error regrettably cost the child's life.
Original pages 704
2.2 Choroid Plexus Papilloma of the Body of the Lateral Ventricle
The tumor may arise in the middle of the ventricular body or near the foramen of Monro and extend into the frontal horn. Papillomas in the body are difficult to remove because nearby motor and sensory fibers place these functions at risk. The choroid plexus and papilloma are usually supplied by the posterior choroidal artery. As the tumor grows, it obstructs cerebrospinal fluid flow from the temporal and occipital horns, which consequently tend to enlarge more than the other ventricular portions.
Tumor removal. A cortical incision directly through the motor or sensory cortex should be avoided because it causes disability. Either of the following two approaches may be used.
Original pages 704–706
2.2.1 Middle Frontal Gyrus Incision
An incision is made in the posterior middle frontal gyrus, anterior to the motor cortex, toward the ventricle (Figure 7.53). This is suitable for a tumor in the anterior ventricular body, adjacent to the foramen of Monro, or extending into the frontal horn. Make a 3–4 cm incision along the gyrus and separate the white matter toward the ventricle. If C.T. shows marked ventricular enlargement, proceed straight inward; with less enlargement, direct the approach slightly medially. Within the ventricle, the septum pellucidum forms the medial wall, the caudate nucleus lies laterally, and the thalamus lies below, with the thalamostriate vein between the latter two structures. The interventricular foramen of Monro lies inferiorly and leads into the third ventricle. Its anterior border is the fornix and its posterior border is the thalamus. The choroid plexus runs into the foramen. As elsewhere, gently rotate the tumor to expose the choroid plexus at the foramen of Monro, then follow it posteriorly along the floor of the lateral ventricle. Coagulate with bipolar forceps and divide the tumor's feeding vessels within the choroid plexus. Usually the very large ventricle permits the tumor to be rotated or displaced sufficiently to expose the plexus. In a very large tumor, such as the papilloma at the foramen of Monro shown in Figure 7.54, the ventricle is markedly enlarged, yet entry through a posterior middle frontal gyrus incision may reveal neither the choroid plexus nor its tumor-feeding vessels. In this situation, use bipolar coagulation and remove small portions of tumor until the choroidal vessels can be seen; this is sufficient. Blood loss is relatively slight with this method. Direct suction of the tumor should be avoided because it causes substantial bleeding. After coagulation and division of the choroidal vessels, the remaining papilloma immediately shrinks and can easily be removed as a whole. Ensure that the choroid plexus attached to the tumor has been completely divided, since traction on an undivided attachment may cause further bleeding.
AI-enhanced and colorized image · Switch to view the originalFigure 7.53 Approaches to a tumor in the body of the lateral ventricle. 1. Middle frontal gyrus approach. 2. Transcallosal approach.Figure 7.54 Contrast ventriculogram showing a large tumor within the body of the lateral ventricle.
Original pages 706–707
2.2.2 Transcallosal Approach
This approach is suitable for tumors in the middle of the lateral ventricular body because it avoids incisions through motor and sensory cortex and the resulting loss of function. It is also suitable for tumors extending into both ventricles (Figure 7.55). Preoperative cerebral angiography should include the venous phase to locate the large veins draining into the superior sagittal sinus. This helps position the craniotomy so that brain retraction does not damage these veins.
AI-enhanced and colorized image · Switch to view the originalFigure 7.55 Approach to a tumor in the body of the lateral ventricle through the corpus callosum (transcallosal approach).
Technique. Position the patient supine with the head facing straight ahead. Place the posterior craniotomy margin approximately 3 cm behind the coronal suture and the anterior margin 5 cm in front of it. Extend the medial margin slightly across the midline to the opposite side. After draining ventricular cerebrospinal fluid, open the dura with its flap based on the superior sagittal sinus. Approach the corpus callosum at a site without a large bridging vein entering the sinus. Occasionally a less important bridging vein must be divided to allow greater lateral retraction of the medial frontal lobe. Gently separate the frontal lobe from the falx cerebri with a self-retaining retractor. The cingulate gyrus and pericallosal artery will be seen over the corpus callosum; protect them carefully. Bring in the microscope at this point. After adequately retracting these structures laterally, incise the corpus callosum approximately 3 cm from the genu and extend the incision posteriorly for about 3 cm. Keep it 0.5–1 cm off the midline to avoid the bodies of the fornices, which lie close together beneath the middle of the corpus callosum. Injury to the fornix may impair memory. Passing through the corpus callosum enters the ventricle. Tumor removal follows the principles already described: expose, coagulate, and divide the feeding vessels first, then remove the tumor completely in pieces. The thalamostriate and septal veins must also be preserved.
Original pages 707–708
Results of Treatment of Choroid Plexus Papilloma
If the tumor is completely removed before the brain is damaged by hydrocephalus, a very large mass, or spontaneous hemorrhage, the results are excellent. The patient is cured, with normal cerebral development and function, because the tumor is benign and well circumscribed. Hydrocephalus due to excess cerebrospinal fluid production by the papilloma or obstruction of cerebrospinal fluid pathways resolves after tumor removal. However, when spontaneous tumor hemorrhage also contributes to hydrocephalus, adhesive obstruction of the basal cisterns and subarachnoid space may leave persistent hydrocephalus after removal. Some patients require a cerebrospinal fluid shunt for its resolution.
Results are poor for malignant papilloma because it infiltrates without clear boundaries and is difficult to remove completely. Surgery therefore cannot cure it, and radiotherapy does not change the outcome.
Postoperative radiotherapy is unnecessary for papilloma because it is benign and can be completely removed.
Original pages 708
MEDULLOBLASTOMA
Medulloblastoma is a malignant cerebellar tumor accounting for approximately 20% of intracranial tumors in children. It occurs most often between ages 3 and 8 years.(78) It is occasionally seen in older children and very rarely in adults.
Location. As described in the pathology chapter, medulloblastoma arises in the cerebellar midline, the vermis, originating in the roof of the fourth ventricle at the posterior medullary velum. Its growth compresses and destroys the vermis, which appears broadened and pale at operation (Figure 7.57). Larger tumors extend into the cerebellar hemispheres. Most commonly, the tumor grows into and fills the fourth ventricle. It frequently extends downward into the cisterna magna and upper cervical spinal canal.
Medulloblastoma grows rapidly and tends to disseminate tumor cells through the cerebrospinal fluid pathways. After its removal, tumor deposits are frequently found throughout the central nervous system, including the spinal subarachnoid space, cauda equina, cisterns, and surfaces of the cerebellum and cerebrum. It is therefore a highly malignant posterior fossa tumor.
Original pages 708–709
Symptoms and Signs
The symptoms and signs of vermian tumors described in Chapter 5 may occur with a large medulloblastoma. Because it arises in the roof of the fourth ventricle, its characteristic clinical features are truncal ataxia and relatively rapid development of raised intracranial pressure from obstruction of cerebrospinal fluid flow at the fourth ventricle or aqueduct. Patients tend to fall forward or backward while sitting or standing, although limb incoordination may be absent or slight when examined lying down. Horizontal nystagmus may be absent but can appear when the tumor extends into a cerebellar hemisphere. Sudden deterioration sometimes follows hemorrhage or hydrocephalus with herniation.
Vomiting and headache are common. Vomiting results from raised intracranial pressure and pressure on the vomiting center in the floor of the fourth ventricle. It often occurs on waking in the morning: during sleep, respiration slows, PCO2 rises, and cerebral venous return is less efficient than in the upright position, raising intracranial pressure. Patients feel better after vomiting because subsequent hyperventilation lowers the pressure. The same explanation applies to headache that is worst on waking or late at night, sometimes severe enough to awaken the patient, and disappears or improves after vomiting. Headache progressively worsens as the mass enlarges or cerebrospinal fluid obstruction increases. Young children may develop head enlargement, usually not very marked because the rapidly growing medulloblastoma produces symptoms before substantial enlargement occurs.
Original pages 709
Diagnosis
Accurate diagnosis from the history and clinical signs alone may be difficult. Nevertheless, the patient's age, signs localizing the lesion to the vermis, relatively rapid symptom development, and raised intracranial pressure should suggest medulloblastoma before other tumor types. Definitive diagnosis requires examination of removed tumor tissue.
Original pages 709–710
Investigations
C.T. is important for suggesting the diagnosis. Medulloblastoma usually appears as a large, round, well-circumscribed hyperdense mass in the middle of the cerebellum, filling the fourth ventricle (Figure 6.102a). Contrast produces marked, uniform enhancement throughout the tumor.(79) On C.T., the absence of cysts and calcification distinguishes medulloblastoma from ependymoma, astrocytoma, and hemangioblastoma,(79) although very large tumors may contain multiple cysts (Figure 7.56).
MRI also shows the tumor very clearly. It is hypointense relative to brain on T1-weighted images and hyperintense and homogeneous on T2-weighted images.(80)
Angiography shows displacement of PICA and its branches and sometimes faint tumor staining, together with features of hydrocephalus. Skull radiographs show changes from raised intracranial pressure, such as separation of the sutures. Neither angiography nor skull radiography is now performed for this purpose, because they fail to show the mass clearly; C.T. or MRI gives much better results.
For dissemination into the spinal subarachnoid space, MRI is the best method of visualizing tumor deposits. If MRI is unavailable, myelography can also demonstrate spinal tumors.
Original pages 710–714
Treatment
The current standard treatment for medulloblastoma is surgical removal followed by irradiation of the entire neuraxis, because the tumor spreads through cerebrospinal fluid and is radiosensitive. Surgery establishes the tumor type and reopens cerebrospinal fluid pathways, allowing obstructive hydrocephalus to resolve without shunting. Shunting in medulloblastoma carries a risk of disseminating tumor cells to other parts of the body. Removal also relieves pressure on the brainstem and cerebellum. The operative options currently used are:
1. Removal of all visible tumor (radical resection), followed by radiotherapy.
2. Partial resection to relieve pressure on surrounding brain and reopen cerebrospinal fluid pathways, followed by radiotherapy.
3. Biopsy and ventriculoperitoneal shunting, followed by radiotherapy.
All three methods have advantages and disadvantages.
Total resection. Attempting complete removal in the fourth ventricle is very hazardous and has high mortality. Survivors, however, live longer and remain symptom-free longer than after other operations. Comparing total with partial resection, Raimondi and Tomita(81) reported one-year survival of 92% and five-year survival of 42% after total removal. After partial removal, survival was shorter: 65% at one year and only 30% at five years.
Technique. The author most often uses the sitting position, although lateral, semiprone, or prone positioning is also possible. Sitting offers good exposure at eye level but has the disadvantages and potential complications already described. Make a midline incision and a moderately wide suboccipital craniectomy. Extensive lateral exposure is unnecessary because the tumor is in the cerebellar midline. After opening the dura, tumor may protrude through the foramen of Magendie, or it may remain hidden behind a bulging, broadened vermis. Sometimes gray-pink sheets of disseminated tumor cover the cerebellar hemispheres and tonsils (Figure 3.51). This is characteristic of medulloblastoma; tumor cells may already have disseminated into the cisternal and spinal cerebrospinal fluid. For this reason, postoperative irradiation of the entire neuraxis is advisable.
To expose the tumor, divide the inferior vermis in the midline while preserving PICA branches and veins, and separate the two sides. The length of the vermian incision depends on tumor size. Before resection, cover the subarachnoid space around the medulla with cotton to prevent tumor cells entering the spinal subarachnoid space. If the tumor can be lifted from the fourth ventricular floor, cover the floor with cotton before cutting the tumor to protect this part of the brain. The tumor is gray-pink, soft, and easily aspirated. Suction combined with bipolar coagulating forceps permits complete removal. Begin internally to reduce tumor bulk and make its margins clearer, then remove the remainder. Where tumor involves important structures such as the dentate nucleus or cerebellar peduncles, complete removal may be dangerous or disabling. If frozen section confirms medulloblastoma, these portions may be left for destruction by radiotherapy. Highly vascular residual tumor, however, may bleed postoperatively and cause death. In such cases, only complete removal ensures that no postoperative hemorrhage arises from residual tumor.
Complete removal of a very large medulloblastoma, or any other large tumor, may itself cause fatal complications. A two-year-old child presented with a one-year history of head enlargement. During the preceding three months, gait had become unsteady, progressing to inability to sit or stand without falling forward or backward. Examination and C.T. showed a very large vermian tumor with hydrocephalus. The tumor was completely removed. Both cerebellar hemispheres then collapsed downward; the operation was being performed in the sitting position. All the bridging veins draining into the transverse sinus became stretched and eventually tore, causing a subdural hematoma and cerebellar swelling. The child died from brain swelling. This experience led the author subsequently to operate with the patient lying down rather than sitting and to favor partial rather than attempted complete resection when frozen section identifies medulloblastoma.
Partial resection. Its aims are: i) to reduce tumor bulk and brain compression; ii) to establish the tumor type; and iii) to reopen cerebrospinal fluid pathways. It is appropriate for very large medulloblastomas such as the example on C.T. (Figure 7.56), filling the vermis and fourth ventricle and compressing the cerebellar hemispheres.
Technique. Expose the posterior fossa as in the first method, but remove bone widely around the exposure and also remove the atlas arch to aid decompression. After opening the dura, tumor is seen on the vermian surface, spreading widely and severely compressing the cerebellar hemispheres. It extends into the cisterna magna as far as C1 (Figure 7.57). Attempted complete removal would be very dangerous, so only partial resection is performed. First coagulate and divide surface vessels, then open a moderately wide window into the tumor. Use suction and bipolar coagulation to remove it from within toward its margins. This reduces fourth ventricular compression and may restore a passage for cerebrospinal fluid. Tumor in the cisterna magna may be an extension of the mass above; if separable from the medulla, remove it to open the foramen of Magendie and permit cerebrospinal fluid flow. In other cases, disseminated cells have grown to cover the entire medulla. Do not attempt to remove this portion because of the extreme danger; use radiotherapy. Biopsy alone may suffice in such a case, followed by radiotherapy once medulloblastoma is confirmed. Even with biopsy alone, a wide craniectomy and dural opening decompress the posterior fossa and reduce brainstem compression. Some patients require a ventriculoperitoneal shunt to relieve obstructive hydrocephalus and improve comfort during radiotherapy.
Figure 7.56 C.T. showing a very large vermian tumor extending into both cerebellar hemispheres, with hydrocephalus.Figure 7.57 Operative view of a large vermian tumor. Histological examination identified medulloblastoma.
Original pages 714–715
Radiotherapy
Medulloblastoma is particularly radiosensitive. Every patient should therefore receive radiotherapy after surgery and histological confirmation. Irradiation without a tissue diagnosis should not be performed, because some cerebellar tumors can be cured by surgery alone.
Radiotherapy should follow surgical relief of posterior fossa pressure and hydrocephalus. Irradiation before decompression may be dangerous because the resulting reactive brain swelling further increases intracranial pressure. Starting irradiation without first relieving pressure also loses valuable time for preventing pressure-related optic nerve damage. If raised pressure persists during almost a month of radiotherapy, the patient may become blind. Because medulloblastoma tends to disseminate through cerebrospinal fluid, particularly after surgery, irradiation must encompass both the head and spine along the entire neuraxis.
The current neuraxis irradiation schedule gives 5400 rads to the posterior fossa, 4000 rads to the rest of the brain, and 3500 rads to the spinal cord.(82)
Original pages 715
Results of Treatment
Patients with medulloblastoma improve immediately after surgery and radiotherapy. If neither the tumor nor the operation has impaired brain function, they can return to work. Nevertheless, even after complete removal and full radiotherapy, the tumor invariably recurs. A review of recent reports covering patients of all ages treated with surgery and irradiation gives a five-year survival rate of approximately 60%. Following complete resection and a full course of radiotherapy, five-year survival reaches 77%.(82) It is generally accepted that postoperative radiotherapy prolongs survival by approximately 1–2 years compared with surgery alone.
Original pages 715–716
Treatment of Recurrent Tumor
Recurrent medulloblastoma has three treatment options: I) repeat surgical removal; II) radiotherapy; or III) surgery followed by radiotherapy. The choice depends on the patient's general condition and neurological impairment, the location and size of recurrence, the radiation dose already given, and the interval since initial treatment. Recurrent symptoms always require repeat C.T. or MRI to guide treatment. If there is a localized mass and the patient can tolerate surgery, repeat removal is advisable. If the patient's condition precludes surgery, radiotherapy is preferable and often improves symptoms.
Original pages 716
PINEAL GLAND TUMORS
Tumors in the pineal region include those arising from the pineal gland itself—pineocytoma, pineoblastoma, pinealoma (germinoma), teratoma, and carcinoma—and tumors of nearby structures. These include the quadrigeminal plate, upper midbrain, posterior third ventricle, and splenium of the corpus callosum, usually astrocytomas, ependymomas, or choroid plexus papillomas. These tumors are appropriately considered together because they produce similar symptoms, signs, and treatment problems.
Original pages 716–717
Symptoms and Signs
Patients with pineal gland tumors have three groups of symptoms and signs:
1. Raised intracranial pressure from hydrocephalus: headache, vomiting, papilledema, and head enlargement in young children.
2. Compression of the quadrigeminal plate produces important localizing signs, including Parinaud's syndrome: paralysis of upward conjugate gaze, dilated pupils unreactive to light (reflex iridoplegia), deafness, and an ataxic gait.
3. Hypothalamic dysfunction results from hypothalamic destruction by an ectopic suprasellar pinealoma or from hydrocephalus. Manifestations include diabetes insipidus, hyperthermia, cachexia, and precocious puberty.
These manifestations were described in detail in Chapter 5.
Original pages 717–718
Diagnosis
A pineal gland tumor can be diagnosed confidently when focal signs indicate damage to the quadrigeminal plate. Most patients present with raised intracranial pressure, and examination reveals Parinaud's phenomenon. Hypothalamic symptoms may or may not coexist. If hypothalamic symptoms are the presenting complaint, suprasellar disease must first be excluded.
Other investigations supporting diagnosis include skull radiographs, contrast ventriculography, and angiography. These methods are now obsolete for this purpose, with C.T. and MRI remaining in use.
1. Skull radiographs show two important changes: signs of raised intracranial pressure and calcification in the pineal region. A calcified pineal gland is not normally found in children, so calcification here should suggest a pineal tumor. It does not, however, identify the tumor type.
2. VENTRICULOGRAPHY establishes the diagnosis by demonstrating hydrocephalus and outlining the tumor in the posterior-superior third ventricle. The aqueduct of Sylvius is usually not seen; if visible, it is displaced downward.
3. VERTEBRAL ANGIOGRAPHY shows characteristic elevation of the posterior choroidal artery, best seen in the lateral view (Figure 6.63). As the tumor grows upward, the great vein of Galen, normally bowed downward, is displaced upward (Figure 6.62). Tumor staining is sometimes visible. Angiography also helps distinguish an aneurysm of the great vein of Galen, which must be recognized before surgery.
4. C.T. is excellent for diagnosing pineal-region tumors. Marked contrast enhancement clearly demonstrates their size and margins, as well as hydrocephalus and calcification (Figure 6.114). It may show ventricular dissemination or simultaneous ectopic pinealoma and a pineal-gland pinealoma (Figure 6.115).
5. MRI also clearly demonstrates tumor margins and hydrocephalus. The tumor is isointense on both T1- and T2-weighted images. Sagittal images are particularly useful in pineal-region disease, showing the relationships to the quadrigeminal plate, splenium, third ventricle, and vein of Galen.(83) Unlike C.T., MRI does not demonstrate calcification.
Original pages 718–719
Treatment
Several treatments are available for pineal gland tumors, depending on tumor type and size. Germinoma, pineocytoma, and pineoblastoma are radiosensitive. If tissue examination identifies one of these types, radiotherapy gives good results. Teratomas are radioresistant; irradiation is ineffective, and surgical removal is required. Complete removal of a large tumor, however, is difficult and highly dangerous.
The treatment options are:
1. Complete surgical removal, particularly for a benign, well-circumscribed teratoma, which is curable by total excision.
2. Biopsy or partial resection to reduce the mass and obtain a histological diagnosis, followed by a ventriculoatrial or ventriculoperitoneal shunt for hydrocephalus. Germinoma or pineoblastoma is then treated with radiotherapy; radioresistant tumors are not irradiated.
3. Ventriculoatrial or ventriculoperitoneal shunting followed by radiotherapy without surgical tissue diagnosis, relying instead on the location, common tumor types in this region, and appearances on C.T. and MRI, with subsequent C.T. monitoring. This approach is not particularly well justified, since it may expose the patient to irradiation without benefit.
Original pages 719–720
Surgical Removal of PINEAL GLAND Tumors
Complete removal of a pineal gland tumor is extremely difficult, hazardous, and associated with high mortality. Postoperative disability is frequent because the tumor adheres closely to the internal cerebral veins, great vein of Galen, basal veins of Rosenthal, quadrigeminal plate, aqueduct of Sylvius, third ventricle, and superior cerebellum, while the operative corridor is narrow. Consequently, complete removal has been possible in very few patients. The microscope and microsurgical instruments now permit total excision in a higher proportion. Several approaches are available; selection depends on the tumor's character, size, and location. Sagittal MRI clearly shows its position, size, and direction of growth and helps choose the approach. Three principal routes are used (Figure 7.58).
AI-enhanced and colorized image · Switch to view the originalFigure 7.58 Approaches to pineal gland tumors. 1. Parietal interhemispheric approach. 2. Occipital transtentorial approach. 3. Infratentorial supracerebellar approach.AI-enhanced and colorized image · Switch to view the originalFigure 7.59 Parietal interhemispheric approach to a pineal gland tumor. Note the division of the splenium of the corpus callosum and tentorium.
This is suitable for tumors extending upward and bulging into the posterior third ventricle (Figure 7.59).
Technique. Seat the patient with the head moderately flexed and the body slightly reclined to place the tentorium horizontally. Make a right paramedian scalp incision approximately 1–1.5 inches from the midline, or a horseshoe incision. Reflect the scalp and perform a parieto-occipital craniotomy extending approximately 2 cm across the sagittal suture to the left. Before opening the dura, drain cerebrospinal fluid through a previously placed ventriculostomy to lower intracranial pressure; hydrocephalus is invariably present. Open the dura with its flap based on the sagittal sinus. Protect the relatively large parietal bridging veins. Gently separate the medial posterior parietal surface from the falx where no bridging vein is present. Some small, less important bridging veins may be coagulated and divided to widen retraction. Retract the parietal lobe with a self-retaining retractor until the splenium and tentorium are visible. Drainage of the hydrocephalic ventricles allows them to collapse, providing broad pineal exposure without excessive brain retraction. Incise the tentorium approximately 1 cm from the midline straight sinus, extending 3–4 cm posteriorly, and retract both edges with sutures. The great vein of Galen, posterosuperior to the tumor and running upward, becomes visible, with the cerebellum behind the tumor. Divide and separate the splenium along the midline for approximately 3 cm. Protect the internal cerebral veins on either side of the midline beneath the splenium, closely applied to the tumor's superior surface. The opaque white arachnoid membrane here must be divided to reveal these veins. The basal vein of Rosenthal lies lateral to the tumor. Open the tumor surface between the basal and internal cerebral veins, or behind the basal vein, where no major vessels lie. Aspirate, coagulate, and cut the tumor in small pieces from within toward its surface, reducing its size enough to separate its wall from the vessels. Do not attempt removal as a single intact mass, which is highly dangerous. In some cases, the microscope and microsurgical instruments permit complete removal.
The disadvantage is the narrow operative corridor. With the usual right-sided approach, only the central and right portions of the tumor and veins are readily visible. The left side and its veins are difficult to see because the lower falx edge, containing the inferior sagittal sinus, obstructs the view. Furthermore, the tumor's arterial supply from the posterior choroidal artery becomes visible only late in the operation and may be injured.
This is suitable for tumors extending posteriorly, compressing the cerebellum and displacing the splenium upward (Figure 7.60).
AI-enhanced and colorized image · Switch to view the originalFigure 7.60 Occipital transtentorial approach to a pineal gland tumor.
Technique. Use the sitting position with the occipital pole elevated so that little force is needed to separate the occipital lobe from the falx and tentorium. Perform a right craniotomy over the occipital pole and posterior parietal lobe. Extend it widely laterally to prevent the bone edge compressing the brain during lateral retraction. Medially, expose the superior sagittal sinus. After cerebrospinal fluid drainage, open the dura with its flap based beside the sinus. Gently retract the occipital pole and medial surface away from the falx and tentorium. Coagulate and divide the one or two occipital bridging veins usually draining into the lateral sinus. Once the tentorium is visible, use the operating microscope. There is no need for excessive retraction to expose the splenium. Incise the tentorium approximately 1 cm from the straight sinus for about half its length and suspend its edge with sutures. The superior cerebellar surface, great vein of Galen, and tumor become visible. Avoid touching this vein.
To approach the tumor, separate the cerebellum from the vein of Galen by dissecting the arachnoid close to the cerebellum. Do not dissect immediately beside the vein, which may tear. The arachnoid is thick, tough, and opaque centrally but thinner and easier to separate laterally. Continue laterally to the cleft between the tumor and thalamic pulvinar. During cerebellar dissection, the precentral vein entering the vein of Galen may be divided without loss of cerebellar function. This widens exposure as the cerebellum drops away from the vein of Galen. The tumor is then framed by the veins: the vein of Galen above and posteriorly, the basal vein of Rosenthal laterally, and the internal cerebral vein above. The tumor hides the third ventricle and quadrigeminal plate. These veins must not be torn or occluded by coagulation, as this may be fatal.
If the tumor is well circumscribed and noninfiltrative, begin resection at its posterior-right surface between the cerebellum and vein of Galen. Aspirate, coagulate, and cut from within outward to markedly reduce its bulk before separating the wall. The posterior choroidal artery is seen laterally near the pulvinar. Divide only its tumor-feeding branches.
With a very large tumor, only debulking may be possible. Do not attempt complete removal at the risk of disability or death.
For an infiltrative tumor, perform biopsy or partial resection and determine its histological type. Follow with radiotherapy if it is radiosensitive.
Original pages 723–725
3. INFRATENTORIAL SUPRACEREBELLAR APPROACH
This is suitable for tumors extending posteriorly and compressing the cerebellum, quadrigeminal plate, and aqueduct of Sylvius, with most of the mass below the tentorial edge (Figure 7.61).
AI-enhanced and colorized image · Switch to view the originalFigure 7.61 Infratentorial supracerebellar approach to a pineal gland tumor.
Technique. Seat the patient with moderate neck flexion and the body leaning forward to bring the pineal gland into the surgeon's line of sight. Through a midline incision, perform a suboccipital craniectomy extending above the lateral sinuses and torcular Herophili and inferiorly to the foramen magnum. Drain ventricular cerebrospinal fluid through a previously placed ventriculostomy before opening the dura. Avoid tearing cerebellar bridging veins, except that those at the vermis and upper cerebellar hemispheres near the midline may be coagulated and divided. Gravity then allows the cerebellum to fall away from the tentorium,(87,86) widening the operative field without brain retraction. Upward tentorial retraction widens it further. Bring in the microscope, then dissect the arachnoid and remove the tumor as described for the second approach, beginning posteriorly.
This approach usually avoids injury to important brain structures, and no vein lies directly across the route to the tumor. Its disadvantage is poor access to extension into the third ventricle. In some patients, the tentorial edges obscure the superolateral tumor. It is therefore best suited to small tumors. Cerebellar swelling and postoperative ataxia may occasionally result from impaired venous drainage.
Original pages 725
ACOUSTIC NEURINOMAS
These benign tumors arise from Schwann cells surrounding the vestibular division of the eighth cranial nerve and are the commonest tumors of the cerebellopontine angle. They are usually unilateral but may be bilateral, particularly in von Recklinghausen's disease. They most often occur in middle age.
Original pages 725–727
Symptoms and Signs
Acoustic neurinomas have a distinctive clinical presentation, making diagnosis relatively straightforward after a careful history and examination. As discussed in Chapter 5, important structures in the cerebellopontine angle include cranial nerves V, VII, VIII, IX, X, and XI; the brainstem, cerebellum, and cerebellar peduncle; and the fourth ventricle and its outlets. Symptoms and signs reflect dysfunction of these structures.
Because these tumors grow very slowly, symptoms develop gradually. For clarity, their course may be divided into four stages.
Stage 1. Initial symptoms involve the eighth cranial nerve. Since the tumor arises from the vestibular nerve, patients experience vertigo and impaired balance, often after rapid changes in position. Episodes are brief, resolve, and recur. Tinnitus follows, with progressively diminished hearing on the tumor side until deafness develops, indicating cochlear nerve compression. The character of tinnitus varies between patients; it may be continuous or intermittent and disappears when the ear becomes completely deaf. Besides vertigo, tinnitus, and progressive hearing loss, some patients have dysesthesia or pain in the ear and mastoid region, probably from compression of the nervus intermedius within the internal auditory canal.(88) Others have no vertigo or tinnitus, only progressive hearing loss noticed while using the telephone.
Stage 2. As the tumor enlarges in the posterior fossa, it compresses neighboring cranial nerves V, VII, IX, X, and XI, most commonly V and VII. The fifth nerve is affected more often than the seventh, although the latter lies immediately beside the eighth. Patients report ipsilateral facial numbness, and examination shows loss of facial sensation and the corneal reflex. Facial pain is rare and usually has another cause. In the author's experience, acoustic neurinoma has never caused loss of trigeminal motor function. Sensory loss may result from compression of the nerve itself, its brainstem tract, or both. Facial motor function is usually preserved, with perhaps only slight flattening of the nasolabial fold. Clear facial nerve impairment appears only with very large tumors, indicating the substantial resistance of the motor components of cranial nerves V and VII to compression.
Stage 3. The enlarging mass compresses the cerebellum and cerebellar peduncles, producing incoordination, a gait veering toward the tumor, and slow, slurred speech. Horizontal nystagmus is usually present. Compression of the corticospinal and ascending brainstem tracts also occurs, causing contralateral spastic hemiparesis.
Stage 4. A very large tumor raises intracranial pressure through the combined effects of its bulk and obstruction of cerebrospinal fluid flow at the fourth ventricle, its outlets, the basal cisterns, and ambient cistern. Patients develop headache, blurred vision, vomiting, worsening ataxia, and progressive drowsiness, eventually becoming unconscious and dying without treatment.
Progression from stages 1 to 2 is slow, often taking years before specialist consultation. Progression from stages 3 to 4 is relatively rapid and prompts urgent medical attention.
Original pages 727–729
Diagnosis
A detailed history and examination are essential and usually establish the correct diagnosis because of the characteristic localizing syndrome. The initial eighth-nerve symptoms are particularly important. Vertigo, tinnitus, and progressive hearing loss should raise suspicion of acoustic neurinoma and prompt audiometry and radiological investigation, so that diagnosis is made while the tumor is still small.
Helpful investigations include:
1. AUDIOMETRY. An electronic audiometer measures hearing and distinguishes cochlear from retrocochlear (eighth-nerve) disease. Audiologists and ear specialists use pure-tone air and bone conduction, speech reception threshold, speech discrimination, tone decay, short-increment sensitivity index, alternate binaural loudness balance, and Békésy testing. Brainstem auditory evoked response (BSER) testing is a more recent addition. These tests permit accurate early diagnosis. Details may be found in neuro-otology texts.
Ordinary tuning-fork examination with the Rinne and Weber tests can distinguish conductive from sensorineural hearing loss but cannot localize it precisely, so audiometry is needed. Since the introduction of C.T. and MRI, neurosurgeons have paid less attention to audiometry because imaging demonstrates the tumor clearly. Other diagnostic investigations include:
2. Skull radiographs in Towne's and Stenvers' views, with tomograms of the internal auditory canals, show enlargement on the tumor side and often a funnel-shaped internal auditory meatus (Figure 6.20). Acoustic neuromas arising outside the canal may leave it normal.
3. CISTERNOGRAPHY. Air or Myodil is introduced into the lumbar subarachnoid space and directed into the basal cisterns and internal auditory meatus. Skull radiographs then demonstrate the tumor, particularly a small one. Both methods are now rarely used and are obsolete.
4. VERTEBRAL ANGIOGRAPHY adds little diagnostic benefit for acoustic neuroma.
5. COMPUTED TOMOGRAPHY. Contrast-enhanced C.T. clearly demonstrates the tumor, but lesions smaller than 1.5 cm or confined to the internal auditory canal may be missed and require MRI. Acoustic neurinomas appear hyperdense; large masses may have central cystic degeneration. Small tumors may remain invisible on conventional C.T. even after intravenous contrast. Introducing air into the lumbar subarachnoid space and directing it to the cerebellopontine angle before C.T. can display a small tumor beautifully (Figure 6.92). Sections through both internal auditory canals allow comparison: the affected canal may be enlarged and funnel-shaped, with the tumor itself also visible (Figure 6.116).
6. MAGNETIC RESONANCE IMAGING (MRI). This newest investigation clearly shows the tumor and its relationships to surrounding brain. Its advantage over C.T. is the detection of small tumors, particularly within the internal auditory canal, without obscuration by skull bone (Figure 6.125). When clinical findings suggest acoustic neurinoma but C.T. is negative, MRI should follow.
Original pages 729–731
Treatment
Acoustic neurinoma is benign but continually challenges surgical skill. Complete excision is the best treatment and is curative. Safe total removal without disability depends on tumor size, surgical expertise, microsurgical instruments, and the microscope. Size is particularly important: small tumors are easier and safer to remove. In Thailand, these tumors are generally large by the time patients reach a neurosurgeon, and postoperative facial nerve disability remains frequent. Earlier referral is now becoming more common because precise audiological tests, C.T., and MRI permit early diagnosis.
Small tumors. Masses no larger than 2 cm cause only eighth-nerve dysfunction, without signs of neighboring cranial nerve or brainstem involvement. Removal is easy because the nerves, vessels, and brainstem are clearly visible. Microsurgical instruments and the microscope permit complete excision without facial palsy and occasionally restore hearing.
Medium-sized tumors. At approximately 2–3 cm, the tumor begins to compress cranial nerves V and VII and the brainstem. The facial nerve becomes flattened and difficult to identify, increasing its vulnerability. Removal is more difficult and should always begin with intracapsular debulking. Reducing the mass then permits total removal while preserving the facial nerve.
Large tumors. Tumors larger than 3 cm are common in Thailand. They produce multiple cranial nerve, brainstem, and cerebellar signs, sometimes with hydrocephalus. Complete removal is very difficult and carries high mortality. In the author's opinion, a very large stage-4 tumor should not be completely removed in a single operation, because direct brainstem injury and damage to its vessels and the cranial nerves cause high mortality. No approach exposes every part of such a tumor satisfactorily, even after partial cerebellar hemisphere resection; operating without seeing the structures involved is dangerous. The author therefore prefers maximal intracapsular removal from within outward, leaving only a thin capsule. This decompresses the brainstem, cerebellum, and cranial nerves. Staying inside the capsule avoids injury to the facial nerve and brainstem. Patients may return to normal work for many years but require clinical follow-up and repeated C.T. If deterioration and C.T. indicate regrowth, repeat removal can be performed. Some surgeons disagree, wishing to avoid repeat surgery and believing that residual tumor causes hydrocephalus through elevated cerebrospinal fluid protein. They therefore attempt complete removal at the first operation without sufficient regard for immediate disability or death. Even a highly experienced neurosurgeon who removes a large tumor completely may still cause some postoperative disability.
Sheptak and Jannetta(89) reported improved results for large acoustic neurinomas using two-stage surgery. At the first operation, central and lateral tumor portions are removed for decompression, allowing the remaining medial portion to shift laterally into the space created. Two weeks later, a second operation removes the remainder.
Original pages 731
Operative Approaches
Several approaches to acoustic neurinoma are available, depending on tumor location and size. Small intracanalicular tumors may be approached through the middle fossa as described by House:(90) an extradural subtemporal exposure followed by removal of the roof of the internal auditory canal. Another option is the translabyrinthine approach,(91) using mastoidectomy and labyrinthectomy, then opening the dura anterior to the sigmoid sinus toward the internal auditory meatus to expose the intracanalicular tumor.
The author has never used the middle fossa or translabyrinthine approaches, because patients referred to the neurosurgical unit generally have large tumors already extending into the posterior fossa. Only the posterior fossa transmeatal approach has therefore been used.
Original pages 731–737
Posterior Fossa Transmeatal Approach
This approach consists of unilateral suboccipital craniectomy, opening the dura into the posterior fossa, and removing the posterior wall of the internal auditory meatus to expose the intracanalicular portion of the tumor. The posterior fossa approach has the following advantages:
1) It provides a sufficiently wide operative corridor.
2) Tumor dissection can be performed under direct vision on nearly every side except anteriorly.
3) The anterior inferior cerebellar artery and brainstem vessels can be seen.
4) The facial and other cranial nerves can be seen. If the facial nerve is divided, immediate repair may sometimes be possible.
Positioning. Either the sitting or lateral recumbent position may be used (see the beginning of this chapter). Both have advantages and disadvantages. Sitting gives the surgeon a direct view of the tumor at eye level, with easily understood anatomical relationships. Blood drains downward instead of pooling in the field. Its principal disadvantages are air embolism and the need to lift the cerebellar hemisphere against gravity, potentially bruising or tearing the brain. Hypotension is also more difficult to correct.
In the recumbent position the tumor can be seen without much cerebellar retraction, because the cerebellum falls downward under its own weight. Air embolism does not occur. However, anatomical relationships are harder to appreciate, looking downward strains the surgeon's neck—although a microscope can alleviate this—and bleeding tends to flood the operative field.
For acoustic tumor surgery in the sitting position, flex the head until the chin is approximately one fingerbreadth from the sternum. Ensure that neither the internal jugular veins nor the endotracheal tube is compressed. Turn the face toward the operative side to place the field directly before the surgeon. Flex both hips and knees and elevate the legs to increase central venous pressure. Before positioning, perform a venous cutdown and insert a catheter into the right atrium, permitting aspiration of air if an embolism is detected by a Doppler device placed over the precordium.
Incision. Make a vertical incision approximately 3 cm from the mastoid process and 10 cm long, with its upper end above the transverse sinus and its lower end slightly below the foramen magnum. Alternatively, use a paramedian or midline hockey-stick incision. Separate the muscles laterally to the mastoid edge; medially, dissection need not reach the midline. A large emissary vein at the mastoid edge must be securely sealed with bone wax. Perform a craniectomy approximately 4 cm wide, extending laterally to the sigmoid sinus. If mastoid air cells are opened, cover them completely with a sheet of bone wax. Superiorly, expose the transverse sinus; inferiorly, reach the foramen magnum, sometimes removing its rim. Medially, remove bone almost to the midline so that its edge does not compress the cerebellar surface during retraction. The essential point in acoustic tumor surgery is to extend the opening as far laterally as possible, shortening the route to the tumor and internal auditory canal and minimizing cerebellar retraction or the need to resect part of the cerebellum.
Before opening the dura, assess intracranial pressure. If elevated, drain CSF through the previously placed ventriculostomy tube until the dura relaxes. The author no longer performs ventriculostomy for acoustic tumor surgery, instead opening a small hole into the cisterna magna and draining CSF until pressure falls and the dura is slack. Open the dura in a curve following the lateral craniectomy edge, leaving a margin of approximately 0.5 cm for easy closure. Extend the incision superiorly almost to the transverse sinus and inferiorly to the foramen magnum. If greater cerebellar retraction is needed, a perpendicular transverse incision in the dura covering the hemisphere prevents its edge from pressing on the brain. Suspend the dural edges with sutures. Use a self-retaining retractor to lift the cerebellum upward and slightly medially, exposing the underlying arachnoid. Open the arachnoid from the foramen magnum toward the tumor, protecting the cranial nerves and the anterior inferior cerebellar artery and its branches. Allow CSF to escape until the brain relaxes; little retraction force is then needed to see the tumor at the internal auditory canal (Figure 7.65). Elevating the cerebellum reveals the following important anatomy (Figure 7.62).
Figure 7.62. Important structures in the cerebellopontine angle. From Koos W.T., Spetsler R.F., Pendl G., Perneczky A., and Lang J., Color Atlas of Microneurosurgery.
Cranial nerves IX, X, and XI are the first nerves seen on entering the cerebellopontine angle. The accessory nerve enters the posterior fossa through the foramen magnum, ascends against the dura, and turns laterally into the jugular foramen. The vagus and glossopharyngeal nerves emerge from the lateral medulla between the inferior cerebellar peduncle and the olive, then run laterally into the middle of the jugular foramen, with the inferior petrosal sinus anteriorly and the sigmoid sinus posteriorly. The glossopharyngeal nerve lies anterior to the vagus.
Cranial nerves VII and VIII emerge from the lateral brainstem at the lower border of the pons. The facial nerve is approximately 1–2 mm anterior to the acoustic nerve, and the flocculus lies behind both at their origin. Choroid plexus protruding from the foramen of Luschka lies posterior to the glossopharyngeal and vagus nerves, which are inferior to the facial and acoustic nerves. In the cerebellopontine angle, VII and VIII run laterally and slightly upward into the internal auditory meatus and canal, approximately 1 cm anterosuperior to the jugular foramen. Throughout their course from brainstem to canal, the facial nerve lies anterior and slightly inferior to the acoustic nerve. Thus, in acoustic tumors, the facial nerve usually lies anteroinferior to the mass, but this is not invariable and the surgeon must remain cautious. For this reason, the safest entry into the tumor is through its posterior capsule, avoiding injury to the facial nerve.
The nervus intermedius is a small nerve separate from the facial nerve. Together with the vagus and glossopharyngeal nerves, it conveys pain and touch from the external auditory canal.(92) It also carries taste from the anterior two-thirds of the tongue and controls secretion from the lacrimal and submaxillary glands. Rhoton(92) described an 8-mm proximal segment attached to the acoustic nerve, a 10-mm middle segment lying between the facial and acoustic nerves, and a distal segment joining the facial nerve. These anatomical and functional relationships may explain auricular hypesthesia when an acoustic neurinoma compresses this nerve.
Cranial nerve V, the trigeminal nerve, is seen approximately 1 cm anterior to the acoustic and facial nerves and is broader and larger than all the other nerves. Its motor branch is not visible during surgery because it runs anterior to the trigeminal nerve.
Cranial nerve VI, the abducens nerve, emerges from the anterior brainstem at the lower border of the pons and runs in front of the brainstem toward the cavernous sinus. It is usually little involved in acoustic tumor surgery, but a large mass displacing the brainstem may expose it, and it must be preserved.
Cranial nerve IV emerges from the dorsal midbrain, winds around its margin, and passes forward into the cavernous sinus beneath the tentorial edge. Protect it when a large acoustic tumor extends into the tentorial notch.
The vertebral artery enters the posterior fossa lateral to the medulla and anterior to the vagus and glossopharyngeal nerves. It then turns medially in front of the medulla to join its fellow at the pontomedullary junction, forming the basilar artery. This ascends in the midline anterior to the pons and divides at its upper border into the two posterior cerebral arteries. Just before its termination, it gives rise to the two superior cerebellar arteries.
The posterior inferior cerebellar artery arises from the vertebral artery beside the medulla and runs anterior to the accessory, vagus, and glossopharyngeal nerves.
The anterior inferior cerebellar artery (AICA) arises from the basilar artery and may pass anterior or posterior to the facial and acoustic nerves, or between them. It then courses posteriorly onto the middle cerebellar peduncle above the flocculus.(93) Sometimes its loop approaches or enters the internal auditory canal with the nerves. During tumor dissection, protect this artery, because its destruction causes brainstem infarction.(93)
The internal auditory or labyrinthine artery arises from the AICA loop. It is the sole arterial supply to the labyrinth and cochlea and must be preserved if hearing is to recover.
The superior cerebellar artery arises from the basilar artery before its division into the posterior cerebral arteries. It lies inferior to the oculomotor nerve, winds around the lateral midbrain posteriorly, and supplies the cerebellar hemisphere and vermis. When a large acoustic tumor extends into the tentorial notch, identify and preserve this artery to prevent cerebellar infarction.
Veins. Important veins that require protection during acoustic tumor surgery include the following.
The transverse sinus carries blood from the torcular Herophili, chiefly draining the supratentorial compartment, to the sigmoid sinus. Do not cut this sinus when opening the dura.
The sigmoid sinus continues from the transverse sinus along the posterior mastoid margin and exits through the jugular foramen into the internal jugular vein.
The petrosal vein is a bridging vein anterior to the acoustic tumor, draining the cerebellar hemisphere into the superior petrosal sinus. It may be coagulated and divided if necessary during dissection, but preservation is preferable.
The other veins of the brainstem and cerebellum should also be preserved.
Original pages 737–741
Tumor Removal
Acoustic neurinoma usually arises from Schwann cells of the vestibular nerve and always originates at the internal auditory meatus. It therefore commonly expands simultaneously into the internal auditory canal and posterior fossa, thinning the canal walls so that they are easily drilled away. C.T. helps determine how far laterally to remove the canal wall. Origin at the meatus displaces the facial nerve anteroinferior to the tumor and pushes AICA medially. The trigeminal nerve is displaced anteriorly beside the petrosal vein. In tumors larger than 2 cm, the medial surface compresses the pons, while nerves IX, X, and XI lie posteroinferior to the tumor. Keep these relationships constantly in mind during surgery. After opening the arachnoid and releasing CSF, retract the cerebellar hemisphere with a self-retaining retractor until the tumor and these structures are visible, then proceed as follows.
1. Identify cranial nerves IX, X, and XI and the jugular foramen posterior to the tumor. These are the first easily identified nerves. Cover them completely with cotton patties throughout the operation. Otherwise, blood from the tumor can obscure them and they may be injured during suction.
If a large tumor compresses these three nerves and they cannot be carefully separated, first debulk the tumor internally. The reduced mass then permits their separation. Injury to IX and X causes inability to swallow, aspiration, and hoarseness. Remove the protective cotton slowly: first thoroughly moisten it, then carefully separate it from the nerves. Otherwise, nerves adhering to the cotton can be pulled out and torn. It would be unfortunate to remove the tumor successfully only to leave the patient disabled through the surgeon's carelessness.
2. If cerebellar retraction does not adequately expose the tumor, cranial nerves, and brainstem, the lateral third of the ipsilateral cerebellar hemisphere may need to be resected without loss of function (Figure 7.63).
Figure 7.63. Removal of the lateral third of the cerebellar hemisphere provides broad exposure of an acoustic neurinoma.
3. Open the internal auditory canal with an electric drill. Incise the dura over the petrous bone in a semicircle whose diameter lies along the internal auditory meatus, always keeping clear of dural sinuses. Begin with a 4–5-mm burr, changing to smaller burrs as the canal is approached. Drill above the meatus, always moving upward from below, never downward from above: a slip could injure nerves and brain. Do not extend too far superolaterally, where the semicircular canal lies, or posteroinferiorly, where the jugular bulb lies. The curvature of the tumor's lateral border indicates the required lateral extent (Figure 7.64). After completing the superior portion, drill away the posterior wall.
Figure 7.64. The intracanalicular tumor (small arrow) exposed by electrically drilling open the acoustic canal. Most of the tumor is intracranial (large arrow).
For a large tumor, the author prefers to finish opening the canal before removing the main mass, because the tumor protects the brain, nerves, and vessels should the drill slip (Figure 7.64). Keep cotton patties away from the drilling site: they can wind around the burr, startle the surgeon, and damage nerves by traction.
4. Tumor excision. The principles are: i) When the tumor occupies the internal auditory meatus and canal, open the canal. ii) Always enter through the posterior tumor surface to avoid injuring the facial nerve, which lies anteroinferiorly. iii) Remove tumor from inside outward to reduce its size before separating its surface from nerves, brainstem, and vessels. Strongly avoid attempting en bloc dissection. iv) Leave the capsule densely adherent to brain until last. If it cannot be separated from the brainstem, leaving only a thin layer protects the brainstem. v) The facial nerve is most easily found proximally near the brainstem and within the auditory canal.
The intracanalicular tumor is surrounded by thin dura. After opening the canal, incise this covering to expose the tumor, coagulate its surface vessels with bipolar forceps, open the capsule, and remove the contents using a microdissector, tumor forceps, tumor curette, and punch forceps. When little remains except the capsule, lift it and separate the nerves from its wall. Avoid grasping the nerves, which bruises them. Once they are separated, divide both ends of the nerve from which the tumor arises, completing removal. In small tumors, AICA is clearly visible and easily separated and preserved.
Large tumors obscure the proximal and distal acoustic and facial nerves, AICA, and brainstem. Apply the same principle of extensive internal debulking. An ultrasonic aspirator now facilitates this. Aspirate horizontally or along the direction of the nerves to reduce injury. The facial nerve is initially invisible in every case because it lies anteroinferiorly, and a large tumor flattens it against its wall. Do not begin facial nerve dissection at this point. After reducing the mass and dividing the AICA branches supplying it, lift the capsule edge. The facial nerve is most clearly identifiable near its brainstem origin and at the extreme lateral end of the tumor; if the tumor extends into the canal, the nerve can be found there. On identifying the vestibular nerve medially or laterally, divide it, then gently separate the tumor surface from the facial nerve. A few small fibers firmly attached to the tumor may be divided while preserving the bulk of the nerve. Do not grasp the facial nerve and push the tumor wall away from it: this bruises the nerve and makes functional recovery difficult.
After freeing the facial nerve, separate the tumor from the trigeminal nerve, proceeding from lateral toward the brainstem. This is easier because the tumor margin here is usually separate from the nerve and readily visible. Widely open the overlying arachnoid to identify and follow the trigeminal nerve. To do so, divide the lateral attachment of the tumor capsule and reflect it medially.
Finally, separate the capsule from the brainstem. Identify AICA branches supplying the tumor, coagulating and dividing them as close to the tumor as possible. Gradually separate the capsule from posterior to anterior. Small cotton patties supporting the tumor away from the brainstem help reveal the cleavage plane. At the middle of the pons, protect the trigeminal nerve. The tumor can eventually be removed. If it extends superiorly, protect the superior cerebellar artery running above it. Leave any portion inseparable from the brainstem, reducing it to a thin capsule. Insisting on total removal may damage the brainstem's blood supply or the brainstem itself.
After removal and secure hemostasis, close the dura tightly with a continuous suture, then close muscle and skin in layers.
Original pages 741–744
Postoperative Complications
In addition to the general surgical complications described at the beginning of this chapter, acoustic neurinoma surgery has several important specific complications: facial palsy, CSF leakage, and hydrocephalus. Facial palsy is the most frequent.
Facial palsy may be temporary or permanent. In either case, protect the cornea immediately on leaving the operating room. Without protection, keratitis or corneal ulceration may subsequently cause blindness. Protection consists of: i) an eye shield with a transparent center, excluding wind and dust while allowing vision. Do not use an eye pad: the eye remains open and corneal sensation is impaired, so rubbing by the fabric may cause ulceration. ii) Artificial tears to prevent dryness. iii) Temporary or permanent tarsorrhaphy as appropriate.
There are two forms of facial palsy after acoustic neurinoma surgery.
1. Immediate palsy is evident when the patient awakens from anesthesia. It results from division of the facial nerve or, if continuity remains, contusion or axonotmesis. A definitely divided nerve may be repaired by end-to-end anastomosis, or with a sural nerve graft if the ends cannot meet, immediately after tumor removal.(94) If intracranial repair is impossible, perform hypoglossal–facial anastomosis within 1–2 weeks.
If some continuity of the facial nerve is certainly preserved, observe for functional recovery for approximately 2–3 months. If none occurs, hypoglossal–facial anastomosis should be performed; even slight recovery warrants further waiting. Reasons for using the hypoglossal rather than accessory nerve are:(95) i) the tongue and face representations in the motor cortex are anatomically closer than those of shoulder and face; ii) facial and tongue muscles constantly act together in speech and eating, more than facial and shoulder muscles do; and iii) hypoglossal–facial anastomosis generally gives better results than accessory–facial anastomosis.
2. Delayed palsy appears approximately 2–3 days after surgery, results from facial nerve swelling, and is temporary. Await spontaneous improvement without further surgery. Facial function should therefore be examined as soon as the patient awakens, to establish whether paralysis was immediate—a distinction important for treatment decisions.
CSF leakage commonly occurs with hydrocephalus and elevated CSF pressure. Formerly it was frequent because posterior fossa closure involved suturing dura to muscle, leaving an opening through which CSF collected outside the dura. Poor wound healing together with hydrocephalus then permitted leakage. The author now closes the dura completely in its original position after tumor removal, reducing this risk.
The author has encountered CSF rhinorrhea following acoustic neurinoma surgery when mastoid air cells were opened. In one patient undergoing posterior fossa removal of an acoustic nerve tumor, lateral removal of occipital bone opened mastoid air cells, which were covered with a sheet of bone wax. After tumor removal, the dura and wound were closed in layers. Postoperatively, CSF rhinorrhea occurred whenever the patient sat up. Despite waiting 12 days for spontaneous closure, it persisted. Reopening the wound revealed an approximately 2-mm leak at the dural suture line. This was sutured closed, and the bone wax over the mastoid cells was replaced with a muscle patch. Rhinorrhea ceased immediately. CSF had passed through the opened mastoid cells into the middle ear, along the Eustachian tube to the nasopharynx, and out through the nostril. This complication does not occur unless the mastoid air cells are opened.
Hydrocephalus may precede surgery for a large tumor or develop afterward from blood left in the subarachnoid space during surgery or from brain swelling. Recovery is poor and progressive drowsiness may develop. Ventriculostomy or a V-P or V-A shunt drains CSF, lowers intracranial pressure, and prevents hydrocephalus from causing a CSF leak.
Original pages 744
Treatment Results
Small tumors can be completely removed while preserving facial nerve function, providing a cure (Figure 7.65). Cochlear nerve function sometimes recovers. For large tumors, attempts at total removal commonly leave every patient with disability and carry high mortality; facial palsy is the most frequent disability. Debulking while leaving only the capsule permits many years of survival without this disability, but the tumor eventually regrows, cure is not achieved, and another operation is required. Because the tumor is benign, this is considered preferable to immediate postoperative death or disability.
For medium-sized tumors, improved surgical instruments have increased the rate of complete removal with facial nerve preservation and permit cure.
Original pages 744–749
Meningiomas
As explained in the chapter on brain tumor pathology, meningiomas arise from arachnoid cells. Most therefore lie outside the brain, with a surface attached to the dura mater. They grow inward against the cortex and become embedded within surrounding cortex, causing focal symptoms according to the compressed region. A small number arise within a ventricle from the leptomeninges of the tela choroidea and choroid plexus.
Meningioma is benign and second in frequency to gliomas. It usually occurs in middle age and is more common in women. Favored sites include the parasagittal region, convexity, lesser sphenoid wing, olfactory groove, tuberculum sellae, tentorium, foramen magnum, and ventricles. Each produces characteristic focal symptoms and requires a different operative approach, as discussed below.
Growth is slow, so symptoms develop gradually over years before medical attention is sought. Because the tumor is well circumscribed and does not infiltrate brain tissue, complete excision is the principal means of cure. However, tumors at critical sites require constant consideration of possible functional loss and disability. Sometimes a portion must be left to preserve brain function.
Figure 7.65. Small acoustic neurinoma. A. Tumor at the internal auditory meatus. B. Opening the acoustic canal permits complete removal while preserving the facial nerve. C. Normal postoperative facial muscle function.
Most meningioma blood supply comes from the external carotid artery through the dura attached to the outer tumor wall. The middle meningeal artery is particularly important and may enlarge greatly when supplying a convexity or parasagittal tumor over the frontal or parietal lobe. Its conspicuous enlargement on angiography helps establish the diagnosis. The internal carotid circulation supplying the brain contributes less. Dividing the dural tumor supply before dissection therefore substantially reduces blood loss. Fibrous meningiomas are less vascular than other types, permitting internal debulking with little bleeding and relatively uncomplicated surgery. Conversely, angiomatous (angioblastic) meningiomas are highly vascular: dissection may cause severe bleeding and hemorrhagic shock. Surgery is difficult and mortality high, making early interruption of feeding vessels at their origin necessary.
The degree of edema surrounding a meningioma depends on its size and location; large tumors cause more edema than small ones. The author frequently finds edema as extensive as that of glioblastoma multiforme or metastatic brain tumors when meningiomas lie parasagittally or in the Sylvian fissure. Compression of cortical veins and impaired venous drainage probably explain this surrounding edema (Figures 6.88 and 6.89).
A meningioma abutting the brain surface and attached to the dura may cause inward bony projections that indent the dura, providing sites through which arteries and veins pass. Diploic veins draining the tumor enlarge, and profuse bleeding here during craniotomy indicates the tumor's location(96) (Figure 7.66). Hyperostosis may also extend outward, sometimes forming an externally visible, hard, nontender skull swelling (Figure 7.67) that localizes the underlying tumor. Both scalp arteries and veins enlarge (Figure 7.67); the superficial temporal artery is larger and more strongly pulsatile than on the opposite side. Hyperostotic bone may or may not contain tumor. Infiltrating meningioma is usually central within the raised bone and is clearly demonstrated by C.T. (Figure 7.68). Most tumors do not extend outside the skull as a palpable soft mass, but occasionally a very large tumor penetrates the skull and forms a mass beneath the galea and scalp (Figure 7.69). Meningioma of the lesser sphenoid wing, particularly its lateral half, often causes temporal and orbital hyperostosis, producing unilateral exophthalmos and temporal swelling (Figure 6.17). This is commonly associated with meningioma en plaque and is an important sign. Hyperostosis is unrelated to histological type or tumor size and can occur anywhere, although it favors the parasagittal region.(96)
Figure 7.66. A surface meningioma causes inward skull growth that presses upon the dura and underlying tumor. Note the numerous newly formed vascular grooves in the inner table.Figure 7.67. A hard mass near the vertex in a patient with meningioma. Note the enlarged scalp vessels leading toward it. A. Anterior view. B. Lateral view.Figure 7.68. Meningioma infiltrating the central portion of hyperostotic bone.Figure 7.69. A large meningioma extending through the skull to form a soft mass over the forehead and eye.
Original pages 749–752
Investigations
In addition to general symptoms and focal signs, investigations demonstrate characteristic features of meningioma and improve diagnostic accuracy. Before C.T. and MRI, skull radiographs and angiography were the principal investigations.
1. Skull radiographs show changes from raised intracranial pressure (see Chapter 6). Additional focal findings include: i) homogeneous tumor calcification; ii) hyperostosis adjacent to the tumor surface, involving the inner table alone or also extending outward, sometimes producing an externally visible swelling. The hyperostotic region may show a “sunray” appearance. Falx meningiomas do not cause hyperostosis because they do not abut the skull. iii) Occasionally adjacent bone is destroyed rather than thickened, leaving an irregular-edged defect. A lesser sphenoid wing meningioma may cause demineralization, making that wing less radiopaque than the unaffected side. iv) Vascular grooves in the inner table enlarge as the tumor's feeding vessels enlarge. The foramen spinosum may also enlarge, and neovascularization may be clearly visible at the tumor site.
2. ANGIOGRAPHY is very useful in diagnosing meningioma. With C.T. and MRI available it is now performed less often, principally to determine the location and caliber of important feeding arteries, tumor vascularity, and dural sinus occlusion. These findings guide surgery. For example, a large external carotid supply may require embolization or external carotid ligation. Angiography may also help when C.T. is inconclusive.
Characteristic angiographic features may be summarized as follows.
i) External carotid branches, particularly the middle meningeal artery supplying the tumor, become enlarged and tortuous, increasingly so near the tumor.
ii) A sunburst appearance radiates outward from a central point corresponding to the tumor pedicle at its dural attachment.
iii) Supply comes from both external and internal carotid arteries. External carotid angiography can establish the diagnosis definitively.
iv) Homogeneous tumor staining begins in the late arterial phase and persists into the venous phase. Staining is harder to see in skull-base or cerebellopontine-angle tumors.
v) Early venous drainage is uncommon except in angioblastic or malignant meningioma.
3. COMPUTED TOMOGRAPHY is the best investigation for diagnosing meningioma, demonstrating location, size, surrounding edema, calcification, bone changes, and brain displacement caused by raised intracranial pressure.
Generally, a noncalcified meningioma is slightly dense on unenhanced C.T. (40–80 Hounsfield units)(97) and markedly hyperdense after contrast injection (Figure 6.105). C.T. can also show tumor extending into the skull (Figure 7.68).
Peritumoral edema is regularly seen. Parasagittal tumors often produce more edema than those elsewhere, possibly because cortical veins are compressed or the superior sagittal sinus is invaded.
Important C.T. features of malignant meningioma are: i) poorly defined margins; ii) multiple projections into white matter; iii) extensive vasogenic edema; iv) skull destruction; v) absence of calcification; vi) necrosis causing heterogeneous enhancement; and vii) a mushroom-shaped mass or a large en plaque lesion.
4. MRI is the newest method and depicts meningioma clearly. It is inferior to C.T. for calcified tumors, however, because bone is poorly demonstrated. Meningioma shows relatively little difference in T1 and T2 relaxation times; small tumors may therefore be overlooked, particularly if calcified. Despite little distinction between T1 and T2 appearances, a low-attenuation rim is often seen around the tumor, representing CSF in the subarachnoid space. Furthermore, MRI provides multiple imaging planes and clearly demonstrates posterior fossa meningiomas, especially at the craniocervical junction.
Original pages 752
Symptoms, Signs, and Treatment by Meningioma Location
Meningiomas favor particular sites, including the parasagittal region, convexity, olfactory groove, sphenoid ridge, and posterior fossa. Each produces a characteristic syndrome, so their symptoms and signs are discussed separately. Treatment and operative techniques also differ by location and are likewise considered individually.
Original pages 752–753
A. Parasagittal and Falx Meningioma
These two locations are closely related to each other and to the superior sagittal sinus and are therefore discussed together. A parasagittal meningioma originates near the sinus wall, grows in the angle between the falx and convexity dura, and pushes the cerebral angle away from the sinus. A large tumor may extend along the falx and compress the corpus callosum and pericallosal artery, or spread along the convexity dura. It commonly extends through the superior sagittal sinus wall, narrowing or occluding the sinus (Figure 7.70), and often causes hyperostosis.
A falx meningioma originates on the falx away from the superior sagittal sinus, enlarging against the medial cerebral hemisphere, corpus callosum, and anterior cerebral artery. Some penetrate the falx and grow on both sides, forming a dumbbell tumor. This is surgically important: the opposite component must also be removed to achieve cure. Most are not visible immediately after craniotomy; the medial hemisphere must be separated from the falx to expose them. Their distance from the skull explains the absence of hyperostosis. A large tumor extending toward the brain surface may eventually reach the superior sagittal sinus.
AI-enhanced and colorized image · Switch to view the originalFigure 7.70. A parasagittal meningioma extending into and occluding the superior sagittal sinus.
Original pages 753–755
Symptoms and Signs
Tumors here may be divided by location and syndrome into anterior, middle, and posterior thirds of the superior sagittal sinus and falx. The anterior third extends from the crista galli to the coronal suture, the middle third from the coronal to the lambdoid sutures, and the posterior third from the lambdoid sutures to the torcular. The middle third is most commonly affected, followed by the anterior third; posterior-third tumors are least frequent.
Anterior-third parasagittal and falx meningioma causes no focal symptoms because it lies away from the motor and sensory speech centers, so the tumor is often large at diagnosis. Symptoms and signs develop slowly, chiefly personality, memory, and intellectual changes, indifference to surroundings, and headache from raised intracranial pressure. Seizures may occur, usually generalized rather than focal. A very large frontal tumor may produce ataxic gait or tremor with papilledema and be mistaken for a posterior fossa tumor.
Middle-third parasagittal and falx meningioma often presents with focal seizures for several years, followed by numbness and spastic weakness. The tumor irritates and compresses the leg areas of the motor and sensory cortex. Seizures usually begin in the foot and spread to the leg, arm, and face—marching or Jacksonian epilepsy. Generalized seizures often cause urinary incontinence because the micturition center lies here. Raised intracranial pressure is uncommon because symptoms usually appear before the tumor becomes large. Extension to the opposite side may cause spastic paraparesis resembling a thoracic spinal tumor. The distinction is straightforward: parasagittal meningioma lacks the sensory level of a spinal lesion and produces cerebral symptoms such as headache, vomiting, and focal seizures. A large tumor extending laterally may weaken the shoulder as well as the leg because the shoulder motor area lies near the vertex.
Posterior-third parasagittal and falx meningioma compresses the medial occipital surface. A large tumor produces homonymous hemianopia. A small tumor near the tentorium compresses the region below the calcarine fissure, producing homonymous superior quadrantanopia; one above the fissure causes homonymous inferior quadrantanopia. Slow growth often leaves patients unaware of their visual deficit, allowing the tumor to become large. Raised intracranial pressure is therefore more frequent than with middle-third tumors.
Original pages 755–756
Diagnosis of Parasagittal and Falx Meningioma
In addition to the history and localizing neurological signs, examination of the head and radiological studies improve diagnostic certainty.
A parasagittal meningioma may produce a hard swelling near the cranial midline (Figure 7.67), usually marking the underlying tumor. This is skull hyperostosis, sometimes containing meningioma tissue.
Skull radiographs may show focal hyperostosis or calcification outlining the tumor. Grooves in the inner table for middle meningeal branches supplying the parasagittal region enlarge, although these changes are usually absent in falx meningioma. Neovascularization may be visible over the tumor.
Angiography is important. Besides showing feeding vessels, tumor staining, and anterior cerebral artery compression, it reveals superior sagittal sinus occlusion by tumor invasion, collateral circulation, and the relationship of cortical veins to the mass. These findings are important surgically, especially for middle- and posterior-third parasagittal tumors, where the surgeon must decide how to manage the sinus. In falx meningioma, cortical vein positions likewise determine the route of approach.
C.T. and MRI are the best diagnostic studies, showing location, size, calcification, skull changes (hyperostosis), tumor extending into the skull, edema, and brain displacement from tumor pressure (see the chapter on investigations).
Original pages 756
Treatment of Parasagittal and Falx Meningioma
Removal of tumors in this region is difficult, requires technical knowledge, and carries substantial risk. Access is particularly difficult for falx meningiomas deep beneath the surface along the medial hemisphere. Important cortical veins and the superior sagittal sinus also obstruct the approach.
The following hazards of parasagittal meningioma surgery must always be considered.
1) Blood loss from scalp, vascular bone, dura mater, and the superior sagittal sinus, particularly near the torcular. In some cases, opening the skull alone results in loss of 4–5 bottles of blood. Appropriate prevention and hemostatic techniques must therefore be understood.
2) Extensive hyperostosis or tumor invasion of the affected bone makes craniotomy difficult. Lifting the bone flap may tear tumor and vessels, causing major blood loss.
3) Important large cortical veins entering the superior sagittal sinus must be preserved. Injury may cause disability or death. Dividing or ligating the middle third of the superior sagittal sinus may cause spastic diplegia; ligating and dividing its posterior third causes death from venous infarction, brain swelling, and raised intracranial pressure.
Original pages 756–759
Operative Technique
Positioning. Because the sagittal sinus lies in the midline, keep the face straight, varying the head's angle to the floor according to tumor location. For an anterior-third tumor, place the patient supine with the face straight, optionally elevating the head of the table slightly. For a middle-third tumor, use the supine position with moderate head flexion so that the tumor is uppermost, again slightly elevating the table head. Posterior-third tumors may be approached semisitting or semiprone. For semisitting, elevate the table head approximately 60°, moderately flex the head, keep the face straight, and secure the head with three-point skeletal fixation. Disadvantages are air embolism and increased susceptibility to cerebral ischemia during major blood loss; the semiprone position avoids these problems.
Incision. A straight incision perpendicular to the sagittal sinus may be centered over the tumor's diameter. The author prefers this because it can be extended in either direction, divides fewer vessels, bleeds less, and is easy to close. An anterior-third tumor may be exposed through a transcoronal incision. A conventional horseshoe incision is another option, but must cross the midline because the craniotomy may also need to cross it.
Craniotomy. Opening the skull for parasagittal meningioma is more dangerous than at other sites because bone, sinus, dura, and tumor may bleed profusely. If C.T. and angiography show neither hyperostosis nor invasion of bone and vascularity is modest, a routine bone flap is straightforward. Two precautions are important. First, when crossing the midline, place burr holes on both sides of the sagittal sinus and remove the intervening bone with a rongeur. Do not use a Gigli saw, which may injure the sinus. A unilateral tumor may not require a midline-crossing flap, but the bone edge must still be removed to expose the sinus. Place medial burr holes approximately 1–1.5 cm from the sinus and remove bone along the sagittal suture from the posterior to the anterior hole, exposing the sinus throughout. Second, separate bone carefully from dura and sinus to avoid tears. Bleeding here may arise from the sinus or arachnoid granulations and is venous. Apply Gelfoam to the bleeding point, cover with cotton, and press gently with a finger for a short time. Some points can be controlled with bipolar coagulation.
Hyperostosis, with or without tumor invasion, makes the opening harder and bloodier. Place multiple burr holes around the hyperostotic area and remove the bone between them circumferentially (Figure 7.71).
AI-enhanced and colorized image · Switch to view the originalFigure 7.71. Craniotomy for a highly vascular meningioma associated with hyperostosis.
This frees the hyperostotic segment from the surrounding skull, making separation from dura, sinus, and tumor easier. The resulting bony gap also permits suture ligation of large dural vessels running toward the tumor, reducing its blood supply. Rapid completion of the craniotomy is another means of reducing blood loss.
Original pages 759–765
Tumor Removal
After opening the skull, palpate the dura to determine the tumor's extent; it feels firmer than the surrounding area. If the tumor is attached to the dural surface, the outer dura may show changes such as tumor tissue and newly formed vessels. Incise the dura along the tumor's outer margin toward the superior sagittal sinus, leaving the flap hinged at the sinus. If the tumor is not attached to the dura, open and separate the dura completely from its surface to display the relationship between the tumor and cortical veins. Firmly adherent dura need not be separated, but lifting the tumor may then tear a cortical vein near the superior sagittal sinus because the vein is hidden. Adherent dura is useful for traction: place a suture through both dura and tumor and weight the thread with an arterial clamp to lift the tumor away from the brain. If an important large cortical vein lies there, however, separate the dura from the tumor to expose the vein entering the sinus and avoid tearing it. Damage to these veins may cause neurological disability.
Begin dissection by dividing the arachnoid membrane circumferentially between the tumor margin and cortex, avoiding tears in cortical veins. For a relatively avascular tumor, coagulate its surface vessels and use an electrical loop to remove the interior piecemeal, creating a cavity and reducing tumor size. An ultrasonic aspirator, if available, now makes removal much easier, leaving only a thin tumor wall. Drawing this wall inward toward the cavity separates it readily from the cortex and permits convenient coagulation and division of feeding vessels. Inserting cotton patties between the cortex and tumor wall helps separate the tumor further. On reaching the sagittal sinus, take care not to damage cortical bridging veins. Remove the tumor completely from the sinus wall and falx. Coagulate any suspected remnant or excise the involved portion of falx. Tumor may adhere to a cortical vein and be difficult to dissect away. If further dissection risks tearing the vein, stop; leaving a small remnant attached to it may be safer. Small, unimportant veins may be divided.
The neurosurgeon often faces a difficult decision when tumor adheres to the superior sagittal sinus: remove the entire tumor together with the sinus to cure the disease and prevent recurrence, accepting the risk of disability or death, or merely dissect tumor from the wall of a still-patent sinus, leaving possible remnants that will regrow but with far less disability. The following principles apply to parasagittal meningioma attached to the superior sagittal sinus.
1) If tumor is attached to the sinus wall without entering its lumen and the sinus remains normally patent, as judged by inspection and venography, separate it from the wall wherever it lies along the sinus. Coagulate adherent remnants until charred to prevent recurrence. This does not prevent recurrence in every case; the author has seen tumors recur several years later. Nevertheless, this approach avoids the risks of disability and death.
2) If tumor extends into the anterior third of the superior sagittal sinus, the involved sinus may be excised safely whether or not it is completely occluded. Open the dura on both sides, clamp, divide, and suture-ligate the sinus anterior and posterior to the tumor, and remove the falx beneath that segment.
3) If tumor involves the middle or posterior sinus and enters its lumen without occluding it, do not remove the sinus with the tumor. This may cause cortical venous infarction, bilateral paralysis, or fatal cerebral swelling. Dissect the tumor only from the sinus wall, leaving the intraluminal remnant. This avoids risking disability and life, although recurrence or later sinus occlusion remains possible. Should the sinus subsequently become occluded by tumor, removing the occluded segment is no longer dangerous, even in its middle or posterior portion. It is essential, however, to preserve collateral cortical veins anterior and posterior to the occlusion.
The following examples illustrate removal of parasagittal meningioma.
Case 1. A 35-year-old patient had a parasagittal meningioma attached to the dura over the motor cortex. Focal and Jacksonian seizures began with jerking of the left leg, spread to the arm, and then became generalized, with loss of consciousness and urinary incontinence. Occasionally only the left leg jerked before the seizure stopped. Todd's paralysis followed seizures. There was no headache, blurred vision, or vomiting. Examination showed mild left-leg weakness but was otherwise normal. A right carotid angiogram demonstrated a parasagittal tumor in the leg motor area.
A straight incision approximately 15 cm long was made perpendicular to the superior sagittal sinus, passing through the tumor's center from left to right. A self-retaining retractor separated the scalp, and a craniotomy crossing the midline exposed the sinus. Opening the dura revealed a surface tumor attached to it. Newly formed capillaries in the dura supplied the tumor, a characteristic meningioma appearance (Figure 7.72A). A suture was placed through the dura over the tumor, and an arterial clamp was attached to the thread and allowed to hang downward, lifting the tumor slightly. The arachnoid between its margin and the cortex was then divided. As this dissection approached the sinus, additional arterial clamps increased traction, gradually rolling the tumor completely away from the cortex (Figure 7.72B). This requires little or no brain retraction. Because this tumor was relatively small, internal debulking was unnecessary. When rolling the dura and tumor over, protect cortical veins entering the sinus. If a vein tears, do not coagulate it: occlusion may cause cerebral swelling and disability. Instead, wrap a thin sheet of Gelfoam around it and cover briefly with cotton; bleeding stops while flow through the vein is preserved. An unimportant vein may be coagulated. After freeing the tumor from the vein, dissect and divide its attachments to the dura and sagittal sinus wall, then char all residual tumor there. Alternatively, incise the dura circumferentially around the tumor and remove both together. Near the sinus, leave a 0.5-cm dural cuff for suturing a dural graft. Carefully strip tumor from the sinus wall and destroy the remaining tissue with bipolar coagulation. Finally, close the dural defect with a pericranial graft.
Figure 7.72. Operative views of a parasagittal meningioma. A. A surface tumor attached to the dura mater; note its numerous feeding capillaries. B. Traction on sutures through the dura and tumor separates the tumor from the cortex.
A large tumor must always be reduced in size first. Use an electrical loop to remove the interior outward in all directions until only a thin wall remains. Drawing this wall inward toward the cavity allows separation from the brain without destroying brain tissue. An ultrasonic aspirator makes internal removal faster, easier, and less dangerous than an electrical loop, and bleeding is easier to control. For a large parasagittal meningioma over the motor cortex, internal decompression down to a thin wall is particularly important because it minimizes cortical injury. Conversely, dissecting the tumor out as one piece usually impairs motor cortical function. In such cases, weakness of the opposite leg may be accompanied by shoulder weakness because their anatomical representations lie close together in the parasagittal region.
Case 2. A 40-year-old woman had a frontal parasagittal meningioma anterior to the motor cortex. She presented with headache, declining memory, and one generalized seizure with loss of consciousness. Neurological examination was normal except for early papilledema. C.T. showed a left frontal parasagittal tumor anterior to the motor cortex. Craniotomy exposed the superior sagittal sinus. Opening the dura revealed tumor at the cortical surface of the superior frontal gyrus, unattached to the dura. Its medial side adhered to the sinus wall. A large cortical vein lay against its posterior aspect, with no vein visible anteriorly (Figure 7.73A).
Removal required excision of the cortex covering the tumor. This cortex had no important function and had been thinned by tumor pressure. Enough brain had to be removed to expose the tumor margins, allowing easy removal without brain retraction. The large posterior vein required protection. After cortical excision, the attachment to the sinus wall became visible. Draw the tumor laterally and divide it along the sinus wall, carefully protecting the cortical vein that curves forward to enter the sinus. Once detached, the entire tumor can be removed (Figure 7.73B, C). Alternatively, dissect the tumor using suture traction weighted with arterial clamps as described above, finally dividing the remaining pedicle attached to the sinus.
Figure 7.73. Parasagittal meningioma attached to the superior sagittal sinus. A. Superior frontal cortex covers the tumor, with a large cortical vein posteriorly. B. The extent of cortical excision permitting complete tumor removal while preserving the cortical vein. C. The meningioma specimen.
Approaching a subcortical parasagittal meningioma by removing brain whose excision produces no clinical neurological deficit provides wide exposure with little retraction and a low risk of cortical vein injury. This is suitable for parasagittal tumors in the frontal lobe anterior to the motor cortex, parietal lobe, and occipital lobe. Choose a corridor without a large cortical vein and preserve the motor cortex.
Original pages 765–768
Falx Meningioma
Falx meningioma lies deep in the cerebral midline, covered by cortex. Access is difficult and dangerous because cortical bridging veins obstruct the approach and limit brain retraction (Figure 7.74). The craniotomy should cross the midline to expose the sagittal sinus. Open the dura with its hinge at the sinus, inspect the cortical veins, and select a route that preserves them. There are two approaches.
1) Retract the medial cerebral surface laterally without excising brain. Cortical veins may limit exposure. Dividing certain unimportant bridging veins may permit greater retraction. Draining CSF through a ventriculostomy also reduces the amount of retraction required.
2) Excise a corridor of brain as wide as the tumor, exposing it without retraction. This can be done in the frontal lobe anterior to the coronal suture or motor cortex. Choose a site without large cortical veins; small obstructing veins may be divided. If a large cortical vein crosses the middle of the tumor, remove brain anterior and posterior to it while preserving the bridging vein entering the sinus (Figure 7.75). This creates two small access corridors. Remove the tumor in small pieces, since extracting a large piece may tear the bridging vein.
AI-enhanced and colorized image · Switch to view the originalFigure 7.74. A falx meningioma expands against the medial surfaces of both cerebral hemispheres and is not visible from the brain surface.AI-enhanced and colorized image · Switch to view the originalFigure 7.75. Excision of noneloquent brain overlying a falx meningioma to create an access corridor. A. Superior view of the brain. B. Section through the brain.
During removal, preserve the anterior cerebral artery and its major branches beneath the tumor, which give off tumor feeders. Begin dissecting along the falx, using bipolar coagulation to interrupt dural feeding vessels. At the same time, remove tumor adjacent to the falx to create a channel allowing deeper access. On reaching its inferior margin, the tumor is detached from the falx. Next separate the tumor from the brain. Remove its interior piecemeal with an electrical loop to reduce its size and facilitate separation of the wall from cortex. Lift the anterior wall and push it posteriorly to expose the anterior cerebral artery and its branches. Coagulate and divide tumor feeders, finally freeing the mass (Figure 7.76A, B, C). Before using the electrical loop, inspect the angiogram for vessels running through the tumor, since the loop could divide them.
Alternatively, use scissors to cut the falx circumferentially along the tumor margin. Do not use electrical cutting, which may injure the opposite hemisphere. This interrupts the dural blood supply. After completing the falx incision, place sutures through the dura and tumor anteriorly and posteriorly for traction, exposing the anterior cerebral artery and its feeding branches. Coagulate and divide these branches to remove the tumor (Figure 7.77).
An ultrasonic aspirator now makes removal of such deep tumors easier and less dangerous. Begin aspiration adjacent to the falx to interrupt the blood supply, then work outward in all directions toward the tumor wall. Separate the wall from vessels and brain as described above.
Original pages 768–771
Bilateral Falx Meningioma
In bilateral falx meningioma (Figure 7.76A), do not attempt to divide the falx and dissect both sides out together. The author prefers first to remove the larger component by the method described above, creating access to the opposite component. Incise the falx around that tumor's margin; C.T. indicates the necessary extent. Once the falx has been cut circumferentially, use it for traction to separate the tumor from the opposite hemisphere's cortex. Identify the anterior cerebral artery and tumor-feeding branches as described above, then coagulate and divide those branches. The contralateral tumor can finally be lifted out (Figure 7.78).
AI-enhanced and colorized image · Switch to view the originalFigure 7.76. Removal of a falx meningioma proceeds as follows. A. Divide feeding vessels at the falx. B. Remove the tumor interior to reduce its size. C. Divide tumor-feeding branches of the anterior cerebral artery.AI-enhanced and colorized image · Switch to view the originalFigure 7.77. Incising the falx around the margin of a falx meningioma.AI-enhanced and colorized image · Switch to view the originalFigure 7.78. Removal of the contralateral component of a falx meningioma.
Original pages 771
B. Convexity Meningioma
This refers to a meningioma arising on the cerebral cortical surface, unattached to the superior sagittal sinus or falx and not situated on the underside of the brain. It may arise anywhere but commonly lies near the parasagittal region without attaching to the superior sagittal sinus. Approximately 70% of convexity meningiomas lie anterior to the Rolandic fissure.(106)
Original pages 771–772
Symptoms and Signs
These depend on tumor location. Frontal meningiomas anterior to the coronal suture are often large because this site rarely produces localizing symptoms. Instead, they cause raised intracranial pressure and personality changes.
Meningiomas over the motor and premotor cortex usually cause localizing symptoms, most often beginning with seizures affecting the limbs opposite the tumor. Jerking starts in the contralateral hand, arm, and face, with the eyes and head turning toward the convulsing side. Todd's paralysis follows. As the tumor enlarges, arm monoparesis gradually develops, followed by leg weakness. These changes progress slowly because the tumor is benign and slow-growing. A dominant-hemisphere tumor also causes dysphasia.
Parietal meningiomas often begin with sensory epilepsy caused by postcentral gyrus irritation. Patients describe an electric-shock sensation in the arm. Because this gyrus adjoins the motor cortex, limb jerking commonly accompanies it. A large tumor causes loss of parietal cortical sensation and, in the dominant hemisphere, receptive dysphasia.
Occipital meningiomas are very rare. When present, they are usually large and associated with raised intracranial pressure. Localizing signs include homonymous hemianopia. Some patients have seizures consisting of flashing lights, a visual hallucination.
Temporal meningiomas also commonly present as large masses causing raised intracranial pressure, contralateral facial and arm weakness, and various homonymous visual-field defects depending on location. Dominant-hemisphere tumors may cause dysphasia. Some patients have seizures affecting the opposite arm and face.
Original pages 772
Diagnosis of Convexity Meningioma
Diagnosis depends on the location-specific symptoms and signs described above. Because meningiomas grow slowly, symptoms evolve gradually and may take years to become obvious. This sometimes makes distinction from a benign glioma difficult, requiring additional features. A convexity meningioma may show:
1) Skull hyperostosis over the tumor, sometimes producing a hard bony swelling on the head (Figure 6.15).
2) Enlargement of scalp vessels directed toward the tumor (Figure 7.67).
3) Enlarged middle meningeal arterial grooves, neovascularization, calcification, and enostosis on skull radiographs.
4) Enlargement of the middle meningeal artery and its branches on angiography. Tumor staining begins in the arterial phase and persists into the venous phase; some tumors have a sunray appearance.
5) C.T. and MRI clearly show a mass attached to the convexity dura.
Original pages 772–780
Treatment of Convexity Meningioma
Meningiomas here are easier to remove than at other sites because they lie on the brain surface and their relationships are readily visible. Complete removal and cure are therefore usually possible. Exceptions are tumors in the Sylvian fissure and over the motor cortex near the superior sagittal sinus, where important large arteries and veins make removal difficult and dangerous.
The usual operative principles apply:
1) If the tumor adheres to the dura, incise the dura circumferentially close to its margin, interrupting feeding vessels and providing a means of traction to roll the tumor toward the brain surface.
2) If the tumor is large but not highly vascular, reduce its size internally, then separate its wall from the cortex and divide cortical vessels supplying it.
3) Apply traction to the tumor. Avoid excessive brain retraction, which may injure brain tissue.
4) Sweep a finger along the meningioma margin, clipping and dividing encountered vessels, then scoop out the tumor. This is a very crude technique for brain tumor surgery because it damages brain and vessels. Nevertheless, it removes the whole mass rapidly with little blood loss. It is an old method dating to Cushing and Dandy. Once the entire tumor has been removed, everything becomes quiet and bleeding stops. Thus, this technique is suited to a meningioma with uncontrollable bleeding, no operative progress, and continuous major blood loss without any sign of stopping. Reserve it as a last resort for convexity tumors outside important areas. Do not use it for meningiomas beneath the brain, where cranial nerves and major vessels may be injured.
The following cases illustrate convexity meningioma removal.
Case 1: Convexity meningioma over the left motor area. A 35-year-old woman had her first seizure, with jerking of the face, arm, and hand, while teaching. She remained conscious but could not speak during the seizure. Examination on arrival at hospital was normal. This history is important: a first seizure in an adult must always raise suspicion of a brain abnormality, here localizing to the facial motor area. Immediate investigation is required; anticonvulsants alone are insufficient. Among cerebral abnormalities, tumors are a common cause. Investigation demonstrated a mass in the facial motor cortex.
A large craniotomy was unnecessary because the seizure history and investigations indicated a small localized tumor. After opening the skull, the dura showed evidence of tumor attachment. Palpation defined its margins, and the dura was incised around them. Begin the incision away from the motor cortex to protect it. Once the tumor is visible, use a loupe or microscope to divide the intervening arachnoid accurately without damaging cortical vessels. After completing arachnoid dissection, suture and tie the dura together with the tumor, attaching an arterial clamp to the thread to lift the mass by its weight. Meanwhile, gently separate it from cortex, coagulating and dividing feeding vessels, until removal is complete. The same method can be used for a large surface convexity meningioma. Correct technique preserves cortex and cortical vessels (Figure 7.79). Patients can return to normal work and be cured. The surgeon's skill is therefore important in meningioma surgery.
Figure 7.79. A large surface convexity meningioma can be removed completely without damaging cortex or blood vessels.
Case 2: Large subcortical frontal meningioma. This patient presented with raised intracranial pressure, memory impairment, and personality changes. Angiography showed a large right frontal tumor anterior to the premotor area. Its size required a wide craniotomy to display its margins and the local cortical and vascular anatomy. Opening the dura revealed tumor beneath the middle and inferior frontal gyri. The cortex covering its outer wall was markedly thinned by pressure and showed degenerative changes (Figure 7.80A).
The cortical opening must be wide enough to show the tumor margins while preserving healthy cortex. A linear incision would inadequately expose this large tumor. Instead, excise the thin cortex in a circle to expose the entire margin (Figure 7.80B). This adds no functional loss because compression has already rendered this tissue nonfunctional, and the cortex here has relatively little clinical importance. After cortical excision, internal pressure lifts the mass slightly. Upward traction allows easy separation from the underlying brain. Coagulate and divide vessels entering the tumor and insert cotton patties between it and the brain to support its elevation. The whole tumor can ultimately be removed without prior internal debulking.
Sometimes sutures must be placed at several tumor corners and weighted with arterial clamps (Figure 7.81A, B, C), as described earlier, to lift the mass out intact. These sutures provide traction for sequential separation from the brain.
This method suits a subcortical tumor close to the surface in a clinically silent area where the thinned cortex is already nonfunctional. Do not use it in important regions such as the motor area or speech center. There, preserve as much cortex as possible in the hope of postoperative functional recovery.
An ultrasonic aspirator now permits a smaller cortical opening. Aspirating the tumor interior in all directions reduces its size, after which its wall can be removed with very little brain injury, benefiting the patient. For a highly vascular angiomatous meningioma, major feeding vessels must be coagulated and divided before opening the tumor wall. Circumferential external dissection is therefore preferable to internal debulking intended to reduce its size. Internal removal causes major blood loss; this was the error in Case 3, which nearly killed the patient. Besides coagulating and dividing vessels entering the tumor wall, blood loss may be reduced by ligating external carotid branches identified as major feeders or by inducing intraoperative hypotension with sodium nitroprusside.
Figure 7.80. Right frontal subcortical meningioma. A. The inferior and middle frontal cortical convolutions have been compressed and thinned. B. Removing the overlying cortex exposes the tumor and greatly facilitates removal.Figure 7.81. Removal of a subcortical meningioma. A. Wide excision of thinned, noneloquent brain exposes the tumor margins. B. Sutures weighted with arterial clamps at several points lift the tumor, facilitating easy, complete removal. C. Cerebral cortex after tumor removal.
Case 3: Angiomatous temporal meningioma. A 36-year-old woman had headache, blurred vision, and left facial numbness for one year. During the 2–3 months before admission, right-sided limb weakness and difficulty speaking developed. Examination showed mild motor dysphasia, papilledema, homonymous superior quadrantanopia, mild left ptosis, impaired left facial sensation, and right facial weakness (Figure 7.82A). A left temporal tumor was diagnosed. Left carotid angiography showed a large tumor supplied by both internal and external carotid arteries, indicating meningioma. The middle meningeal artery was enlarged and gave numerous tumor branches (Figure 7.82B, C), while the internal carotid contribution was small. The plan was to approach the middle meningeal artery first to interrupt the blood supply, then internally debulk the mass to facilitate safe separation from the middle cerebral artery. A frontotemporal craniotomy encompassed the whole tumor and exposed the Sylvian fissure. Temporal bone was removed low down to expose the proximal middle meningeal artery, but the large tumor prevented visualization of the foramen spinosum. Only visible branches could therefore be suture-ligated, partially reducing the blood supply. Opening the dura revealed a red-gray tumor unattached superiorly but adherent laterally. Bipolar coagulation was used to separate its wall from the dura and divide entering vessels. Its size made this difficult and prevented complete disconnection. Partial tumor removal was therefore attempted to create access to the proximal middle meningeal artery. This caused continuous bleeding and very slow progress. Despite induced hypotension, blood loss reached 15 bottles. Ultimately, however, the entire mass was removed and the patient recovered sufficiently to return home.
Figure 7.82. A patient with a left temporal meningioma. A. Left ptosis and right facial weakness. B. Arterial-phase carotid angiogram showing middle meningeal arterial supply. C. Capillary-phase carotid angiogram showing tumor staining.
This case shows how a large tumor obstructs access to its feeding vessels. Failure to interrupt the proximal supply results in major bleeding during internal debulking. Had external carotid ligation in the neck been planned first, as suggested by the lateral angiogram, this complication would probably have been avoided and blood loss should have been much smaller.
Original pages 780–782
Case 4: Sylvian Meningioma
Meningiomas at this site are very difficult to remove because the middle cerebral artery and vein lie against their medial surface. Some extend into the posterior frontal region and anterior temporal fossa. Dominant-hemisphere tumors are especially difficult and require greater care because Broca's speech center lies near the Sylvian fissure.
A 40-year-old female vendor had headache and a heavy-headed sensation without vomiting for nine months. During the three months before admission, she collided three times with pedal tricycles on her left while cycling, sustaining minor arm injuries but no head injury. Two months later, she had two generalized seizures with loss of consciousness, beginning in the left face and spreading to the limbs. Examination showed early papilledema, left homonymous hemianopia, and mild left facial and arm weakness. A right temporal tumor was diagnosed. C.T. showed a large right Sylvian fissure mass whose lateral wall abutted the skull (Figure 7.83A). Carotid angiography demonstrated supply from both external and internal carotid arteries, characteristic of meningioma.
A frontotemporal craniotomy was required, with its anterior bony margin extending low to the lateral lesser wing to expose the tumor's anterior margin. The principles were the same as for meningiomas elsewhere. First, after opening the skull, ligate the middle meningeal artery as low as possible to interrupt the tumor supply, then open the dura. Identify the Sylvian fissure posterior to the tumor and correlate this with the middle cerebral artery's angiographic position. Protect these vessels throughout, particularly the Sylvian vein, whose division may cause fatal cerebral swelling. In this case, the middle cerebral artery was displaced upward and medially (Figure 7.83B). Do not dissect a meningioma here out intact, because Sylvian vessels are easily damaged. First remove its interior until it is greatly reduced and the vessels become visible, then carefully separate the remaining wall from them using a loupe or microscope. An electrical loop may be used, but readily endangers the middle cerebral vessels. Their angiographic position indicates a safe depth of removal; palpating the residual mass also helps.
Figure 7.83. A. C.T. showing a large Sylvian meningioma. B. Carotid angiogram showing tumor staining.
An ultrasonic aspirator is now well suited to tumors here and at the skull base. It safely removes the interior down to a thin wall, exposing small intratumoral vessels for easy bipolar hemostasis. Draw the residual wall upward, downward, or forward to reveal feeding branches from the middle cerebral artery. Coagulate and divide these with bipolar instruments to free the tumor.
Original pages 782
C. Olfactory Groove Meningioma
This meningioma arises at the junction of the posterior cribriform plate and planum sphenoidale.(107) The region produces few symptoms, so patients usually present with a large mass in the midline of the anterior skull base. Initially unilateral, the tumor subsequently expands to both sides.
Original pages 782–783
Symptoms and Signs
Its location places the olfactory nerve and prefrontal area at risk. Initially, anosmia develops on the tumor side and subsequently on the other side, but patients often fail to notice it for years. A large mass causes headache and blurred vision from raised intracranial pressure, together with personality and mental changes, impaired memory, and poor concentration. These changes are less severe than the dementia associated with a large frontal glioma. Some patients have generalized seizures. Posterior extension may cause Foster–Kennedy syndrome: compression of one optic nerve produces optic atrophy or blindness, while raised intracranial pressure causes contralateral papilledema.
Original pages 783–784
Diagnosis of Olfactory Groove Meningioma
The important clinical combination is unilateral or bilateral anosmia with personality change. Radiological abnormalities include:
1) Destruction of the cribriform plate or hyperostosis of the planum sphenoidale on skull radiographs.
2) C.T. and MRI are important, showing a large round mass in the midline of the anterior cranial fossa, with mild surrounding cerebral edema (Figure 7.84).
Figure 7.84. C.T. showing an olfactory groove meningioma.
3) Lateral carotid angiography shows upward and backward bowing of the frontopolar and anterior cerebral arteries (Figure 6.49). Because the tumor is midline, both vessels remain elevated in the midline. A unilateral tumor instead displaces them toward the opposite side. Feeding vessels include the anterior ethmoidal artery, anterior middle meningeal branches, and ophthalmic artery, entering at the midline of the anterior skull base. This is therefore the first point to approach surgically to interrupt the tumor blood supply.
Original pages 784–789
Treatment of Olfactory Groove Meningioma
Surgery may use a bifrontal or unilateral craniotomy. The author prefers a unilateral opening, which allows removal on both sides without dividing the superior sagittal sinus. An ultrasonic aspirator greatly facilitates this. For a midline mass, the author always opens on the right because it is the nondominant hemisphere and the surgeon is right-handed. For a unilateral tumor, open on that side; if bilateral but larger on one side, open on the larger side.
1) Unilateral frontal approach. Place the patient supine with the face turned approximately 45° away. Make a transcoronal incision and a frontal craniotomy extending down to the orbital rim and medially close to the midline. If the frontal sinus is opened, remove its mucous membrane, pack it with muscle, and suture pericranium over it as another layer. Reduce intracranial pressure with mannitol, hyperventilation, or, in some cases, frontal ventriculostomy to drain CSF. Open the dura and use a self-retaining retractor to gently elevate the lateral anterior frontal lobe upward and medially, exposing the orbital roof and lesser wing. This reveals the tumor's inferior margin at the cribriform plate and planum sphenoidale. Little frontal retraction is needed at this stage because work is confined to the skull base. Bipolarly coagulate and divide tumor attachments at the cribriform plate and planum to interrupt its feeding vessels. Then remove the interior with a cautery loop or, preferably, an ultrasonic aspirator. Use the anterior cerebral artery's angiographic position to judge how deep and posteriorly the loop may safely pass; intermittently palpating the remaining mass provides additional guidance. Remember that the anterior cerebral artery may be encased by tumor and could be divided by the loop. After substantial debulking leaves a thin wall, gently separate it from cortex and remove the wall on the approach side, leaving only the opposite component. Divide the falx attachment to the crista galli, then cut along the contralateral tumor margin. This exposes its posterior extension toward the tuberculum sellae and optic nerve. Do not dissect from anterior to posterior, which readily injures the optic nerve and vessels. Instead, follow the lesser wing medially to the anterior clinoid, a landmark for the optic nerve immediately medial to it. Separate and elevate the tumor wall, dissecting forward to expose the optic nerves, internal carotid artery, and anterior cerebral artery. Follow the latter toward the midline to establish its course, coagulating and dividing tumor-feeding branches to free it. Internal removal can then proceed more confidently without fear of injuring this artery. Use a loupe or microscope to separate tumor from the tuberculum sellae, both optic nerves, chiasm, and anterior cerebral artery. If exposure has been inadequate at any stage, some brain may be excised if necessary. The author considers extensive frontal lobectomy unnecessary and has never performed it, yet has achieved complete olfactory groove meningioma removal (Figure 7.85).
Debulk the contralateral component internally, or aspirate it ultrasonically, until only a thin wall remains. Separate this from the opposite frontal cortex to complete removal. Char residual tumor attached to the planum sphenoidale and cribriform dura with electrical coagulation. Cover the cribriform region with muscle and Gelfoam to prevent CSF rhinorrhea (Figure 7.86).
2) Bifrontal approach.(108) Place the patient supine, face straight, neck extended, and head slightly lowered so the frontal lobes fall away, reducing retraction. Make a transcoronal incision and bifrontal bone flap down to both orbital rims. Open the anterior dura bilaterally, suture-ligate and divide the superior sagittal sinus, and divide the falx. Both frontal lobes are exposed. Coagulate and divide any bridging veins, which are generally small. Use self-retaining retractors to separate the frontal lobes and expose the tumor (Figure 7.87). Debulk with a cautery loop or ultrasonic aspirator until only a thin wall remains. Turn the wall to expose its dural attachment, coagulate the wall and dural feeders, and divide the attachment. The posterior remnant often conceals the anterior cerebral artery and optic nerves. Draw its wall forward to expose them. This is difficult because the posterior frontal lobes cannot be separated widely; marked posterior tumor extension increases the difficulty. Gradual ultrasonic aspiration down to the wall, however, facilitates microscopic separation from the anterior cerebral artery, optic nerves, and chiasm. After complete removal, suture the dura and sagittal sinus together.
AI-enhanced and colorized image · Switch to view the originalFigure 7.85. Unilateral frontal approach to an olfactory groove meningioma. A. Route to the tumor base. B. Creating a narrow channel at the base and coagulating and dividing feeding vessels. C. Internal tumor reduction with an ultrasonic aspirator.AI-enhanced and colorized image · Switch to view the originalFigure 7.86. Removal of the contralateral olfactory groove meningioma component after removal of the right-sided component.AI-enhanced and colorized image · Switch to view the originalFigure 7.87. Bifrontal approach to an olfactory groove meningioma.
This method exposes both sides of the tumor simultaneously and avoids frontal lobectomy, but has several disadvantages:
1) Bridging veins entering the sinus must be divided.
2) Both frontal lobes require retraction, causing bilateral contusion.
3) Access to the posterior tumor is narrow, making separation from the anterior cerebral artery and optic nerves difficult. It is therefore not a particularly good method.
Original pages 789
D. Tuberculum Sellae Meningioma
Original pages 789–790
Symptoms and Signs
Tuberculum sellae tumors are usually relatively small because their proximity to the optic nerves and chiasm causes visual disturbances resembling those of pituitary adenoma, namely bitemporal hemianopia. Patients therefore seek medical attention earlier than with meningiomas elsewhere. Untreated, both eyes become blind. The commonest pattern is unequal visual loss: acuity declines or the field narrows in one eye first, later involving both.(107,109) (Figure 7.88) Because the tumor is relatively small, there are no symptoms of raised intracranial pressure.
AI-enhanced and colorized image · Switch to view the originalFigure 7.88. Gradual growth of a tuberculum sellae meningioma damages the optic nerve, chiasm, and pituitary gland.
Original pages 790
Diagnosis
In addition to the symptoms and signs above, radiological investigations establish the diagnosis by showing:
1) Skull radiographs may reveal tuberculum sellae hyperostosis (Figure 7.89). Because the tumor arises above the sella and rests on the diaphragma sellae, the sella turcica remains unchanged. Impaired acuity and abnormal fields together with tuberculum hyperostosis and a normal sella turcica therefore permit a diagnosis of tuberculum sellae meningioma with almost 100% certainty.
2) Anteroposterior angiography shows elevation of the anterior cerebral artery's A1 segment (Figure 7.90). Lateral views may show upward and posterior bowing of its proximal segment and downward displacement of the internal carotid artery. Feeders from the ophthalmic, posterior ethmoidal, and middle meningeal arteries may also be visible.
3) C.T. clearly shows the size and characteristics of a hyperdense mass at the tuberculum sellae (Figure 7.91).
4) Sagittal MRI clearly displays the meningioma and its relationship to the optic nerve.
Original pages 790–794
Treatment of Tuberculum Sellae Meningioma
The optic nerves, chiasm, internal carotid artery, and anterior cerebral artery require particular care during surgery. A large tumor extending posteriorly may encase them, making removal dangerous.
Approach through the right, nondominant hemisphere. Position the patient supine with the right shoulder elevated and face turned left approximately 30°. Make a transcoronal incision and frontotemporal craniotomy with its anterior margin as close as possible to the right orbital rim. Reduce intracranial pressure before opening the dura. Approach as for a pituitary tumor: retract the frontal lobe with a self-retaining retractor to expose the orbital roof and lesser wing, then follow the latter to the anterior clinoid process. Here the tumor margin and optic nerve, medial to the clinoid, become visible. The anterior cerebral artery lies behind the tumor. Divide the arachnoid over the optic nerve, chiasm, and anterior cerebral artery. If the tumor is small with little posterior extension, separate it from these structures and protect them with cotton patties. A large mass requires internal reduction first. Begin by coagulating and dividing its dural attachment to interrupt the blood supply, then remove the interior with a small cautery loop. Carefully study the anterior cerebral artery's angiographic position beforehand to avoid injury. An ultrasonic aspirator is preferable, removing tumor down to a thin wall without the loop's risk of cutting the artery. When using a cautery loop, work from anterior to posterior and stop near the posterior wall. Draw that wall forward to expose the anterior cerebral artery and its branches, coagulating and dividing any tumor feeders. After separation, remove the entire wall from the tuberculum sellae and electrically coagulate all residual tumor on the dura (Figure 7.92).
Figure 7.89. Tuberculum sellae hyperostosis in a patient with meningioma.Figure 7.90. Carotid angiogram showing elevation of the anterior cerebral artery and lateral displacement of the internal carotid artery.Figure 7.91. C.T. showing a tuberculum sellae tumor, histologically confirmed as meningioma.
If tumor is firmly attached to the optic nerve, chiasm, or optic nerve vessels and cannot be completely separated, a thin remnant may be left to preserve optic nerve function. Conversely, attempting total removal at the expense of these vessels or the nerve itself may cause postoperative blindness.
In the author's experience, visual recovery after tuberculum sellae meningioma surgery has been disappointing, particularly for large tumors. Vision often worsens postoperatively because prolonged compression has already flattened and rendered the optic nerves and chiasm ischemic. Attempts at dissection then commonly worsen vision. The surgeon should explain this possible outcome to the patient.
AI-enhanced and colorized image · Switch to view the originalFigure 7.92. Surgery for a tuberculum sellae meningioma through a unilateral frontal approach.
Original printed pages 794–795
e) SPHENOID RIDGE MENINGIOMA
The sphenoid ridge forms part of the boundary between the anterior and middle cranial fossae. It lies close to the anterior Sylvian fissure and thus separates the frontal and temporal lobes. The medial two-thirds of the ridge is the lesser wing of the sphenoid bone, ending at the anterior clinoid process. The lateral third belongs to the greater wing and meets the frontal, temporal, and parietal bones at the pterion. Cushing divided sphenoid ridge meningiomas into three groups according to their site of origin: the inner third (inner or clinoidal), middle third (middle or alar), and outer third (outer or pterional) (Figure 7.93). With this classification, it may be difficult to distinguish middle-third from outer-third meningiomas by symptoms and signs alone. Inner-third tumors, however, are usually recognizable because cranial nerve abnormalities are relatively prominent. Sphenoid ridge meningiomas may therefore be divided into two clinical groups, inner and outer, which differ in their manifestations and require different operative planning and techniques. Nevertheless, very large tumors at either site may produce overlapping manifestations.
AI-enhanced and colorized image · Switch to the original imageFigure 7.93 Three sites of sphenoid ridge meningioma. 1. Inner third of the sphenoid ridge (inner or clinoidal). 2. Middle third of the sphenoid ridge (middle or alar). 3. Outer third of the sphenoid ridge (outer or pterional).
Original printed pages 795–796
Symptoms and signs
The manifestations of sphenoid ridge meningioma may be divided into two groups.
1) INNER SPHENOID RIDGE MENINGIOMA These tumors arise close to the optic nerve, chiasm, oculomotor, trochlear, abducens, and trigeminal (V1,V2) nerves, cavernous sinus, superior orbital fissure, internal carotid artery, and its branches. The presenting symptom is therefore gradually progressive visual loss in the eye on the side of the tumor, developing over years. Fundus examination shows primary optic atrophy on the side where the optic nerve is compressed. Various visual field defects may occur, depending on which portion of the optic nerve is compressed: nasal hemianopia from lateral compression of the nerve, for example, or blindness in the ipsilateral eye. Temporal hemianopia in the opposite eye indicates associated chiasmal compression. As the tumor enlarges it compresses adjacent cranial nerves, including the oculomotor, trochlear, abducens, and trigeminal nerves. The oculomotor nerve is affected more often than the others. Some patients report facial pain or numbness in the distribution of V1. When the tumor is large, mild exophthalmos and chemosis may occur, either from impaired venous drainage from the eye into the cavernous sinus or from tumor extension into the orbit. If the tumor causes raised intracranial pressure, Foster–Kennedy syndrome may be present: primary optic atrophy on the side of the tumor and papilledema in the opposite eye.
2) OUTER SPHENOID RIDGE MENINGIOMA Tumors in this region do not cause the cranial nerve palsies described in the first group because they lie farther laterally. Patients are consequently often diagnosed only when the tumor is very large and produces manifestations of raised intracranial pressure, including headache and papilledema. There may be no localizing signs. However, extension toward the frontal and temporal lobes may cause seizures in some patients. A large mass may cause contralateral facial weakness, and a tumor in the dominant hemisphere may also produce motor dysphasia.
Meningiomas in this region take two forms: a discrete mass (en masse) or a sheet spreading along the dura (en plaque). The former is more common and usually produces little hyperostosis. Although less common, the en plaque type may produce very marked hyperostosis of the sphenoid, orbital bones, and bones around the pterion.(111,112) Patients develop gradually progressive, nonpulsatile proptosis. Severe cases may also have swelling of the eyelids and conjunctiva, and the temple may appear fuller than on the opposite side. Proptosis results from reduction of the orbital space as its walls thicken through hyperostosis, as well as impaired venous drainage into the cavernous sinus. En plaque meningiomas usually do not produce focal cerebral signs because they spread along the dura instead of forming a large round mass compressing the brain. In a few cases, medial extension causes loss of function of the nearby cranial nerves, as in inner sphenoid ridge meningioma.
Original printed pages 796–797
Diagnosis of sphenoid ridge meningioma
A tumor at the medial end of the lesser wing produces a history of slowly progressive loss of optic, oculomotor, and trigeminal (V1) nerve function, with or without unilateral exophthalmos. Laterally situated meningiomas may produce no signs. However, gradually progressive exophthalmos and temporal bulging should suggest a meningioma in this region rather than another lesion.
Investigations supporting the diagnosis include:
1) Skull radiographs were important before CT became available but are now seldom obtained. They show hyperostosis of the lesser wing, anterior clinoid, or pterion. This is best seen on an anteroposterior skull view with the lesser wing projected in the middle of the orbit. In some cases, erosion is seen instead of hyperostosis.
2) ANGIOGRAPHY makes the diagnosis more definite by showing displacement of the internal carotid, middle cerebral, and anterior cerebral arteries, depending on the site of the tumor.
A tumor at the medial end of the lesser wing that grows upward from below elevates the proximal middle cerebral artery and internal carotid artery (Figure 6.66). If it arises above the lesser wing, the internal carotid artery and its bifurcation are displaced downward and backward. The internal carotid artery may be encased by the tumor, producing focal narrowing and segmental irregularity. Tumor staining and feeding vessels may also be seen.
A tumor at the lateral end of the lesser wing elevates and displaces the horizontal segment of the middle cerebral artery backward (Figure 7.101). A large mass also displaces the internal carotid artery medially.
3) CT and MRI clearly demonstrate the location and extent of the tumor. CT shows an enhancing hyperdense mass attached to the sphenoid ridge.
Original printed pages 797–799
Treatment of sphenoid ridge meningioma
The following important points must always be considered during surgery:
1) The internal carotid and middle cerebral arteries may be encased by the tumor (Figure 7.94). Tumor removal may therefore injure either artery. Carotid angiography should always be performed before surgery to establish whether the vessels lie within or outside the tumor and guide the surgeon’s dissection. With an ultrasonic aspirator, this problem is reduced, as illustrated below, because tumor can be aspirated without injuring the vessels. Angiography also identifies feeding arteries, such as the middle meningeal artery, and helps determine whether the external carotid artery should be ligated before tumor removal.
2) The optic nerve may be displaced or encased by the tumor. Attempts to dissect tumor from the optic nerve may cause blindness. If separation is impossible, a thin layer of tumor may be left on the nerve’s surface.
3) The oculomotor nerve is particularly liable to injury because it lies closely against the underside of the tumor.
AI-enhanced and colorized image · Switch to the original imageFigure 7.94 Inner sphenoid wing meningioma encasing the optic nerve and internal carotid artery.
4) Injury to the Sylvian vessels may be fatal. Tearing of the Sylvian vein must be prevented.
5) Complete removal of a medial lesser-wing tumor may be impossible without injuring the hypothalamus, vessels, or nerves. In such cases, resection should stop at that point.
Operative technique. Place the patient supine with the face turned approximately 60° away from the tumor. Elevate the shoulder on the operative side to prevent vascular compression from neck rotation. Perform a frontotemporal craniotomy with the medial edge of the bone flap approximately 2 cm from the midline and its lower edge sufficiently low to expose more of the anterior temporal lobe. Anteriorly, the opening should extend down to the orbital rim, as for tuberculum sellae meningioma. After opening the dura, elevate the frontal lobe along the lesser wing until the tumor is seen. If the tumor is not large, the subarachnoid space around the optic nerve may be accessible. Open the arachnoid and aspirate CSF to relax the brain and facilitate retraction. If the prechiasmatic cistern cannot be seen, perform ventricular drainage.
For an inner sphenoid ridge meningioma, identify the optic nerve, internal carotid artery, and its bifurcation. If exposure is inadequate, divide the arachnoid at the medial Sylvian fissure to separate the frontal and temporal lobes more widely. Resection follows two principles: interrupt the blood supply and reduce the bulk of the mass. I prefer to coagulate and divide the tumor’s attachment along the lesser wing, proceeding from lateral to medial as far as the anterior clinoid process. This avoids injury to the internal carotid artery and optic nerve because their positions here are constrained by bone and do not change. Once the internal carotid artery is identified, dissect tumor from it and from the optic nerve, proceeding from proximal to distal with microsurgical instruments and the operating microscope. After locating the internal carotid artery, look for the middle cerebral artery, usually situated above and behind the tumor. It can be identified distally near the medial Sylvian fissure and followed medially for a clear view. Once the vessels are clearly seen, remove tumor internally with loop cautery or an ultrasonic aspirator, leaving a thin wall. Do not use the loop at the upper posterior part of the tumor, where it might divide the middle cerebral artery. Then turn the residual tumor wall in various directions to expose and separate the vessels and optic nerve from it (Figure 7.95)
Original printed pages 799–802
Case 1: Inner lesser wing meningioma; incomplete removal with complications
A 38-year-old man presented with progressively blurred vision in the left eye and radiating pain in the left orbit for one year. Six months before admission he developed diplopia and left ptosis, together with increasing prominence of the left eye. Examination showed mild left exophthalmos and left ptosis (Figure 7.96). Visual acuity was 20/20, 6/36. The left optic disc was slightly pale. The left pupil was dilated and unreactive to light, with paralysis of the extraocular muscles supplied by the oculomotor nerve. Left corneal sensation was reduced. CT showed a tumor at the medial end of the left lesser wing. Coronal images showed encasement of the internal carotid artery (Figure 7.97 A, B). Carotid angiography showed superior and medial displacement of the internal carotid artery. The middle cerebral (M1) and anterior cerebral artery (A1) were elevated (Figure 6.66).
AI-enhanced and colorized image · Switch to the original imageFigure 7.95 Operation for inner sphenoid wing meningioma. A. Coagulation and division of the tumor attachment along the lesser wing and anterior clinoid to expose the internal carotid artery and optic nerve. B. Internal tumor debulking with loop cautery or an ultrasonic aspirator, followed by separation of the tumor wall from the internal carotid artery and optic nerve.Figure 7.96 Left ptosis and pupillary dilatation with mild left exophthalmos in a patient with inner sphenoid wing meningioma.Figure 7.97 CT of inner sphenoid wing meningioma. A. Axial view. B. Coronal view. Note tumor encasement of the internal carotid artery (arrow).
A frontotemporal craniotomy was performed, using the approach described above. The tumor encased the internal carotid artery and compressed the optic nerve from above and laterally. Dissection along the lesser wing and anterior clinoid exposed the internal carotid artery, permitting separation of tumor from the upper surfaces of the artery and optic nerve under the microscope. Once their courses were identified, internal debulking with an ultrasonic aspirator or loop was continued posteriorly, because CT showed extension toward the left cerebral peduncle. The tumor wall was then reflected forward to expose the oculomotor nerve and separate it from the tumor. Anteriorly, the nerve was firmly adherent, so further dissection was stopped. Tumor in this region was nevertheless thinned to a small residual wall to reduce pressure on the nerve. Separation from the optic nerve was easy because the nerve was not encased. Separation from the internal carotid artery was very difficult, however. Traction and instrumentation provoked arterial vasospasm, necessitating termination of the operation. Postoperatively, vision improved but ptosis increased. Transient right hemiparesis occurred, followed by recovery of normal strength.
This case reminds the surgeon that complete removal of inner lesser wing meningioma is difficult and that attempts at total removal often produce complications involving the internal carotid artery, optic nerve, or oculomotor nerve. Continuing dissection despite internal carotid vasospasm in this patient might have caused permanent hemiplegia. Because the lesion was in the dominant hemisphere, speech could also have been lost. Leaving a remnant of a very slowly growing meningioma with little disability is preferable to complete removal at the cost of severe disability.
Original printed pages 802–805
Case 2: Sub-lesser wing and parasellar meningioma; complete removal
A 39-year-old woman had a history of headache and right orbital pain for two months. The right orbital pain subsequently increased, with blurred vision and occasional diplopia. One month before admission she developed right ptosis and right facial numbness. Neurological examination showed visual acuity of 20/200, 20/20, normal visual fields, and no optic atrophy or papilledema. There was mild right ptosis and weakness of the medial rectus, inferior rectus, superior oblique, and inferior oblique muscles. The right pupil measured 3 mm and reacted sluggishly; the left measured 2 mm and reacted briskly. There was right facial numbness in the V1 distribution of the trigeminal nerve.
These findings constituted a syndrome localizing to the superior orbital fissure. CT showed a hyperdense mass at the inner lesser wing and parasellar region (Figure 7.98). Carotid angiography showed focal narrowing and irregularity of the internal carotid artery at the distal siphon and proximal clinoid segment. Frontotemporal craniotomy revealed a red tumor beneath the medial lesser wing and in the parasellar region, supplied by numerous small vessels from the dura of the lesser wing. The tumor encased the internal carotid artery and compressed the optic nerve from below (Figure 7.99 A).
The edge of the lesser wing had to be removed with a dental drill to expose the tumor underneath. An ultrasonic aspirator was then used for removal and bipolar coagulation for hemostasis. This permitted satisfactory removal of tumor surrounding the internal carotid artery and elsewhere (Figure 7.99 B). The patient’s neurological function returned to normal.
Figure 7.98 CT showing an inner lesser wing and parasellar meningioma.Figure 7.99 Operation for inner lesser wing meningioma. A. A red tumor beneath the lesser wing and in the parasellar region completely surrounds the internal carotid artery. B. Tumor removal after resection of the lesser wing, using an ultrasonic aspirator. Note that the internal carotid artery is no longer encased.
This case shows that resection of the lesser wing is sometimes necessary to expose tumor concealed beneath it, allowing easy and complete removal with an ultrasonic aspirator.
Outer sphenoid ridge meningiomas are easier to operate on than inner tumors because the optic nerve and internal carotid artery are less involved, except with very large masses. The important structures to protect are the Sylvian arteries and veins, especially the veins. I have seen severe cerebral swelling and death after a middle cerebral vein was torn during tumor dissection. The middle cerebral artery usually lies above and behind the tumor. In the dominant hemisphere, Broca’s area must always be protected, because frontal lobe retraction for exposure may injure it. Marked hyperostosis around the pterion may complicate craniotomy. Several closely spaced burr holes should be made and joined with a rongeur. Patients with exophthalmos may require removal of hyperostotic superior and lateral orbital walls to allow the eye to return to its normal position.
For removal, perform a frontotemporal craniotomy extending well down into the temporal fossa to facilitate exposure. Before opening the dura, suture-ligate the feeding middle meningeal artery. Avoid direct retraction of the Sylvian fissure. Instead, use the approach described above, elevating the frontal lobe to expose the tumor. Coagulate and divide its attachment to the sphenoid ridge to interrupt the blood supply, then debulk it internally. It can then be separated from the frontal lobe, Sylvian fissure, temporal lobe, and middle cerebral artery (Figure 7.100)
If the mass extends more into the temporal than the frontal fossa, resection of the anterior temporal lobe may facilitate exposure, as in the following case.
Original printed pages 805–807
Case 3
A 40-year-old patient had experienced retro-orbital headache for one year, followed by blurred vision, occasional flashing lights, and dizziness. Relatives had repeatedly noticed brief episodes of behavioral arrest without falling or convulsive movements. Headache subsequently became progressively worse. Examination revealed early papilledema and left homonymous superior quadrantanopia. A tumor of the anterior right temporal lobe was diagnosed. Carotid angiography demonstrated an outer sphenoid ridge tumor displacing the middle cerebral artery upward, medially, and backward (Figure 7.101 A, B). A frontotemporal craniotomy was performed. An important step was removal of the temporal bone and sphenoid ridge low down toward the floor of the middle fossa. After opening the dura, abnormal cortex was seen at the anterior temporal lobe (Figure 7.102 A), with a firm mass on palpation. Resection of the temporal cortex, already thinned by compression, provided wide, clear exposure of the tumor (Figure 7.102 B) without temporal lobe retraction. Its superior extension was exposed by retracting the frontal lobe. The mass was reduced with loop cautery or an ultrasonic aspirator, while vessels from the temporal fossa and sphenoid ridge were coagulated from lateral to medial. Once substantially reduced, the tumor wall was grasped and gently separated from the temporal lobe and Sylvian vessels. Attempting to remove the tumor in one piece could be fatal.
AI-enhanced and colorized image · Switch to the original imageFigure 7.100 Operative technique for lateral sphenoid wing meningioma. A. Craniotomy for lateral sphenoid wing meningioma. B. Division of the dura around the tumor and of the middle meningeal artery to reduce the tumor’s blood supply. C. Dissection and coagulation along the sphenoid wing, followed by internal debulking with an ultrasonic aspirator and separation of the tumor wall from vessels and the brain surface.
Original printed page 807
f) TENTORIAL MENINGIOMA
These tumors arise at or near the tentorial edge. They may grow into the supratentorial or infratentorial compartment, or both, forming a so-called dumbbell tumor. Anterior and posterior tentorial tumors produce different symptoms and signs.
Original printed pages 807–809
Symptoms and signs of tentorial meningioma
Symptoms generally begin with cranial nerve dysfunction because meningiomas arise outside the brain. As the tumor enlarges, dysfunction of the compressed brainstem and cerebellum develops. Hydrocephalus or raised intracranial pressure appears late in the course. The clinical manifestations therefore depend on the site of the tentorial meningioma.
ANTERIOR TENTORIUM Tumors at the anterior tentorium mainly affect the oculomotor and trochlear nerves, as in Case 1 below. Enlargement compresses trigeminal branches and the cerebral peduncle, causing ptosis, ophthalmoplegia in the distributions of the oculomotor and trochlear nerves, ipsilateral facial numbness, and contralateral corticospinal tract signs. Upward extension toward the temporal lobe may cause temporal lobe epilepsy.
Figure 7.101 Carotid angiograms showing lateral sphenoid wing meningioma. A. Anteroposterior view: the middle cerebral artery is elevated and displaced medially. B. Lateral view: the middle cerebral artery is displaced backward and upward. Tumor staining is visible (arrows).
POSTERIOR TENTORIUM A tumor arising in the posterior half of the tentorium and growing supratentorially compresses the occipital lobe, causing a homonymous visual field defect or seizures with visual hallucinations. Infratentorial growth compresses the posterolateral midbrain and cerebellum, producing quadrigeminal plate syndrome and ipsilateral cerebellar signs.
Figure 7.102 Operation for lateral sphenoid wing meningioma. A. The anterior temporal cortex is compressed and thinned by the tumor. B. The tumor (arrow) is clearly exposed after removal of the overlying temporal cortex.
Original printed pages 809–810
Diagnosis
In addition to the symptoms and signs described above, CT or MRI provides a reliable diagnosis. Plain skull radiographs contribute little.
CT shows a markedly hyperdense mass in the tentorial region, with compression of the brainstem and cerebellum and associated hydrocephalus.
Vertebral angiography shows downward and medial displacement of the superior cerebellar artery and elevation of the posterior cerebral artery. More posterior tumors depress the great vein of Galen and internal cerebral vein. Angiography may also demonstrate a feeding tentorial artery arising from the meningohypophyseal trunk of the internal carotid artery, an important diagnostic feature of tentorial meningioma.
Original printed page 810
Treatment of TENTORIAL MENINGIOMA
This is another site where surgical removal is difficult and hazardous. The tumor lies beneath the brain, requiring a deep approach among closely adjacent critical structures: cranial nerves; the basilar, posterior cerebral, and superior cerebellar arteries; the great vein of Galen, internal cerebral vein, and basal vein of Rosenthal; the brainstem; and the cerebellum.
The approach must be selected according to the tumor’s position and direction of growth: anterior or posterior tentorium, with supratentorial or infratentorial extension.(113)
Original printed pages 810–813
Case 1: Anterior TENTORIAL MENINGIOMA
A 44-year-old patient presented with temporal and retro-orbital pain for one year. Six months before admission, progressively increasing left ptosis and diplopia began, accompanied by right arm and leg weakness, easy fatigue at work, and an unsteady gait. Examination showed left oculomotor nerve palsy (Figure 7.103). CT demonstrated an anterior tentorial tumor extending downward and medially to compress the left cerebral peduncle (Figure 7.104)
Figure 7.103 Oculomotor and trochlear nerve palsies in a patient with left anterior tentorial meningioma.Figure 7.104 CT showing left anterior tentorial meningioma.
Two approaches are possible for a tumor at this site:
1) Transsylvian approach. Perform a frontotemporal craniotomy extending well down toward the middle fossa. Divide the arachnoid at the anterior Sylvian fissure and separate the frontal and temporal lobes with a self-retaining retractor to expose the tumor. Disadvantages are: i) possible injury to the Sylvian vessels or, on the dominant side, Broca’s area; and ii) the great depth of the posterior part of the tumor.
2) Subtemporal approach. I used this approach in the present patient. Position the patient supine, elevate the shoulder on the operative side, and turn the face to the opposite side. Make a temporofrontal incision and a craniotomy extending as low as possible into the temporal fossa. After reducing intracranial pressure, open the dura and gently elevate the temporal lobe anterior to the vein of Labbé. If CSF drainage is needed for further relaxation, tap the temporal horn or open the arachnoid beside the brainstem. Once the tentorium and tumor are exposed, apply the same principles as for meningiomas elsewhere: interrupt the blood supply and debulk the tumor.
Critical structures to protect during surgery in this region include the oculomotor and trochlear nerves and the posterior cerebral and superior cerebellar arteries (Figure 7.105). The vein of Labbé, although superficial, is equally important. Avoid tearing it when retracting the temporal lobe with a self-retaining retractor. A tear produces immediate cerebral swelling that prevents further surgery. If exposure remains inadequate and the vein of Labbé is taut, remove only the necessary portion of the inferior temporal gyrus to improve exposure without excessive retraction.
AI-enhanced and colorized image · Switch to the original imageFigure 7.105 Anterior tentorial meningioma and its relationships to cranial nerves, vessels, and the brainstem.
Begin removal by incising the tentorium along the lateral tumor margin, curving anteriorly to the tentorial edge. This divides the feeding tentorial branch of the meningohypophyseal artery. Near the edge, protect the trochlear nerve, which runs forward beneath it: separate the nerve from the tentorium before cutting. The oculomotor nerve is usually compressed beneath and medial to the tumor. Next, debulk the tumor internally. An ultrasonic aspirator, if available, is preferable. Loop cautery may be hazardous here because it is unipolar and used close to the brainstem. Once the tumor is substantially reduced, grasp and turn its dural attachment or wall to expose the cranial nerves, vessels, and brainstem described above, then separate them from it. Coagulate small feeding branches with bipolar forceps before dividing them. If the tumor encases the trochlear nerve, first free the nerve to avoid injury. The operating microscope and microsurgical instruments facilitate confident, safe dissection from nerves and vessels (Figure 7.106)
Original printed pages 813–817
Case 2: SUPRA- AND INFRATENTORIAL MENINGIOMA
A 40-year-old woman had experienced headache for two years, initially intermittently. Six months before admission it became more severe, sometimes with vomiting. She subsequently noticed stiffness of both legs when walking, a tendency to veer to the right, and reduced hearing in the right ear. Examination confirmed right hearing loss and right cerebellar signs. CT showed a large tumor in the right cerebellar hemisphere and occipital lobe. The fourth ventricle was effaced, causing hydrocephalus; the right occipital horn was also effaced (Figure 7.107). Right carotid and vertebral angiography showed displacement of the posterior cerebral and superior cerebellar arteries and a feeding occipital meningeal branch, indicating meningioma.
AI-enhanced and colorized image · Switch to the original imageFigure 7.106 Steps in removal of anterior tentorial meningioma. A. Incision of the tentorium around the tumor margin, followed by internal aspiration to reduce the mass. B. Separation of the tumor wall from cranial nerves, vessels, and the brainstem.Figure 7.107 CT showing supra- and infratentorial meningioma.
Such a tumor requires a combination of two approaches: i) occipital supratentorial and ii) infratentorial. Either approach alone would not permit complete removal. Both components may be removed in one operation or in two stages. If staged, the infratentorial component should be removed first because it compresses the brainstem and fourth ventricle, producing obstructive hydrocephalus. Satisfactory removal of this component facilitates subsequent supratentorial surgery because the lateral ventricles become smaller and access improves.
Positioning. The patient may be seated with the face turned approximately 30° toward the tumor. In addition to the complications of sitting described earlier, this position requires elevation of the occipital lobe against gravity, making exposure more difficult and less satisfactory. The lobe may tear easily under retraction. An alternative is a semiprone position with the neck flexed and the head slightly turned away, bringing the incision between the midline and mastoid uppermost. The right shoulder must be pulled downward to widen the operative field, and foam padding placed beneath the chest to prevent brachial plexus compression.
Make a hockey-stick incision halfway between the inion and mastoid process, with its upper end approximately 6–7 cm above the transverse sinus and its lower end extending to the upper neck. Drape sufficiently low to permit inferior extension if a large tumor requires wide posterior fossa exposure. After incising down to the skull, strip the periosteum and spread the wound with a self-retaining retractor. Make a small occipitotemporal craniotomy above the transverse sinus, then a suboccipital craniectomy, using a rongeur to remove bone over the sinus and continuing into the occipital bone on the tumor side only. The opening should be slightly wider than the tumor. Suture-ligate feeding meningeal branches. Drain CSF through a previously placed ventriculostomy tube to reduce intracranial pressure, then open the dura above and below the tentorium, with dural flaps based on the transverse sinus. Gently elevate the occipital lobe and follow the upper tentorial surface medially to the tumor and incisura. Unimportant bridging veins may be coagulated and divided to improve exposure, but the vein of Labbé must not be torn. Next, incise the tentorium around the tumor to reduce its blood supply: lift the posterior tentorium with a hook and cut toward the incisura. As the free edge is approached, identify and protect the trochlear nerve beneath it.
With a large tumor, the transverse sinus may obstruct access and occasionally must be divided to facilitate removal. Before division, test whether this will cause cerebral swelling by clamping the ipsilateral transverse sinus and observing the brain and veins for about five minutes. If there is no bulging or venous congestion, collateral venous drainage is sufficient and the sinus may be divided.(114)
Remove the supratentorial component by bipolar coagulation and division along the tentorium. Internal debulking near the dural attachment may be necessary to permit deeper dissection along the tentorium. After detaching the tumor, debulk it internally to leave only a thin wall, which can then be separated from the occipital lobe, posterior cerebral artery, trochlear nerve, and brainstem (Figure 7.108)
Infratentorially, opening the dura may reveal cerebellar tissue overlying part of the tumor. If necessary, remove a portion that can be sacrificed without functional loss. The tumor is attached to the tentorium and the dura on the posterior surface of the petrous ridge, where its feeding vessels enter. Coagulate and divide these attachments parallel to the dura to reduce blood flow. Some internal debulking at the dural pedicle facilitates this step. Once the tumor is substantially devascularized, aspirate it internally with an ultrasonic aspirator until only a thin wall remains. Turn this wall to separate it from the fourth and fifth cranial nerves, superior cerebellar artery, brainstem, and cerebellum. Finally, suture the dura closed rather than leaving it open: removal of the large mass creates ample space and the brain is no longer tense.
Original printed page 817
g) PETROUS RIDGE MENINGIOMA
This is another site where meningioma removal is very difficult, especially at the anterior petrous ridge, because of its depth and proximity to the midbrain, fourth, fifth, and sixth cranial nerves, and posterior cerebral and superior cerebellar arteries. Large tumors often extend toward the clivus and upward into the supratentorial compartment (see the case below).
Original printed pages 817–819
Symptoms and signs
Because these tumors arise in the cerebellopontine angle, their manifestations resemble those of acoustic neurinoma, with dysfunction of the trigeminal, acoustic, and facial nerves. Anterior petrous tumors often begin with facial numbness before auditory symptoms, and some eighth-nerve function usually remains, making distinction from trigeminal neurinoma difficult. They can be distinguished from acoustic neurinoma, however, because the latter always begins with auditory symptoms. As the tumor enlarges, it compresses the midbrain and cerebellar peduncle, producing contralateral limb weakness, gait unsteadiness, and ipsilateral cerebellar signs.
AI-enhanced and colorized image · Switch to the original imageFigure 7.108 Surgery for posterior tentorial meningioma with supratentorial and infratentorial extension. A. Incision and planned cranial opening. B. Separation of the tumor from the tentorium.
Posterior petrous tumors cause dysfunction of cranial nerves IX, X, and XI through compression at the jugular foramen.
Original printed pages 819–820
Diagnosis of PETROUS RIDGE MENINGIOMA
Symptoms, signs, and radiological investigations may not readily distinguish meningioma from trigeminal or acoustic neurinoma. Hyperostosis of the petrous bone without alteration of the internal auditory meatus favors meningioma over other tumors.
CT shows a sharply defined, densely enhancing mass at the petrous ridge (Figure 7.109)
Figure 7.109 CT showing petrous ridge meningioma with supra- and infratentorial extension.
Angiography usually shows no tumor staining. Most appear as avascular masses displacing the basilar artery and its branches (Figure 7.110 A, B).
Figure 7.110 Vertebral angiograms in a patient with petrous ridge meningioma (CT in Figure 7.109). A. Anteroposterior view: rightward displacement of the basilar artery and its branches. B. Lateral view: the basilar artery is displaced away from the clivus.
Original printed pages 820–822
Case: PETROUS RIDGE MENINGIOMA WITH CLIVAL AND SUPRATENTORIAL EXTENSION
A 33-year-old woman had experienced headache for about ten years. One year before admission, the headache became progressively worse and left facial numbness developed, followed by left auditory impairment progressing to deafness. Six months before admission she developed an unsteady gait, a tendency to fall leftward, dizziness, and diplopia. Examination showed dysfunction of left cranial nerves IV, V, VI, and VIII, ataxia, and incoordination of the left arm. CT showed a densely enhancing petrous ridge mass extending to the clivus and supratentorial compartment (Figure 7.109). Angiography showed displacement of the basilar artery and its branches to the right and away from the clivus (Figure 7.110 A, B).
Operative technique. Most of this tumor was in the posterior fossa, so a left suboccipital craniectomy was appropriate, with the patient either sitting or semiprone. Resection of the lateral third of the cerebellar hemisphere provides wider exposure. Begin dissection at the attachments to the petrous and tentorial dura to interrupt the tumor’s blood supply, then debulk internally with an ultrasonic aspirator. Avoid loop cautery because of the proximity to the brainstem. Under the microscope, gently separate those portions of the tumor wall that can be freed from surrounding structures. Do not remove portions firmly adherent to the brainstem: leaving a thin wall avoids additional brain injury. Because the tumor grows slowly, the patient may live for a long time without increased disability. Approach the remaining supratentorial component through a subtemporal route one to two weeks later. Incise the tentorium around the tumor and debulk internally to leave a thin wall, as described above. During dissection, protect the acoustic nerve posteriorly and inferiorly, the abducens nerve medially, the trigeminal nerve usually inferiorly, and the trochlear nerve beneath the tentorial edge. The basilar artery and its branches lie medially.
Although complete removal was impossible and a thin wall remained attached to the brainstem, this patient improved and could perform household work. Headache diminished, while facial numbness and deafness remained unchanged. Attempting to separate the adherent tumor from the brainstem might have injured it and impaired recovery.
Posterior petrous tumors are much easier to remove than anterior tumors because they lie more superficially, as shown in the operative photograph inFigure 7.111. A unilateral suboccipital craniectomy is performed on the tumor side, with the patient lying laterally, tumor side uppermost, and the face turned slightly away. Opening the dura demonstrates the advantage of this position: the cerebellar hemisphere falls away under gravity without retraction, exposing almost the entire tumor (Figure 7.111) and facilitating removal. First identify cranial nerves IX, X, and XI at the jugular foramen, or follow them laterally from their origins at the brainstem to the foramen. Cover them with cotton patties for protection. If the tumor is not highly vascular, debulk it substantially from within, then grasp its wall and separate it from the dura and adjacent structures. If it is highly vascular, first dissect its dural attachment to interrupt the blood supply, then debulk internally. In this case, complete removal was achieved and all cranial nerves remained intact.
Figure 7.111 Left posterior fossa operation in the lateral position. The posterior petrous meningioma is clearly exposed without cerebellar retraction.
Original printed pages 822–823
h) FORAMEN MAGNUM MENINGIOMA
Meningiomas at this site are very rare. They usually arise anterolateral to the junction of the medulla and spinal cord and extend into the upper spinal canal or lower clivus. The next most common site is the anterior margin of the foramen magnum, where surgical removal is particularly difficult because the medulla obstructs access.
Original printed page 823
Symptoms and signs
Pain in the upper posterior neck and occiput is usually the first symptom. Neck movement aggravates the pain and may produce neck stiffness. Flexion of the head may cause radiating electric sensations or paresthesia throughout the body (Lhermitte’s phenomenon), particularly when the tumor extends to compress the upper spinal cord. Limb paresthesia or numbness, usually more marked in the arms, and quadriparesis develop subsequently. Weakness generally begins in the arm on the tumor side, followed by the leg. Limb weakness may be unequal on the two sides because corticospinal fibers to the arms and legs cross at different levels here and are compressed unevenly. Some patients develop wasting of the hands and distal arms, resembling syringomyelia. This wasting is thought to result from compression of the anterior spinal artery, which, together with radicular arteries, supplies the cervical cord as far as the seventh cervical segment.(114) Large tumors also cause gait and swallowing disturbances(115) through compression of cranial nerves IX and X. Bilateral corticospinal tract signs or spastic quadriparesis are present, with greater weakness in the arms than in the legs. Sensory loss is dissociated. The spinal accessory nerve is the cranial nerve most commonly affected, in approximately 25% of patients.(116) Other cranial nerve deficits are uncommon.
Original printed pages 823–824
Investigations
CT often fails to show meningiomas here clearly because the surrounding bone at the foramen magnum obscures them. MRI demonstrates these tumors clearly. Angiography shows displacement of the vertebral artery on the tumor side. Tumor staining is usually indistinct unless the tumor is angiomatous or subtraction techniques are used to improve its visibility.
Original printed pages 824–827
Treatment
Surgery at this site is difficult and hazardous. The operating microscope, microsurgical techniques, and ultrasonic aspirator have improved the likelihood of successful removal.
Surgical technique is particularly important. The medulla, containing the respiratory and cardiac centers, must be protected, as must cranial nerves IX–XII, the vertebral artery and its branches, the anterior spinal artery, and the posterior inferior cerebellar artery.
The patient may be positioned sitting or semiprone, with the tumor side uppermost.
Make a midline incision from just above the external occipital protuberance to the spinous process of C4 or C5. A wide suboccipital craniectomy is unnecessary. Superiorly, the opening extends to about halfway up the cerebellar hemisphere; laterally, to halfway between the midline and mastoid process; and inferiorly, it includes the posterior rim of the foramen magnum and the posterior arch of the atlas. If the tumor extends farther downward, remove the C2 lamina as well.
Before opening the dura, assess its tension. If it is tight and nonpulsatile, slowly release CSF through a previously placed ventriculostomy. Once intracranial pressure has fallen, make a Y-shaped dural incision. The tumor lies anterolateral to the junction of the medulla and spinal cord (Figure 7.112) and is reddish pink, displacing the medulla posteriorly and to the opposite side.
Precautions:
1. Do not retract the medulla: this may cause apnea, bradycardia or arrhythmia, and hypotension.
2. Do not use unipolar coagulation to remove the tumor, because it may damage the medulla and the patient may fail to regain consciousness after surgery.
Figure 7.112 Foramen magnum meningioma situated anterolateral to the medulla oblongata.
Use a self-retaining retractor to elevate the tonsil and cerebellar hemisphere, exposing more of the tumor. The vertebral artery enters the cranial cavity at the level of the highest dentate ligament and courses inferomedial to the tumor. It gives off the posterior inferior cerebellar artery approximately 1 cm before reaching the basilar artery. These vessels must be exposed and protected. Separate any cranial nerves visible before opening the tumor wall and cover them with cotton patties. In the sitting position, occlude the subarachnoid space to prevent blood from entering the spinal subarachnoid space and causing postoperative aseptic meningitis and hydrocephalus. Next, use bipolar coagulation to coagulate and divide vessels in the tumor wall near its dural attachment, reducing its blood supply. Open the wall and remove the tumor internally with suction, an ultrasonic aspirator, and bipolar coagulation. Do not use unipolar coagulation. After reducing the mass, grasp and turn its wall, separating it from the nerves, vertebral artery, medulla, cerebellum, and arachnoid membrane with microsurgical instruments under the operating microscope (Figure 7.113). At the dural attachment, try to remove the tumor completely and then coagulate the site with bipolar coagulation. After hemostasis, moisten the cotton patties and gently separate them from the nerves before removing them. Never lift a patty without first separating the nerve, because an adherent nerve may be pulled up and torn. Finally, close the dura and wound.
AI-enhanced and colorized image · Switch to the original imageFigure 7.113 Technique for removing a foramen magnum meningioma. A. Internal tumor removal with an ultrasonic aspirator, leaving only the tumor wall. B. Separation of the tumor wall from the cranial nerves, vessels, medulla, and cerebellum.
Original printed page 827
i) INTRAVENTRICULAR MENINGIOMA
These tumors arise from arachnoid cells of the choroid plexus. Most occur at the trigone of the lateral ventricle.(117, 118) They may also occur in the third ventricle, whereas fourth ventricular meningiomas are extremely rare.(119)
Original printed pages 827–829
Symptoms and signs
Because the tumor develops within the pre-existing ventricular cavity, it is usually large by the time the patient seeks medical attention and produces few localizing symptoms. Most patients present with manifestations of raised intracranial pressure: headache, vomiting, blurred vision, and personality change. Large tumors may produce focal symptoms, including contralateral limb numbness or weakness, a homonymous visual field defect, dysphasia when the dominant hemisphere is involved, and gait ataxia.(117,120) Because the mass lies within a ventricle, symptoms may worsen with the head in one position as the tumor blocks CSF flow, and improve in another position when the tumor shifts and permits CSF to escape.
Figure 7.114 CT showing a lateral ventricular meningioma. Note the absence of ventricular enlargement.Figure 7.115 CT showing a third ventricular meningioma with marked ventricular enlargement.
Lateral ventricular meningiomas usually do not cause the marked ventricular enlargement seen with choroid plexus papilloma (Figure 7.114). Unlike papillomas, meningiomas do not produce CSF, so manifestations of raised intracranial pressure do not develop rapidly.
Meningiomas of the third and fourth ventricles tend to produce raised intracranial pressure relatively early because they obstruct CSF flow at the foramen of Monro, proximal aqueduct, or fourth ventricle. The lateral ventricles may become greatly enlarged (Figure 7.115). A fourth ventricular meningioma also causes enlargement of the third ventricle. In addition to raised intracranial pressure, a large third ventricular meningioma may cause hypothalamic dysfunction and a chiasmal syndrome (see the chapter on localizing symptoms).
Figure 7.116 Carotid angiogram showing an enlarged, tortuous anterior choroidal artery supplying a meningioma at the trigone of the lateral ventricle (CT in Figure 7.114).
Original printed pages 829–830
Diagnosis
Most patients present with raised intracranial pressure and few localizing symptoms. Symptoms alone therefore cannot establish the diagnosis. Radiological investigations are required to locate the tumor.
1. CT or MRI is an important investigation that clearly demonstrates the intraventricular tumor and hydrocephalus. The mass is hyperdense and sharply defined (Figure 7.115)
2. ANGIOGRAPHY usually cannot directly establish that a mass is intraventricular, even when tumor staining is present, because the ventricular boundaries are not visible. This is a disadvantage compared with CT. Angiography does, however, identify the vessels supplying the meningioma, namely the anterior and posterior choroidal arteries, which become enlarged and tortuous (Figure 7.116). Some tumors show tumor staining that indicates their vascularity. This information helps plan removal with minimal blood loss.
3. VENTRICULOGRAPHY was formerly very useful when angiography did not clearly locate the tumor, but it was hazardous and could cause severe headache. Its use was abandoned after CT became available.
Original printed pages 830–835
Treatment of INTRAVENTRICULAR MENINGIOMA
Intraventricular meningioma is another difficult tumor to remove because of its deep location near important medial brain structures: the hypothalamus and internal cerebral veins in third ventricular meningioma, or the optic radiation, pulvinar of the thalamus, and tail of the caudate nucleus in trigonal meningioma. Their functions must always be considered and preserved during surgery.
1. MENINGIOMA AT THE TRIGONE OF THE LATERAL VENTRICLEThis is the most common intraventricular site. The mass is usually large because it grows within a cavity without producing localizing symptoms, making removal rather difficult. A single cortical incision may not adequately expose the feeding vessels and tumor boundaries.(121)
Surgical technique. Removal of meningiomas in this region requires attention to the following:
i) In the dominant hemisphere, avoid making a cortical incision through or damaging the sensory speech center (Wernicke’s center), including the angular and supramarginal gyri. Injury may cause postoperative sensory dysphasia, dyslexia, and other deficits.
ii) Avoid damage to the optic radiation coursing through the temporal lobe and lower parietal lobe to the occipital lobe.
iii) Most meningiomas here are supplied by the anterior choroidal artery. On entering the ventricle, identify this vessel and divide it close to the tumor to facilitate successful removal.
The cortical approaches commonly used to reach tumors at the trigone are of three types:
1. lateral temporo-parietal approach
2. middle temporal gyrus approach
3. parieto-occipital paramedial approach
The technical details, advantages, and disadvantages of each approach have been described in the section on surgery for choroid plexus papilloma of the lateral ventricle.
After passing through the cortex and exposing the tumor, use a self-retaining retractor to separate the brain and enter the temporal horn, which is often enlarged by obstruction at the trigone. This permits wider exposure in this region. The choroid plexus lies inferomedial to the tumor. Identify, coagulate, and divide the branch of the anterior choroidal artery supplying the mass. Do not coagulate or divide the proximal anterior choroidal artery, because it also supplies the inferior internal capsule and injury may cause hemiparesis. Next, remove the tumor from within outward using loop cautery or an ultrasonic aspirator and bipolar coagulation. As the mass becomes smaller, its wall can be turned and separated from the ventricular wall, exposing medial feeding vessels or branches of the posterior choroidal artery, if present. After these vessels are divided, the tumor can be lifted out.
2. MENINGIOMA OF THE THIRD VENTRICLEThese tumors are less common than trigonal meningiomas. This is an important region because it is surrounded by vital structures, including the hypothalamic–pituitary axis and vessels at the base of the brain. Its deep location and narrow operative corridor make access difficult. The operating microscope, microneurosurgical instruments, and bipolar coagulation have greatly improved surgical removal.
Other tumors and lesions found in the third ventricle include colloid cyst, choroid plexus papilloma, ependymoma, craniopharyngioma, epidermoid, dermoid, teratoma, ependymal cyst, and pinealoma.
Before operating on a third ventricular tumor, detailed radiological investigation is essential to establish its location, type, and size and, importantly, its relationship to the optic pathway, hypothalamus, and basal cerebral vessels, as well as its feeding arteries and vascularity. Its position within the third ventricle is important because this may suggest its type and the appropriate surgical route. Third ventricular tumors are generally divided into anterior and posterior groups. Meningioma arises from the tela choroidea and therefore has its pedicle at the choroid plexus along the roof of the third ventricle. Skull radiographs may help distinguish tumor types: calcification in the posterior third ventricle in a young patient suggests a pineal gland tumor, whereas suprasellar calcification in multiple patches or as a curved outline along a cyst wall (eggshell calcification) suggests craniopharyngioma. Third ventricular meningiomas usually show no calcification. CT or MRI provides the most definitive information, showing tumor size and its relationship to the foramen of Monro and other parts of the third ventricle, and sometimes helping distinguish tumor types. Surgeons frequently use CT to select the operative approach. In some patients, angiography remains important for identifying the arterial supply and important deep venous drainage, including the internal cerebral vein, septal vein, thalamostriate vein, and great vein of Galen. It also helps exclude vascular lesions such as aneurysms and AVMs.
Another essential preoperative assessment for third ventricular meningioma or other tumors in this region is investigation for hormonal abnormalities such as hypopituitarism and hypothyroidism. These must always be treated adequately before surgery.
Surgery for third ventricular meningioma. The third ventricle is small and vital because its two lateral walls are formed by the hypothalamus. Surgery here may cause intraoperative and postoperative complications and carries a high mortality rate.Modern microneurosurgical instruments, the operating microscope, and good technique can, however, permit complete removal and cure. The approach must be selected individually according to tumor position, size, feeding vessels, and vascularity. Because meningiomas are related to the choroid plexus in the anterosuperior third ventricle, three approaches are available:
1) TRANSCALLOSAL APPROACHThis approach reaches the third ventricle through the frontal interhemispheric fissure, followed by division of the anterior corpus callosum to enter the lateral ventricle, where the foramen of Monro and third ventricular tumor are seen.
Technique. Position the patient supine, facing straight upward, with the head elevated approximately 30°. Make a coronal incision and raise a right craniotomy flap with one-third behind and two-thirds in front of the coronal suture. Its medial edge should lie at the midline or extend slightly across it. Open the dura with its base at the superior sagittal sinus. Choose an area with few, small bridging veins that can be coagulated and divided without harm. Retract the medial frontal surface laterally until the cingulate gyrus and anterior cerebral artery are visible. Lateral retraction of the cingulate gyrus exposes the pericallosal artery on the white, otherwise avascular corpus callosum. Preserve these arteries. Divide the corpus callosum just behind the genu with suction and bipolar coagulation along a sagittal incision about 3 cm long. Beyond the callosum, the ependymal lining of the lateral ventricle and small ependymal veins are seen. Incise the ependyma to enter the lateral ventricle, where the choroid plexus, septal vein, thalamostriate vein, and fornix are identified. Follow the choroid plexus anteriorly to the foramen of Monro; the tumor surface is usually visible through it. Obstructive hydrocephalus usually enlarges the foramen. If wider exposure is needed, the foramen of Monro can be enlarged by dividing the ipsilateral fornix anterior to it, or posteriorly by removing a small portion of the anterior tubercle of the thalamus.
Precautions in this region are: i) Remove as little brain tissue as possible and do not divide both fornices. ii) Only small, unimportant veins should be divided; protect the internal cerebral, septal, and thalamostriate veins. iii) If the tumor adheres to the third ventricular wall and separation would damage the hypothalamus, a portion may be left behind.
Begin removal by coagulating and dividing the vessels at the choroid plexus pedicle that supply the tumor. Debulk it internally, then gently separate its wall and remove it piecemeal until complete. If complete removal is impossible because of adherence to the hypothalamus, a fragment may be left. This is a benign, slow-growing tumor, and neither hypothalamic function nor the patient’s life should be jeopardized. If CSF obstruction persists, insert a shunt.
2. TRANSCORTICAL APPROACHThe ventricle is reached through a cortical incision in the posterior middle frontal gyrus. Once the lateral ventricle is entered, the anatomy is the same as described for the transcallosal approach, and access to the third ventricular tumor is obtained in the same way.
3. SUBFRONTAL APPROACHElevate the frontal lobe and enter the third ventricle through the lamina terminalis between the anterior communicating artery and the superior surface of the optic chiasm. This approach suits tumors in the lower third ventricle above the sella turcica. It is unsuitable for meningioma because only the inferior portion can be removed. The superior pedicle cannot be reached, preventing division of its feeding vessels and removal of the upper tumor.
Original printed pages 835–836
HEMANGIOBLASTOMA
This is a benign tumor arising from vascular endothelial cells, with a predilection for the posterior fossa. It is often found in middle-aged adults around 30–40 years old. The cerebellum is the most common location, either the vermis or a cerebellar hemisphere. The tumor may consist of a cyst with a mural nodule or a solid mass alone, but 90% of these tumors have an associated cyst.(122) Cerebellar hemangioblastomas may be solitary or multiple; the author has encountered as many as two lesions in one patient (Figure 7.122). Some patients also have hemangioblastomas elsewhere in the CNS, such as the spinal cord. Cerebral hemangioblastomas are very rare.
Associated conditions include syringomyelia and polycythemia or erythrocytosis. Syringomyelia occurs with spinal cord hemangioblastomas. Polycythemia is consistently associated with hemangioblastoma, regardless of location, and can aid clinical diagnosis. The tumor is believed to secrete erythropoietin, a hormone isolated from cyst fluid, tumor tissue, and the patient's plasma.(123) Erythrocytosis returns to normal after complete tumor removal, but may recur if residual tumor regrows after incomplete removal. Testing for erythrocytosis may therefore indicate whether removal was complete or whether the tumor has regrown.(124)
Cystic hemangioblastomas usually have a small nodule in the cyst wall, most often posteriorly (Figure 7.118). The cyst contains yellow fluid with a high protein concentration, which may clot on standing. A defining feature of the tumor nodule is its rich blood supply. Its feeding vessels are large, and its veins are consistently enlarged and contain arterialized blood, visible both on angiography and during surgery. This gives an appearance resembling an AVM, a feature not seen in other cerebellar tumors and therefore another aid to diagnosis.
Hemangioblastoma is a component of von Hippel–Lindau syndrome. This syndrome comprises a hemangioblastoma at some site in the CNS, accompanied by one or more of the following: retinal angiomatosis, hepatic and renal angiomas, renal cell carcinoma, pheochromocytoma, and pancreatic and renal cysts.(125)
Original printed pages 836–837
Symptoms and Signs
Because these tumors usually arise in the cerebellum, patients present with cerebellar manifestations: ataxia, incoordination on the side of the tumor, and nystagmus, together with symptoms of raised intracranial pressure caused by obstruction of CSF flow, including headache, vomiting, and papilledema. Headache is the earliest and most common symptom. These manifestations are not specific to any particular tumor, and further investigations are needed to establish its type. Some patients may develop sudden severe headache and lose consciousness. For example, a 35-year-old male engineer suddenly developed occipital headache and vomiting. Shortly afterward, he became drowsy and then unconscious, with rigidity of the limbs on both sides and hyperventilation. The history strongly suggested intracranial hemorrhage. Angiography, performed when CT was not yet available, showed a vascular cerebellar tumor (Figure 7.117) and signs of hydrocephalus. Ventriculostomy revealed blood in the CSF. After a period of CSF drainage, his condition improved and the tumor was removed. It proved to be a hemangioblastoma responsible for intraventricular hemorrhage. After surgery, he recovered sufficiently to return to desk work.
Figure 7.117. A vascular cerebellar tumor in a patient who became unconscious because of intraventricular hemorrhage. Histological examination showed hemangioblastoma.Figure 7.118. CT showing a cystic cerebellar tumor with a mural nodule (arrow). Histological examination showed hemangioblastoma.
Original printed pages 837–839
Diagnosis
Cerebellar symptoms and signs alone cannot establish the diagnosis. A thorough examination of the rest of the body is also necessary, looking for components of von Hippel–Lindau syndrome, including retinal angiomatosis, pheochromocytoma, and pancreatic and renal cysts. Blood should also be tested for polycythemia, which is consistently associated with this tumor.
Radiological investigations are important for both diagnosis and treatment.
CT and MRI demonstrate both cystic and noncystic tumors. Contrast-enhanced CT clearly shows the cyst and the hyperdense mural nodule (Figure 7.118), providing valuable information for operative planning.
Figure 7.119. Vertebral angiogram showing tumor staining associated with an avascular cystic component.Figure 7.120. Vertebral angiogram showing abundant vessels confined to the tumor periphery. Histological examination showed hemangioblastoma.Figure 7.121. A highly vascular solid cerebellar hemangioblastoma without a cyst.Figure 7.122. Multiple solid cerebellar hemangioblastomas.
Vertebral angiography is very helpful in diagnosing hemangioblastoma and should be performed whenever this tumor is suspected. It demonstrates abnormal feeding arteries, tumor vascularity, and draining veins, all of which are important for successful surgery with minimal blood loss. Most hemangioblastomas show intense tumor staining and very well-defined margins. Four patterns have been observed: i) a stained mural nodule surrounded by an avascular cyst (Figure 7.119); ii) a tumor with no abnormal central vessels but abnormal vessels around its periphery, forming a vascular ring (Figure 7.120), indicating central degeneration or a cyst; iii) a solid tumor without a cyst (Figure 7.121); and iv) multiple foci of tumor staining (Figure 7.122)
Original printed pages 839–843
Treatment of Hemangioblastoma
Surgical removal is the best treatment. Complete removal cures the patient because the tumor is benign. Cystic tumors with a mural nodule respond well to removal of the nodule. In contrast, hemangioblastomas of the brainstem cannot be removed completely and will regrow.
Figure 7.123. Surgery for a cerebellar hemangioblastoma with a mural nodule and cyst. A. A red tumor near the surface of the left cerebellar hemisphere, with a red draining vein. B. The cyst after removal of the tumor, showing no tumor tissue in its wall. C. The tumor and dark tea-colored fluid obtained from the cyst.
Operative technique. For tumors in the posterior fossa, a suboccipital craniectomy is performed with the patient sitting or semiprone. A midline incision can be used for tumors of the vermis or cerebellar hemisphere; a paramedian incision is another option for a hemispheric tumor.
The principles of tumor removal are as follows:
1) For a cyst with a mural nodule, complete removal of the nodule alone is sufficient; the cyst need not be removed (Figure 7.123A–C). On opening the dura, the mural nodule is usually found adjacent to the cerebellar pia. Its red color indicates a rich blood supply. Surrounding yellow hemosiderin indicates previous tumor hemorrhage. The cortical vein contains bright red blood, reflecting drainage from a highly vascular tumor with shunting. Removal must not begin by dividing the cortical vein draining the tumor. First incise the cerebellar tissue immediately adjacent to the medial and superior tumor margins, allowing branches from the vermian and superior cerebellar arteries to be divided first and reducing blood loss. The vein will turn dark. The draining vein is divided close to the tumor only at the end. The cyst wall need not be dissected out because it contains no tumor cells and will not give rise to a recurrent mass. Attempting to remove it would damage the cerebellum. In this patient, only the mural nodule was removed; follow-up for 10 years showed no symptoms of recurrence. Other patients have had similar results.
2) A large, highly vascular solid tumor without a cyst should be removed using the same principles as an AVM. All or most of the surrounding arterial feeders must first be divided. The tumor is then gradually dissected out in one piece, leaving the venous drainage to be divided last. Biopsy or piecemeal debulking to make removal easier should not be attempted, because this may cause massive hemorrhage that is sometimes uncontrollable and fatal. Histologically, these tumors consist of a network of thin-walled vessels lined only by endothelial cells. These vessels cannot contract, making hemostasis difficult.
The following case illustrates removal of a highly vascular solid tumor. The patient presented with symptoms of raised intracranial pressure and mild gait ataxia. CT was not yet available, so carotid angiography was performed first. It showed hydrocephalus, suggesting a posterior fossa lesion. Ventriculography then demonstrated obstruction of the fourth ventricle (Figure 7.124). The posterior fossa was explored without preceding vertebral angiography. This was very risky because the tumor feeders and draining veins had not been studied before surgery. Opening the dura revealed a group of red vessels over the cerebellar tonsil, hemisphere, and lower vermis (Figure 7.125A). Dissection must not begin at these surface vessels: they are draining veins carrying arterialized blood, and injury would cause severe bleeding. Instead, the cerebellum should be incised and separated to expose the tumor margins. The ventriculogram showed a tumor obstructing the fourth ventricle, with its upper portion still visible, indicating the superior tumor margin and the appropriate point of approach. The vermis therefore had to be divided in the midline and separated to both sides, exposing the superior and bilateral lateral tumor margins (Figure 7.125B). Once the margins were clearly exposed, feeders from the posterior inferior and superior cerebellar arteries could be coagulated with bipolar forceps and divided. The tumor visibly shrank and could be turned to reveal additional branches that were easily coagulated and divided. Gradual retraction of the tumor from anterior to posterior allowed complete removal after division of the draining vein at the tonsil, without damage to the floor of the fourth ventricle (Figure 7.125C). The patient recovered and had no subsequent recurrence.
In this case, dissection from posterior to anterior, starting at the tonsil, would have made the tumor margins difficult to see. A draining vein crossed the approach and could have been dangerously torn.
For multiple posterior fossa hemangioblastomas, the same operative principles apply as for a solitary lesion. Identify the arterial feeders first, coagulate them with bipolar forceps, and divide them before removing the tumors.
Figure 7.124. Contrast ventriculogram showing fourth ventricular obstruction and hydrocephalus. A. Frontal view. B. Lateral view.
Original printed pages 843–845
Radiotherapy
For tumors that cannot be completely removed, or inoperable tumors located in the brainstem, radiotherapy at a dose of 5000 rad may reduce tumor size, slow growth, and decrease vascularity, prolonging survival.(126,127)
Figure 7.125. Surgery for cerebellar hemangioblastoma. A. A highly vascular tumor in the lower vermis, with a very large draining vein resembling an AVM. B. Midline division of the lower vermis clearly exposes the margins of the highly vascular tumor. C. After complete removal, the fourth ventricle and brainstem remain intact.
Original printed pages 845–849
CRANIOPHARYNGIOMA
Craniopharyngioma is a benign maldevelopmental tumor arising from squamous epithelial remnants of Rathke’s pouch. This pouch of buccal epithelium grows upward to join the downward extension of the diencephalon, forming the pituitary gland. Rathke’s pouch subsequently becomes the craniopharyngeal duct. The proximal duct later disappears, losing its connection with the buccal cavity, while its distal portion forms the anterior pituitary lobe, pars intermedia, and pituitary stalk. Residual duct cells anywhere along this course may develop into a craniopharyngioma. Other names include Rathke’s pouch tumor or cyst, suprasellar cyst, adamantinoma, and cholesteatoma.
Craniopharyngioma is not, strictly speaking, a true neoplasm, but a mass formed by epithelial proliferation and separation. Epithelial debris subsequently desquamates into the cyst and eventually breaks down into cholesterol ester crystals in the cyst fluid. Epithelial growth stimulates reactive tissue formation within the mass, and calcification is invariably present.(128)
Craniopharyngioma is the most common childhood tumor after tumors arising from glial cells, occurring particularly at about 10–20 years of age. It also occurs in adults, but less frequently.
The embryological development of the pituitary gland explains the relationship of craniopharyngioma to the sella turcica. Clinically, three locations can be distinguished: i) intrasellar, ii) suprasellar, and iii) intraventricular. Their symptoms and signs differ, and the operative techniques also vary somewhat.
Image enhanced and colorized with AI · Switch to the original imageFigure 7.126. Intrasellar craniopharyngioma containing a cyst and calcification. The tumor compresses the anterior pituitary lobe; the optic chiasm and anterior cerebral artery are not compressed or displaced.
Intrasellar craniopharyngioma is a tumor arising within the sella turcica (Figure 7.126). It is less common than the suprasellar type. Compression of the pituitary causes early loss of function, producing symptoms similar to those of a pituitary tumor and enlargement of the sella turcica. Most patients present after the tumor has enlarged and extended through the diaphragma sellae into the suprasellar region, giving it a dumbbell shape. It may extend anterior or posterior to the chiasm, affecting both the clinical manifestations and the difficulty of removal. Prechiasmatic tumors are easier to remove than those extending posteriorly.
Suprasellar craniopharyngioma is the most common type. The tumor lies above the diaphragma sellae and usually expands anterior to the chiasm. It generally causes no sellar changes and does not compress the pituitary itself. The expanding mass may lie anterior to the chiasm (prechiasmatic), beneath it and displace it upward (subchiasmatic), or extend behind it (retrochiasmatic) (Figure 7.127A–C). Posterior and superior extension compresses the inferior third ventricle and hypothalamus and may obstruct the foramen of Monro, producing obstructive hydrocephalus and symptoms of raised intracranial pressure. Complete dissection in this situation is difficult and potentially fatal because it can damage the hypothalamus, which is often adherent to the tumor as a result of reactive gliosis. Extension into the retroclival and interpeduncular cisterns is very rare.
Image enhanced and colorized with AI · Switch to the original imageFigure 7.127. Suprasellar craniopharyngioma. A. Suprasellar prechiasmatic craniopharyngioma lies anterior to the optic chiasm and expands beneath the frontal lobe and corpus callosum. B. Suprasellar subchiasmatic craniopharyngioma displaces the chiasm and foramen of Monro upward and the pituitary downward. C. Suprasellar retrochiasmatic craniopharyngioma extends behind the chiasm into the interpeduncular fossa, obstructing the foramen of Monro and aqueduct of Sylvius. The optic chiasm and anterior cerebral artery are displaced forward.Image enhanced and colorized with AI · Switch to the original imageFigure 7.128. Intraventricular craniopharyngioma displaces the floor of the third ventricle downward and the chiasm, lamina terminalis, and anterior cerebral artery forward. The foramen of Monro is obstructed.
Intraventricular craniopharyngioma arises within the third ventricle, a very rare location. It usually obstructs the foramen of Monro (Figure 7.128). It can be extremely difficult to distinguish this type from a suprasellar craniopharyngioma extending upward into the third ventricle. This distinction is important surgically: if a suprasellar tumor is approached intraventricularly, the inferior hypothalamus will be damaged before the tumor is reached.
Original printed pages 849–851
Symptoms and Signs
Craniopharyngioma does not produce hormones, invade brain tissue, or spread elsewhere. Symptoms result from expansion and compression of the adjacent brain, nerves, CSF pathways, and blood vessels. The principal manifestations are:
1) Visual loss from compression of the optic nerve, chiasm, or optic tract, together with involvement of other cranial nerves.
2) Pituitary and hypothalamic dysfunction, usually producing hypopituitarism and diabetes insipidus.
3) Raised intracranial pressure due to obstruction of CSF flow in the basal cisterns and at the foramen of Monro.
4) Frontal and temporal lobe signs when a large tumor extends into the posterior frontal and medial temporal regions.
The tumor grows slowly, so symptoms develop gradually. Children usually present with raised intracranial pressure because they are often unaware of visual abnormalities. Adults more often present with visual and hormonal symptoms.
Visual symptoms result from compression of the optic nerve, chiasm, or optic tract. Recognition is often delayed in children; some are identified only when they repeatedly bump into objects. Visual acuity and visual field impairment are usually unequal between the eyes, depending on the direction of tumor extension. Various field defects may occur, but because most tumors occupy the midline suprasellar region, temporal field loss is usually present. It may initially be asymmetric, but later progressive bitemporal hemianopia develops, ultimately leading to blindness. Rarely, posterior extension compresses an optic tract and produces homonymous hemianopia. Prolonged optic nerve compression causes primary optic atrophy, with a pale optic disc and progressive loss of acuity until vision is lost.
Figure 7.129. A 16-year-old patient with craniopharyngioma, showing delayed growth and immature genitalia (hypogenitalism).
Pituitary and hypothalamic symptoms. Compression of the pituitary causes hypofunction, with reduced secretion of growth hormone and thyrotrophic, adrenotrophic, and gonadotrophic hormones. Growth hormone deficiency is most conspicuous. Patients are short and fail to grow appropriately for their age. They are often tired and weak, with small, immature genitalia and absent pubic hair (Figure 7.129). The skin is dry and pale. Intelligence initially remains appropriate for age, but cognition gradually deteriorates late in the disease when intracranial pressure rises. Children with concomitant thyrotrophic hormone deficiency are often obese.
Upward extension of a suprasellar tumor against the third ventricle and hypothalamus produces symptoms and signs of diabetes insipidus or disturbances of fat metabolism, causing either obesity or emaciation. Damage to the posterior third ventricular region may disrupt central autonomic regulation, producing hypersomnia or insomnia, hyperthermia or hypothermia, hyperglycemia or hypoglycemia, and excessive or reduced sweating.(129)
Hydrocephalus. A craniopharyngioma extending into or arising within the third ventricle may obstruct CSF flow at one or both foramina of Monro. Some tumors obstruct the entrance to the aqueduct of Sylvius. Obstruction at either site causes raised intracranial pressure. Children develop headache and vomiting, and tumors in young children may cause head enlargement.
Other neurological symptoms. A large craniopharyngioma may extend beyond the sellar region along the skull base, compressing the frontal and temporal lobes, cranial nerves, and brainstem (Figures 3.103 and 3.104). Extension along the floor of the anterior cranial fossa may cause anosmia, occasionally the only finding. Compression of the medial temporal lobe may produce uncinate fits (see the chapter on symptoms and signs). Posterior extension may impair the oculomotor, trochlear, trigeminal, and abducens nerves, as well as the corticospinal tract in the brainstem.
Original printed pages 851–854
Diagnosis of Craniopharyngioma
The patient’s age, the visual and hormonal abnormalities described above, and radiological investigations together permit a high degree of diagnostic accuracy. Measurement of growth hormone, antidiuretic hormone, thyrotrophin, and ACTH supports the diagnosis, although abnormalities are not specific to craniopharyngioma and may occur with other tumors in this region. Preoperative hormone measurements also help assess operative risk: hypoadrenalism and hypothyroidism may cause serious problems during and after surgery.(130)
Radiological investigations are particularly useful and offer a high degree of diagnostic accuracy. They include:
1. Skull radiographs. This simple, inexpensive examination often reveals diagnostic changes. Intrasellar or suprasellar calcification is a particularly important finding. Calcification is seen in up to 85% of childhood craniopharyngiomas and 40% of adult cases.(131,132) It may appear as small scattered nodules in the sellar region (Figure 6.12C), or as an eggshell-like curved line in the cyst wall (Figure 6.12A). In some cases it is not visible radiographically, although it is invariably present histologically.
Changes in the sella turcica depend on tumor location and intracranial pressure. Intrasellar craniopharyngioma produces changes resembling a pituitary adenoma, with ballooning of the sella and possible destruction of its floor. Suprasellar extension widens the sellar opening, flattens the dorsum sellae backward, and thins the anterior clinoid processes. A purely suprasellar tumor may leave the sella unchanged. In young children, raised intracranial pressure may produce sutural separation on skull radiographs.
2) CT and MRI. These newer investigations provide excellent diagnostic information. CT distinguishes calcified, solid, and cystic components (Figure 6.112). Coronal and sagittal CT or MRI is particularly useful for establishing whether a tumor is intrasellar, suprasellar, or dumbbell-shaped (Figure 6.129).
3) Angiography. The main purpose is to establish the relationship of the tumor to the internal carotid, anterior cerebral, and basilar arteries, rather than to demonstrate tumor feeders or vascularity. The vessels supplying craniopharyngiomas are small and difficult to see angiographically. Angiography therefore does not diagnose craniopharyngioma more accurately than CT or MRI.(130,133) It does, however, help exclude an aneurysm in this region, improving operative safety.
The angiographic appearance varies with tumor location. In large intrasellar tumors, the intracavernous internal carotid artery appears normal but may lie relatively high above the sellar floor, because tumor expansion has displaced the floor downward. The carotid siphon may be displaced laterally on the anteroposterior view, while the anterior cerebral artery remains unchanged. In suprasellar tumors, or intrasellar tumors with suprasellar extension, the appearance varies according to whether growth is anterior, inferior, or posterior to the optic chiasm. Important signs of a suprasellar mass are elevation of the clinoid segment of the internal carotid artery, opening of the carotid siphon on the lateral view, and elevation of the anterior cerebral artery. When the tumor extends anterior to the chiasm into the posterior frontal region, the clinoid segment of the internal carotid artery is depressed, while the anterior cerebral artery is bowed upward and backward, resembling a subfrontal tumor. With posterior extension, the anterior choroidal and posterior communicating arteries are displaced laterally, while the internal carotid bifurcation and anterior cerebral artery are elevated and displaced forward.
Figure 7.130. Contrast ventriculogram showing a suprasellar mass displacing the inferior third ventricle upward, with sellar calcification. Histology confirmed craniopharyngioma.
4. Ventriculography and pneumoencephalography. Air ventriculography or an opaque contrast medium can clearly demonstrate a suprasellar mass (Figure 7.130). Pneumoencephalography (PEG) also delineates suprasellar tumor margins. Both ventriculography and pneumoencephalography have now been discontinued.
Original printed pages 854–864
Treatment of Craniopharyngioma
Complete surgical removal is the best treatment because the tumor is benign and can be cured. Unfortunately, craniopharyngiomas lie among vital structures—the hypothalamus, pituitary gland, optic nerves, chiasm, and major blood vessels—which obstruct access and make surgery difficult and hazardous. The tumor is often adherent to the hypothalamus, pituitary, and optic nerves, and attempts to separate it from these structures frequently have poor results. Most patients also present with large tumors, making attempted total removal particularly dangerous. Partial removal is therefore often necessary.
Surgical approaches. Several routes are available, depending on tumor location and size, cystic components, calcification, and hydrocephalus. The approach must be selected individually.
Six approaches to craniopharyngioma are described below.
1) SUBFRONTAL APPROACH This is suitable for anterior suprasellar tumors or intrasellar tumors extending into the suprasellar region anterior to the optic chiasm (Figure 7.131). It offers good visualization of the optic nerves, chiasm, ipsilateral internal carotid artery, and anterior circle of Willis. Its disadvantages are poor visualization of tumor beneath the optic nerves and chiasm and inability to see a tumor within the third ventricle. Craniotomy is performed on the right, the nondominant side, which is also more convenient for the usually right-handed surgeon. A left frontotemporal craniotomy may nevertheless be used when the mass extends into the left temporal or frontal region. The opening should be low, close to the anterior cranial fossa floor, to expose the sellar region well. If hydrocephalus is present, frontal ventricular drainage should first reduce intracranial pressure, permitting easy frontal lobe retraction and clear sellar exposure. The olfactory nerve should be coagulated and divided to prevent avulsion of the olfactory bulb from the cribriform plate, which could cause CSF rhinorrhea. Once the anterior clinoid process is identified, the optic nerve lies just medial to it. Microsurgical assistance is then used. Incising the arachnoid to open the chiasmatic cistern provides wider visualization of the optic nerves, chiasm, internal carotid artery, and tumor.
Image enhanced and colorized with AI · Switch to the original imageFigure 7.131. Trans-subfrontal approach to a suprasellar craniopharyngioma anterior to the optic chiasm (prechiasmatic extension).Figure 7.132. Routes to craniopharyngioma through the subfrontal approach. 1. prechiasmatic route 2. opticocarotid route 3. lamina terminalis routeFigure 7.133. Subfrontal operative view of a craniopharyngioma extending anterior to a postfixed chiasm.
Several corridors are available and may be combined, depending on the size and direction of tumor extension (Figure 7.132)
1.1 PRECHIASMATIC ROUTE This route is frequently used because most craniopharyngiomas lie anterior to the chiasm, bowing it upward and backward (Figure 7.133). The tumor wall is approached between the two optic nerves. Coagulate and incise the wall to aspirate the fluid, which is usually brown with golden flakes of cholesterol crystals. An ultrasonic aspirator is then used to remove the solid component until the wall collapses and can be separated from adjacent structures. Separation from the optic nerves, chiasm, and internal carotid artery is usually easy. Tumor adherent to the hypothalamus should not be completely removed unless its wall separates readily. Firmly adherent portions should be left, otherwise the patient may die. The pituitary stalk, essential for pituitary function, must likewise be protected. Some craniopharyngiomas arise in the stalk, however, and division may be necessary for removal. With the operating microscope, the stalk can now be dissected free. If an intrasellar tumor has suprasellar extension, its intrasellar component must also be aspirated.
Figure 7.134. Operative view of a craniopharyngioma posterior and superior to the chiasm. The chiasm is displaced against the tuberculum sellae, making the optic nerves appear short. The tumor was removed through the lamina terminalis route.
With a prefixed chiasm and tumor extending beneath the tuberculum sellae, the interval between the chiasm and tuberculum is narrow. Drilling away the tuberculum sellae permits visualization of the tumor.
1.2 OPTICOCAROTID ROUTE The tumor is approached through the interval between the optic nerve and tract and the internal carotid artery. This is suitable for a prefixed chiasm or a chiasm displaced forward by tumor, making the optic nerves appear short. Combined with the first route, it permits more extensive removal beneath the optic nerve and chiasm.
1.3 LAMINA TERMINALIS ROUTE The lamina terminalis above the optic chiasm is opened. This route is suitable for tumors extending upward and behind the chiasm (Figure 7.134). After a midline opening in the lamina terminalis, the tumor wall is not yet visible because the thin floor of the third ventricle still covers it. The floor must be incised sagittally and separated to expose the tumor, which is then internally debulked. For an intraventricular craniopharyngioma, opening the lamina terminalis reaches the tumor directly.
This route provides good exposure of the anterior third ventricular tumor, but poor visualization of its lateral aspects. Dissection here carries a relatively high risk of hypothalamic injury.
The surgeon should always consider all three corridors on reaching the sellar region, selecting the one providing the widest view and greatest feasible removal. Tumor extension should first be studied on CT and MRI so that appropriate positioning can be planned.
2. PTERIONAL APPROACH This short route is suitable for retrochiasmatic (Figure 7.135) or parasellar craniopharyngiomas. Its disadvantage is poor visualization of the contralateral tumor wall and optic nerve. Positioning is similar to the subfrontal approach, but the craniotomy must reach the pterion, and the anterior temporal squama and greater sphenoid wing must be removed low down to expose the anterior temporal lobe and Sylvian fissure. Opening the anterior Sylvian arachnoid allows the frontal and temporal lobes to separate more widely from the sphenoid wing, exposing the optic nerve, chiasm, internal carotid artery, and its bifurcation. A retrochiasmatic tumor usually pushes the chiasm against the tuberculum sellae and bows the optic tract laterally. The tumor lies behind the internal carotid artery, close to the oculomotor nerve and posterior communicating artery, which must be protected. Incise the arachnoid between the optic nerve and internal carotid artery and separate the optic nerve and tract from the artery to expose the tumor. Remove the tumor through this interval (Figure 7.135), reducing its size by internal debulking. Complete removal through this corridor alone is usually impossible because of extension into the third ventricle; the lamina terminalis route described above must therefore be added. As the tumor becomes smaller, the optic chiasm recedes from the tuberculum sellae, unless it is prefixed, opening an interval between the two optic nerves that provides another route for removal.
Image enhanced and colorized with AI · Switch to the original imageFigure 7.135. Approaches to suprasellar retrochiasmatic craniopharyngioma. 1. subfrontal approach, lamina terminalis route 2. Pterional approach: the Sylvian arachnoid is opened to separate the frontal and temporal lobes.Image enhanced and colorized with AI · Switch to the original imageFigure 7.136. Approaches to intraventricular craniopharyngioma. 1. Transventricular approach (transcortical or transcallosal). 2. trans-subfrontal, lamina terminalis routeFigure 7.137. Transventricular operative view showing the craniopharyngioma cyst wall at an enlarged foramen of Monro (1). Note the choroid plexus at the edge of the foramen (2).
3. TRANSCORTICAL APPROACH The tumor is approached through an incision in the posterior middle frontal cortex into the frontal horn, providing a good view of the ipsilateral foramen of Monro (Figure 7.136). This is suitable for tumors within the third ventricle, which usually cause obstructive hydrocephalus. The foramen of Monro is enlarged, permitting clear visualization of the tumor wall (Figure 7.137). Greater hydrocephalus makes access easier and exposes more of the inner third ventricular wall. This route is therefore unsuitable without hydrocephalus, and the frontal cortical incision may cause postoperative seizures.
After entering the lateral ventricle, the choroid plexus, septal vein, thalamostriate vein, and fornix are seen. Following the choroid plexus forward leads to the foramen of Monro. In the example in Figure 7.137, the foramen is already very wide and requires no enlargement. The tumor wall is coagulated and incised. In this cystic case, drainage causes the wall to collapse, allowing separation from the foramen margin and third ventricular wall. The superior portion of a craniopharyngioma generally separates readily, whereas the inferior portion often adheres to the third ventricular wall because of gliosis. The surgeon must decide early whether further dissection is appropriate. My practice is to leave tumor that cannot be separated from the third ventricular wall, reducing tumor or calcification as much as possible and relieving the obstructive hydrocephalus so that a shunt is unnecessary. Attempts at complete removal often end in death. If the inferior tumor wall separates readily, however, it should be removed completely. Some calcification is extremely hard and cannot be fragmented even with biting instruments; it may be left because this component grows very slowly.
Figure 7.138. Transventricular operative view showing a large craniopharyngioma displacing the third ventricular wall and obstructing the foramen of Monro. The tumor wall is not visible (1). The choroid plexus (2) lies at the margin of the foramen.
When the foramen of Monro is not greatly enlarged, the narrow corridor can be widened by dividing only the ipsilateral anterior column of the fornix, which has been found not to cause functional loss. Both fornices must not be divided, because this causes memory loss.
A transcortical approach may sometimes be harmful. In Figure 7.138, the tumor was not within the third ventricle but outside it, displacing the ventricle upward until the foramen of Monro was obstructed. Brain tissue covered the mass. Incising this tissue to reach the tumor was an error in this patient. Even a small opening at the foramen for cyst drainage and biopsy caused drowsiness lasting several days, presumably from partial hypothalamic injury. The lesson from this case is that closure followed by a subfrontal or pterional approach would have been preferable.
Image enhanced and colorized with AI · Switch to the original imageFigure 7.139. Approaches to intrasellar craniopharyngioma. 1. transsphenoid approach 2. Subfrontal approach (with a postfixed chiasm, identifiable on MRI).
4. TRANSCALLOSAL APPROACH A third ventricular craniopharyngioma is approached by retracting the medial frontal lobe laterally and incising the corpus callosum to enter the lateral ventricle. The structures described under the transcortical approach are then seen (see the section on intraventricular tumors for operative details). The advantage is avoidance of a frontal cortical incision and thus of the associated risk of seizures. Both third ventricular walls can also be viewed through the two foramina. The disadvantage is division of the corpus callosum, which connects the hemispheres. Care is also required to avoid injuring both fornices, which lie close together here; bilateral injury causes memory loss.
5. TRANSSPHENOIDAL APPROACH This nasal approach reaches the sella turcica through the sphenoid sinus without a craniotomy. It is suitable for an intrasellar craniopharyngioma with an enlarged sella (Figure 7.139). It does not expose tumor extending into the suprasellar, parasellar, or retrosellar regions and is unsuitable for young children because their nostrils are small and the sphenoid sinus is not yet developed.
An intrasellar craniopharyngioma extending upward anterior to the optic chiasm may sometimes be completely removed by combining transsphenoidal and subfrontal approaches.(134,129) This is performed in two stages. The transsphenoidal approach first removes the intrasellar component while attempting to preserve pituitary tissue. Some suprasellar tumor may also be removed through this route, reducing the mass. A frontal craniotomy and subfrontal approach subsequently remove the remaining tumor. More than one month should separate the operations, allowing intrasellar postoperative inflammation to resolve and hormonal status to improve before the second stage.(134)
6. PALLIATIVE SURGERY A catheter is placed in the cyst and connected to a reservoir implanted in the temporal region. Cyst fluid can then be aspirated by inserting a needle into the reservoir. This is suitable for a large cyst whose wall is firmly adherent to vital surrounding structures, when dissection is considered dangerous. I have used this method and observed immediate improvement in vision and headache after aspiration in patients deteriorating from cyst-fluid accumulation. These patients return for aspiration when vision worsens again, approximately every 3–4 months. A disadvantage is eventual obstruction of the catheter tip within the cyst, preventing further aspiration.
Original printed pages 864–866
Postoperative Care
Patients with craniopharyngioma commonly have hormone deficiencies, usually including hypoadrenalism, and tolerate surgical stress and infection poorly. Corticosteroids are therefore required before and after surgery, followed by gradual reduction to a maintenance dose.
Attempted total removal of a craniopharyngioma causes diabetes insipidus in almost every case. Postoperative urine output generally follows three phases. During the first 12–18 hours, output is initially low. The second phase is true diabetes insipidus: polyuria usually begins 24–48 hours after surgery and lasts 2–3 weeks. In the third phase, urine output decreases; desmopressin acetate (1-deamino-8-D-arginine vasopressin, DDAVP) may or may not be required.
During the first 2–3 days, mild diabetes insipidus should initially be managed with adequate fluid replacement. If the patient is alert and able to drink, oral water may replace or supplement intravenous fluids. Excessive dextrose-containing fluid should be avoided because, together with steroids, it may raise blood glucose and cause osmotic diuresis, further increasing urine output. Persistent thirst, polyuria, or hypernatremia warrants short-acting aqueous Pitressin, 3–5 units every 4–6 hours in adults, or long-acting Pitressin in oil, 5 units every 18–24 hours. DDAVP is now given intranasally at 0.05–0.2 mg, or 0.05–0.2 cc, every 12–24 hours, a convenient method suitable for prolonged use. As noted above, diabetes insipidus usually lasts about 2–3 weeks and then gradually improves. When the pituitary stalk is divided to achieve total removal, however, more than 90% of patients develop permanent diabetes insipidus, controllable with DDAVP.(135) Fluid and electrolyte imbalance may be compounded by loss of the thirst mechanism, usually after anterior hypothalamic injury, making management still more difficult.(136) The hypothalamus must therefore be carefully protected during surgery. Fluid intake and output, urine specific gravity, and electrolyte levels require continual monitoring and correction to maintain normal values.
Other deficiencies, including thyroid hormone, growth hormone, and gonadotrophic hormone, require replacement when levels are found to be low.
Seizures are common after craniopharyngioma surgery and are probably related to frontal lobe retraction combined with osmotic, fluid, and electrolyte disturbances, particularly sodium imbalance. Dilantin and phenobarbital should therefore always be given prophylactically.
Original printed page 866
Radiotherapy
It has long been recognized that radiation does not destroy craniopharyngioma and that only complete surgical removal can cure the patient. Total removal is difficult, however, and residual tumor often regrows after 3–5 years, creating a treatment problem. Studies of postoperative radiotherapy have shown prolonged survival and longer intervals before recurrence.(132,137–140) Results are better when as much tumor as possible is removed, leaving only a small residual component before radiotherapy.(141,142)I believe that radiotherapy does not destroy craniopharyngioma and have therefore never referred these patients for it. Instead, I attempt complete or maximal removal, then follow the patient with hormone measurements and repeat CT. Evidence of regrowth prompts reoperation. Another reason for avoiding radiotherapy is that these tumors often occur in children whose brains are still developing. Radiation has numerous adverse effects, including necrosis, endocrine deficiency, optic neuritis, dementia, and possible induction of tumors. In children in particular, it may impair intelligence.(143,130) Radiotherapy should therefore not be used in children.
Original printed pages 866–867
Dermoid and Epidermoid Tumors or Cysts
Dermoids and epidermoids are maldevelopmental tumors. At 3–5 weeks of embryonic development, the dorsal midline ectoderm folds inward and fuses to form the neural tube, which then separates from the surface ectoderm. Abnormal development during this process can leave ectoderm between the neural canal and the skin, termed ectopic epithelium.(144) This may later form a dermal sinus, dermoid or epidermoid cyst, or tumor. An epidermoid generally contains only dermal epithelium, whereas a dermoid also contains hair follicles and dermal glands, including sebaceous and sweat glands.
Both epidermoid and dermoid tumors are very rare. Epidermoids are generally about 10 times more common than dermoids.(145)
Epidermoid tumors occur at any age but are most common between 30 and 50 years.(146) Dermoids usually occur in younger patients, between 10 and 20 years. I have operated on three posterior fossa dermoids in older patients, aged 35, 40, and 56 years. Epidermoids grow much more slowly, expanding through epithelial desquamation and accumulation of cellular debris. Dermoids expand through sebaceous secretion of sebum together with epithelial desquamation.
Original printed page 867
Locations
Epidermoids may occur in the skull diploë, cerebellopontine angle, parasellar region, optic chiasm region, fourth or lateral ventricle, cerebellum, or cerebrum. Dermoids are commonly found in the cerebellar midline and fourth ventricle and may also occur at the cauda equina, scalp, orbit, or paranasal region.
Epidermoids are usually unaccompanied by other anomalies. Dermoids often coexist with a dermal sinus, abnormal hair growth, localized skin discoloration such as a port-wine spot, or other malformations such as spina bifida.
Original printed pages 867–870
Symptoms and Signs
Because both tumors grow slowly, symptoms may evolve over years before medical attention is sought. Manifestations depend on location and reflect dysfunction of compressed brain tissue and cranial nerves, together with obstruction of CSF pathways. These tumors often occur in or near the midline and obstruct the ventricular system at the corresponding level. Cyst rupture may release keratin and cholesterol esters into the subarachnoid space or ventricles, producing chemical meningitis.(147) Patients with a dermoid cyst may present with bacterial meningitis repeatedly, with fever and neck stiffness. A dermal sinus and tract connecting to an intracranial or spinal dermoid allow microorganisms to enter the CSF. Recurrent bacterial meningitis should therefore always prompt a search for a midline dermal sinus over both the head and spine.
Figure 7.140. Contrast-enhanced CT showing a low-density epidermoid cyst in the cerebellopontine angle.Figure 7.141. Operative view of the cerebellopontine angle showing the epidermoid cyst wall compressing cranial nerves.
Suprasellar cysts produce visual manifestations by compressing the optic nerves and chiasm. Bitemporal hemianopia or optic atrophy may occur, with or without pituitary hormone deficiency. A large cyst extending laterally into the temporal lobe may present with seizures.
Cerebellopontine angle cysts cause local cranial nerve dysfunction, as do other tumors in this region. Enlargement produces corticospinal tract and cerebellar signs and eventually obstructive hydrocephalus. Some present with trigeminal neuralgia. For example, a 30-year-old patient developed sharp left facial pain and left tinnitus for 2 years and was treated medically for trigeminal neuralgia. Hearing subsequently declined and pain changed to numbness. Examination showed a diminished left corneal reflex and facial sensation, mild left facial weakness, and poorer hearing on the left than the right. CT showed a left cerebellopontine angle cyst compressing the pons (Figure 7.140). A suboccipital craniectomy approaching the left cerebellopontine angle revealed cranial nerves V, VII, and VIII compressed by an epidermoid cyst (Figure 7.141). This case illustrates the slow growth of epidermoids and their usually relatively mild compression of brain and nerves. Irritative symptoms often precede deficits: here, trigeminal neuralgia preceded facial numbness by 2 years. Relatively young patients with trigeminal neuralgia, hemifacial spasm, or tinnitus should therefore undergo detailed investigation of the cerebellopontine angle, where an epidermoid or another lesion may be found.
Intraventricular epidermoids and dermoids usually present with obstructive hydrocephalus. Headache is followed by vomiting and blurred vision associated with papilledema. Some patients have intermittent severe headaches. Most cysts are in the fourth ventricle, causing ataxia and nystagmus as well as raised intracranial pressure. Young children may develop head enlargement.
Figure 7.142. CT showing a low-density epidermoid cyst without enhancement after contrast administration.
Original printed pages 870–872
Diagnosis
Neurological symptoms and signs alone cannot establish the differential diagnosis, since they are the same as those of other expanding masses. Important diagnostic clues include a dermal sinus, a skin lump, a port-wine spot, or abnormal hair along the midline of the head, especially over the occiput, together with cerebellar signs and raised intracranial pressure.
Radiological investigations that may support the diagnosis include:
1. Skull radiographs may show a midline opening in the occipital bone through which a dermal tract passes. Lesions involving the skull produce an area of bone destruction with a clearly defined bony margin, and the affected region of the skull bulges outward.
2. CT is a very useful investigation. An epidermoid tumor appears as a low-density mass without enhancement after contrast injection(148,149) (Figure 7.142). This indicates that neither the wall nor the contents have a blood supply.
A dermoid tumor has the same CT appearance as an epidermoid tumor and cannot be distinguished from it on this basis. However, calcification or an associated dermal sinus may help differentiate them.
Figure 7.143 Operative photographs of a dermoid cyst in the fourth ventricle A. Sebum within the dermoid cyst B. A tuft of hair within the cyst C. Sebum and the tuft of hair D. The dermoid cyst wall firmly adherent to the brain surface
3. ANGIOGRAPHY is not useful for establishing the diagnosis; it shows only an avascular mass.
4. Ventriculography can demonstrate obstruction of CSF flow and the extent of the tumor when it lies within a ventricle.
Original printed pages 872–874
Treatment
For intracranial epidermoid and dermoid tumors, treatment consists of surgical removal of the entire cyst wall and its contents. Whether complete removal is possible depends on the location, size, adherence to brain tissue, cranial nerves and blood vessels, and the presence of infection. In locations such as the fourth ventricle and cerebellopontine angle, the wall is often firmly adherent to brain tissue, nerves and vessels. Attempting to dissect it away may do more harm than good. I have removed all the contents and excised the portions of wall that could be separated, leaving portions firmly adherent to important brain structures. If obstructive hydrocephalus is present, a V-A or V-P shunt is inserted. For example, a 35-year-old Chinese woman who sold food presented with unsteady gait and blurred vision. Examination revealed cerebellar signs and papilledema. A right brachial angiogram in 1973 (B.E. 2516) showed a posterior fossa mass and hydrocephalus. Contrast ventriculography then demonstrated a mass obstructing the fourth ventricle. Posterior fossa exploration revealed a dermoid tumor in the fourth ventricle and cisterna magna. On opening the cyst wall, soft white material (sebum) was found in the fourth ventricular portion and a clump of black hair in the cisterna magna (Figure 7.143, A–D). After all the contents had been removed, with care to prevent their dispersal into the CSF, the anterior and lateral walls were found to be firmly adherent to the tonsils, cerebellar hemisphere, vermis, floor of the fourth ventricle, blood vessels and cranial nerves. The outlets of the fourth ventricle could not be seen. In these circumstances, attempting to dissect the wall from the fourth ventricular floor and the other structures would damage vital brainstem centers. I therefore decided to close the wound and insert a V-A shunt. The patient recovered and returned home. At follow-up 18 years later, no symptoms had recurred. Two subsequent patients with dermoid cysts in the fourth ventricle were treated in the same way, also with good results. I consider this method suitable for dermoid cysts adherent to the floor of the fourth ventricle. Although treatment consisted only of removing all the cyst contents and leaving some epithelium attached to the brain, none of these three patients developed chemical aseptic meningitis. Nevertheless, when an epidermoid or dermoid cyst can be completely dissected away without loss of brain function, it should be removed in its entirety to cure the disease. Care must be taken to prevent the contents from spreading through the CSF, which can cause chemical meningitis(150)
Complete removal of an epidermoid or dermoid cyst in the cerebellopontine angle, as in the first example, is likewise difficult. Cysts in the basal cisterns often extend their walls into spaces between the brain, nerves and vessels because they are soft rather than firm like a tumor. Some extend upward into the middle cranial fossa, making complete excision impossible. The operative principle is to use a microscope and first remove the contents so that the cyst collapses. The wall is then grasped and dissected from the brain, nerves and vessels, aiming to remove it completely. Previous meningitis makes this dissection more difficult because of firm adhesions. If any portion is firmly adherent to a vessel, nerve or the brainstem, a small remnant should be left. Attempts at total removal may impair the function of that structure.
The same principles apply to intraventricular epidermoid or dermoid cysts. They are often easier to remove than those in the cerebellopontine angle because nerves and vessels are not attached to their walls. However, a ventricular cyst may adhere to important brain centers, such as the floor of the fourth ventricle or the hypothalamus in a third ventricular cyst. Its wall should not be dissected from these structures.
Original printed page 874
COLLOID CYST
A colloid cyst is a benign cyst that occurs specifically in the third ventricle. It is attached to the tela choroidea of the choroid plexus along the roof of the third ventricle, close to the posterior margin of the foramen of Monro. As it enlarges, it may obstruct one or both foramina of Monro, producing obstructive hydrocephalus.
Original printed pages 874–875
Symptoms and signs
Because the cyst obstructs CSF flow and causes hydrocephalus, most manifestations are the general symptoms of raised intracranial pressure: headache, vomiting and blurred vision (papilledema), without focal symptoms. Another important pattern may occur: very severe headache and vomiting followed by drowsiness or loss of consciousness, and even sudden death(152). These symptoms may improve after a change in head position. This can be explained by a stalked, mobile colloid cyst acting like a ball valve to open and close the foramen of Monro. In one head position, the cyst moves to obstruct CSF flow through the foramen, raising CSF pressure and producing severe headache. When the head position changes, the cyst moves away, CSF can flow out, and the headache subsides. Such episodes may recur. Similar manifestations may occur with tumors elsewhere within the ventricles, so they are not specific to a colloid cyst. Mechanistically, this pattern would be expected only with a small, mobile colloid cyst; a cyst filling the third ventricle would not produce it. Another possible explanation for improvement is that markedly raised pressure in the lateral ventricle displaces the cyst obstructing the foramen, opening the passage and allowing CSF to escape.
Weakness of both legs may accompany the headache. This results from hydrocephalus with markedly enlarged lateral ventricles compressing the corticospinal fibers to both legs, which lie close to the lateral ventricular walls.
In addition, longstanding, progressively worsening hydrocephalus may produce a syndrome resembling organic dementia, with unusual behavior and an unsteady gait resembling that caused by a posterior fossa tumor(153). This dementia is more likely to result from expansion of the lateral ventricles compressing cerebral hemispheric white matter than from compression of the anteroinferior hypothalamus by the cyst, since a colloid cyst lies above that region(154)
Original printed page 875
Diagnosis
Symptoms and signs alone cannot establish the diagnosis of a third ventricular colloid cyst because there are no specific focal manifestations. Nevertheless, a colloid cyst should always be considered when a patient reports intermittent attacks of very severe headache with improvement related to head position. Before CT and MRI became available, diagnosing a colloid cyst was difficult.
Original printed pages 875–877
Radiological investigations
In the past, cerebral angiography was used together with ventriculography. Angiography demonstrated only the features of hydrocephalus, without outlining the mass or showing tumor staining. In the venous phase, the internal cerebral vein might be displaced upward in an arch. Angiography was therefore of limited usefulness, but was important when surgery was planned and a vascular lesion, such as a basilar tip aneurysm, was suspected.
Ventriculography could outline the mass and identify the site of CSF obstruction. However, when both foramina of Monro were obstructed, it could not show the extent of the mass within the third ventricle. At that time, pneumoencephalography (PEG) was performed by injecting air into the lumbar subarachnoid space with the patient sitting, after draining CSF through a ventriculostomy tube to lower intracranial pressure. The air rose into the third ventricle and outlined the cyst. PEG is no longer performed because it is cumbersome, distressing to the patient and highly hazardous.
CT is regarded as the best investigation for a colloid cyst(155). It shows a round mass at the foramen of Monro, obstructing the foramen and producing hydrocephalus. The cyst is homogeneously hyperdense and enhances after contrast injection. MRI also delineates the location of the cyst and its relationship to surrounding brain structures well, because it provides views in multiple planes: axial, coronal and sagittal.
Image enhanced and colorized with AI · Switch to view the originalFigure 7.144 Approaches to a third ventricular colloid cyst and its excision
Original printed pages 877–878
Treatment of a colloid cyst
Surgical removal of the cyst is the best treatment and can provide a complete cure. However, the cyst lies in a difficult location to reach, and access may carry substantial risk. Fortunately, a colloid cyst has a stalk and its wall is not firmly adherent to the third ventricular wall, so complete removal is not particularly difficult with the aid of an operating microscope. The aims of surgery are to restore CSF flow and treat obstructive hydrocephalus, and to establish the tissue diagnosis, since radiological investigations cannot determine the tissue type.
There are two approaches to a colloid cyst (Figure 7.144):
1) Transcortical approach
2) Transcallosal approach
Both approaches enter the frontal horn of the lateral ventricle; see the section on craniopharyngioma for the technique. The transcortical approach is suitable when hydrocephalus is present, because the cortex is thin and the enlarged frontal horn makes ventricular entry easy. Its disadvantage is the possibility of postoperative seizures. The transcallosal approach is suitable when there is no hydrocephalus or the ventricles are small. It provides access to both foramina of Monro and does not cause seizures. However, both fornices may be injured during division of the corpus callosum, resulting in memory loss(156)
After entering the frontal horn, do not aspirate all the CSF, especially when the ventricles are very large. Leaving CSF within the ventricle prevents collapse, allowing the anatomy to be seen clearly, and also prevents acute subdural hematoma from tearing of bridging veins. The choroid plexus of the lateral ventricle leads to the foramen of Monro. In obstructive hydrocephalus, the foramen will be larger than normal. The colloid cyst has a pale green wall bulging at the foramen, with choroid plexus attached. First open the cyst wall and aspirate the thick, viscous fluid until the cyst collapses. Then grasp and turn the wall until its attachment to the choroid plexus is visible. Coagulate the attached portion of choroid plexus with bipolar coagulation and divide it. The cyst can then be removed easily. Finally, refill the ventricle with fluid and close the dura.
If the foramen of Monro is not sufficiently large, it may be enlarged by dividing the fornix on the operative side only. The veins around the foramen of Monro—the septal, thalamostriate and internal cerebral veins—should not be divided.
Original printed page 878
STEREOTACTIC ASPIRATION
This technique was introduced after CT became available. CT guidance is used to aspirate the viscous fluid within the cyst. Because the procedure is not performed under direct vision, it carries considerable risk, such as intraventricular hemorrhage. The viscous contents are also difficult to aspirate; only part may be removed, requiring repeat aspiration. In some patients, hydrocephalus persists and surgery is ultimately required(152). I have never used this method.
Original printed page 878
SHUNTING
Shunting treats only the hydrocephalus, not its cause, and has both advantages and disadvantages. It relieves raised intracranial pressure and reduces markedly enlarged ventricles, lowering the risk of subdural hematoma from tearing of bridging veins. A disadvantage is that a colloid cyst often obstructs both foramina. Inserting a shunt ventricular catheter on only one side may shift the opposite side of the brain toward the operated side and worsen the patient’s condition. This can be avoided by inserting ventricular catheters on both sides and connecting them to the shunt. In addition, prolonged shunting makes the ventricles small, making subsequent transcortical removal of the cyst difficult.
Original printed pages 878–879
Postoperative complications
With the operating microscope and microneurosurgical instruments, a colloid cyst can now be removed readily and successfully. Nevertheless, complications may occur: acute subdural hematoma from ventricular collapse and tearing of bridging veins; subdural hygroma when CSF escapes into the subdural space through the cortical or callosal opening; memory impairment from injury to the fornix; and seizures after a transcortical approach.
Original printed page 879
PITUITARY TUMORS
These are tumors of the pituitary gland, most arising in the adenohypophysis, or anterior lobe, which contains several types of cells. Formerly, they were named according to the H & E staining of the tumor cells: chromophobe adenoma, in which cytoplasmic granules do not stain; acidophilic adenoma, in which the granules stain red; and basophilic adenoma, in which they stain purple. Some neurosurgeons still use this older nomenclature. Electron microscopy and immunoperoxidase staining now identify hormone secretory granules in the cytoplasm, allowing tumors to be named according to the hormone secreted or its function: growth hormone–secreting adenoma; prolactin-secreting adenoma (prolactinoma); ACTH-secreting adenoma; TSH-secreting adenoma; FSH- and LH-secreting adenoma; plurihormonal adenoma, secreting more than one hormone, usually growth hormone and prolactin; and, finally, adenoma that produces no hormone.
Pituitary adenomas can thus be divided into two groups: hormone-producing, or endocrine-active, adenomas and non-hormone-producing, or endocrine-inactive, adenomas. Hormone-producing adenomas tend to cause endocrine manifestations related to the type of tumor cell rather than neurological symptoms. By contrast, non-hormone-producing adenomas cause no noticeable hormonal disturbance. They become large, and patients commonly seek medical attention because of optic chiasm compression, sometimes accompanied by other neurological symptoms. Hormone tests in this group are within normal limits, although some patients show hypopituitarism.
Original printed pages 879–880
PITUITARY ADENOMA
This is a tumor of adults, most commonly encountered between 35 and 45 years of age. In general, hormone-producing adenomas occur in younger patients than nonsecreting adenomas because hormonal abnormalities produce recognizable manifestations earlier, as in gigantism.
Pituitary adenocarcinoma and glioma of the posterior lobe (neurohypophysis) are very rare.
For details of the pathology of pituitary adenoma, see Chapter 3.
Original printed pages 880–882
Symptoms and signs
Details have already been discussed under focal manifestations in Chapter 6. The principal manifestations of pituitary adenoma can be summarized as follows.
1. Manifestations of mass effect These result from expansion of the tumor compressing structures around the sella turcica. The symptoms depend on the direction of extension:
1.1 Upward extension
I. The optic chiasm is compressed first, producing abnormalities of the visual fields and visual acuity. Characteristic findings are bitemporal hemianopia and primary optic atrophy. Patients often report bumping into people or objects at their sides. If the compressing tumor is not removed, blindness in both eyes will result.
II. Compression of the pituitary gland, pituitary stalk and hypothalamus. Some large tumors not only fail to secrete hormones but also compress normal glandular tissue. The nonneoplastic cells lose their function, causing hypopituitarism, with fatigue and impotence. Tumors compressing the stalk and hypothalamus disturb eating, sleep, thirst, temperature regulation and fluid balance, and may cause inappropriate ADH syndrome and diabetes insipidus.
III. Obstruction of CSF flow. A large mass compresses the basal cisterns and foramen of Monro, causing obstructive hydrocephalus. Patients develop headache and vomiting. Blurred vision is due to primary optic atrophy from direct chiasmal compression, not papilledema. Headache can in fact occur before hydrocephalus develops. I frequently find that patients initially describe pain behind the eyes and over the forehead. I believe that the expanding tumor exerts pressure on the sellar dura, particularly the diaphragma sellae, which is supplied by sensory branches of the trigeminal nerve. Later, when obstructive hydrocephalus develops, the headache becomes severe and generalized.
IV. Frontal lobe compression causes a frontal lobe syndrome, loss of smell from olfactory nerve compression, and seizures.
1.2 Lateral extension impairs cranial nerves III, IV, V and VI. Third nerve dysfunction is the most common, so patients often have ocular deviation, diplopia, ptosis and a dilated pupil. All extraocular muscles supplied by the third nerve are affected. Facial pain also occurs from trigeminal nerve compression. Extension to the medial temporal lobe may produce uncinate fits.
1.3 Posterior extension compresses cranial nerves and the brainstem, particularly the cerebral peduncle, causing limb weakness together with manifestations of the affected cranial nerves.
1.4 Downward extension may cause CSF rhinorrhea or a nasopharyngeal mass. Both are very rare.
2. Endocrine manifestations (endocrinopathies) Both hyperpituitarism and hypopituitarism occur. Hyperpituitarism produces manifestations according to the hormone excessively secreted by the tumor cells. For example, excessive growth hormone from a growth hormone–secreting adenoma causes gigantism in children or acromegaly in adults. Excess prolactin from a prolactinoma causes galactorrhea, amenorrhea and infertility. When one cell type in the gland becomes neoplastic, it may compress other cell types and impair their function, producing deficiencies of their hormones.
For detailed symptoms and signs associated with each hormone, see Chapter 5.
3. Manifestations of pituitary apoplexy Pituitary apoplexy means hemorrhage within the pituitary gland, most often in a pituitary adenoma. It causes rapid onset of neurological symptoms and signs.The cause of the hemorrhage has not been established, but an enlarging mass may undergo ischemic necrosis followed by hemorrhage. It is often encountered after preoperative radiotherapy and during bromocriptine treatment. The tumor rapidly swells, compressing the optic nerves and chiasm, cranial nerves, cavernous sinus, internal carotid artery, hypothalamus and the pituitary gland itself. Patients may or may not have had previous manifestations of a pituitary adenoma. They suddenly develop headache, vomiting, loss of vision and deterioration of consciousness progressing to coma, with shock due to acute adrenal insufficiency. Some have neck stiffness and photophobia, indicating subarachnoid hemorrhage caused by rupture of the region of pituitary apoplexy.
Original printed pages 882–885
Diagnosis
The diagnosis of a pituitary tumor can be based on the following:
A. Symptoms and signs As described above, these include:
1. Manifestations of hyperpituitarism according to the hormone-secreting tumor cell type, such as prolactinoma (hyperprolactinemia), gigantism and acromegaly (elevated growth hormone), and Cushing’s disease (elevated ACTH); and manifestations of hypopituitarism or panhypopituitarism. The latter include fatigue, loss of libido, absence of pubic and axillary hair, poor tolerance of temperature changes, dry, coarse, cool skin, testicular atrophy, and possibly diabetes insipidus.
2. Chiasmal compression causing bitemporal hemianopsia, an important focal sign of pituitary adenoma.
B. Endocrine investigations Pituitary hormones are measured to identify the different tumor types.
1. The hormone excessively secreted by the cells of a hyperfunctional pituitary adenoma determines the endocrinopathy: for example, hyperprolactinemia, excess growth hormone (acromegaly or gigantism), or ACTH excess (Cushing’s disease).
2. Pituitary hormone reserve. In a patient with a pituitary adenoma, assessment of hormone deficiencies and the reserve function of both anterior and posterior lobes is important. These patients commonly have accompanying hypopituitarism that may not be clinically obvious, but becomes apparent during stress or surgery and may lead to failure and death. The various hormone deficiencies and the true residual function of the gland must therefore be assessed so that they can be corrected before and after surgery.(158,159) Important preoperative investigations include target-gland hormones such as cortisol (adrenal gland) and T4 and T3 (thyroid gland), together with urine output and serum electrolytes (ADH, posterior lobe).
Methods of hormone investigation can be found in endocrinology and physiology textbooks.
C. Radiological investigations These can delineate the size of the sella turcica, the size and type of tumor, and the positions of the optic nerves, chiasm and vessels in considerable detail.
1. Skull radiographs. A pituitary adenoma growing within the sella turcica produces important changes on the lateral skull film. The sella becomes enlarged and rounded, extending beneath the anterior clinoid or tuberculum sellae, an appearance called “ballooning of the sella” (Figure 6.18). The dorsum sellae is displaced backward and thinned, or may disappear entirely when the mass is large. The sellar floor may also be eroded away. In some cases, the anterior clinoid process is thinned and elevated. Unequal growth on the two sides of the sella often produces sellar floors at different heights, termed a “double sellar floor” (Figure 6.19). This appearance may also occur with a medial sphenoid wing meningioma or an intracavernous internal carotid artery aneurysm. These changes are most often seen with chromophobe adenomas. Acidophilic and basophilic adenomas usually produce little or no sellar change, because these functioning adenomas cause symptoms before the sella turcica changes. Calcification, although very rare, may also be seen, as may a tumor shadow within the sphenoid sinus
For a surgeon planning a transsphenoidal operation, the lateral skull radiograph is useful because it shows the size and position of the sphenoid sinus and whether its configuration is sellar, presellar or conchal(86). These configurations differ in the ease of access to the sellar floor. The film also shows the thickness of that floor.
2. POLYTOMOGRAPHY provides sectional radiographs showing greater detail of the sella. This investigation has been abandoned since CT became available.
3. ANGIOGRAPHY is performed to assess suprasellar or parasellar extension. The frontal view shows elevation of the anterior cerebral artery and lateral displacement of the carotid siphon. On the lateral view, the carotid siphon is widened because the clinoid segment of the internal carotid artery is elevated. Angiography also excludes aneurysms of the internal carotid and anterior communicating arteries, an essential consideration in surgery for sellar lesions. In the past, surgeons have inadvertently entered an aneurysm, resulting in death. CT and MRI now demonstrate the pathology and tumor so clearly that angiography is seldom performed.
4. PNEUMOENCEPHALOGRAPHY (PEG) clearly shows suprasellar tumor extension and its relationship to the optic chiasm and third ventricle. However, it cannot exclude an aneurysm, so angiography must always accompany it for this purpose (Figure 6.136). PEG is now obsolete and is no longer performed.
5. COMPUTED TOMOGRAPHY and MRI are the best investigations for pituitary tumors. They clearly show the margins, shape, composition and relationship to adjacent structures, rendering other investigations obsolete.
Original printed pages 885–886
Treatment of pituitary adenoma
Several methods are available:
1) Surgery
2) Drug treatment
3) Radiotherapy
The choice depends on several factors: the patient’s age, physical condition and medical illnesses, and the abnormalities caused by the tumor, such as optic chiasm compression, ocular palsy, extension into the frontal and temporal lobes, and the type of hyperpituitarism—acromegaly or gigantism, Cushing’s disease, or hyperprolactinemia—as discussed below.
There are four principal objectives in treating a pituitary adenoma:
i) Relieve compression of the optic pathways, other cranial nerves and adjacent brain.
ii) Reduce excessive endocrine activity to restore normal, or as nearly normal as possible, hormone secretion.
iii) Preserve normal function of both anterior and posterior pituitary lobes so that hormone replacement is unnecessary; and
iv) Prevent tumor recurrence.
These objectives can be achieved only by complete surgical removal of the tumor. This is generally possible only for a small tumor, termed a microadenoma, confined to the sella and removable through a transsphenoidal approach. By contrast, complete removal of a large tumor with suprasellar or parasellar extension without damaging other parts of the pituitary gland is difficult, and additional treatment may be needed. Drug treatment, such as bromocriptine for a prolactinoma, can reduce optic pathway compression and hormonal symptoms, but is effective only while the drug is being taken. If it is stopped, the symptoms recur. Such treatment is therefore not curative and must be continued for life.
Once a pituitary adenoma has been diagnosed, the treating physician must carefully consider and decide on a treatment plan. Some patients do not require immediate treatment, whereas others need urgent intervention. The first group comprises patients whose adenomas cause no neurological symptoms and show no intracranial extension. Headache or some hypopituitarism alone does not indicate an urgent need for surgery, since treatment may not improve the outcome and may cause complications. Such patients should be followed with neurological examinations, hormone measurements and repeat CT to detect changes. In some, the tumor may grow intracranially and require surgery.
The other group requires prompt surgery. It is generally accepted that surgery is necessary when the tumor causes progressive visual deterioration. Removal offers two benefits: immediate relief of optic pathway compression and determination of the tumor type.
Original printed pages 886–887
I. Surgical treatment
Surgery is considered the best treatment, especially for small adenomas, termed microadenomas, whether endocrine-active or endocrine-inactive. Using an operating microscope and microneurosurgical instruments, the surgeon can achieve complete removal while preserving the function of the normal gland, allowing normal hormone secretion after surgery.
No single operation is ideal for all pituitary adenomas. In general, there are two approaches:
i) Transcranial approach
ii) Trans-sphenoidal approach
The choice must take into account the size and shape of the tumor, suprasellar or lateral parasellar extension, visual pathway compression, the anatomy of the sella and sphenoid sinus, and the patient’s health, in order to obtain the best operative result. In some cases, both methods may be needed, using a transsphenoidal approach first and then a transcranial approach to remove the suprasellar component.
Original printed pages 887–891
1) TRANSCRANIAL APPROACH
The tumor is approached through a frontal or frontotemporal craniotomy. This is suitable for pituitary adenomas with suprasellar, parasellar or retrochiasmal extension, or a dumbbell configuration, especially a suprasellar tumor with a normal sella turcica or a very small sphenoid sinus. Tumors of these configurations cannot be completely removed by a transsphenoidal approach.
Several corridors can be used to reach and remove the tumor, depending on its location, the direction of extension and the position of the optic chiasm, as demonstrated by CT and MRI. Each has the following advantages and disadvantages.
1.1 Subfrontal approach The frontal lobe is elevated, providing three routes to the tumor (Figure 7.132):
i) Between the two optic nerves when the chiasm is postfixed.
ii) Between the optic nerve and internal carotid artery, suitable for a prefixed chiasm with lateral tumor extension.
iii) Through the lamina terminalis when the tumor is retrochiasmal or within the third ventricle.
The subfrontal approach has the advantage of displaying both optic nerves, the chiasm, the internal carotid artery and its branches, and the pituitary stalk. It is therefore suitable for an adenoma extending into the anterior suprasellar region with a postfixed chiasm, allowing extensive visualization of the tumor (Figure 7.133). Its disadvantage is poor tumor exposure when the chiasm is prefixed.
Technique of the subfrontal approach For frontal craniotomy, see the beginning of Chapter 7. Good exposure of the sellar region requires the anterior edge of the craniotomy to be low, close to the orbital ridge or roof, minimizing frontal lobe retraction. After opening the dura, a tense brain can be relaxed by draining CSF from the subarachnoid space at the chiasmatic cistern or by frontal ventriculostomy. Retract the lateral portion of the frontal lobe to expose the lesser sphenoid wing, then follow it medially to the anterior clinoid process. Open the subarachnoid space between the optic nerve and internal carotid artery, allowing CSF to flow slowly while continuously aspirating it. After a short wait, the brain relaxes considerably and the frontal lobe can be elevated readily. Divide the olfactory nerve, leaving the bulb attached to the cribriform plate to prevent CSF rhinorrhea. If the nerve is not divided, tearing often causes bleeding. Elevation and retraction of the posterior frontal lobe first expose the internal carotid artery, right optic nerve and chiasm. Wide division of the arachnoid around the chiasm allows further frontal retraction, clearly revealing the left optic nerve and chiasm. With a postfixed chiasm, the tumor wall is clearly visible between the two optic nerves, with the chiasm behind and tuberculum sellae in front (Figure 7.145)
Figure 7.145 Subfrontal operation for a pituitary adenoma, showing the tumor (1), both optic nerves (2), and the internal carotid artery (3)Figure 7.146 The same operation as Figure 7.145 after tumor removal
Next, puncture the tumor wall with a needle and aspirate its contents to ensure that it is not an aneurysm. Coagulate the vessels on the adenoma surface between the two optic nerves, excise a circular opening in the wall, and aspirate or curette the tumor internally to reduce its size (Figure 7.146). Control bleeding within the tumor with bipolar coagulation. The wall adjacent to the left optic nerve is readily seen and easily dissected away. Continue toward the chiasm, but do not pull the wall away from the chiasm or hypothalamus, as this may tear their supplying vessels. Hemostasis is difficult behind the obscuring chiasm and often endangers the patient. Leaving a small portion of wall attached to the chiasm or hypothalamus may be safer. Avoid damage to the pituitary stalk and normal gland. Tumor on the right, usually hidden by the right optic nerve and chiasm, may be exposed by placing a cotton pledget between the optic nerve and internal carotid artery and pushing the tumor wall medially. It can then be grasped and excised while its vessels are coagulated. If a bleeding point is poorly seen and cannot be treated with bipolar coagulation, cover it with Gelfoam and apply pressure until bleeding stops. Hemostasis must be certain; otherwise, an expanding hematoma may cause postoperative loss of vision and, in most cases, death. During tumor dissection, avoid traction on the optic nerves and chiasm, as this may further impair vision. Preserve their supplying vessels, most of which lie on the undersurface.
Figure 7.147 Frontotemporal approach to a pituitary adenoma with lateral (parasellar) extension. The tumor is clearly visible (arrow).
1.2. fronto-temporal approach This approach is suitable for a prefixed chiasm and parasellar tumor extension, exposing tumor in both the anterior and middle fossae. A disadvantage arises when the face is turned too far to the opposite side, obscuring the contralateral optic nerve.
Perform a frontotemporal craniotomy with a low temporal opening to expose the anterior temporal lobe and Sylvian fissure widely. Retract the frontal and temporal lobes apart to reveal the parasellar tumor, optic nerve, chiasm, optic tract and internal carotid artery (Figure 7.147). If greater separation of the lobes is required, divide the arachnoid at the anterior Sylvian fissure.
In this region, the optic nerve lies medial to the anterior clinoid process and the internal carotid artery lies below and lateral to the optic nerve. Behind the internal carotid artery is the margin of the tentorial notch. The posterior communicating and anterior choroidal arteries and the oculomotor nerve are generally seen lateral or posterior to the tumor.(161) Remove the tumor through the interval between the optic nerve and chiasm on one side and the internal carotid artery on the other, or lateral to the artery. Debulk it internally to reduce its size, then separate the wall from the optic nerve, chiasm, oculomotor nerve, internal carotid artery and its branches. However, the intrasellar component is relatively difficult to remove. Because the tumor is often large, attempts at complete removal may endanger the patient’s life. The surgeon must decide during the operation when to stop. If further removal appears hazardous, do not attempt total excision; use additional treatment afterward.
1.3. subtemporal approach This approach elevates the temporal lobe and is suitable for an adenoma extending behind the chiasm (retrochiasmal suprasellar extension)(162). The craniotomy must extend down to the floor of the temporal fossa, and CSF must be drained to relax the brain. This facilitates temporal lobe retraction and tumor exposure. Remove the tumor internally with suction and a curette to reduce its size and relieve compression of the optic chiasm and hypothalamus. I consider this sufficient, since this approach cannot completely remove tumor occupying both the sella and retrochiasmal region. Attempts at total removal often damage the hypothalamus, leaving the patient unconscious and ultimately resulting in death.
Original printed pages 891–893
2. TRANSSPHENOIDAL APPROACH
This operation passes through the sphenoid sinus into the sella turcica without a craniotomy. It has been performed since Cushing’s time, but initially was not very popular because the tumor and surrounding structures were poorly visualized. It is now gaining considerable popularity thanks to aids such as operating microscopes providing good magnification and illumination, microneurosurgical instruments, and televised fluoroscopy for intraoperative guidance, making surgery faster and more successful. Its advantages are:
i) There is no externally visible wound, and the operation is less traumatic than a craniotomy.
ii) Once the pituitary gland is reached, the adenoma can be distinguished from normal glandular tissue, particularly in microadenomas. Complete tumor removal is possible while preserving normal hormone-secreting tissue, making hormone replacement unnecessary.(163)
iii) After complete removal, radiotherapy is unnecessary, so the patient avoids the hazards of irradiation.(164)
iv) The risk of injury to the optic nerves, chiasm and olfactory nerves is low.
Indications for the transsphenoidal approach include:
i) An intrasellar microadenoma, still small and confined to the sella, or with suprasellar extension that does not extend beyond the optic chiasm.
ii) An adenoma projecting into the sphenoid sinus and extending laterally toward the cavernous sinus.
iii) A prefixed chiasm, now identifiable with CT and MRI.
iv) A tumor associated with CSF rhinorrhea; the transsphenoidal route allows closure of the leak at the sphenoid sinus.
v) Poor general health that is considered incompatible with tolerating a craniotomy.
vi) Other lesions, such as an intrasellar craniopharyngioma, nasopharyngeal carcinoma, or a sphenoid mucocele or cyst.
vii) When hypophysectomy is required.
Contraindications to the transsphenoidal approach include:
i) Extensive suprasellar growth with a dumbbell configuration, or parasellar extension, for example into the frontal, temporal or retrochiasmatic regions.
ii) Infection of the sphenoid sinus.
iii) A normal-sized sella turcica with a conchal sphenoid sinus, making access to the pituitary fossa difficult. Some surgeons do not consider this a contraindication(162) because a bone drill can be used.
Original printed pages 893–897
Technique of the transsphenoidal approach
There are several routes to the sphenoid sinus, but the simplest and most popular is the sublabial rhinoseptal transsphenoidal approach. General anesthesia is used. Position the patient supine with the head of the table slightly elevated, the neck flexed approximately 20°, and the head turned to the right. A right-handed surgeon enters through the left nostril. Position a C-arm fluoroscope to obtain a lateral skull view with the sphenoid sinus centered. Prepare the mouth, nose and lower abdomen with antiseptic solution and drape them. The abdominal site is used to obtain fat for packing the sellar region.
Begin by elevating the upper lip and making a transverse incision approximately 3 inches long at the junction of the gingival and labial mucosa. Elevate the submucosal tissue to expose the nasal apertures. Separate the nasal mucosa from both maxillary fossae and from the left side of the nasal septum. Detach the base of the septum from the maxilla and dissect the mucosa along the vomer toward the sphenoid sinus until its anterior wall is reached (Figure 7.148, A and B). Insert a nasal speculum between the nasal septum and vomer on one side and the nasal mucosa on the other. Opening it exposes the left half of the anterior sphenoid sinus wall. Fracture the vomer at its attachment to that wall to allow further opening of the speculum, exposing both halves of the anterior wall while displacing the nasal septum to the right (Figure 7.148, C). During the dissection, use brief intermittent C-arm fluoroscopic views on the television monitor to improve confidence and speed. Once the sinus is reached, use the operating microscope. Remove the anterior sphenoid sinus wall with a rongeur, making the opening wide enough to allow easy removal of the sellar floor. Remove all sphenoid sinus mucosa and advance the speculum tip into the sinus. Once an adequate bony opening has been made, do not forcibly widen the speculum further, as this may fracture the bone. After identifying the sellar floor, confirm its position with C-arm fluoroscopy before removing it (Figure 7.149). In some patients the floor is very thin, or tumor may already protrude into the sphenoid sinus. Laterally, stop removal of the sellar floor at the cavernous sinus wall; superiorly, extend to the intercavernous sinus. Extending too high to the diaphragma sellae may cause CSF rhinorrhea. Then open the dura. A large adenoma is readily seen, whereas a microadenoma may be difficult to identify. CT or MRI may be needed to locate it before incising the gland to reach the tumor. Before opening the tumor wall, puncture it with a needle and aspirate to ensure that it is not an aneurysm. Dissect the adenoma from the normal gland. Its color and appearance are clearly different from normal pituitary tissue. It can be removed readily with blunt ring curettes, an enucleator (Figure 7.150) and suction. Secure hemostasis with Gelfoam or bipolar coagulation to prevent a hematoma, which could impair vision and be fatal. Pack the sellar cavity with the fat previously obtained from the abdomen to prevent CSF rhinorrhea. Reinforce the sellar floor with nasal cartilage. Remove the speculum and pack both nostrils with Vaseline gauze to restore the nasal mucosa and align the septum in the midline. Close the gingivolabial incision with catgut. Remove the Vaseline gauze after 24–48 hours.
Image enhanced and colorized with AI · Switch to view the originalFigure 7.148 AImage enhanced and colorized with AI · Switch to view the originalFigure 7.148 BImage enhanced and colorized with AI · Switch to view the originalFigure 7.148 Sublabial rhinoseptal transsphenoidal approach for a pituitary tumor A. Incision at the junction of the lip and gingival mucosa. B. Elevate the submucosal tissue to expose the nasal apertures and separate the mucosa from the nasal septum and maxillary sinus wall. C. Insert the nasal speculum and fracture the vomer at its attachment to the sphenoid sinus wall.Image enhanced and colorized with AI · Switch to view the originalFigure 7.149 Removal of the anterior sphenoid sinus wall and sellar floor, with the speculum tip within the sphenoid sinus.
Original printed pages 897–904
Preoperative and postoperative care of patients with pituitary tumors
Pituitary hormone deficiency in patients with pituitary tumors may be life-threatening and requires treatment before, during and immediately after surgery, as well as in the long term. Important deficiencies to investigate and correct before surgery include adrenal hormones, thyroid hormones and posterior pituitary vasopressin. Vasopressin deficiency is particularly important immediately after surgery, because fluid and electrolyte balance can change rapidly. Failure to correct these hormonal deficiencies may cause circulatory failure and death in the early postoperative period. Gonadotropin and growth hormone deficiencies are less important initially, since these hormones are not essential for survival under stress, but they require attention in long-term care.
Image enhanced and colorized with AI · Switch to view the originalFigure 7.150 Opening the dura and removing the adenoma.
1) Preoperative care Every patient undergoing pituitary surgery must undergo assessment of ACTH reserve, adrenal function, thyroid function and electrolyte balance. Abnormalities commonly take the form of hypopituitarism, hypothyroidism and adrenal insufficiency. Patients must also be investigated for diabetes mellitus, diabetes insipidus and hypertension, which may accompany a pituitary tumor. These abnormalities must always be treated with hormone replacement and appropriate medication before surgery.
STEROIDS must be given before surgery in every case, even when pituitary and adrenal hormone investigations are normal, because some pituitary damage almost always occurs during the operation. The steroid administered should be a target-gland hormone. Hydrocortisone is preferred, replacing deficient adrenal corticosteroids, at a total dose of 200–300 mg/day in divided doses. In practice, 100 mg is given intravenously on the night before surgery, followed by another 100 mg on the morning of surgery, mixed with 1,000 cc of intravenous fluid and infused throughout the operation and over a total of 24 hours. The dose is gradually reduced over subsequent days and discontinued approximately 4–5 days after surgery. Patients with preoperative adrenal insufficiency require continued maintenance treatment. Prednisolone is commonly used because it is readily available and inexpensive, at 5 mg orally every morning.
Dexamethasone or prednisolone may be substituted for hydrocortisone at equivalent doses. In practice, dexamethasone 5 mg intravenously every 6 hours is given for at least 24 hours before surgery and continued through postoperative day 4–5, with gradual dose reduction until it is stopped or a maintenance dose is reached.
Thyroid hormones. Patients with hypothyroidism require thyroid hormone treatment for 3–4 weeks before surgery. Adrenal reserve must always be assessed before thyroid hormones are administered. If reserve is abnormal, corticosteroids must be given for 2–3 days before starting thyroid hormones to prevent adrenal crisis, because thyroid hormones increase metabolism and adrenal activity.(165) Thyroid hormone treatment must begin at a low dose and gradually increase to 0.1–0.2 mg/day. Starting immediately with a high dose may cause angina pectoris, arrhythmia or heart failure.(166)
Patients with diabetes mellitus require individualized insulin treatment before, during and after surgery. They are at risk of hyperglycemia because steroids, hyperosmolar agents and phenytoin are used relatively frequently. Hyperglycemia causes osmotic diuresis, worsening neurological symptoms and hypovolemia.
In patients with diabetes insipidus, dehydration must likewise be corrected with Pitressin or the desmopressin analogue DDAVP (1-deamino-8-D-arginine vasopressin), both before and after surgery.
2) Postoperative care Treatment can be divided into immediate postoperative treatment and long-term postoperative treatment.
2.1 Immediate postoperative treatment This is the most critical period: part of the pituitary gland may have just been damaged during surgery, and the patient is under stress. Adrenal hormone (cortisol) requirements increase, particularly during the first 24 hours, then decrease over subsequent days. Hydrocortisone must therefore be administered promptly and in adequate amounts to replace the deficiency and meet increased needs. Three major conditions requiring immediate postoperative correction are pituitary or adrenal insufficiency, hypothyroidism and diabetes insipidus.
adrenal insufficiency For adrenal insufficiency, hydrocortisone must be given before, during and after surgery as described above. When preoperative pituitary–adrenal function is normal, as in a microadenoma, complete tumor removal without damage to the pituitary gland usually leaves this function normal after surgery.(167,168) Steroids are therefore given for only 3–4 days, and the patient can go home without replacement medication. Patients with preoperative pituitary–adrenal insufficiency, however, require adequate postoperative steroid replacement and a maintenance dose after discharge. They must be told that the dose may need to be increased during stress or illness.
hypothyroidism In patients who are euthyroid before surgery, pituitary surgery may cause thyroid-stimulating hormone (TSH) deficiency. This is of limited importance in the immediate postoperative period because circulating thyroxine has a plasma half-life of up to 7 days.(165) In contrast, patients with preoperative hypothyroidism who have not received adequate thyroxine replacement may develop worsening thyroid deficiency immediately after surgery, causing drowsiness and eventually unconsciousness. Such patients therefore require thyroid hormones both before and after surgery. In practice, sodium L-thyroxine is given at 50–200 micrograms/day, starting low and gradually increasing. Elderly patients and those with coronary artery disease must start at a very low dose, increased very slowly. A high dose or rapid escalation may precipitate angina. The dose is individualized according to symptoms and serum thyroxine (T4).
diabetes insipidus This is an important and common complication of pituitary surgery, with variable severity. If diabetes insipidus was absent before surgery and neither the pituitary stalk nor the posterior lobe was damaged, postoperative diabetes insipidus is usually transient, lasting approximately 2–3 weeks before gradually resolving. This may be explained by the sensitivity of the hypothalamic–neurohypophyseal unit, including the pituitary stalk, to changes in local blood flow, traction on the stalk during surgery and postoperative local swelling. In patients with preexisting diabetes insipidus, the condition usually worsens after surgery and requires lifelong treatment, because the neurohypophysis and stalk have been damaged by a large tumor and by the surgeon’s efforts to remove it.
Diabetes insipidus usually becomes apparent 12–24 hours after pituitary surgery. Diagnostic findings include urine output exceeding 150 cc/hour, specific gravity below 1.005, urine osmolarity below 200 mOsm/kg, serum osmolarity above 300 mOsm/kg or serum sodium above 145 mEq/L. Accurate diagnosis and prompt treatment prevent dehydration and electrolyte disturbances. Untreated diabetes insipidus causes hypovolemia, hyperosmolarity and dehydration, leading to fever, hyperpnea, progressive drowsiness, unconsciousness and ultimately death. Urine output and fluid intake must therefore be measured carefully throughout, initially perhaps hourly, then every 4 hours as the patient improves. Serum electrolytes and osmolarity should be measured, with a urine sample sent simultaneously for osmolarity.
Treatment of diabetes insipidus Once diabetes insipidus has been diagnosed, several treatments are available, selected according to the individual patient’s condition. An alert postoperative patient with mild diabetes insipidus, an intact thirst mechanism and no contraindication to oral intake should drink enough water to replace urinary losses. If polyuria and polydipsia prevent sleep, or consciousness is impaired and the thirst mechanism is defective, other treatment is required, such as intravenous fluid and appropriate medication.
Intravenous hydration. Intravenous fluid should be given as 5% D/W because diabetes insipidus causes predominantly water loss, with very little Na+ loss. Nevertheless, saline should also be given at approximately 75 mEq/day (equivalent to 500 cc of normal saline). The fluid volume for each 6-hour period is calculated from the urine output during the preceding 6 hours plus 6 hours of insensible loss (12.5 cc/kg/24 hours divided by 4).
ADH should be considered when urine output exceeds 4,000 cc/day. Several preparations are currently available:
i) Aqueous Pitressin is suitable for the first postoperative days. It acts rapidly but has a short duration of approximately 3–6 hours. The dose is 2–5 units subcutaneously every 3–6 hours. Its disadvantages are frequent injections and continual fluctuations in water and sodium balance. It also causes vasoconstriction, which may precipitate angina in patients with preexisting coronary artery disease.
ii) Pitressin tannate in oil acts slowly but lasts 24–72 hours. The dose is 5–10 units intramuscularly once daily or on alternate days, individualized for each patient. Correct preparation before injection is essential; otherwise treatment will be ineffective. Warm the ampoule for approximately 15 minutes to facilitate suspension, then immediately shake it vigorously until the drug particles are completely suspended in the oil. This ensures that the required amount of active drug is withdrawn. Because this preparation is long-acting, excessive oral or intravenous fluid intake may cause water intoxication, and caution is required.
iii) DDAVP is a synthetic vasopressin with a duration of approximately 12–24 hours. Start at 2.5 micrograms by nasal insufflation and increase in 2.5-microgram increments until the desired effect is achieved. Give the first dose at night so that the patient can sleep without getting up to urinate. Repeat during the day when the night-time dose wears off. DDAVP is easy to administer and has no cardiovascular effects at therapeutic doses, so it is now preferred over other drugs for long-term treatment of diabetes insipidus(169), although its high cost is a disadvantage.
iv) Other drugs, such as chlorpropamide and clofibrate, have been used for mild diabetes insipidus in patients who can replace losses by drinking and retain some ADH-producing tissue. In the author’s experience, they are ineffective in severe diabetes insipidus.
Chlorpropamide stimulates ADH release and potentiates the effect of the ADH already present. The dose is 100–500 mg/day, with an effect apparent after 1 week of treatment. As chlorpropamide is an antidiabetic drug, hypoglycemia must be watched for.
Clofibrate also stimulates ADH release from the neurohypophysis but does not potentiate ADH action. It is therefore useful only when some ADH-producing tissue remains. The dose is 500 mg three times daily. Combining it with chlorpropamide improves the response.
2.2 Long-term postoperative treatment Conditions requiring continued treatment include pituitary–adrenal insufficiency, hypothyroidism, diabetes insipidus, hypogonadism and growth hormone deficiency.
Hypothalamic–pituitary–adrenal function must be reassessed 4–6 weeks after surgery, withholding steroids for 48–72 hours before testing. Patients with low cortisol and an inadequate response to testing require steroid replacement. Reassess glandular function after approximately 6–12 months; if it has improved, the steroid dose may be reduced or stopped. Patients with hypothalamic–pituitary–adrenal dysfunction who have undergone removal of a large tumor often have permanent hypopituitarism and require lifelong steroid replacement.
Prednisolone 5 mg/day generally provides adequate replacement. The dose may need to increase during stress. With severe stress, such as injury or surgery, intravenous steroids are required: hydrocortisone 100 mg every 8 or 6 hours. Patients with preoperative hypothyroidism require postoperative thyroid hormone replacement with sodium L-thyroxine 0.1–0.2 mg/day, adjusted for body size and blood T4 and T3 levels.
Preoperative or postoperative hypogonadism does not require immediate hormone replacement. Wait another 3–6 months to allow gonadal function to recover spontaneously; this delay does not harm the patient. Amenorrhea–galactorrhea syndrome likewise may take several months, or even a year, to return to normal, so hormones should not be given during this period.
If hormone replacement is necessary in men, testosterone propionate is given at 200–300 mg intramuscularly every 2–3 weeks.(170) In women, give ethinyl estradiol 10–15 micrograms/day or conjugated estrogens 0.625–1.25 mg/day for 25 days each month, followed by oral medroxyprogesterone 5–10 mg/day for the remaining 5 days to induce menstruation.
Growth hormone deficiency does not require replacement in adults who have reached full body size. In growing children, however, if growth is less than 4.5 cm/year and bone age is 2 years below normal or less, hormone treatment is required until full height for age is reached.(171)
Original printed pages 904–905
II Drug treatment
Drug treatment of pituitary tumors is used mainly for functioning tumors, which overproduce prolactin, growth hormone or ACTH according to tumor type. The aim is to reduce or eliminate excessive hormone secretion by tumor cells, restoring normal levels so that the resulting systemic abnormalities resolve. These drugs are generally used together with other treatments, such as surgery or radiotherapy. Medication alone cannot eradicate the tumor, although some drugs may temporarily shrink it while treatment continues. If treatment is stopped, excessive hormone secretion and tumor growth may recur. Furthermore, tumor shrinkage does not occur in every patient, even when hormone secretion is reduced, and the drugs may cause adverse effects.
There is no drug treatment for nonfunctioning pituitary tumors, except that patients with hypopituitarism caused by compression of the gland require hydrocortisone, thyroxine and vasopressin to replace their deficiencies.
Individual drugs are discussed below under the treatment of each type of functioning pituitary tumor.
Original printed page 905
III Radiotherapy
See the sections on the individual types of pituitary tumor.
Original printed page 905
FUNCTIONAL PITUITARY TUMORS
In order of frequency, the common types are prolactin-secreting adenoma, growth hormone-secreting adenoma and ACTH-secreting adenoma (Cushing’s disease).
Original printed pages 905–906
A. PROLACTIN-SECRETING ADENOMA
Also called a “prolactinoma,” this is the most common hyperfunctioning pituitary tumor. It causes hyperprolactinemia, producing amenorrhea and galactorrhea in women, and impotence and hypogonadism in men, sometimes with gynecomastia and galactorrhea.
Prolactin secretion into the bloodstream is controlled by hypothalamic neurohormones that stimulate or inhibit secretion (releasing and inhibiting factors)(172), although their predominant action is to inhibit prolactin secretion(170). The term prolactin inhibition factor (PIF) is therefore used. PIF is necessary to prevent unrestricted excessive prolactin secretion by the adenohypophysis. It passes through the pituitary stalk to regulate the adenohypophysis. Consequently, damage to the stalk or hypothalamus reduces PIF production or delivery to the anterior lobe, allowing serum prolactin to rise(173). PIF acts like dopamine(174,175), and there are reasons to believe that PIF is dopamine(175). Dopamine or dopamine agonists stop prolactin secretion; this action is used to treat prolactin-secreting tumors. The hypothalamic hormone that stimulates the anterior pituitary to secrete prolactin is called prolactin releasing factor (PRF).
Hypothalamic thyrotropin releasing hormone (TRH) is another PRF that stimulates prolactin secretion. Patients with low TRH or hypothyroidism also have low prolactin.
Although prolactinoma is the main cause of hyperprolactinemia, several other causes are possible:
Physiological states: pregnancy, early lactation, stress, sexual intercourse and sleep.
Pituitary tumors: prolactinoma, acromegaly and Cushing’s disease.
Lesions damaging the hypothalamus and pituitary stalk, such as craniopharyngioma, Rathke’s pouch cyst, germinoma, astrocytoma, meningioma, aneurysm and brain injury.
Drugs, including monoamine-depleting drugs (reserpine, methyldopa); dopamine-blocking drugs (haloperidol, phenothiazine, chlorpromazine, pimozide); histamine 2 blockers (cimetidine); and opiates (morphine, methadone).
primary hypothyroidism
“Empty sella” syndrome
Other causes, such as renal failure, polycystic ovary syndrome and chest injury.
In practice, there are four common causes: i) prolactin-secreting tumors; ii) drugs, particularly phenothiazines; iii) primary hypothyroidism; and iv) lesions damaging the hypothalamus and pituitary stalk(176,177). Distinguishing causes of hyperprolactinemia that produce similar signs and symptoms is sometimes difficult, particularly with a microadenoma and a serum prolactin level that is not markedly elevated.
Original printed pages 906–908
Diagnosis of prolactinoma
Diagnosis is based on:
1. Signs and symptoms of endocrinopathy due to hyperprolactinemia, mass effect, or both. Mass effect produces symptoms similar to those of other nonfunctioning pituitary tumors. In particular, compression of the remaining pituitary gland and optic chiasm causes hypopituitarism and bitemporal hemianopia. A large mass may compress the hypothalamus and cause raised intracranial pressure by obstructing the foramen of Monro.
The manifestations of hyperprolactinemia differ somewhat between the sexes. Women have oligomenorrhea or amenorrhea, galactorrhea and infertility. Amenorrhea is the principal presenting complaint in all cases. Among these patients, 95% of those with hyperprolactinemia have a prolactinoma(178). The tumors are usually not very large because hormonal symptoms appear earlier and are more conspicuous than in men. Men experience loss of sexual potency. In the absence of clear early warning symptoms, most present with mass effects, including hypopituitarism and chiasmal compression, and their tumors are usually large. Galactorrhea is much less common in men than in women(179)
. These manifestations suggest prolactinoma but are not specific to it. Only immunocytochemical analysis of tumor tissue provides a definitive diagnosis(180)
2. Persistently marked elevation of serum prolactin. Although serum prolactin may rise in several conditions listed above, levels in conditions other than prolactinoma are usually only moderately elevated, generally not exceeding 150 ng/ml. Persistent levels above 200 ng/ml are almost invariably due to prolactinoma. The larger the tumor, the greater the prolactin level. Modest elevations may be difficult to interpret and require other supporting evidence. If tumor size does not correlate with the prolactin level—for example, a large tumor with only a modest elevation—a prolactin-secreting adenoma is unlikely; compression of the pituitary stalk or hypothalamus is more likely. Failure of the mass to shrink with bromocriptine also argues against prolactinoma. This criterion is not invariably reliable, because some prolactinomas do not shrink during bromocriptine treatment.
3. Radiological investigation. High-resolution CT and MRI are now extremely useful for diagnosing pituitary tumors and perisellar lesions, even small tumors. Coronal CT sections show tumor size, shape and suprasellar or parasellar extension well. When CT demonstrates a pituitary tumor together with hyperprolactinemia above 200 ng/ml, the lesion is invariably a prolactinoma.
MRI is particularly suitable for large tumors extending beyond the sella. It shows their relationship to nearby brain structures and is therefore useful for surgery.
Plain skull radiographs are now rarely obtained because CT and MRI demonstrate tumors better. Pituitary adenomas may produce erosion, a double floor and ballooning of the sella turcica.
Carotid angiography is also no longer necessary except when an intracranial aneurysm extending into the sella is suspected and serum prolactin is only modestly elevated (below 150 ng/ml). This suggests a pseudoprolactinoma—a mass compressing the pituitary stalk, such as an aneurysm or craniopharyngioma—rather than a true prolactinoma.
Original printed pages 908–911
Treatment
Although prolactinoma is the most common pituitary tumor, its treatment remains controversial, because both medication and surgery give good results when appropriately selected. Current options include drug treatment, usually bromocriptine, surgery and radiotherapy, as this tumor is radiosensitive. Some patients do not yet require treatment. Important considerations include sex, age and tumor size: a microadenoma is smaller than 10 mm, whereas a macroadenoma is larger than 10 mm and may extend to compress adjacent structures.
As with other pituitary tumors, treatment aims to: i) preserve vision; ii) restore normal serum prolactin; iii) remove the tumor completely or prevent further growth; and iv) preserve normal pituitary function.
macroadenoma These tumors exceed 10 mm. A very large tumor extending to compress nearby structures, particularly the optic chiasm, requires immediate surgical removal to relieve chiasmal compression. Either a transfrontal or transsphenoidal approach may be used, depending on tumor size and extension. If all macroscopically visible tumor is removed but prolactin does not normalize, continue bromocriptine after surgery; radiotherapy is unnecessary. When a large tumor cannot be completely removed, postoperative radiotherapy should be given, possibly with bromocriptine to lower serum prolactin.
Women with a macroadenoma who wish to become pregnant should undergo surgery first, because without bromocriptine the tumor enlarges during pregnancy and may threaten vision(181,182,183). If prolactin normalizes after surgery and pregnancy occurs, bromocriptine is unnecessary. Persistent postoperative hyperprolactinemia should be treated with bromocriptine to permit conception and prevent regrowth during pregnancy. During this period, CT or MRI should be repeated periodically, because the tumor has an approximately 25–75% chance of regrowth within 5 years(184,185)
. If the tumor enlarges during pregnancy and threatens vision, one of three treatments may be used(186): i) bromocriptine to shrink the tumor and prevent further enlargement; ii) termination of pregnancy or premature delivery to stop tumor enlargement; or iii) tumor removal during pregnancy, with the attendant operative risks. On balancing these options, bromocriptine appears most appropriate, with surgery considered after delivery. Bromocriptine cannot eradicate the tumor, and growth resumes when treatment is stopped.
microadenoma These tumors are smaller than 10 mm and do not extend beyond the sella. Some physicians initially prescribe bromocriptine, reserving surgery for failure of medication. This approach seems questionable, because CT and MRI can now identify and locate small adenomas well. In experienced hands, transsphenoidal microsurgery has very low morbidity and mortality. Complete removal cures the disease while preserving pituitary function and avoids lifelong medication. Bromocriptine, in contrast, requires lifelong treatment, is expensive and cannot eradicate the tumor; it grows again when the drug is stopped. Reports also indicate that microadenomas treated with bromocriptine for more than 6–12 months before surgery have a lower surgical cure rate than tumors not treated beforehand(187, 188), because bromocriptine produces fibrosis within the tumor(189). Surgical removal of a microadenoma therefore appears preferable. If CT or MRI cannot clearly demonstrate the microadenoma, however, bromocriptine should be given to normalize prolactin, with clinical observation and periodic repeat CT to assess tumor changes.
A patient with a microadenoma who wishes to become pregnant but declines surgery should receive bromocriptine to reduce serum prolactin, allowing menstruation, ovulation and conception. During pregnancy, the risk that a microadenoma will enlarge enough to impair vision is low, and bromocriptine provides an additional means of controlling growth. Weiss M.H.(190) reported 35 patients who received bromocriptine during pregnancy, all of whom delivered healthy infants. Bromocriptine is therefore considered safe for the fetus.
Start bromocriptine at a low oral dose of 1.25 mg/day for 1 week. If there are no adverse effects, increase the daily dose by 1.25 mg each week until 7.5 mg/day is reached, divided into three doses of 2.5 mg. Once serum prolactin has normalized, continue this dose. Some patients require up to 30 mg/day; treatment must be individualized. At these doses, menstruation returns in 85% of treated women(191), and appreciable tumor shrinkage occurs within approximately 4–6 weeks. Stopping treatment leads to recurrent hyperprolactinemia and tumor regrowth(192)
. The tumor-shrinking effect of bromocriptine is useful as an adjunct to surgery. Give it for 3–4 weeks before surgery, then repeat CT. Once substantial shrinkage has occurred, the tumor can be removed more easily and completely.
Original printed page 911
Radiotherapy
Radiotherapy should supplement other treatments rather than serve as the initial treatment, particularly for microadenomas, which can be completely removed and cured without irradiation. It should be used for large tumors with mass effects that cannot be completely removed, or for recurrent tumors.
Original printed pages 911–913
B. GROWTH HORMONE-SECRETING ADENOMA
This tumor causes excessive growth hormone secretion by somatotrophs. If it occurs at a young age before epiphyseal plate closure, longitudinal bone growth produces extreme height, termed “gigantism.” If it occurs after adolescence, when the epiphyseal plates have closed, the body enlarges in breadth, producing the characteristic appearance of “acromegaly.” Growth hormone hypersecretion beginning before epiphyseal closure and persisting afterward produces “acromegalic gigantism.”
Both pituitary acromegaly and gigantism are uncommon and occur more often in men than in women. Bodily changes develop slowly, so patients generally seek medical advice only once acromegaly is conspicuous. Tumors may be small (less than 10 mm), or large enough to compress adjacent structures or destroy the sella turcica. The signs and symptoms of acromegaly can be divided into two groups:
1. Signs and symptoms caused by elevated circulating growth hormone, with changes in tissues, bones and organs that shorten life expectancy.
1.1 Abnormal soft-tissue and bone growth. Before epiphyseal closure, growth hormone accelerates longitudinal bone growth; the hands, arms and legs become abnormally long, and the patient is very tall (Figure 5.25). After epiphyseal closure, bones become wider and thicker throughout the body, most conspicuously in the hands, arms, legs and face. The hands and feet become large and thick, with stubby digits. Facial features include a protruding forehead, prominent brow ridges and cheekbones, a large nose, an enlarged thick mandible with prognathism and widely spaced teeth, and thick lips (Figure 5.26). Abnormal growth of vertebrae and articular cartilage can compress spinal nerves, causing back pain, limb numbness and weakness. Hand numbness is common, typically involving the thumb, index and middle fingers as part of carpal tunnel syndrome; some patients also have muscle weakness. These manifestations result from median nerve compression at the wrist. Arthritic pain results from bony overgrowth, irregular articular surfaces and thickening of periarticular tissues.
1.2 Skin changes. The skin becomes thick and coarse. Increased sweat and sebaceous gland activity produces hyperhidrosis, oily skin and often an unpleasant odor.
1.3 Enlargement of organs, including the heart, liver, spleen, kidneys, thyroid, tongue and salivary glands. In addition to cardiomegaly, patients may develop hypertension, coronary artery disease and heart failure. Some attribute this to myocardial abnormalities termed acromegalic cardiomyopathy(193,194)
1.4 Endocrine abnormalities include diabetes mellitus, glucose intolerance and reduced sexual potency. Some patients have galactorrhea and amenorrhea because growth hormone-secreting adenomas often secrete other hormones as well. The most important and commonly associated hormone is prolactin.
2. Local signs and symptoms caused by tumor expansion include retro-orbital headache due to displacement of the diaphragma sellae. Large tumors cause visual loss, as described earlier, and hypopituitarism through compression of other pituitary cell types.
Original printed pages 913–914
Diagnosis
Diagnosis depends on three types of abnormality:
1. Clinical signs and symptoms characteristic of acromegaly and gigantism, as described above. Advanced disease has a striking, recognizable appearance that is similar in all patients. In early disease, when bodily changes are subtle, radiological and endocrine investigations are particularly important.
2. Radiological investigation
2.1 Plain skull radiographs demonstrate the sellar changes described earlier, but these are not specific to a GH-secreting adenoma, so such radiographs are now rarely obtained. The skull is generally thicker than normal, with loss of the diploic space. Enlargement of the paranasal sinuses is consistently conspicuous, particularly the frontal sinus, which may become very large and impede a frontal surgical approach. The mandible is enlarged.
2.2 Hand and foot radiographs show mushroom-shaped distal phalanges. The joints may show osteoarthritic changes. Soft-tissue shadows are also markedly thickened, especially at the heel.
2.3 CT and MRI best demonstrate small tumors and extrasellar extension. MRI shows the relationship between the tumor, optic chiasm and blood vessels particularly well.
3. Assessment of abnormal growth hormone secretion, either by direct GH measurement or by measuring somatomedin C (SmC). In normal individuals, the upper limit of basal serum GH is 5 ng/ml(195). In acromegaly, GH exceeds this level. An important diagnostic test is suppression of GH secretion by hyperglycemia during an oral glucose tolerance test (OGTT). In normal individuals, 100 g of oral glucose suppresses GH below 5 ng/ml within 90–180 minutes. In acromegaly, GH is not suppressed and remains elevated(159). An additional test measures the GH response to thyrotropin releasing hormone (TRH). TRH has no effect on GH secretion in normal individuals but raises serum GH in acromegaly.
The principal hormonal diagnostic criteria for acromegaly are therefore: i) basal GH above 5 ng/ml; ii) failure of hyperglycemia to suppress GH; iii) elevated somatomedin C; and iv) a rise in GH after TRH.
Original printed pages 914–915
Treatment
Treatment of GH-secreting adenomas follows the same principles as treatment of other pituitary adenomas, but should begin early because acromegaly shortens life expectancy. Studies indicate that untreated patients over 40 years of age have a mortality rate up to 50% higher than people of the same age(239). Excess GH affects multiple systems, particularly the cardiovascular system, with hypertension, diabetes and organ enlargement. Changes in the limbs, face, joints and soft tissues cause persistent discomfort. Tumor growth may also threaten vision. Early treatment can prevent these harmful consequences. Treatment must be individualized, aiming to normalize GH, prevent the effects of hormone excess, remove the tumor to relieve optic chiasmal compression and preserve normal function of the remaining pituitary gland. Three forms of treatment are available:
1. Surgery Surgery offers the possibility of cure by rapidly lowering GH and improving clinical manifestations. It also immediately relieves tumor compression of surrounding structures. Success depends on tumor size, direction of extension and surgical expertise. Small tumors with only moderately elevated basal GH have better surgical outcomes(196,197). Outcomes are less favorable for large tumors with very high GH, which require additional radiotherapy or medication.
Original printed pages 915–916
Two surgical approaches are used
1.1 The transfrontal approach is suitable for a large tumor extending into the suprasellar region, compressing the optic chiasm, with a postfixed chiasm. Surgery in acromegaly is somewhat more difficult than in other conditions because the skull is very thick and the frontal sinus is large. Extending the craniotomy down to the orbital ridge opens the frontal sinus, creating a risk of CSF rhinorrhea or meningitis. Outcomes are less favorable than with other approaches because these patients usually have large tumors and high GH levels.
1.2 The transsphenoidal approach is suitable for small intrasellar tumors, with cure rates of up to 80% for microadenomas(198,199,200). It is now a widely favored approach because hormonal investigations, CT and MRI identify tumors while they are still small, and the enlarged sphenoid sinus facilitates access.
GH falls immediately after surgery. Soft-tissue signs and symptoms improve: the hands and feet gradually become smaller, excessive sweating and headache disappear, and paresthesia gradually improves. Changes in facial appearance and bony abnormalities are less conspicuous. Associated diabetes improves, sometimes eliminating the need for insulin or allowing a very small dose(200)
2. Drug treatment Drugs that lower GH include dopamine agonists. Several are available, but bromocriptine, an ergot derivative that reduces GH secretion, is currently the most widely used and effective(201,202). It can also shrink GH-secreting adenomas, particularly tumors that cosecrete prolactin, which shrink more conspicuously than tumors secreting GH alone(203). Approximately 95% of patients receiving bromocriptine improve clinically(204). It should not, however, be the initial treatment, because GH is then very high and large doses of 20–60 mg/day are required; some patients cannot tolerate the adverse effects. It is preferable as an adjunct to surgery or radiotherapy. Surgery lowers GH immediately, so if bromocriptine is needed for residual postoperative elevation, a low dose is sufficient.
3. Radiotherapy Several methods are available:
i) Conventional irradiation, approximately 4,000–5,000 rads.
ii) Proton beam or heavy-particle irradiation.
iii) Intrasellar implantation of radioisotopes, such as yttrium or Au (gold).
With any radiation technique, the response is delayed. GH begins to fall approximately 6 months to 2 years after treatment, and normalization may take about 10 years. If normal GH is defined as below 5 ng/ml, 69–75% of patients reach this level 10 years after treatment(205,206). Because of this delay and the risk of complications, including hypopituitarism, optic nerve injury and brain necrosis, radiotherapy should supplement other treatment. Examples include incomplete tumor removal with persistently elevated GH, or recurrence indicated by a gradual rise in GH and enlargement on repeat CT.
Original printed pages 916–917
Selection of treatment
Because the treatments for acromegaly described above have differing results, the physician must select the best method for each patient.
1. In a previously untreated patient whose CT shows an intrasellar tumor, complete removal by a transsphenoidal or transfrontal approach is the best treatment. It rapidly lowers GH and can cure the disease without additional treatment, but should be performed by an experienced surgeon.
2. A large tumor extending beyond the sella turcica should be removed through a transfrontal approach to relieve compression of nearby structures, especially the optic chiasm, and simultaneously lower GH. These patients are generally not cured, so postoperative irradiation should destroy the remaining tumor.
3. Patients in poor health who are unsuitable for general anesthesia and surgery should receive radiotherapy. Because a fall in GH may take years, bromocriptine should also be given.
Original printed pages 917–918
C. ACTH-SECRETING PITUITARY ADENOMA (Cushing’s disease)
This pituitary tumor secretes excessive adrenocorticotropic hormone (ACTH), causing hypercortisolism or Cushing’s syndrome. Cushing’s syndrome has several causes: an ACTH-secreting pituitary adenoma; an adrenocortical tumor; an ectopic ACTH-secreting neoplasm, such as oat-cell carcinoma of the lung, thymoma or pancreatic cancer; and treatment with ACTH or glucocorticoids. Cushing’s syndrome of pituitary origin is termed “Cushing’s disease.” It is the major cause, accounting for up to 80% of cases; the remainder are due to adrenocortical tumors and ectopic ACTH-secreting neoplasms(207). Nelson’s syndrome also results from excessive ACTH secretion by a pituitary adenoma, developing 1–16 years after bilateral adrenalectomy(208). It comprises progressive hyperpigmentation after adrenalectomy, elevated ACTH and sellar mass effects caused by tumor enlargement. In addition to the history of adrenalectomy and these manifestations, CT helps establish the presence of a pituitary adenoma.
Original printed pages 918–919
Signs and symptoms
Hypercortisolism produces similar manifestations regardless of its cause. In Cushing’s disease, signs and symptoms may be divided into three groups:
1. Manifestations of hypercortisolism These include:
1.1 Increased appetite and obesity, with fat accumulation on the trunk and face. The face becomes round, full and red (“moon face”), with acne and increased hair on the upper lip, chin and sideburn areas. Fat accumulates at the nape as a “buffalo hump” and increases in both supraclavicular regions.
1.2 Pink-purple striae on the abdomen, thighs and posterior shoulders. The skin is thin, bruises easily after minor trauma, and heals slowly.
1.3 Bone pain from osteoporosis, sometimes with easy fractures, kyphosis and associated back pain.
1.4 Muscle weakness and wasting, usually proximal myopathy. Patients have difficulty rising from a squatting position unaided and climbing stairs.
1.5 Emotional disturbances are common.
2. Manifestations of dysfunction of other hormones These include amenorrhea or oligomenorrhea, reduced sexual potency in men and often hirsutism in women.
3. Mass effects These result from tumor growth compressing adjacent structures, particularly the optic chiasm. In the author’s experience these tumors are usually small, so chiasmal compression is uncommon.
4. Other manifestations include hypertension due to salt retention together with increased plasma renin substrate caused by excessive glucocorticoids(209,210). Diabetes occurs in approximately 25%, and more than half of patients have abnormal glucose tolerance. Infections, particularly fungal infections, are also common.
Original printed pages 919–920
Diagnosis
Diagnosis is based on:
1. The signs and symptoms described above. Advanced disease can be recognized on sight because the features are conspicuous and similar in all patients.
2. Elevated cortisol and metabolite levels in blood or urine. Normal plasma cortisol follows a daily rhythm: it is high on waking in the morning, falls toward bedtime and reaches its lowest level during sleep. In Cushing’s syndrome, plasma cortisol remains high throughout the day.
Measurement of 24-hour urinary free cortisol is a very useful assessment of cortisol secretion because urinary free cortisol is directly proportional to cortisol production. Values above normal, particularly at least twice normal, indicate Cushing’s syndrome.
The best diagnostic method is the dexamethasone suppression test, of which several variants exist (see endocrinology textbooks). The principle is that dexamethasone, a glucocorticoid given at bedtime, suppresses ACTH secretion and lowers morning blood cortisol. Failure of plasma cortisol to fall below 5 micrograms/dl suggests Cushing’s syndrome.
3. Radiological investigation. CT or MRI of the sellar region should be obtained in axial, coronal and sagittal planes. ACTH-secreting pituitary adenomas are usually small and cannot be demonstrated in every patient. CT detects adenomas in 60%, while MRI detects them in 80(211). An adenoma may be hypodense, isodense or hyperdense relative to pituitary tissue. Most macroadenomas are clearly visible. Failure of CT to demonstrate a microadenoma does not exclude one. If sellar CT does not clearly show an adenoma, CT of the abdomen, including the adrenals and pancreas, and of the chest should be obtained to seek other causes of Cushing’s syndrome.
Original printed pages 920–922
Treatment
An ACTH-secreting pituitary adenoma requires prompt treatment because mortality may reach 50% within 5 years(212). Causes of death include infection, heart failure, myocardial infarction and cerebrovascular accidents. As with other adenomas, three treatments are available: surgery, medication and radiotherapy.
1. Surgery Surgery is the best initial treatment for both macroadenomas and microadenomas because it immediately resolves hypercortisolism while preserving other pituitary functions.
A microsurgical transfrontal approach is suitable for large tumors with suprasellar extension. Complete removal is impossible, so cure rates are lower than for microadenomas and recurrence rates are higher.
The microsurgical transsphenoidal approach is now widely used and gives excellent results for microadenomas in experienced specialist hands. If the microadenoma can be seen and completely removed without damaging the remaining gland, the patient is cured without losing other pituitary functions. Surgical cure rates for microadenomas range from 87–96%(213,214,215)
. Occasionally, no definite pituitary abnormality is visible during surgery. The surgeon has three options: i) total hypophysectomy; ii) medication and radiotherapy; or iii) adrenalectomy. Before hypophysectomy, investigations must establish that the cause lies in the pituitary gland, and the postoperative consequences must be clearly explained and accepted by the patient. This is suitable for adults who do not wish to have children. Hypophysectomy should not be performed in children or young people who still wish to have children; medication and radiotherapy should be used instead(207, 211)
. Bilateral adrenalectomy was formerly popular. I believe it should be the last resort after pituitary surgery, radiotherapy and medication have failed. It rapidly resolves hypercortisolism but requires lifelong glucocorticoid and mineralocorticoid replacement. Nelson’s syndrome may also develop later, necessitating subsequent pituitary surgery. The pituitary adenoma of Nelson’s syndrome grows rapidly like a carcinoma, invading the skull base and compressing the optic chiasm and other cranial nerves(159)
2. Drug treatment Because the manifestations of Cushing’s disease result from excessive ACTH and adrenal steroid secretion, medication aims to reduce pituitary ACTH secretion or inhibit adrenal steroid synthesis.
Cyproheptadine and bromocriptine reduce ACTH secretion. Cyproheptadine is a serotonin antagonist; at 24 mg/day it normalizes serum cortisol and ACTH and resolves symptoms in 50% of patients(216). Symptoms recur immediately when treatment stops. Common adverse effects include drowsiness, increased appetite and weight gain.
Drugs that inhibit adrenal cortisol synthesis by blocking the necessary enzymes include aminoglutethimide, metyrapone and mitotane (O,P-dichlorodiphenyl dichloroethane; O,P-DDD). Their usefulness is limited because a fall in serum cortisol increases ACTH secretion, overcoming the enzyme blockade.
Drug treatment of Cushing’s disease should accompany radiotherapy or be used when surgery and radiotherapy have failed. It is also useful before surgery, restoring abnormalities to normal and improving the patient’s fitness for the operation.
3. Radiotherapy Although surgery is the best treatment, radiotherapy is sometimes necessary, either initially or as an adjunct, for example after incomplete removal or when the patient’s health precludes surgery. Conventional radiation or heavy-particle irradiation may be used. Both have similar complications, including hypopituitarism and cranial nerve palsies, and require 6 months to 1 year before a response becomes apparent. Reports of conventional radiation indicate cure rates as high as 80% in children(217,218), but lower rates of 25–50% in adults.
All patients with Cushing’s disease should therefore initially undergo pituitary microsurgery by an experienced surgeon, unless surgery is contraindicated, in which case radiotherapy or medication is used. Severe hypercortisolism should first be treated medically until the patient improves, followed by surgery. Radiotherapy and medication should serve as adjuncts to surgery.
Original printed pages 922–924
METASTATIC BRAIN TUMORS
These tumors arise in brain tissue through spread from cancers in other organs. They are common brain tumors and an important cause of disability and death. Autopsies of patients who die of cancer reveal brain metastases in up to 25%; two-thirds of these patients had neurological symptoms during life(219,220,221)
. Tumor cells reach the brain through arteries and lodge at the ends of small arterial vessels. Most metastases therefore lie near the surface, in the subcortical region at the gray–white matter junction; some are visible on the brain surface. Their frequency in the cerebrum, cerebellum and brainstem varies with regional blood flow and tissue volume. Normally approximately 60% of blood flow passes through the internal carotid arteries, while the vertebrobasilar arteries carry 40%. Metastases are consequently more common in the cerebrum than the cerebellum and least common in the brainstem. In the cerebral hemispheres, they often occur near the central fissure in the middle cerebral artery territory. Another route is direct extension from the skull base into the base of the brain, commonly from nasopharyngeal carcinoma.
Lesions may be solitary or multiple, but approximately two-thirds of patients have multiple tumors, an important diagnostic feature. Before CT, angiography and radioisotope scanning had difficulty demonstrating multiple lesions, especially small ones, so apparently solitary tumors were reported more often than multiple tumors. CT and MRI now readily demonstrate multiple lesions, even when small, and show tumors of varying sizes. The proportion of patients classified as having a solitary tumor is therefore lower.
Lung cancer is generally accepted as the most common source of brain metastases, followed by breast, colon, kidney and uterine cancers, in that order. Melanoma has a marked tendency to metastasize to the brain, but because this skin tumor is uncommon, cerebral melanoma metastases are seen less frequently. When present, they are usually multiple and prone to intratumoral hemorrhage. Another group of patients presents with a metastatic brain tumor whose primary site is unknown.
Both solid and cystic metastases are well circumscribed and consistently accompanied by marked surrounding brain edema, regardless of tumor type. The degree of edema does not correlate with tumor size: a small tumor may produce extensive edema, an important characteristic. Possible contributing factors include tumor vascularity, vascular permeability, metabolism and fluid production by tumor cells(222). Peritumoral edema facilitates surgical removal because the soft edematous brain separates clearly from the firmer tumor margin. However, edema also has harmful effects, causing relatively rapid loss of function in the affected region and raising intracranial pressure.
Original printed pages 924–930
Symptoms and Signs
The neurological symptoms and signs of metastatic brain tumors cannot be clearly distinguished from those of other intracranial expanding lesions, because their manifestations are similar. Common important features include headache, papilledema, vomiting, focal seizures, monoparesis or hemiparesis, and a gradually deteriorating level of consciousness.
Patients presenting with these manifestations may be divided into two groups according to the course of their symptoms.
1. Gradual onset. Symptoms begin with headache, often worse in the morning, which subsequently becomes more severe as cerebral edema increases. Other manifestations of raised intracranial pressure follow, including vomiting, papilledema, and gradually deteriorating consciousness. Marked papilledema does not necessarily indicate a large tumor: a small tumor with extensive surrounding edema may also cause severe papilledema. In the author's experience, marked papilledema is often associated with multiple metastatic lesions.
Monoparesis or hemiparesis is another common manifestation, because most tumors arise in regions supplied by the middle cerebral artery. Speech impairment may occur when the tumor is in the dominant hemisphere. These symptoms gradually worsen as edema compresses the surrounding brain, but gradually improve with dexamethasone treatment or complete surgical removal of the tumor.
Example of a progressive neurological deficit A 75-year-old male merchant developed headache 3 weeks before admission. The headache progressively intensified. Two weeks before admission, he began giving inappropriate answers to questions and repeatedly miscalculating change. He developed blurred vision in both eyes and vomiting. Subsequently, he became unable to speak and developed progressively worsening weakness of the right arm and leg. On examination, he was conscious but unable to speak. Fundoscopy showed papilledema, and he had right hemiplegia and right hemianopia. CT demonstrated a tumor in the left posterior parieto-occipital region, with extensive edema involving all lobes of the left hemisphere (Figure 7.151). Investigation did not identify a primary cancer elsewhere. He received dexamethasone, and the tumor was completely removed. Histological examination showed adenocarcinoma. After surgery, the headache resolved and he was able to speak and walk normally.
This example illustrates relatively rapid deterioration over approximately 2 weeks. Most of the neurological deficits resulted from edema compressing the surrounding brain, because the tumor itself was not situated in the speech or motor areas. Once the tumor causing the edema had been removed and dexamethasone had been given to reduce the swelling, neurological function returned to normal.
Figure 7.151. CT showing a metastatic brain tumor in the posterior part of the left parietal lobe. Note the extensive hypodense area of cerebral edema.
Metastatic brain tumors in certain locations that cause monoplegia, particularly of the leg, may be mistaken for nerve root compression, as illustrated below.
Example of left foot drop A 45-year-old man who had smoked heavily since youth presented with weakness of the left leg for 1 week. His toes dragged along the ground when walking, requiring him to lift the leg high to avoid tripping, and his foot slapped the ground when placed down. He had neither numbness in the leg nor low back pain. Examination showed distal weakness of the left leg, a foot-drop gait, and an absent left ankle jerk. The first examining physician diagnosed lumbar nerve root compression and requested lumbosacral spine radiographs and a lumbar myelogram, both of which were normal. A neurosurgical consultation elicited a history of occasional headache and progressively worsening leg weakness without numbness. Fundoscopy showed engorgement of the central retinal vein. Together with the absence of dermatomal sensory loss in the leg, these findings suggested a lesion in the cerebral motor leg area. CT demonstrated a tumor with surrounding edema in the medial part of the posterior frontal lobe (Figure 7.152 A). A chest radiograph revealed lung cancer, making a brain metastasis from the lung highly likely. The brain tumor was completely removed (Figure 7.152 B), and leg strength improved after surgery. The patient subsequently underwent removal of the lung tumor but died 6 months later from multiple brain metastases. This example shows that a rapidly growing tumor with extensive edema in the motor leg area, such as a metastatic brain tumor, may cause flaccidity of the leg and foot and be mistaken for a peripheral nerve disorder in the lumbar region. A thorough neurological history and examination should prevent such a diagnostic error.
For a cerebellar metastasis, the principal symptoms are headache and unsteadiness toward the side of the tumor. The headache often increases rapidly because these tumors cause hydrocephalus more readily than tumors elsewhere. Examination reveals papilledema, nystagmus, gait ataxia, and incoordination.
Figure 7.152. A small metastatic brain tumor in the motor leg area causing foot drop. A. CT showing hypodense edema surrounding the tumor (small arrow).Figure 7.152 B. Operative view showing the removed tumor placed on the brain surface.
2. Acute onset. Common manifestations include the following:
2.1 Seizures. These are usually focal and may spread to other parts of the body, a pattern termed marching or Jacksonian epilepsy. Some patients develop generalized seizures with loss of consciousness. After a seizure, weakness may affect the limbs involved in the seizure (Todd's paralysis or postictal paralysis). Seizures are common in patients with multiple brain metastases.
2.2 Stroke-like symptoms. Hemiplegia develops suddenly, with or without loss of consciousness, although drowsiness is common. This presentation generally results from hemorrhage into the tumor, particularly in choriocarcinoma and malignant melanoma. Subarachnoid hemorrhage may also occur. These patients often deteriorate rapidly: the substantial edema already associated with such tumors is compounded by bleeding, causing a rapid rise in intracranial pressure. Delayed diagnosis and treatment often result in death, as illustrated below.
Example of hemorrhage into a brain metastasis from choriocarcinoma A 28-year-old woman developed headache and sudden weakness of the left arm and leg 3 hours before admission. On arrival, she had a focal seizure of the left arm that spread to the face and left leg, followed by a generalized seizure and loss of consciousness. After the seizure, she had flaccid left hemiplegia and did not answer questions. Right carotid angiography was performed because a ruptured arteriovenous malformation was suspected in view of her young age. Instead, it demonstrated a tumor in the right posterior frontal region with marked edema and midline shift. Craniotomy revealed a hemorrhagic tumor on the cortical surface in the motor area, surrounded by subarachnoid hemorrhage. The brain was markedly swollen and bulged beyond the skull margins (Figure 7.153 A). The tumor was completely dissected out (Figure 7.153 B). Histological examination showed hemorrhagic choriocarcinoma. After surgery, she remained hemiplegic and unconscious and died 3 days later from cerebral edema and raised intracranial pressure.
Figure 7.153. A metastatic brain tumor presenting like a hemorrhagic stroke. A. Operative view showing hemorrhage into a tumor on the cortical surface. Note the associated cerebral edema and subarachnoid hemorrhage.Figure 7.153 B. The completely excised tumor.
This example illustrates an acute presentation of a metastatic brain tumor with both seizures and features resembling a hemorrhagic stroke. Deterioration is relatively rapid, neurological deficits are often permanent, and mortality is high because of cerebral edema.
Original printed pages 930–931
Diagnosis
Symptoms and signs alone cannot reliably distinguish the pathology of an intracranial tumor, because different expanding lesions produce similar manifestations. Imaging is therefore required for differentiation. Nevertheless, when the course is characterized by i) relatively rapid neurological deterioration, ii) progressively severe headache, and iii) deterioration in consciousness over a short period—all three resulting from marked cerebral edema—metastatic brain tumors should be considered first and distinguished from glioblastoma multiforme.
CT and MRI are the best investigations, clearly demonstrating multiple tumors and their surrounding edema. On contrast-enhanced CT, the tumor is hyperdense, with an extensive hypodense area of surrounding edema. Central hypodensity may be present because of central tumor necrosis. Important diagnostic features of brain metastases are i) multiple lesions of different sizes and ii) extensive surrounding hypodense edema, even around a small tumor. However, a brain metastasis may be solitary and sometimes difficult to distinguish from glioblastoma multiforme or a brain abscess. Finding a primary cancer elsewhere aids the diagnosis. If cancer is found in the lung, breast, or another organ, an intracranial mass is more likely to be metastatic than another type of lesion.
Besides showing the number of lesions, CT or MRI demonstrates hydrocephalus and various mass effects. These findings help determine the best method of treatment for the patient and are also useful in monitoring the response to treatment.
Cerebral angiography can show the tumor's location, but is less effective than CT at demonstrating multiple lesions and may fail to reveal small tumors. It is now performed infrequently. Findings used to diagnose a metastatic brain tumor include i) a single large feeding artery, in which an embolus of malignant cells has lodged and developed into a tumor, and ii) tumor staining and early venous drainage.
Original printed page 931
Treatment
In general, treatment of metastatic brain tumors is regarded as palliative, intended to relieve symptoms and prolong life for a time. Ultimately, patients die from cancer spreading to other organs. Available treatments include surgery, corticosteroids, radiotherapy, and chemotherapy. One method may be used alone or several may be combined, according to the individual case. Important factors in choosing treatment to obtain the best outcome include:
1. The number of tumors: whether the lesion is solitary or multiple.
2. Whether the tumor is situated where surgery would be hazardous or cause loss of brain function.
3. The extent of neurological impairment before treatment.
4. The patient's age and medical illnesses.
5. The severity of the primary cancer and the extent of spread to other organs.
6. The type of cancer, including whether it is radiosensitive or radioresistant.
7. The interval between treatment of the primary cancer and development of brain metastasis.
Original printed pages 931–932
Surgical Treatment
In appropriately selected patients, surgery offers several benefits:
1. It immediately relieves compression of the brain by a large tumor, which may cause acute deterioration through raised intracranial pressure and cerebral herniation.
2. It removes the cause of cerebral edema, allowing the swelling to subside rapidly and avoiding prolonged corticosteroid use.
3. It establishes the tumor type, guiding subsequent additional treatment.
4. Complete removal of the tumor avoids the potential for extensive radiation damage to the brain.
Original printed pages 932–933
Indications for Surgery
After considering the factors and benefits discussed above, the following criteria may be used to select patients suitable for surgery.
1. A solitary brain metastasis in a location where surgery is unlikely to cause further neurological impairment or readily endanger life, and where relieving compression by the tumor and edema would improve neurological symptoms. Even a solitary tumor, however, may be difficult to locate if it is small and not visible on the cortical surface; attempted removal may sometimes increase disability. In one of the author's cases, CT showed a small solitary metastasis in the medial posterior frontal lobe, causing only slight leg weakness. At craniotomy the tumor could not be found, and the operation was abandoned. The leg weakness increased afterward, indicating additional neurological impairment caused by the operation. This example illustrates the difficulty of locating a small subcortical tumor. The leg weakness was caused by edema. The author therefore considered that treatment should begin with dexamethasone to reduce the edema, followed by waiting for the tumor to enlarge enough to become readily visible at the cortical surface, so that removal would be more reliable. CT or MRI performed with markers attached to the scalp to indicate the tumor's position is another method currently available to assist the surgeon.
In some patients with more than one lesion, tumors situated close together can be removed through a single craniotomy without increasing neurological impairment. In such cases, the tumors should be removed together.
2. When a patient has a solitary brain tumor and the primary site of cancer is unknown, the tumor type cannot be determined. Complete removal for histological diagnosis should therefore be performed, simultaneously providing treatment. If the tumor lies in a critical or deep location, such as the thalamus, stereotactic or CT-guided biopsy may be used.(223)
A solitary brain tumor may not be metastatic. Every effort should therefore be made to establish its type, because treatment differs according to pathology. Identifying the type of tumor in the brain also facilitates the search for the primary cancer.
3. A large brain tumor may cause mass effect, rapidly rising intracranial pressure, and progressive deterioration in consciousness. Radiotherapy or dexamethasone will not act quickly enough. Surgical removal should be performed to relieve mass effect and raised intracranial pressure immediately, allowing the patient to recover.
Some patients deteriorate acutely during radiotherapy, with CT showing increased edema and midline shift. Complete surgical removal of the tumor is necessary in such cases for the patient to recover.
4. When histological examination of cancer elsewhere in the body establishes that it is radioresistant, surgical removal is the only means of eliminating the brain tumor.
Original printed pages 933–935
Contraindications to Surgery
The purpose of removing a metastatic brain tumor is to improve symptoms and reduce suffering for a period of time. Several factors, however, may prevent surgery from producing the expected improvement, and in some patients it may cause further deterioration. Surgery is therefore contraindicated in the following circumstances.
1. Multiple brain tumors of varying sizes in several lobes. In fact, the number of tumors visible on CT may underestimate the true number, because smaller lesions may remain undetectable. Surgery therefore cannot remove them all. Even after a large lesion has been removed, symptoms may recur within a few days. These patients should receive another form of treatment, such as radiotherapy.
2. A metastasis in a deep location, such as the thalamus (Figure 7.154), basal ganglia, or brain stem. Surgery causes further neurological impairment and carries a high mortality rate.
3. Patients with systemic metastases, for example in the liver, lungs, bone marrow, spine, and brain, together with impaired brain function, have a very short life expectancy. Surgery or any other form of treatment is inappropriate because the cancer cannot be arrested. The physician's role is to improve comfort and relieve suffering at the end of life.
Figure 7.154. CT showing metastatic tumors in the thalamus and basal ganglia on both sides.
Original printed pages 935–937
Operative Technique for Metastatic Brain Tumors
Cancer impairs organ function both at its primary site and at other sites to which it spreads. Before surgery, a comprehensive physical examination, laboratory investigations, radiographs, and assessment of organ function are therefore required to establish the extent of cancer, since these factors are important causes of death outside the brain. For example, in a patient with a brain metastasis from lung cancer and no other metastases, if pulmonary function remains good and the lung cancer is resectable, the brain metastasis should be removed first, followed by removal of the lung tumor within 2–3 weeks. If pulmonary function is poor, anesthesia is likely to be hazardous, and the lung tumor cannot be removed, another form of treatment should be used.
Because a metastatic brain tumor may produce extensive edema even when small, dexamethasone should be given for 2–3 days before surgery to reduce swelling. This helps prevent brain herniation through the dural opening and facilitates access to the tumor.
Mannitol may be necessary if the patient deteriorates acutely before surgery, followed by urgent removal of the causative tumor.
The operative principles do not differ from those for other brain tumors. Most metastases are subcortical, with only a few visible on the cortical surface. Subcortical lesions may be difficult to reach because a small tumor can be accompanied by marked swelling. The cortical opening may therefore miss the tumor, and attempts to locate it may cause further neurological impairment. To avoid additional brain injury, the precise location should be established before surgery using coronal MRI or CT with scalp markers. Ordinary axial CT may not localize the lesion precisely. Previously, angiography could also localize small tumors by comparing cortical veins and arteries seen on the angiogram with those visible on the cerebral cortex during surgery. Intraoperative ultrasound(224) is another method of locating the tumor. Accurate localization by these methods reduces both operating time and functional loss by limiting brain injury. In some cases, tumors can be removed from the dominant hemisphere near the speech and motor areas without additional impairment; many patients improve.
In the author's experience, complete removal of the tumor as a whole prevents recurrence at the same site or makes it very uncommon. The surgeon should therefore aim for complete removal. The outcome of leaving residual tumor in the hope that radiotherapy will control it remains uncertain. Another important consideration is that partial removal or biopsy alone often leads to postoperative intratumoral hemorrhage and deterioration. The feasibility of complete removal, however, depends on the tumor's size, location, and characteristics.
For a subcortical tumor, the craniotomy should be centered where the lesion lies closest to the cortical surface, as determined by MRI or CT, preferably with preoperative markers. After the dura is opened, a superficial lesion may be indicated by pale, thinned cortex; a deeper lesion produces no visible cortical change. A Cushing cannula is passed through the cortex to identify the tumor's precise location. The tumor feels more springy than the edematous brain. Withdrawal of the cannula after entering the tumor often releases bright red blood, usually indicating penetration of its vascular wall. If the cortex is thin, considered nonfunctional, and outside the motor and speech areas, the thinned portion may be excised to expose the tumor wall widely. This facilitates removal of the whole tumor without excessive cortical retraction, which can cause postoperative edema. A fine suction tip is used to aspirate the edematous brain around the tumor wall, and cotton patties are used to separate the brain from the tumor progressively at greater depth. Separation is generally easy because the edematous brain is soft, ultimately allowing removal of the entire tumor.
For some deep tumors, there is no clearly visible cortical change. The same approach is used, but if the tumor proves large once its wall is reached, en bloc removal should not be attempted because it would cause extensive brain injury. An ultrasonic aspirator should be used to remove the tumor internally, leaving a thin wall. Folding this wall toward the center permits its separation from the surrounding edematous brain. The operative field should then be thoroughly irrigated. Some large tumors have central necrosis: opening the wall releases cloudy white-yellow fluid resembling the pus of a brain abscess, but Gram staining shows neither bacteria nor polymorphonuclear cells. The entire wall must also be removed in these cases, using the same method.
A transcortical incision should run along the middle and length of a gyrus. In critical regions, the incision should be as small as possible, and deeper dissection should proceed carefully, with the presumed direction parallel to important fiber tracts. An incision across a gyrus should be avoided because it may damage blood vessels and cause extensive brain injury.
For a tumor visible on the cortical surface, the small vessels and adjacent brain around the exposed tumor are coagulated and divided. The tumor is then dissected free from the surrounding brain as described above. If it adheres to the dura, the involved dura must be excised around the attachment. After complete tumor removal, the dura is repaired with fascia or pericranium.
Original printed pages 937–938
Results of Surgery
Results are currently good for a solitary metastatic brain tumor in a noncritical location. Most can be completely removed without increasing disability, while the patient's general condition remains good. Sound technique, together with the operating microscope, ultrasonic aspirator, and CT or MRI localization, increases the likelihood of complete removal. Recurrence at the operative site is therefore uncommon, and survival is prolonged. When the only metastasis is a solitary brain lesion, with no spread to other organs, most patients survive approximately 1 year. If the cancer spreads to other organs and to new sites in the brain, survival is only 3–5 months.
Original page 938
Medical Treatment
corticosteroids are very useful in metastatic brain tumors because they effectively reduce tumor-related cerebral edema. Dexamethasone is given at a dose of 10 mg intravenously, followed by 5 mg intravenously every 6 hours. Headache, level of consciousness, and hemiparesis improve within 2–3 days. Surgery is then easier because intracranial pressure has decreased. Corticosteroids are also useful for reducing postoperative cerebral edema and edema during radiotherapy. Very high doses of corticosteroids may themselves cause seizures.(225)
anticonvulsants are necessary because these tumors are usually subcortical and sometimes involve the cortical surface, making seizures likely. Multiple tumors increase this likelihood considerably. The drugs used are Dilantin 100 mg three times daily after meals together with phenobarbital 30 mg three times daily after meals. Higher doses may be required when corticosteroids are given. Blood anticonvulsant levels must be measured after tumor removal while steroids are being tapered; otherwise, Dilantin intoxication may occur.(222)
chemotherapy has not produced satisfactory results in the treatment of metastatic brain tumors. This lack of effectiveness is attributed to the drugs' inability to penetrate the blood–brain barrier.
Original pages 938–940
Radiotherapy
This is another form of palliative treatment and is suitable in the following circumstances.
1. Radiosensitive metastatic brain tumors, such as lymphoma, germ cell tumors, and oat cell carcinoma of the lung.
2. A solitary tumor that cannot be completely removed surgically and is highly or moderately radiosensitive should be irradiated in the hope of destroying the residual tumor.
Whether radiotherapy should be given after complete removal of a solitary tumor remains controversial. Those who favor radiotherapy argue that fragments of tumor may remain at the operative site and that small tumors elsewhere may not yet be visible on CT. They also argue that radiotherapy prolongs survival. Those opposed believe that the tumor has been removed as an intact mass and that there may be no metastases elsewhere in the brain. They therefore regard irradiation as causing brain damage without benefit and potentially making the patient feel unwell. The author bases the decision on the patient's symptoms and CT findings. After complete removal of a solitary tumor, serial CT examinations are performed. If no new brain metastasis is found, radiotherapy is withheld. During this period, the patient feels better than during a course of radiotherapy. If CT subsequently reveals a new solitary brain metastasis in a location where removal would not impair brain function, the patient is offered a choice between another operation, as before, and radiotherapy, provided that the previous histological findings indicate moderate radiosensitivity. The rationale and benefits of a second operation are the same as for the first: immediate reduction of intracranial pressure and mass effect, and cessation of cerebral edema. In the author's opinion, repeat surgery is appropriate because operative mortality in the hands of an experienced surgeon is now very low. If the patient declines surgery, radiotherapy is used. If CT after the first operation reveals multiple tumors elsewhere, radiotherapy is given without further surgery.
If, after the first operation, the primary cancer and disease at other metastatic sites are advanced and the patient is expected to survive no longer than 2–3 months, radiotherapy should not be given because it does not help the patient.
3. Surgery is considered contraindicated when multiple brain metastases are present; radiotherapy should therefore be given.
4. Surgical removal of deeply situated tumors, such as those in the thalamus or basal ganglia, is also considered contraindicated. If needle biopsy shows a radiosensitive metastatic brain tumor, radiotherapy is required.
5. Radiotherapy should be used when the patient's physical condition is unsuitable for anesthesia and surgery. However, radiotherapy should not be given if the cancer is in its terminal stage.
Original page 940
Results of Radiotherapy
As already stated, radiotherapy is only a palliative measure to prolong life. Patients with radiosensitive tumors survive longer than those with other tumors, sometimes for more than 1 year. In general, patients receiving radiotherapy survive approximately 3–9 months and die from widespread systemic cancer or new brain metastases. It is accepted that radiotherapy after removal of a solitary metastatic brain tumor prolongs survival.
Possible Complications Following Radiotherapy include hemorrhage within the tumor and cerebral edema. Both may cause clinical deterioration or brain herniation. Intratumoral hemorrhage requires urgent tumor removal for the patient's condition to improve. Radiotherapy invariably produces accompanying cerebral edema, so dexamethasone must be given each time. In some patients, however, edema develops rapidly and is so severe that dexamethasone cannot control it. Tumor removal is then required to eliminate the cause of the edema before the patient's condition can improve.
Another complication, occurring approximately 2 years or more after irradiation, is brain necrosis or leukoencephalopathy.(226) This is seldom observed because most patients have already died of their cancer.
Original pages 940–941
GLOMUS JUGULARE TUMOR
A glomus jugulare tumor arises from a cluster of cells in the outer wall (adventitia) of the jugular bulb, called the glomus jugulare.(227) These cells resemble those of the carotid body and chemoreceptors elsewhere. They also occur at several sites in the petrous bone, including beneath the mucosa of the medial wall of the middle ear, along the tympanic nerve, and in the submucosa of the promontory.(228)
A glomus jugulare tumor spreads locally. While it is still small, it may be seen in the middle ear. Otoscopy reveals a reddish-gray mass bulging the tympanic membrane. Alternatively, the tumor may lie in the jugular foramen and extend into the lumen of the jugular bulb and dural sinuses without initially destroying the jugular foramen. As it enlarges, it destroys the jugular foramen and the wall separating it from the middle ear, then spreads into the mastoid and petrous portions of the temporal bone. Eventually, the tumor enters the posterior fossa at the medial margin of the jugular foramen or the cerebellopontine angle, sometimes appearing at several nearby sites,(229) depending on the direction of its destructive expansion. Glomus jugulare tumors extend into the posterior fossa by two distinct routes,(230) a distinction important in surgery. The more common route involves bone destruction followed by displacement of the dura into the posterior fossa. The other is herniation of the tumor through the dura at the jugular foramen. Most of the tumor is therefore extradural. During surgery, every effort must be made to preserve the dura to prevent CSF otorrhea. When the tumor extends intradurally, surgery carries a greater risk of CSF otorrhea.(231) Tumor extension within the petrous bone impairs cranial nerve function to varying degrees depending on its location, involving cranial nerves IX, X, XI, VII, VIII, and V or XII. The tumor may also extend into the neck anterior to the mastoid or into the pterygoid fossa. These tumors grow very slowly, but complete removal is difficult because of their inaccessible location.
Glomus jugulare tumors occur most often between 40 and 50 years of age and are more common in women than in men.
Original pages 941–942
Symptoms and Signs
Because the tumor may arise in the middle ear or the jugular foramen, its symptoms and signs can be divided into two groups.
1. Otological symptoms include pulsatile tinnitus in the ear on the side of the tumor, owing to its abundant blood supply. Ear pain is another presenting symptom. Eventually, conductive hearing loss develops.(232–234) Some patients have bleeding from the ear. Otoscopy reveals a reddish-gray mass bulging the tympanic membrane. Biopsy of this tumor may cause severe hemorrhage and can be dangerous.
2. Neurological symptoms usually result from cranial nerve compression. Extension into the posterior fossa produces symptoms of cerebellar and brainstem compression. Hydrocephalus and raised intracranial pressure develop later.
A tumor arising in the jugular foramen produces jugular foramen syndrome, characterized chiefly by loss of function of cranial nerves IX, X, and XI. The patient has hoarseness, choking on swallowing, and wasting and weakness of the sternocleidomastoid and trapezius muscles. Additional cranial nerves that may be affected are VII, VIII, V, and XII, depending on the direction of tumor extension. Destruction of nerves VII and VIII causes lower motor neuron facial palsy involving the entire side of the face and sensorineural hearing loss. Cranial nerve deficits do not imply that a large tumor mass is present in the posterior fossa; they result from tumor compression of the nerves along their extradural course through the skull foramina.
Tumor extension into the posterior fossa causes an unsteady gait, nystagmus, hemiparesis, and papilledema associated with raised intracranial pressure.
Original pages 942–943
Diagnosis
Diagnosis is based on the otological and neurological symptoms and signs described above, together with radiological changes.
Skull radiographs show enlargement of the jugular foramen and destruction of the inferomedial portion of the petrous bone (Figure 7.156)
CT and MRI are currently the best examinations for demonstrating changes in the jugular foramen and petrous bone. They also show the tumor within the foramen and its extension into the posterior fossa or the neck.
ANGIOGRAPHY is important and must be performed before surgery because these tumors are highly vascular. Four-vessel angiography combined with digital subtraction clearly demonstrates tumor vascularity and feeding vessels. The principal supply is the ascending pharyngeal artery, a branch of the external carotid artery, with collateral anastomoses to the vertebral artery (Figure 7.157). Additional supply may arise from the intrabony portion of the internal carotid artery or the meningohypophyseal trunk. Angiography is also useful for tumor embolization(235) to reduce the blood supply, making surgery easier and reducing blood loss.
Imaging should include the transverse sinus and internal jugular vein, with digital subtraction to assess tumor extension into the veins and occlusion of the sinus or vein. This information helps determine whether the sinus or vein can be ligated and divided during surgery, and at what level.
Original pages 943–944
Treatment
There are three treatment methods: surgery, radiotherapy, and embolization. Surgery is considered the best treatment because complete removal can cure the patient. Unfortunately, this location makes surgical access difficult and places several cranial nerves at risk, potentially causing postoperative disabilities such as dysphagia, choking, hoarseness, and facial palsy. Surgery also entails substantial blood loss because the tumor is highly vascular, and postoperative CSF otorrhea may occur. Radiotherapy and embolization provide symptomatic relief only and are used in conjunction with surgery.
embolization Selective embolization before surgery is very useful in reducing operative blood loss and producing tumor necrosis.(236,237) It is suitable for large tumors supplied by large vessels that can be selectively embolized. Embolization must be performed as close to the tumor as possible, selecting only the vessels that supply it. Vessels anastomosing with intracranial vessels—the vertebral and internal carotid arteries—should not be embolized because cerebral ischemic complications may occur. These vessels should instead be coagulated and divided surgically. Even after embolization, bleeding may still occur from areas supplied by other vessels. The surgeon should therefore always identify, coagulate, and divide feeding vessels before cutting into the tumor.
It is recognized that embolization of tumors in the posterior fossa may cause not only partial tumor infarction and swelling but also infarction of the brainstem and cerebellum. An infarcted, swollen tumor may compress vital centers and cause death. Before embolization, the angiogram must therefore be examined carefully to determine which vessels should and should not be embolized.
Original page 944
Radiotherapy
Opinions about radiotherapy remain divided: some consider it ineffective because of radioresistance, whereas others consider it beneficial. Radiotherapy has been used as an adjunct both before and after surgery. Cole(238) reported treating 20 patients with glomus jugulare tumors using 4,000–5,000 rads and found that the tumors remained unchanged for several years. Radiotherapy is therefore suitable for elderly patients and those with medical conditions that make surgery unsuitable. It is also used for residual tumor after surgery.
Original page 944
Surgical Treatment
With the surgical techniques and instruments now available, surgery is the best treatment. Complete tumor removal can cure the patient. Several surgical approaches are available, depending on the tumor's location. Some cases require cooperation between a neurosurgeon and an otolaryngologist.
Original pages 944–945
Surgical Approaches
1) The mastoidectomy approach is suitable for tumors confined to the ear that have not extended elsewhere. The operation is performed by an otolaryngologist.
2) Suboccipital craniectomy is suitable for tumors extending into the posterior fossa at the cerebellopontine angle and causing compression of the brainstem and cerebellar hemisphere, with hydrocephalus. The aim is to relieve compression of the brain and cranial nerves. However, this approach cannot achieve complete removal because the tumor originates extradurally and extends into the posterior fossa. Its marked vascularity also causes substantial operative bleeding, making safe removal without injury to brain tissue, cranial nerves, or vessels difficult. Results are therefore less satisfactory, and residual tumor must be left in the petrous bone, internal jugular vein, and below the jugular foramen. Pursuing tumor in the jugular foramen from the posterior fossa often further impairs cranial nerves IX, X, and XI.
3) Combined craniectomy and mastoidectomy is a useful approach that provides access to both extracranial and intracranial tumor. It also permits division of branches of the ascending pharyngeal artery, vertebral artery, and other branches of the external carotid artery, substantially reducing tumor blood supply and making removal easier. This approach requires cooperation between a neurosurgeon and an otolaryngologist.
Original pages 945–949
Operative Technique
Position the patient on the side with the tumor uppermost and the head slightly elevated. Before positioning, insert a central venous catheter with its tip in the right atrium so that air can be aspirated if air embolism occurs. Make a question-mark incision starting above the ear, curving posteriorly and downward through the midpoint between the midline and mastoid process, then continuing into the neck anterior to the anterior border of the sternocleidomastoid muscle. This permits exposure, ligation, and division of the external carotid and ascending pharyngeal arteries. Detach the temporalis and sternocleidomastoid muscles from the temporal bone, mastoid process, arch of the atlas, and occipital bone to expose the vertebral artery and its tumor-feeding branches. Ligate and divide these branches. Next, perform a suboccipital craniectomy to expose the transverse sinus, extending above it so that the upper margin reaches the level of the posterior portion of the middle cranial fossa floor. Extend the inferior margin of the suboccipital craniectomy almost to the foramen magnum, or anterior to the arch of the atlas and vertebral artery. Laterally, extend to the mastoid process. Removing bone inferiorly along the sigmoid and superior petrosal sinuses exposes more of the dura of the temporal and posterior fossae. Removing the petrous bone around the jugular foramen reveals the vascular tumor. At this stage, if the tumor extends into the middle ear, an ENT surgeon should assist. The following case illustrates the operative method and complications.
Case example: A 47-year-old woman presented with a 5-year history of a blocked sensation and loss of hearing in the left ear, together with dizziness. A tumor had been found in the left ear and surgery recommended, but she declined. She subsequently developed progressively worsening unsteadiness and facial asymmetry, hoarseness, and occasional choking on food. On this examination, the vascular tumor in the left ear had enlarged. She had left lower motor neuron facial palsy (Figure 7.155), left deafness, a reduced left gag reflex, and ataxia toward the left. Skull radiographs showed destruction of the jugular foramen and petrous bone (Figure 7.156). Selective external carotid angiography showed a large vascular tumor, mostly extracranial, with a smaller component in the posterior fossa. The medial two-thirds of the tumor were supplied by the ascending pharyngeal artery; the remaining supply came from the posterior auricular and internal maxillary arteries (Figure 7.157 A, B). After embolization of the ascending pharyngeal and internal maxillary arteries, the tumor vascularity disappeared. Suboccipital craniectomy, mastoidectomy, and labyrinthectomy were then performed, the latter procedures by the ENT surgeon. The craniectomy must expose the point where the superior petrosal sinus drains into the lateral sinus as it becomes the sigmoid sinus. This is important when ligating the lateral sinus: ligation and division must be below the superior petrosal sinus, toward the sigmoid sinus. The lateral sinus and superior petrosal sinus should not be ligated and divided. After extending the craniectomy inferiorly to expose the tumor at the jugular bulb, a high-speed drill is used to remove mastoid and petrous bone inferiorly along the sigmoid sinus and tumor margin. During mastoidectomy, care must be taken to protect the facial nerve as it runs posteriorly and inferiorly to emerge from the stylomastoid foramen. In this case, radical mastoidectomy extending to the labyrinth exposed a large tumor destroying the petrous bone and jugular foramen. Feeding vessels were coagulated and divided. The dura of the posterior and middle fossae was then opened to ligate and divide the lateral sinus below the superior petrosal sinus, improving access to the inferior part of the tumor. The posterior fossa dura should be opened widely enough to provide a good view of the tumor within the posterior fossa. In this patient, the tumor had penetrated the dura at the internal acoustic meatus and jugular foramen. The extradural component was removed first to interrupt its blood supply, followed by the intradural component. There was very little bleeding, demonstrating the benefit of preoperative embolization. Tumor adjacent to the internal carotid artery had to be removed rapidly using suction and bipolar coagulation to expose the artery, after which its small tumor-feeding branches could be coagulated. Tumor at the jugular foramen had to be carefully separated from cranial nerves IX, X, and XI, situated anteromedially in the foramen. In this patient, cranial nerves VII and VIII had already lost all function and therefore required less caution. The inferior tumor extension was followed to the internal jugular vein, which was ligated and divided. The tumor and vein could then be removed. The dura was sutured closed, but a defect remained where dura had been lost through tumor involvement and dissection. A piece of muscle was used to cover this gap.
Figure 7.155 A patient with a glomus jugulare tumor presenting with facial palsy, left deafness, hoarseness, and choking on swallowing.Figure 7.156 Skull radiograph showing destruction of the jugular foramen and petrous bone.Figure 7.157 External carotid angiogram showing a highly vascular tumor. Histological examination confirmed a glomus jugulare tumor. A. Appearance before embolization.Figure 7.157 B. Appearance after embolization.
The major complication in this patient was CSF leakage, requiring reoperation and repair of the dura with fascia using a continuous suture. The leakage resolved. The patient has remained free of recurrent symptoms for 10 years.
Original pages 949–960
REFERENCE
Brown F.W., Shiau, Y.F., and Richter, G.C. : Anesthesia and surgery in the patient with liver disease. In Goldmann, D.R., Brown, F.H., Levy W.K., Slap, G.B., and Sussmann, E.J., eds. Medical Care of The Surgical Patient, A Problem-Oriented Approach to Management. Philadelphia, J.B. Lippincott Co., pp 326-342, 1982.
Mudge, G.H., : Diuretics and other agents employed in the mobilization of edema fluid. In Goodman, L.S., and Gilman, A., eds : The Pharmacological Basis of Therapeutics. New York, Mac millan Publishing Co., pp 817-847, 1975.
Lester, M.C., Nelson, P.B., Neurological aspects of vasopressin release and the syndrome of inappropriate secretion of antidiuretic hormone. Neurosurgery 8 : 735-740, 1981.
Marshall, L.F., King J., Langfitt, T.W., The complication of high dose corticosteroid therapy in neurosurgical patients. A prospective study. Ann. Neurol. 1:201-203, 1977.
Malis, L.I., Prevention of neurosurgical infection by intraoperative antibiotics. Neurosurgery 5 : 339-343, 1979.
Gordon E., Anesthesia for neurosurgery : A Brain and Practice of Neuroanesthesia. Elsevier North Holland, Biomedical Press. p 218-46, 1981.
Dawson B., Michenfelder J.D., Theye, R.A., Effect of ketamine on canine cerebral blood flow and metabolism : Modification by prior administration of Thiopental. Anesthesia Analg. Curr. Res. p 50-443, 1971.
Shapiro H.M., Wyte S.R., Harris A.B., Ketamine anesthesia in patients with intra cranial pathology. Br. J. Anesthesia 44 : 1200-4, 1972.
Gilbert R.G.B., Mellar R.A., Brindle G.F., Second thought on halothane in neuro surgery. Canad. Anesthesia Soc. J. 7 : 52-55, 1960.
Schittini, A. Schapira M., Kepeser, E.R., Fluothane anesthesia in neurosurgery, Preliminary report. Anesth. Analg. (cleveland) 40 : 345-351, 1961.
Adam R.W., Gronert G.A., Sundt T.M., Michenfelder J.D., Halothane, hypocapnia and CSF pressure in neurosurgery. Anesthesiology 37 : 510-7, 1972.
Schutta, H.S., Kassell, N.F., and Langfitt, T.W. Brain swelling produced by injury and aggravated by arterial hypertension. Brain 91 : 281, 1968.
Mc Comish P.B., Bodley P.O., Monitoring. In Anesthesia for Neurological Surgery. Lloyd-Luke Publication p 169, 1971.
Robinson A.G., : DDAVP in the treatment of central diabetes insipidus., N. Engl J. Med. 294:507-511, 1976.
Allen M.B., Jr., Johnston K.W. : Preoperative Evaluation ; complications, Their prevention and treatment. In Neurological Surgery by Youmans 3rd edition. W.B. Saunders Co. vol. 2 : 833-900, 1990.
Law, E.R., Jr. Abboud C.F., Hayles A.B., The principle of pituitary replacement therapy related to sellar and parasellar surgery. In Clinical Neurosurgery vol. 28 : 108-115, 1981.
Haines, S.J., and Goodman M.L., Antibiotics prophylaxis of post-operative neurosurgical wound infection J. Neurosurg. 56 : 103-105, 1982.
Quartey, J.R.C., and Polyzoidis K. Intraoperative antibiotics prophylaxis in neuro surgery. Clinical study. Neurosurgery. 8 : 669-671, 1981.
Horwitz, N.H., and Rizzoli, H.V., : Postoperative Complications in Neurosurgical Practice. Baltimore, Williams & Wilkins, p 2, 1982.
Gross Joyce Y., : Hematologic Assessment and Management in Medical Perioperative Management. Prentice-Hall International Inc. p 264-303, 1989.
Marshall, B.M., : Air embolism in neurosurgical anesthesia, its diagnosis and treatment. can. Anesth. Soc. J. 12 : 255-261, 1965.
Martin R.W. Colley P.S. : Evaluation of transesophageal Doppler detection air embolism in dogs. Anesthesiology 58 : 117-123, 1983.
Furuya H., suzuki T., Okumura F., Kishi Y., Uefuji T., : Detection of air embolism by transesophageal echocardiography. Anesthesiology 58 : 124-129, 1983.
Bunegin, L., Albin M.S., Helsel, P.E., Hoffman A., Hung T.K., : Positioning of the right atrial catheter : A model for reappraisal. Anesthesiology 55 : 343-348, 1981.
Wipa Suwanchinda: Administration of inhalational anesthesia. In Anesthesiology. Department of Anesthesiology, Faculty of Medicine Siriraj Hospital, pp. 183–203, 1984 (B.E. 2527). [In Thai.]
Dandy W.E., : Control of hemorrhage, In The Brain. W.F. Prior Co. p 144-154, 1966.
Yasargil M.G., Bipolar coagulation in neurosurgery. In Microsurgery. George Thieme Verlag. Stuttgart p 41-45, 1969.
Russell D.S., Rubinstein L.J., : Tumors of central neuroepithelial origin. In Pathology of tumors of the Nervous System. 5th edition, Edward Arnold Co. p 93, 1989.
Needham C.W., : Neurosurgical Syndromes of the Brain-Frontopolar Syndromes. Springfield Ill., Charles C. Thomas, 1973.
Lunsford L.D., Maroon J.C., : C.T. localization and biopsy of intracranial lesions. In Operative Neurosurgical Techniques. Edit. by Schmidek H.H. and Sweet W.H., Grune & Stratton Publisher, vol. I 403-417, 1982.
Conway L.W., : Stereotactic biopsy of deep intracranial tumors. In Operative Neurosurgical Techniques Edit. by Schmidek H.H., Sweet W.H., Grune & Stratton Pub. vol. I 389-401, 1982.
Zulch K.J. : Tumors of the Neuroepithelial tissue. In Brain Tumors, 3rd edit. Springer-Verlag Publ. Co., p 211, 1986.
Kernohan J.W., Mabon R.F., Svien H.J., Adson A.W., : A simplified classification of the glioma. Proc. staff Mtg. Mayo Clin. 24 : 71-75, 1949.
Zulch K.J., : Histology Typing of Tumor of Central Nervous System, Geneva, World-Health Organization 1979.
Burger P.C., : Glioma, Pathology. In Neurosurgery edit by Williams & Rengachary, Mc Graw-Hill Book Co. p 553-563, 1985.
Chandler W.F., Knake J.E., Mc Gillicuddly J.E., Lillehei, K.O., and Silver T.M. : Intraoperative use real-time ultrasonography in neurosurgery. J. N.S. 57: 157-163, 1982.
Fasono A.V., Panzio R.M., Liboni W., and Math M., : Preliminary experience with real-time intraoperative ultrasonography associated with the laser and the ultrasonic aspirator in neurosurgery. Surg. Neurol. 19 : 318-323, 1983.
Dohrmann G.J., and Rubin J.M., : Intraoperative real-time ultrasonography, localization, characterization and instrumentation of lesions of brain & spinal cord. In Fasano V.A., ed. advanced intraoperative techniques in neurosurgery. N.Y., Springer-Verlag, pp 3-19, 1985.
Salcman : Supratentorial gliomas : Clinical features and surgical therapy. In Neurosurgery edit. by Wilkins R.H. and Rengachary S.S. vol. I p 579-590, 1985.
Leibel S.A., Sheline G.E., Wara W.M., Boldrey, E.B., Nielsen S.L. : The role of radiation therapy in the treatment of astrocytoma. Cancer 35 : 1551-1557, 1975.
Kullberg G., West K.A., : The influence of corticosteroids on the ventricular fluid - pressure. Acta neurol. scand 41 suppl. 13 : 445, 1965.
Weir, B., and Elvidge, A.R., Oligodendrogliomas : An analysis of 63 cases. J. N.S. 29 : 500-505, 1968.
Chin H.W., Hazel, J.J., Kin T.H. and Webster J.H., : Oligodendrogliomas. I.A. clinical study of cerebral oligodendrogliomas. Cancer, 45 : 1458-1466, 1980.
Sheline, G.E., : Radiation therapy of brain tumors. Cancer 39 : 873-881, 1977.
Sheline, G.E., Boldrey E., Korlsberg, P., and Phillips, T.L., Therapeutic considerations in tumors affecting the central nervous system : oligodendrogliomas. Radiology 82 : 84-89, 1964.
Stern J., Jakobiec F.A., Housepian E.M. : The architecture of optic nerve gliomas with and without neurofibromatosis. Arch. Ophthalmol 98 : 505-511, 1980.
Marquardt M.D., Zimmerman L.E., : Histopathology of meningiomas and gliomas of the optic nerve. Human Pathol. 13 : 226-235, 1982.
Wilson W.B., Feinsod M., Hoyt, W.F., Nielson S.L., : Malignant evalution of childhood chiamal pilocytic astrocytoma. Neurology 26 : 322-325, 1976.
Chutorian A.M., Schwartz J.F., Evans, R.A., and Carter, S., : Optic nerve glioma in children. Neurology 14 : 83-95, 1964.
Iraci, G., Gerosa M., Scanarini M. et al : Anterior optic gliomas with precocious or pseudoprecocious puberty. Child’s brain 7 : 314, 1980.
Matson D.D., : Gliomas of the optic pathways. In Neurosurgery of Infancy and Childhood 2nd ed. Charles C. Thomas Pub. 523-536, 1969.
Horwich A., Bloom H.J.G., : Optic gliomas, radiation therapy and prognosis. International J. of radiation Oncology and biological physics 11, 1067-79, 1985.
Swenson, S.A., Forbes G.S., Younge, B.R., et al. : Radiologic evaluation of tumors of the optic nerve. A.J.N.R. 3 : 319, 1982.
Usold R., Newton, T.H., and Hoyt, W.F. : C.T. technique of the optic nerve. J. comput. Assist. Tomogr., 5 : 560-563, 1980.
Golden G.S., Ghatak N.R., Hirano, A., French J.H., : Malignant glioma of the brain stem : A clinico-pathological analysis of 13 cases. J. Neurol. Neurosurg. Psychiatry 35 : 732-738, 1972.
Hoffman H.J., : Brain stem gliomas in children. In Intracranial Tumors in Infancy and Childhood. Karger Co., Switzerland p 154-159, 1987.
Hoffman H.J., Becker, L., Carven M.A., : A clinical distinct group of benign brain stem gliomas. Neurosurgery 7 : 243-248, 1980.
Lassiter K.R.L., Alexander E., Jr., Davis, Ch., Jr., Kelley, D.L. Jr., Surgical treatment of brain stem gliomas. J. Neurosurgery 34 : 719-725, 1981.
Epstein, F., McLeary, E.L., : Intrinsic brain stem tumors of childhood : surgical indications. J. Neurosurgery. 64 : 11-15, 1986.
Panitch E., and Berg, B.O., : Brain stem tumors of childhood and adolescence. Am. J. Dis. Child 19 : 465-472, 1970.
Koos W.T., Miller M.H., : Thalamic gliomas. In Intracranial Tumors of Infants and Children. C.V. Mosby Co., p 148-156, 1971.
Schneider R.C., Crosby E.C., Kahn E.A., Taren J.A., : Correlative Neurosurgery 3rd ed. Charles C. Thomas Pub. p 255, 1982.
Bendhein, P.E., and Berg, B.O. : Ataxic hemiparesis from a midbrain mass. Ann. Neurol 9:405-407, 1981.
Schneider R.C., Crosby E.C., Kahn E.A., Taren J.A., : Correlative Neurosurgery 3rd ed. Charles C. Thomas Pub. p 243, 1982.
Eisenberg H.M., Mc Comb J.G., Lorenzo A.V., : Cerebro spinal fluid overproduction and hydrocephalus associate with choroid plexus papilloma. J. Neurosurgery 40 : 381-385, 1974.
Milharat T.H., : Pediatric Neurosurgery (Contemporary Neurology Series, Vol. 16) Philadelphia, Davis pp. 95-99, 1978.
Matson D.D. : Neurosurgery of Infancy and Childhood. 2nd ed. Springfield Ill., Charles C. Thomas pp 581-595, 1969.
Fairburn B. : Choroid plexus papilloma and its relation to hydrocephalus. J. N.S. 17 : 166-171, 1960.
Laurence K.M., The biology of choroid plexus papilloma & carcinoma of lateral ventricle. In Tumors of the Brain and Skull. ed. by Vinken P.J. and Bruyn G.B., North-Holland Pub. Co., pp 555-595, 1974.
Harwood-Nash D.C., Fitz C.R., : Neuroradiology in infants and children. St. Louis, Mosby pp 751-754, 1976.
Koos W.T., Miller M.H., : Tumors of the cerebellum. In Intracranial Tumors of Infants and Children. C.V. Mosby Co. pp 305-315, 1971.
Naidich, T.P., Lin I.P., and Leeds, N.E., : Primary tumors and other masses of the cerebellum and 4th ventricle. Neuroradiology 14 : 153-174, 1977.
Brant-Zawadski M., Davis P.L., Crooke, L.E., Mills, C.M., Norman D., Newton, T.H., Sheldon, P., and Kaufman, L., NMR demonstration of cerebral abnormalities comparison with C.T. A.J.N.R., 4 : 117-124, 1983.
Raimondi, A.J., and Tomita T., : Medulloblastoma in childhood. Acta. Neurochir. 50 : 127-138, 1979.
Berry M.P., Jenkin R.D., Keen C.W., Nair B.D., and Simpson W.J., Radiation treatment for medulloblastoma. A 21 years review, J. Neurosurg. 55 : 43-51, 1981.
Grossman C.B., : Magnetic Resonance Imaging and Computed Tomography of the Head and Spine. Williams & Wilkins Co., pp 131-132, 1990.
Dandy W.E., : Pineal body and pineal tumors. In The Brain. W.F., Prior Co. p 580-590, 1966.
Poppen J.L. : The right occipital approach to pinealoma J.N.S. 25 : 706-710, 1966.
Stein B.M., : The infratentorial supracerebellar approach to pineal lesions. J. N.S. 35 : 197-202, 1971.
Stein B.M., : Surgical treatment of pineal tumors. In Clinical Neurosurgery. Chapter 19. Williams and Wilkins Co. vol. 26 : 490-510, 1979.
House W.F., Hitselberger W.E., : Acoustic tumors. In Tumors of The Brain & Skull, part II, Ed. by Vinken P.J., and Bruyn G.W., North-Holland Publishing Co. p 666-693, 1974.
Sheptak P.E. and Jannetta P.J. : The two-stages excision of huge acoustic neuromas. J.N.S. 51 : 37-41, 1979.
House W.F., : Surgical expose of the internal auditory canal and its contents through the middle cranial fossa. Laryngoscope 71 : 1363-1385, 1961.
House W.F., (ed.) Monograph : Transtemporal bone microsurgical removal of acoustic neuromas. Arch. Otolaryngology 80 : 597-756, 1964.
Rhoton, A.L., Jr. et al : Nervus intermedius J.N.S. 29 : 609, 1968.
Rhoton, A.L., Jr., : Microsurgical anatomy of the brain stem surface facing an acoustic neuroma. Surg. Neurology. 25 : 326-339, 1986.
Samii M., Turel K.E., Penkert G. : Management of seventh and eighth nerve involvement by cerebellopontine angle tumors. In Clinical Neurosurgery vol. 32 : 526, 1984.
Pool L.J., Pava, A.A., Greenfield, E.C., Acoustic Nerve Tumors. 2nd edition. Charles C. Thomas Pub. p 157, 1970.
Northfield D.W.C., The Meningioma : Hemangioblastoma. In The Surgery of the C.N.S., Blackwell Scientific Publication p. 232, 1973.
Moody D.M., Meningiomas : Radiology in Neurosurgery ed. by Williams R. H., and Rengachary. S.S. Mc Graw-Hill Co. p 623-634, 1985.
Stevens J.M., Ruiz J.S., Kendall B.E., : Observations on peritumoral edema in meningioma Part II : Mechanism of edema production. Neuroradiology 25 : 125-131, 1983.
Shadir J., Coblenz, C., Malanson, D., Eyhier R., Robilailh, Y. : New C.T. findings in aggressive meningioma. A.J.N.R. 6 : 101-102, 1985.
New PFJ., Hesselink R.J., O-Corrol C.P., Kleinmann G.M., : Malignant meningioma : C.T. and histological criterion including a new C.T. sign. A.J.N.R. 3 : 267-276, 1982.
Dietermann J.F., Heldt N., Burguet J.F., Medjek L., Maitrit D., Wackerheim A., : C.T. findings in malignant meningiomas, Neuroradiology, 23 : 207-209, 1982.
Mackay I.M., Bydder G.M., Young I.R., : M R imaging of central nervous system tumors that do not display increase in T1 or T2, J. comput. Assist. Tomogr. 9 : 1055-1061, 1985.
Spangoli M., Goldberg H.I., Grossman R.I., : High field M R imaging of intracranial meningiomas. Radiology 161 : 369-375, 1986.
Zimmerman R.D., Fleming C.A., Saint Louis, L.A., Lee BCP. Manning J. J., Deck MDF., : Magnetic resonance imaging of meningiomas. A.J.N.R. 6 : 149-150, 1985.
Cushing H., and Eisenhardt, L., : Meningiomas : Their Classification, Regional Behavior, Life History, and Surgical End Results. Springfield, Ill. Charles C. Thomas, Publisher, 1938.
Ojeman, R.G., : Surgical management of meningioma of the tuberculum sellae, olfactory groove, medial sphenoid wing and floor of the anterior fossa. In Operative Neurosurgical Techniques edit by Schmidek H.H., Sweet W.H., Grune & Stratton Publishers vol. I, p 536-559, 1982.
Mac Carty, C.S., Piepgras, D.G., and Ebersold M.J., Meningeal tumors of the brain. In Neurological Surgery edit. by Youmans p 2936-2966, 1982.
Gregorius F.K., Hepler R.S., Stern W.E., : Loss and recovery of vision with suprasellar meningiomas J.N.S. 42 : 69-75, 1975.
Kempe L.G., : Tuberculum sellae meningioma. In Operative Neurosurgery, Springer-Verlag Pub. vol. I p 94-97, 1968.
Bonnal J., Thebout A., Brotchi J., and Born, J., : Invading meningioma of the sphenoid ridge. J. Neurosurgery 53 : 587-599, 1980.
Derome P.J., and Guiot G., : Bone problem in meningiomas invading the base of the skull. Clin. N.S. 25 : 435-451, 1978.
Frowein R.A., : Meningiomas of the tentorium. Acta Neurochir. (wien) 31 : 283-284, 1975.
Maxwell R.E., Chou S.N. : Posterior fossa meningiomas. In Operative Neurosurgical Techniques ed. by Schmidek H.H., and Sweet W.H., Grune & Stratton Pub. vol. I, 517-532, 1982.
Kempe L.G., : Posterior fossa, spinal cord and peripheral n. disease : in Operative Neurosurgery vol. 2, New York, Springer-Verlag p 259, 1970.
Meyer F.B., Ebersold, M.J., and Ruse D.F. : Benign tumors of the foramen magnum J. N.S. 61 : 136-142, 1984.
Fornari M., Savoiardo M., Morello G., and Solero C.L. : Meningiomas of the lateral ventricle, neuroradiological and surgical consideration in 18 cases J. Neurosurgery 54 : 64-74, 1981.
Ladenhiem J.C., : Choroid plexus meningioma of the lateral ventricle. Springfield Ill., Charles C. Thomas, Publisher 1963.
Kobayashi S., Okazaki H., and MacCarty, C.S., : Intraventricular meningiomas, Mayo Clinic. Proc., 46 : 735-741, 1971.
Spencer D.D., Collins. W.F., : Surgical management of lateral intraventricular tumors. In Schmidek H.H., Sweet W.H., (eds.) : Operative Neurosurgical Techniques : Indications, Methods, and Results. New York, Grune & Stratton p 561-574, 1982.
Gado M., Huete I., and Mikhael M. : computerized tomography of infratentorium tumors. Semin. Roentgenol. 12 : 109-120, 1977.
Jeffrey R., : Clinical and surgical aspects of posterior fossa hemangioblastoma. J. Neurol. Neurosurg. Psychiatr. 38 : 105-111, 1975.
Jeffrey R., : Pathological and hematological aspects of posterior fossa hemangioblastoma J. Neurol. Neurosurg. Psychiatr. 38 : 112-119, 1975.
Horton W.A., Wong V., Eldridge R. : von Hippel-Lindau disease : Clinical and pathological manifestations in nine families with 50 affected member. Arch. Intern. Med. 136 (7) : 769-777, 1976.
Helle T.L., Conley F.K. Britt R.H., : Effect of radiation therapy on hemangioblastoma : A case report and review of the literature. Neurosurgery 6 : 82-86, 1980.
Sung D.I., Chang C.H., Harisiadis L. : cerebellar hemangioblastoma. Cancer 49 : 553-555, 1982.
Matson D.D., Craniopharyngioma, in Neurosurgery of Infancy and Childhood 2nd edit. Charles C Thomar Publisher p 544-574, 1969.
Koos W.I., and Miller M.H. : Craniopharyngioma in Intracranial Tumors of Infants and Children C.V. Mosby Co. p 188-212, 1971.
Michelsen W.J., Mount L.A., and Renaudin J. : Craniopharyngioma. A thirty-nine years surgery. Acta Neurol 18 : 100-106, 1972.
Sung D.I., Chang C.H., Harisiadis L., and Carmel P.W., Treatment & results of craniopharyngioma. Cancer 47 : 847-852, 1981.
Symon L., and Sprich W., : Radical excision of craniopharyngioma. Result in 20 patients J.N.S. 62 : 174-181, 1985.
Kobayashi T., Nakane T., Kageyama N., : combined transphenoidal and intracranial surgery for craniopharyngioma in Prog. Exp. Tumor Res. vol. 30 pp 341-349 (Karger, Basel 1987).
Bruce D.A., : Craniopharyngioma. In Current Therapy in Neurological Surgery, B.C. Decker Inc., p 36-38, 1985.
Carmel P.W., : Brain tumors of disordered embryogenesis. Chapter III in Neurological Surgery, ed. by Youmans, W.B. Saunders Co. p 3223-3249, 1990.
Hoff J.T., and Patterson R.H., Jr. : Craniopharyngioma in children and adults. J.N.S. 36 : 2922-2932, 1972.
Kramer, S., : Craniopharyngioma : The best treatment is conservative surgery and postoperative radiation therapy. In Morley T.P. ed. : Current Controversies in Neurosurg. Phila. W.B. Sounders Co. pp 336-343, 1976.
Kramer S., Mckissock W., and Concannon J.P., Craniopharyngioma : treat by combined surgery and radiation therapy. J.N.S. 18 : 217-226, 1961.
Richmond I.L., Wara W.M., and Wilson C.B., Role of radiation therapy in management of craniopharyngioma in children. Neurosurg. 6 : 513-517, 1980.
Baskin D.S., and Wilson C.B., : Surgical management of craniopharyngioma : A review of 74 cases. J.N.S. 65 : 22-27, 1986.
Shapiro K., Till K., and Grant D.N. : Craniopharyngioma in childhood : A rational approach to treatment J.N.S. 50 : 617-623, 1979.
Moore K.L., : The Developing Human : Clinically Oriented Embryology, Philadelphia, Saunders, 1973.
Baxter J.W., Netsky, M.G., Epidermoid and dermoid tumors : Pathology in Neurosurgery ed. by Wilkins R.H., and Rengachary S.S. Mc Graw Hill Co. p 655-661, 1985.
Ulrich J. : Intracranial epidermoid : A study of their distribution and spread. J. Neurosurgery 21 : 1051-1058, 1964.
Conley F.K., Epidermoid and dermoid tumors : Clinical feature and surgical management in Neurosurgery ed. by Wilkins R.H., Rengachary S.S. p 668-673, 1985.
Davis K.R., Robertson G.H., Taveras J. M., New P.F.J., Trevor R. : Diagnosis of epidermoid tumor by computed tomography : analysis and evaluation of findings. Radiology 119 : 347-353, 1976.
Fawcitt R.A., Isherwood I. : Radiogiagnosis of intracranial pearly tumor with particular reference to the value of computer tomography. Neuroradiology 11 : 235-242, 1976.
Kood W., Th., and Miller M. H. : Congenital and embryonic tumors in Intracranial Tumors of Infants and Children. C.V. Mosby Co. p. 134-137, 1971.
Rosario M., Becker D.H., Conley F.K. : Epidermoid tumors involving the fourth ventricle. Neurosurgery 9 : 9-13, 1981.
Hall N.A. and Lunsford L.D. : Changing concepts in the treatment of colloid cysts. J. Neurosurgery, 66 : 186-191, 1987.
Shulman K., Shapiro K. : Colloid cysts of the third ventricle in infancy and childhood in Pediatric Neurosurgery, Grune & Stratton Inc. p 469-474, 1982.
Northfield D.W. : Colloid cyst of the third ventricle in The Surgery of the Central Nervous System, Blackwell Scientific Pub. p 206-210, 1973.
Ganti S.R., Antunes J.L., Louis K.M., Hilal S.K., Computed tomography in the diagnosis of colloid cysts of the third ventricle. Radiology 138 : 385-391, 1981.
Apuzzo M.L.J., Chikovanti O.K., Gott P.S. et al. Transcallosal interfornicial approaches for lesion affecting the third ventricle. Surgical considerations and consequences. Neurosurgery 10 : 547-155, 1982.
Tindall G.T., Barrow D.L., : Clinical and endocrinologic evaluation of patient with pituitary tumors in Disorders of The Pituitary. C.V. Mosby Co., p 123-143, 1986.
Limfoot J.A. (ed.) : Recent advances in the diagnosis and treatment of pituitary tumors. Reven Press, New York, 1979.
Martin J.B., Reichlin S. (eds): Clinical Neuro-endocrinology, Davis, Philadelphia, 1987.
Tindall G.T., and Barrow D.L., : Tumors of the sellar and parasellar area in adults. In Neurosurgery by Youman, 3rd edition, W.B., Saunders Co. p 3447-3498, 1990.
Samii M and Draf W., Surgery of the Skull Base. Springer-Verlag Pub. p 281, 1989.
Tindall G.T. and Barrow D.L. The Disorder of Pituitary. C.V. Mosby Co. p 367-368, 1986.
Hardy J. : Transsphenoidal surgery for hypersecreting pituitary tumors in Kohler P.O., Ross G.T. (eds.) : Diagnosis and Treatment of Pituitary Tumors, New York, American Elsevier, pp 179-194, 1973.
Hardy J. : Transphenoidal hypophysectomy. Neurosurgical technique, J. Neurosurg. 34 : 582-594, 1971.
Post K.D. Cobb W. Perioperative endocrine management of patients with pituitary tumors in Neurosurgery ed. by Wilkins R.H., Rengachary S.S., Mc Graw Hill book Co. Vol. I p 868-872, 1985.
Wannee Nitiyanant: Pituitary gland. In Endocrinology in Internal Medicine, pp. 167–194, 1984 (B.E. 2527). [In Thai.]
Wilson C.B. Dempsey L.C. : Transsphenoid microsurgical removal of 250 pituitary adenomas. J. Neurosurgery 48 : 13-22, 1978.
Post K.D., Biller B.J., Adelman L.S., Molitch M.E., Wolpert S. M., Reichlin S. : Selective transsphenoidal adenomectomy in women with galactorrhea-amenorrhea. JAMA 242 : 158-162, 1979.
Cobb W.E. : Spare S., Reichlin S. : Neurogenic diabetes insipidus : Management with dDAVP (1-desamino-8-D-arginine vasopressin) Ann. Intern. Med 88 : 183-188, 1978.
Martin J.B. and Copeland P. M. : Hypothalamic hypopituitarism. In Krieger D.T., and Bardin C.W. (eds). Current Therapy in Endocrinology and Metabolism. B.C. Decker, Philadelphia p 11, 1985.
Martin J.B., Reichlin S. : Clinical Endocrinology. F.A. Davis Co. p 276, 1987.
Kolodny H.D., Sherman L. : Laboratory aids in the diagnosis of pituitary tumors. Ann. Clin. Lab. Sci. 4 : 67, 1974.
Turkington R.W., Underwood L.E. Van Wyk J.J. : Elevated serum prolactin levels after pituitary stalk section in man N. Engl J. Med. 285 : 707, 1971.
Daughaday W.H. : The adenohypophysis. In Williams R.H. (ed.). Textbook of endocrinology ed 5 Philadelphia, W.B. Saunders Co. 1974.
Macleod R.M. : Regulation of prolactin secretion in Martini L, Ganong W.F., (eds). Frontiers in neuroendocrinology, New York, Raven Press Vol. 4, 1976.
Jacob H.S. : Prolactin and amenorrhea N. Engl J. Med. 295 : 954, 1976.
Martin J.B. : Management of hypersecreting pituitary adenomas. Clinical Neurosurgery 27 : 99, 1980.
Faria M.A.Jr., Tindall G.T., : Transsphenoidal microsurgery for prolactin-secreting pituitary adenoma. J. Neurosurgery 56 : 33, 1982.
Finn J.E., Mount L.A., : Galactorrhea in male with tumors in the region of pituitary gland. J Neurosurgery 35 : 723, 1971.
Law E.R.Jr. : Prolactinoma in current neurosurgical therapy p 119, 1989.
Thorner M.O., Besser G.M., Jones A., Dacie, J., and Jones A.E. : Bromocriptine treatment of female infertility : result of 13 pregnancies. Br. Med. J. 4 : 694-697, 1975.
Jewelewicz R., and Vande Wiele, R.L., Clinical course and outcome of pregnancy in 25 patients with pituitary microadenomas. Am. J. Obstet. Gynaecol. 136 : 339-343, 1980.
Shewckuk A.B., Adamson G.D., Lessard. P. and Ezrin C., The effect of pregnancy on suspected pituitary adenomas after conservative management of ovulation defect associated with galactorrhea Am. J. Obstet Gynaecol. 136 : 659-666, 1980.
Serri O. Rasio E., Beauregard H., et al : Recurrent of hyperprolactinemia after selective transsphenoidal adenomectomy in woman with prolactinoma N. Engl. J. Med. 309 : 280, 1983.
Sheline G.E., Grossman A., Jones A.E. Besser G.M., : Radiation therapy for prolactinoma. In Black P.M., Zervas N.T., Ridgeway E.C., Martin J.B. (eds). Secretory Tumors of the Pituitary Gland, New York, Raven Press. pp 93-108, 1984.
Evans W.S. Thorner M.O. : Bromocriptine in Neurosurgery by Wilkins R.H., Rengachary S.S., Mc Graw Hill Book Co. Vol. I 873-878, 1985.
Chandler W.F., : Pituitary Syndrome in Surgical Endocrinology, Clinical syndrome 2nd ed. by Friesen S.K., Thompson N.W L.B. Lippincott Co. p 396, 1990.
Landolt A.M., Keller P.J. Froesch E.R., Mueller J. : Bromocriptine : Does it jeopardize the result of later surgery for prolactinomas ? Lancet 1 : 657, 1982.
Landolt A.M., Osterwalder V : Perivascular fibrosis in prolactnomas : Is it increased by bromocriptine. J. Clin. Endocrinol. Metab. 58 : 1179, 1984.
Weiss M.H. Treatment options in management of prolactin-secreting pituitary tumors in Clin. Neurosurgery. Vol. 33 : 547-552, 1986.
Vance M.L., Evans W.S., Thorner M.O. : Drugs five years later : Bromocriptine. Ann. Intern. Med 100 : 78-91, 1984.
Franz A.G. : Hyperprolactinemia in Clinical Endocrinology ed by Collie R., Brown G.M., Van Loon G.R. Blackwell Scientific Pub. p 311-332, 1988.
Jonas E.A., Aloia J.F., Lane F.J. : Evidence of subclinical heart muscle dysfunction in acromegaly Chest 67 : 190, 1975.
Pepine C.J., Aloia J. : Heart muscle disease in acromegaly. Am. J. Med. 48 : 530, 1970.
Daughaday W.H. : New criteria for evaluation of acromegaly. N. Engl. J. Med. 301 : 1175-1176, 1979.
Laws E.R.Jr., Piepgras D.G., Randall R.V., Abboud C.F., : Neurosurgical management of acromegaly. Results in 82 patients treated between 1972 and 1977. J. Neurosurg. 50 : 454-461, 1979.
Hardy J., Soma M. : Acromegaly : Surgical treatment by trans-sphenoidal microsurgical removal of the pituitary adenoma, in Tindall G.T., Collin W.F. (eds) : Clinical Management of Pituitary Disorders, New York. Raven Press, pp 209-217, 1979.
Besser G.M., Wass J.A.H. : The medical management of acromegaly. In Black P.M. Zervas N.T. Ridgeway E.C., Martin J.B. (eds) Secretary Tumors of The Pituitary Gland. New York, Raven Press pp 155-168, 1984.
Tindall G.T., Tindall S.C. : Transsphenoidal surgery for acromegaly : Long-term results in 50 patients. In Black P.M., Zervas N.T., Ridgeway E.C., Martin J.B., (eds) Secretory Tumors of the Pituitary Gland. New York, Raven Press, pp 175-178, 1984.
Weiss M.H. : Acromegaly : Selection parameters and operative results. In Carmel P.W. (ed) : Clinical Neurosurgery. Baltimore, Williams & Wilkins, Vol 27 : pp 31-37, 1980.
Belforte L., Camanni, F., Chiodeni, F., Chiodin P.G., Liuzzi A., Massara F., Molinatti G.M., Muller E.E., and Silvestrini F., : Long term treatment with 2 Br-α-ergocriptine in acromegaly. Acta Endocrinol. 87 : 235-248, 1977.
Cassar J., Mashiter, K., Joplin G.F., : Bromocriptine treatment of acromegaly. Metabolism, 26 : 539-546, 1977.
Wass J.A.H., Mault P.J.A., Thorner M.O., Dacie J.E., Charlesworth M., Jones A.E., and Besser G.M., : Reduction of pituitary tumor size in patients with prolactinomas and acromegaly treated with bromocriptine with and without radiotherapy. Lancet 2 : 66-69, 1979.
Kiwak K.J., Zervas N.T., : Growth hormone-secreting pituitary tumor in Current neurosurgical therapy p 121-124, 1989.
Bloom B., Kramer S. : Conventional radiation therapy in the management of acromegaly. In Black P.M., Zervas N.T., Ridgeway E.C., Martin J.B., (eds) Secreting tumors of the pituitary gland. New York, Raven Press pp 179-190, 1984.
Kliman B., Kjellberg R.N., Swisher B., Butler W., : Proton beam therapy of acromegaly : A 20 years experience. In Black, P.M., Zervas N.T., Ridgeway E.C., Martin J.B., (eds.) : Secreting tumors of the pituitary gland, New York, Raven Press. pp 191-121, 1984.
Chandler W.F., Schteingart D.E., : Controversies in the management of Cushing’s disease. Clinical Neurosurgery, Baltimore, Williams and Wilkins Vol 33 : 553-562, 1986.
Tindall G.T., Barrow D.L. : Cushing’s syndrome and Nelson’s syndrome. In Disorder of the Pituitary, The C.V. Mosby Co. 245, 1986.
Dalakos T.G., Elias A.N., Anderson G.H.Jr., et al : Evidence for an angiotensinogenic mechanism of the hypertension of Cushing’s syndrome J. Clin. Endocrinol. Metab. 46 : 114, 1978.
Krakoff L., Nicolis G., Amsel B. : Pathogenesis of hypertension in Cushing’s syndrome An. J. Med. 58 : 216, 1975.
Mampalam T.J., Wilson C.B., : ACTH secreting tumor, Cushing’s disease and Nelson’s syndrome In Current neurosurgical therapy p 131-135, 19
Boggan J.E., Tyrrell J.B., and Wilson C.B. : Transsphenoidal microsurgical management of Cushing’s disease, J. Neurosurgery 59 : 159-200, 1983.
Hardy J. Cushing’s disease : 50 years later. Can J. Neurol Sci. 9 : 375-380, 1982.
Kuwayama A., Kageyama N. : Current management of Cushing’s disease, Part II, Contemp. Neurosurgery, 7 (3) : 1-6, 1985.
Krieger D.J., Medical treatment of Cushing’s disease In Clinical Neuroendocrinology : A Pathophysiological Approach, edited by G. Tolis, F. Labrie, J.B. Martin and F. Naftolin. Raven Press. New York. p 423-428, 1979.
Gold E.M. : The Cushing’s syndrome : changing views of diagnosis and treatment. Ann. Intern. Med. 90 : 829-844, 1979.
Jennings A.S., Grant W.L., and Orth D.N.: Results of treating childhood Cushing’s disease with pituitary irradiation. N. Engl. J. Med. 297:957–962, 1977.
Cairncross J.G., Kim J.H. and Posner J.B.: Radiation therapy for brain metastasis. Ann. Neurol. 7:529–541, 1980.
Takakura K., Sano K., Hojo S., and Hirano A.: Metastatic tumors of The Central Nervous System. Tokyo Igaku-shoin, 1982.
Gamache F.W., Posner J.B., Patterson R.H.: Metastatic brain tumors, in Neurological Surgery edited by Youmans J.R., 2nd edition p 2872–2898, 1982.
Selka R.G.: Intracranial metastatic disease: Development of a surgical philosophy. In Current Therapy in Neurological Surgery 54–56, 1990.
Young B., Patchell R.A.: Surgery for a single brain metastasis, in Neurosurgery Update I, Wilkins R.H., Rengachary S.S. (eds.) p 473–476, 1990.
Buchanan R.A. and Sholiton J.J.: Dephenyl hydantoin. In Woodbury D.M., Penry J.K., and Schmidt R.P. (eds.): Antianaleptic Drugs, New York, Raven Press, p 181–191, 1972.
Galicich J.H. and Arbit E.: Metastatic brain tumors, in Neurological Surgery ed. by Youman J.R. W.B. Sounders Co. p 3204–3222, 1990.
Guild S.R.: A hitherto unrecognised structure, the glomus jugularis in man. Anat. Rec. 79:28, 1941.
Spector G.J., Druck N.S., and Gado N.H.: Neurologic manifestation of glomus tumors in the head and neck. Arch. Neurol. 33:270–274, 1976.
Robertson J.T., Clark W.C., Robertson J.H., and Gardner L.G.: Glomus jugulare tumor. In Neurological Surgery ed. by Youman J.R. 3rd ed. p 3654–3666, 1990.
Gardner G., Cooke E.W., Robertson J.H., Palmer R.E., Bellott A.L. and Hamm C.W.: Skull base surgery for glomus jugulare tumors. Am. J. Otol. (suppl.) p 126–134, 1985.
Gardner G., Cocke E.W. Jr., Robertson J.T., Trumbull M.L., Palmer R.E.: Glomus jugulare tumors-combined treatment, Part I. J. Laryngol. Otol. 95:437–454, 1981.
Gardner G., Cocke E.W. Jr., Robertson J.T., Trumbull M.L., Palmer R.E.: Glomus jugulare tumors-combined treatment: part II. J. Laryngol. Otol. 95:567–580, 1981.
Robertson J.T., Gardner G., Cocke E.W. Jr., Gerald B.E., Trumbull M.L., Palmer R.E.: Glomus jugulare tumors, in Schmidek H.H., Sweet W.H. (eds.): Operative Neurosurgical Technique: Indications, Methods, and Results. New York, Grune & Stratton p 649–670, 1982.
Curtin H.D.: Radiologic approach to paragangliomas of the temporal bone. Radiology 150:837–838, 1984.
Hilal S.K., Michelsen J.W.: Therapeutic percutaneous embolization for extra-axial vascular lesions of the head, neck and spine. J. Neurosurg. 43:275–287, 1975.
Simpson G.T. II, Konrad H.R., Takahashi M., House J.: Immediate postembolization excision of glomus jugulare tumors. Advantages of new combined techniques. Arch. Otolaryngol. 105:639–643, 1973.
Colle J.M.: Panel discussion: Glomus jugulare tumors of the temporal bone. Radiation of glomus tumors of the temporal bone. Laryngoscope 89:1623–1627, 1979.
Wright A.D., Hill D.M., Lowy C. and Fraser T.R.: Mortality in acromegaly. Q.J. Med. 39:1–16, 1970.
Original page 961
Index
Browse topics alphabetically, then select a page number to read the corresponding text.

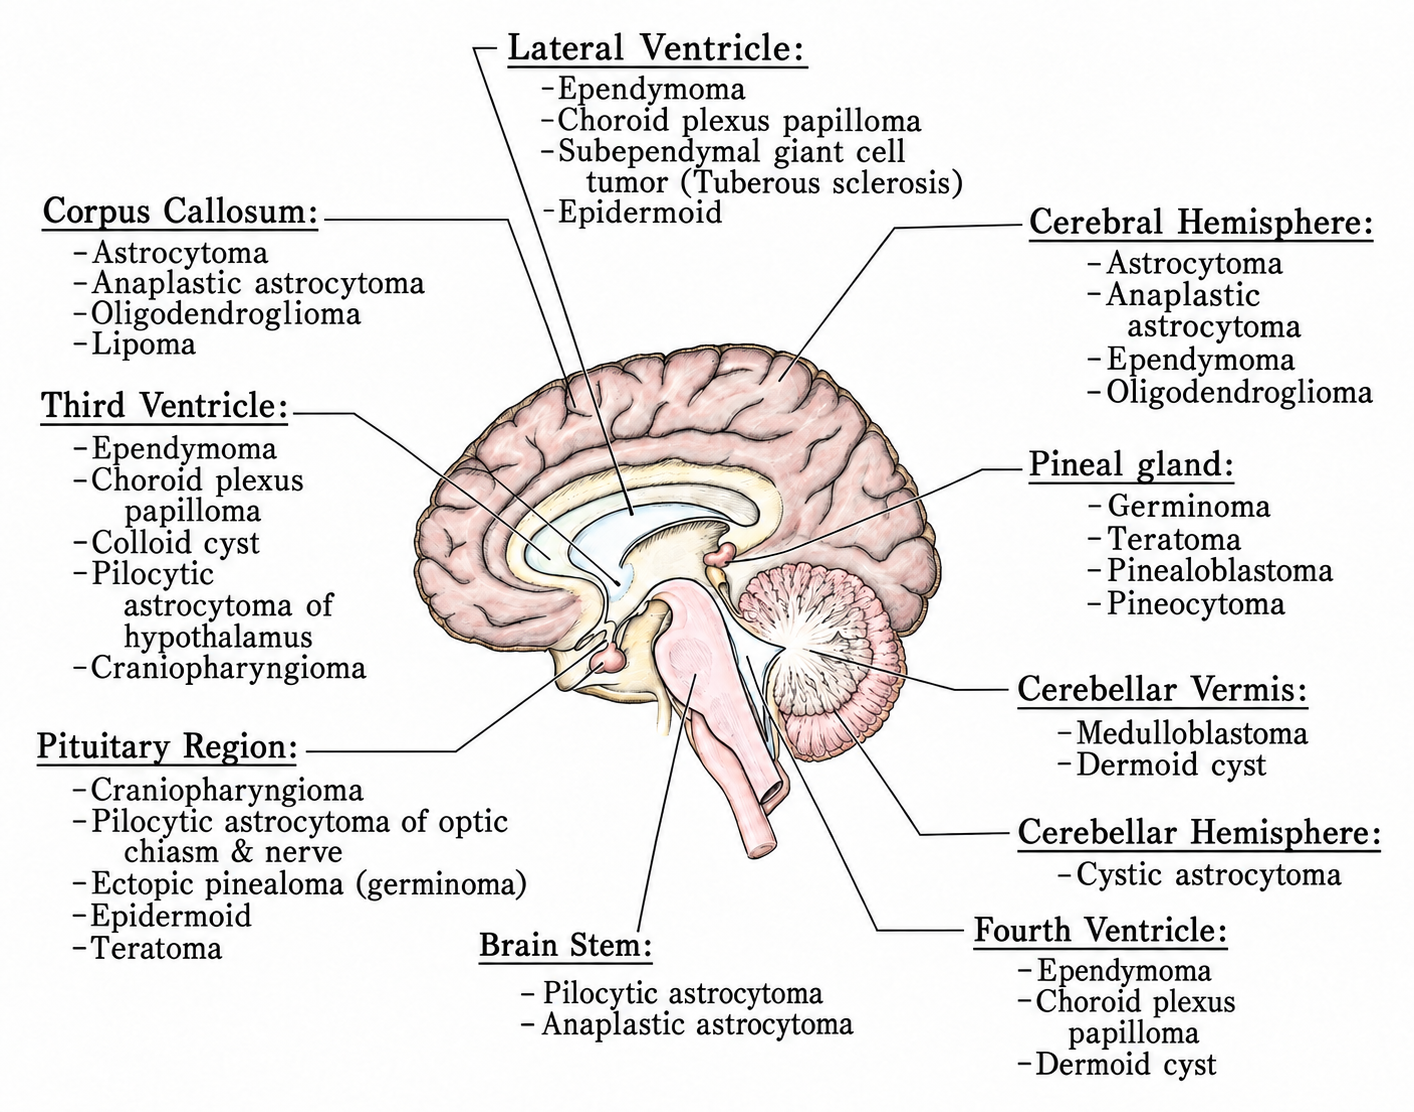
 Colour interpretation; refer to the original for anatomical details.
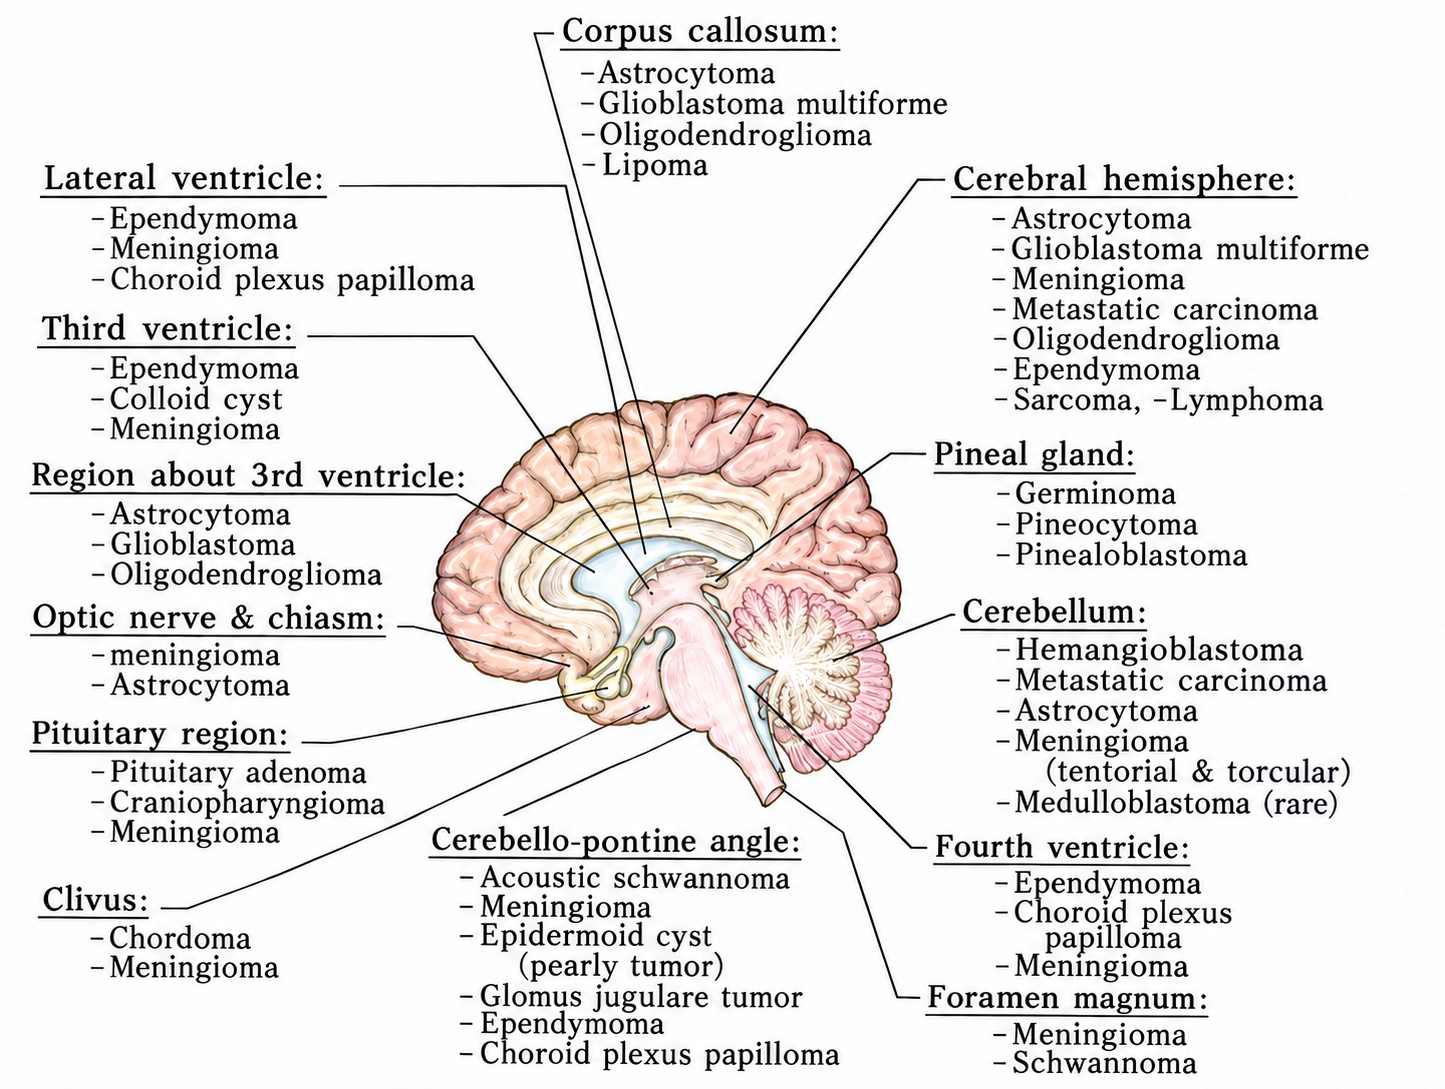
 Colour interpretation; refer to the original for anatomical details.
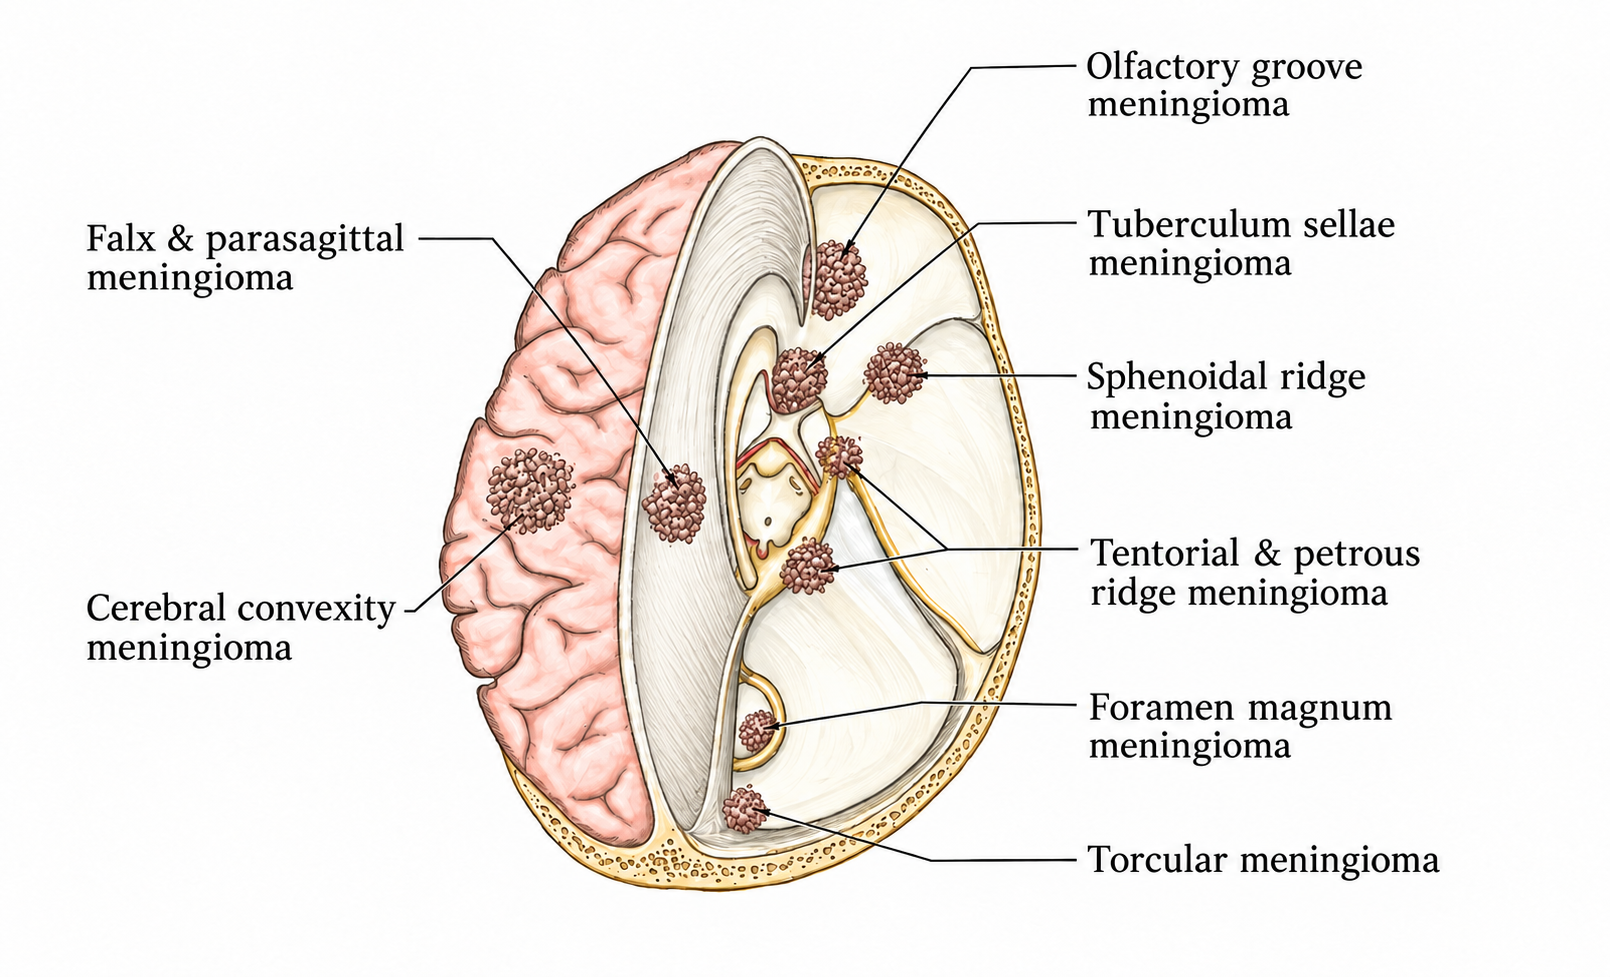
 Colour interpretation; refer to the original for anatomical details.
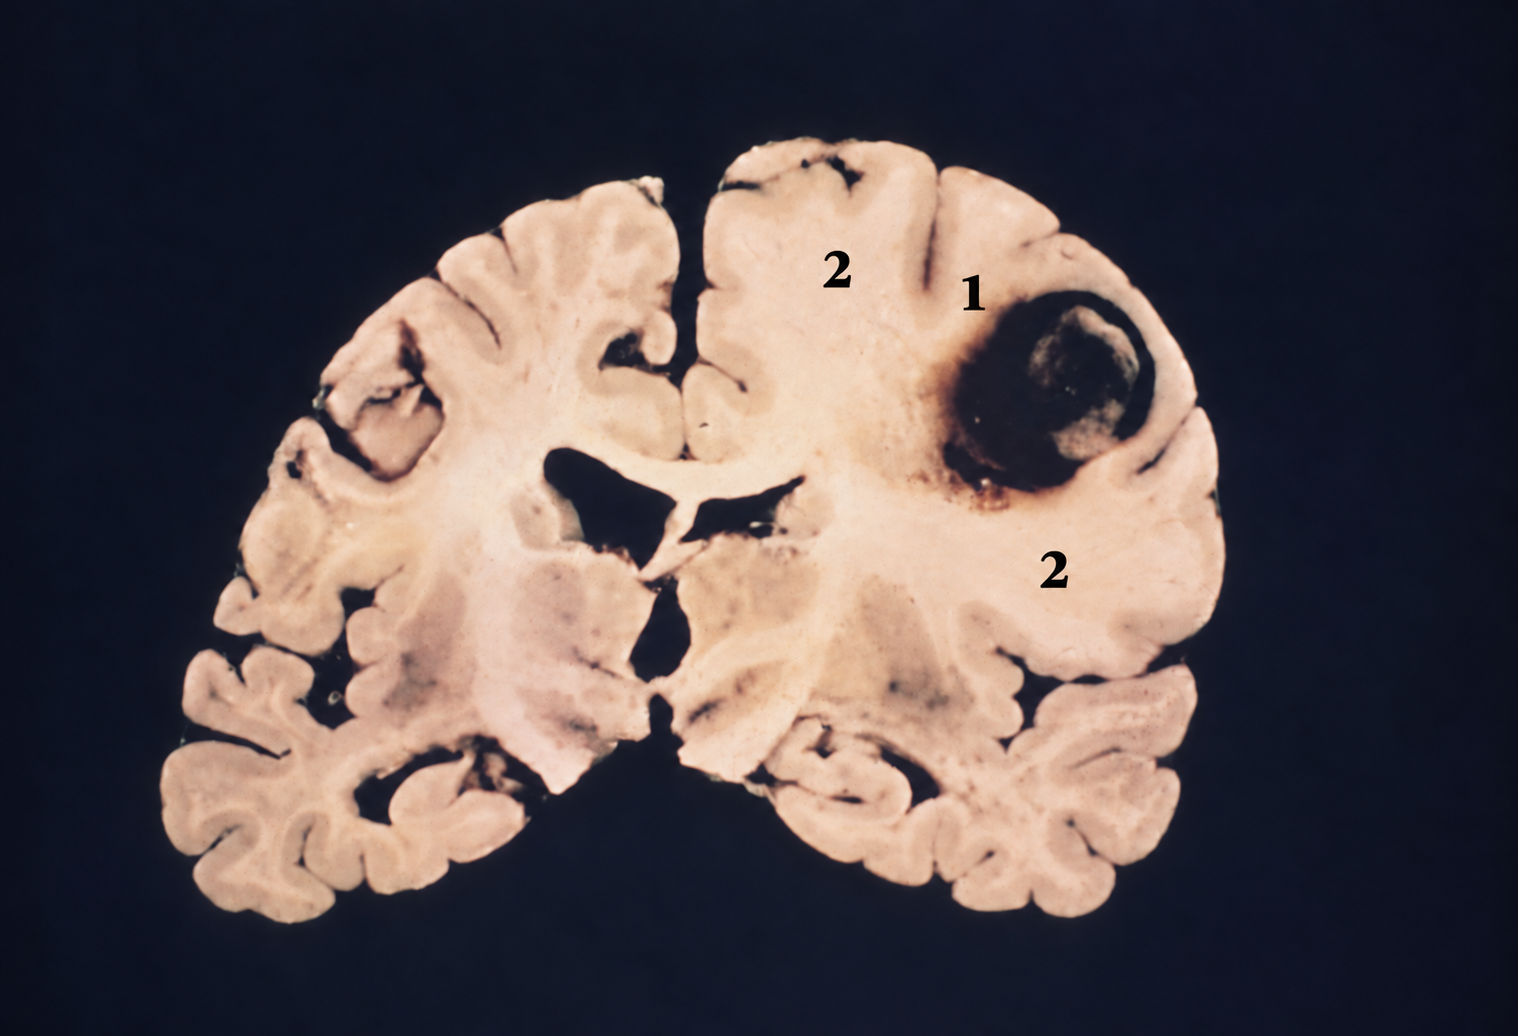
 Restored colour slide · Numbering follows Figure 1.4.


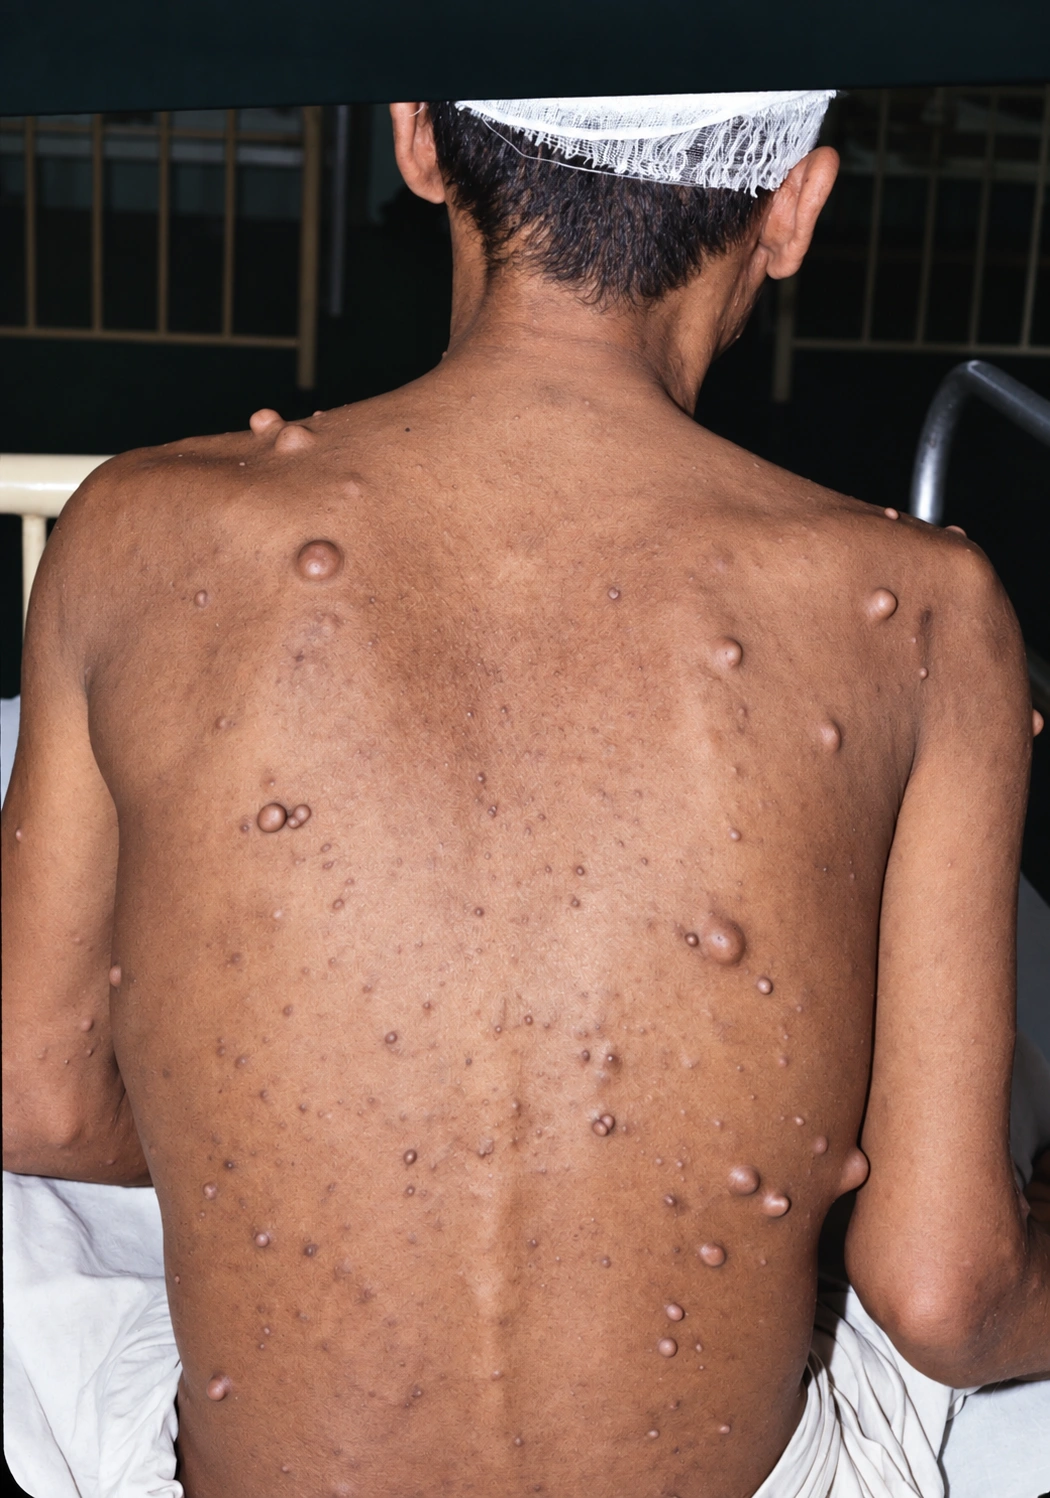

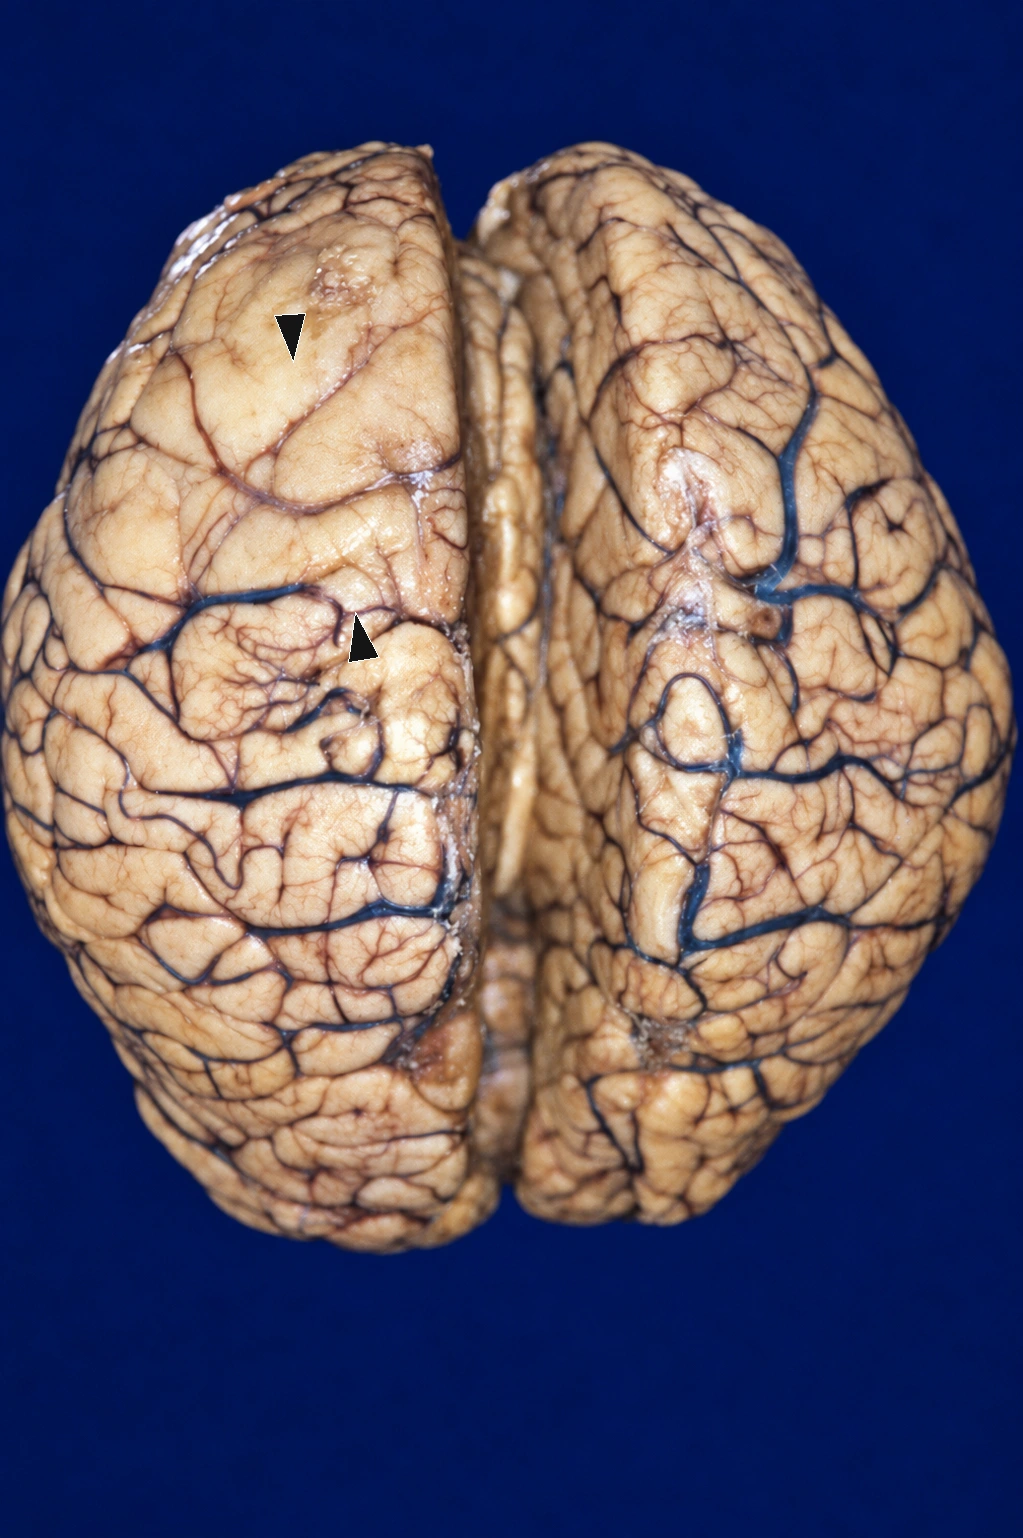


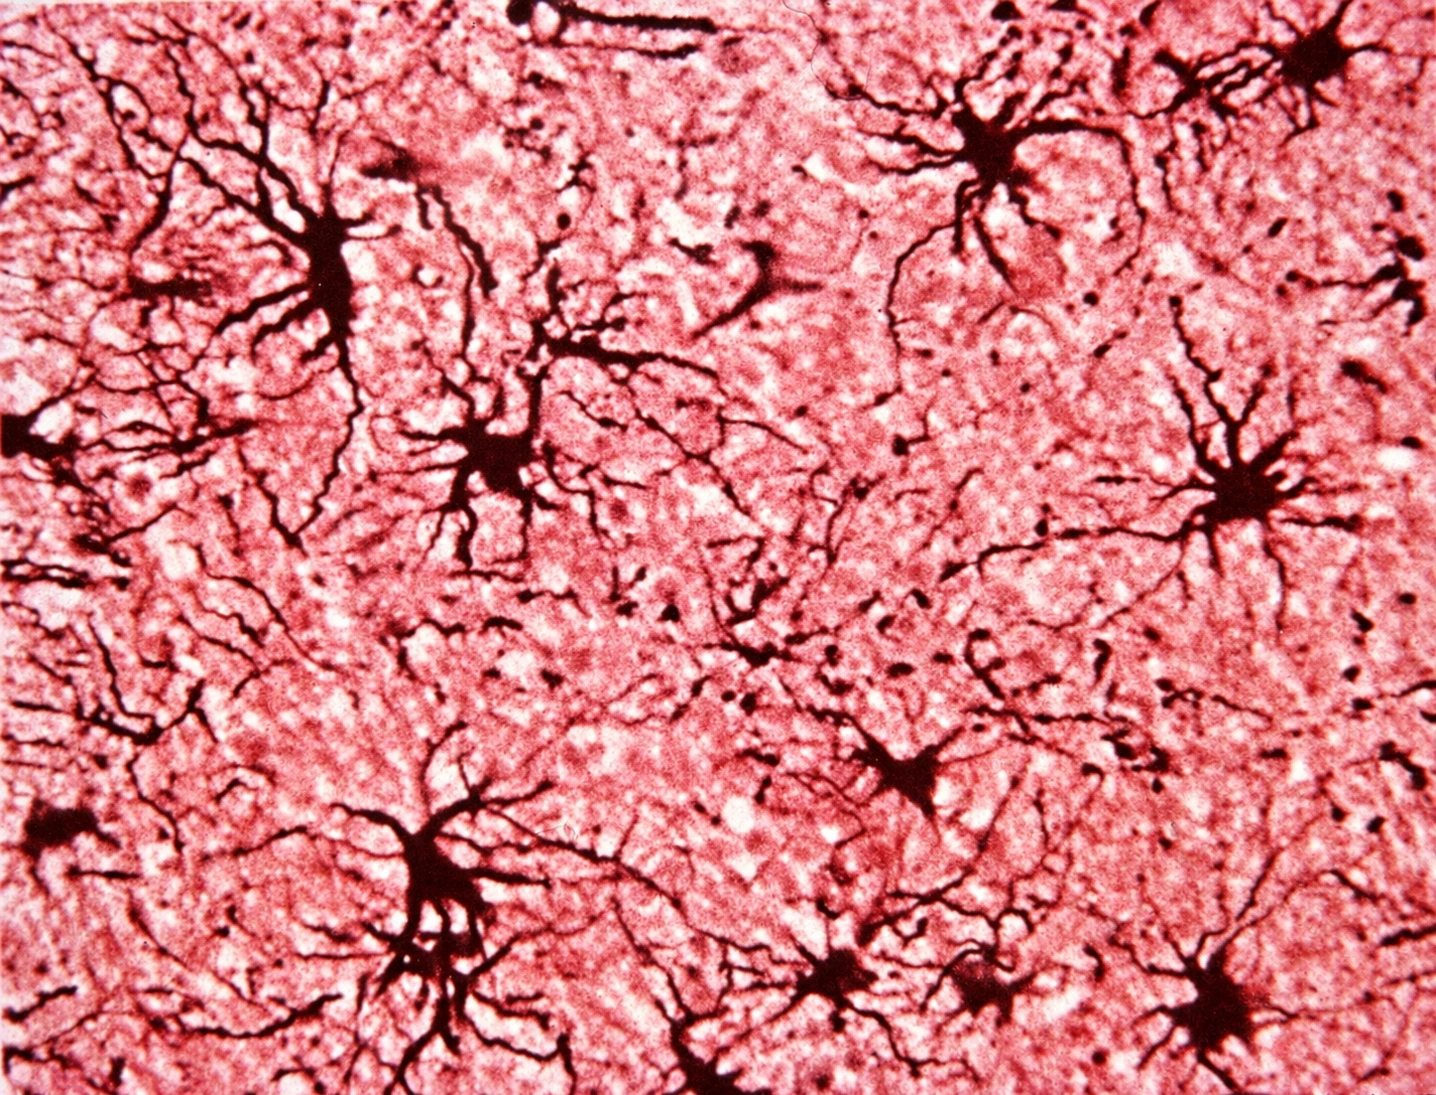
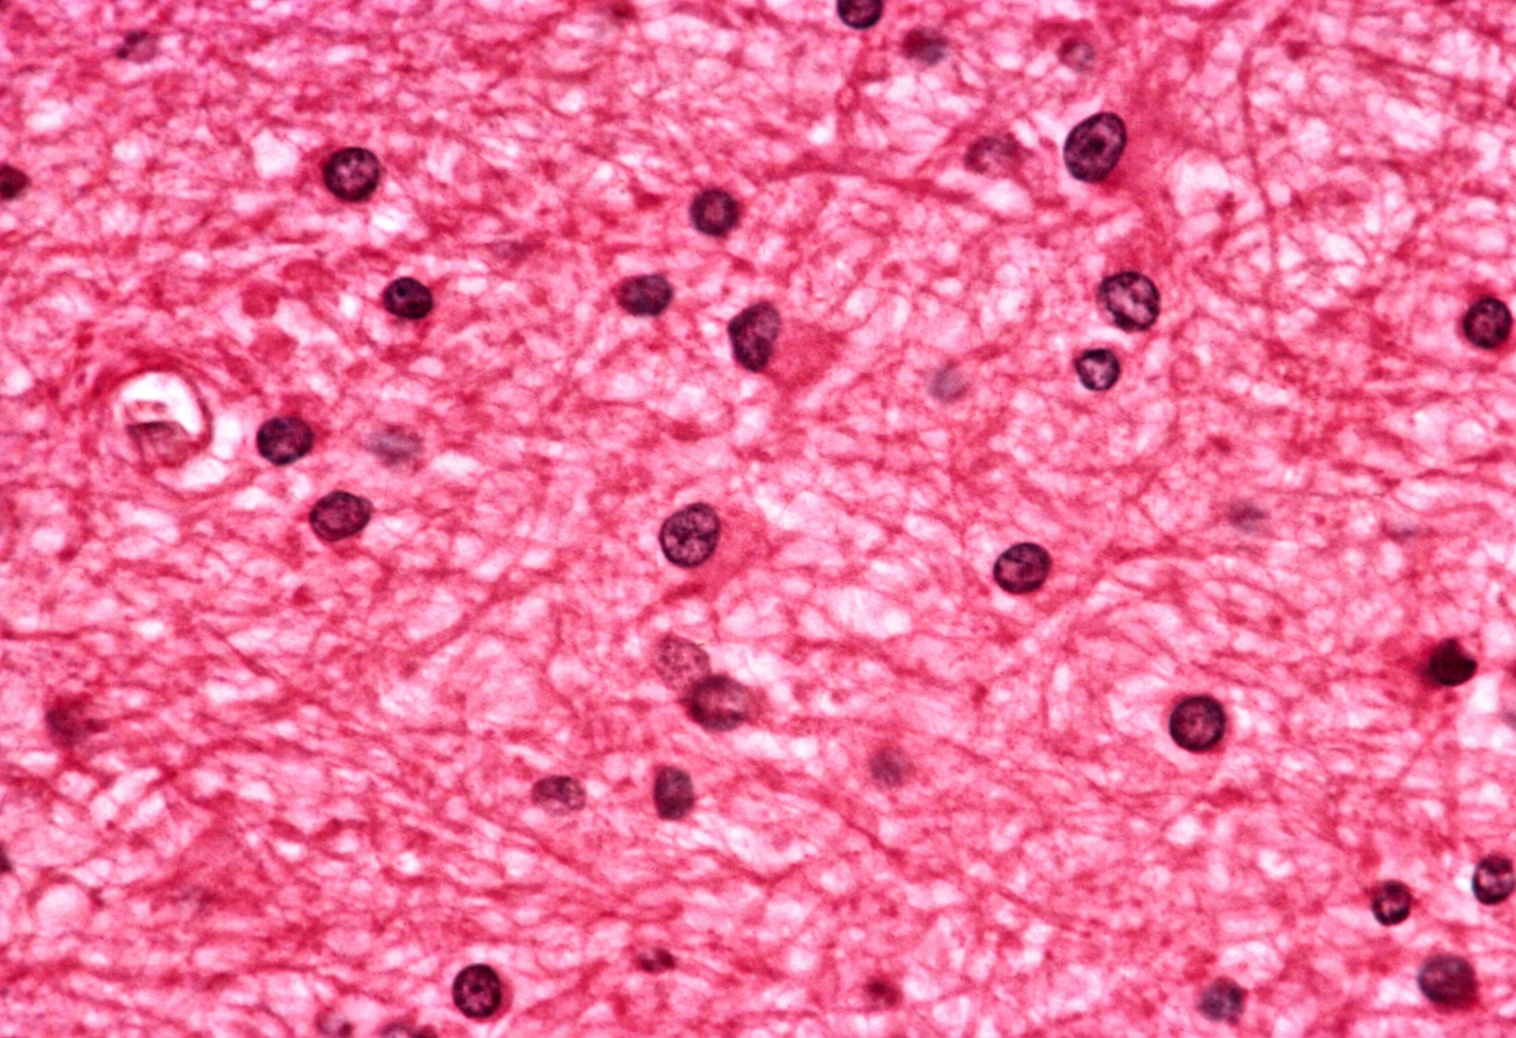
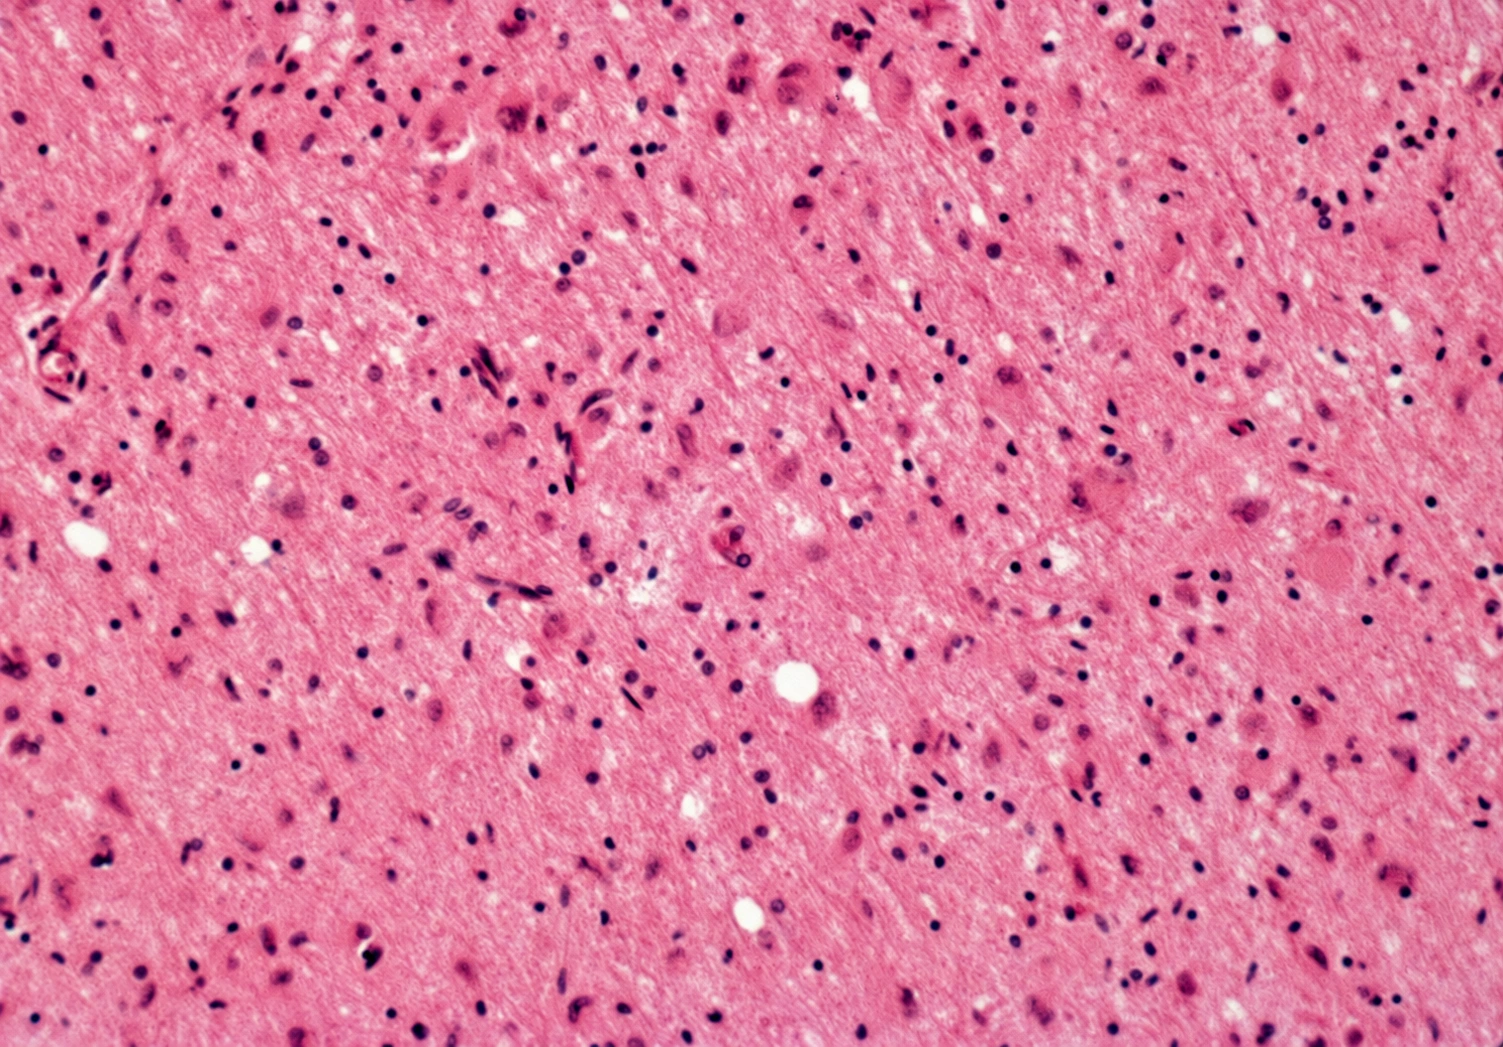


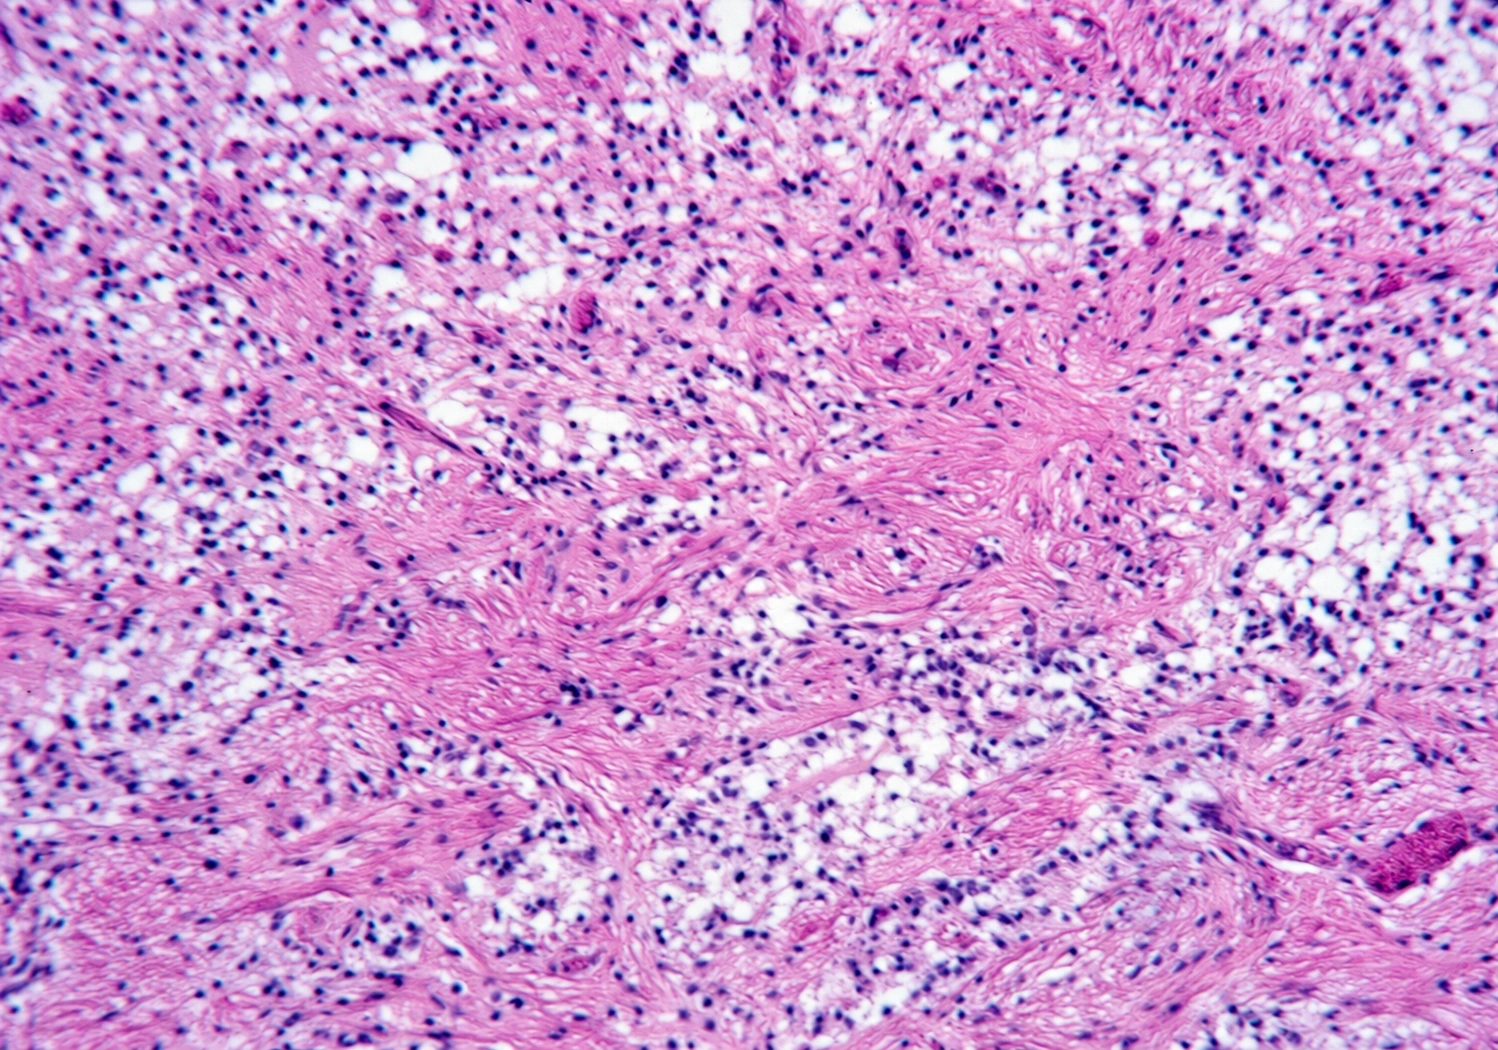
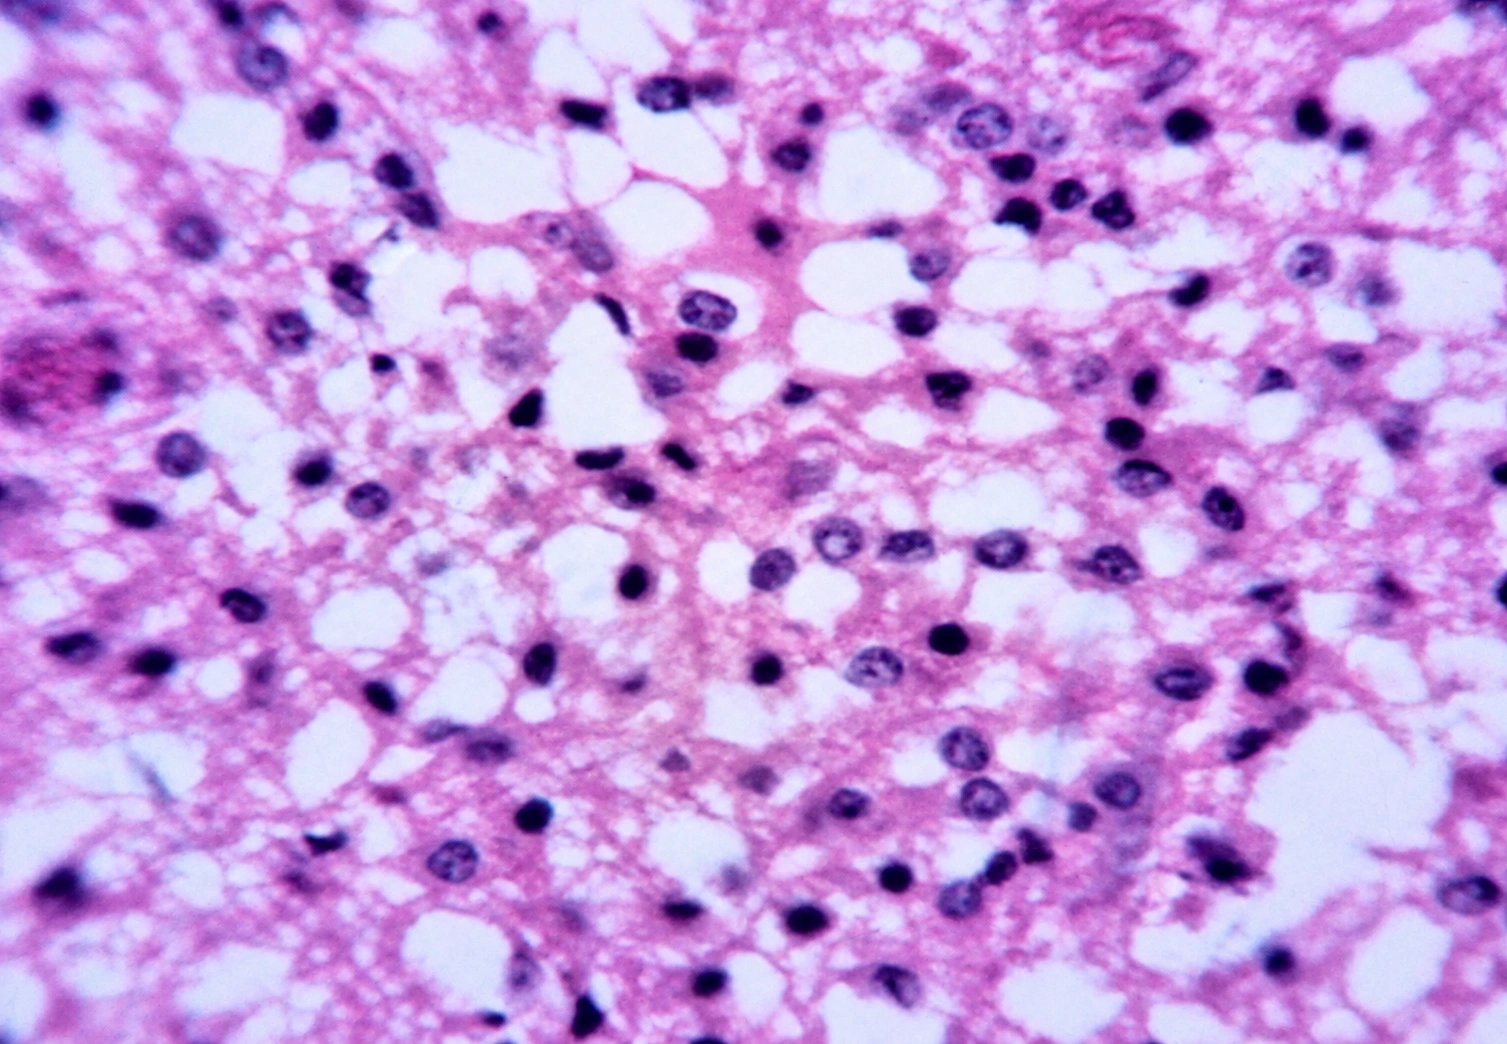


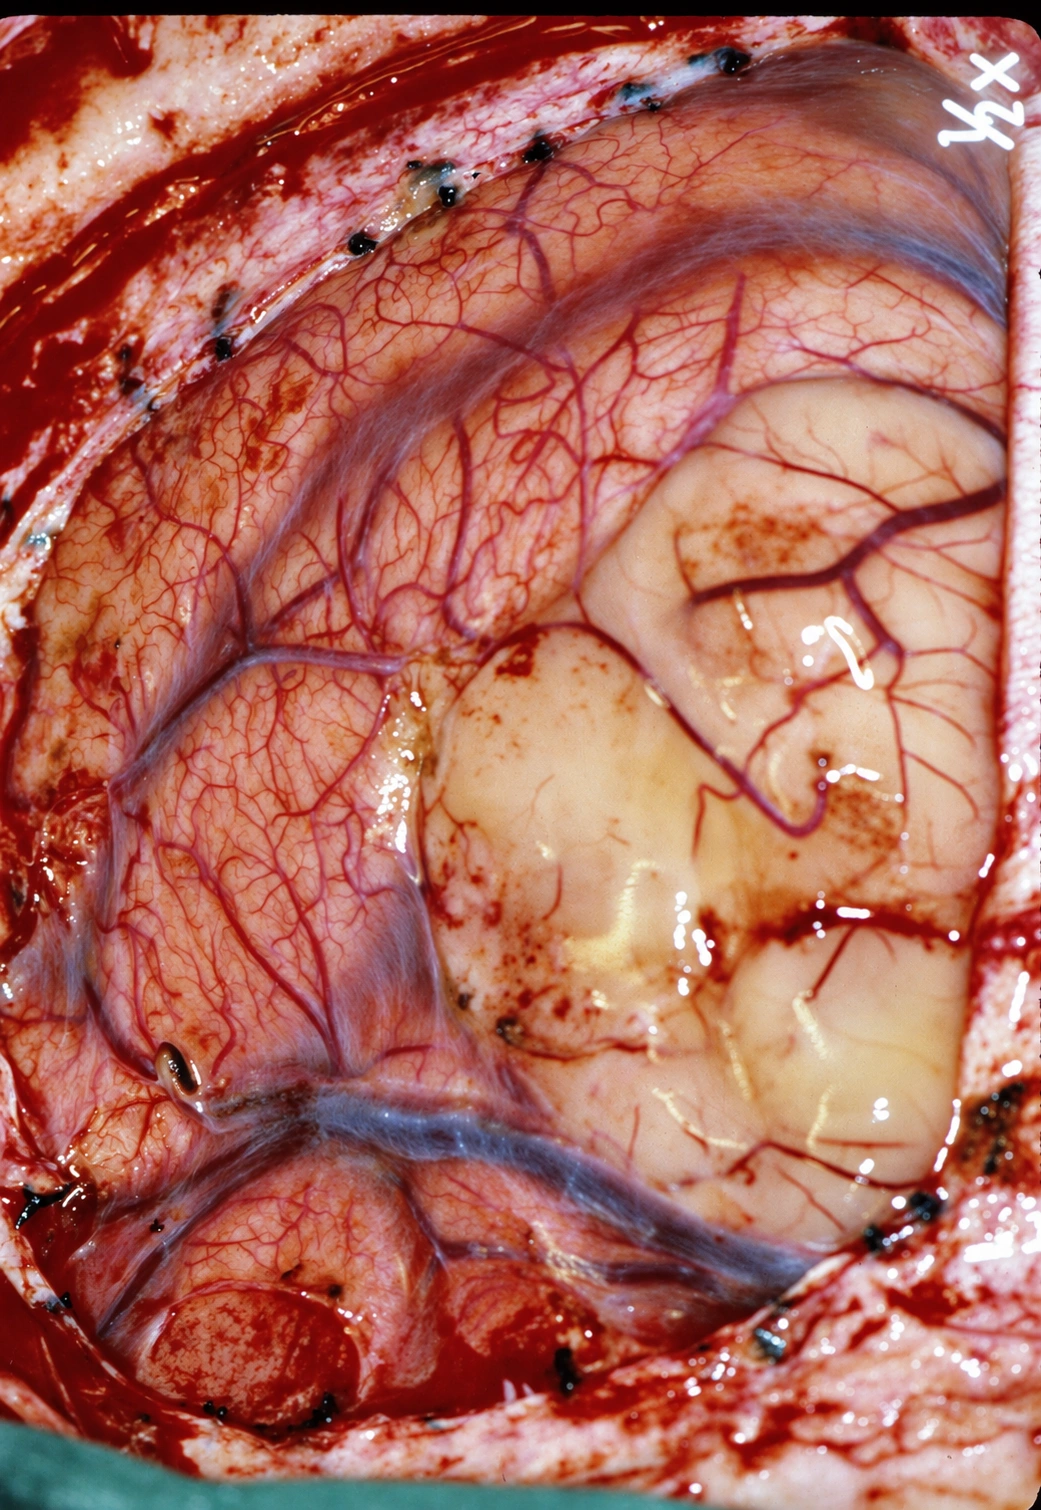

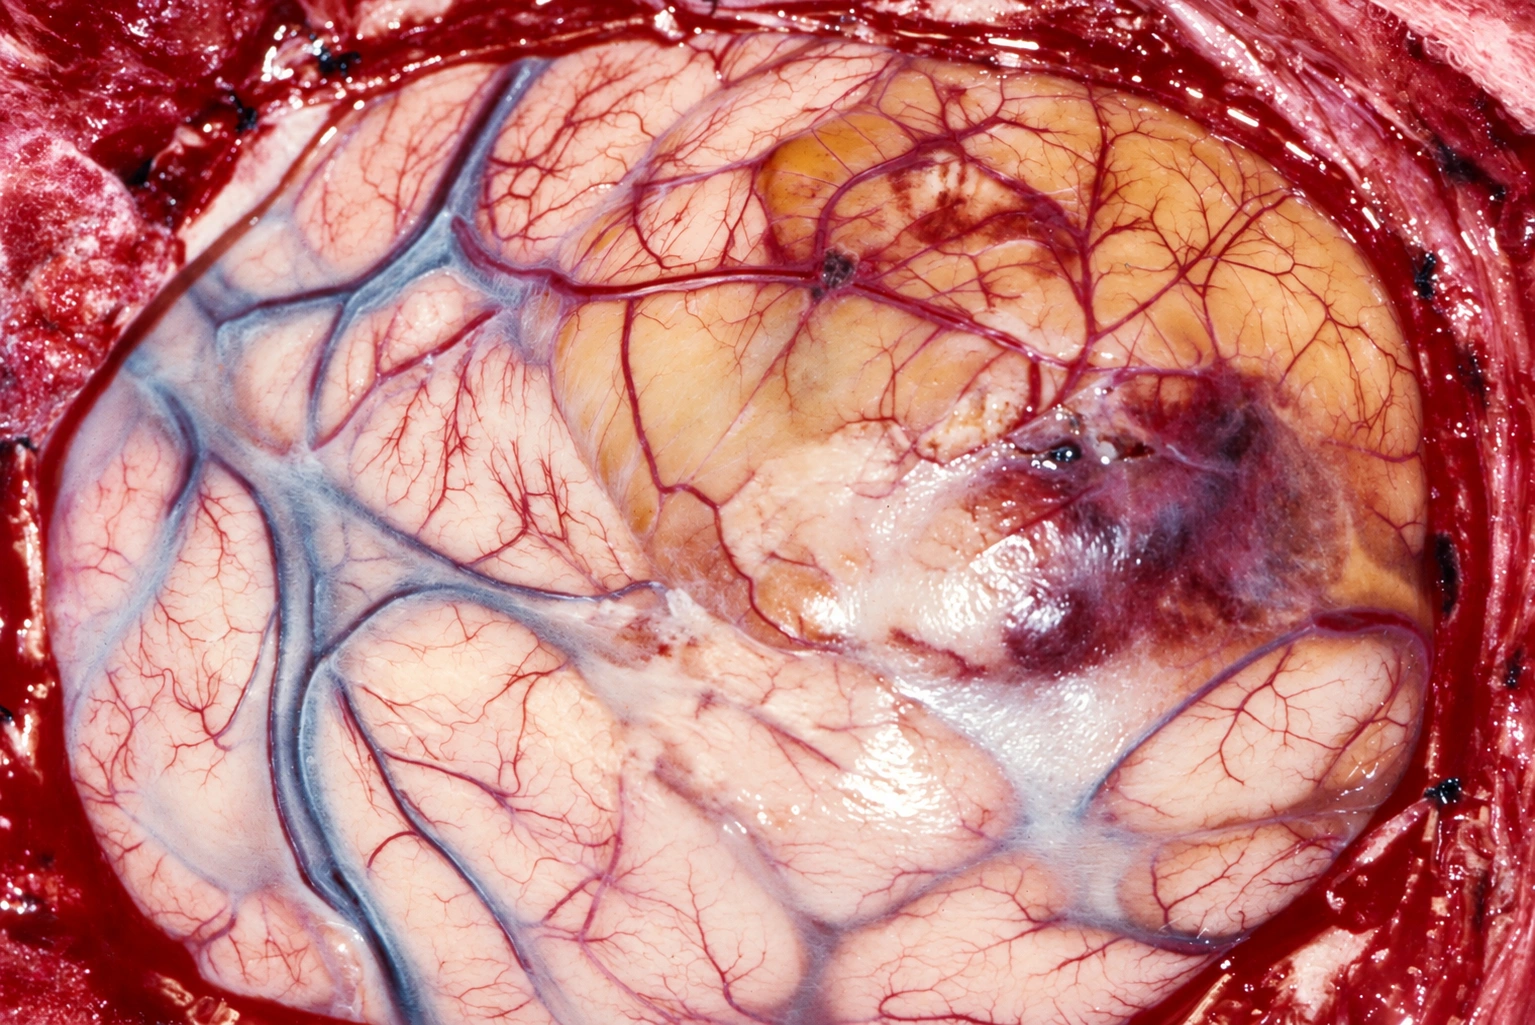

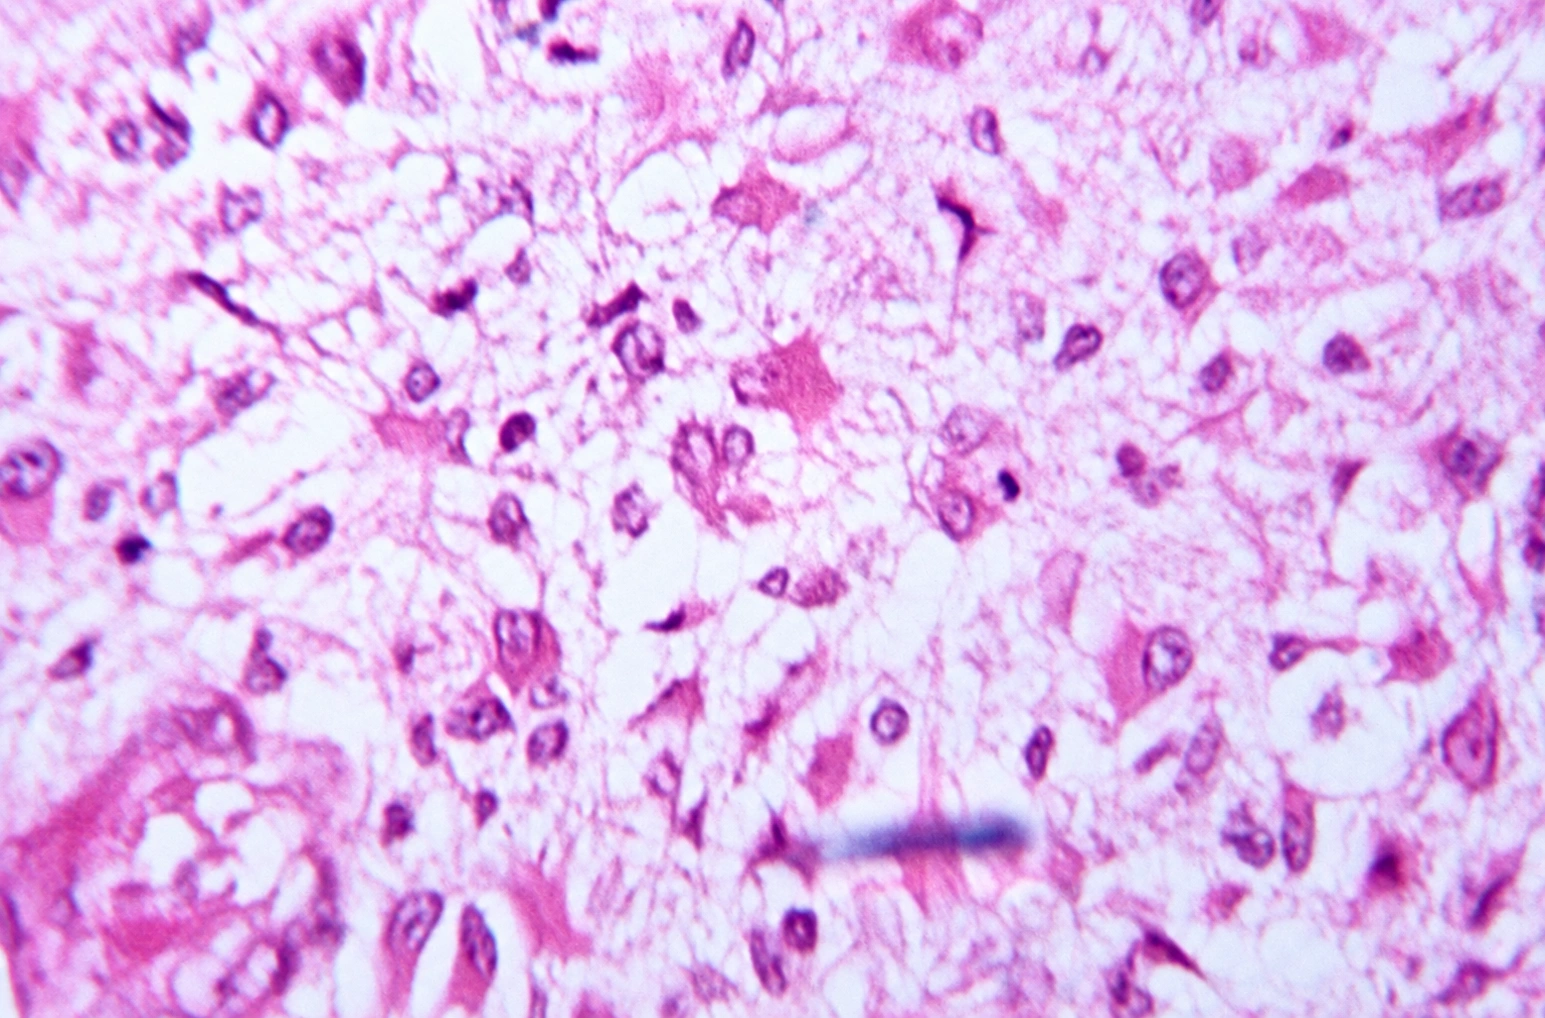

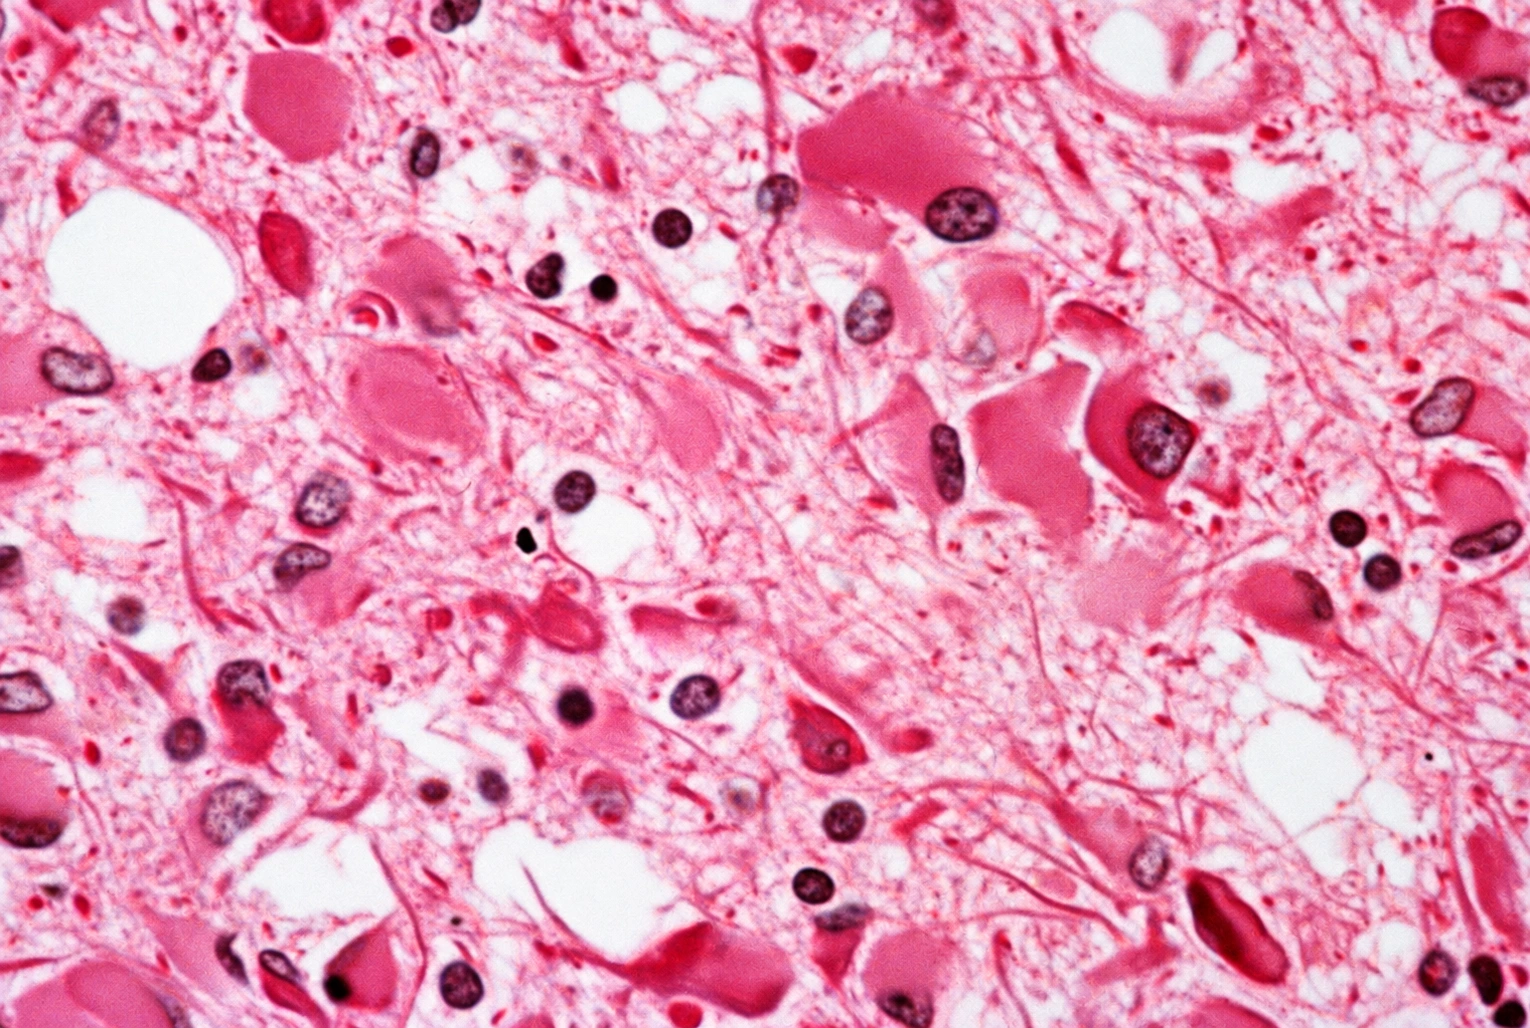

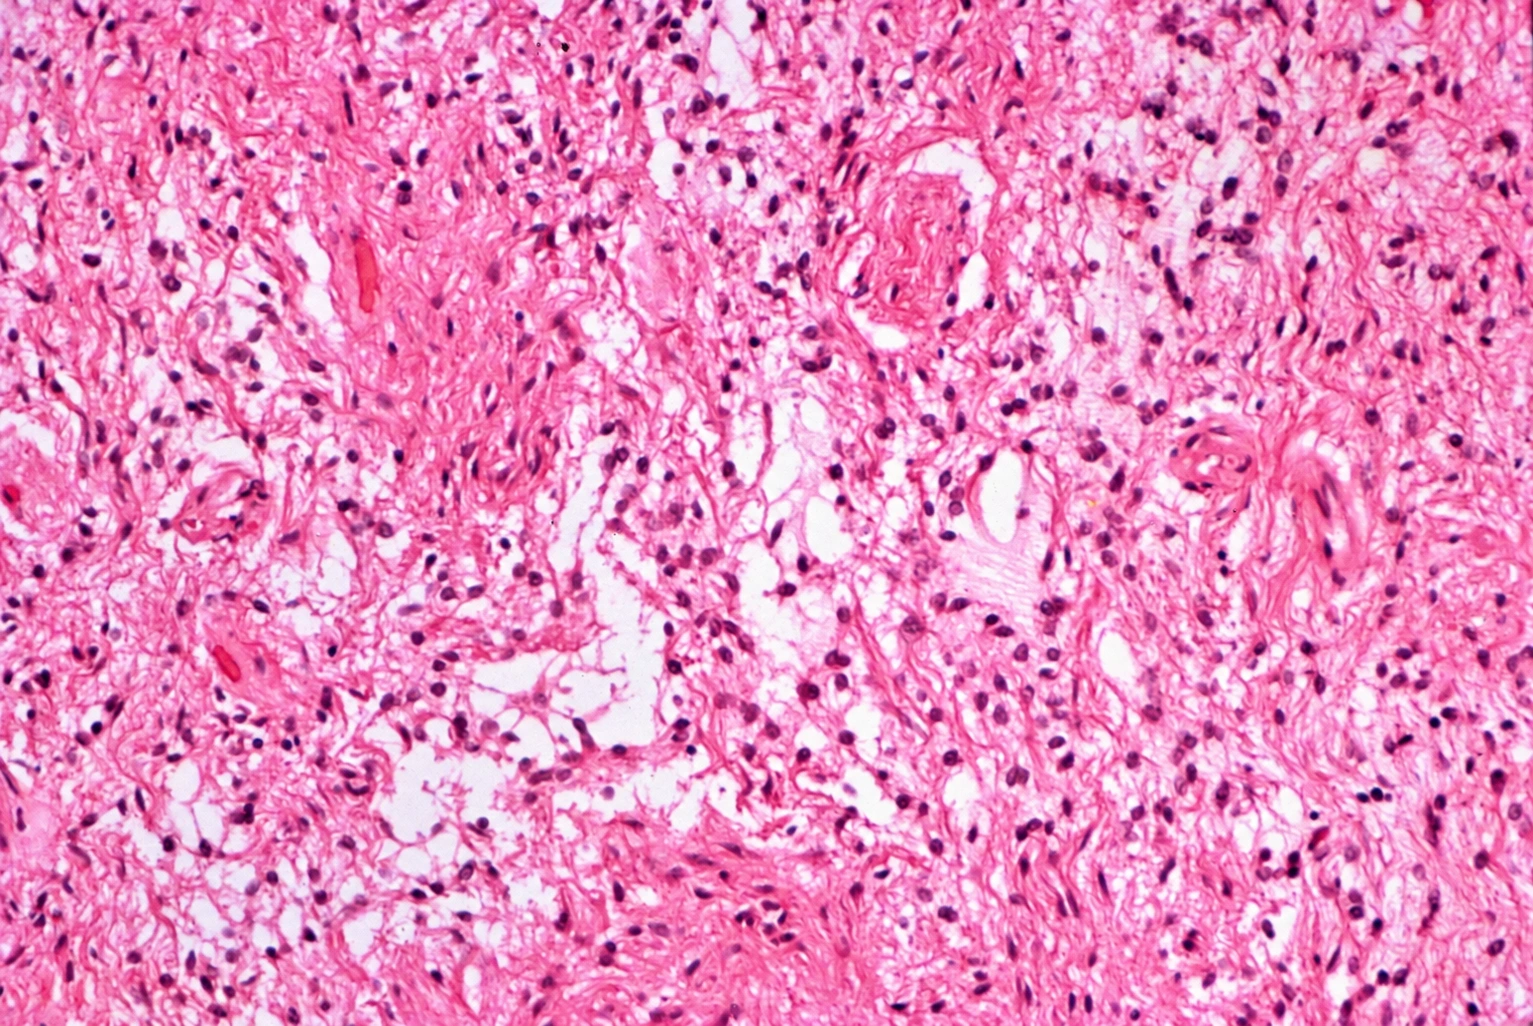

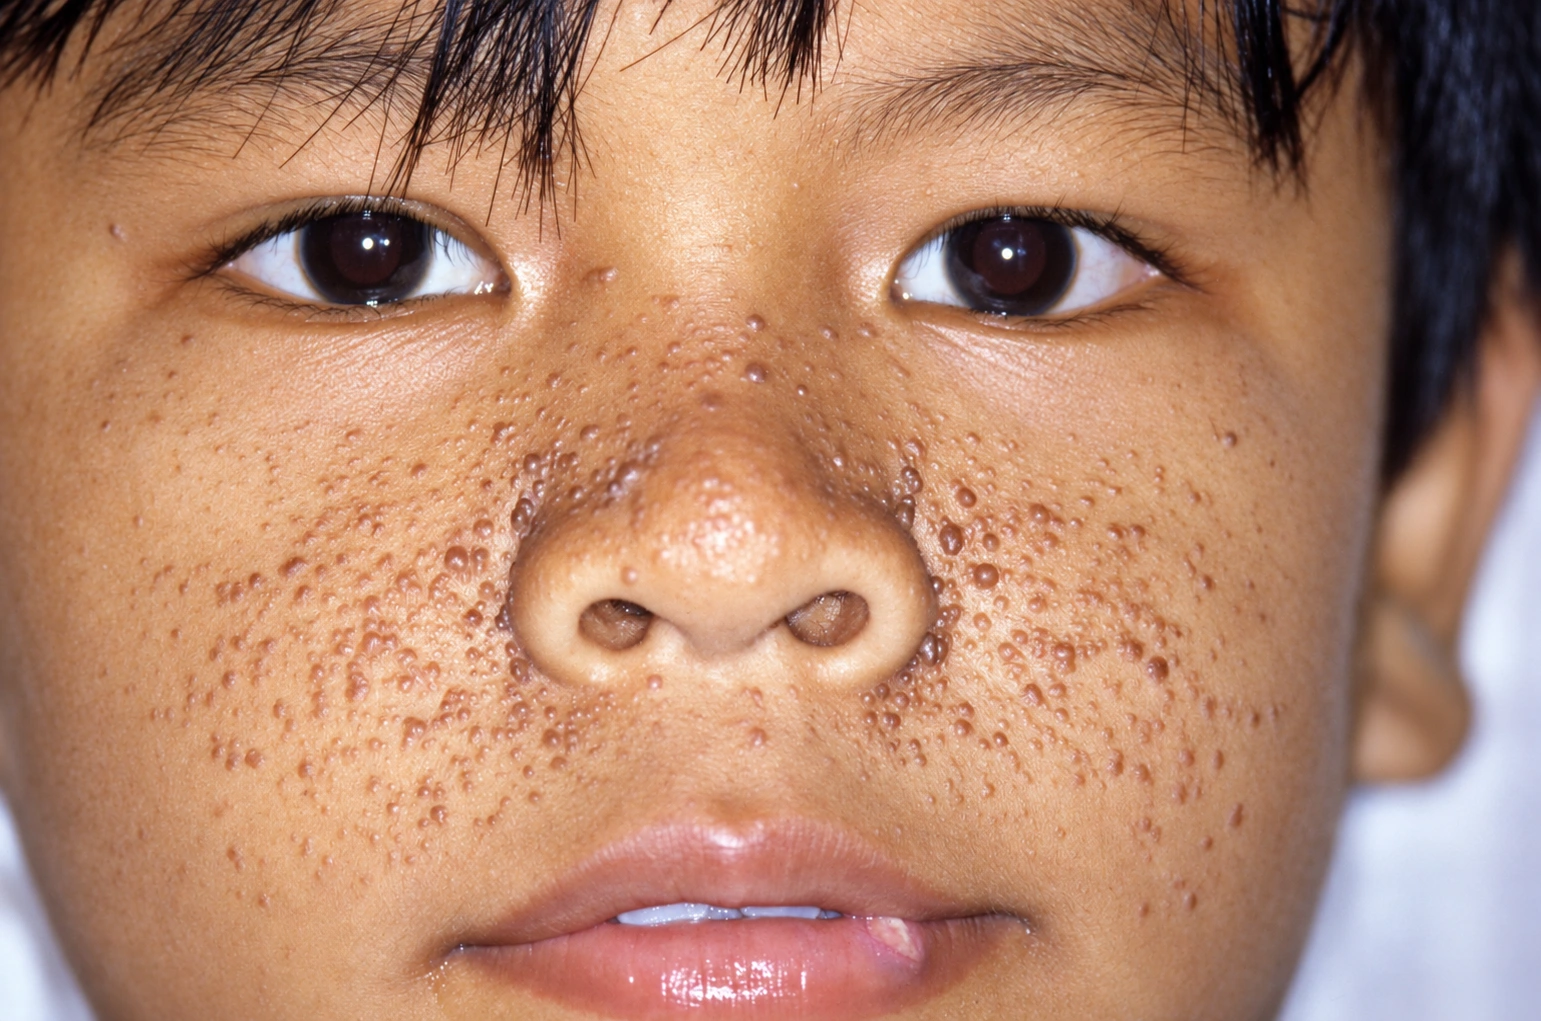

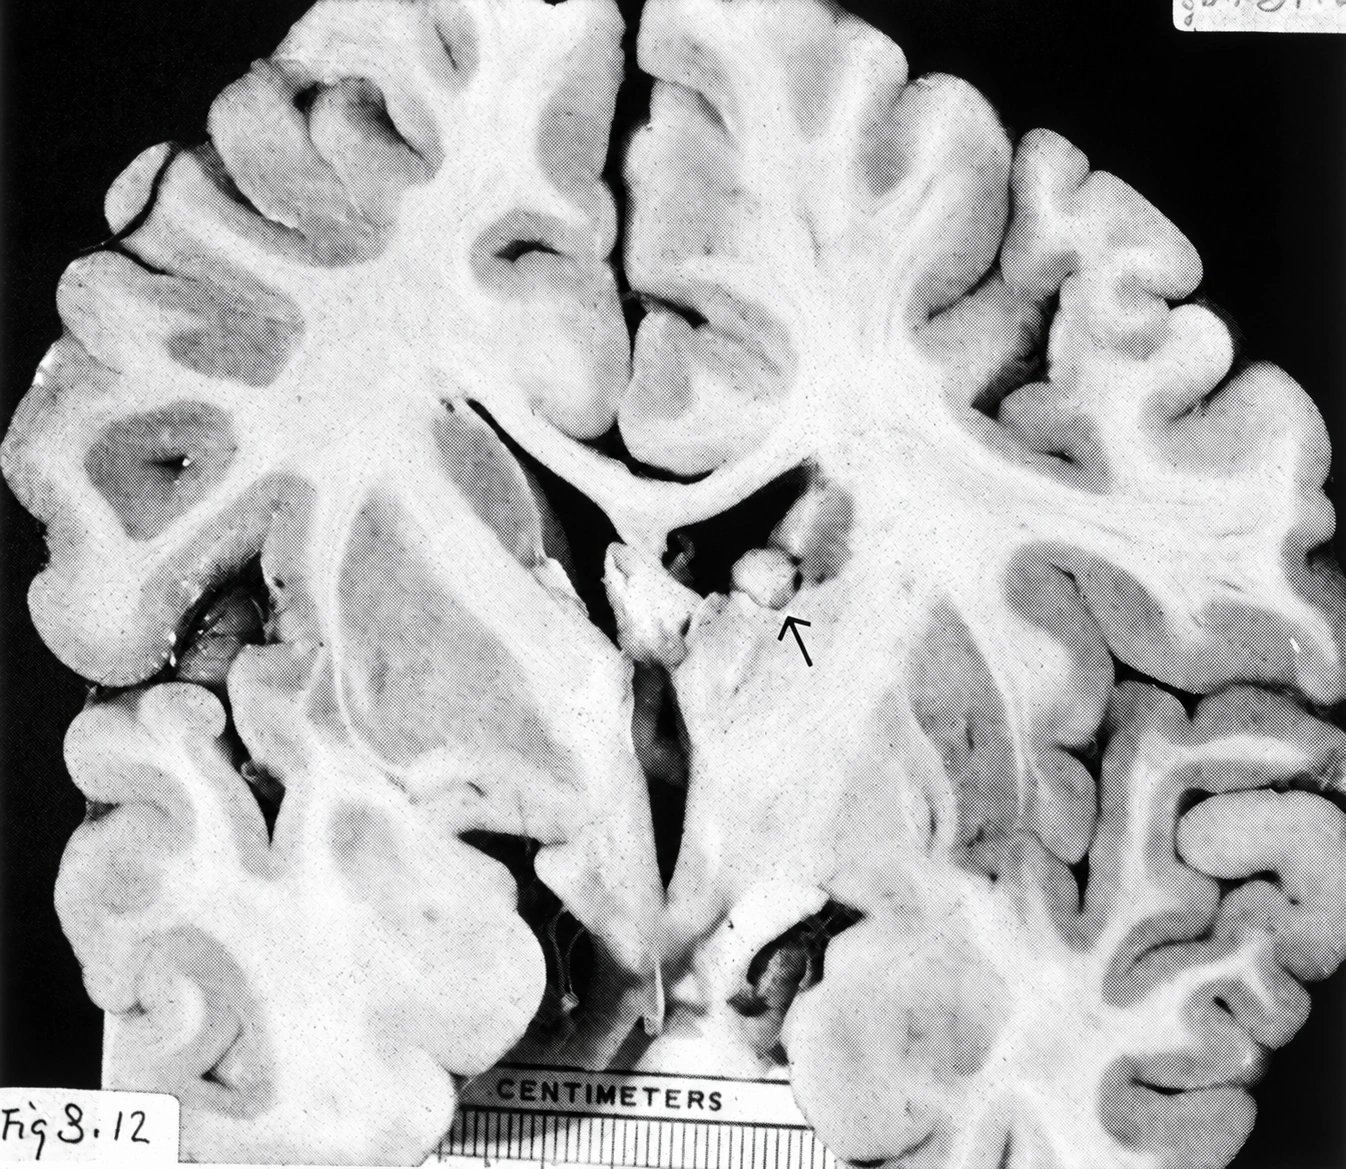






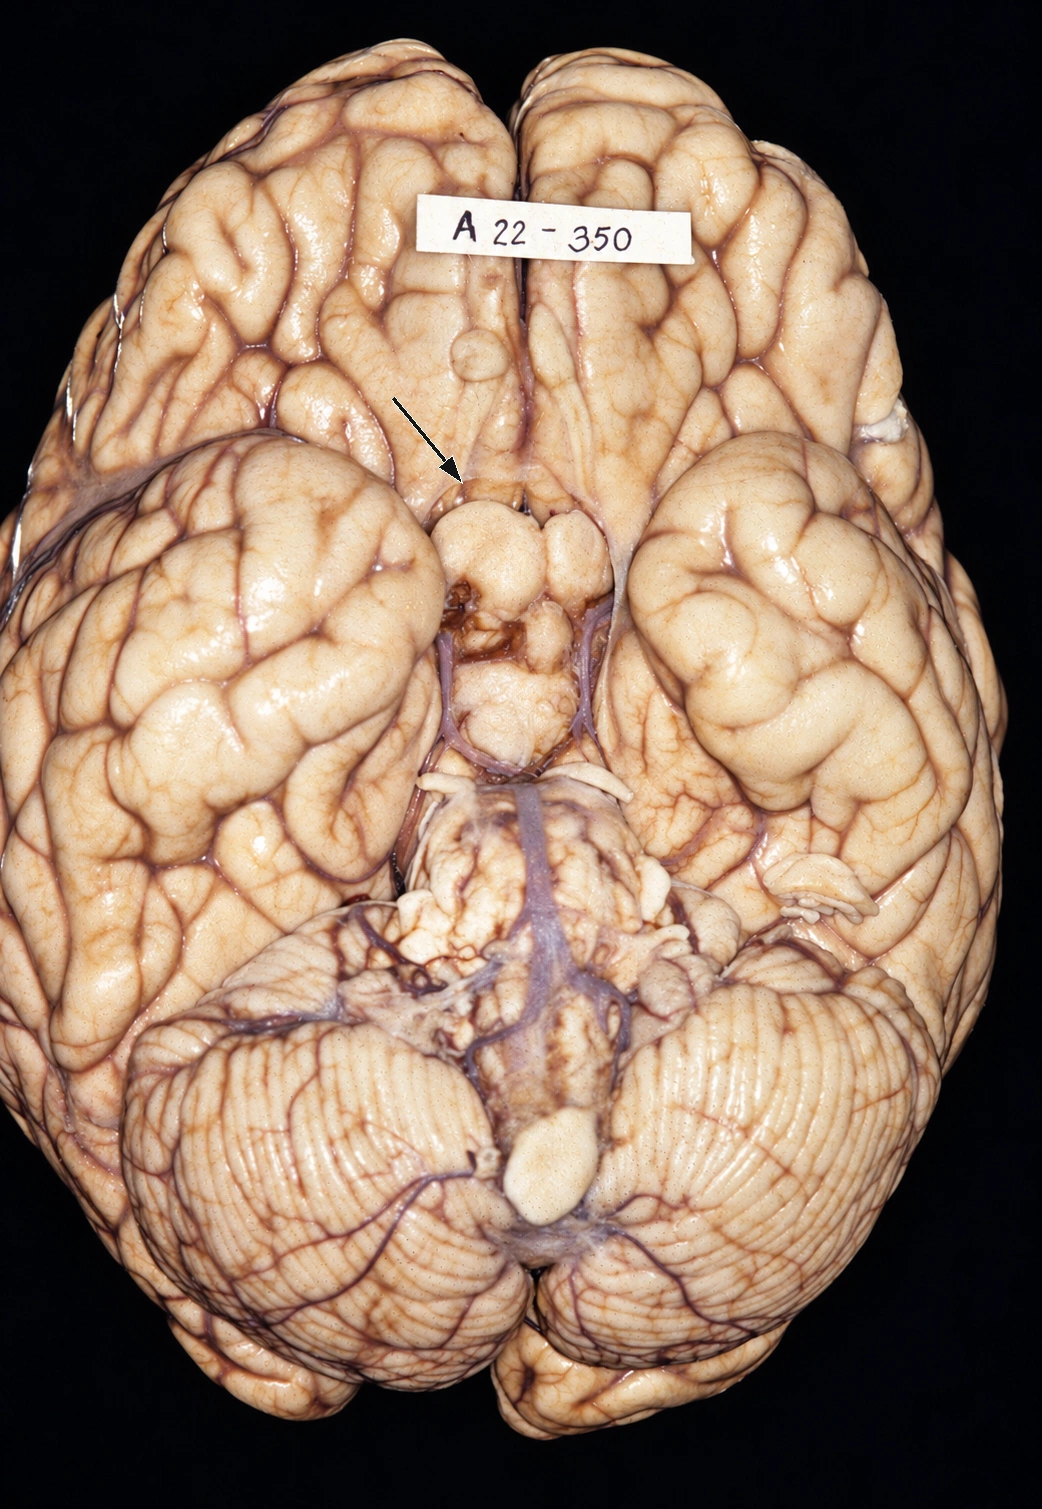
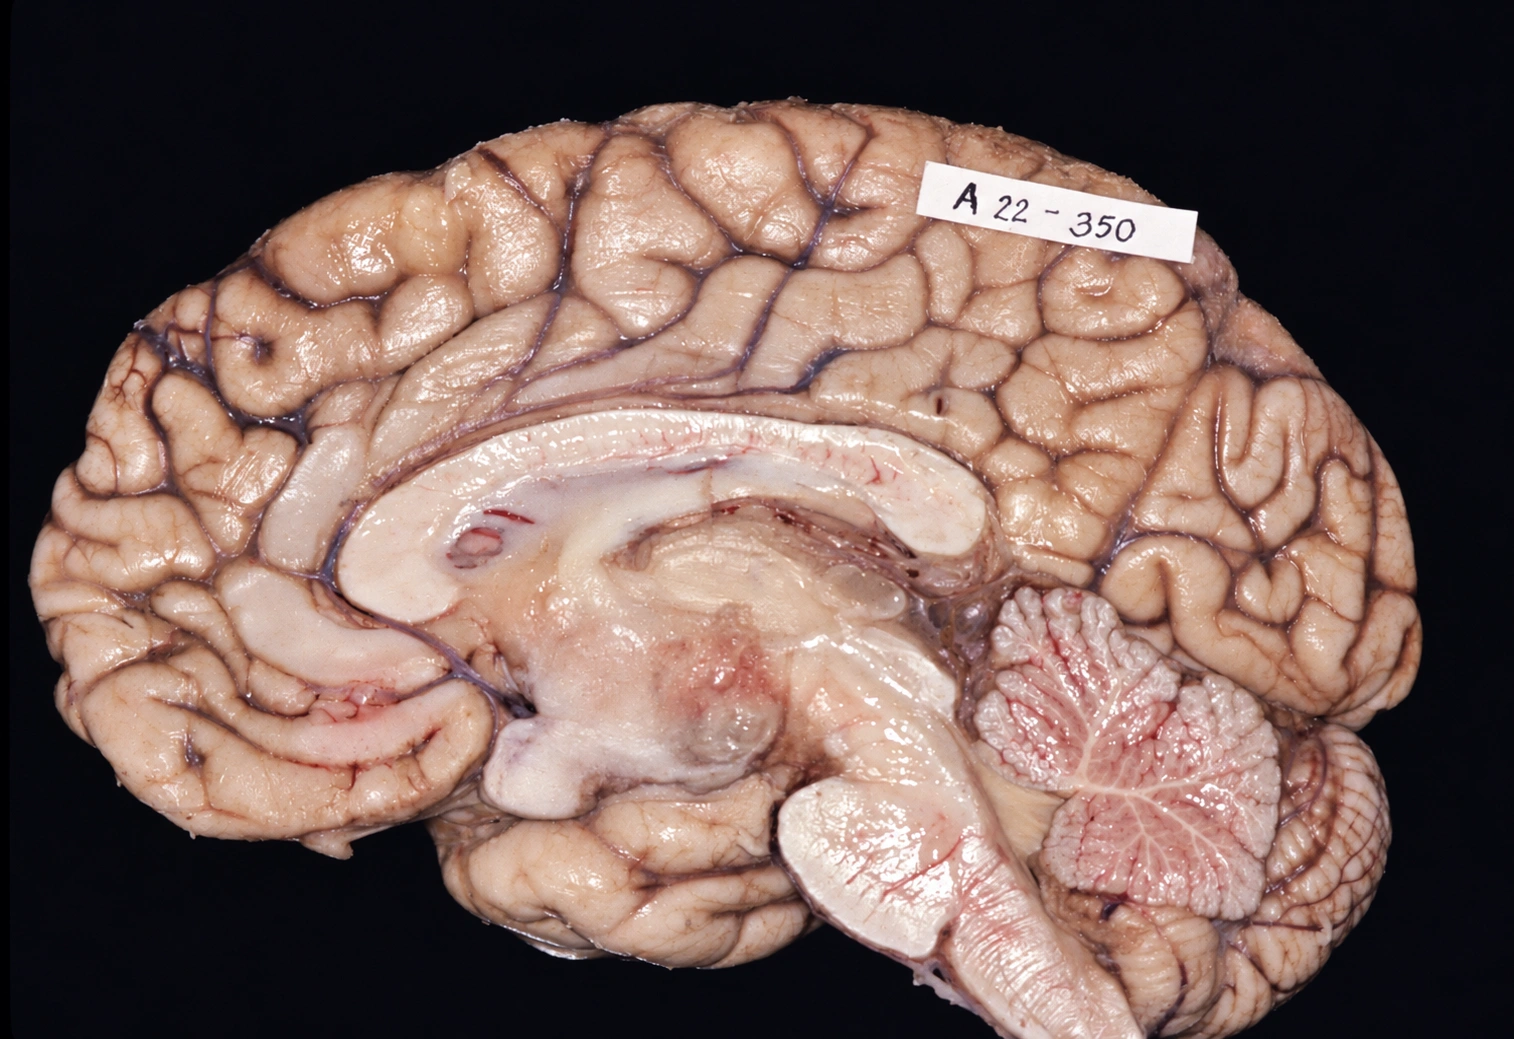


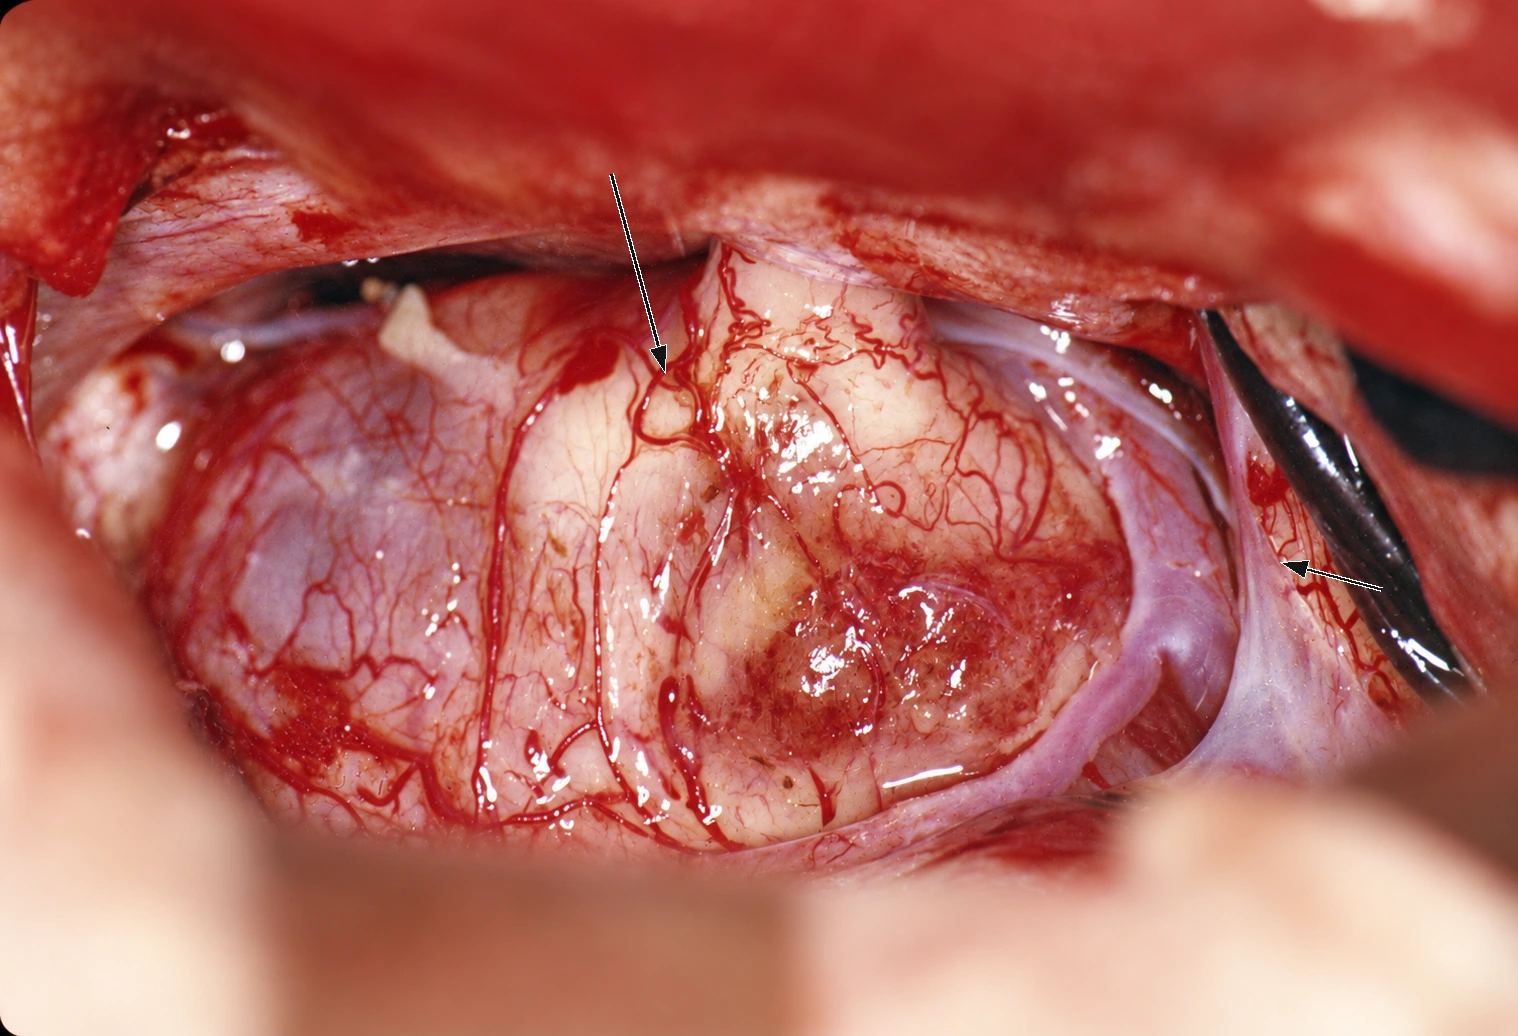

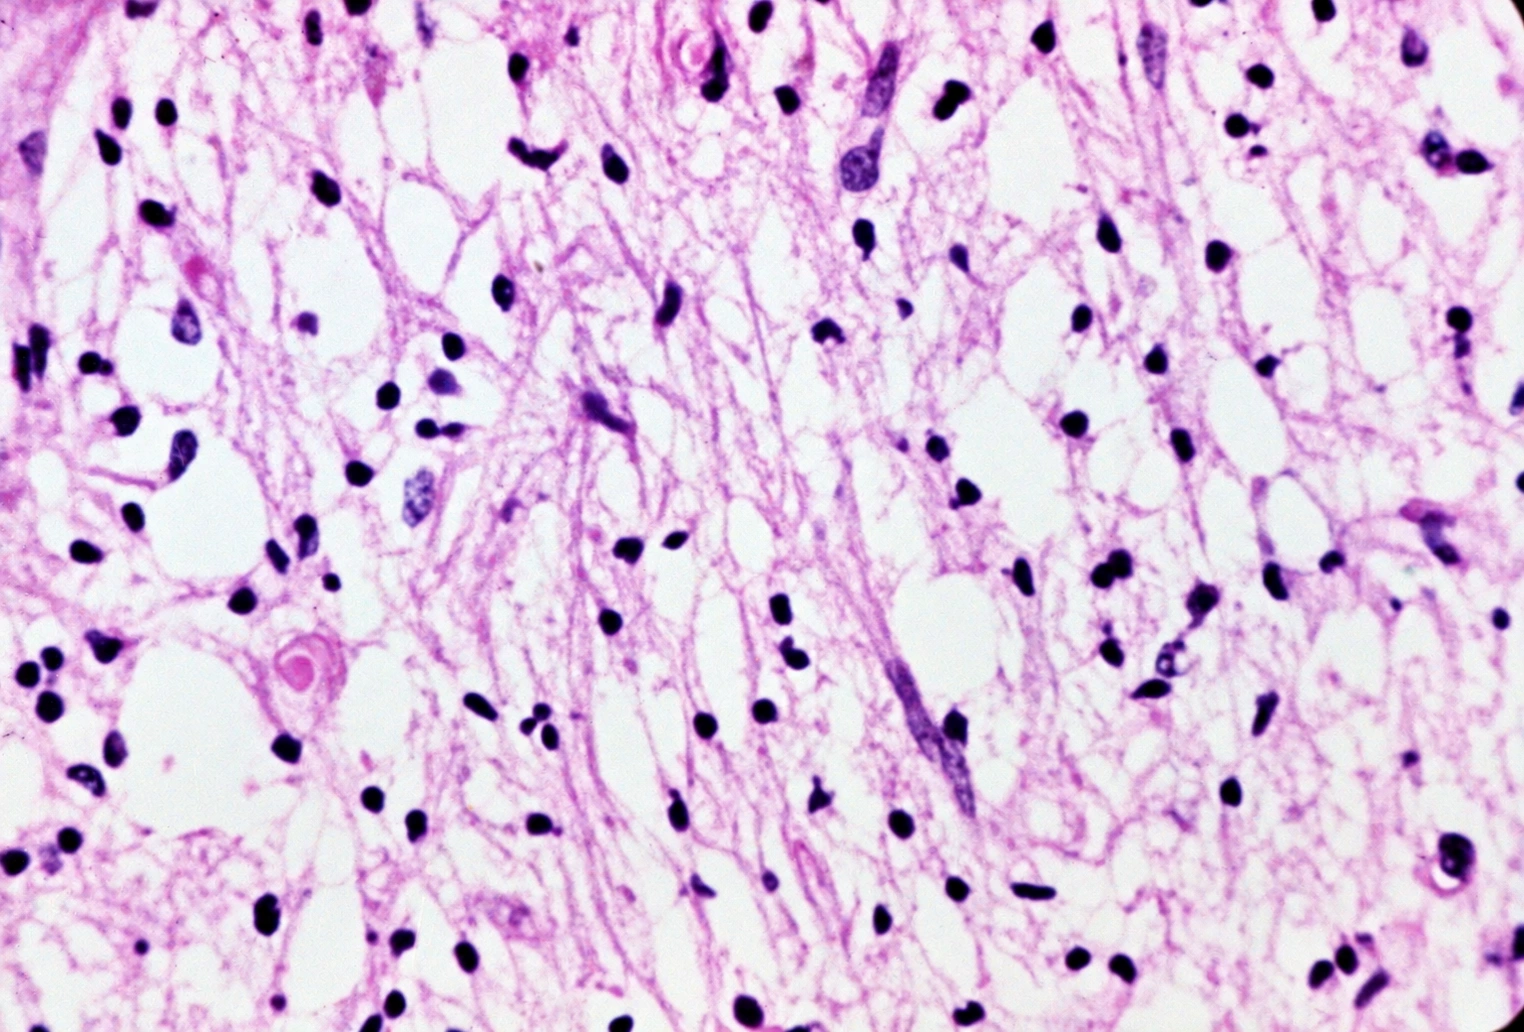

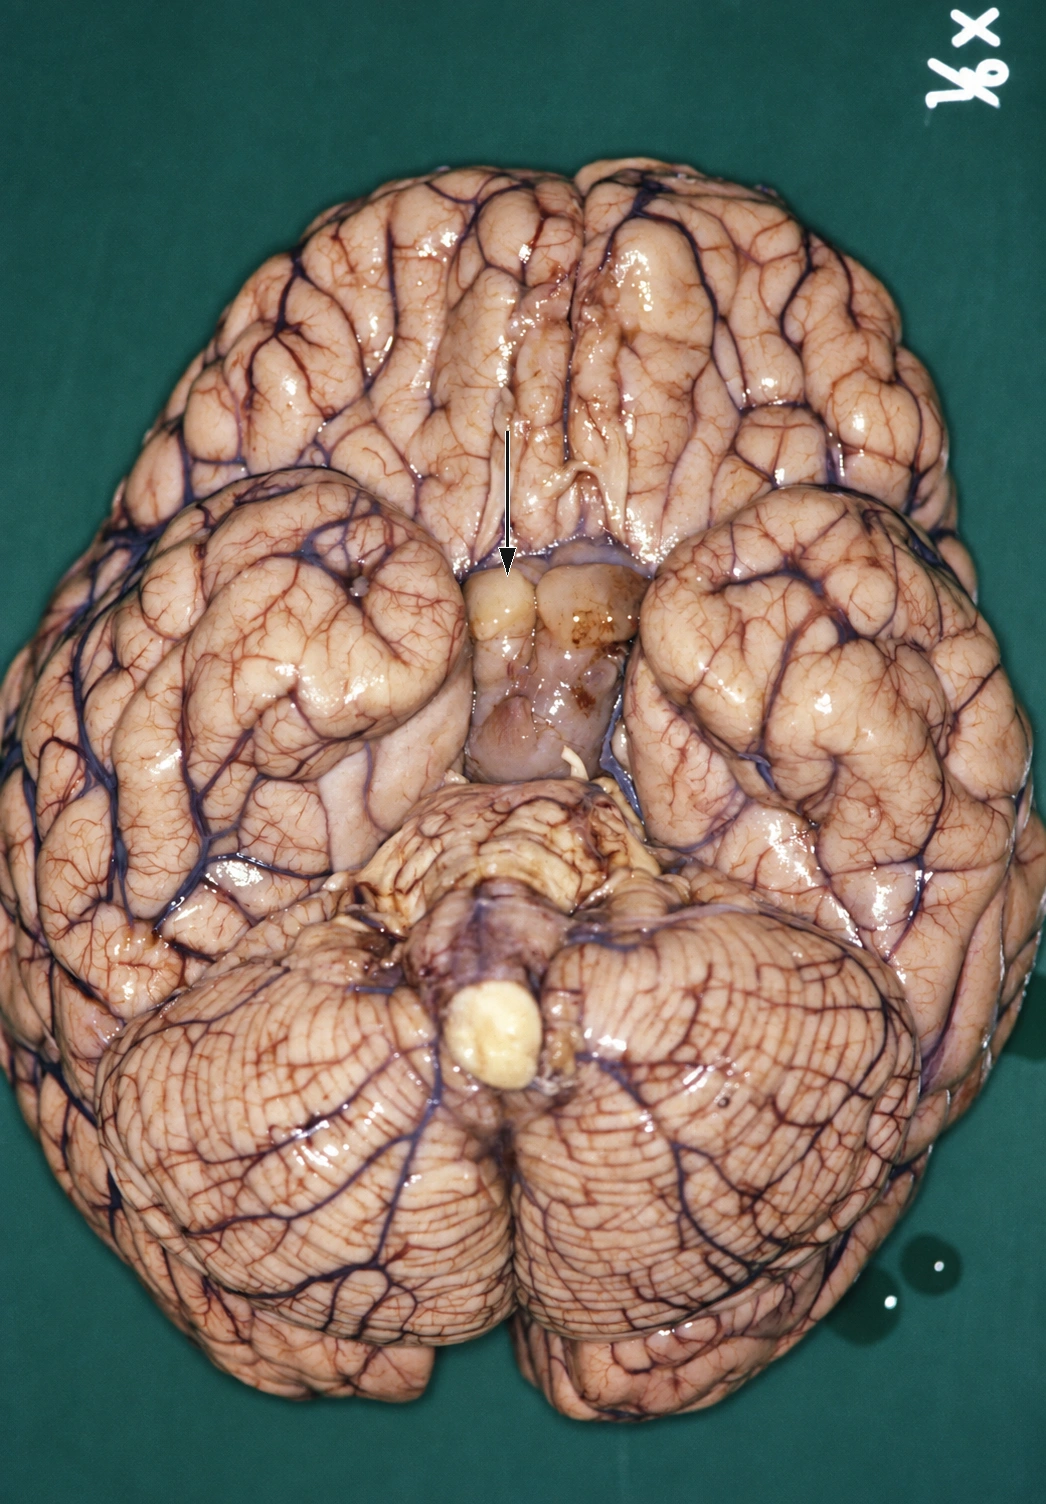
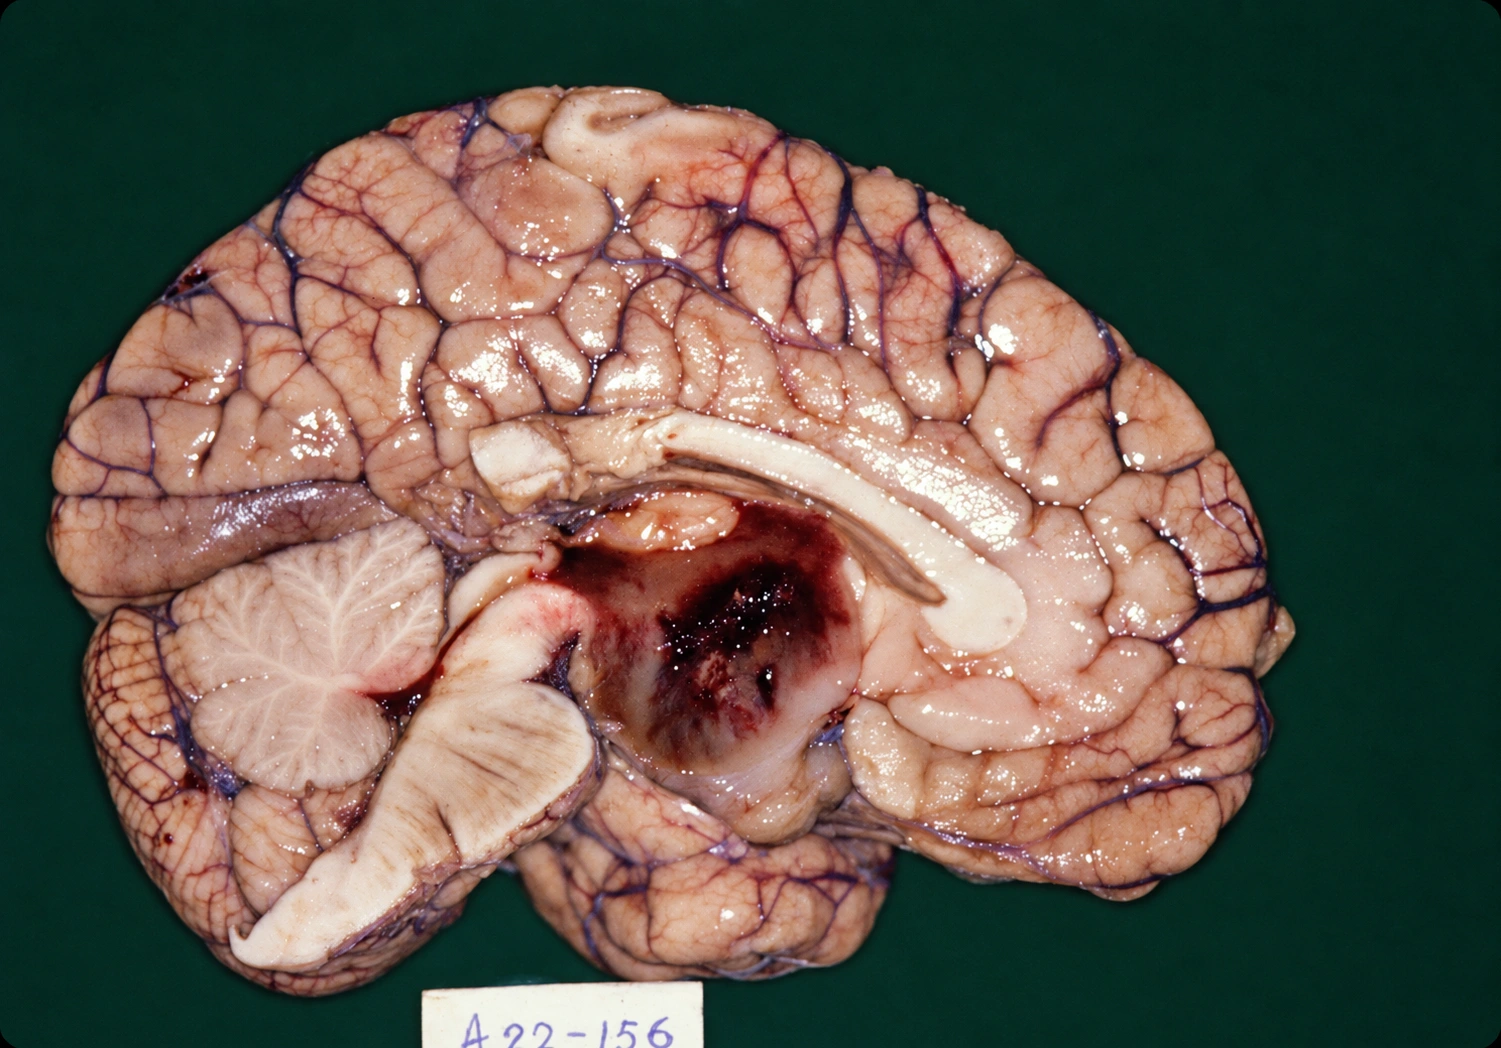

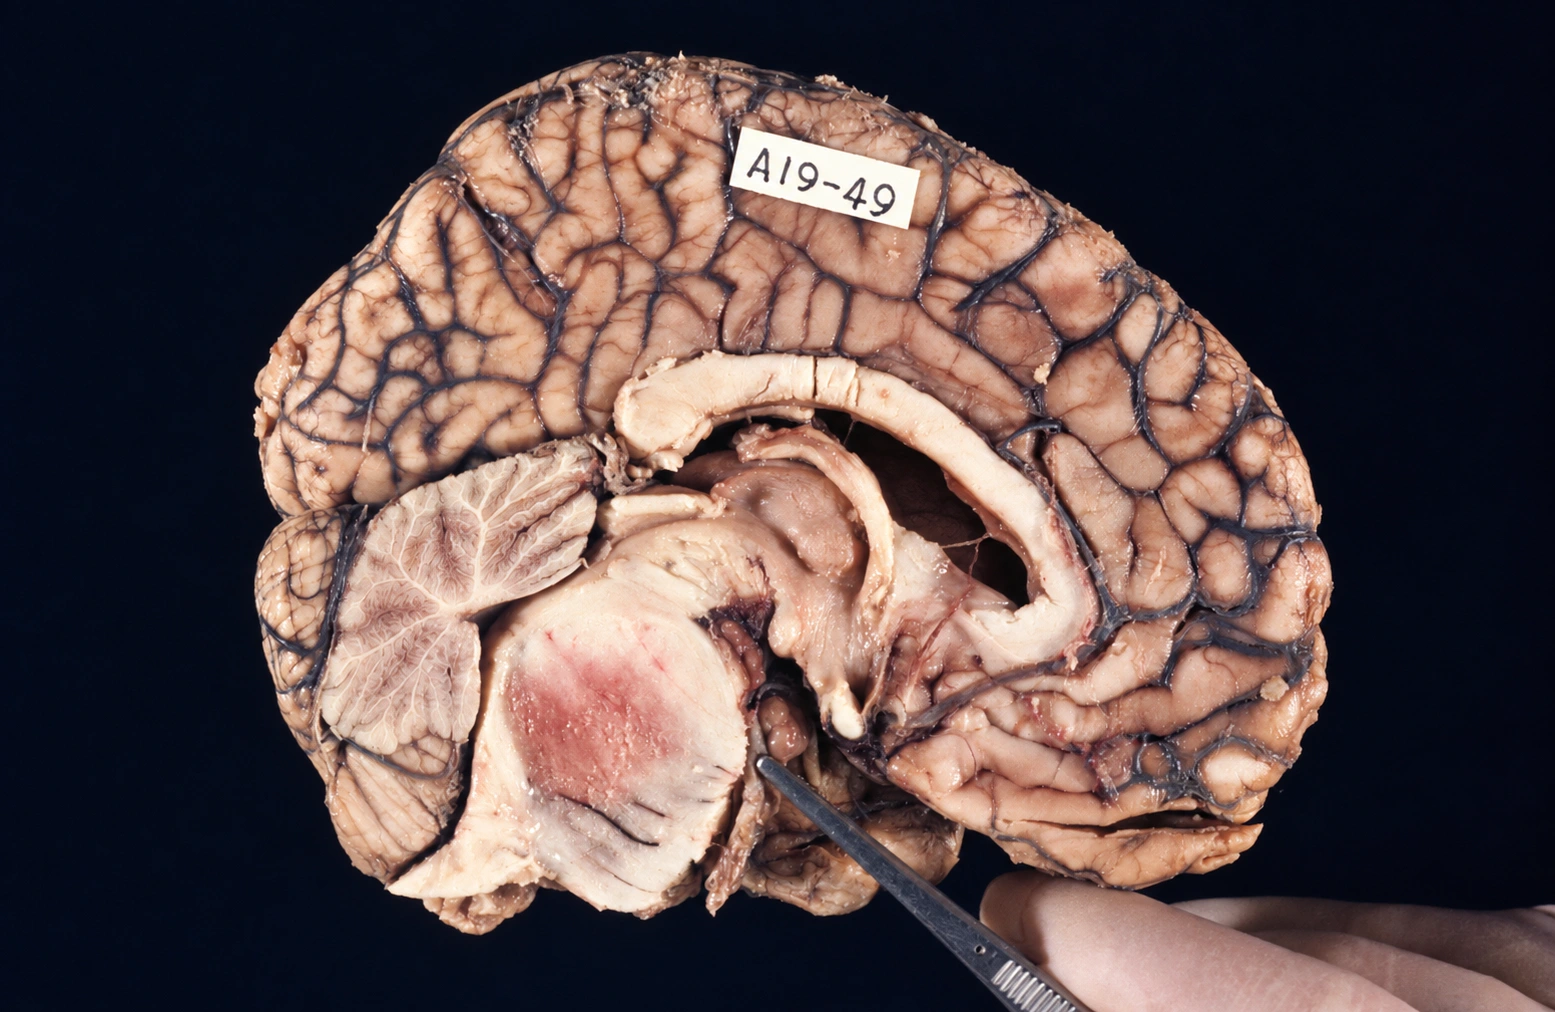

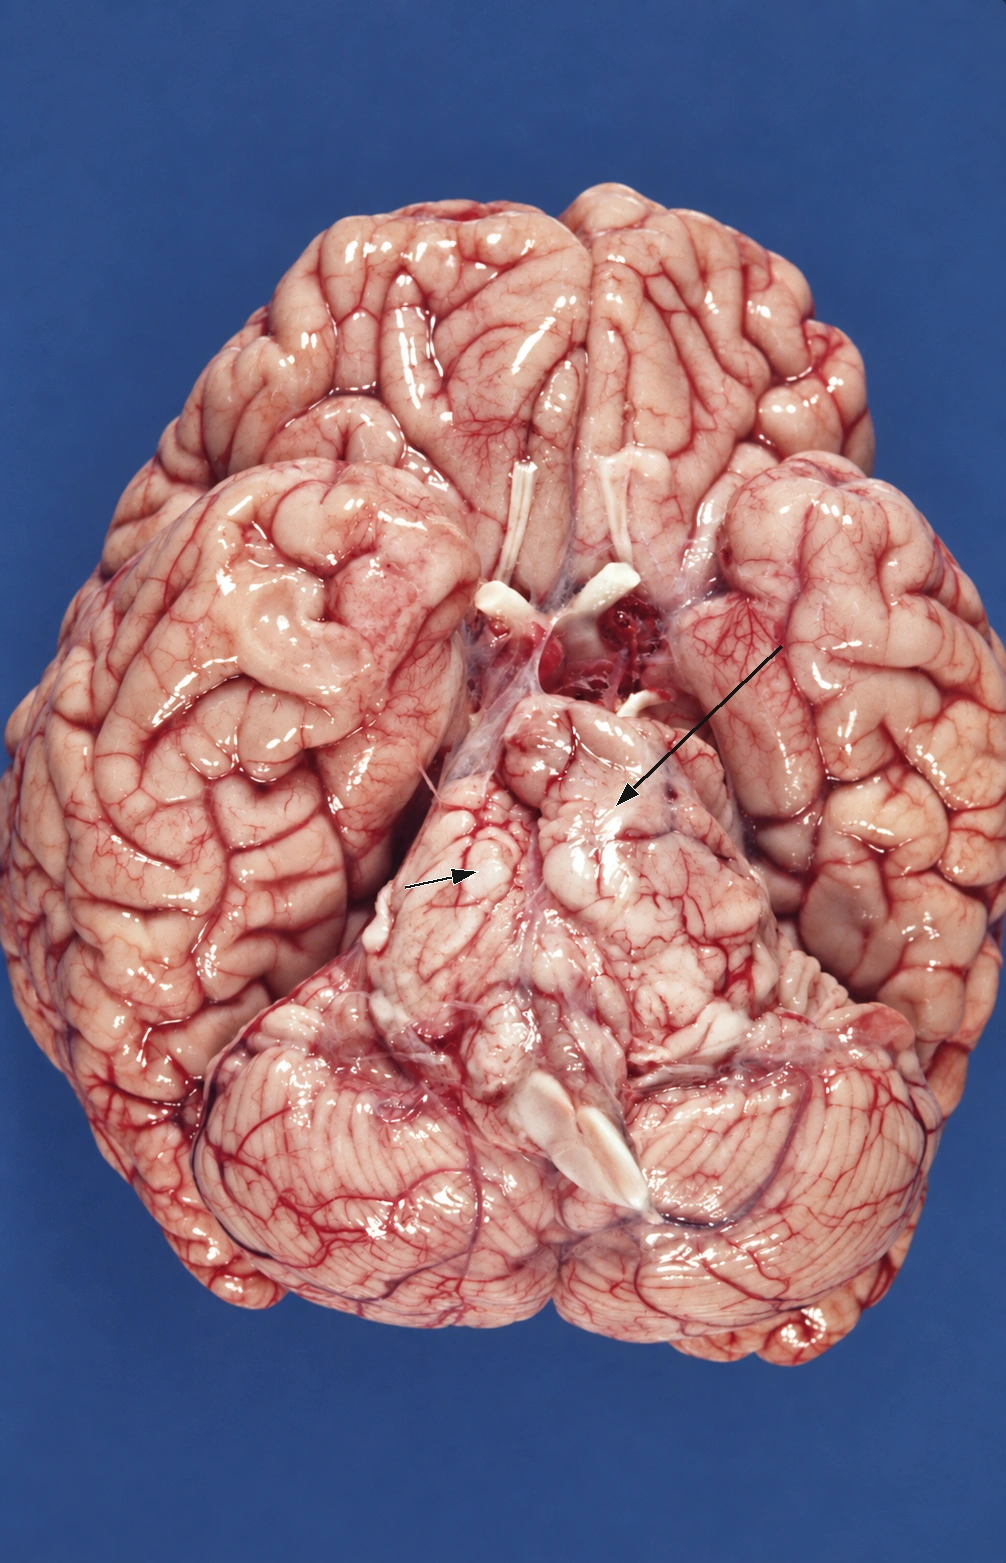


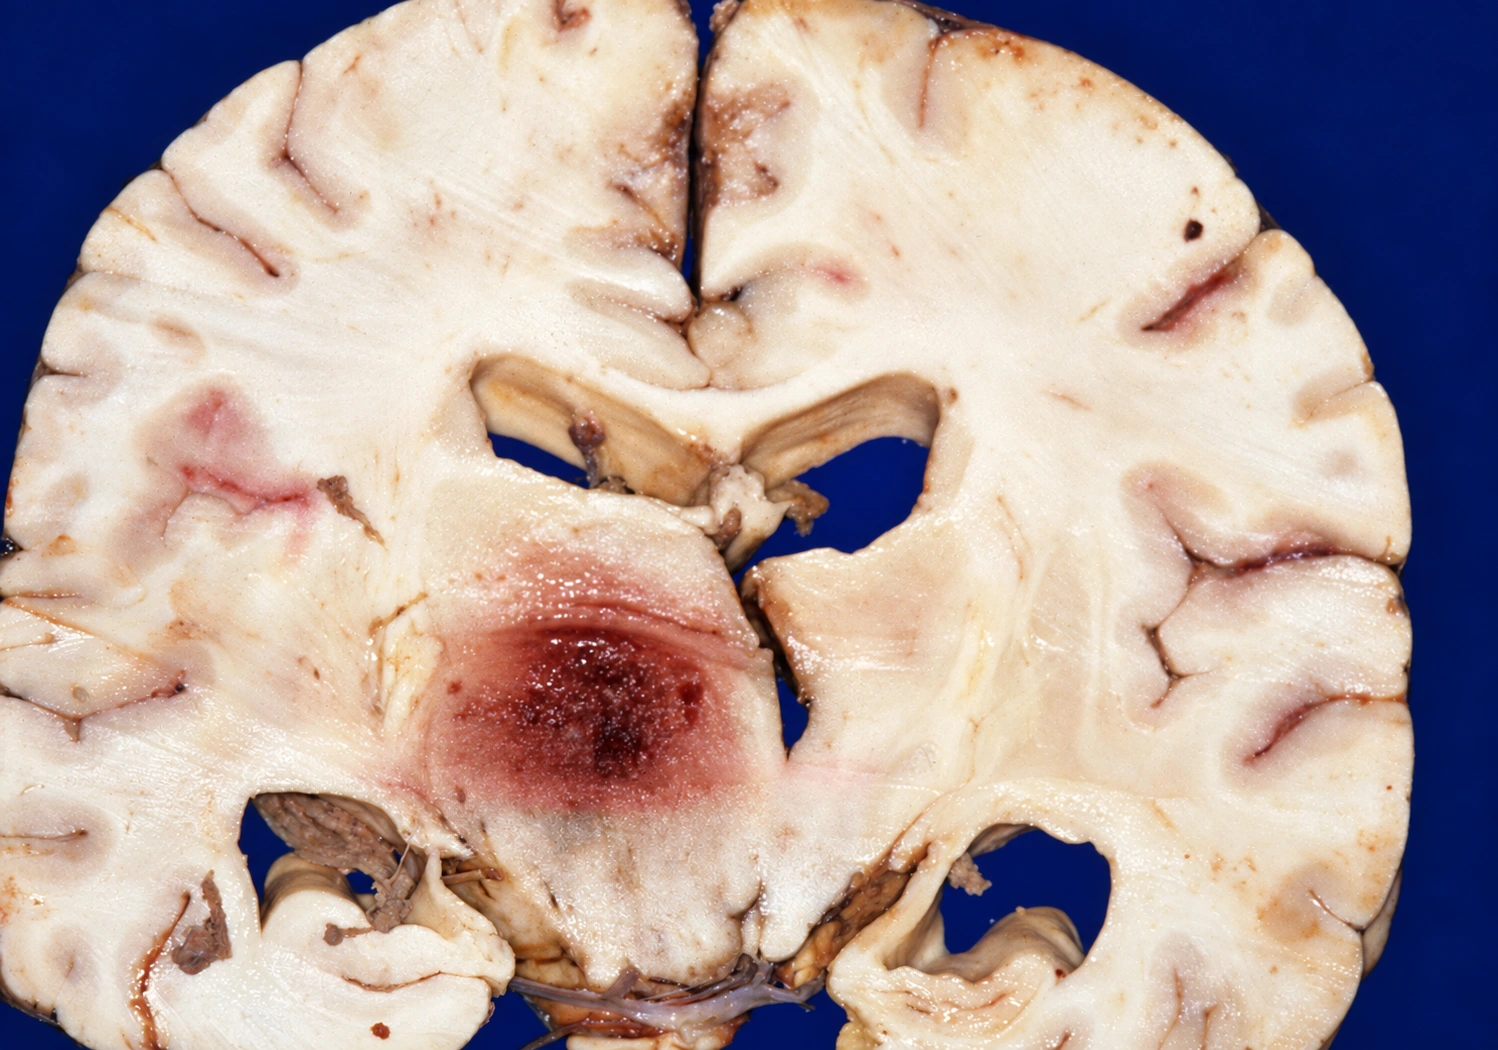
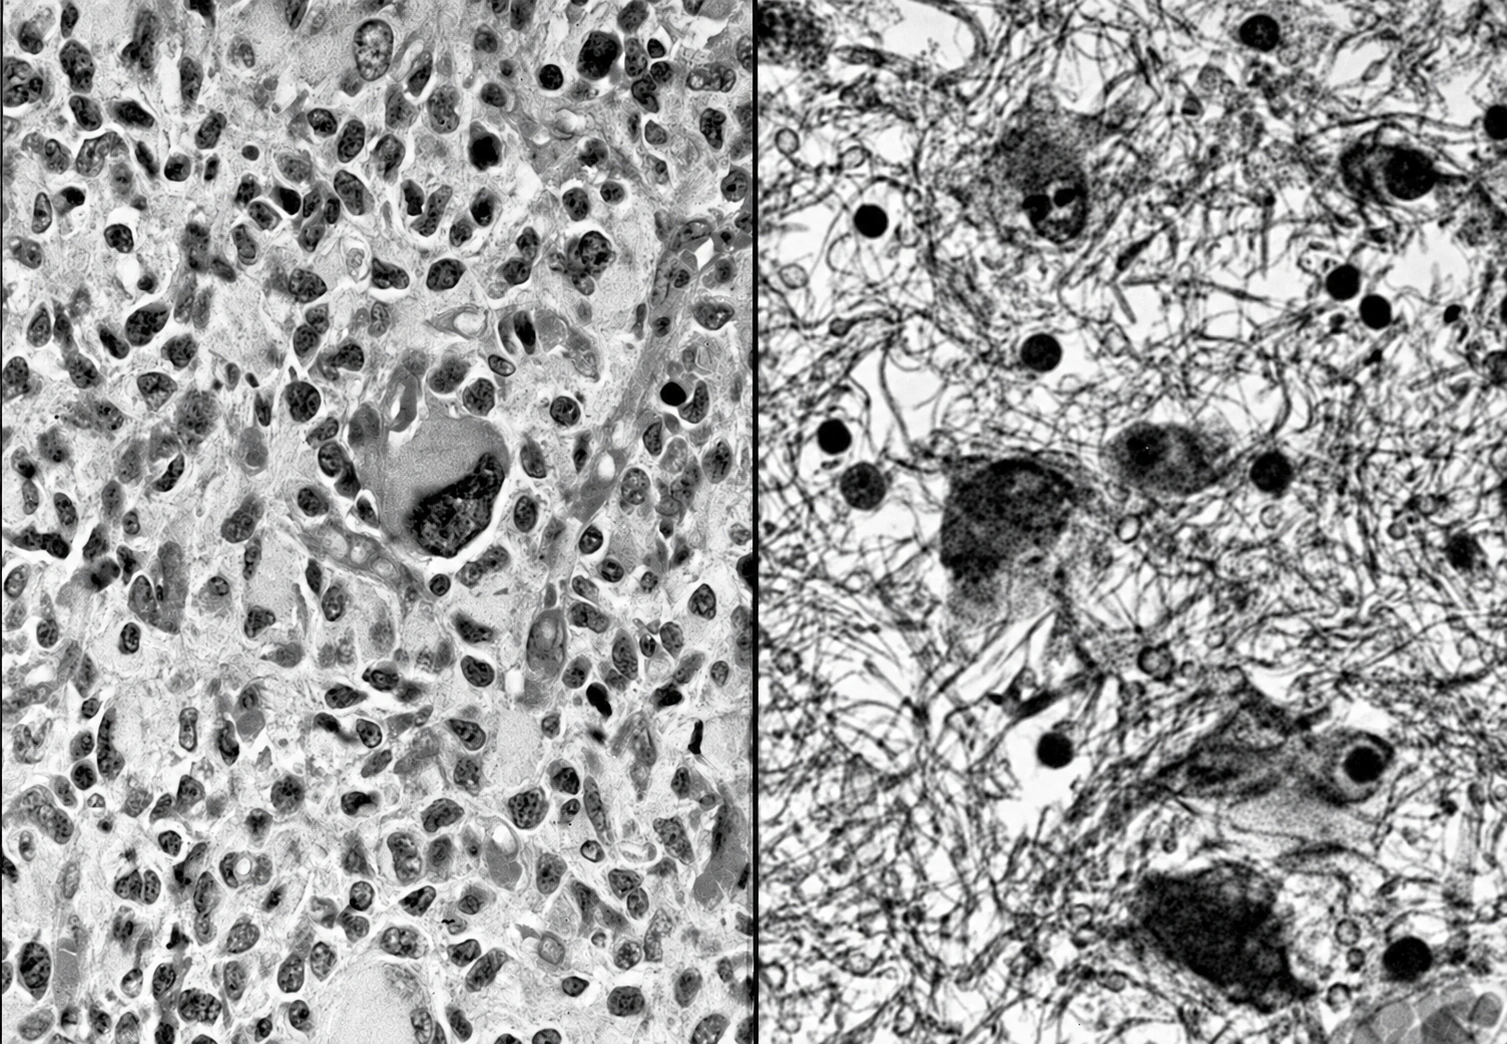

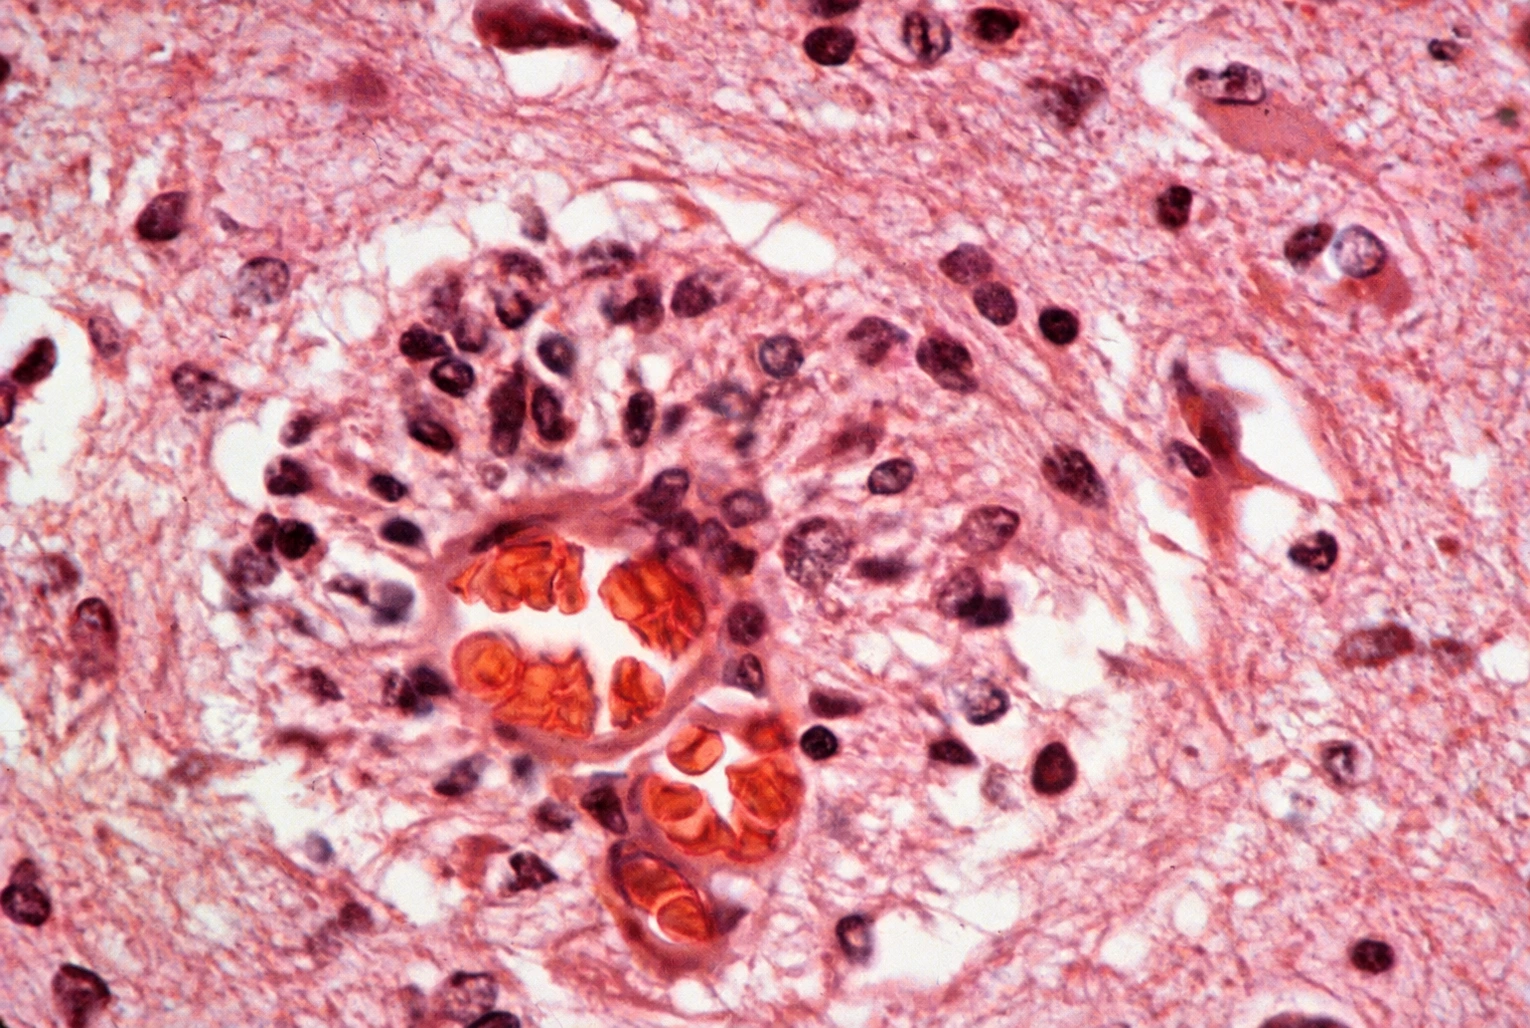

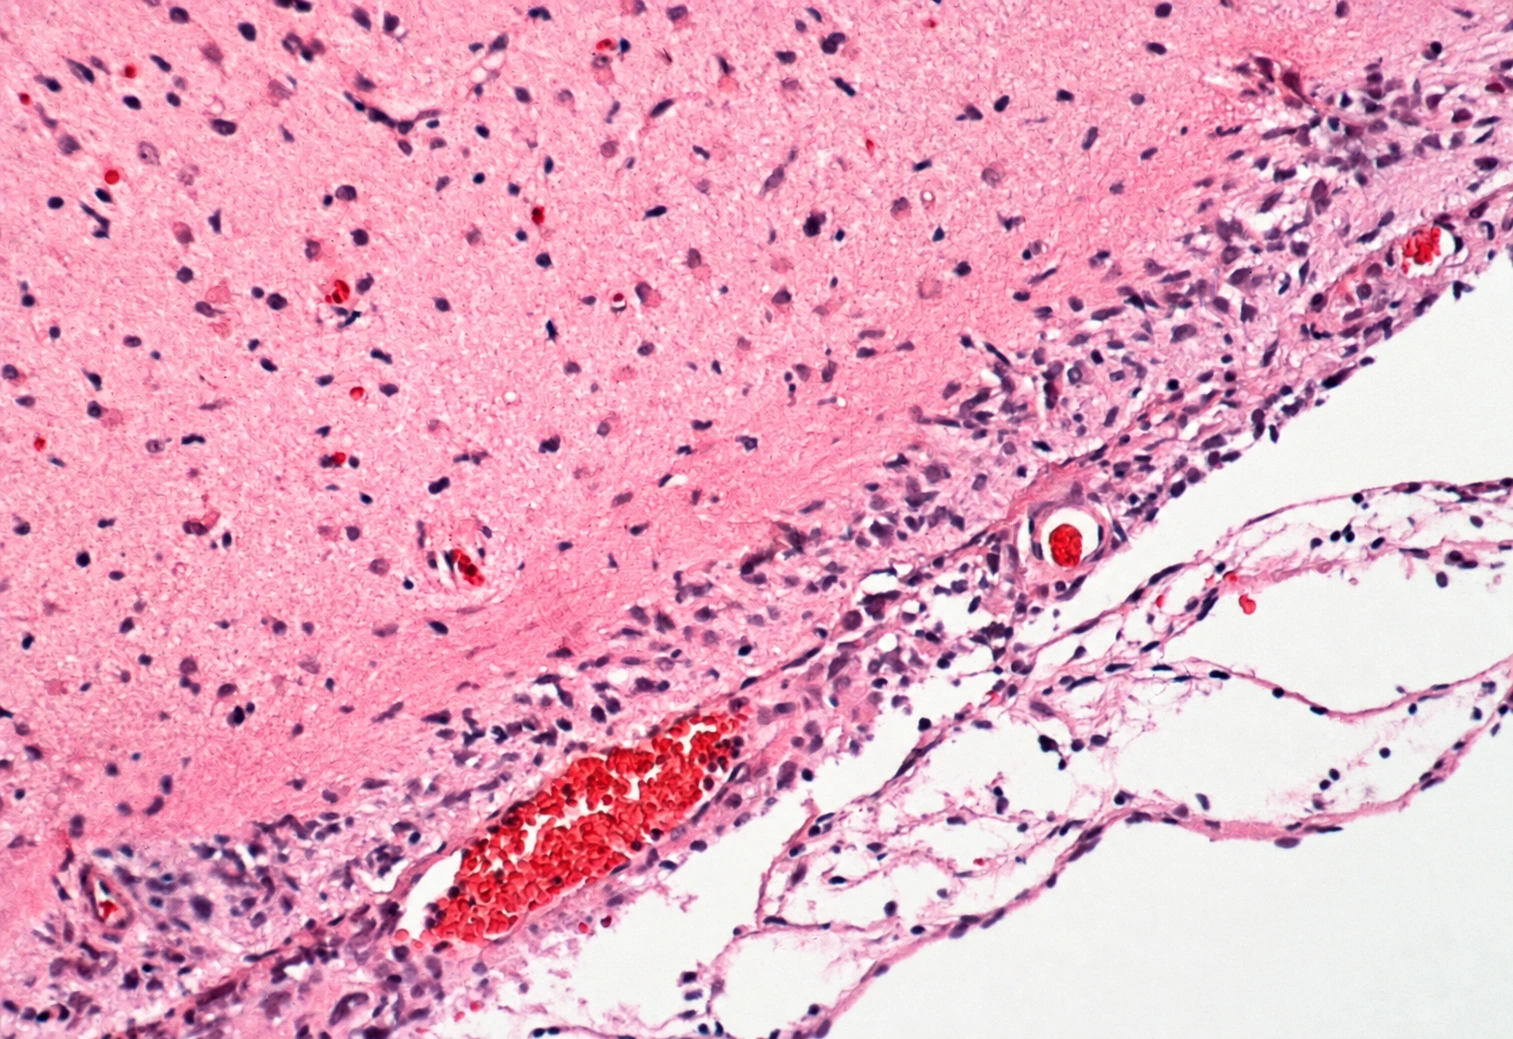

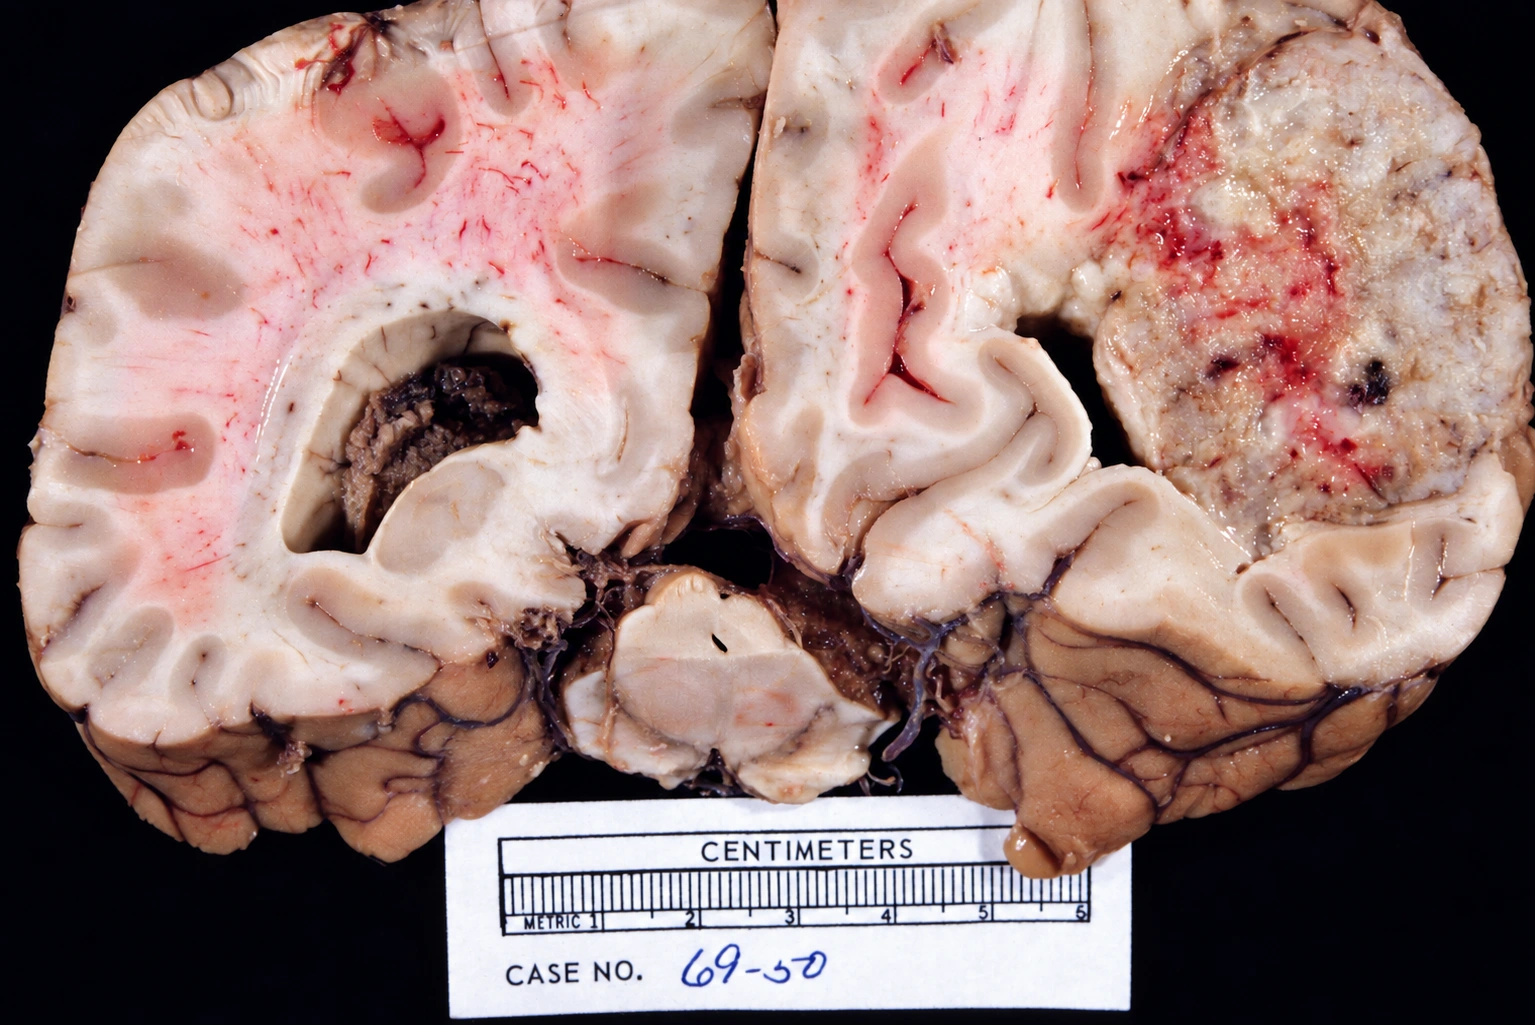

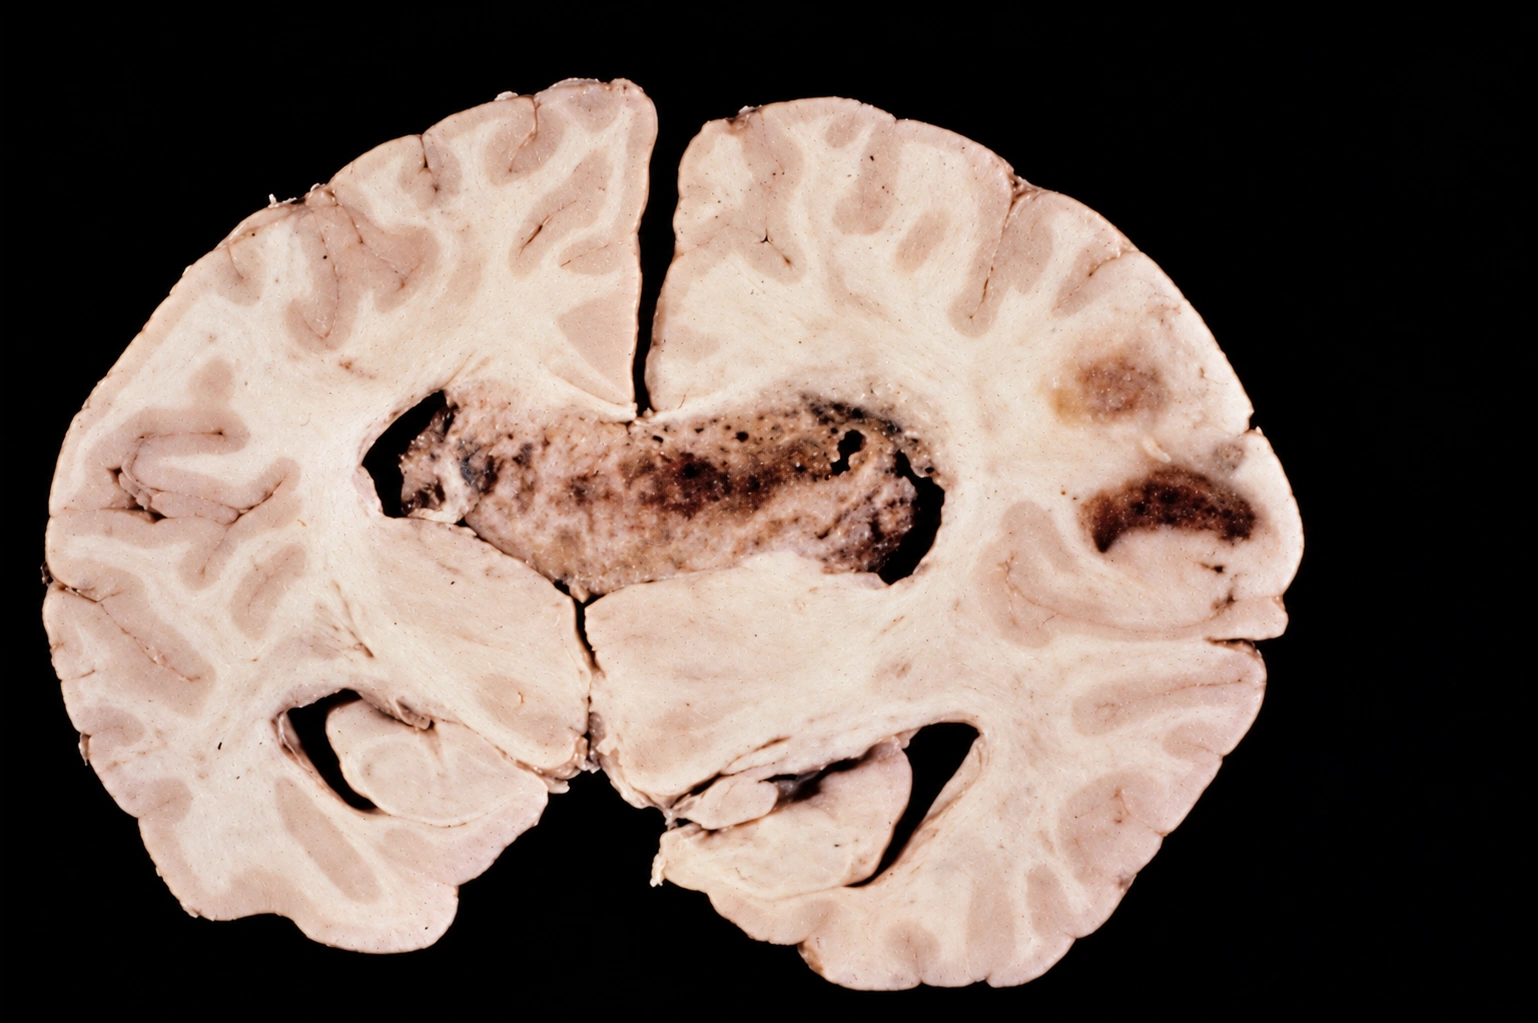

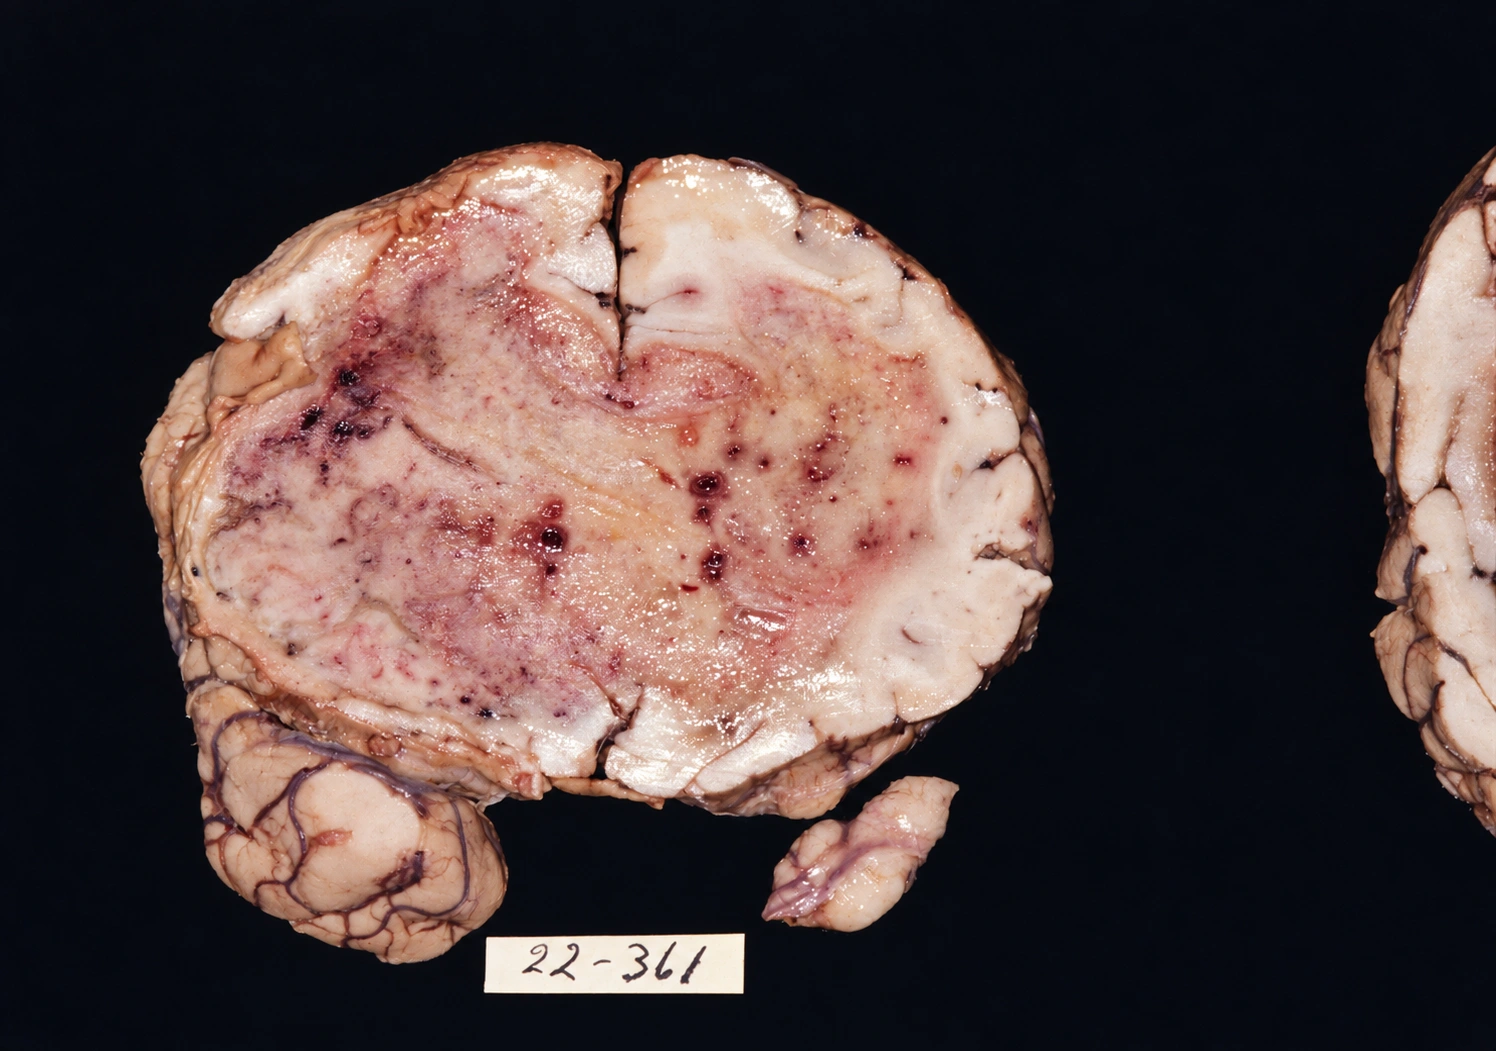

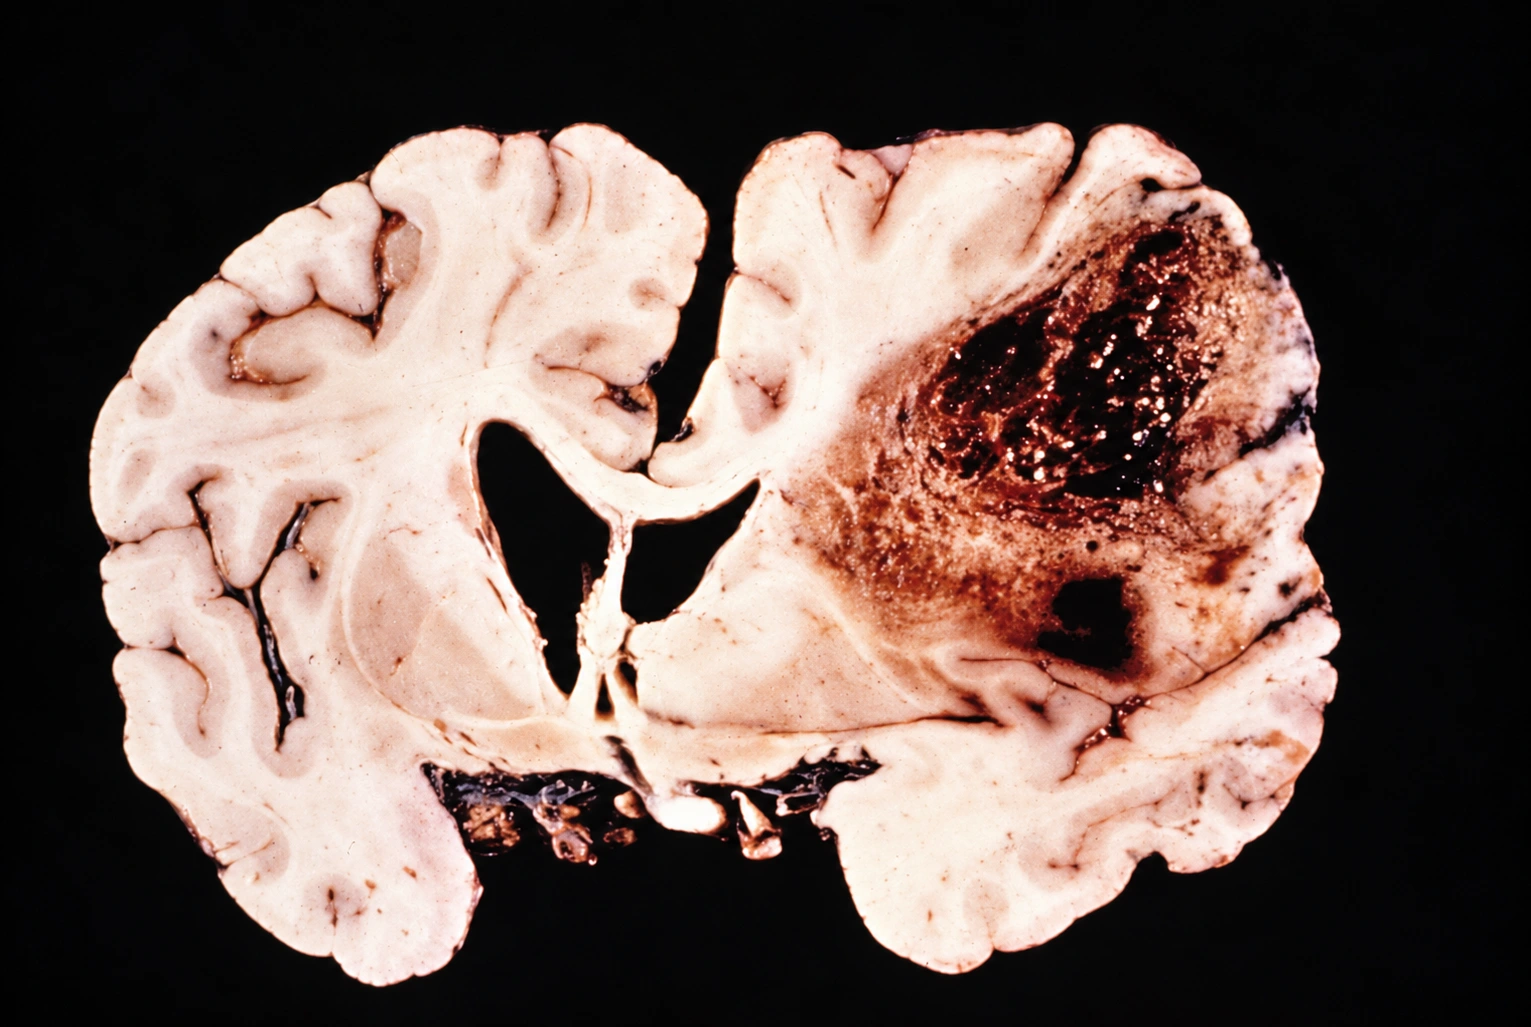

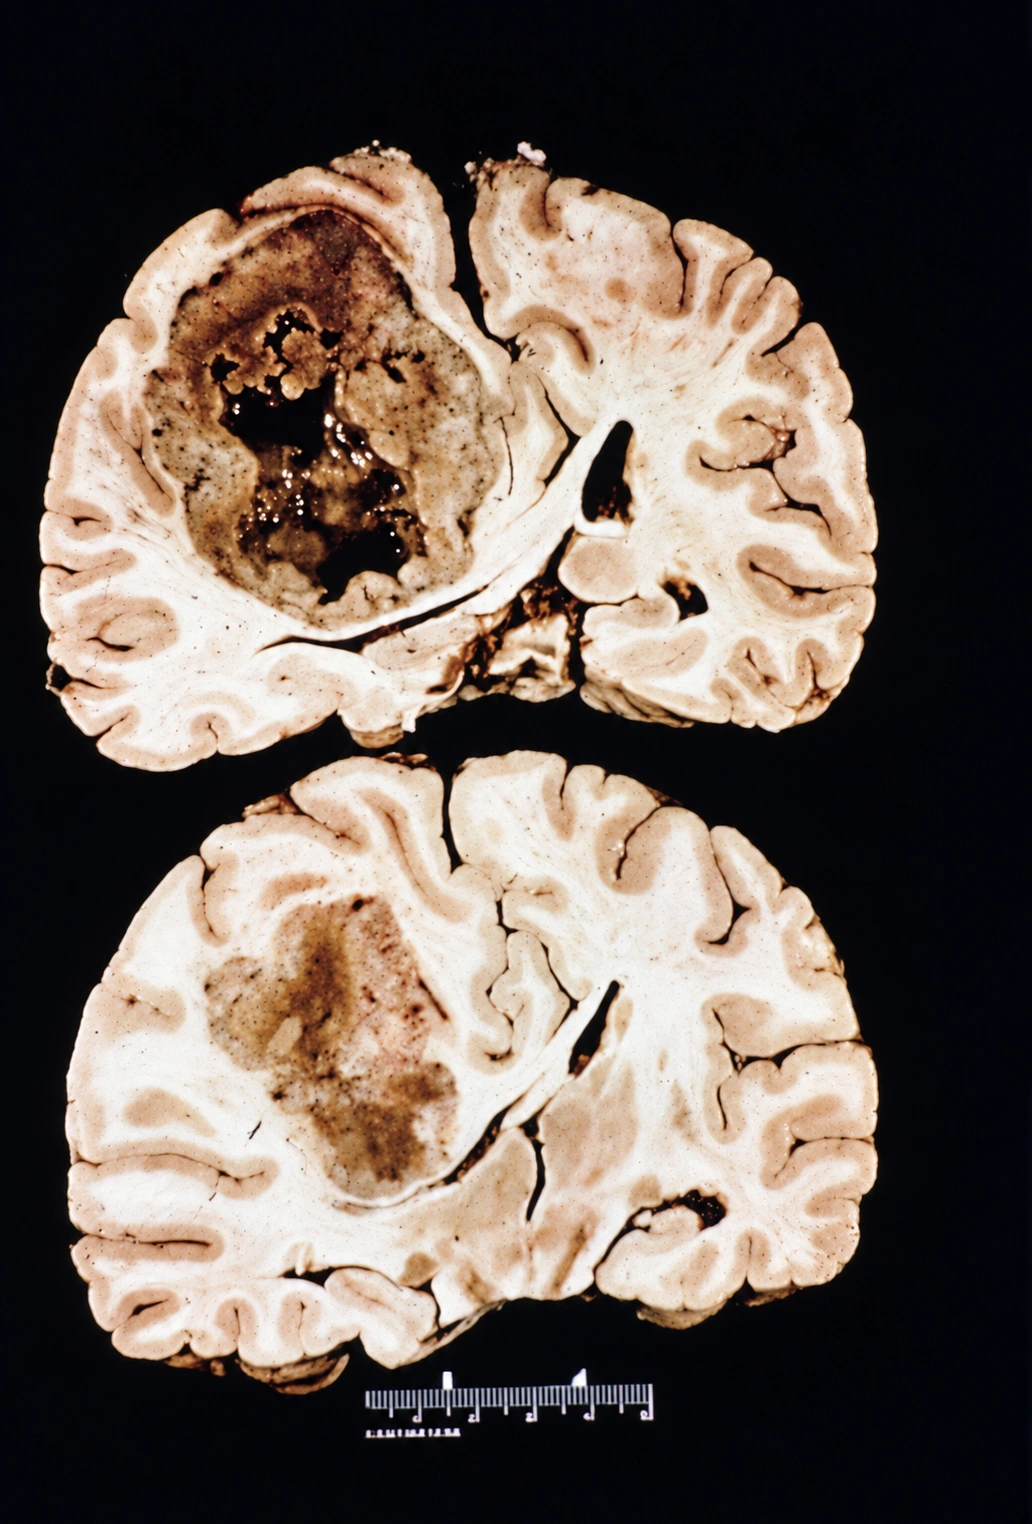

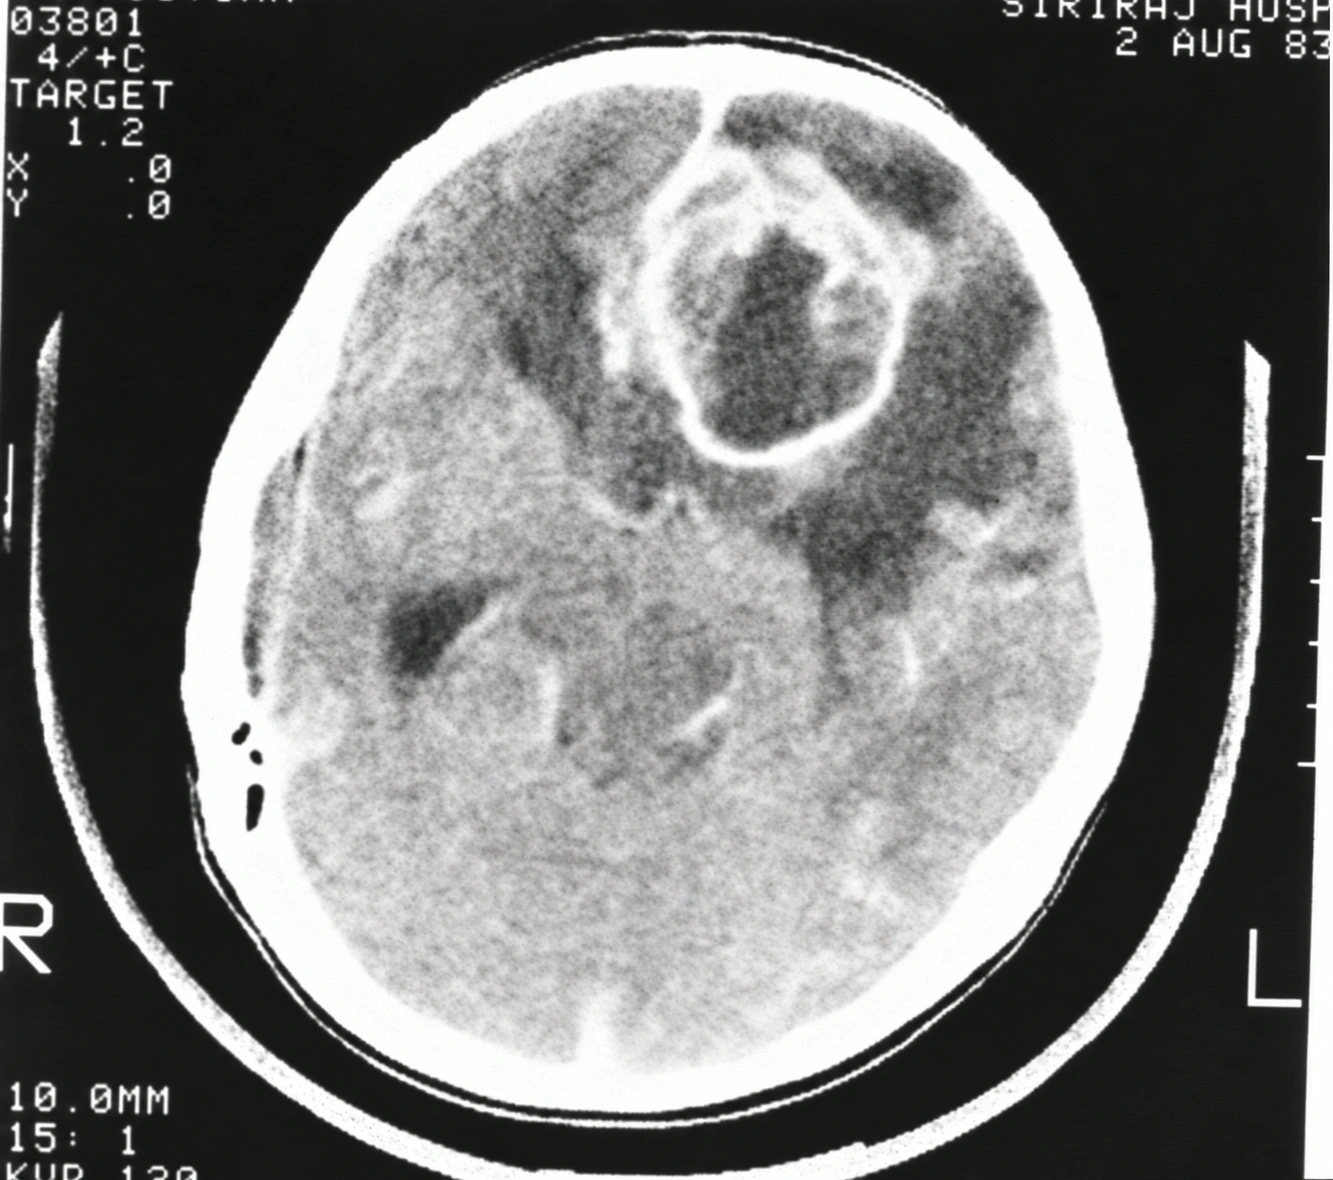

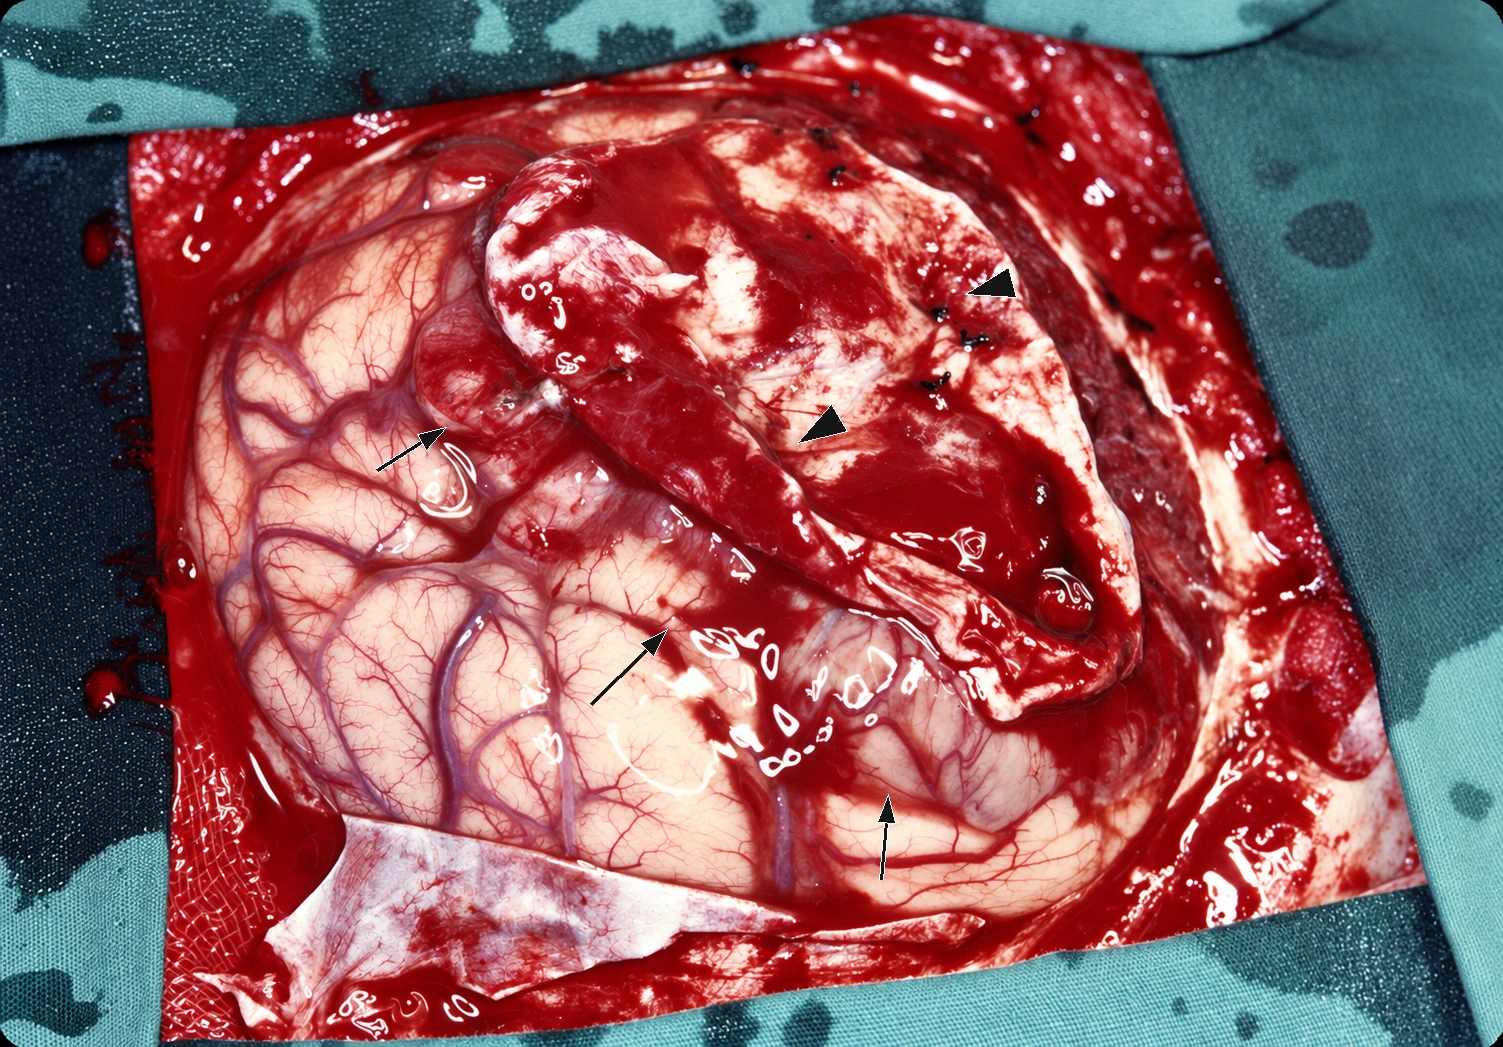



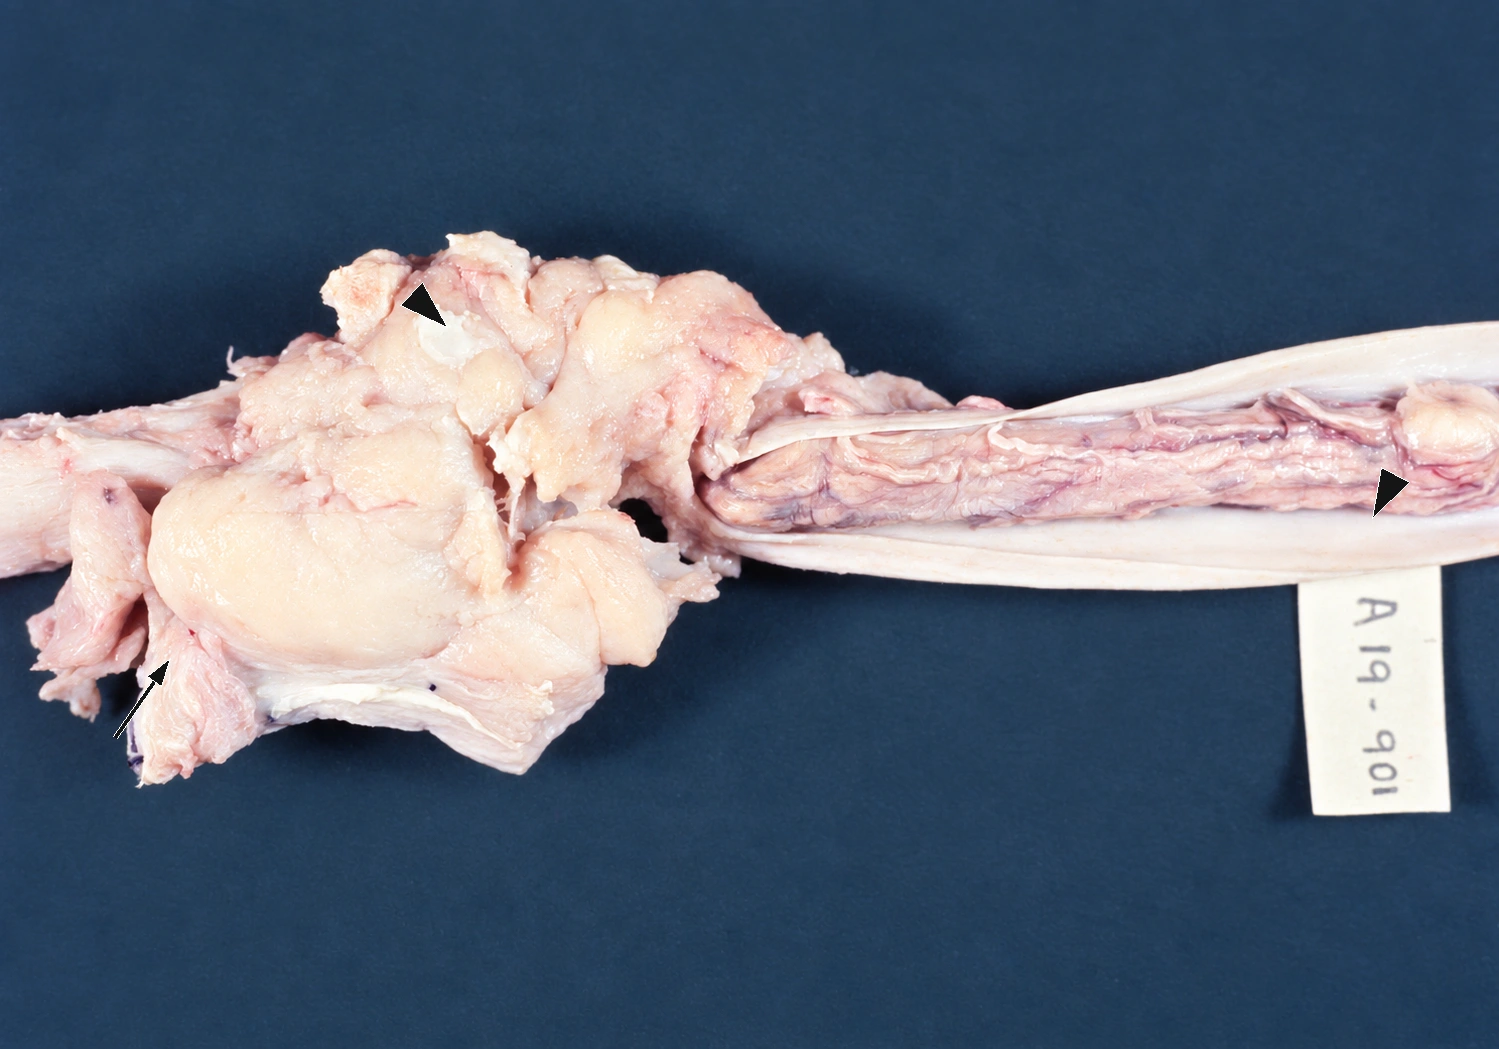

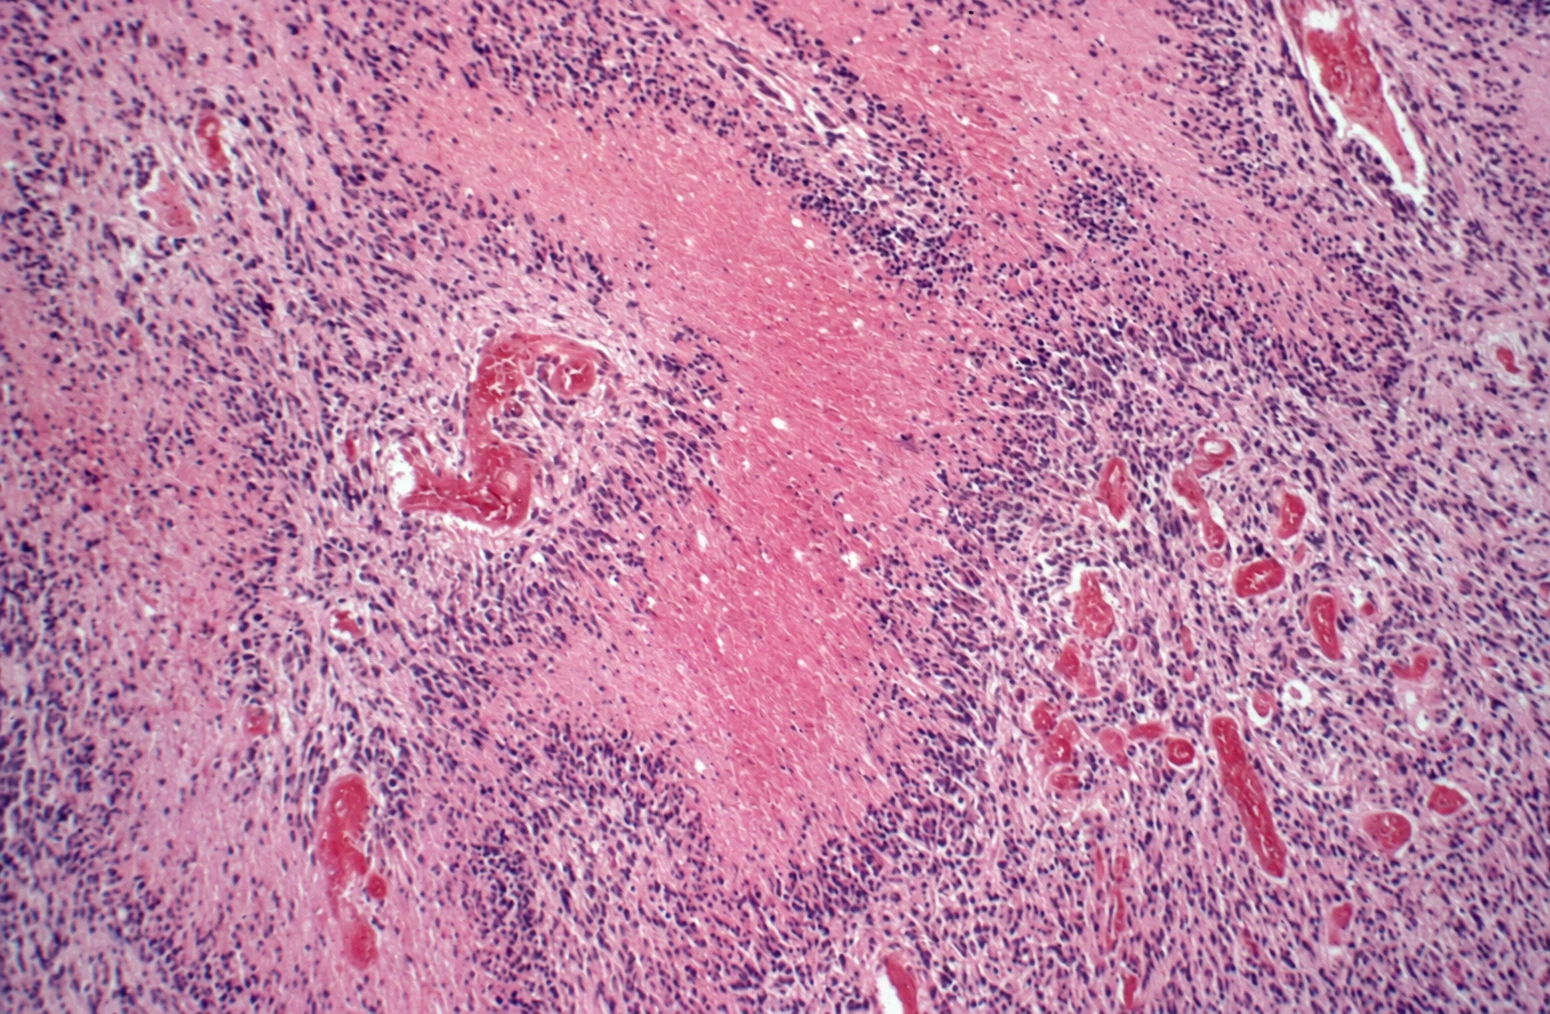


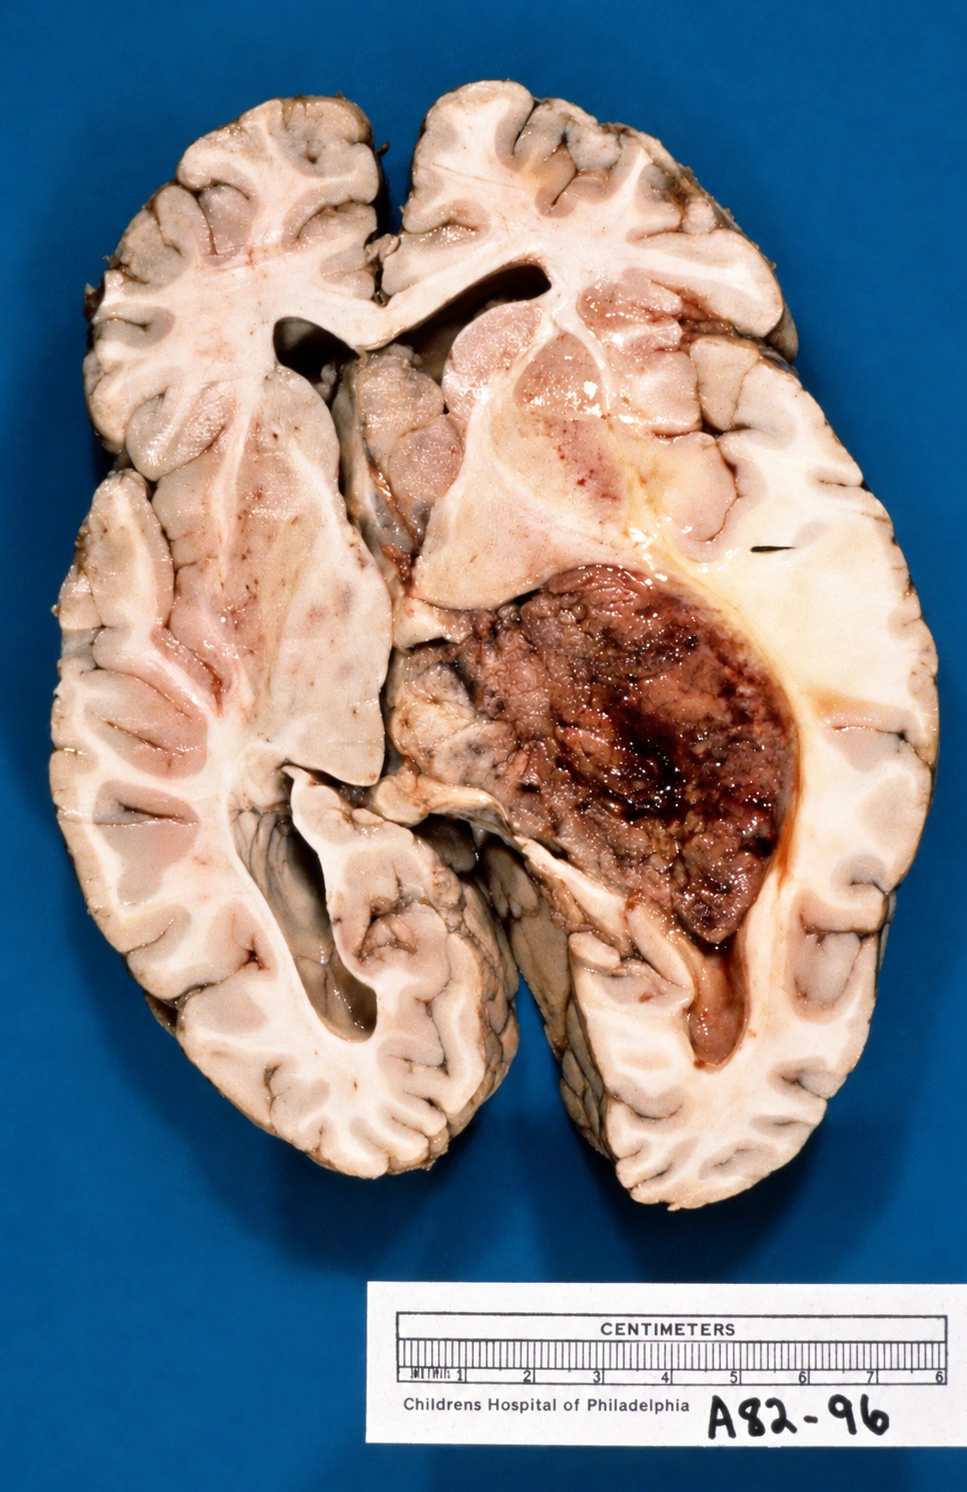

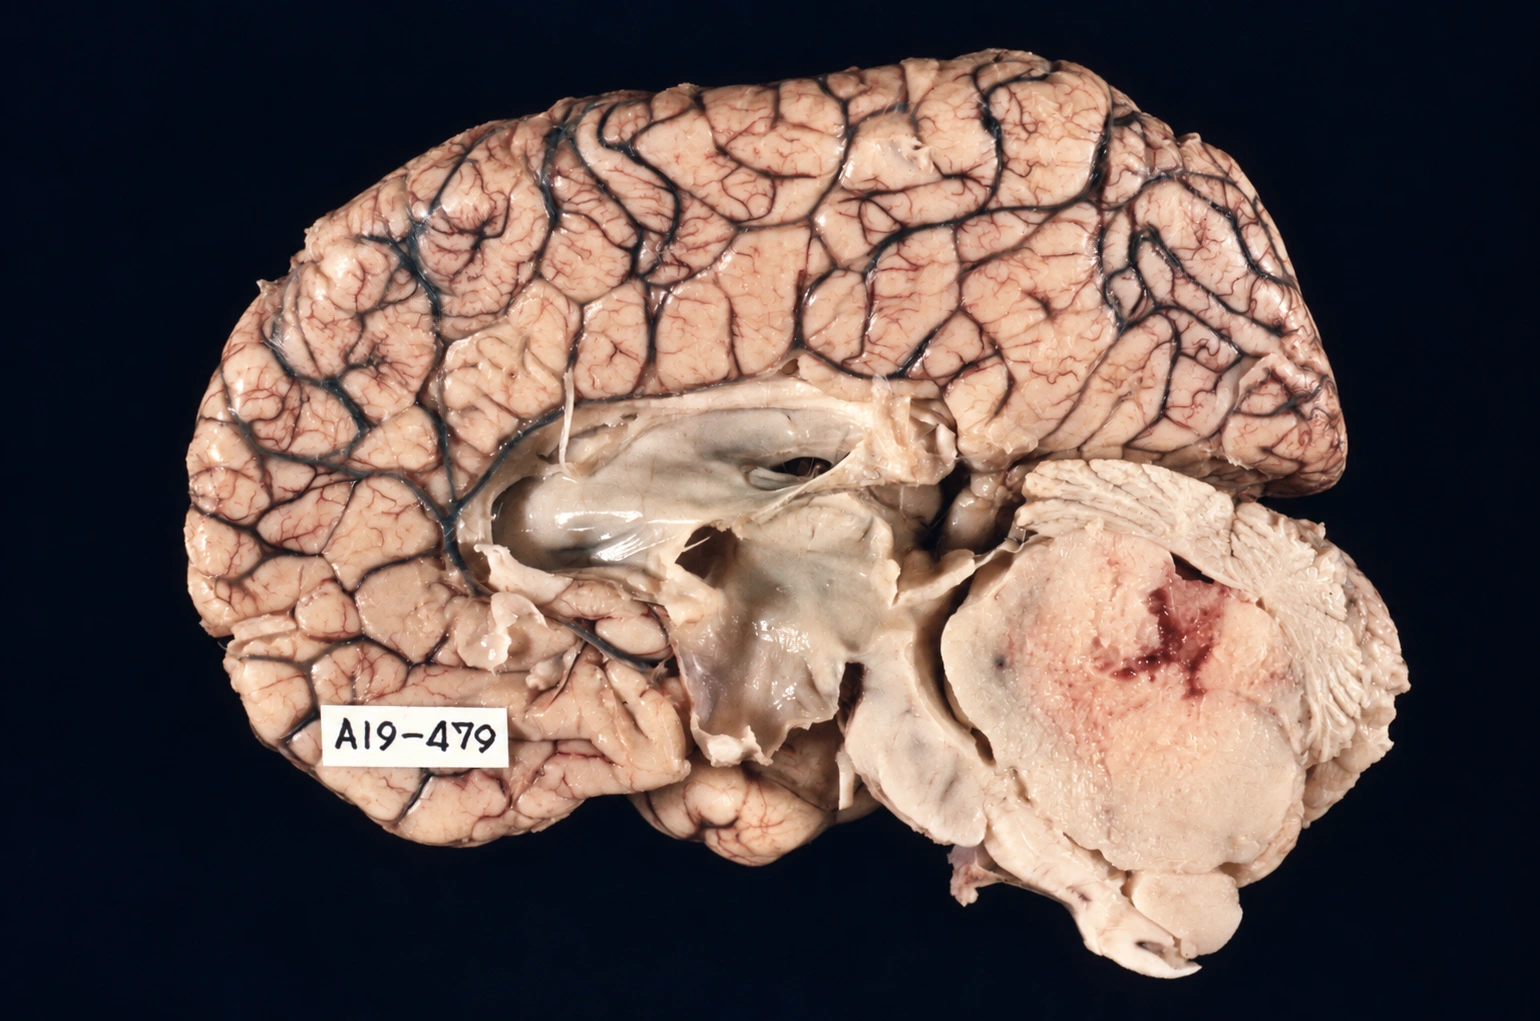


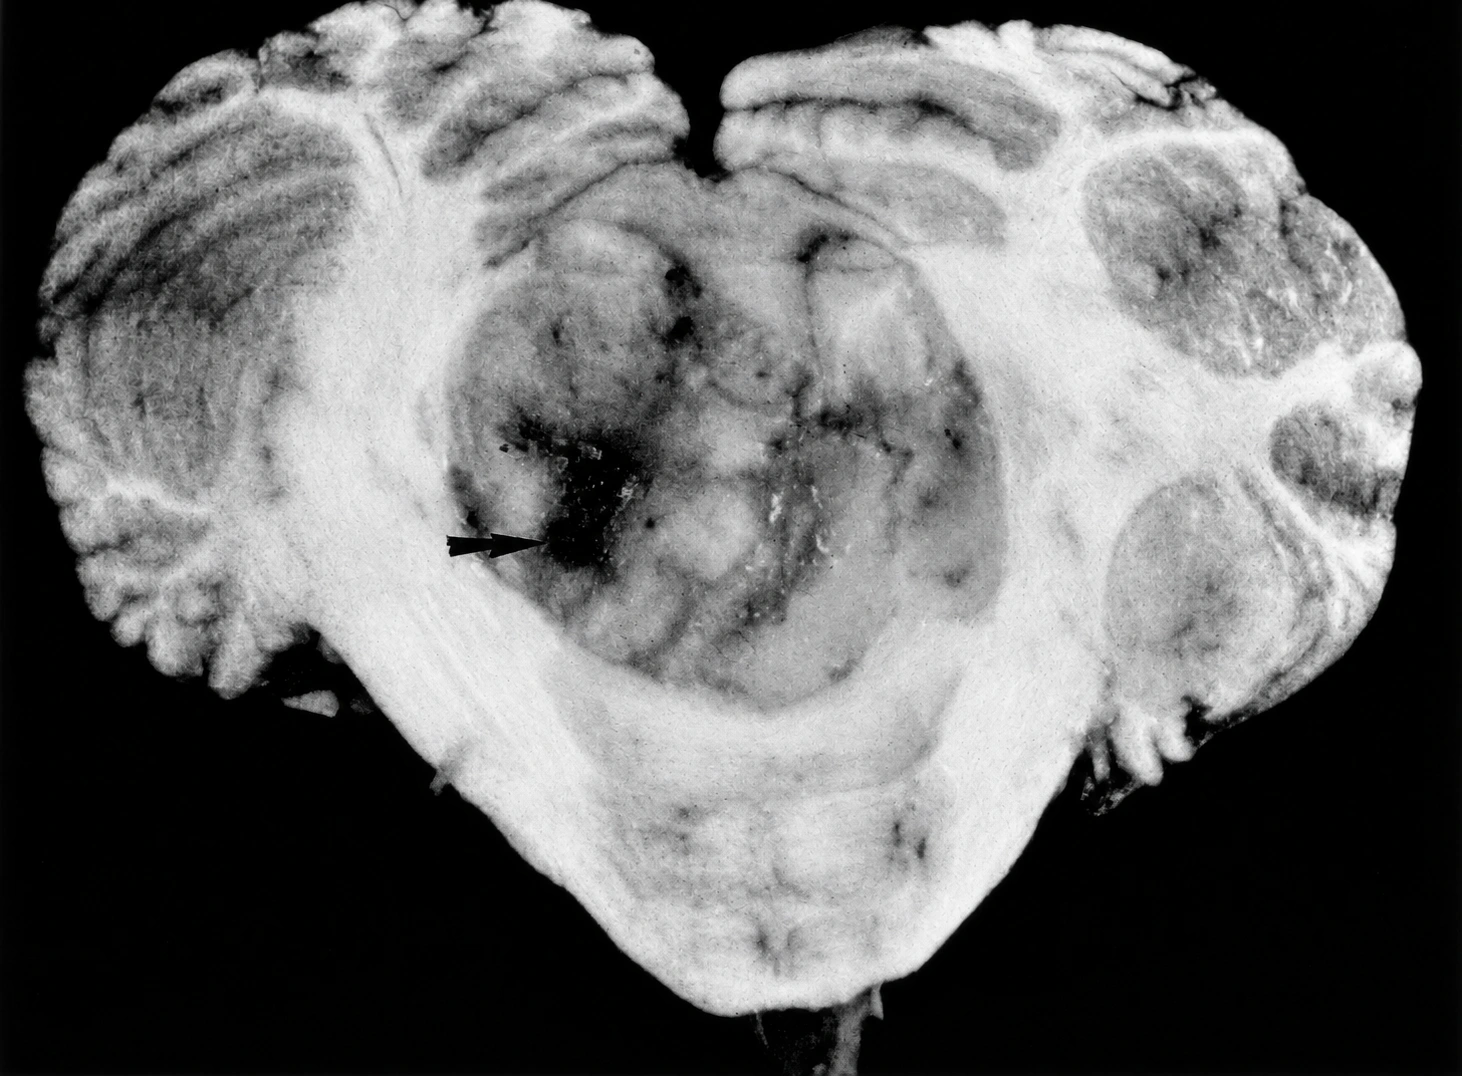

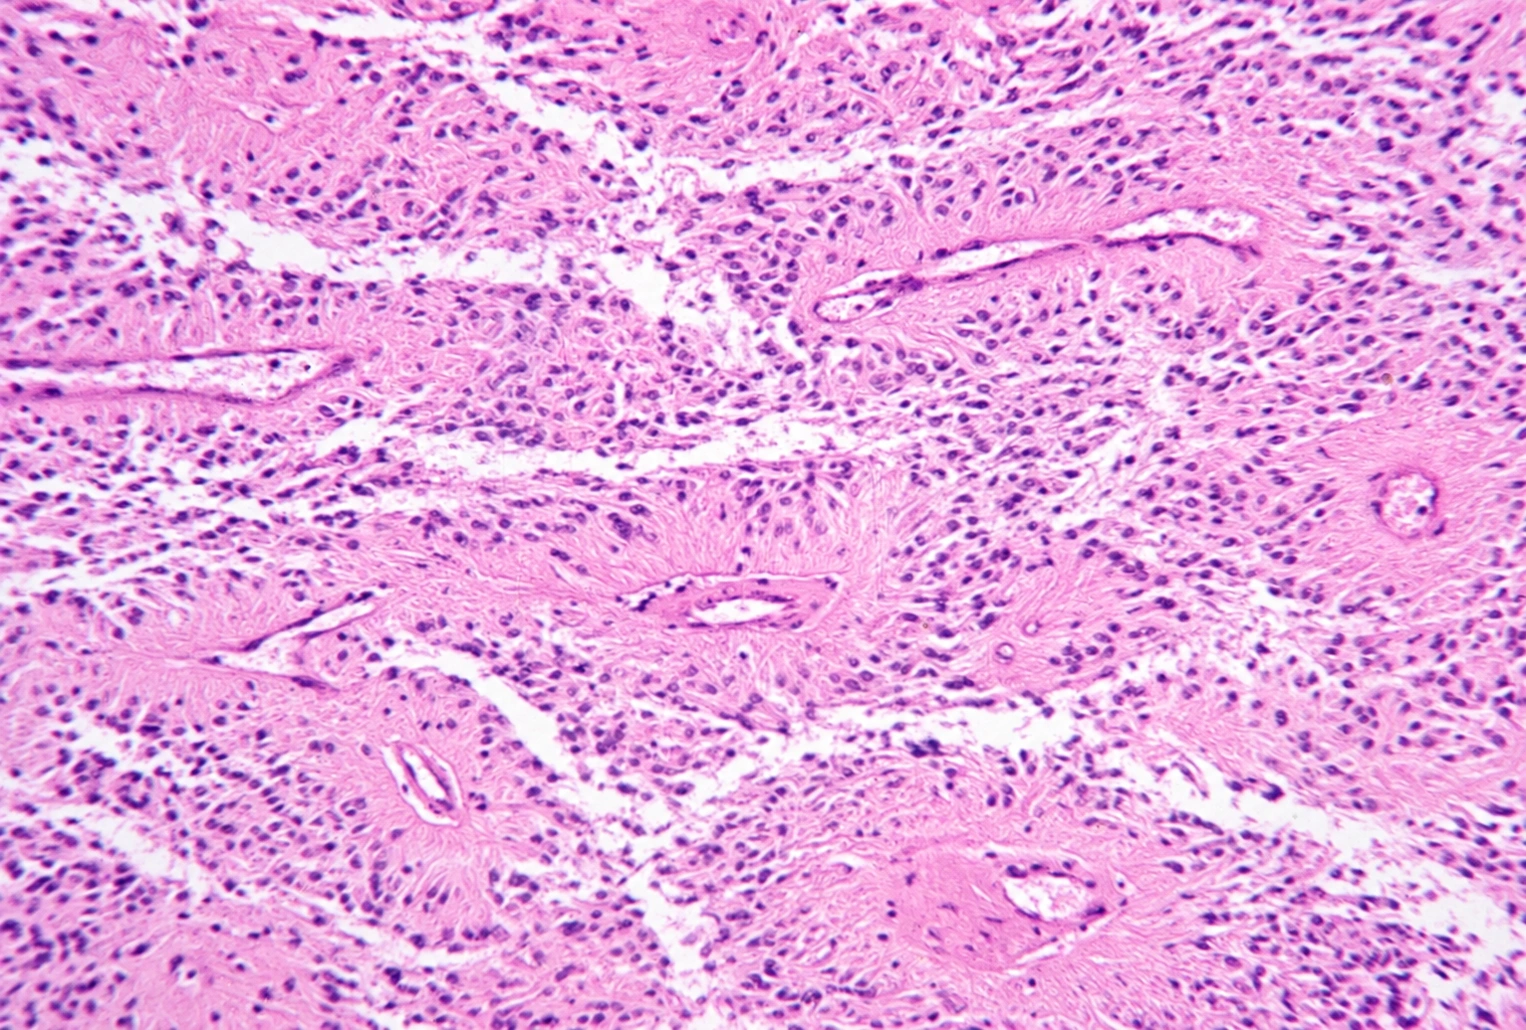
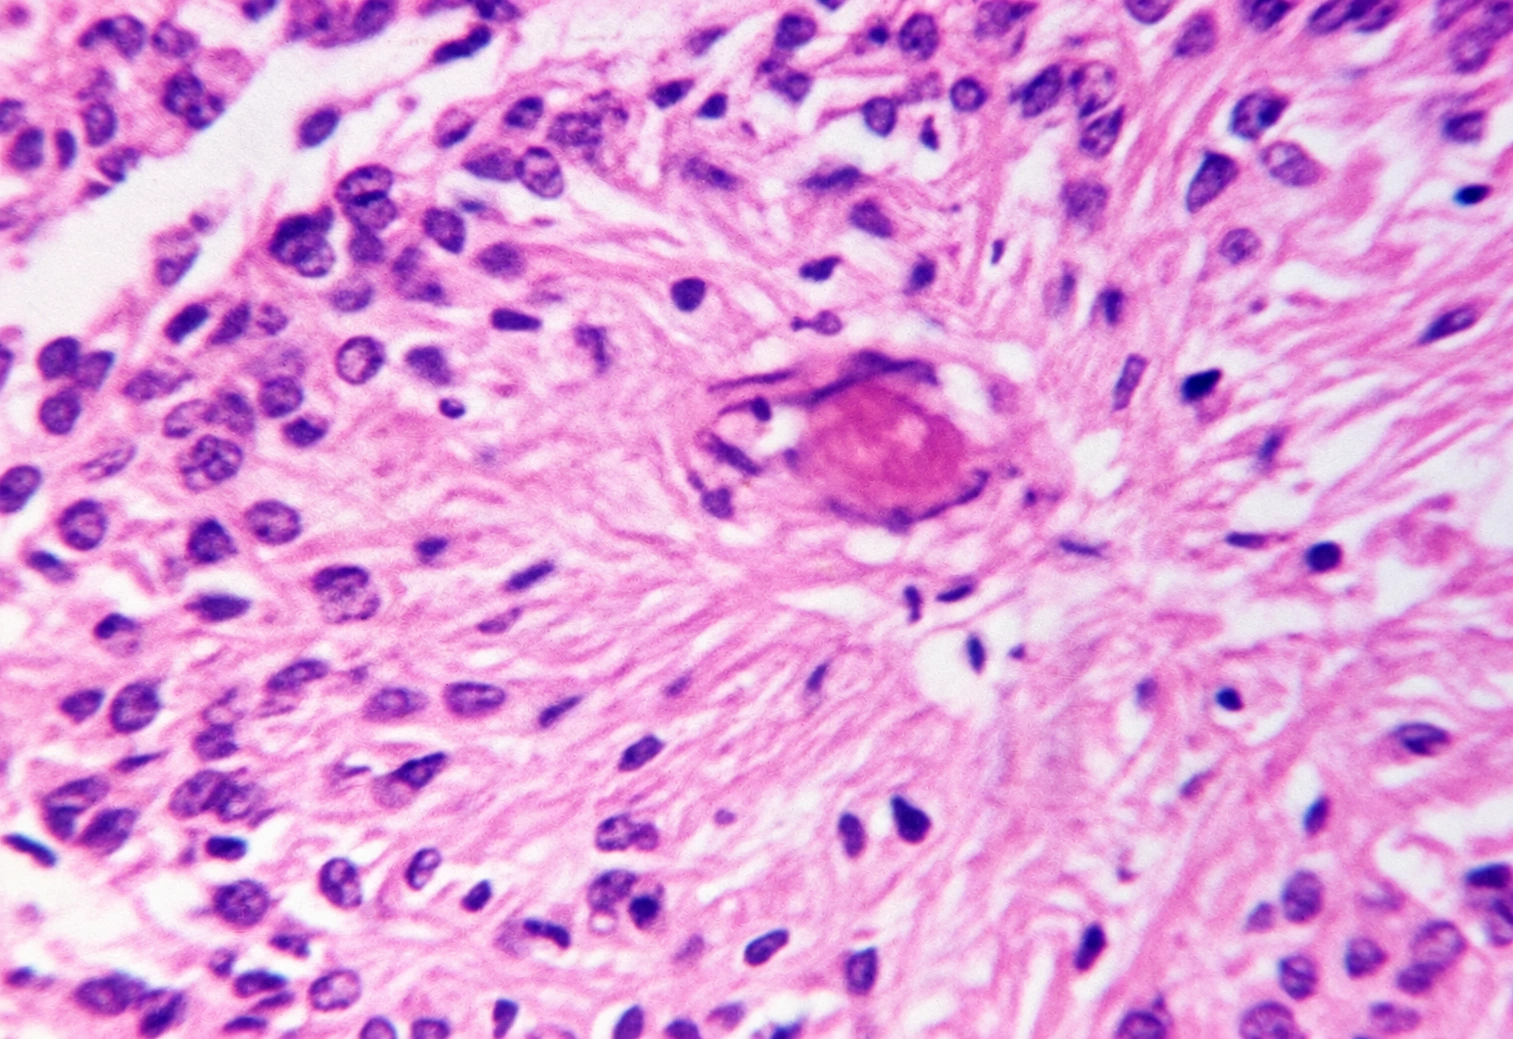


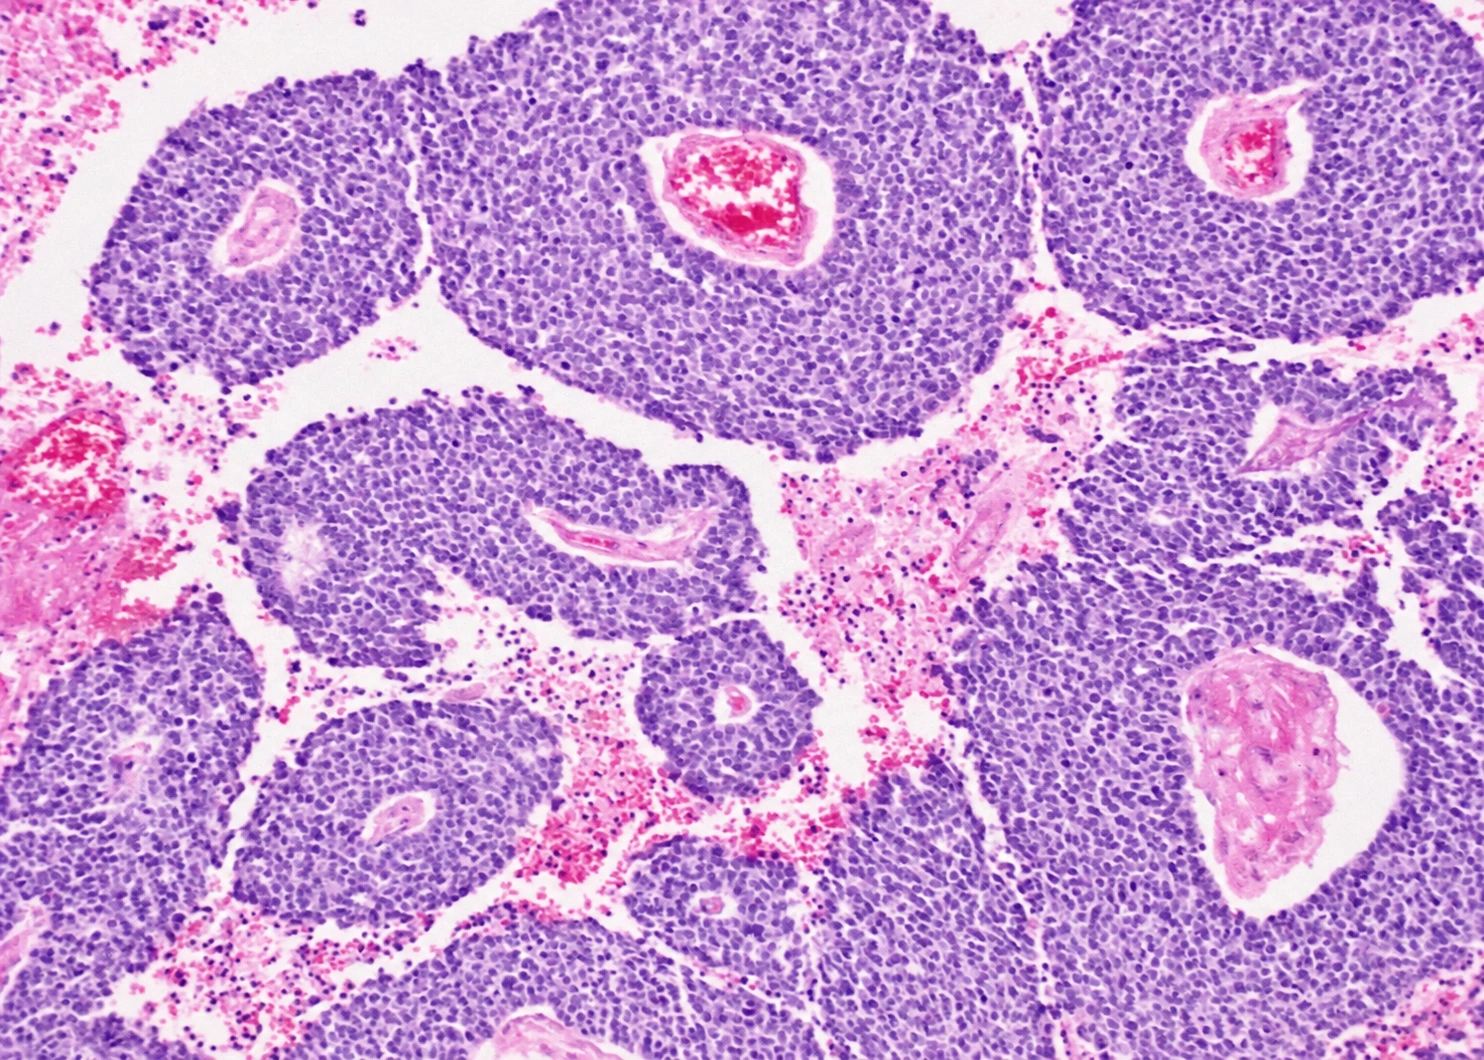
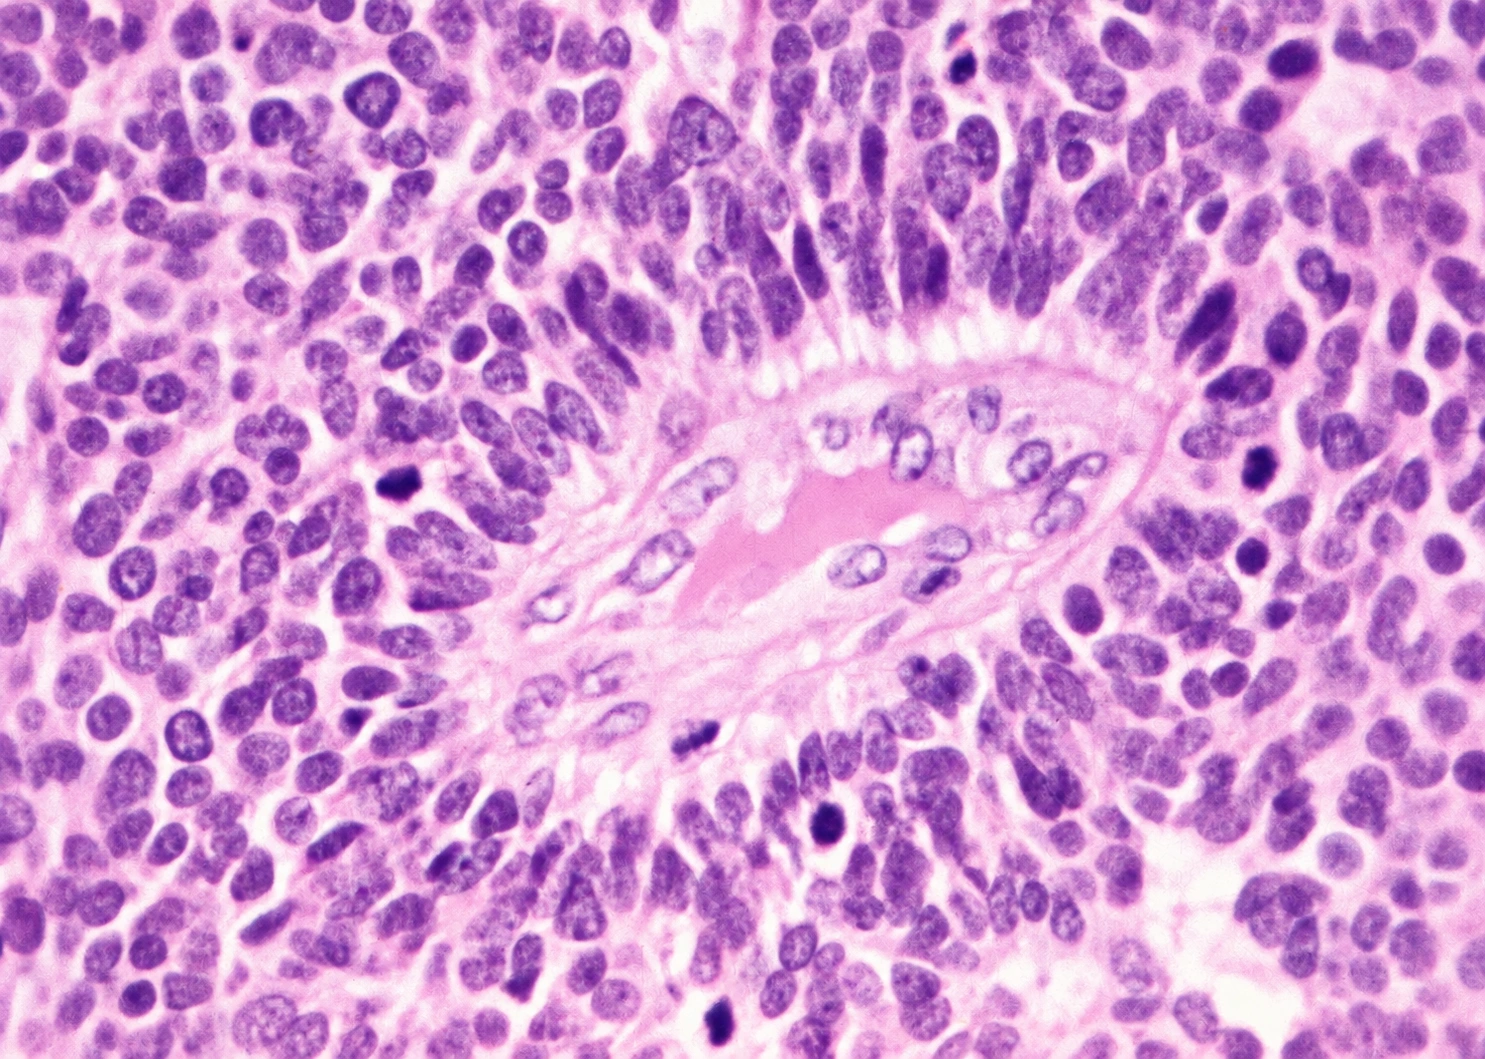

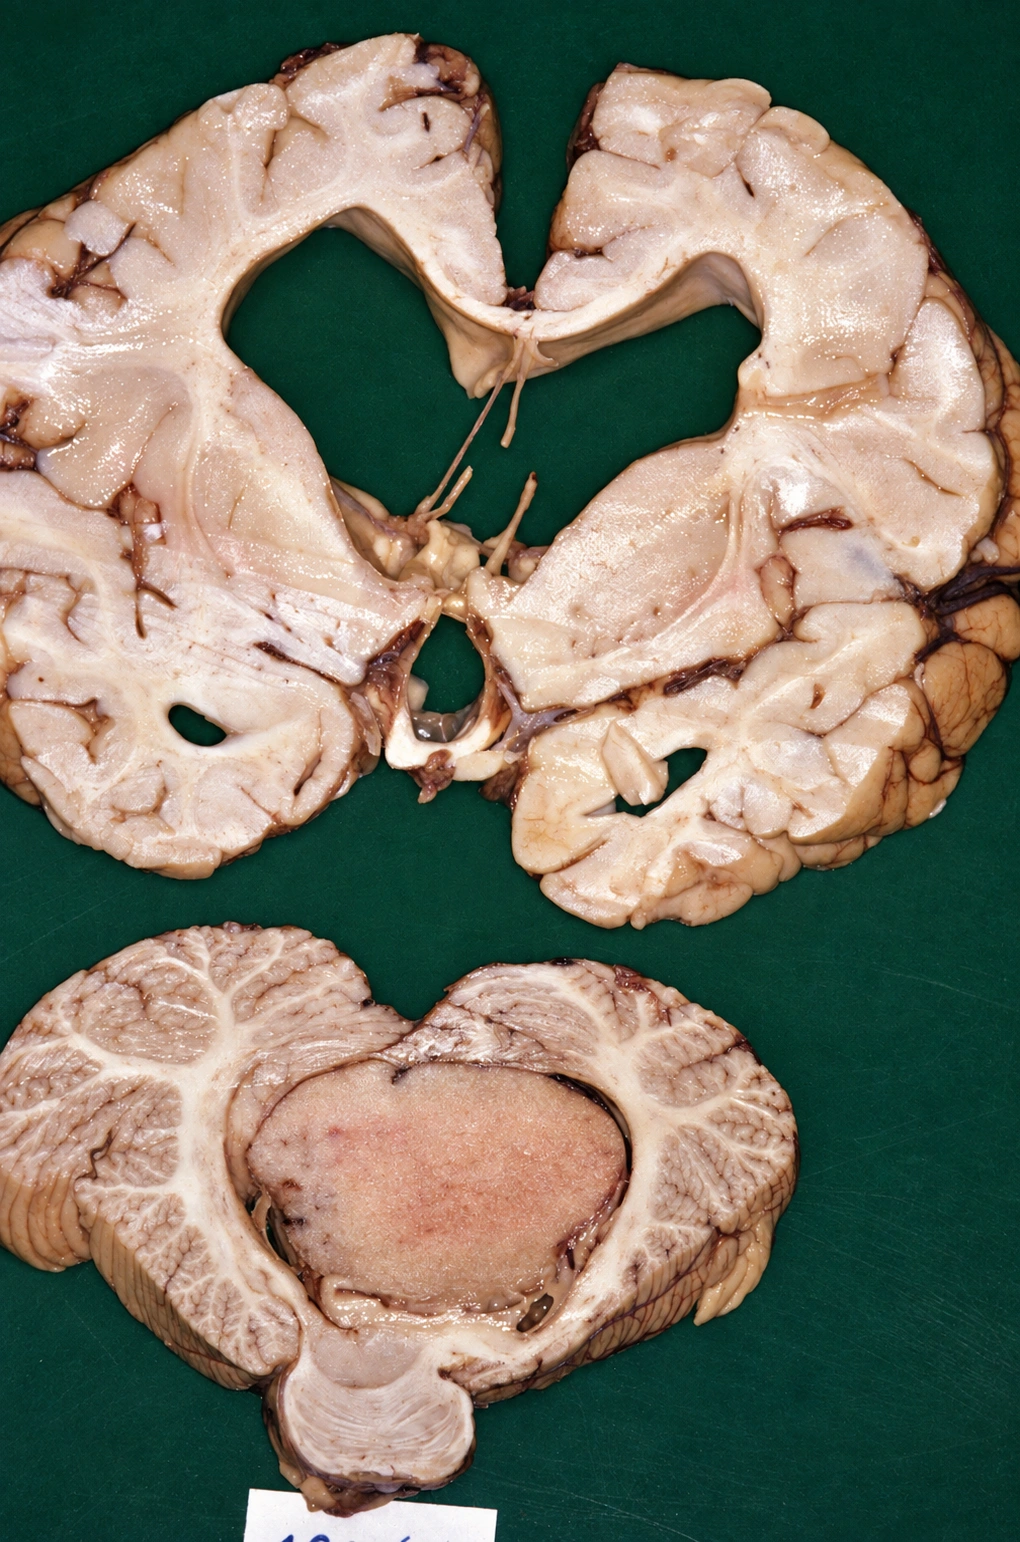

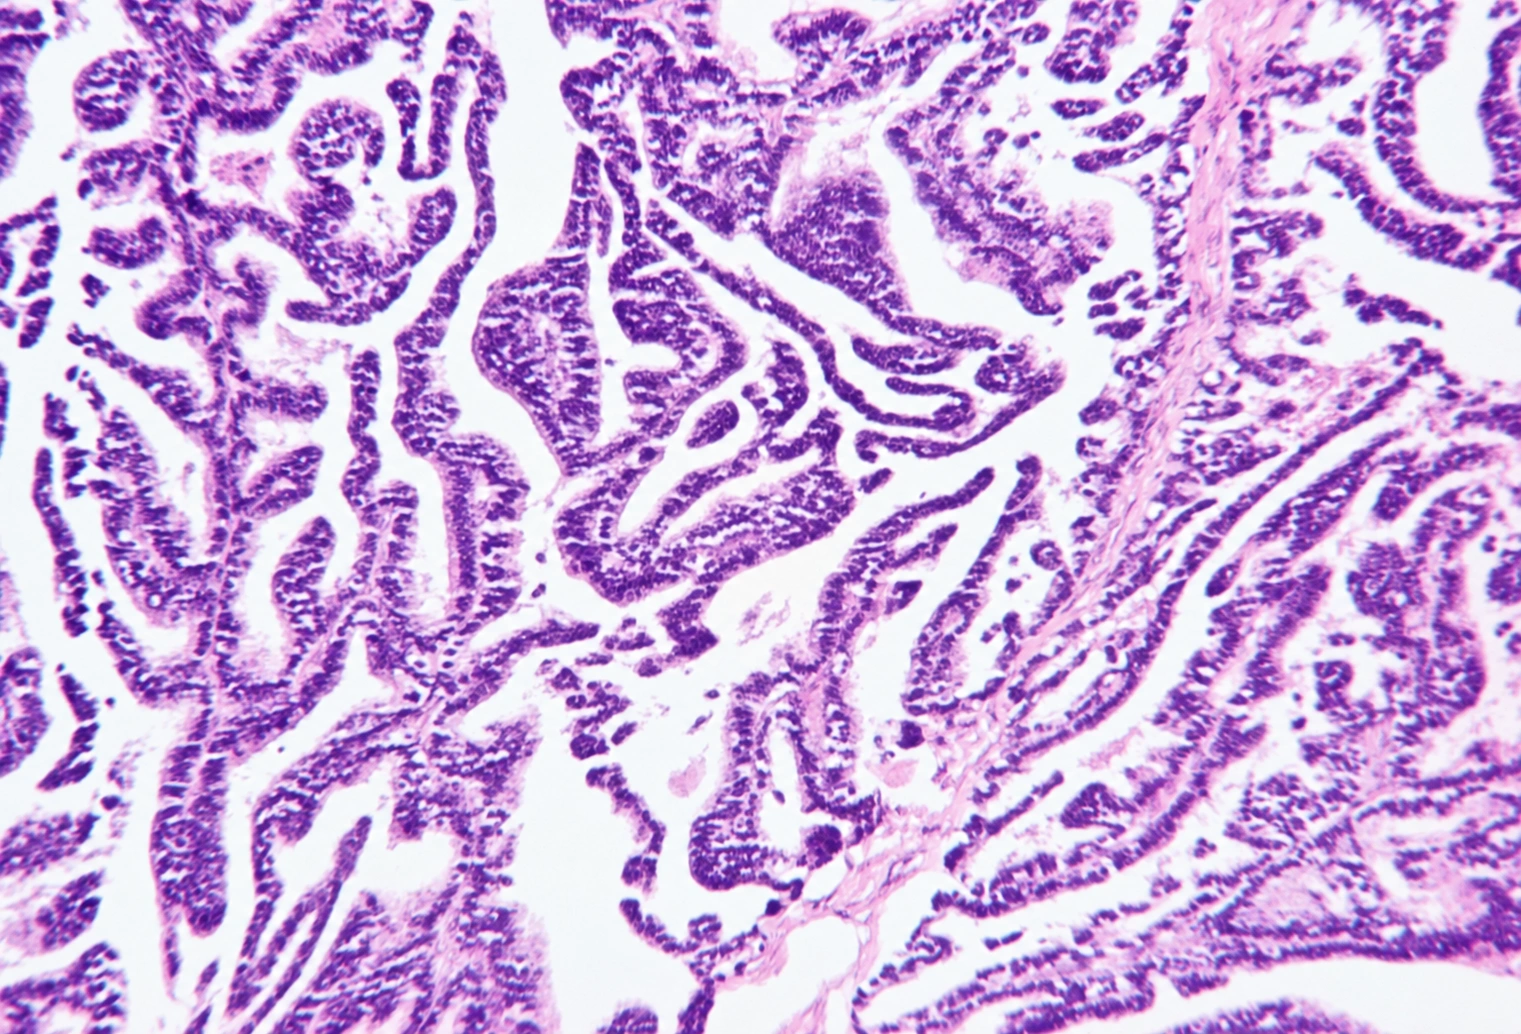

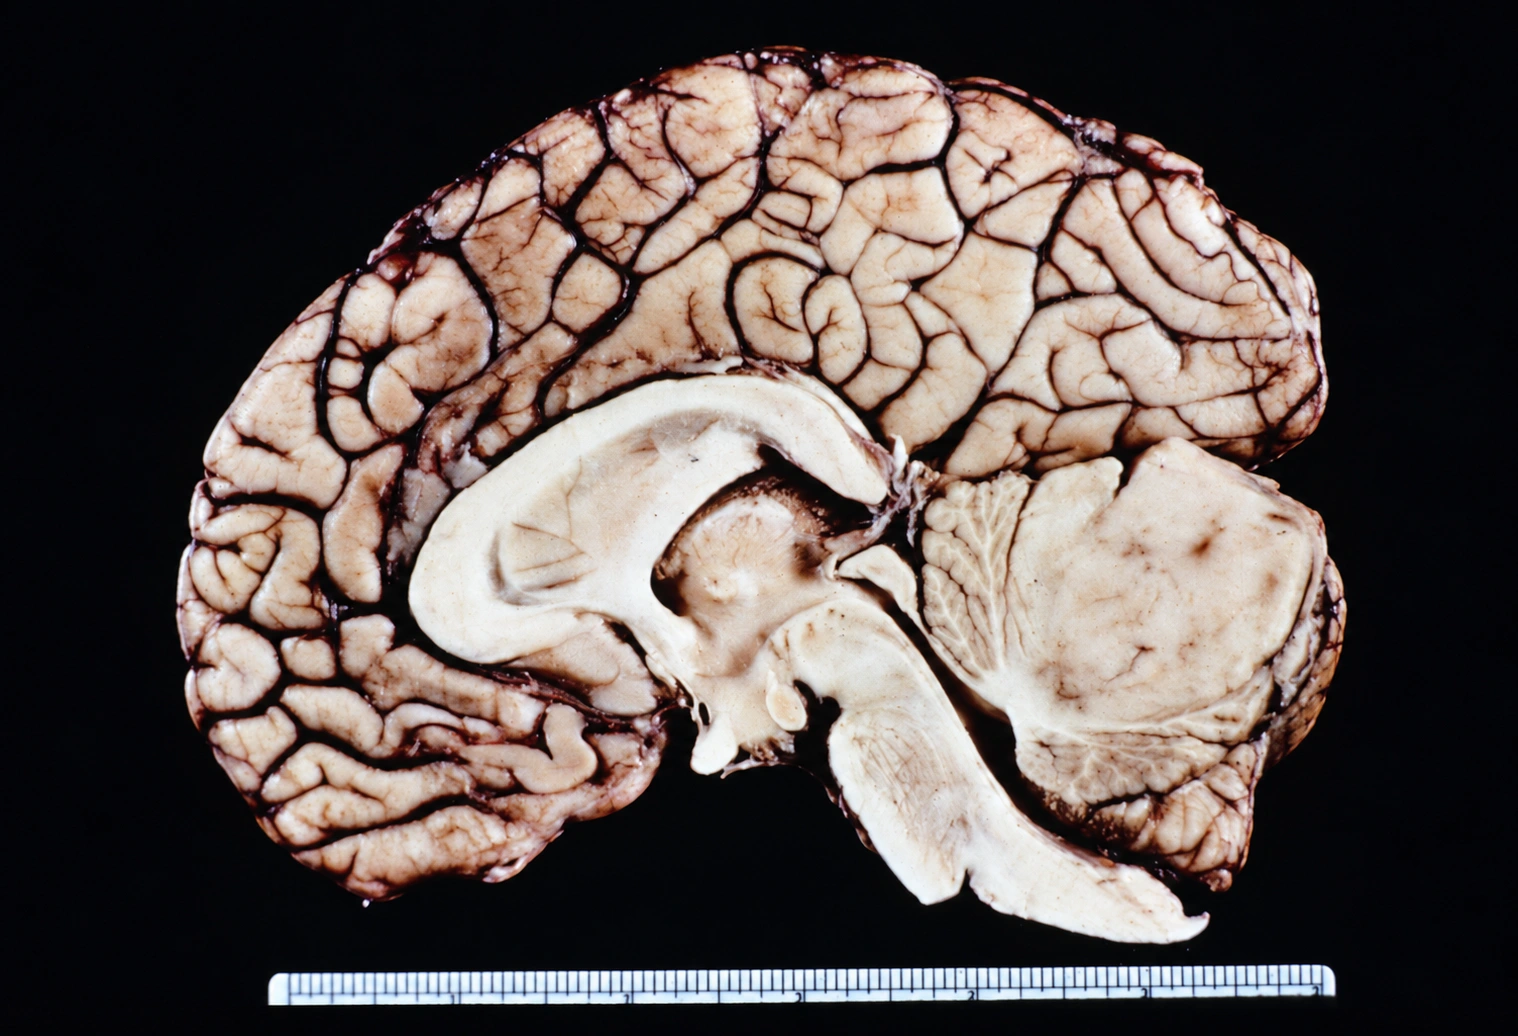

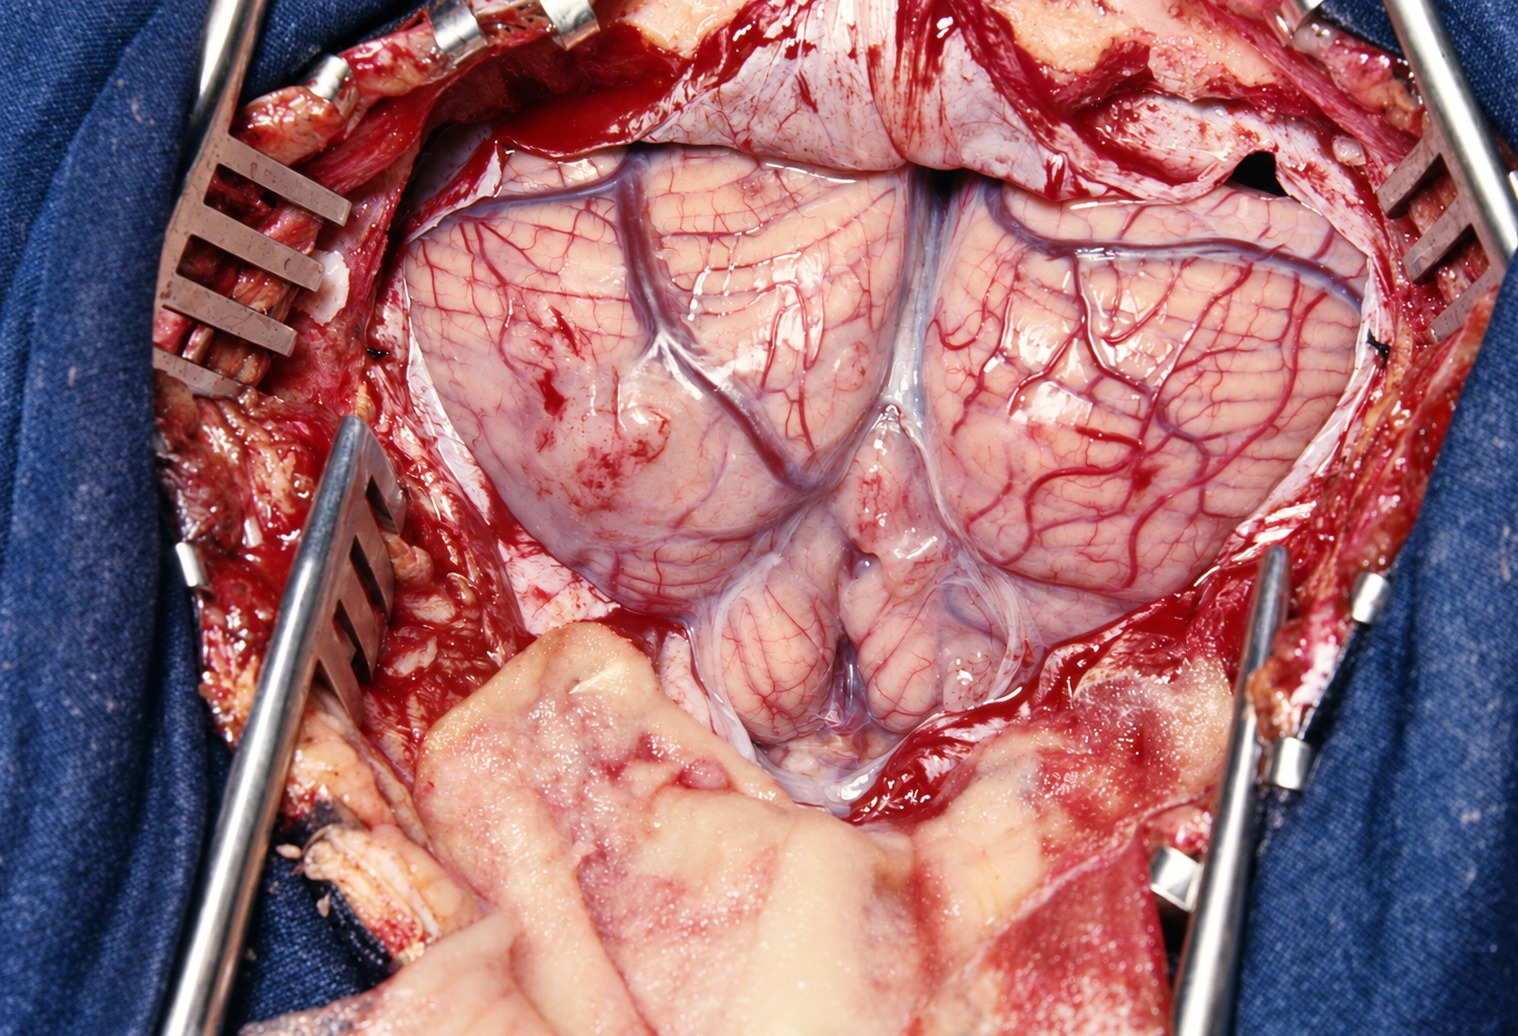


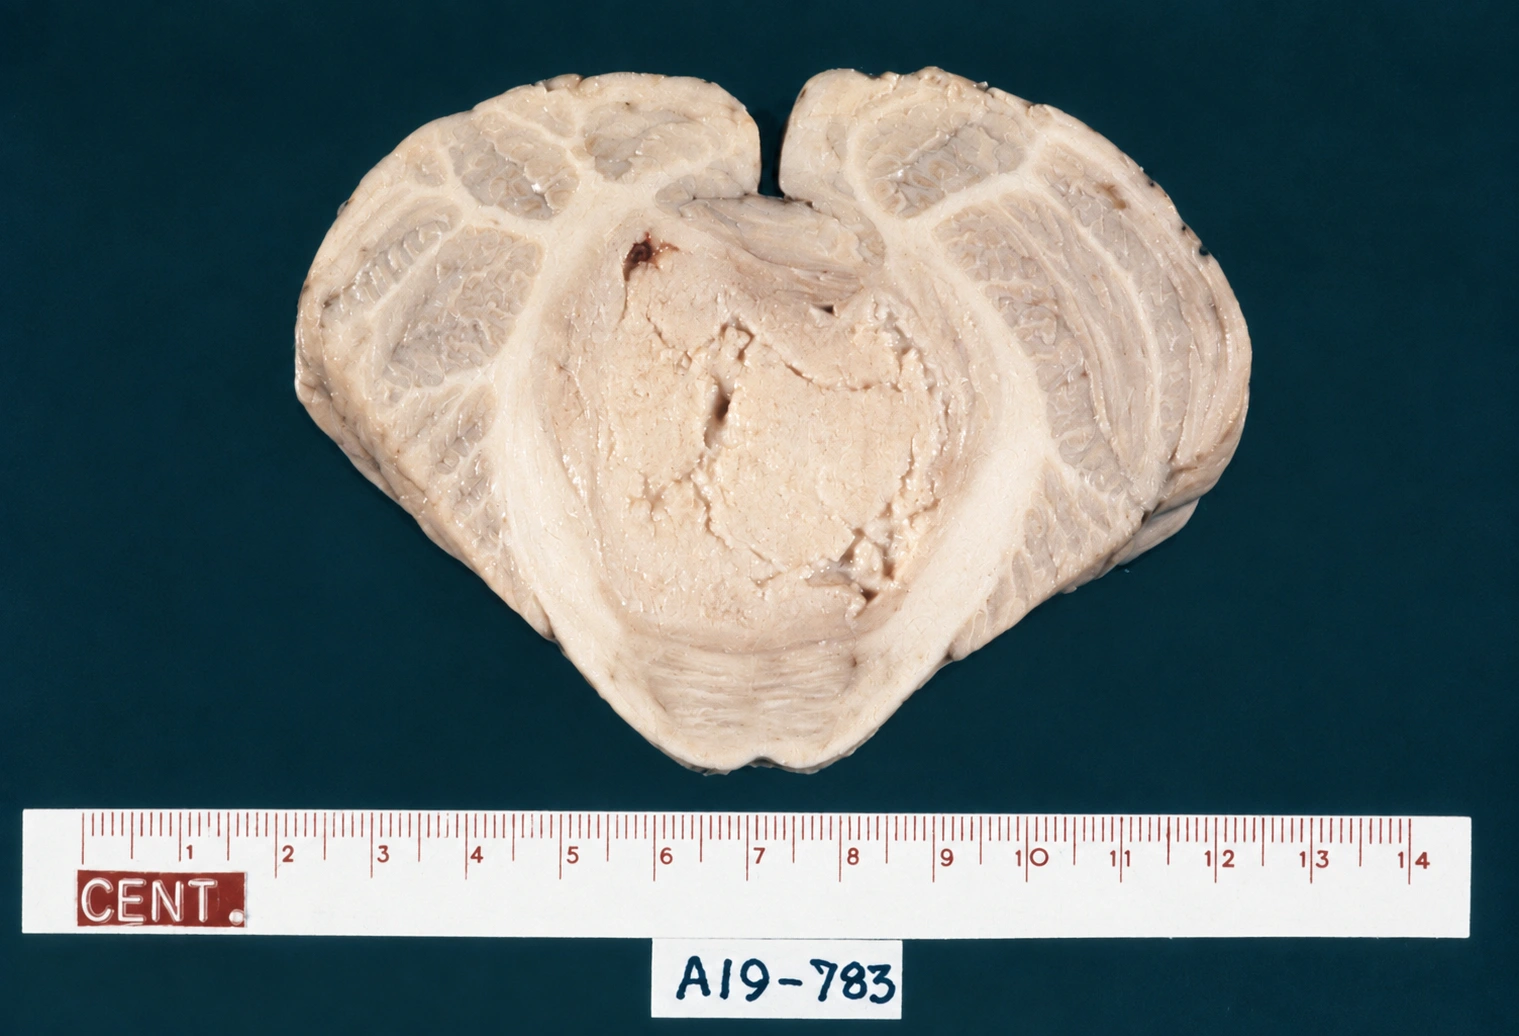

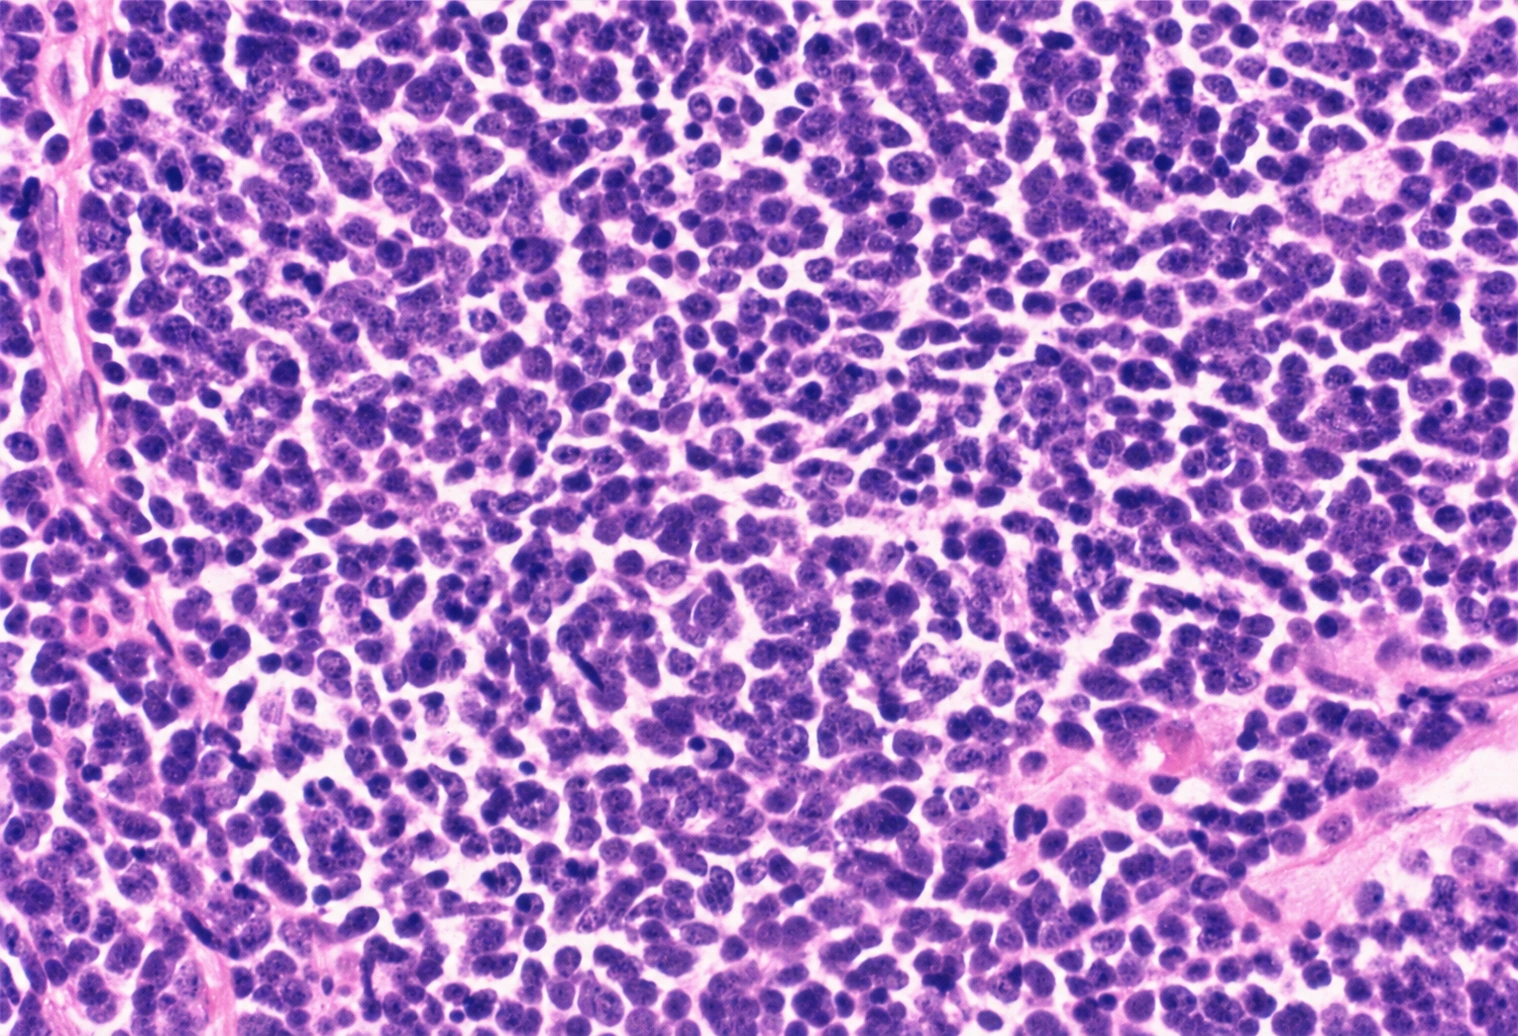
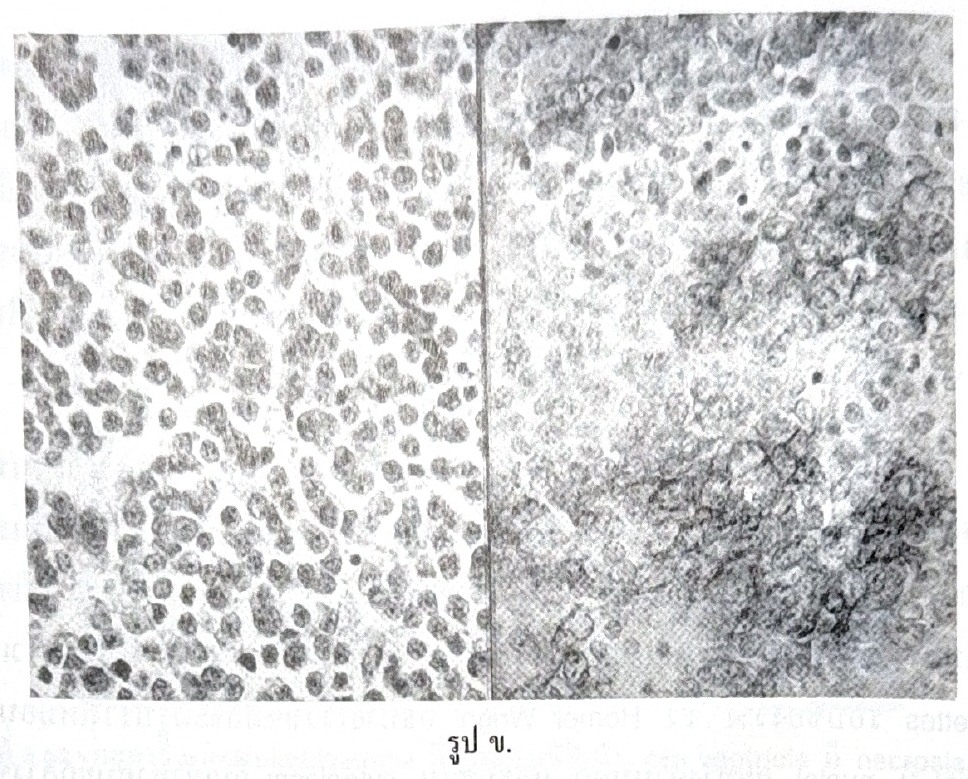


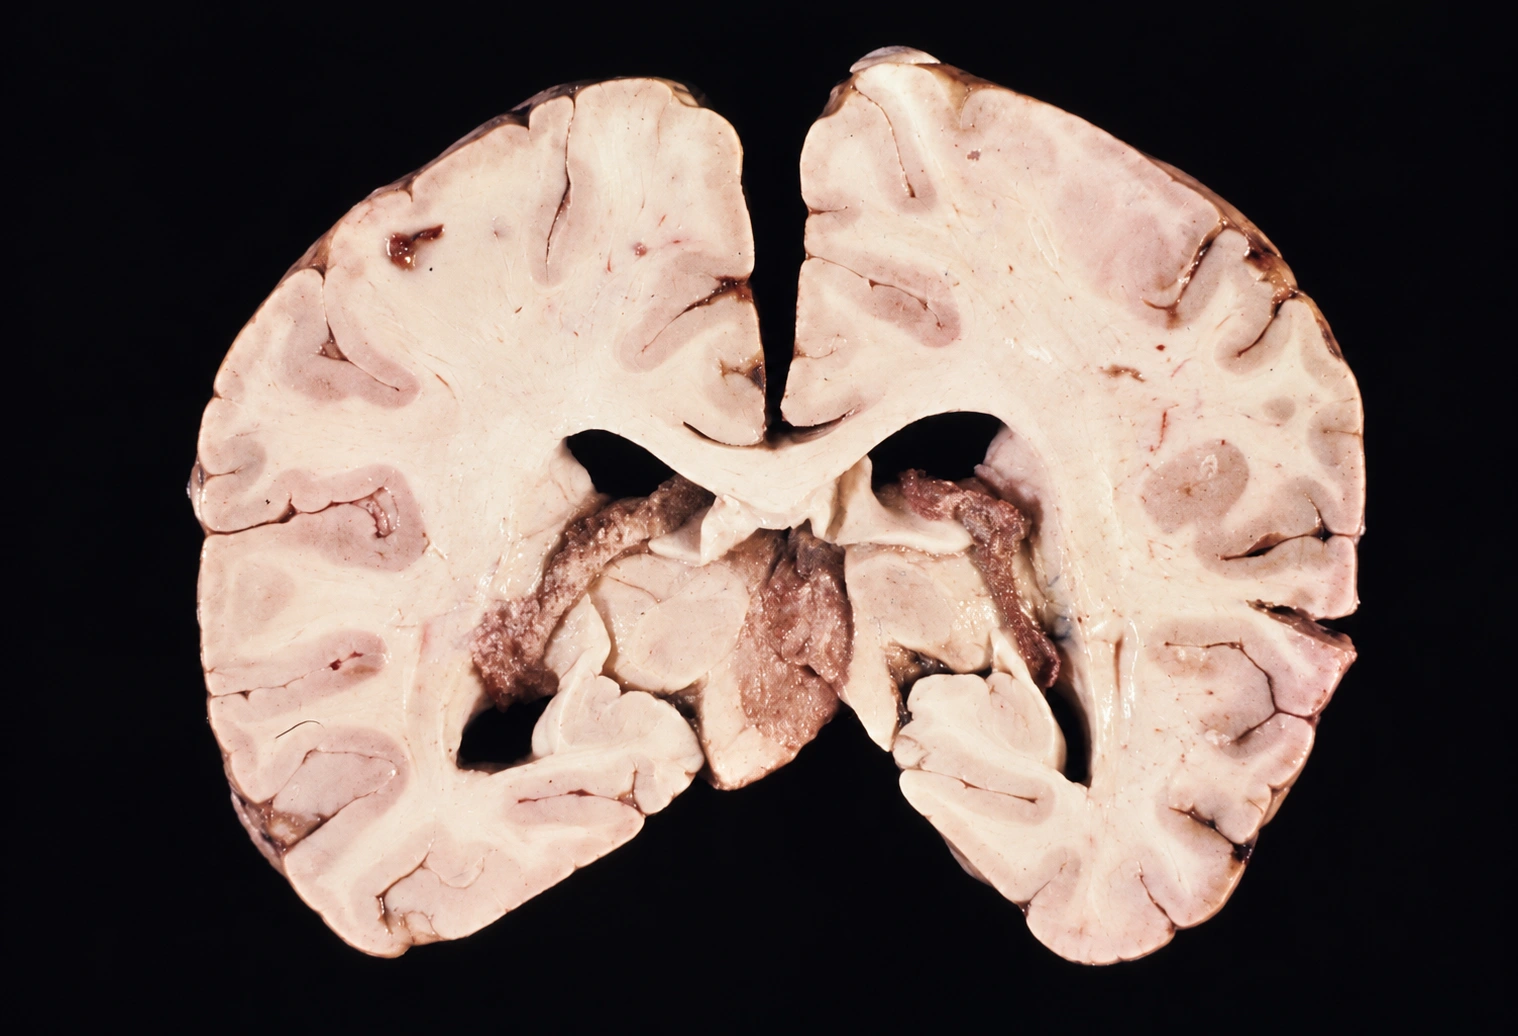
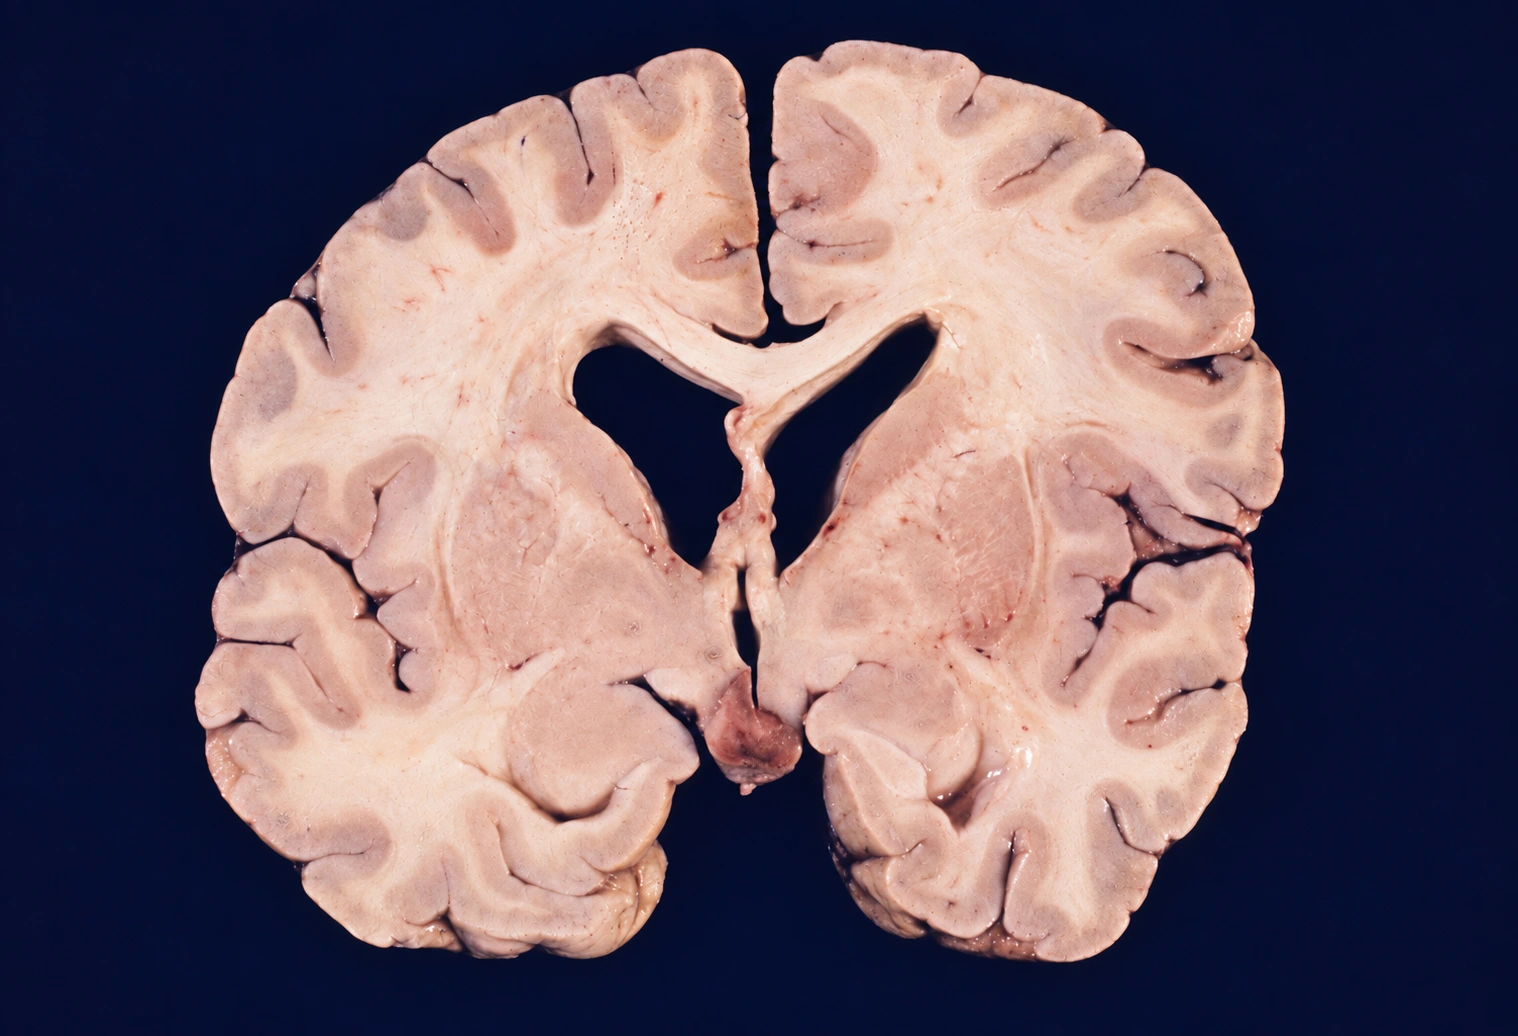


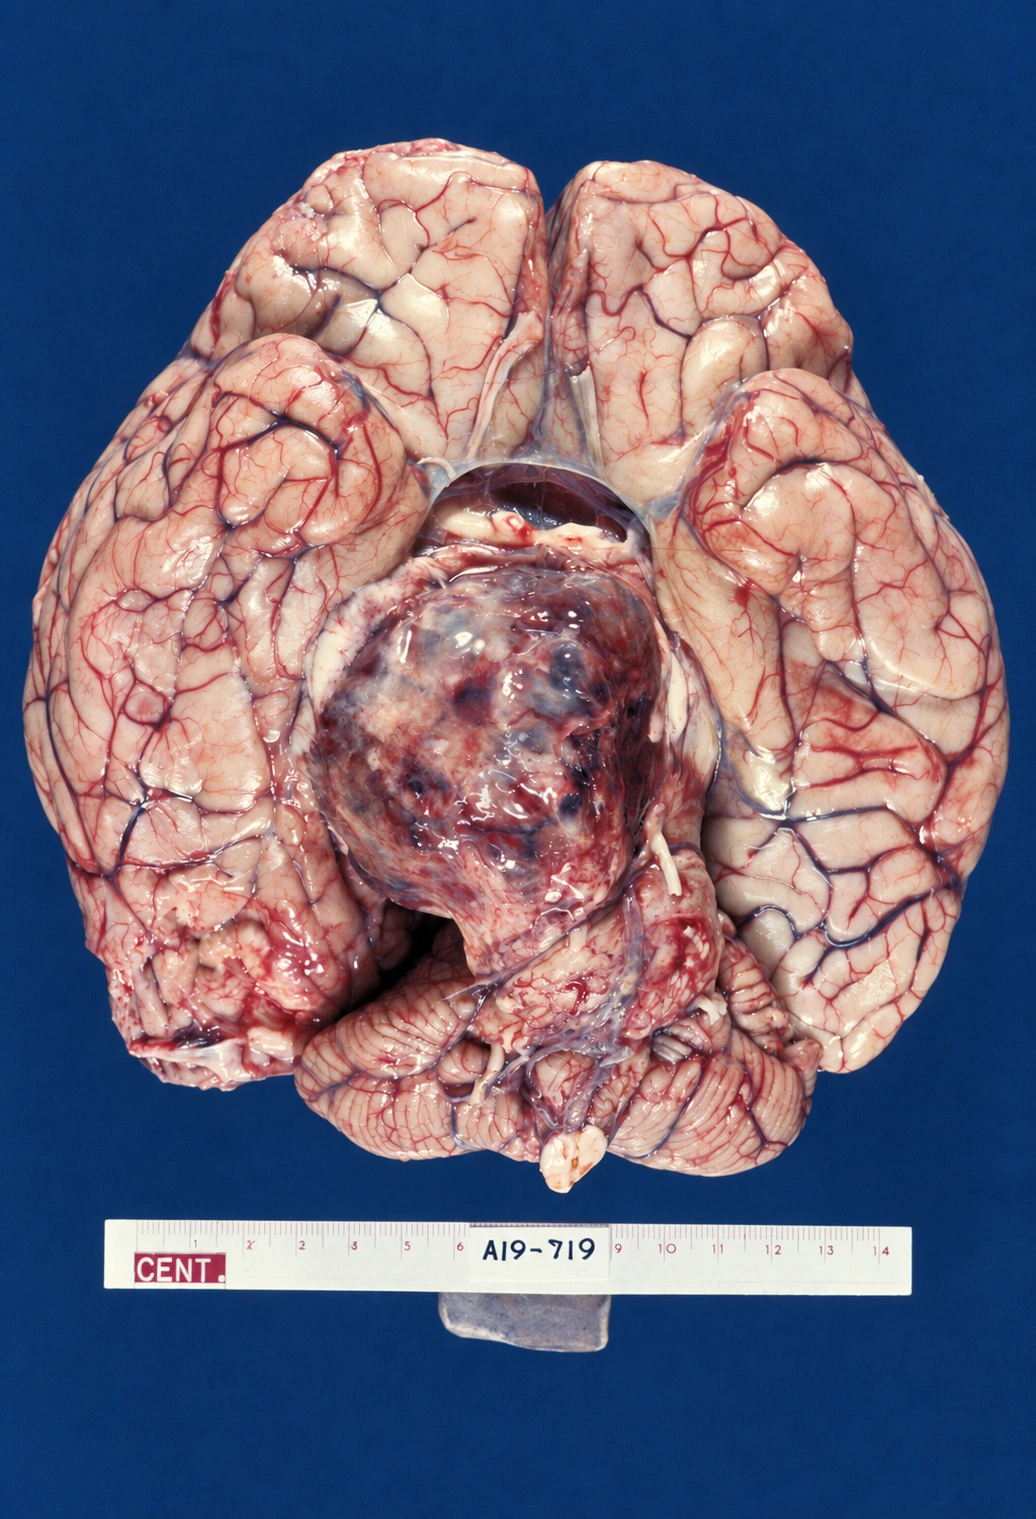
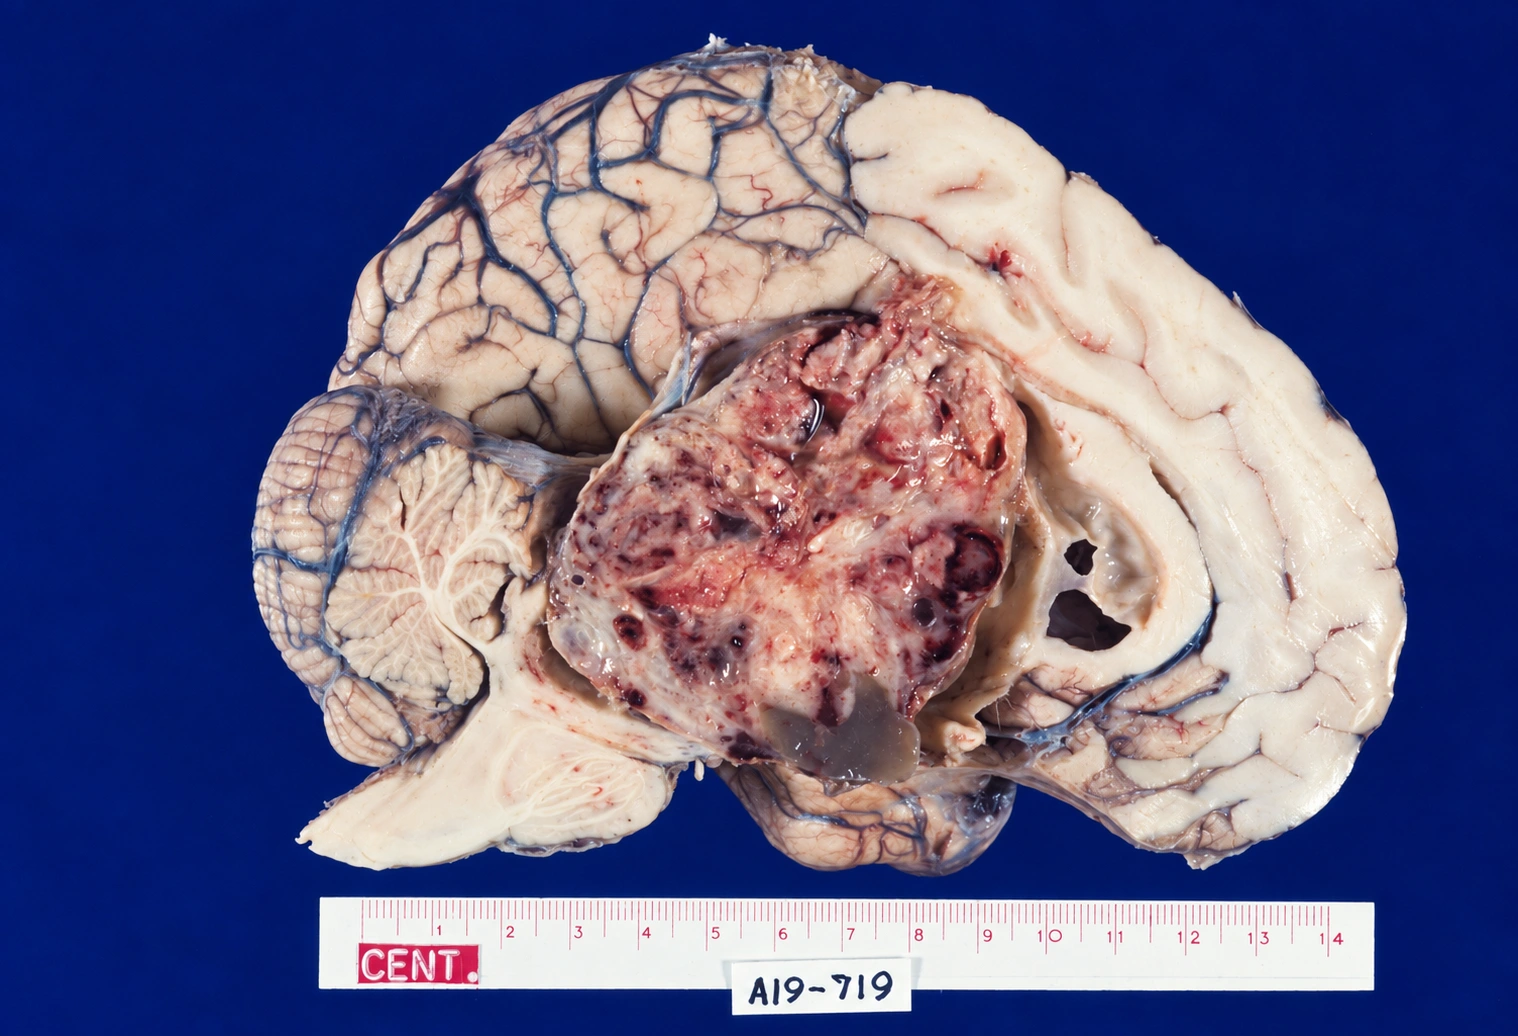

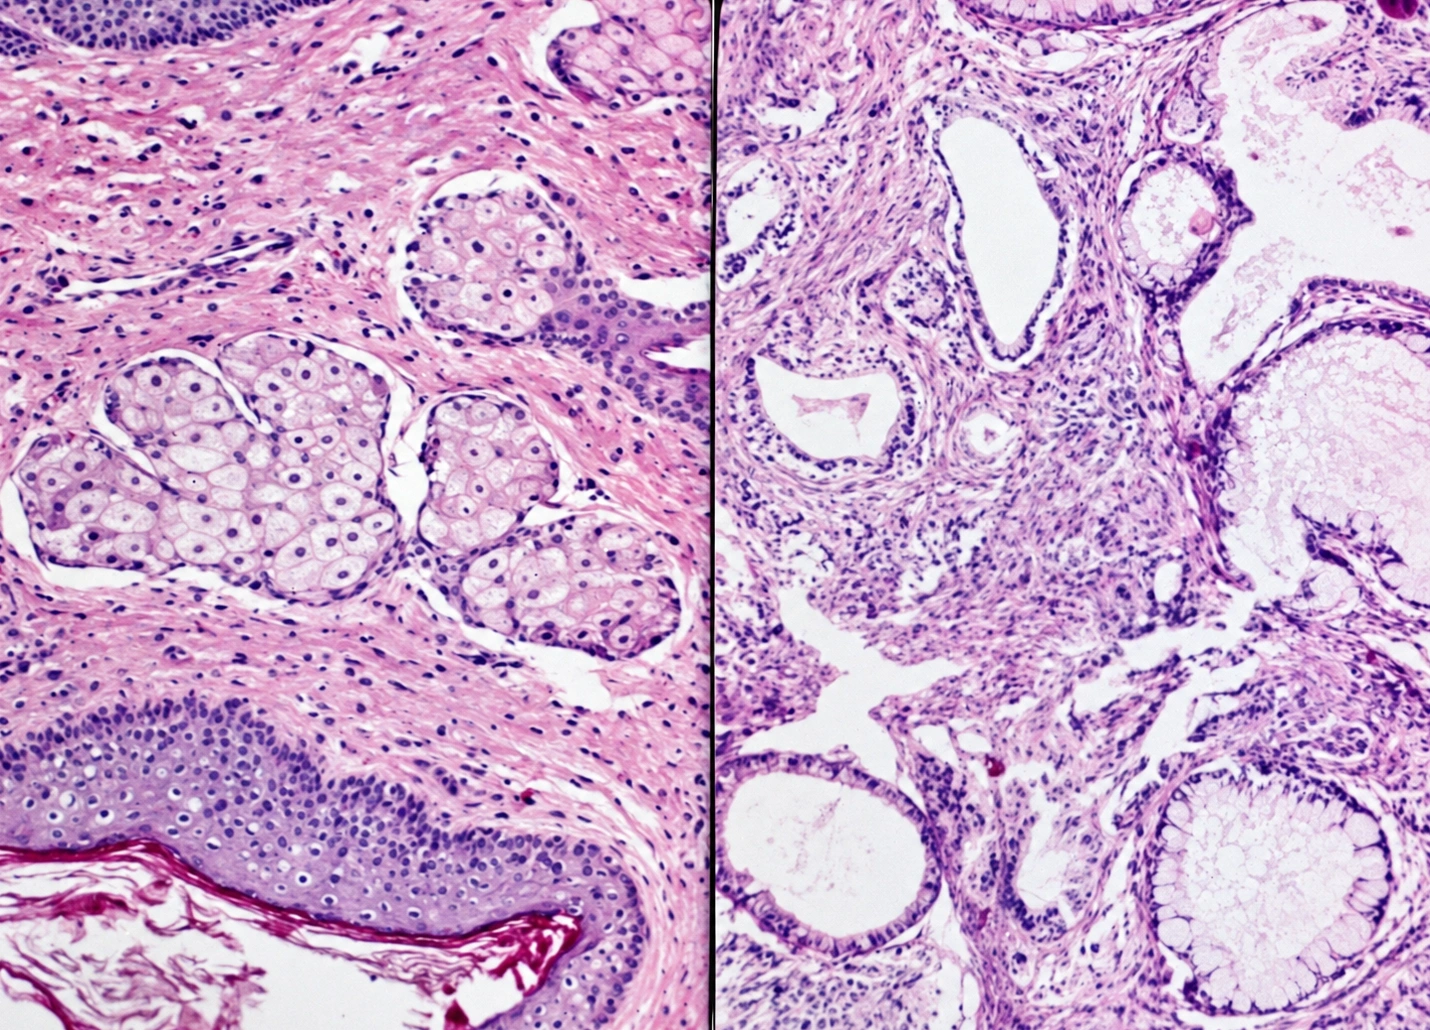


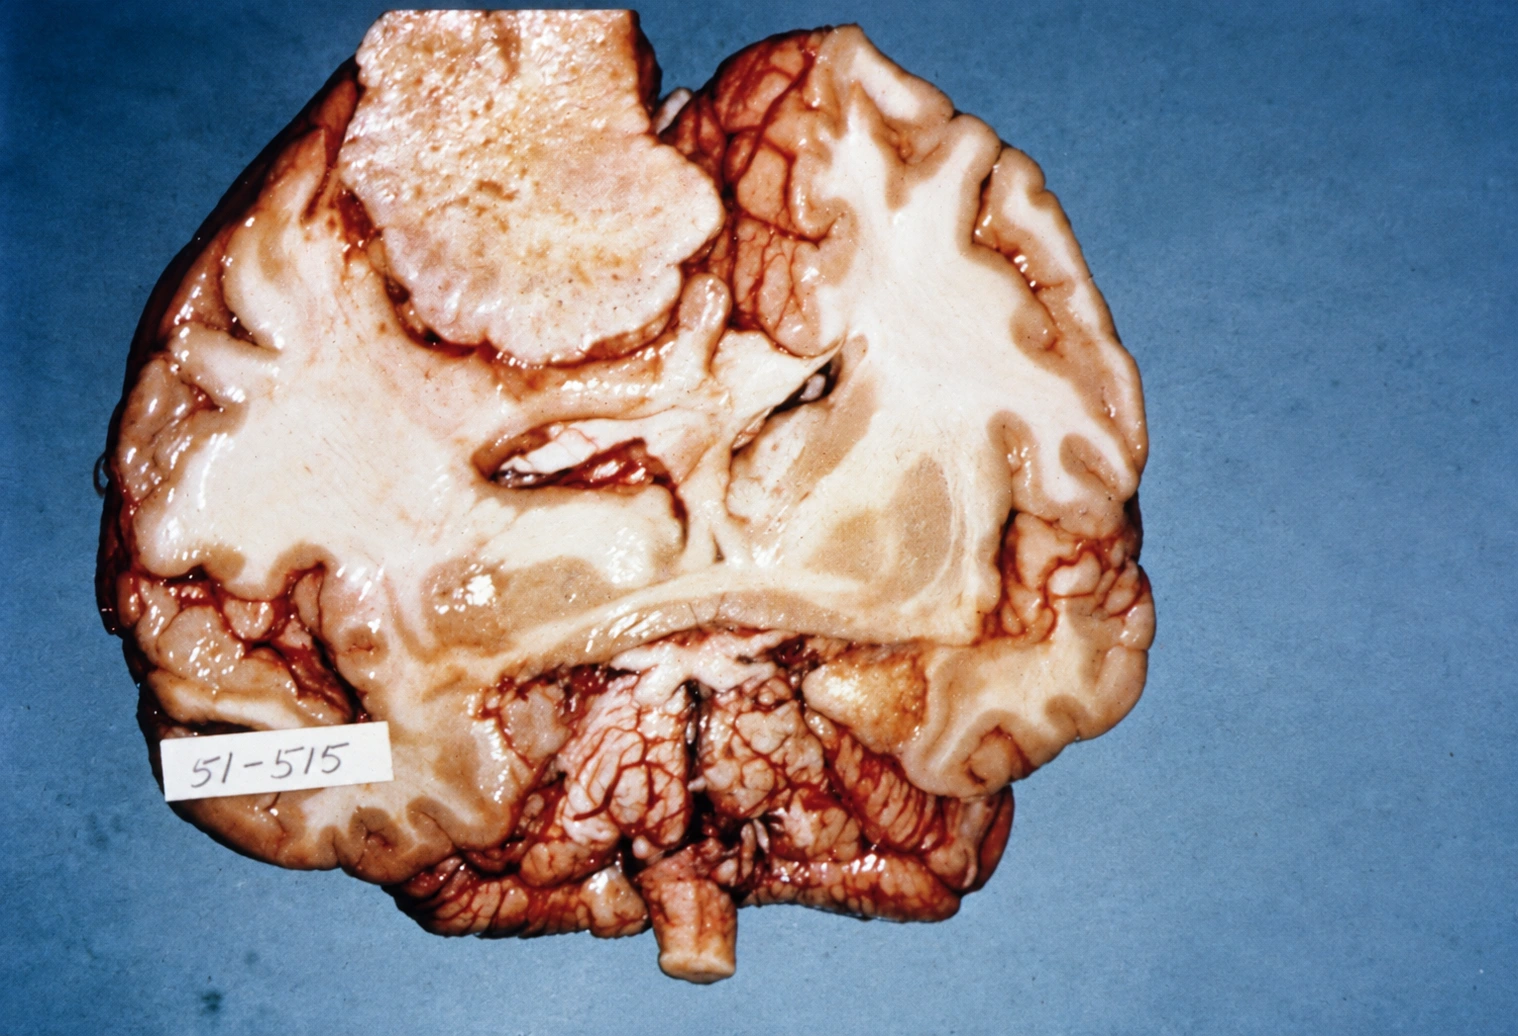

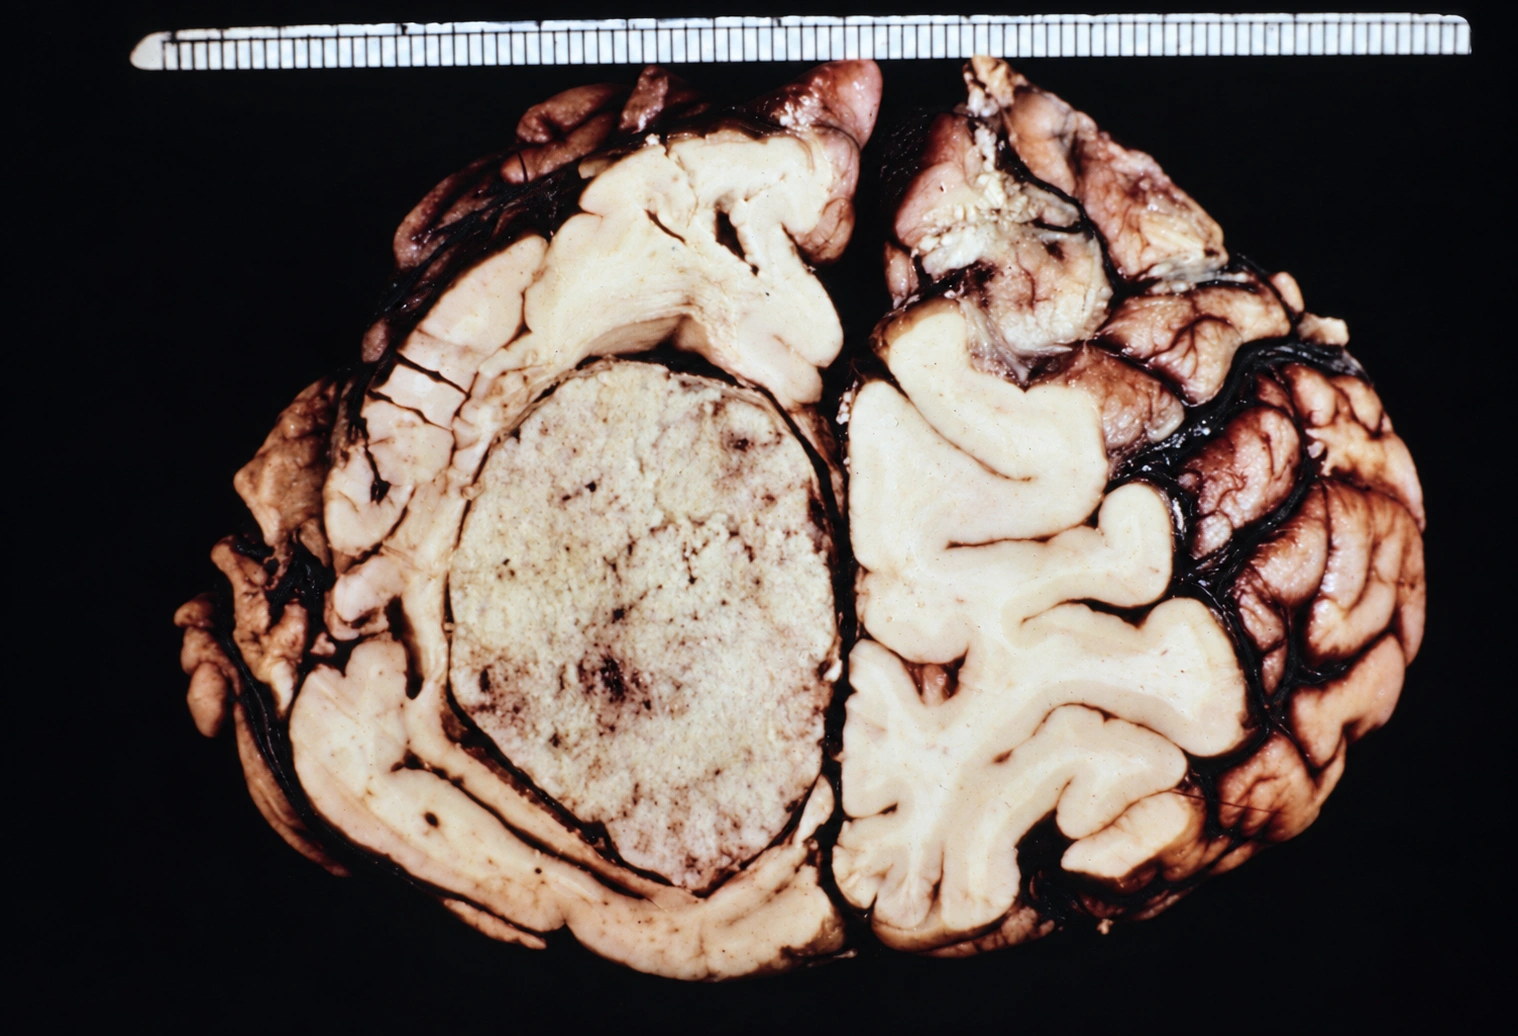

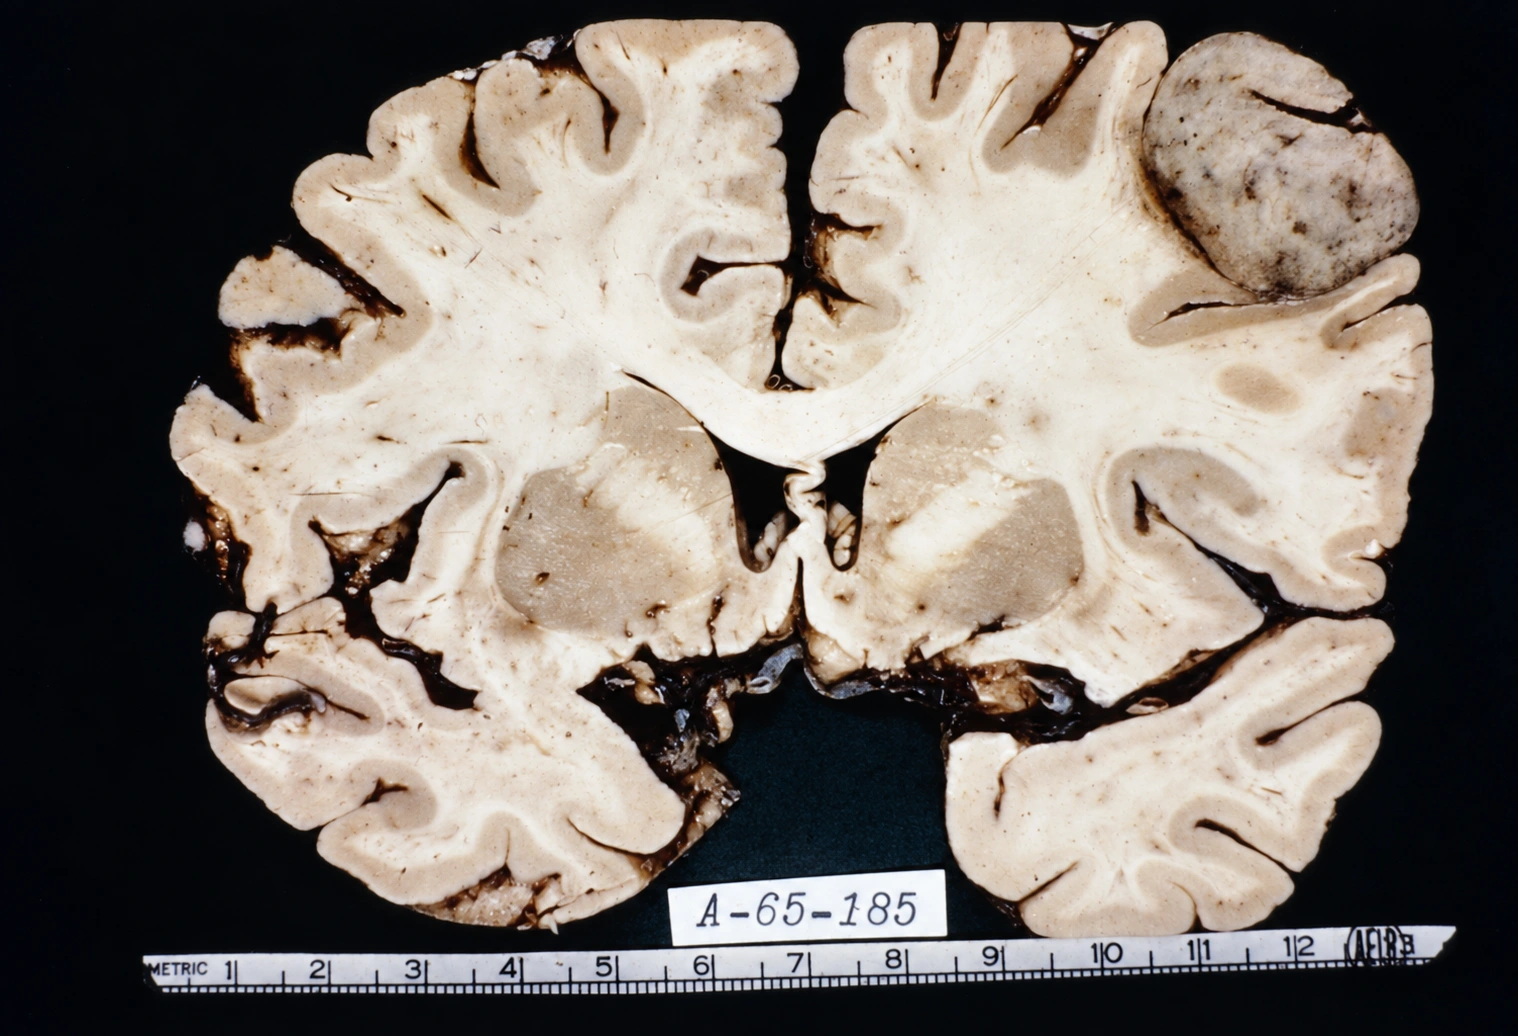

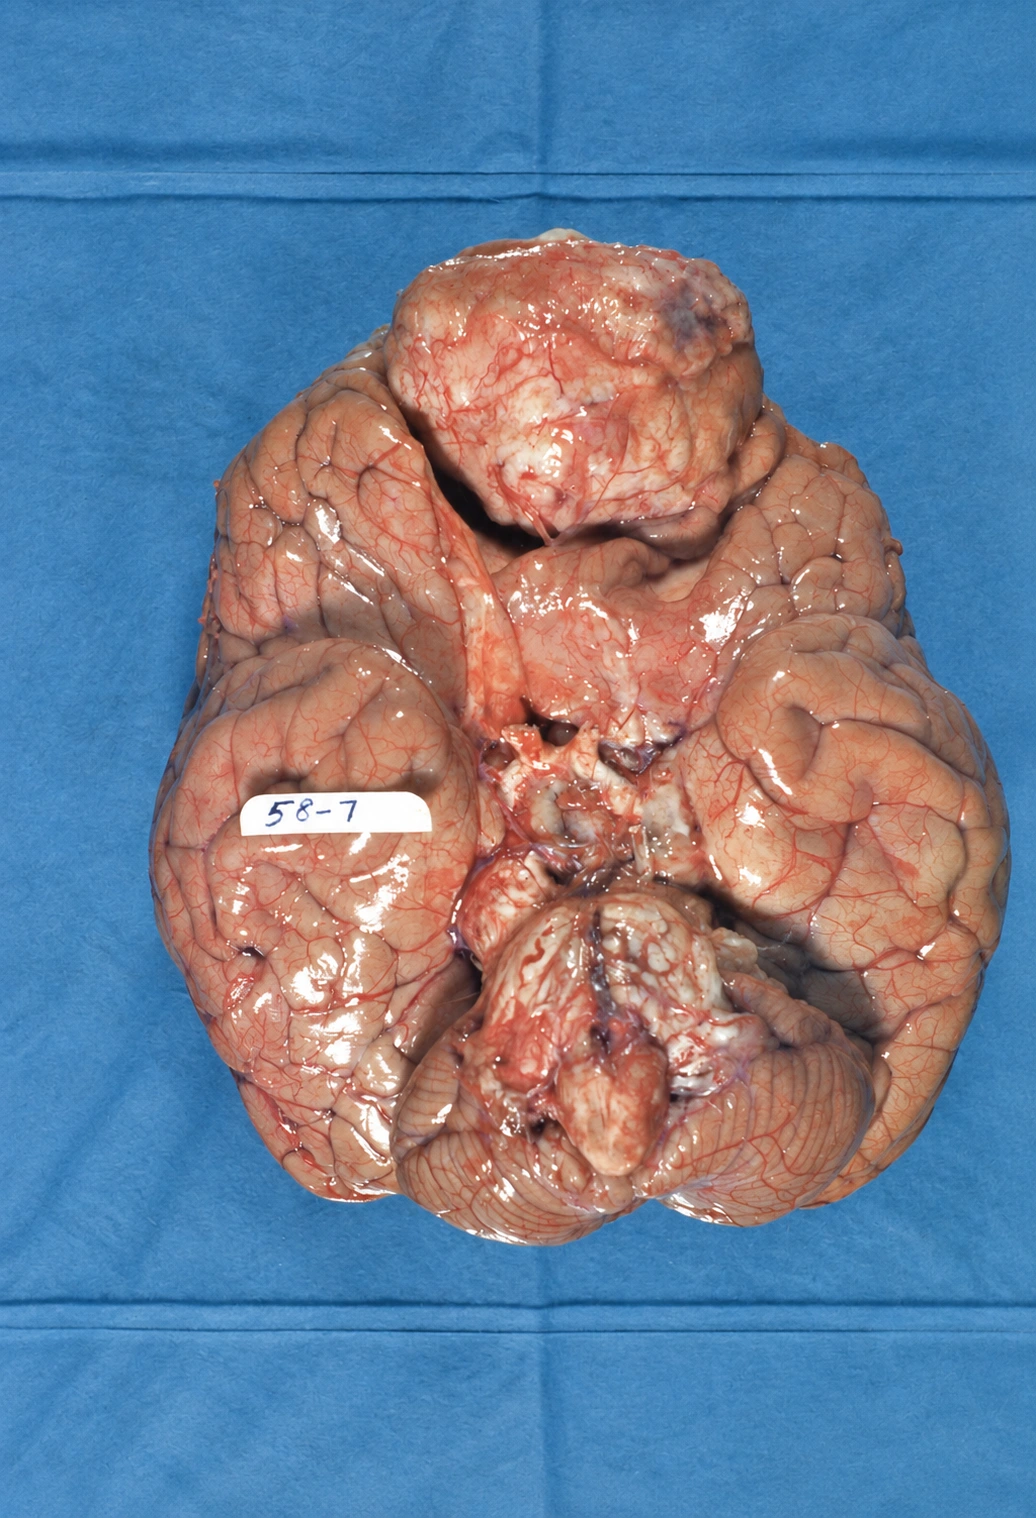

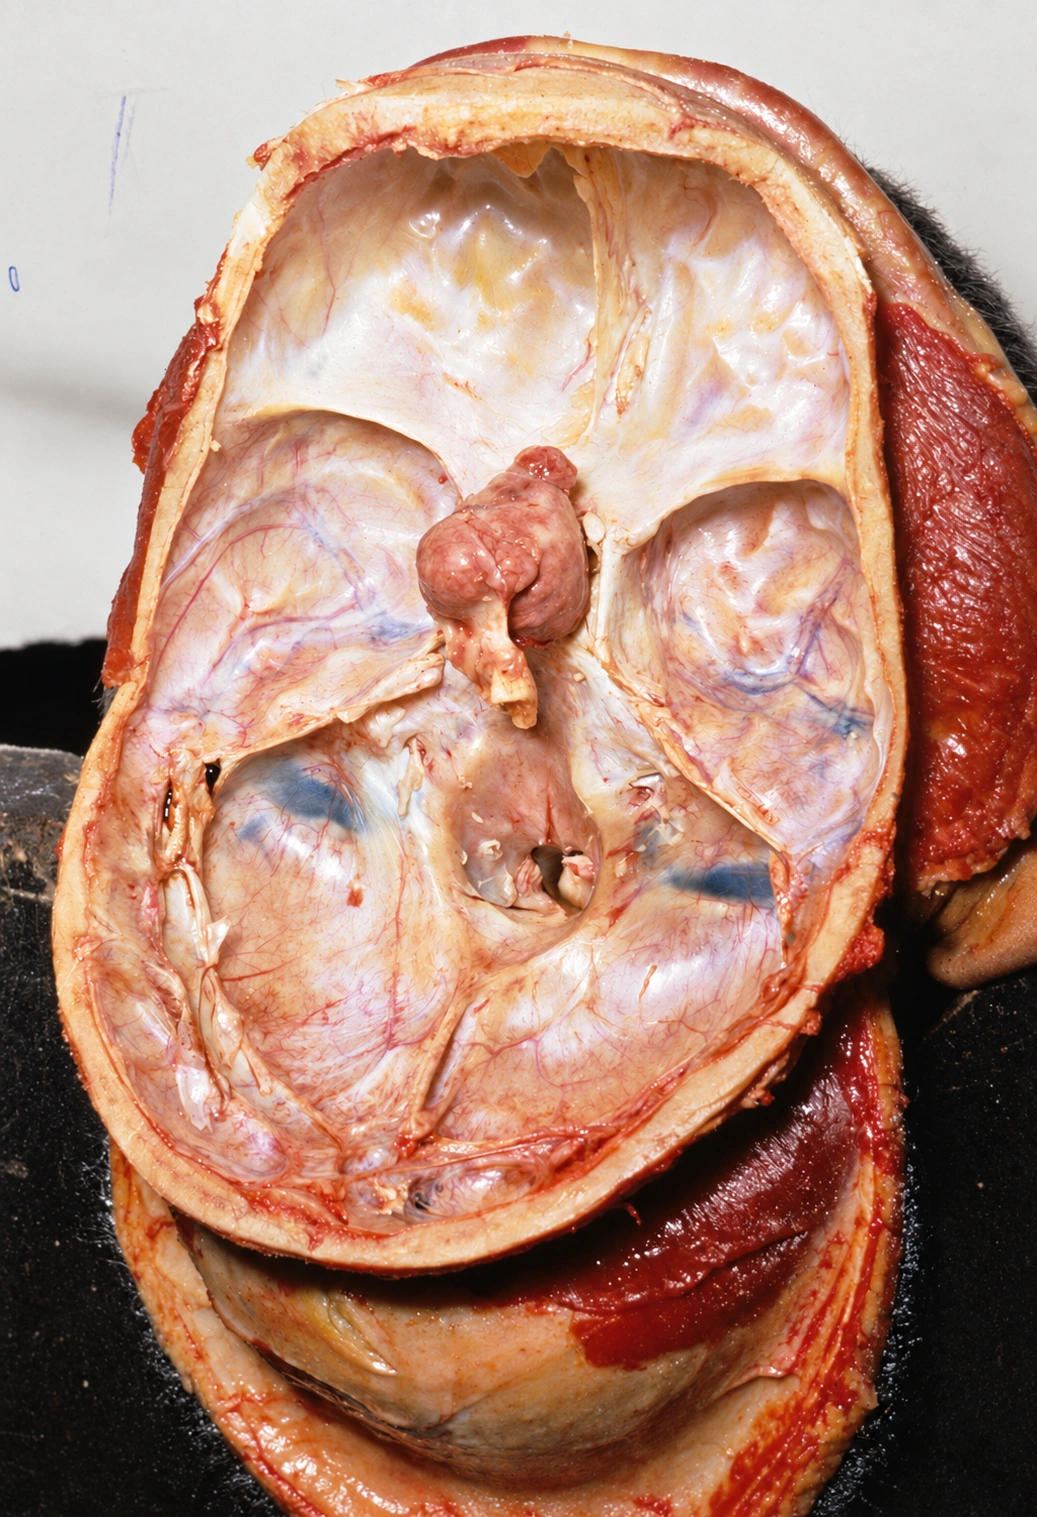


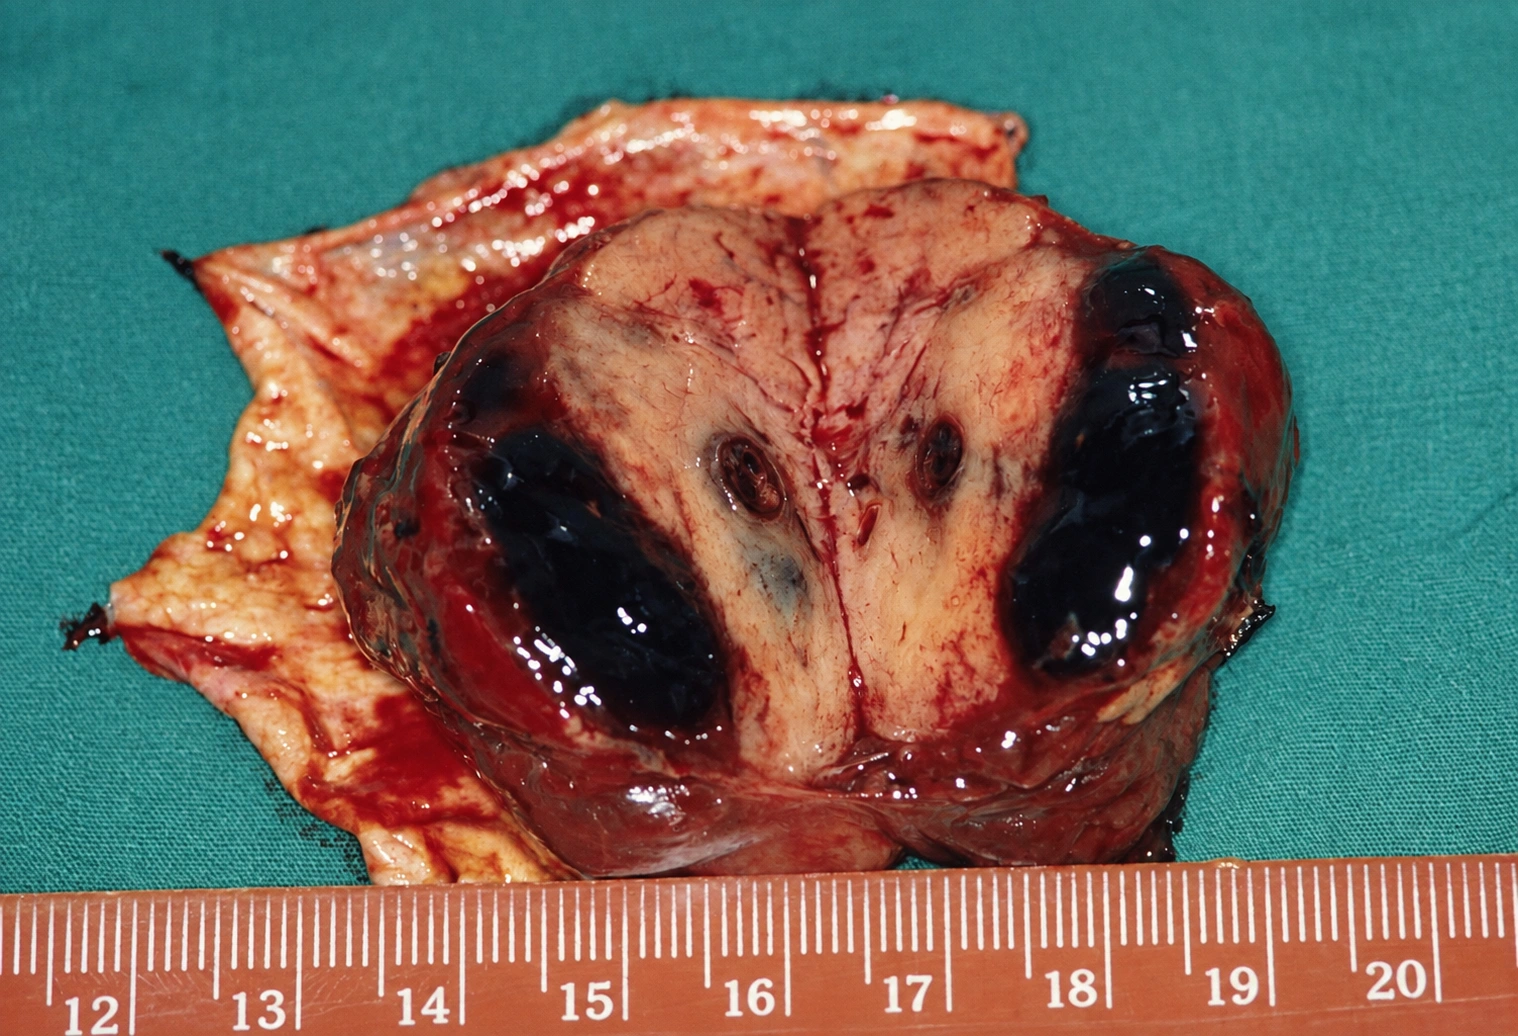

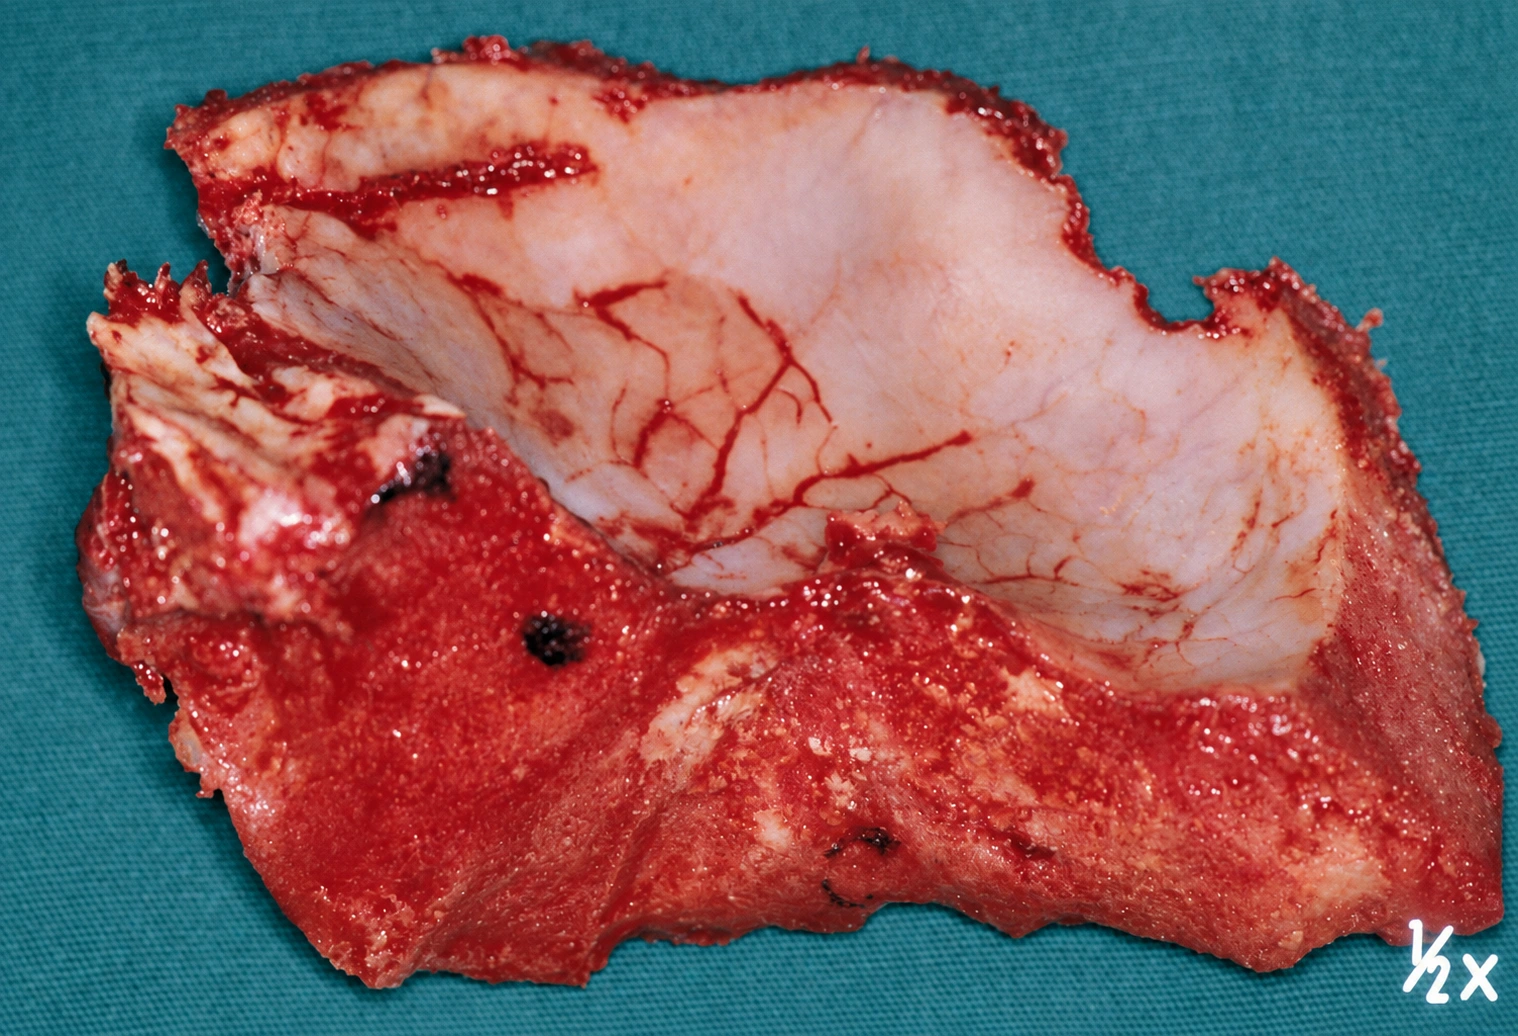


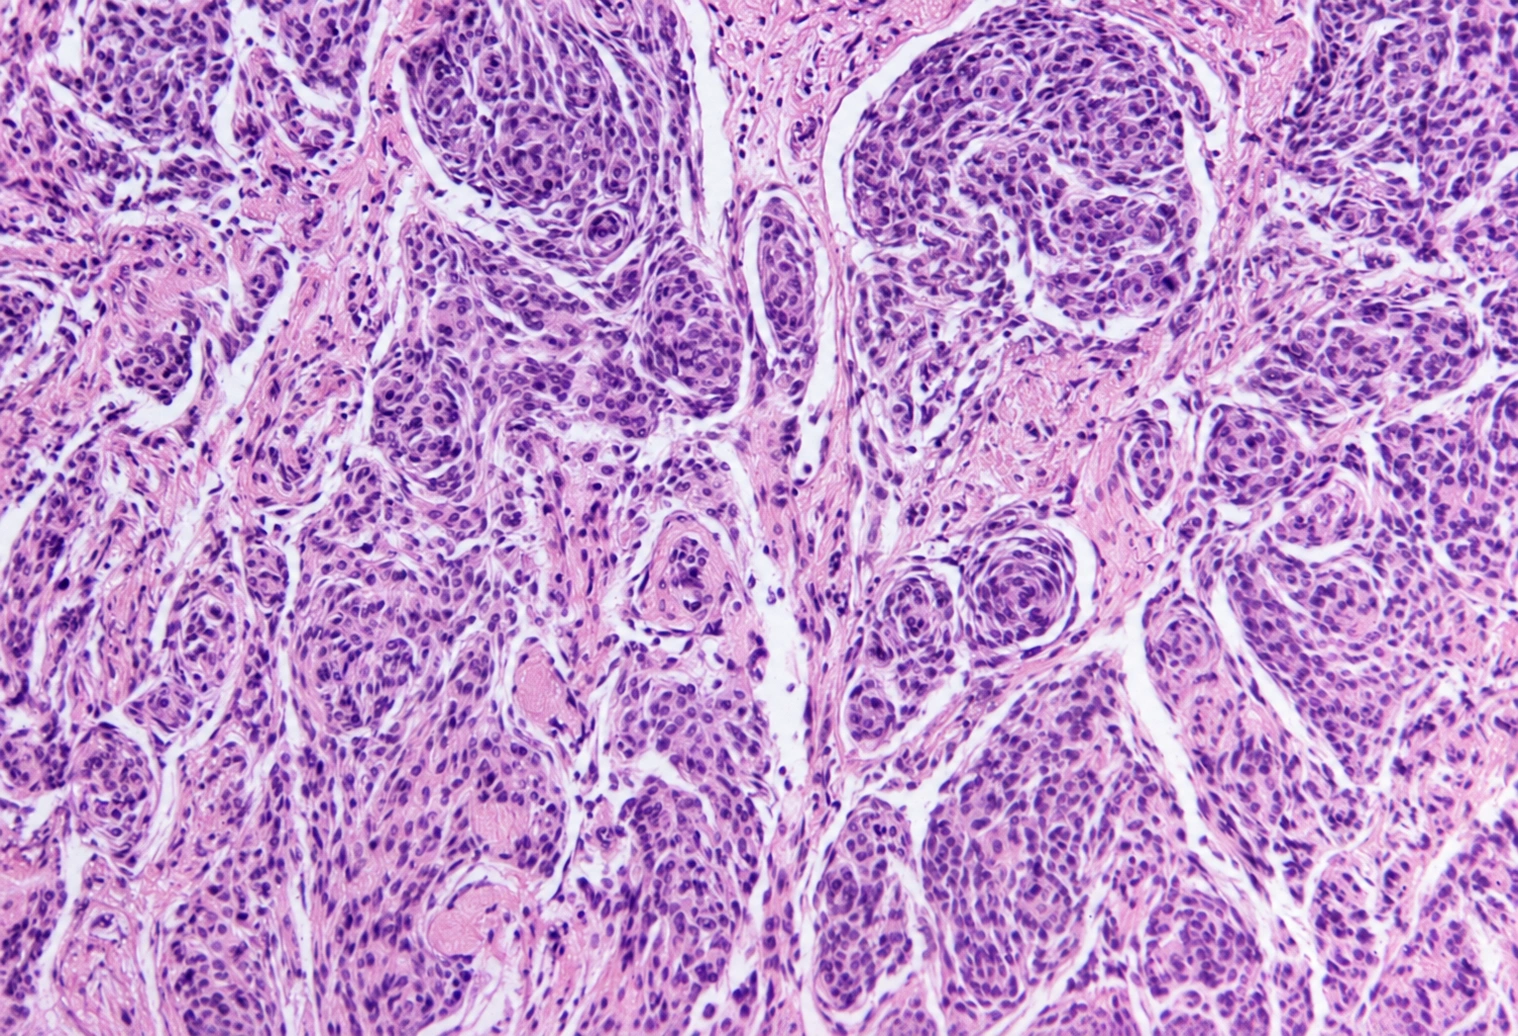

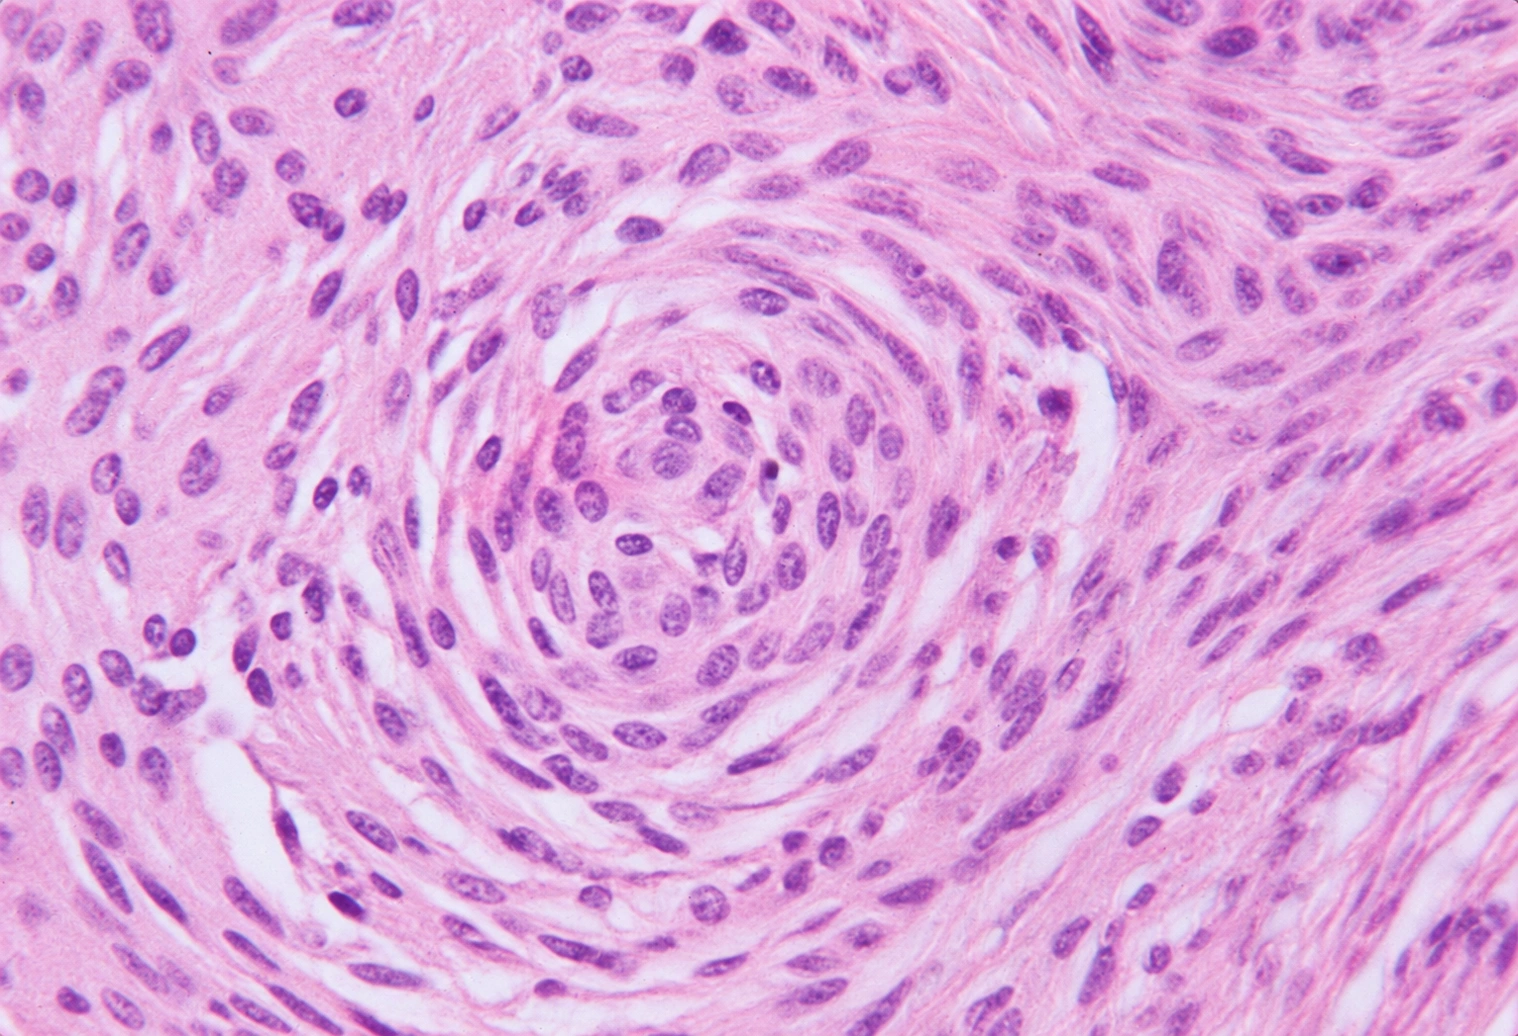

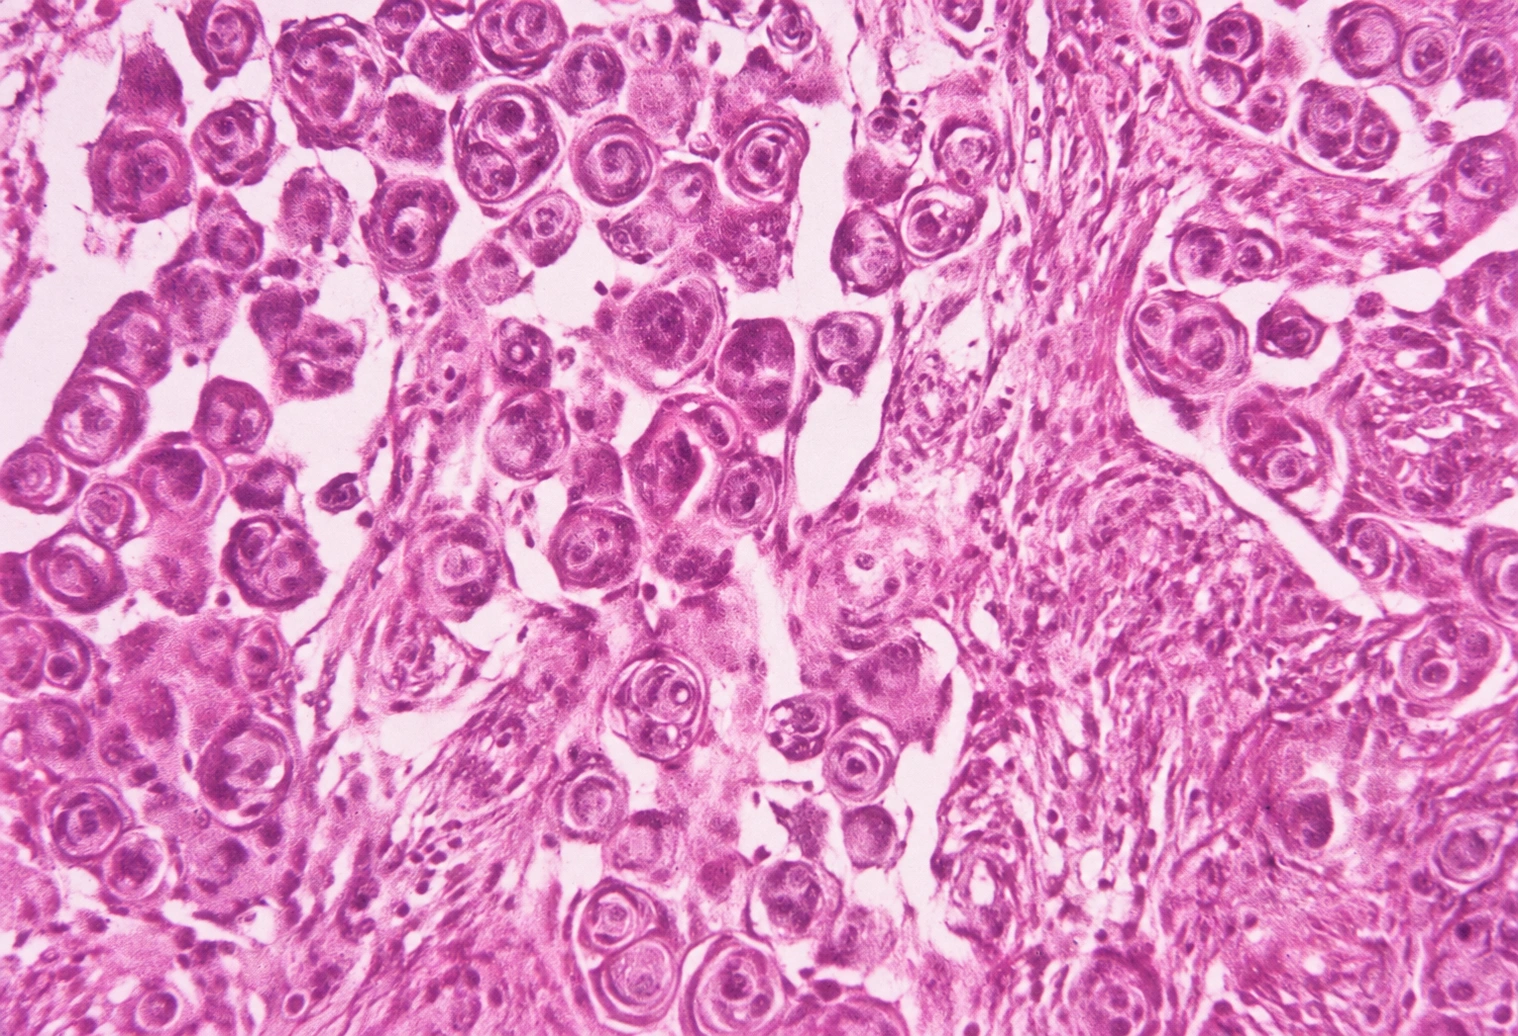

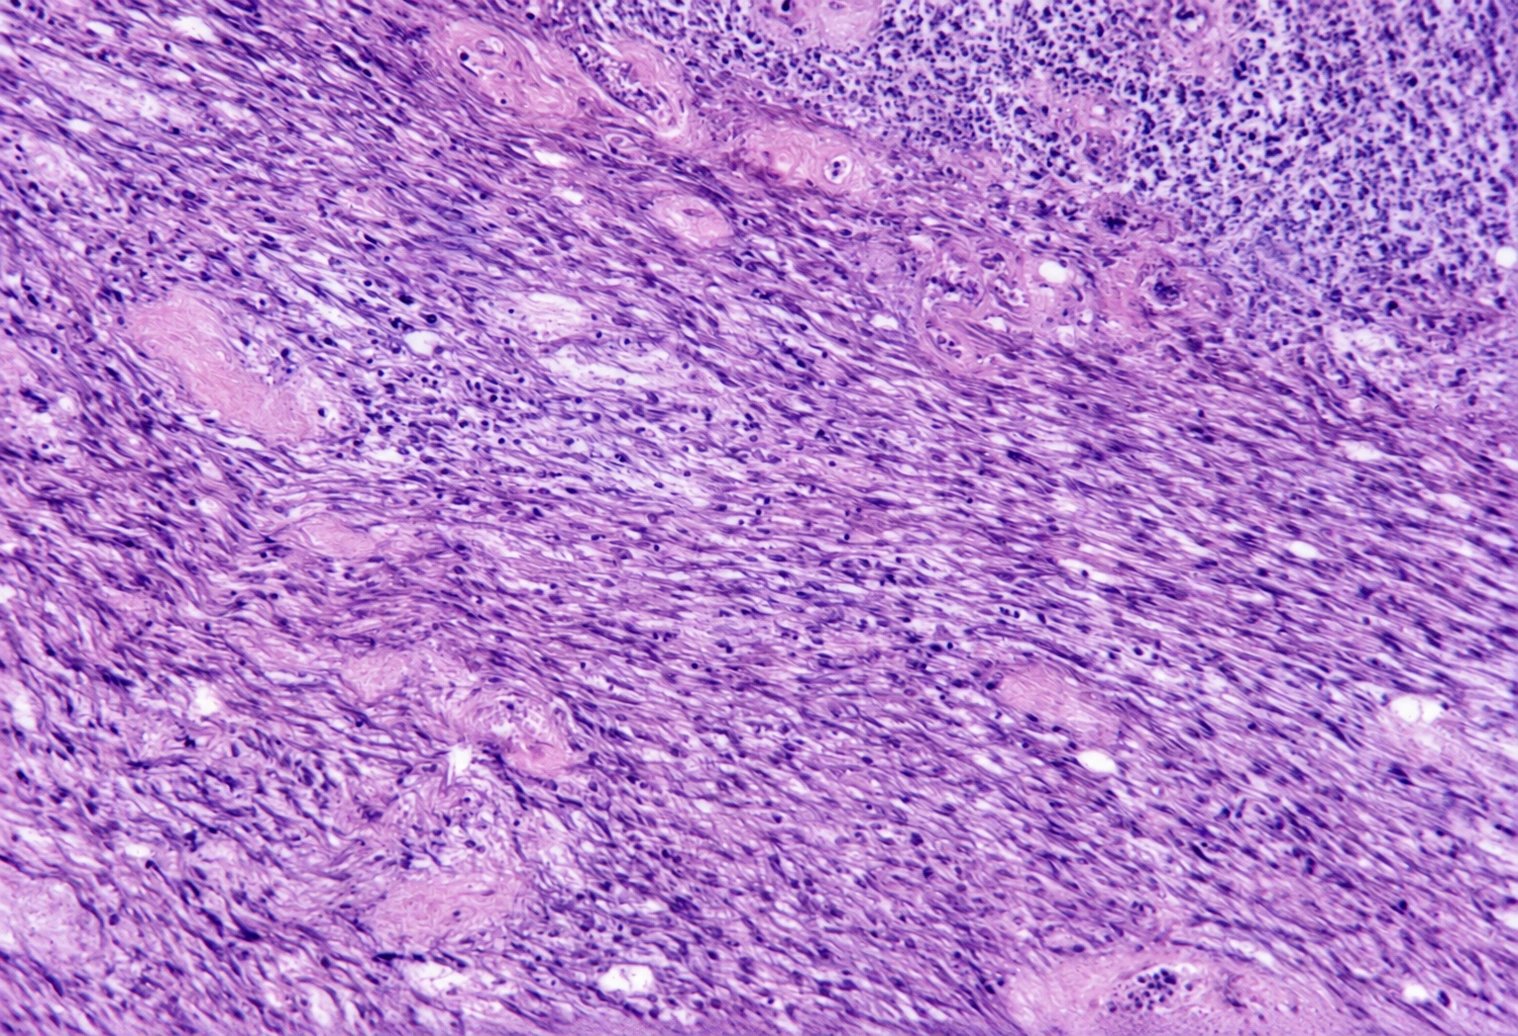


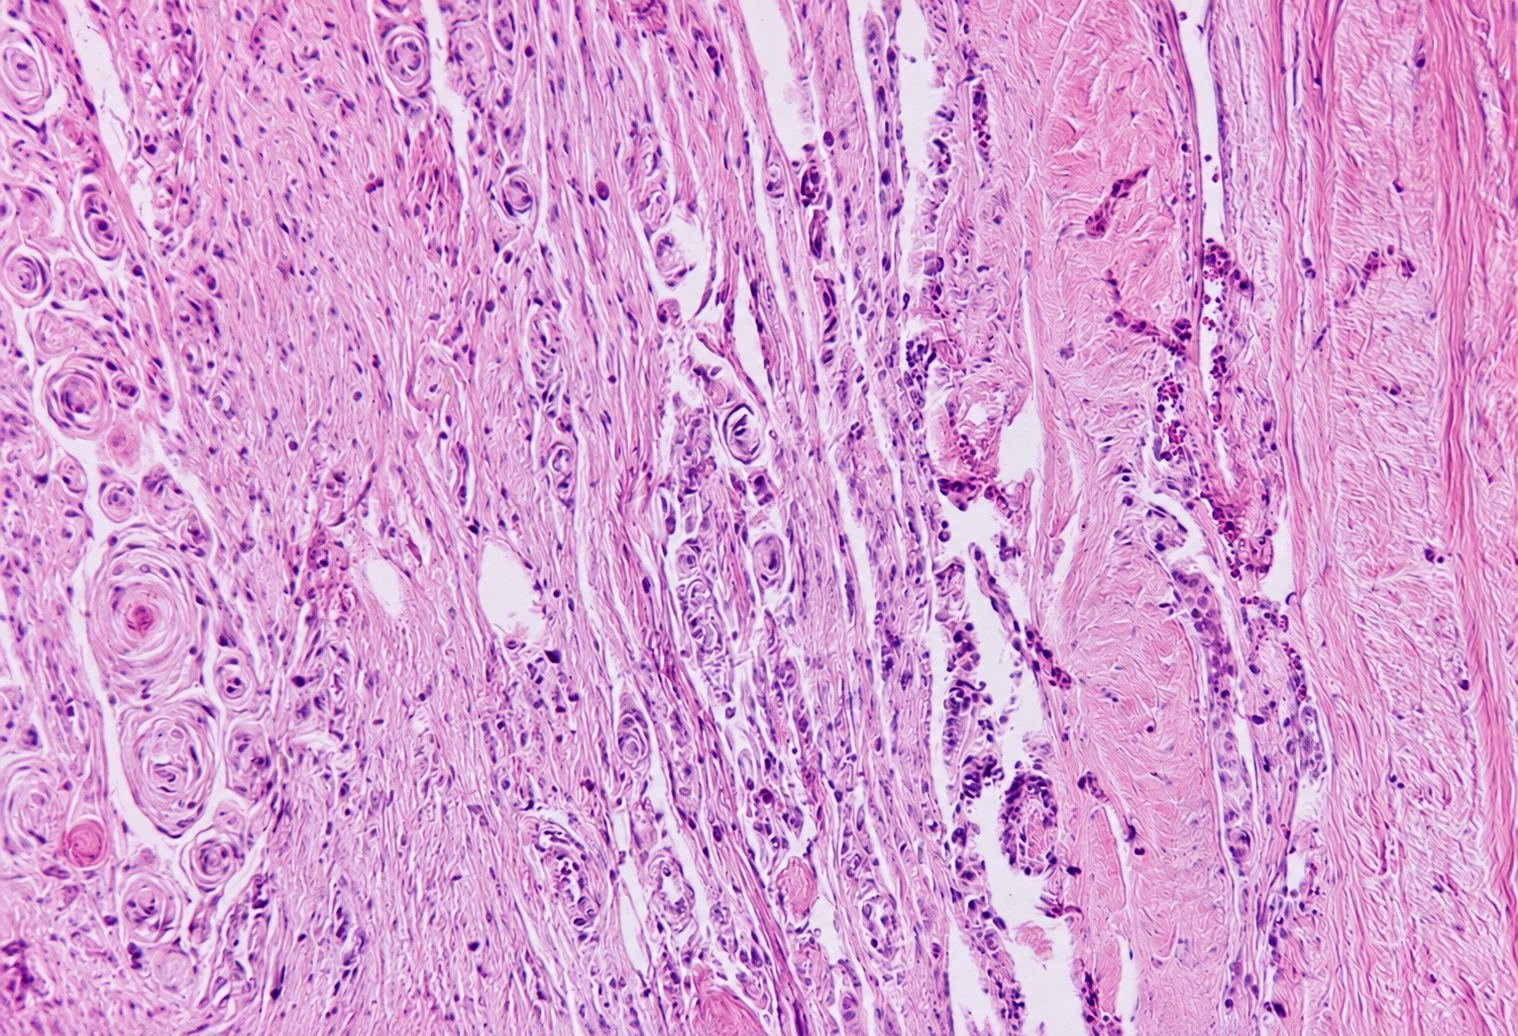

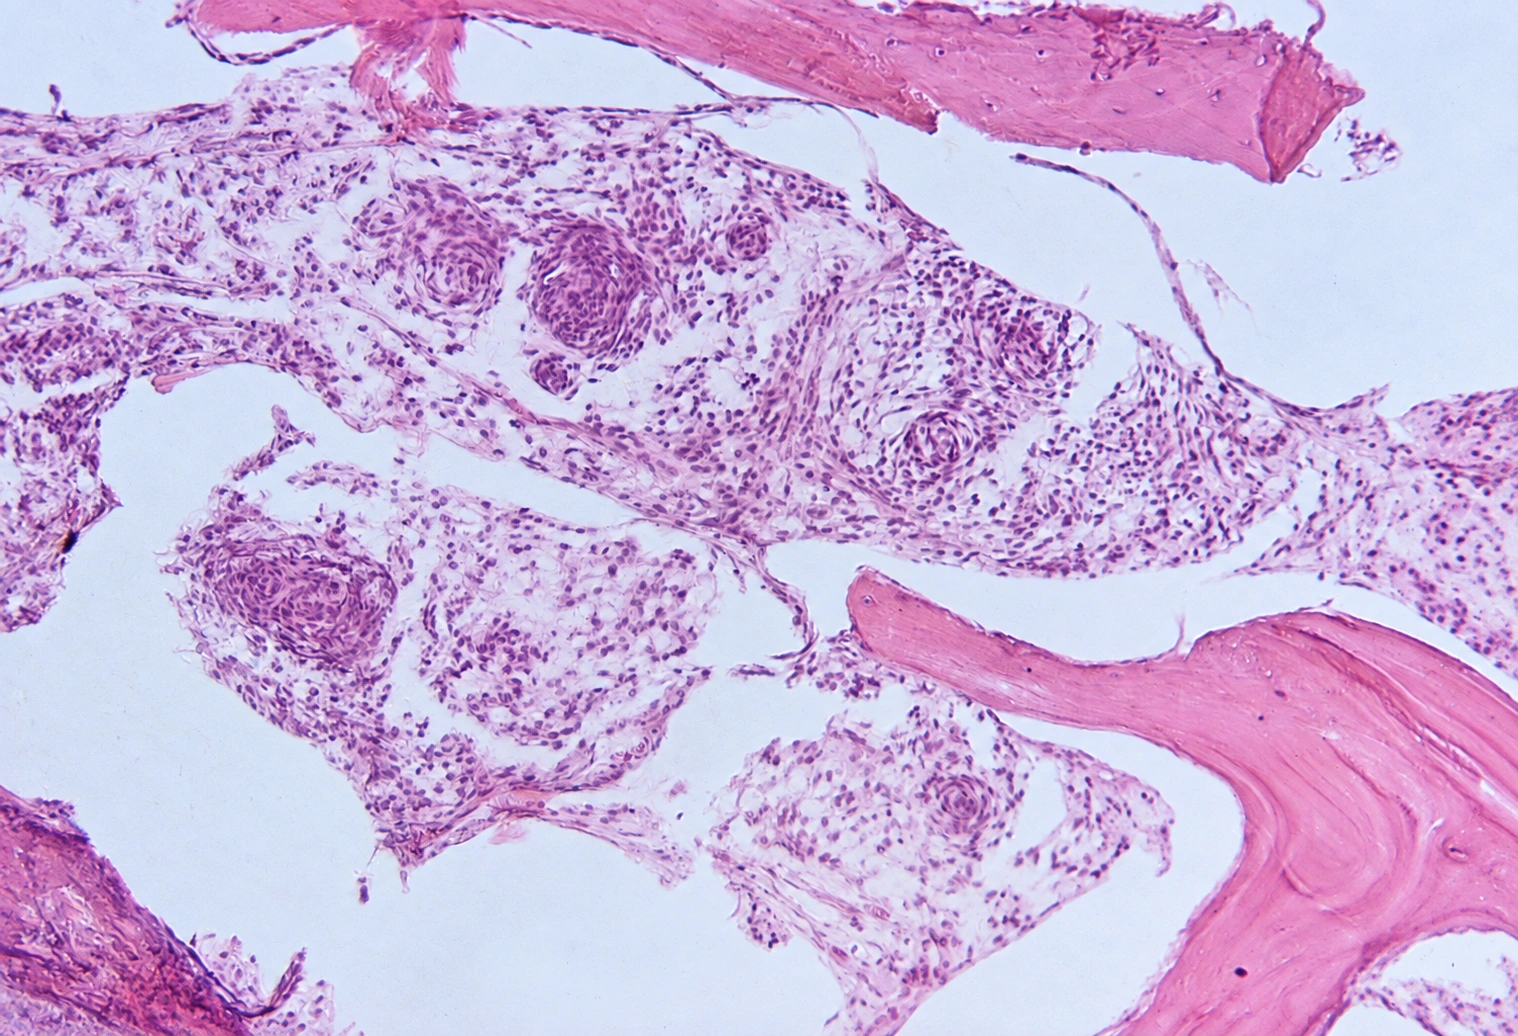


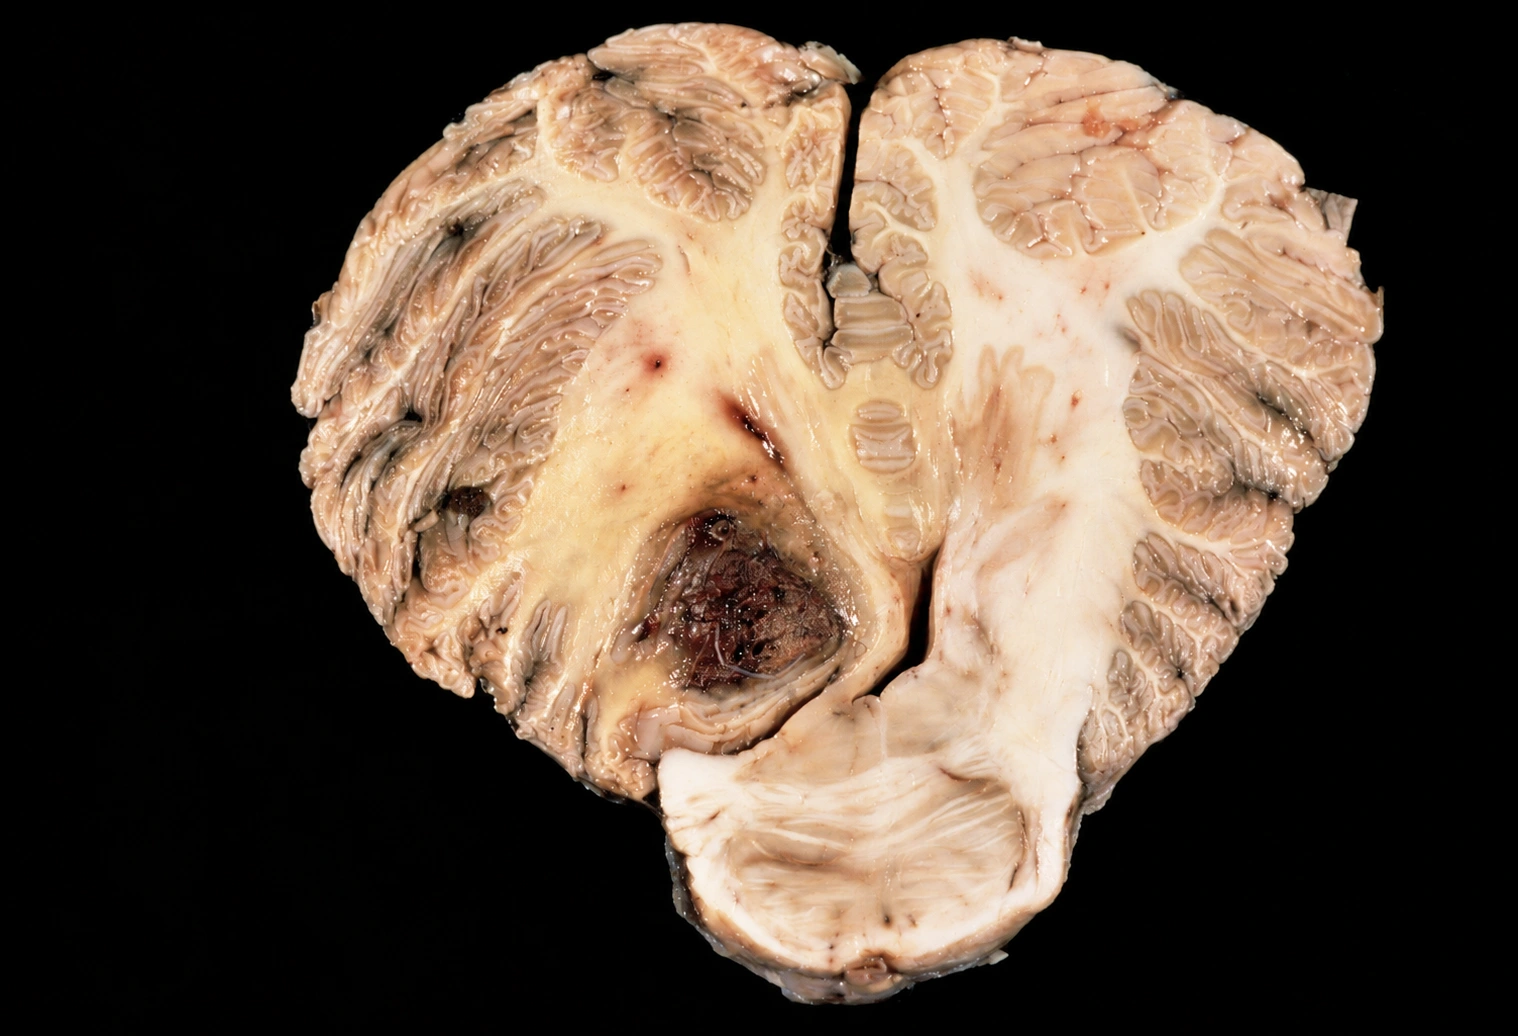

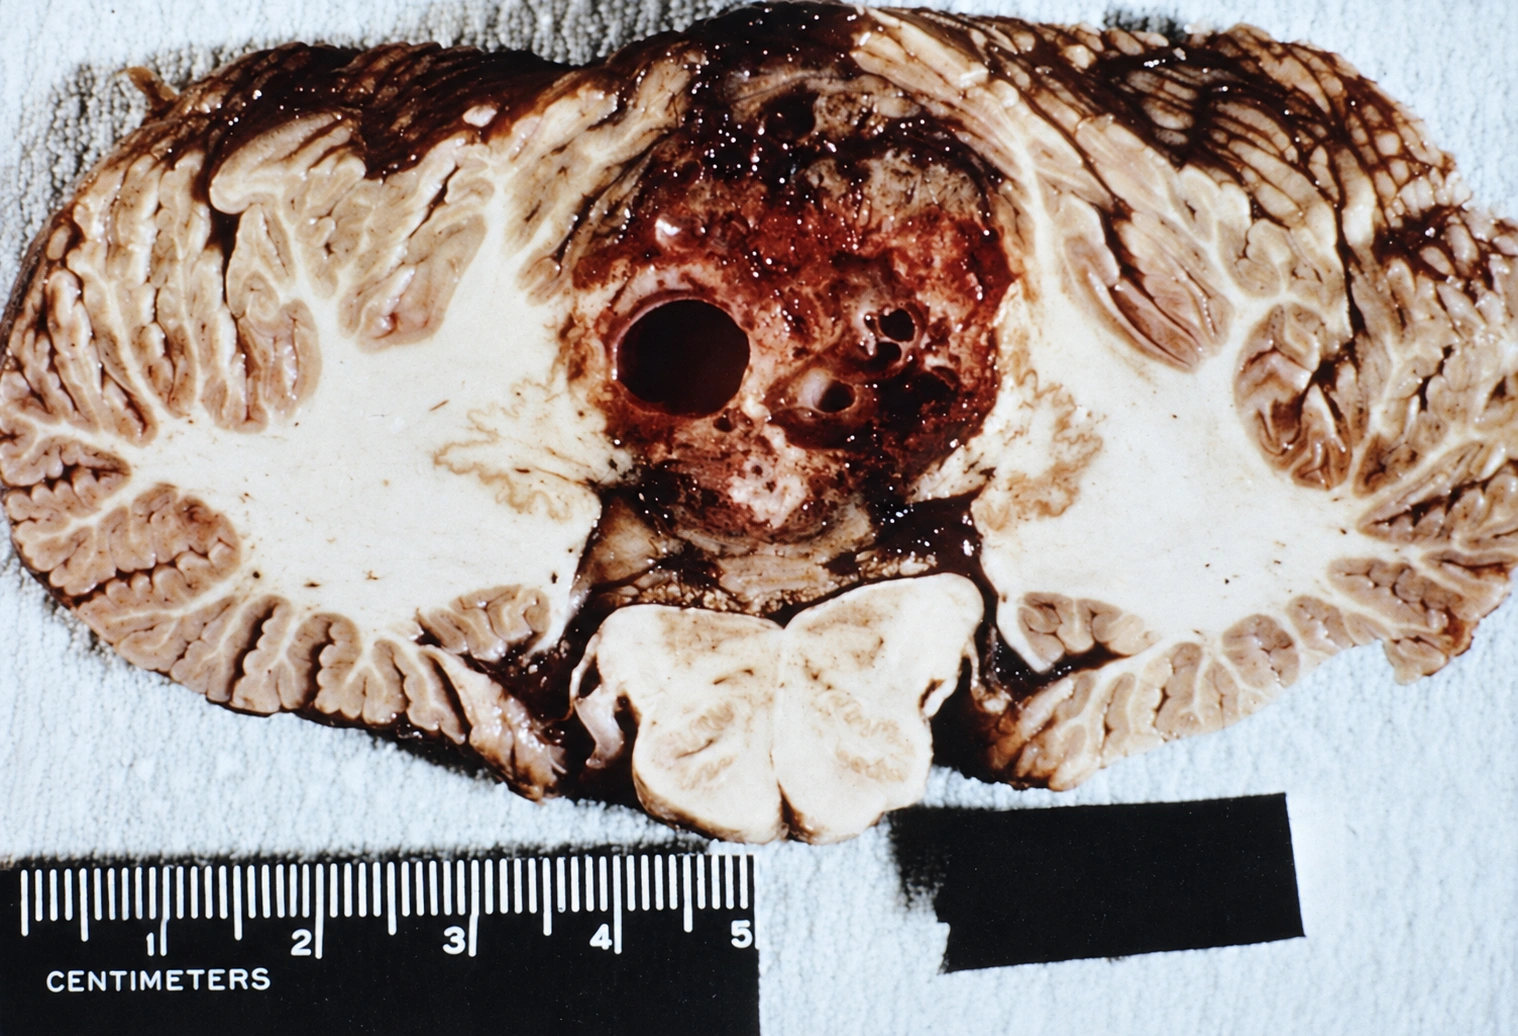


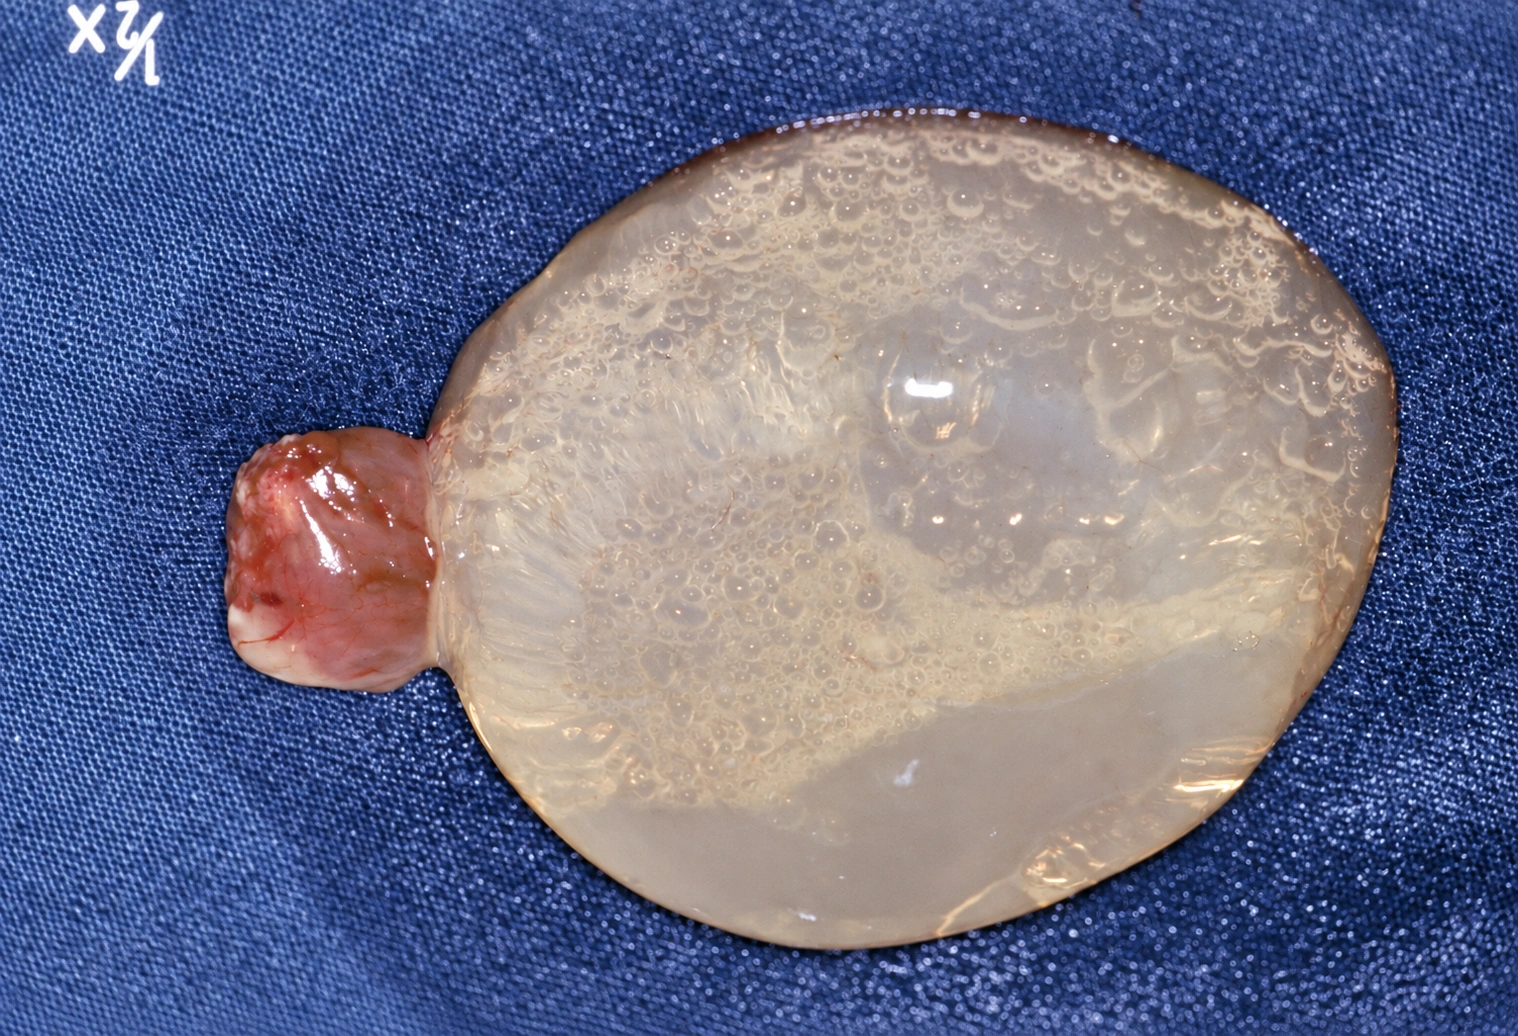

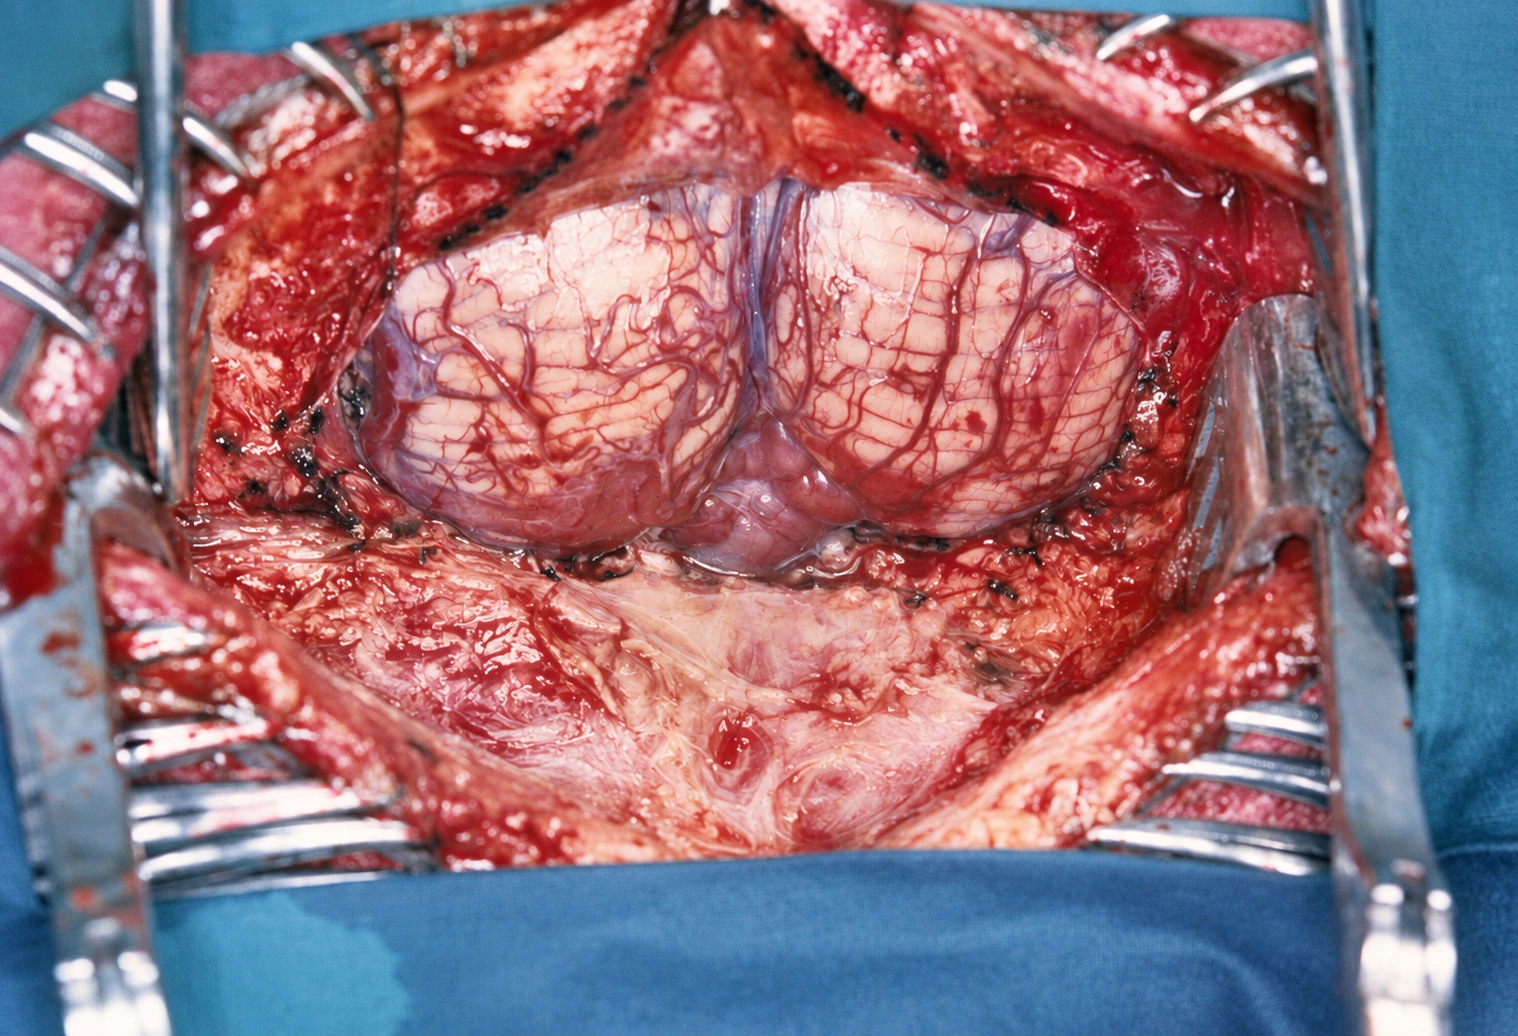


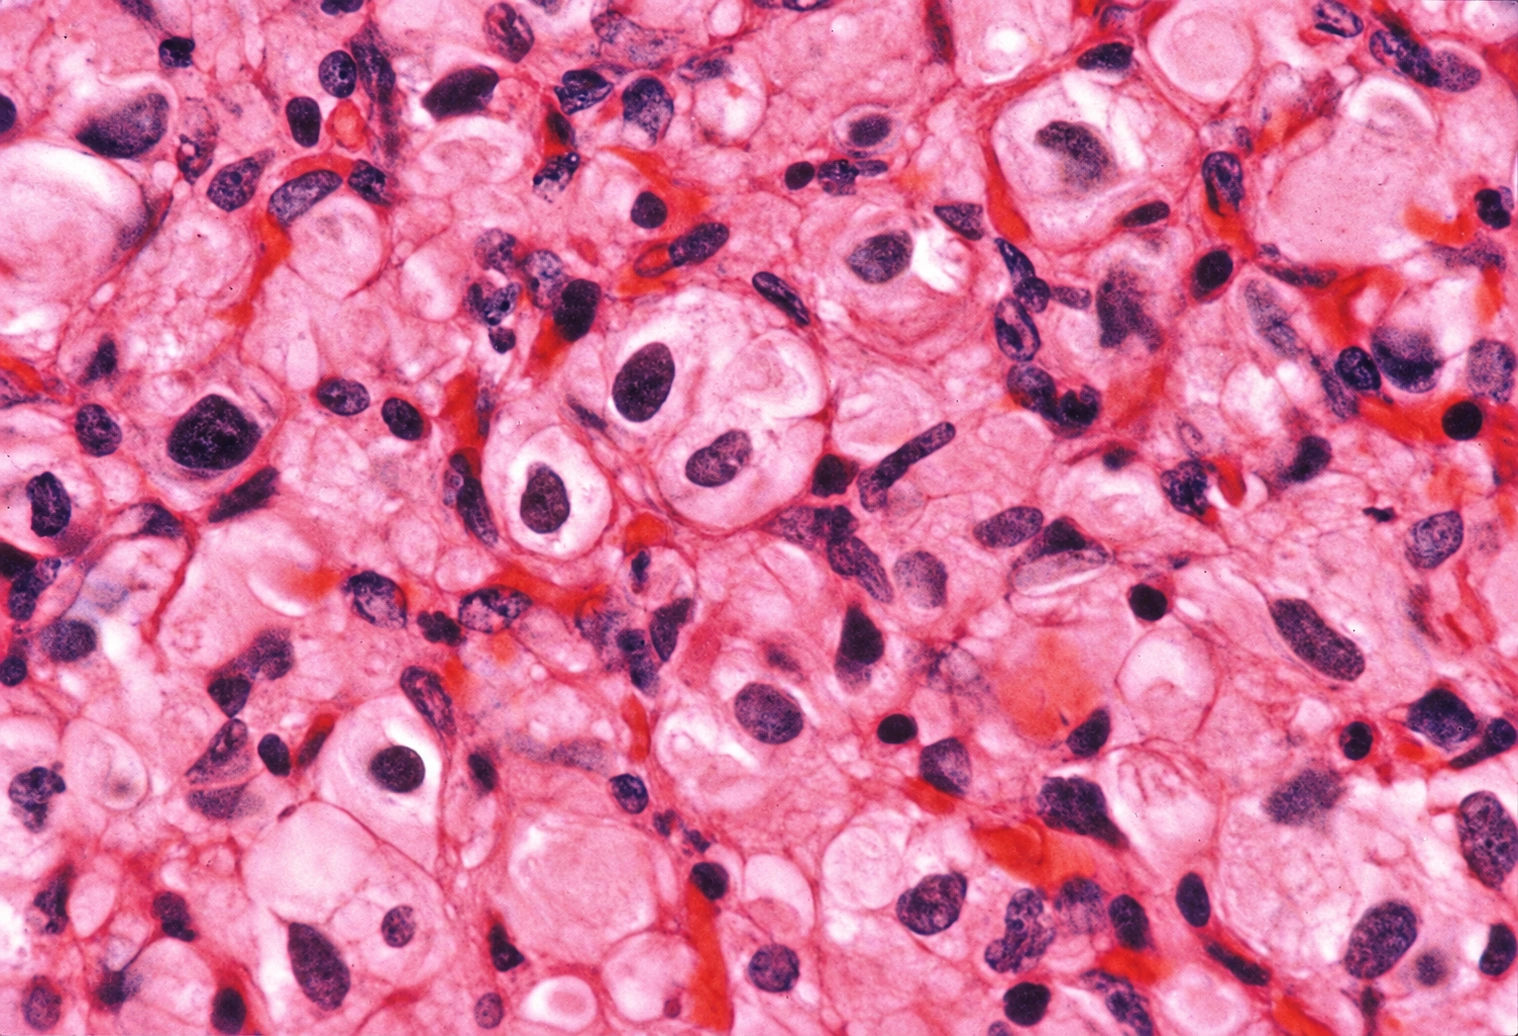


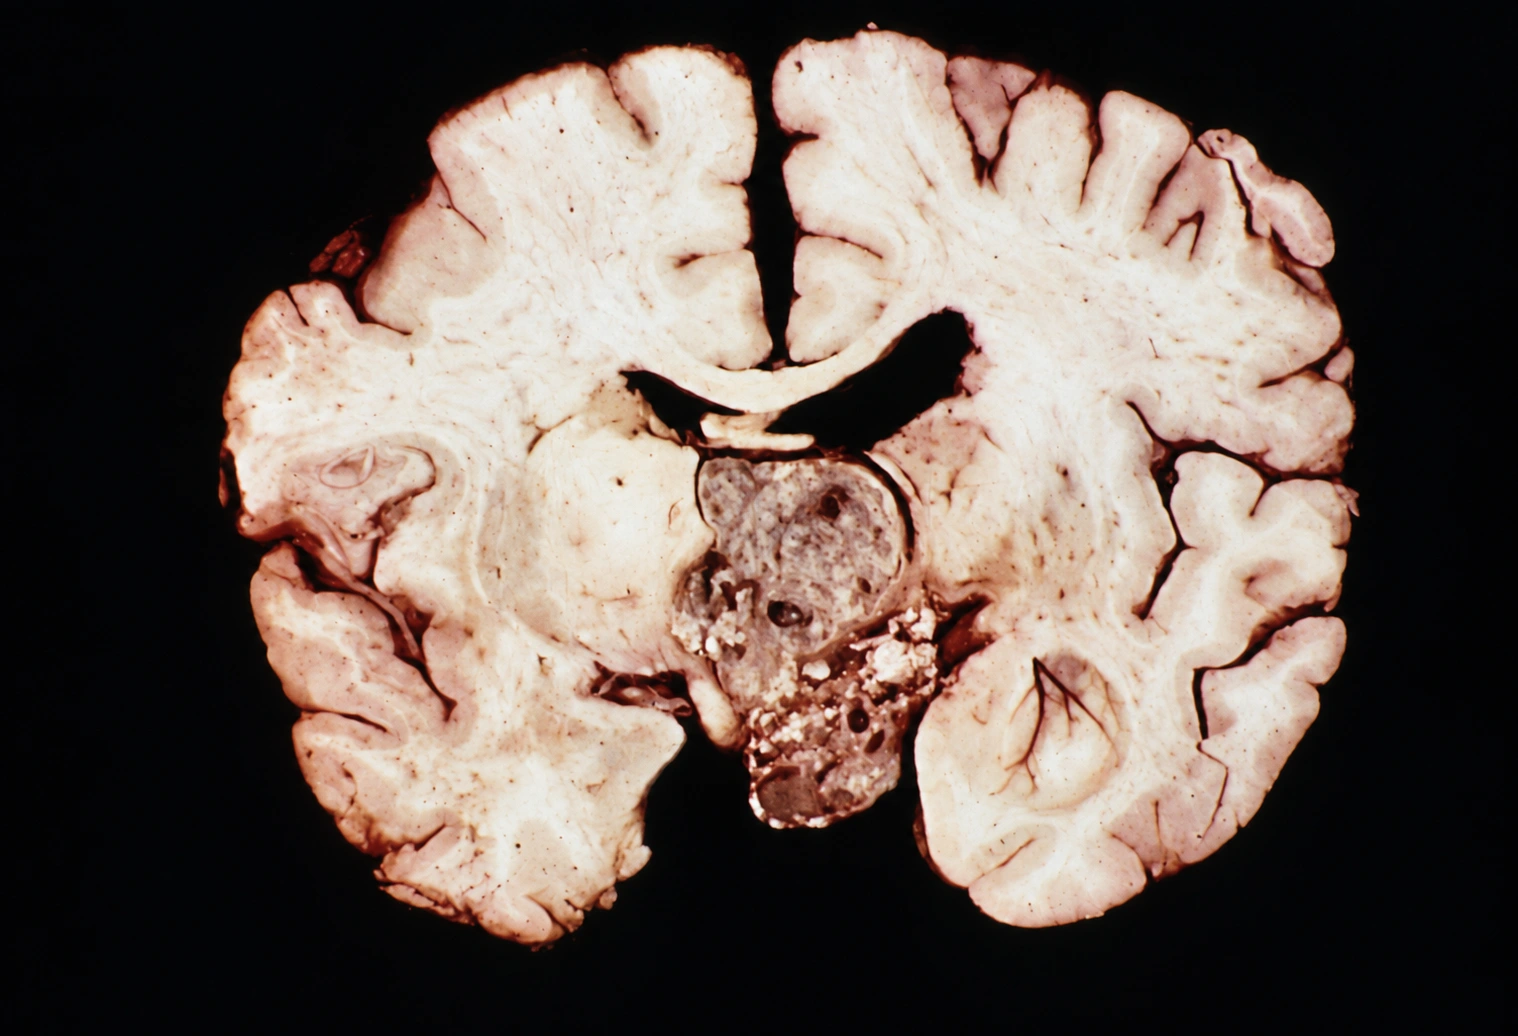


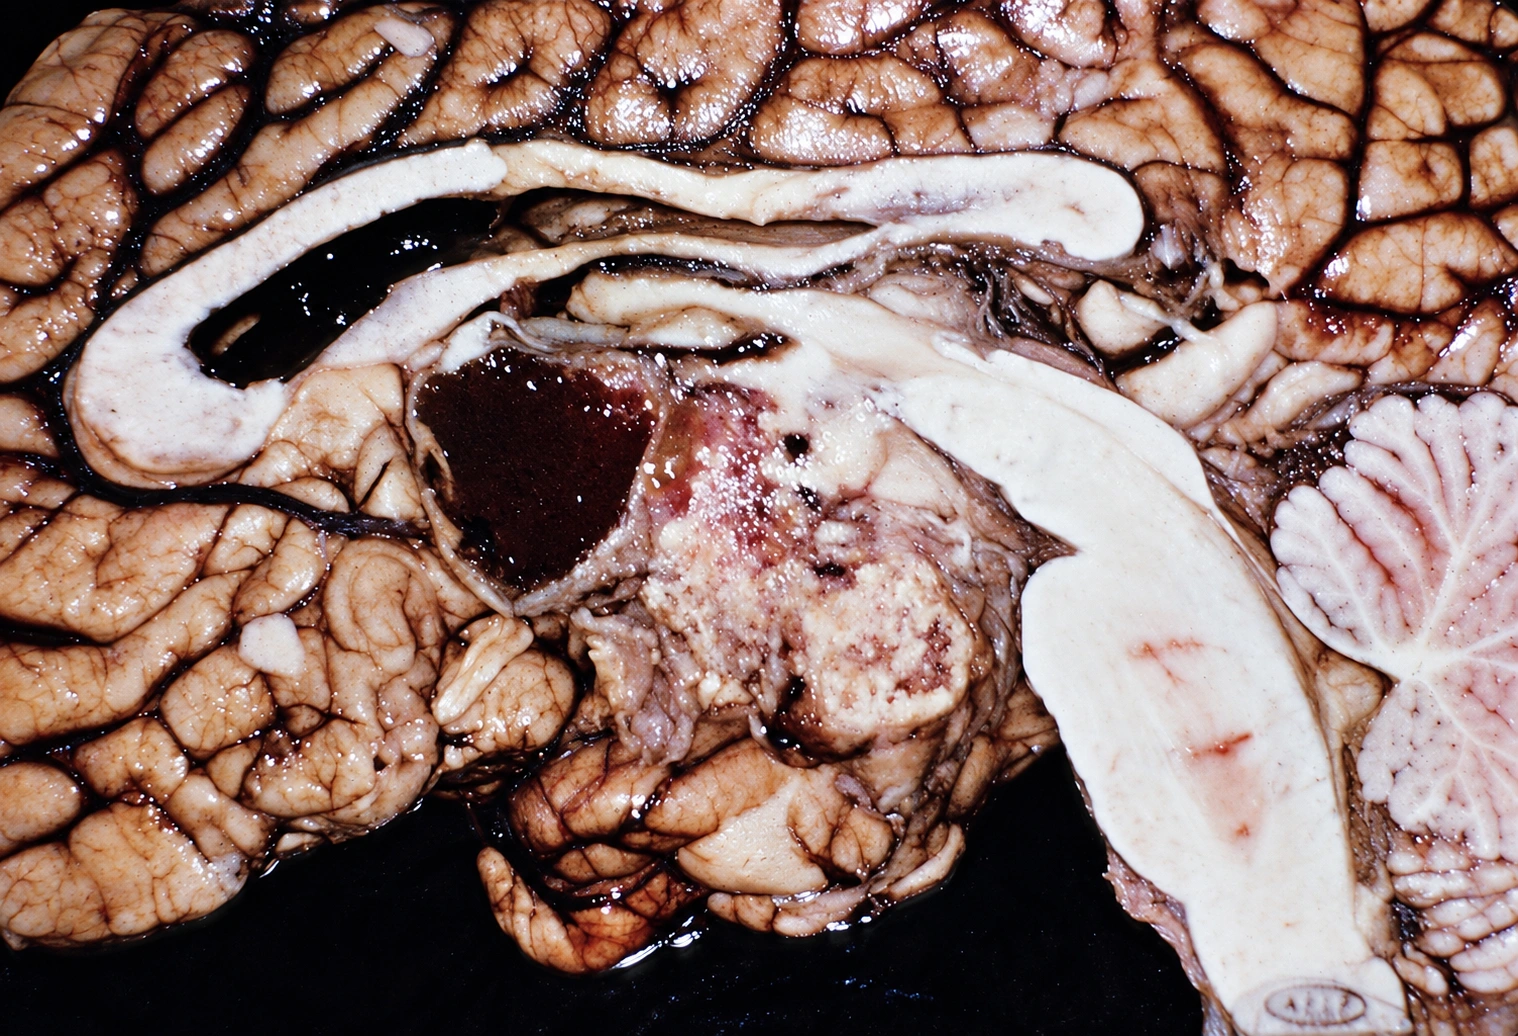

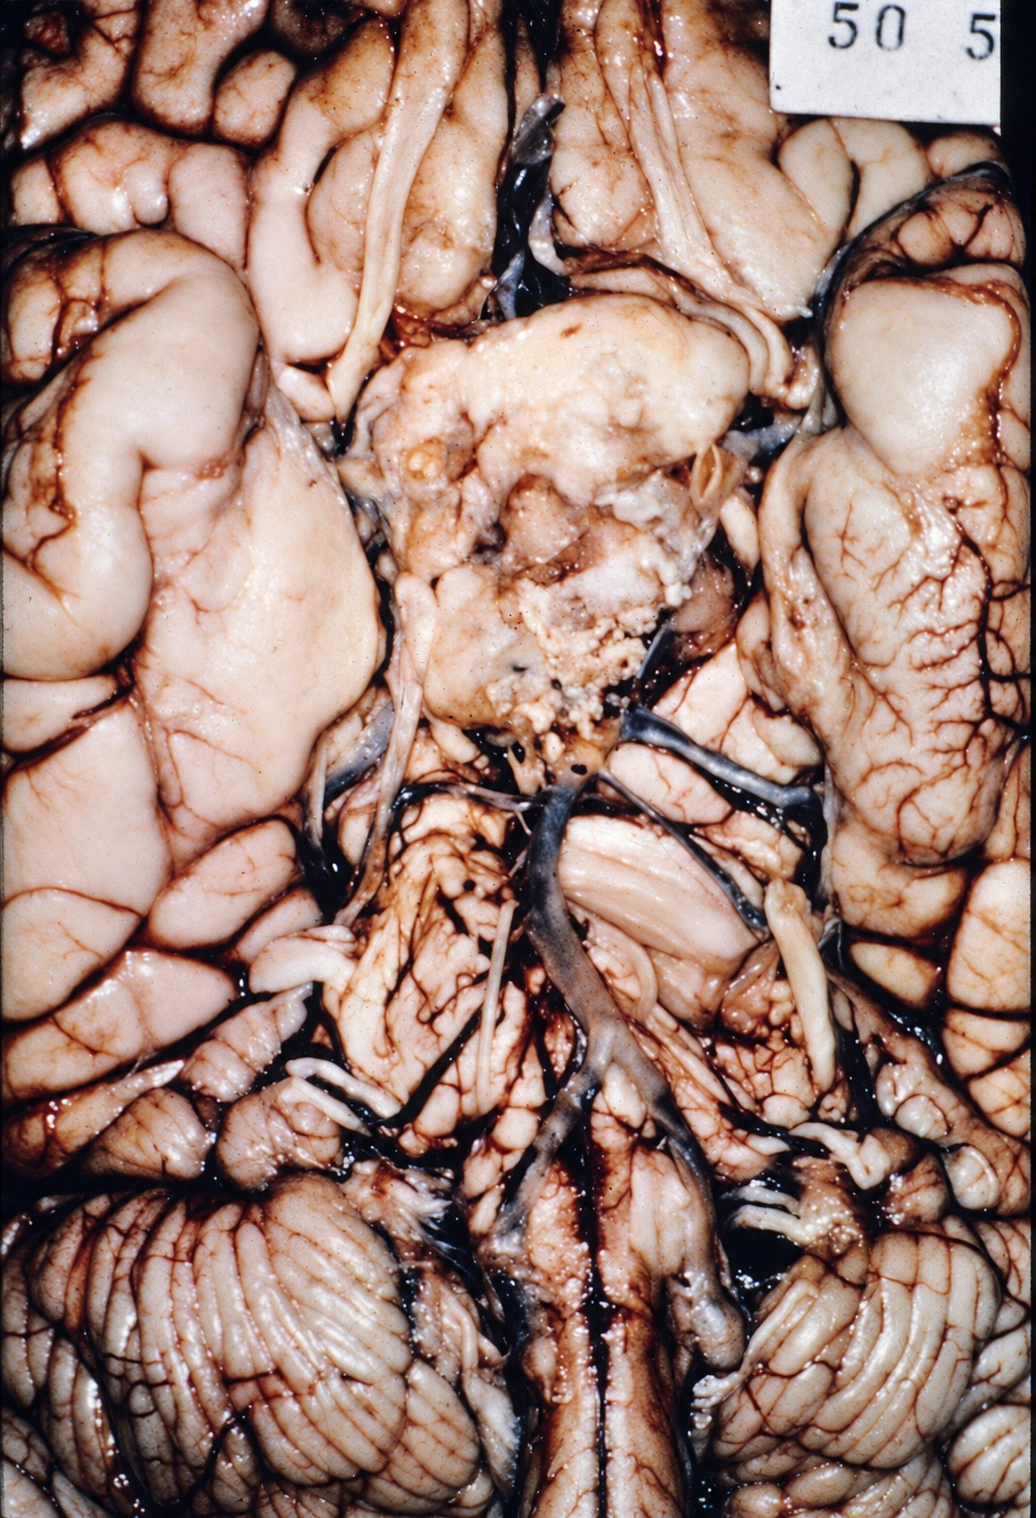


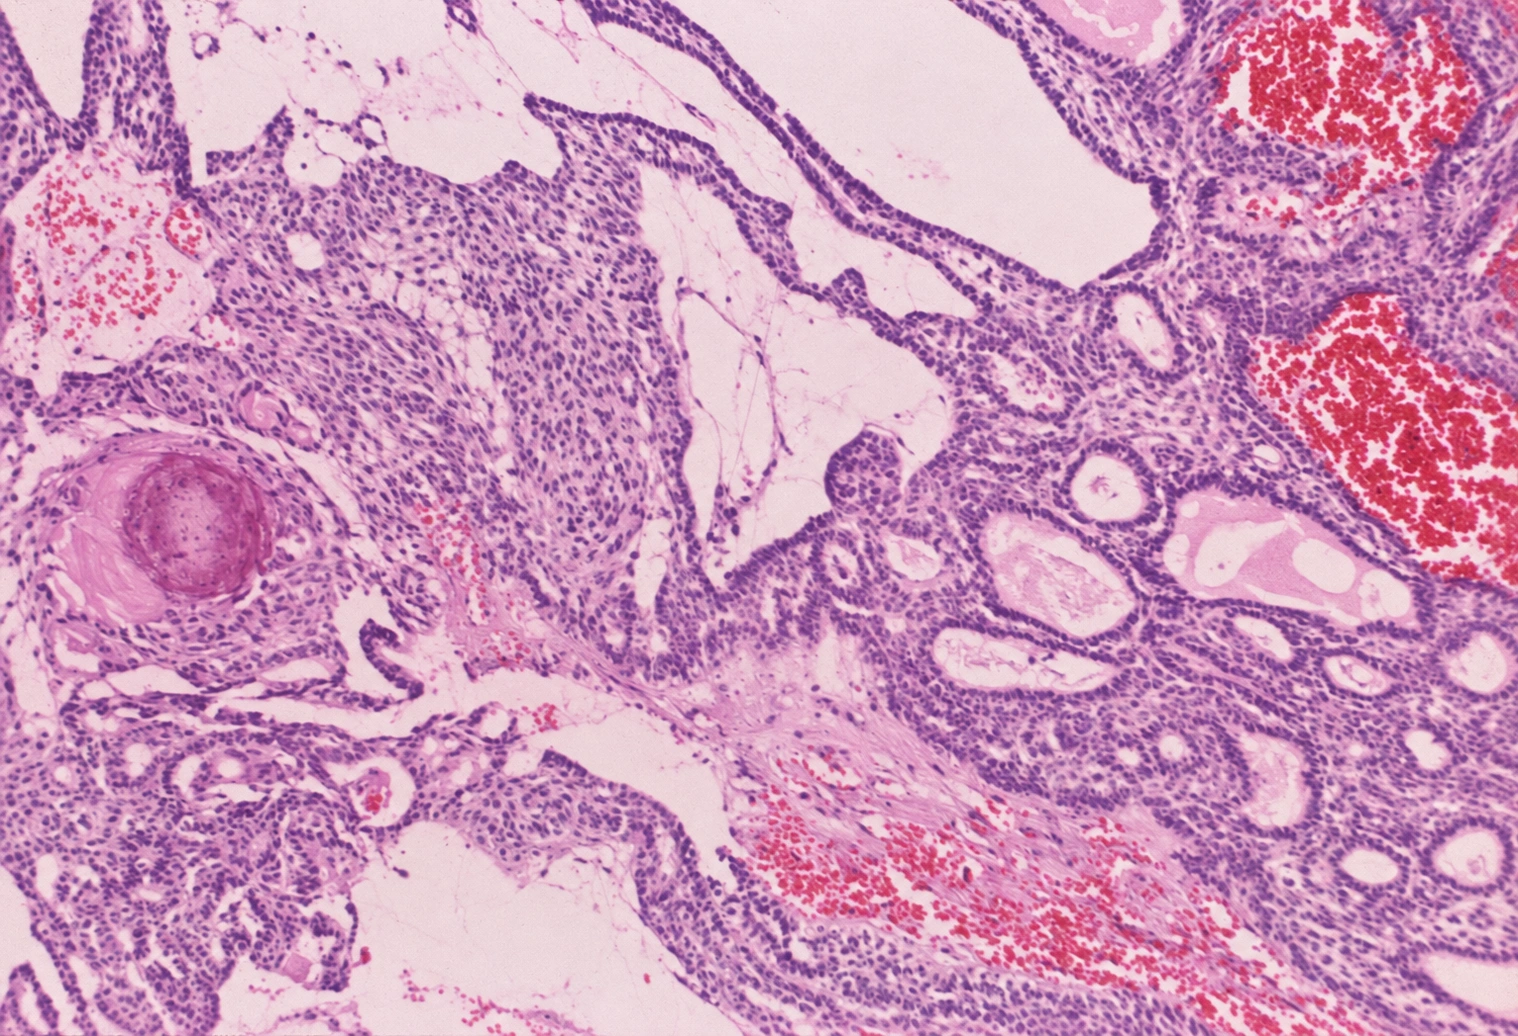

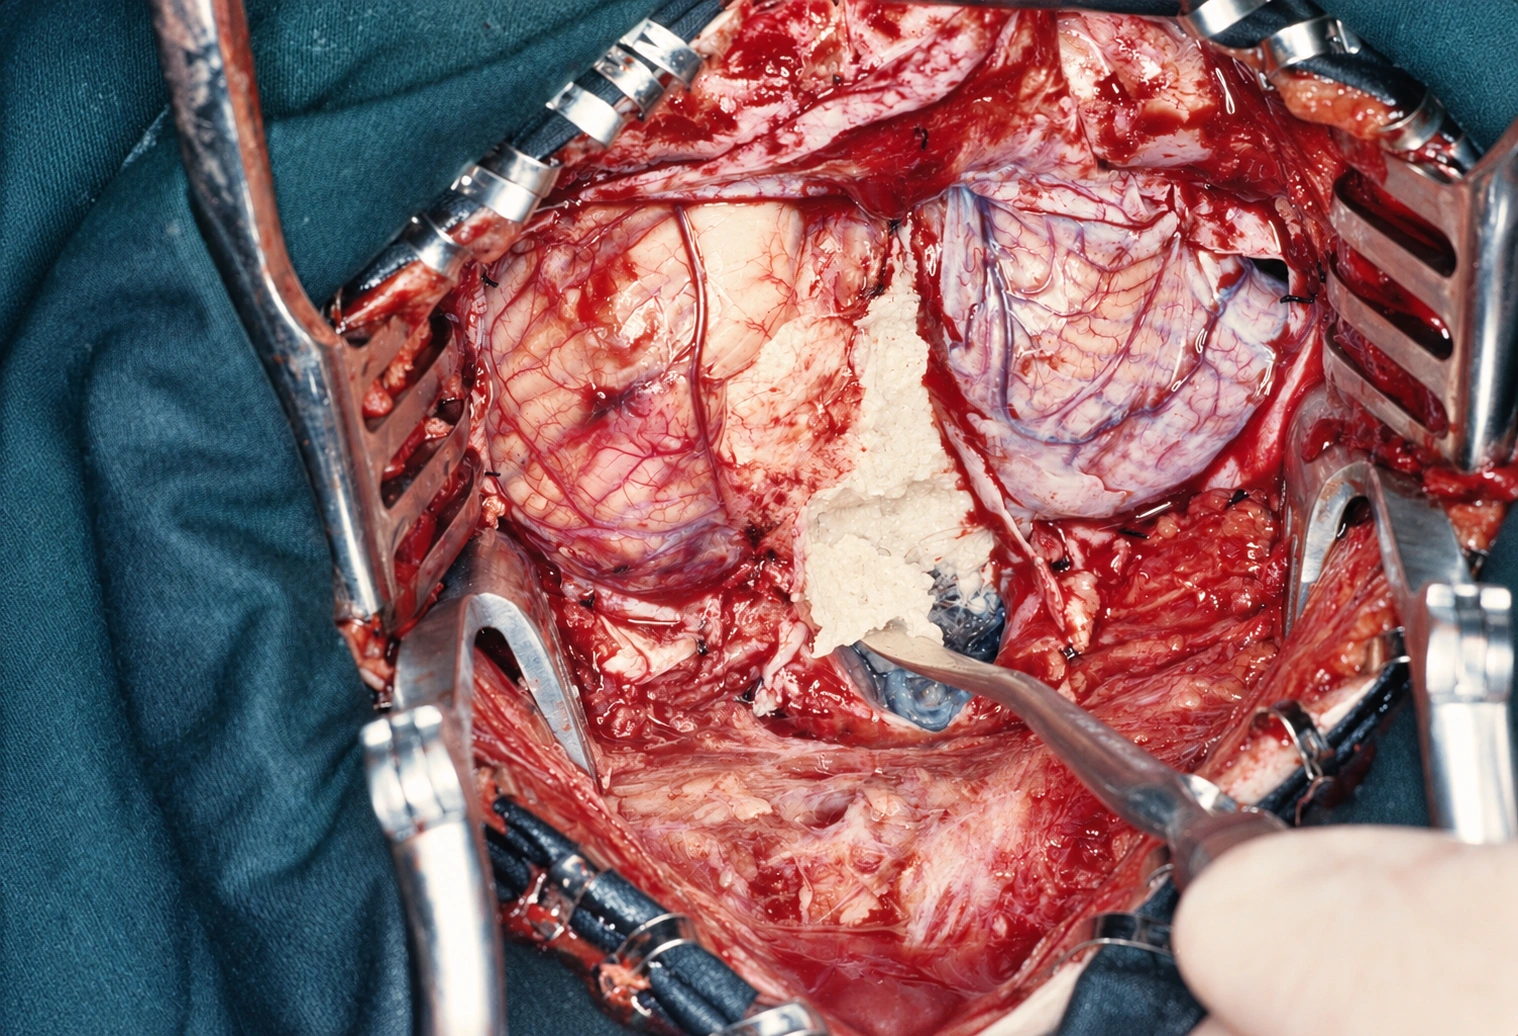

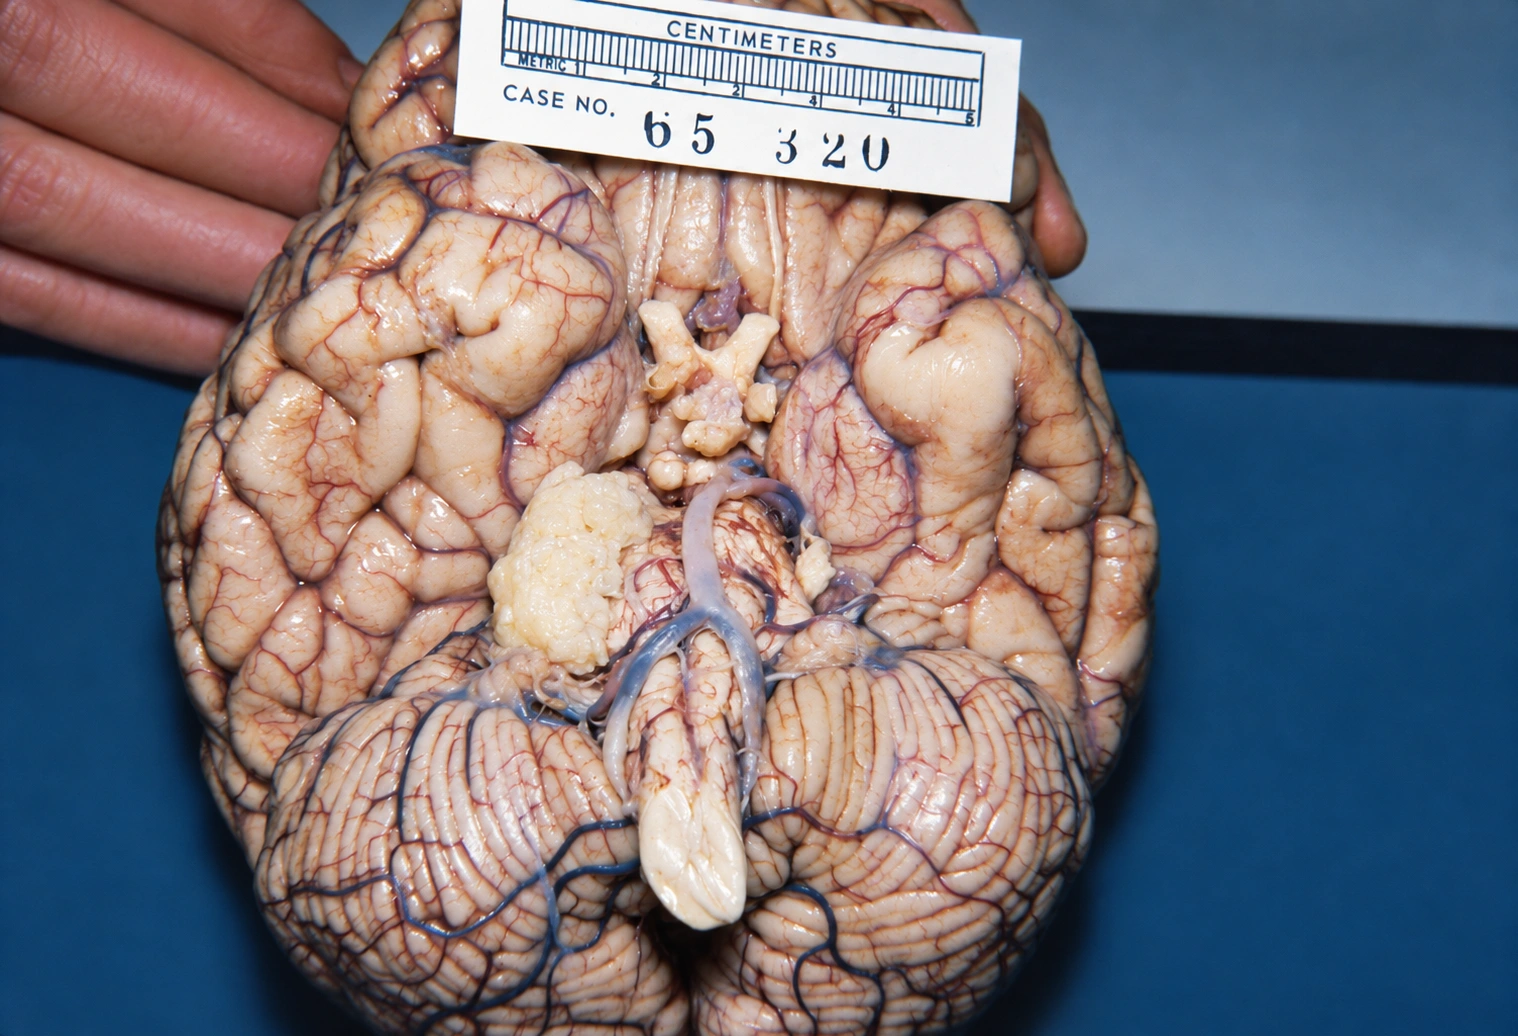

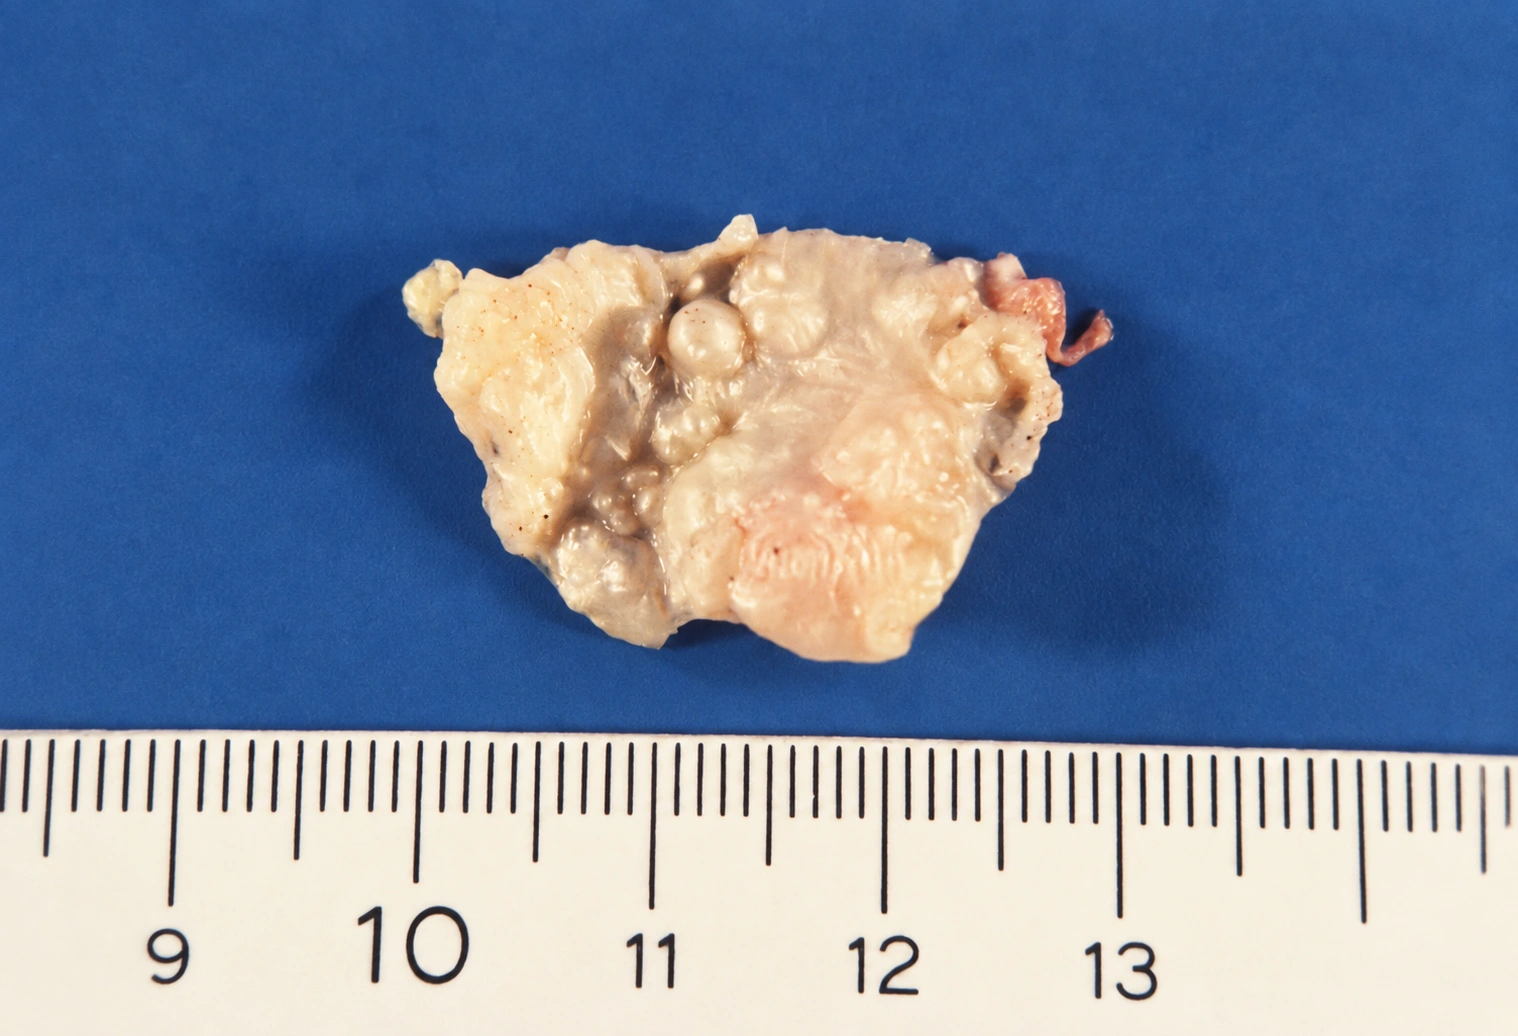


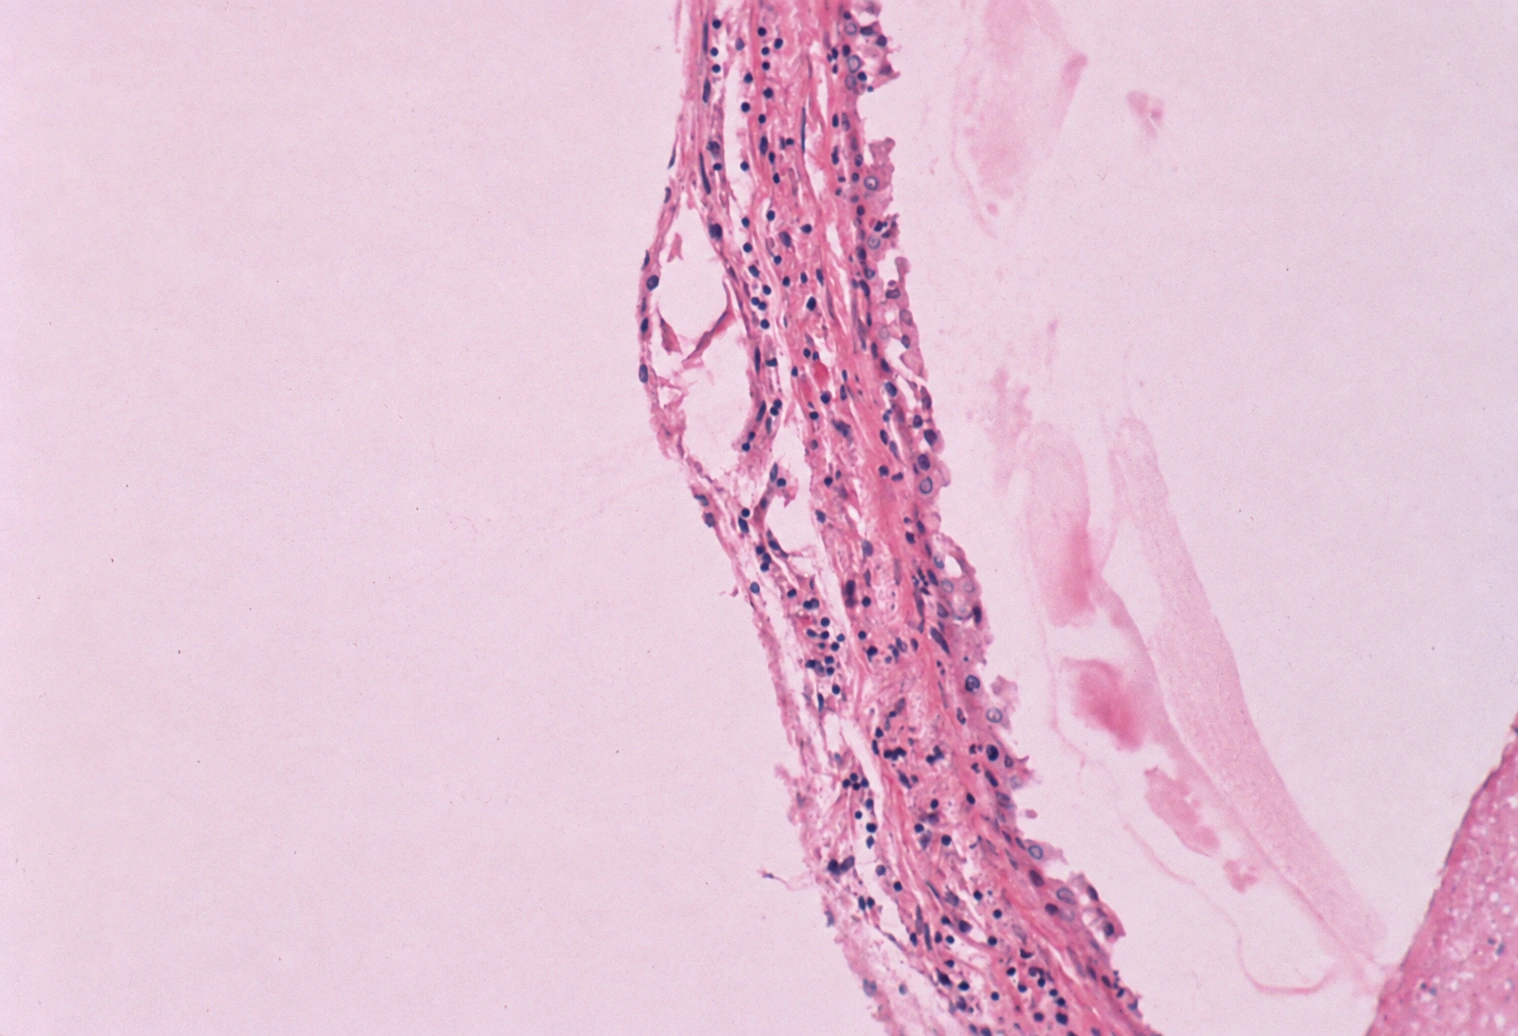
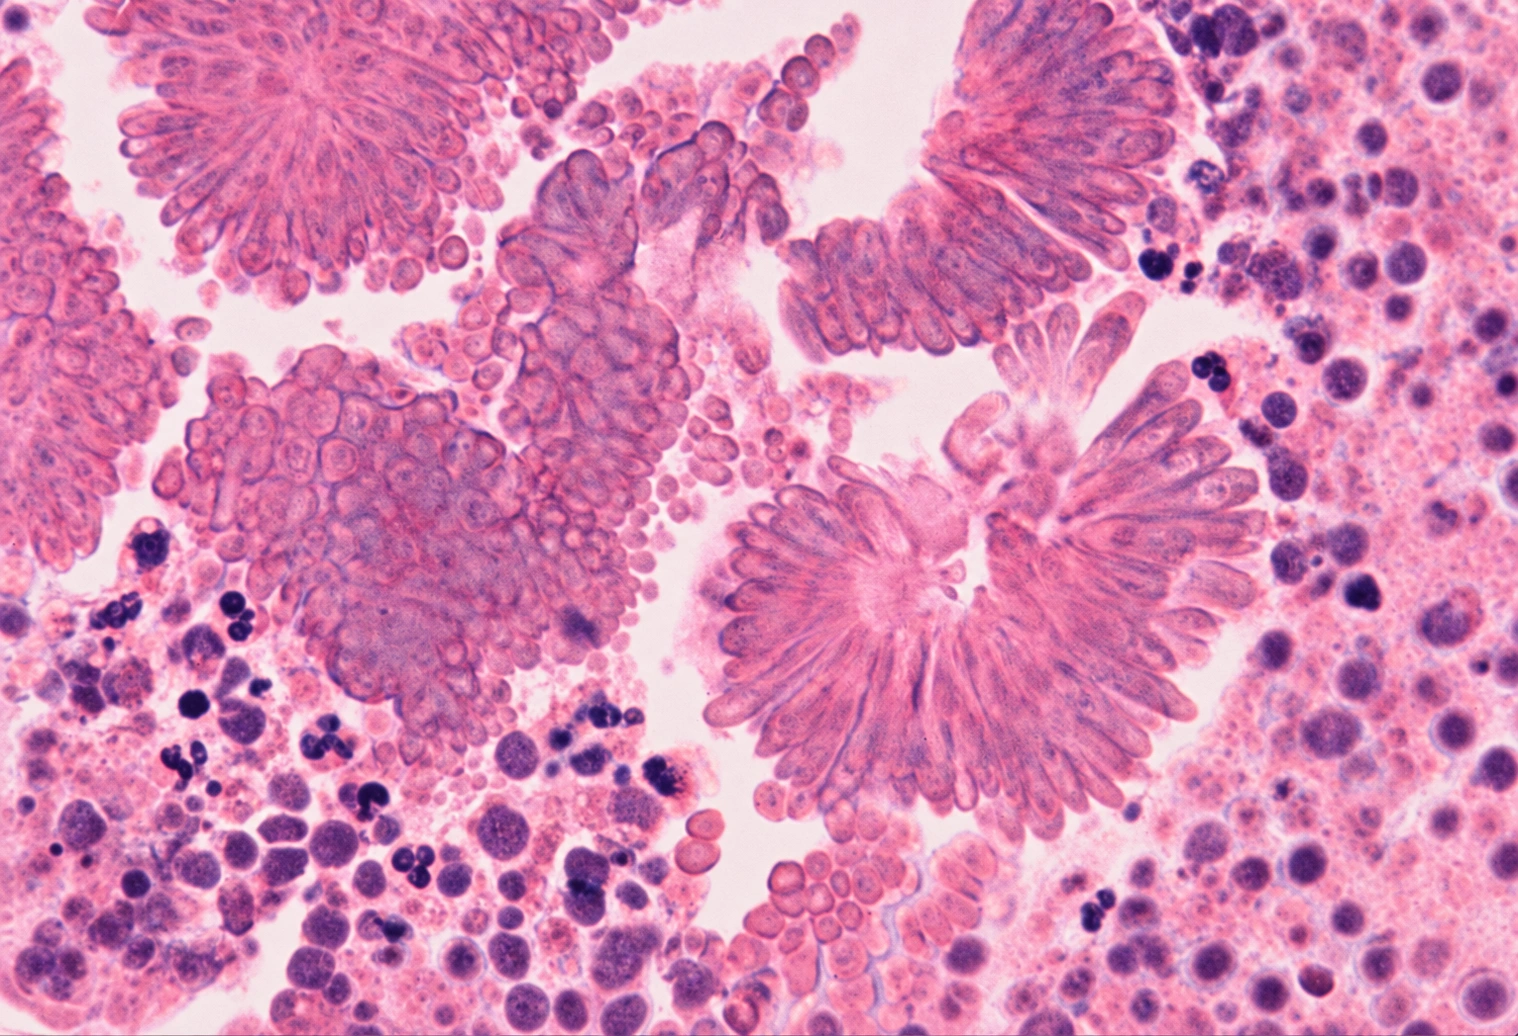

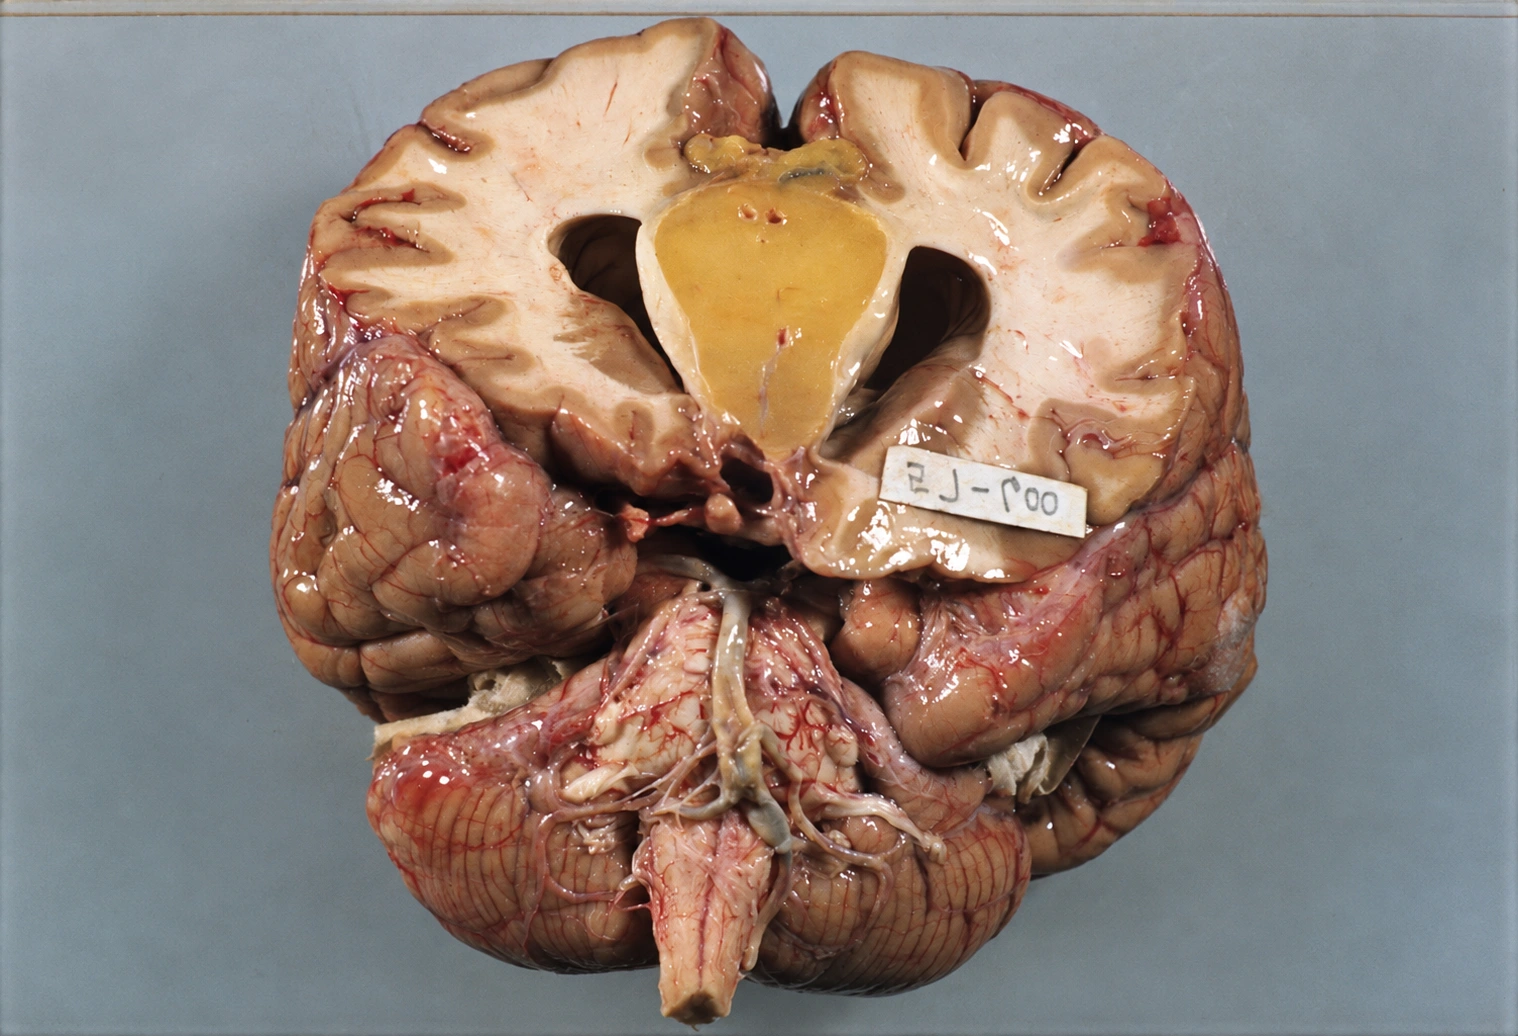

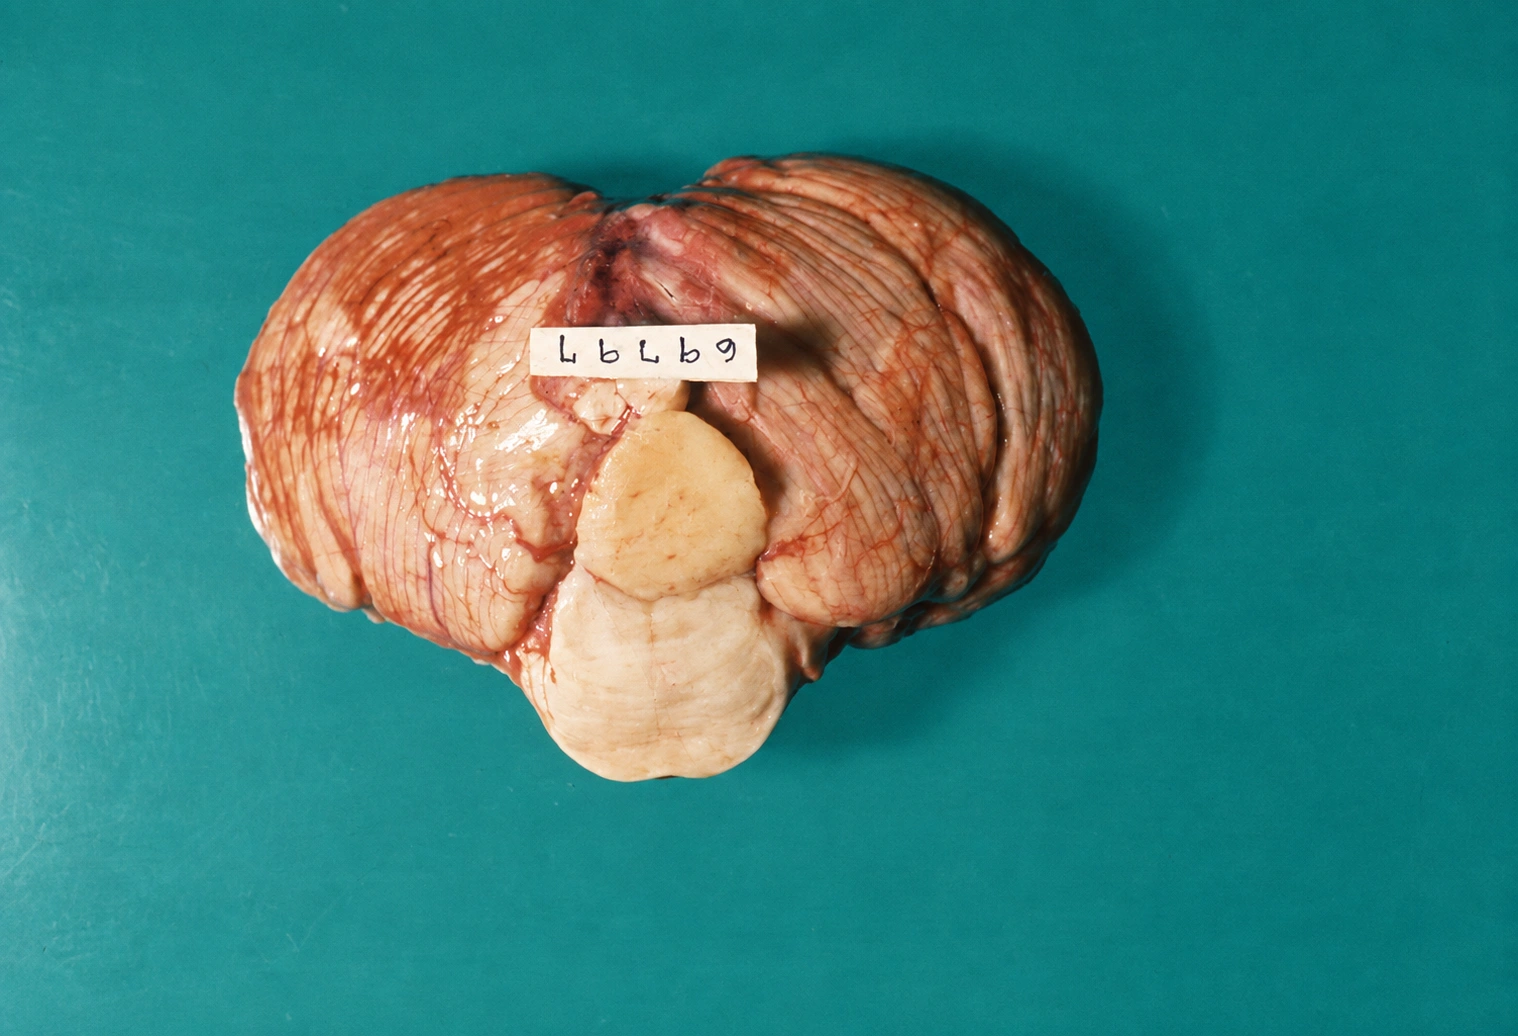


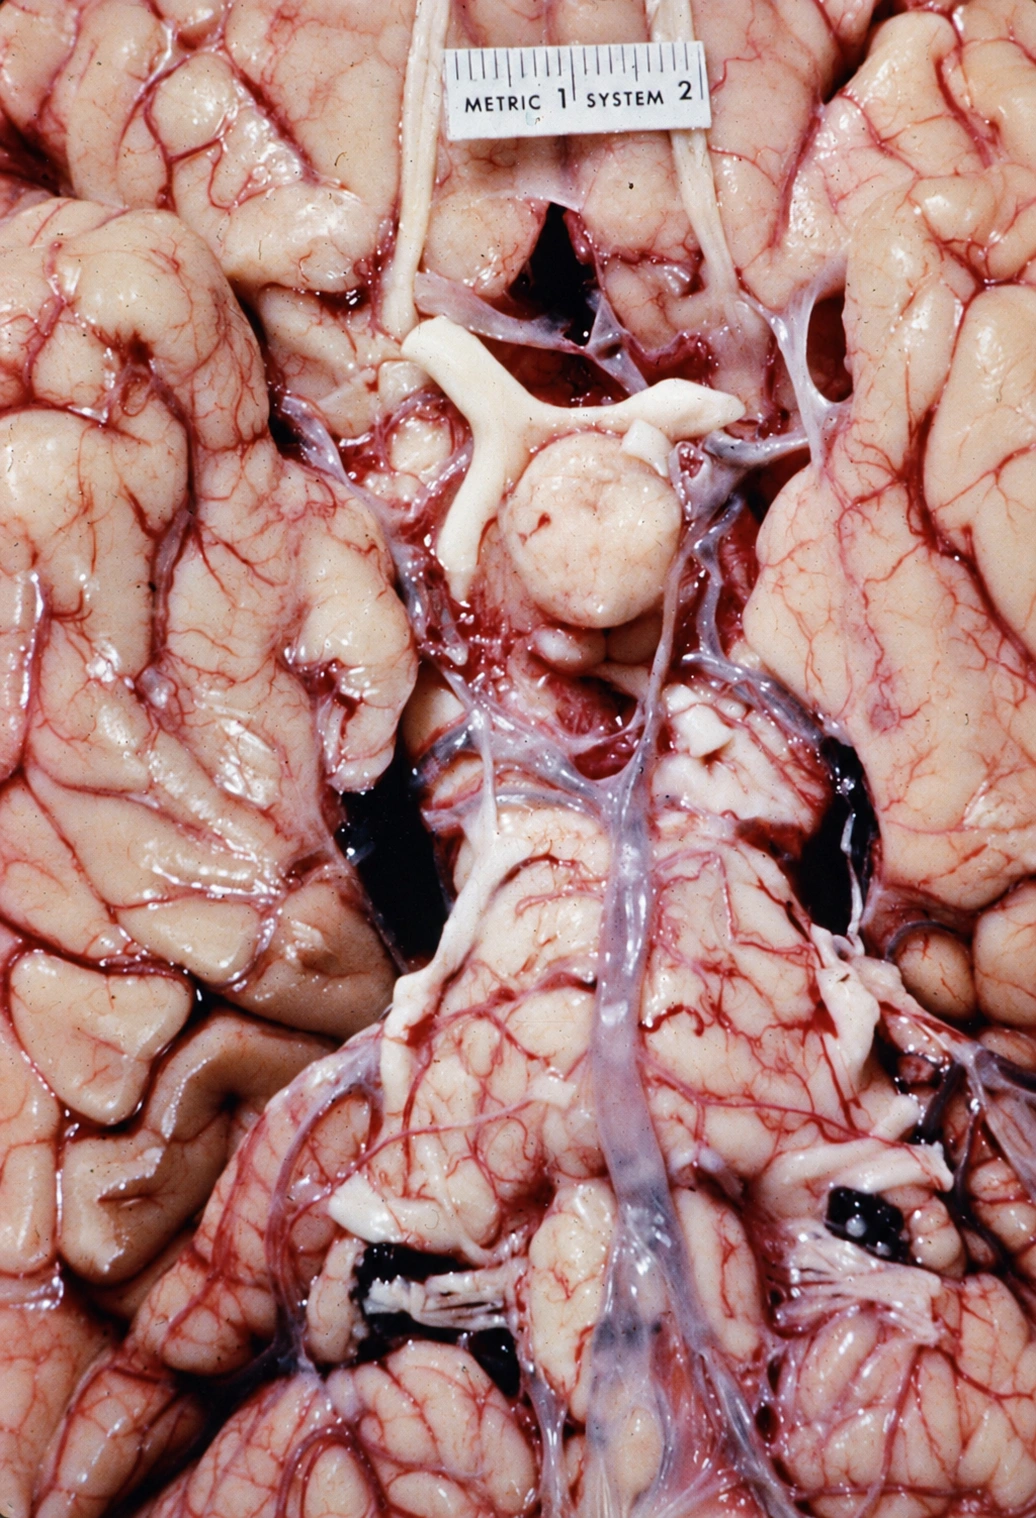

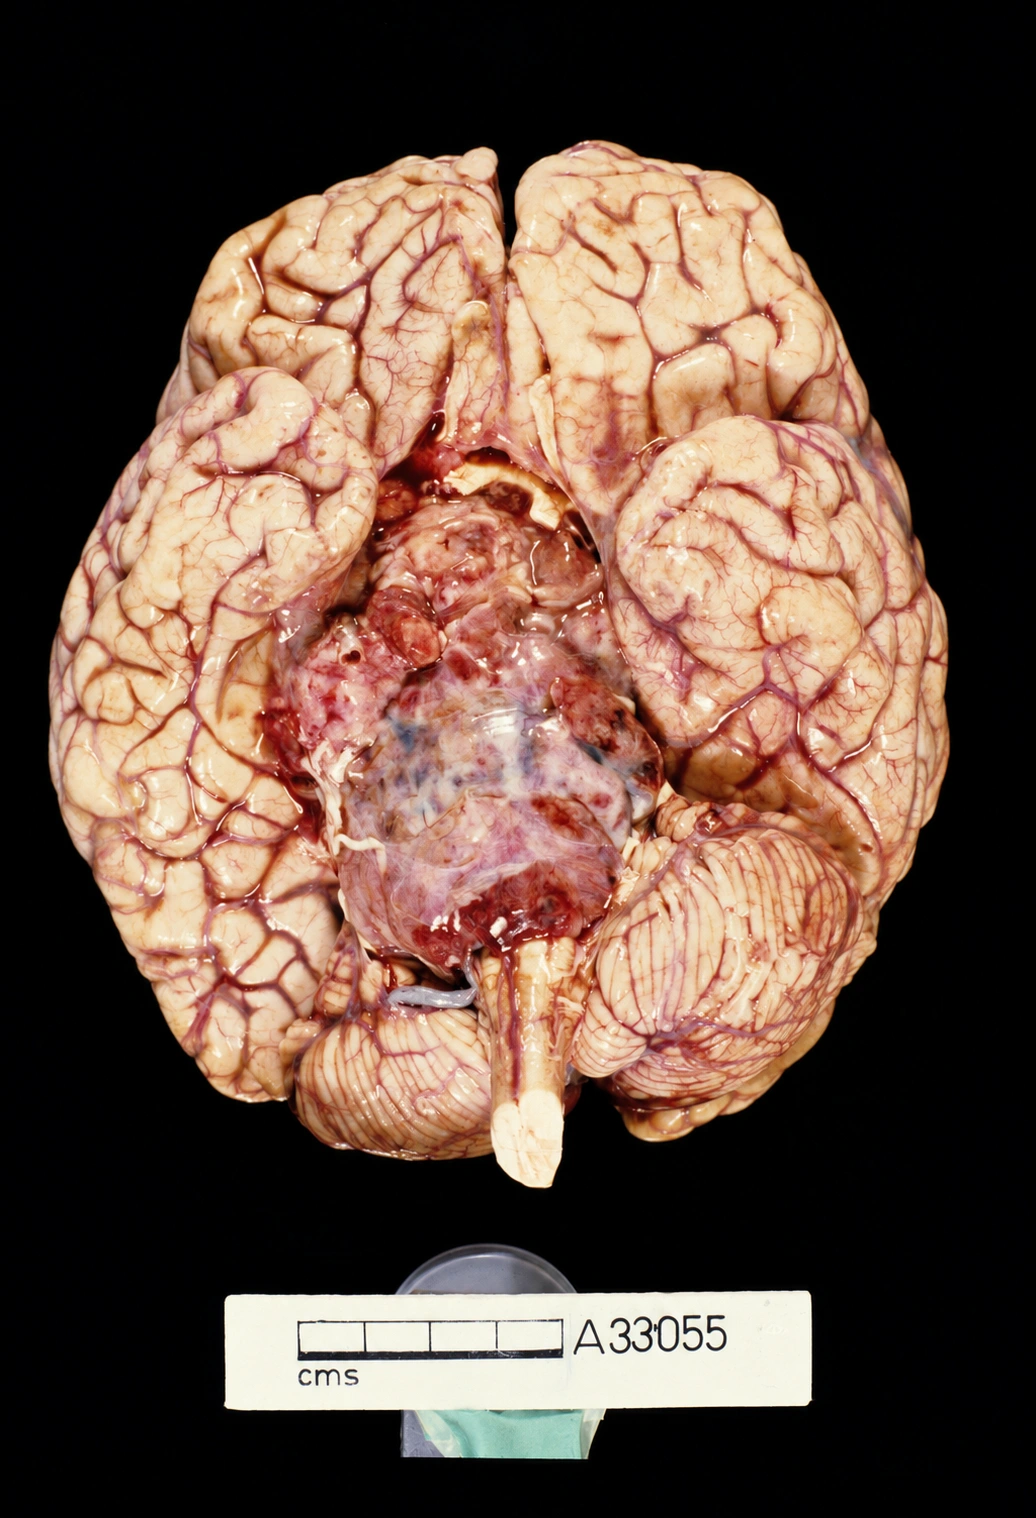


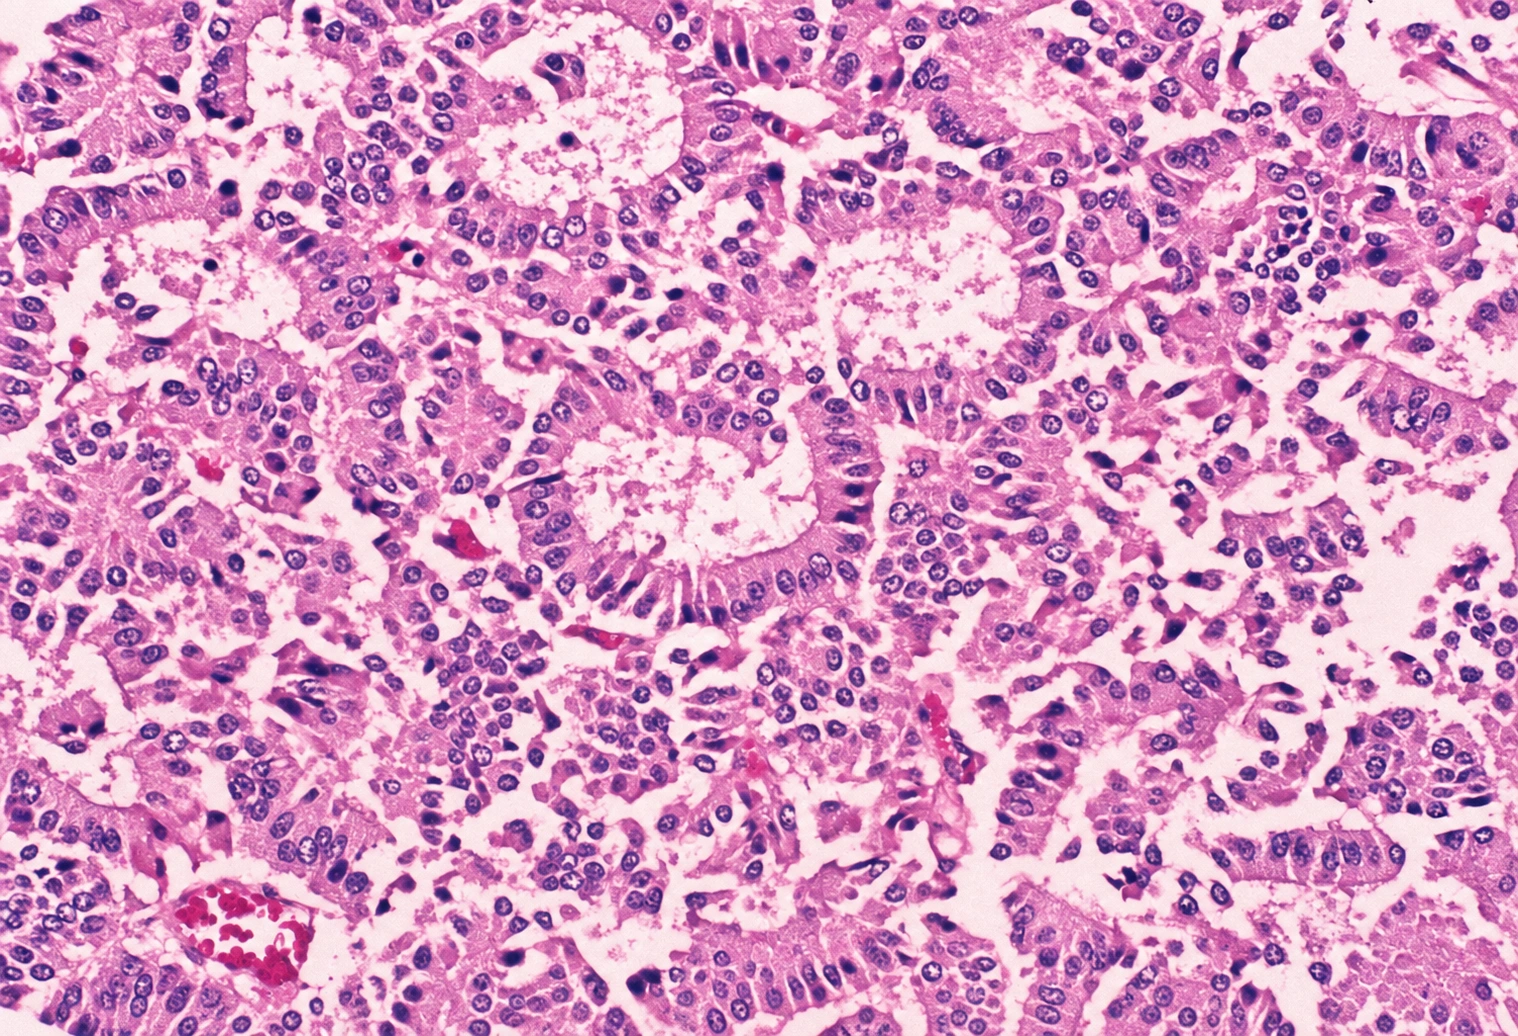

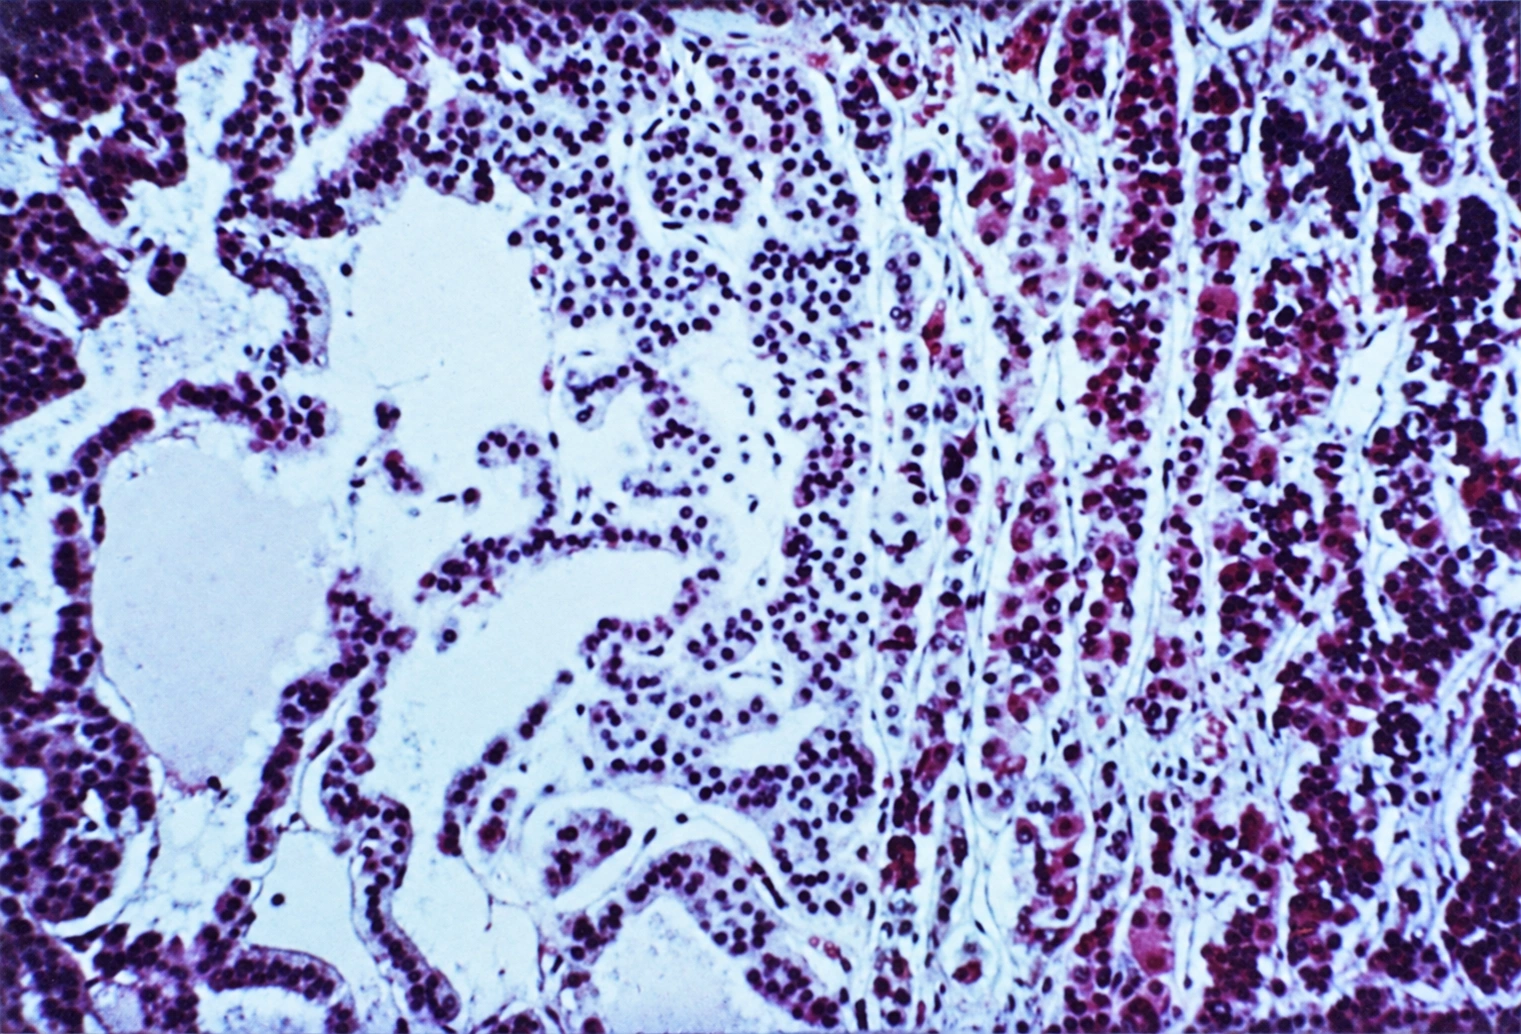

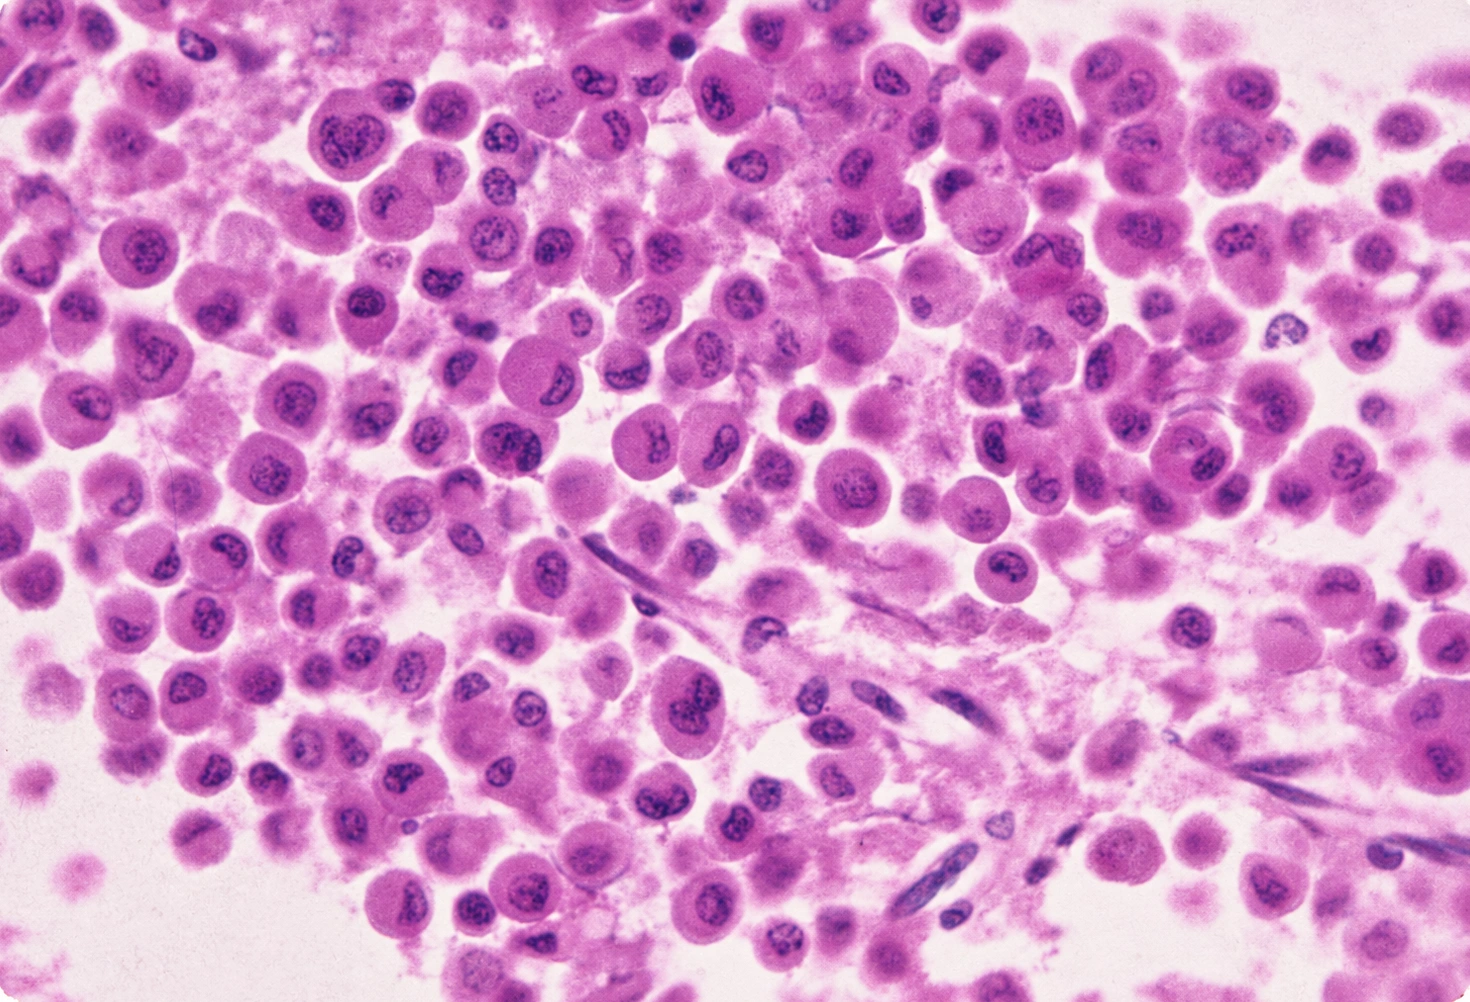

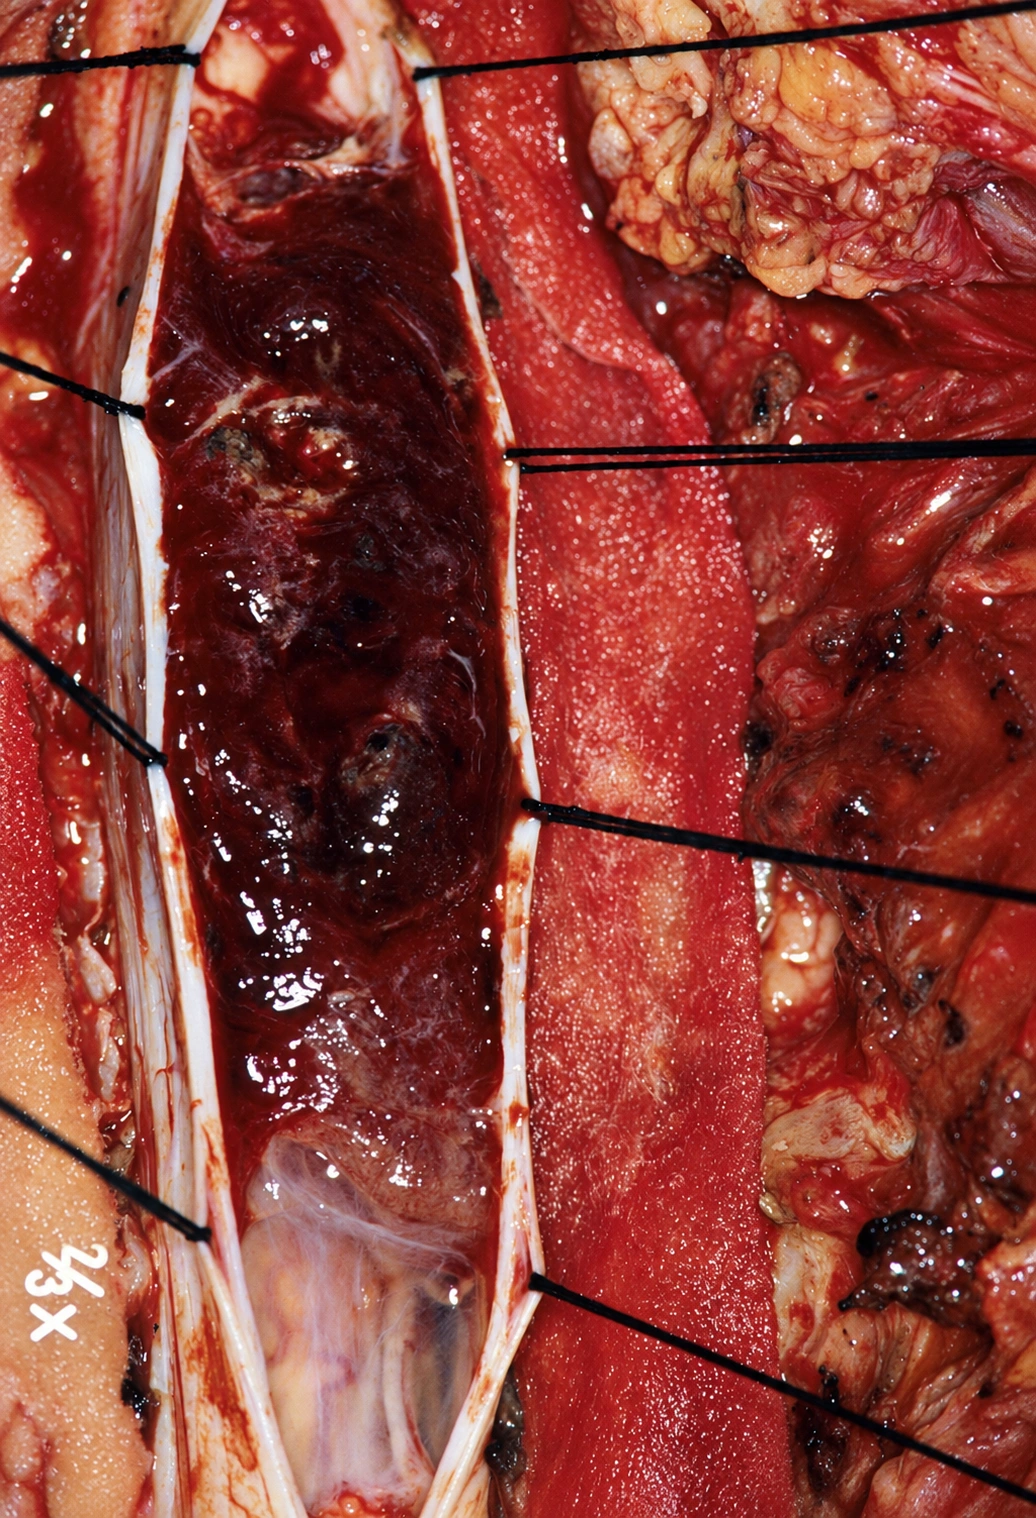

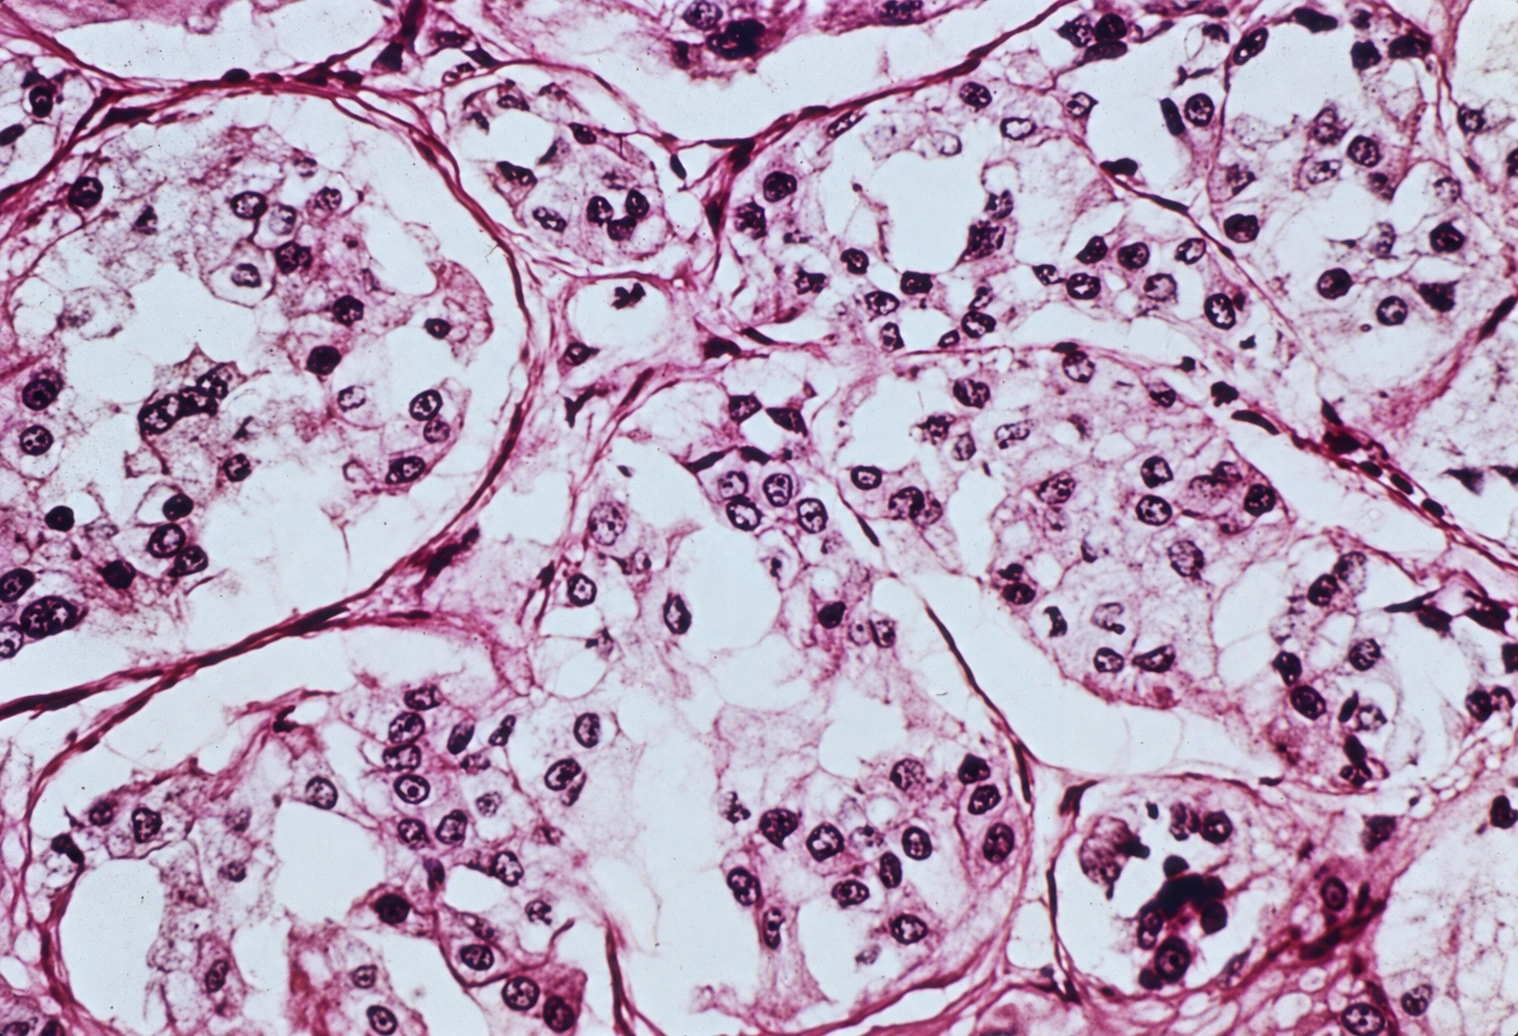

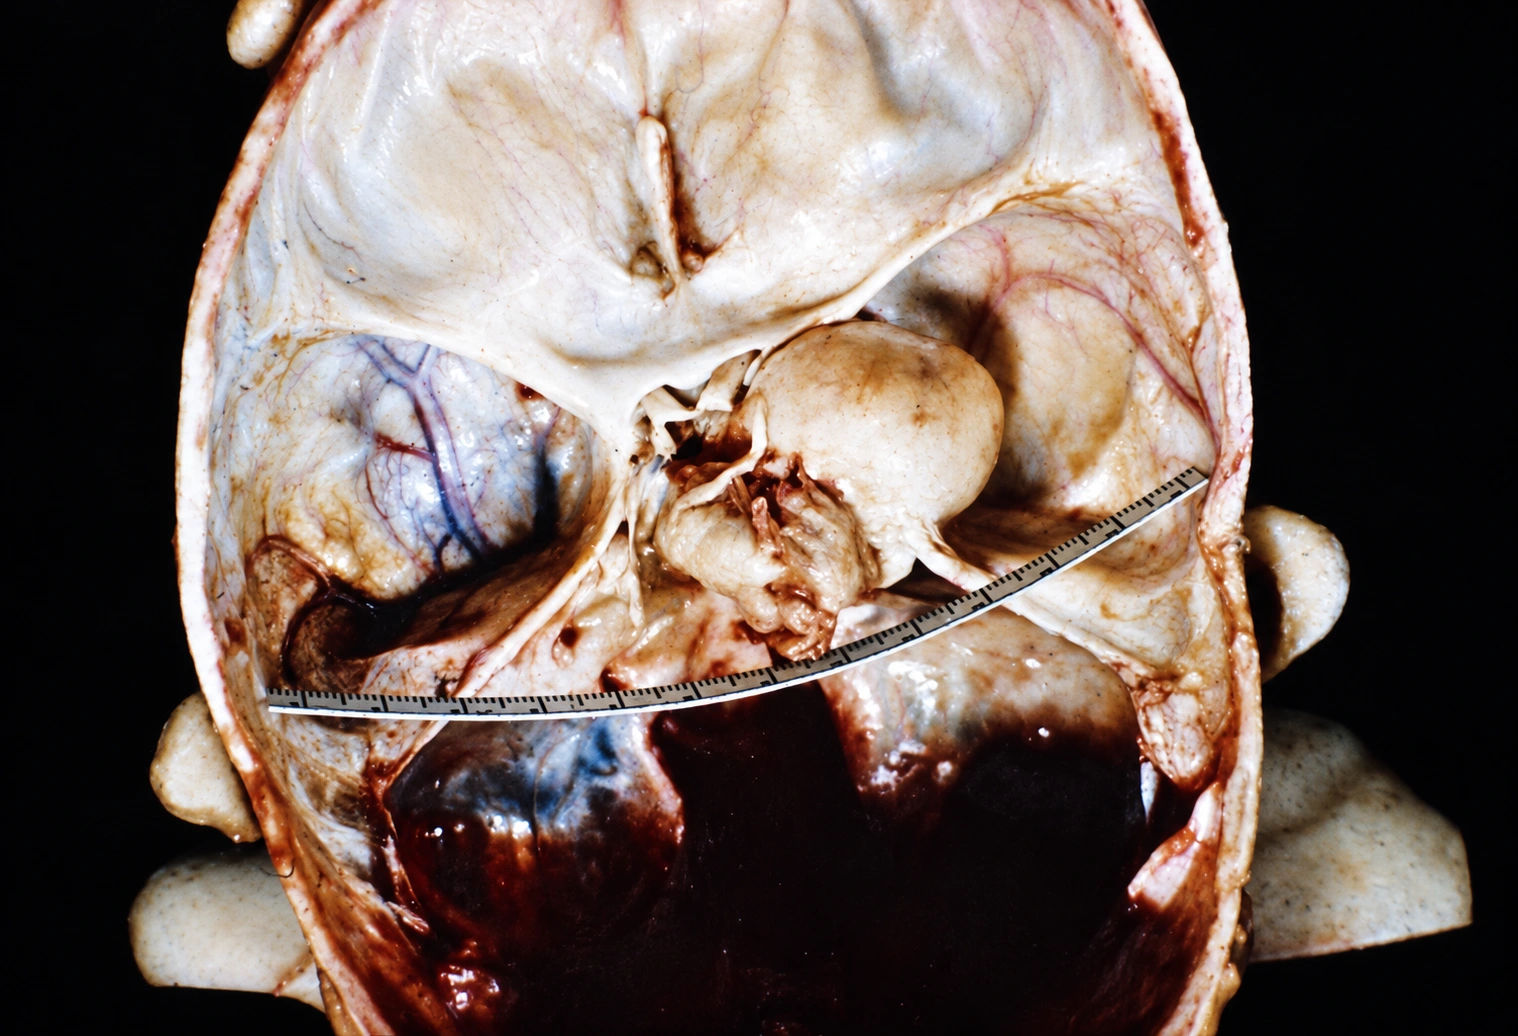

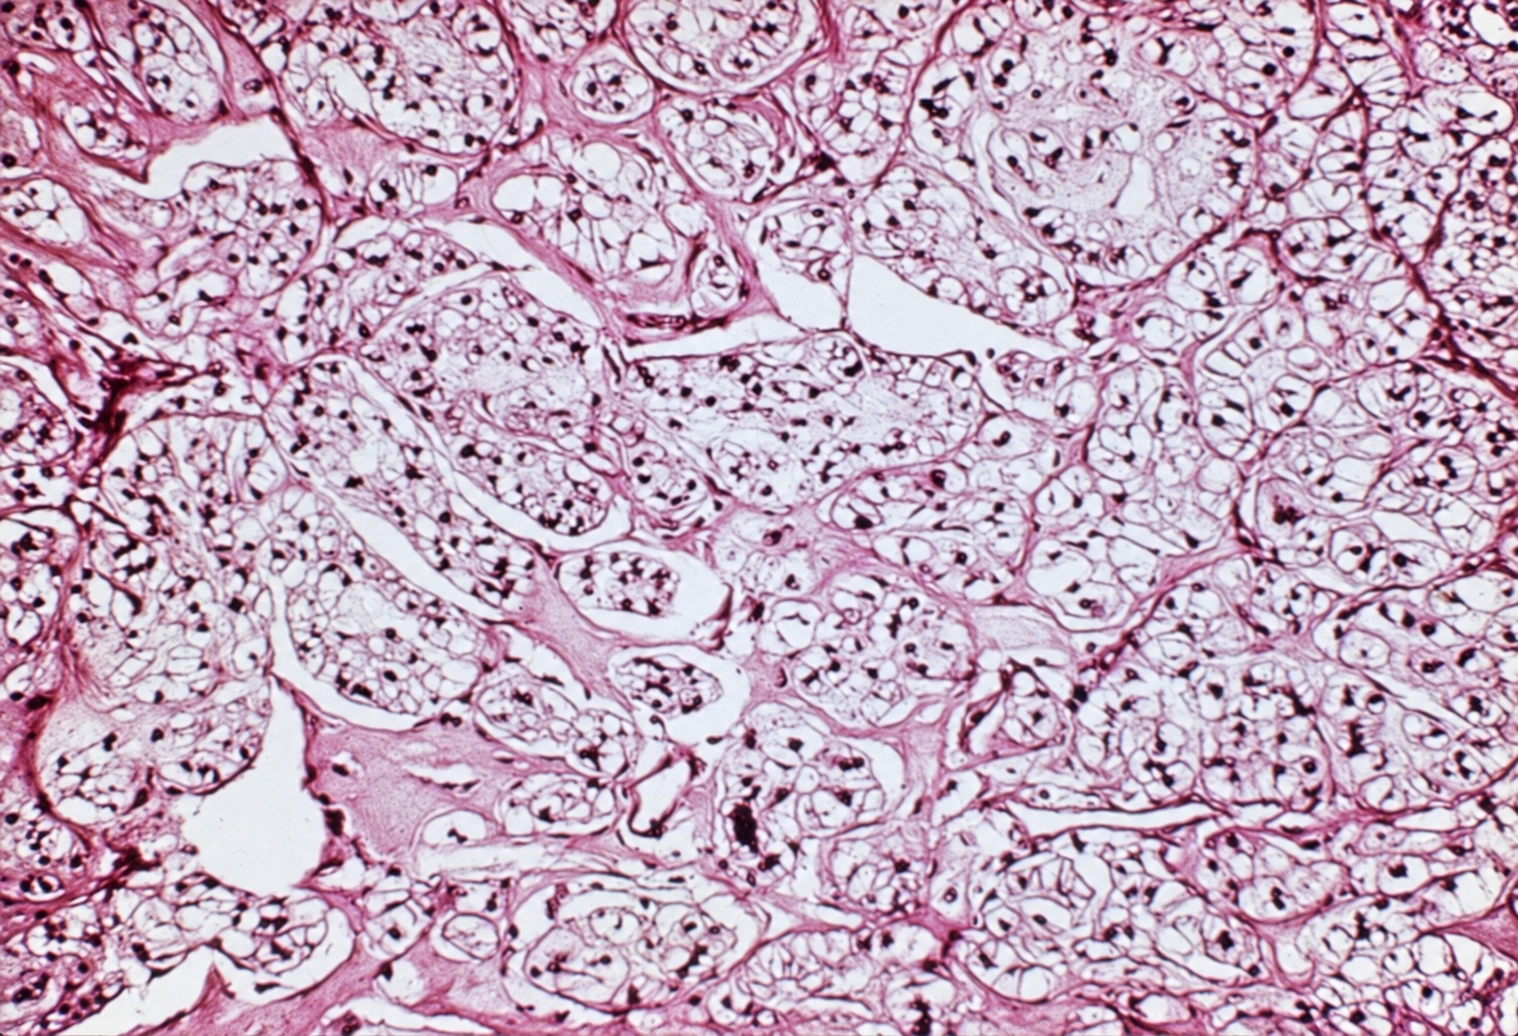







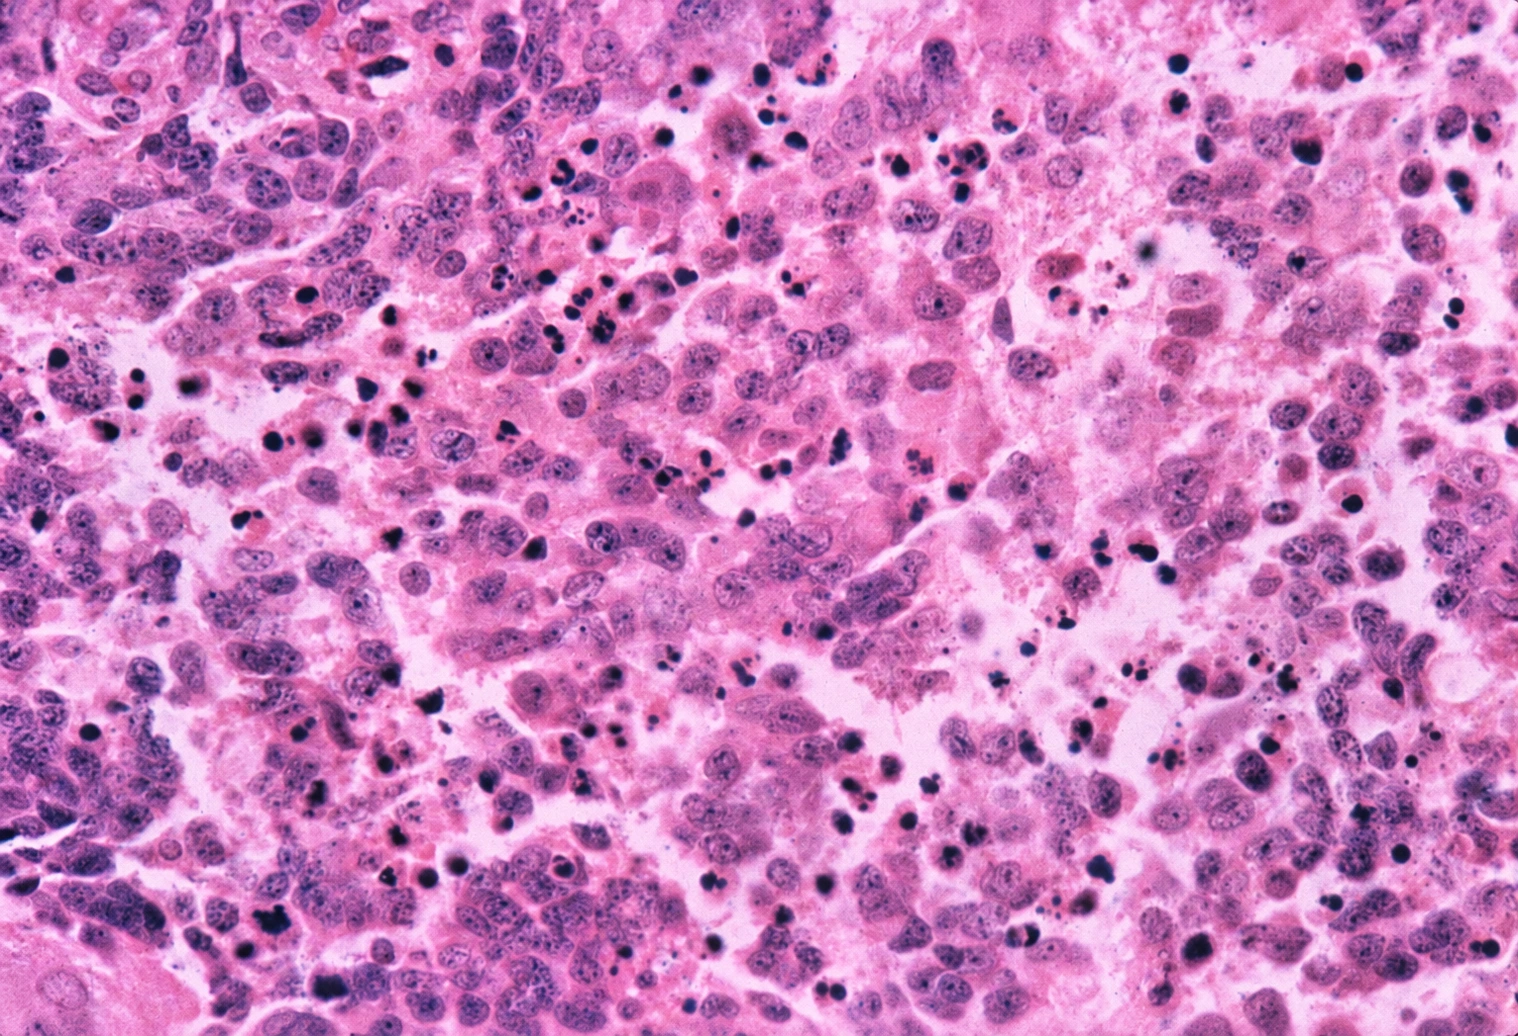

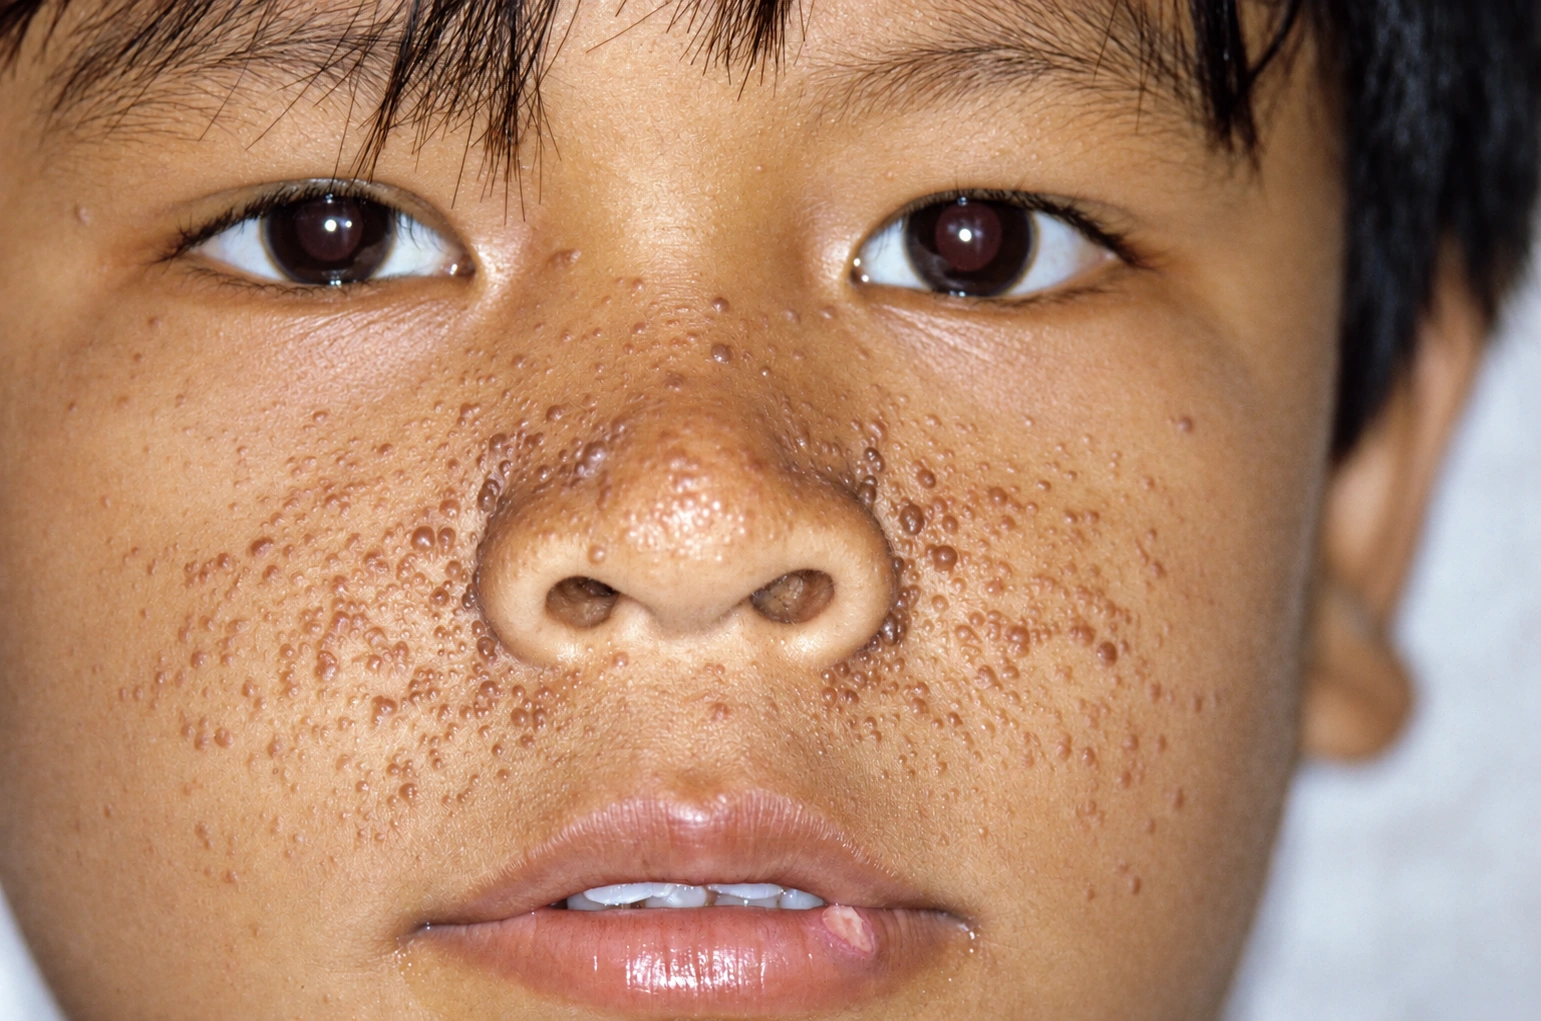
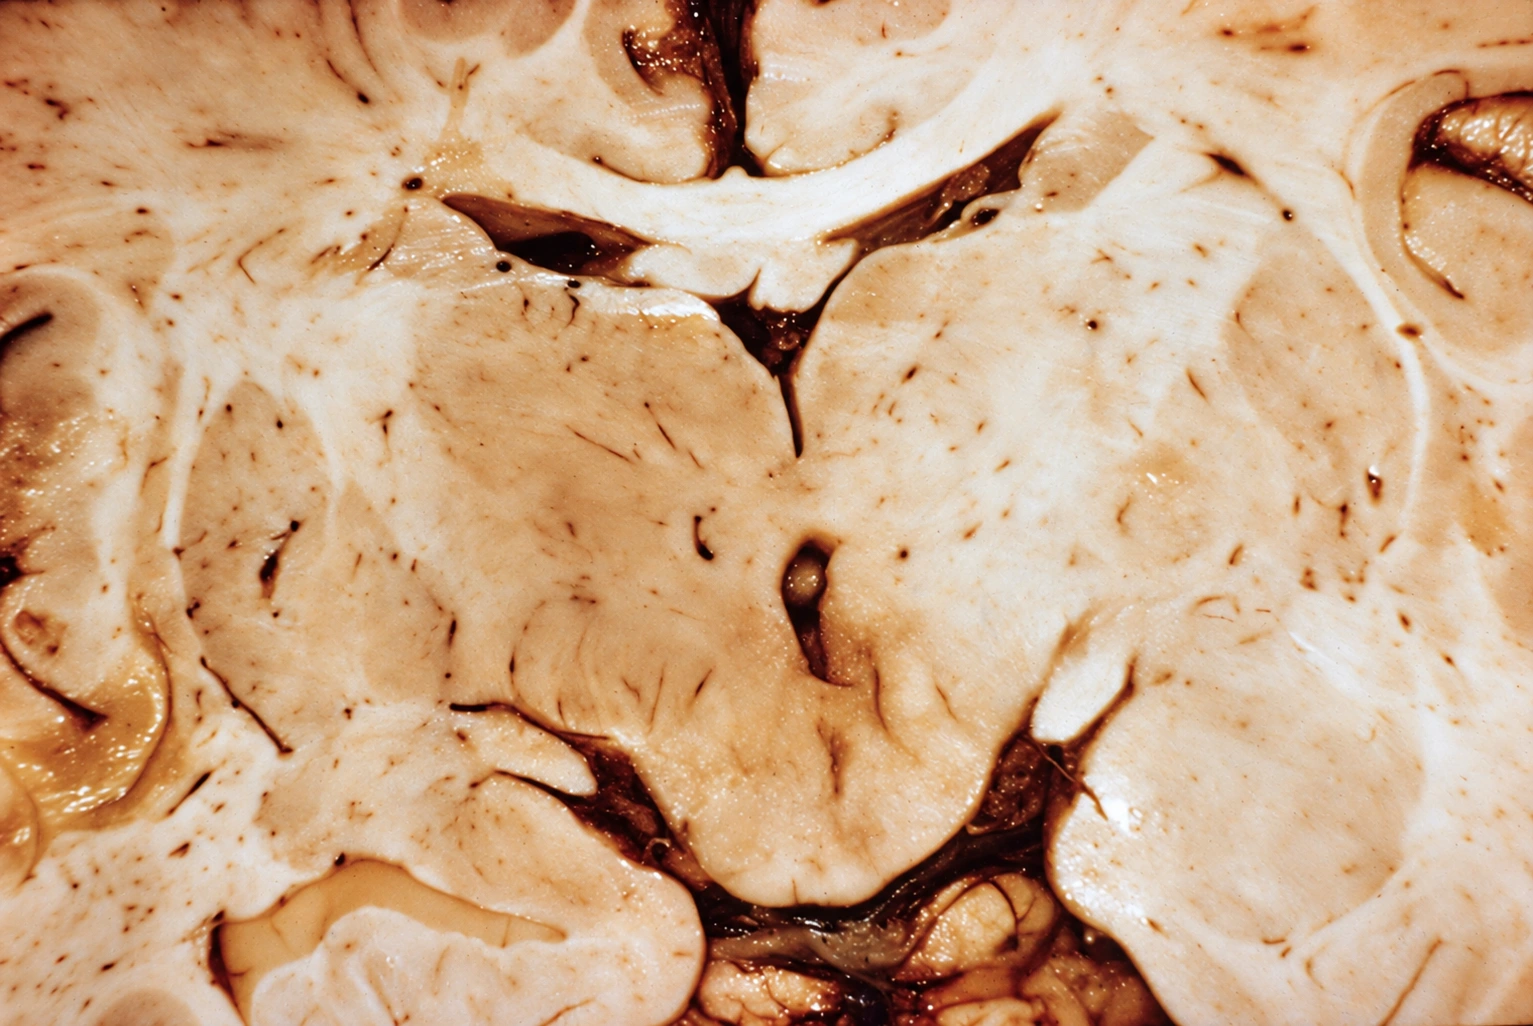
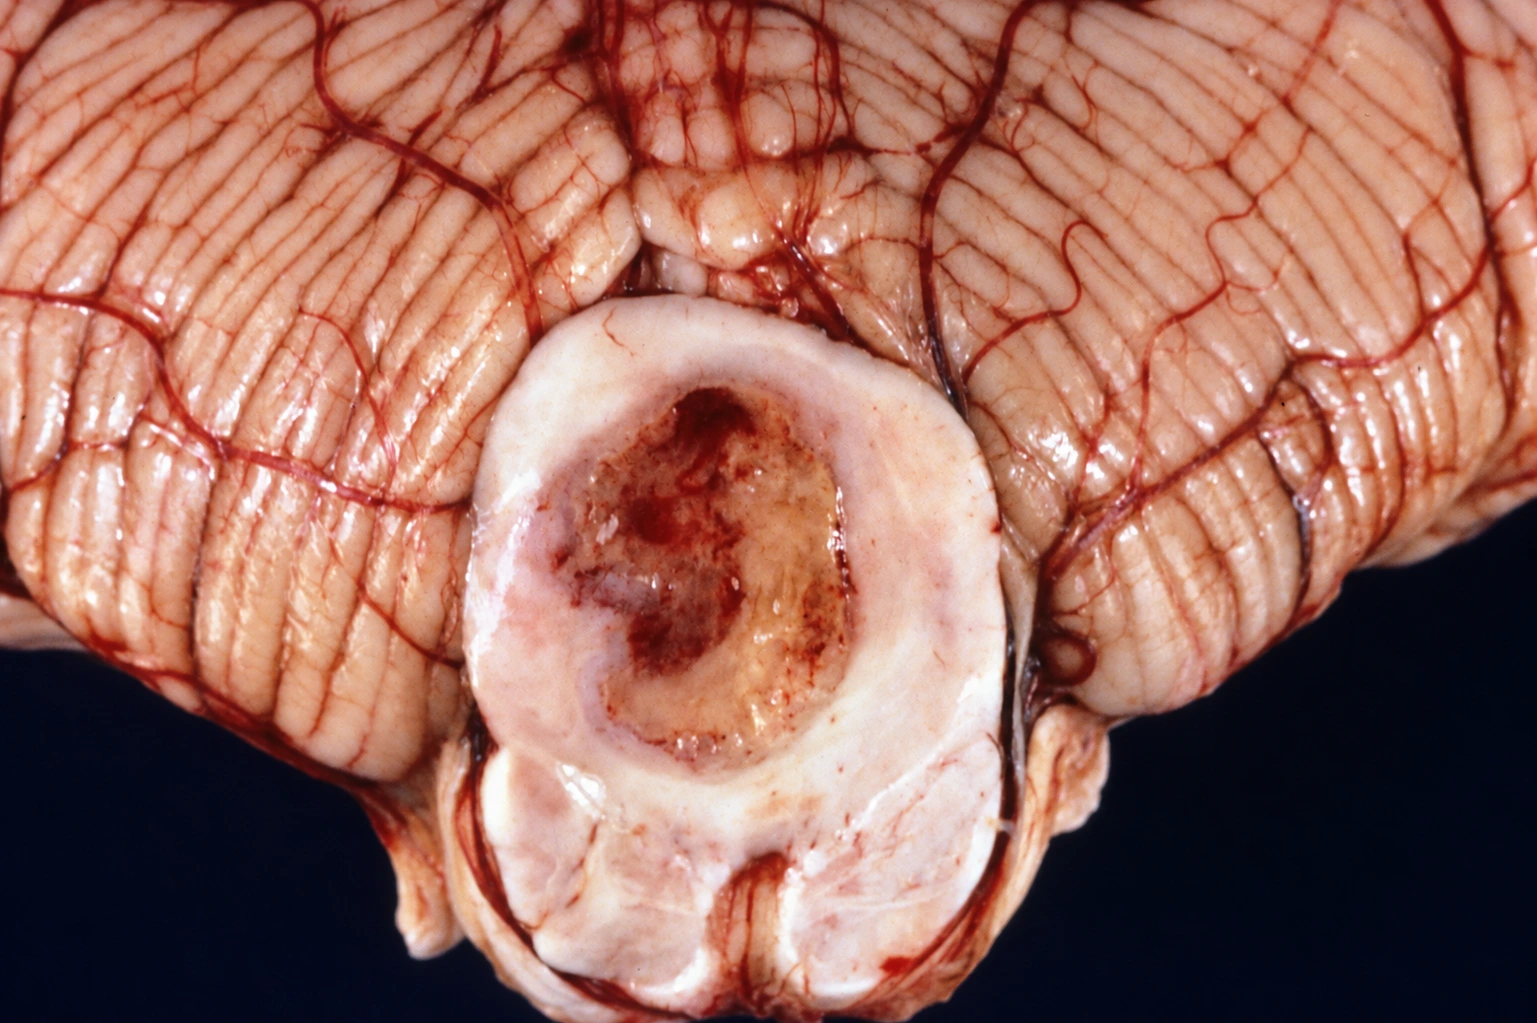
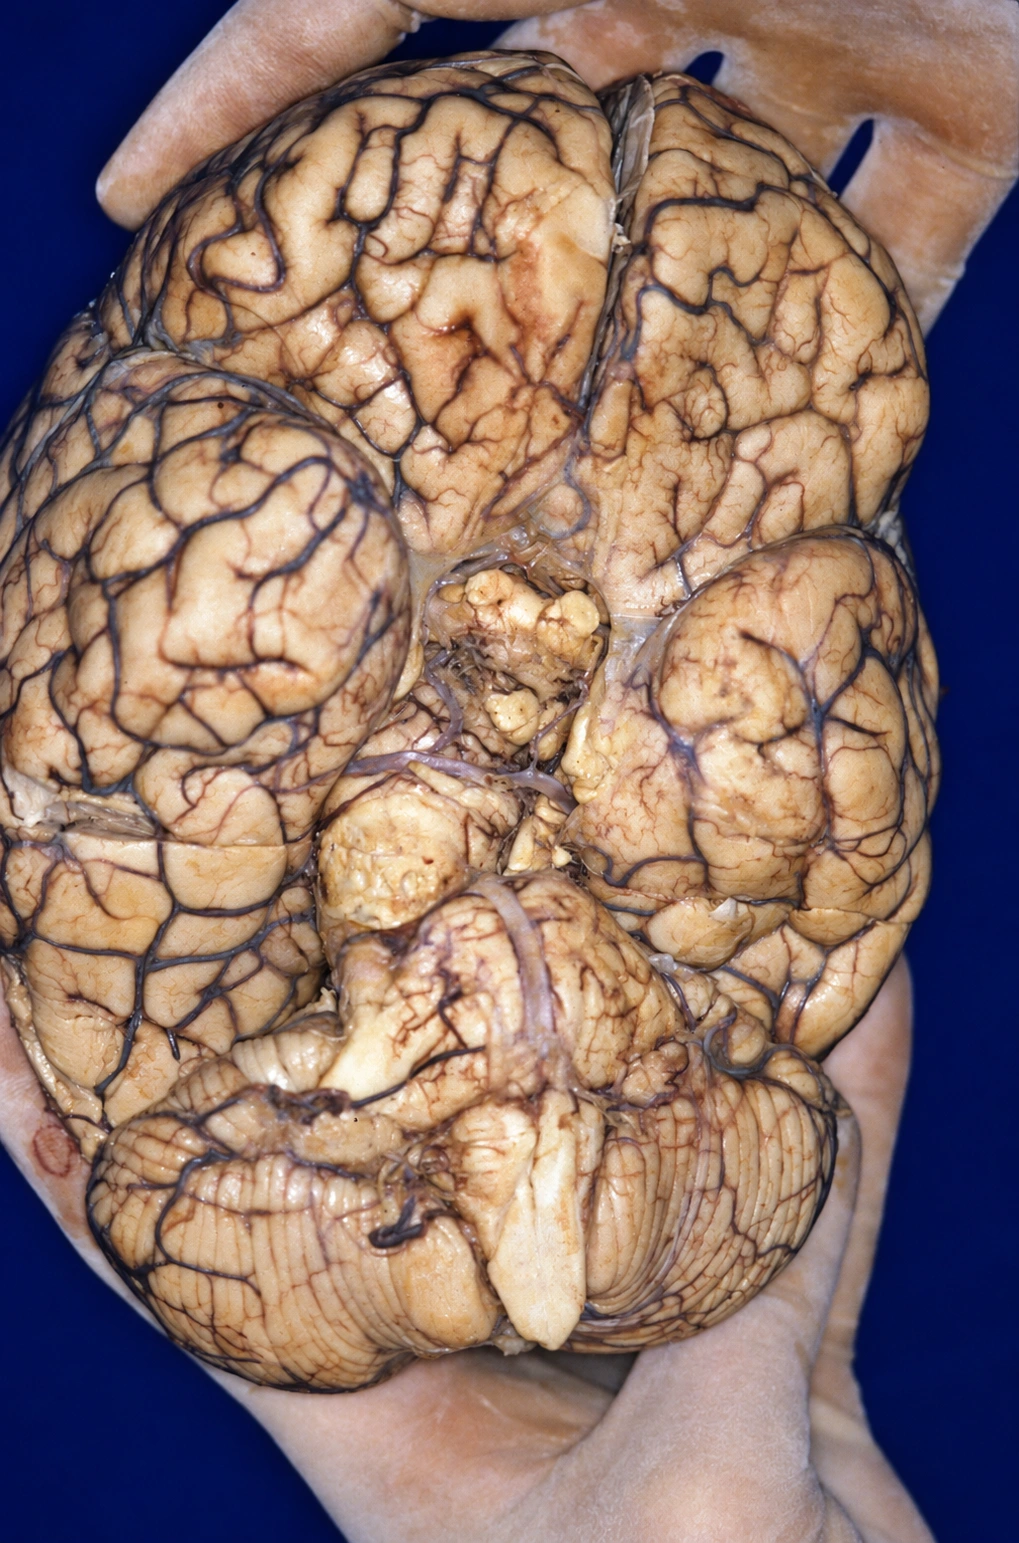
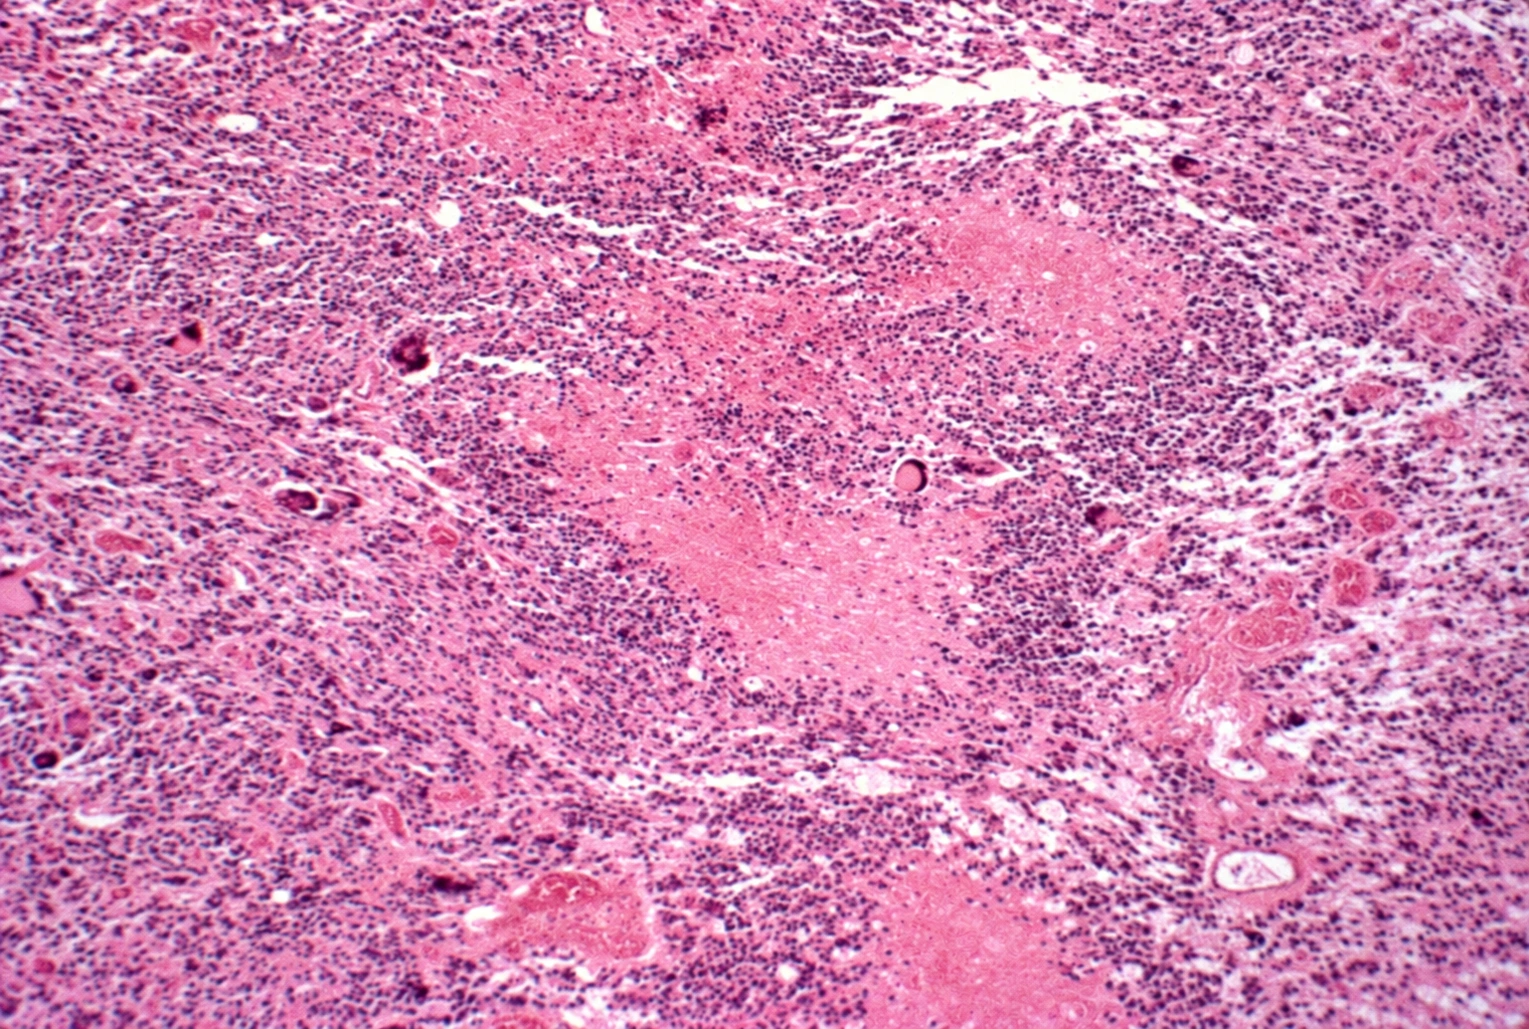
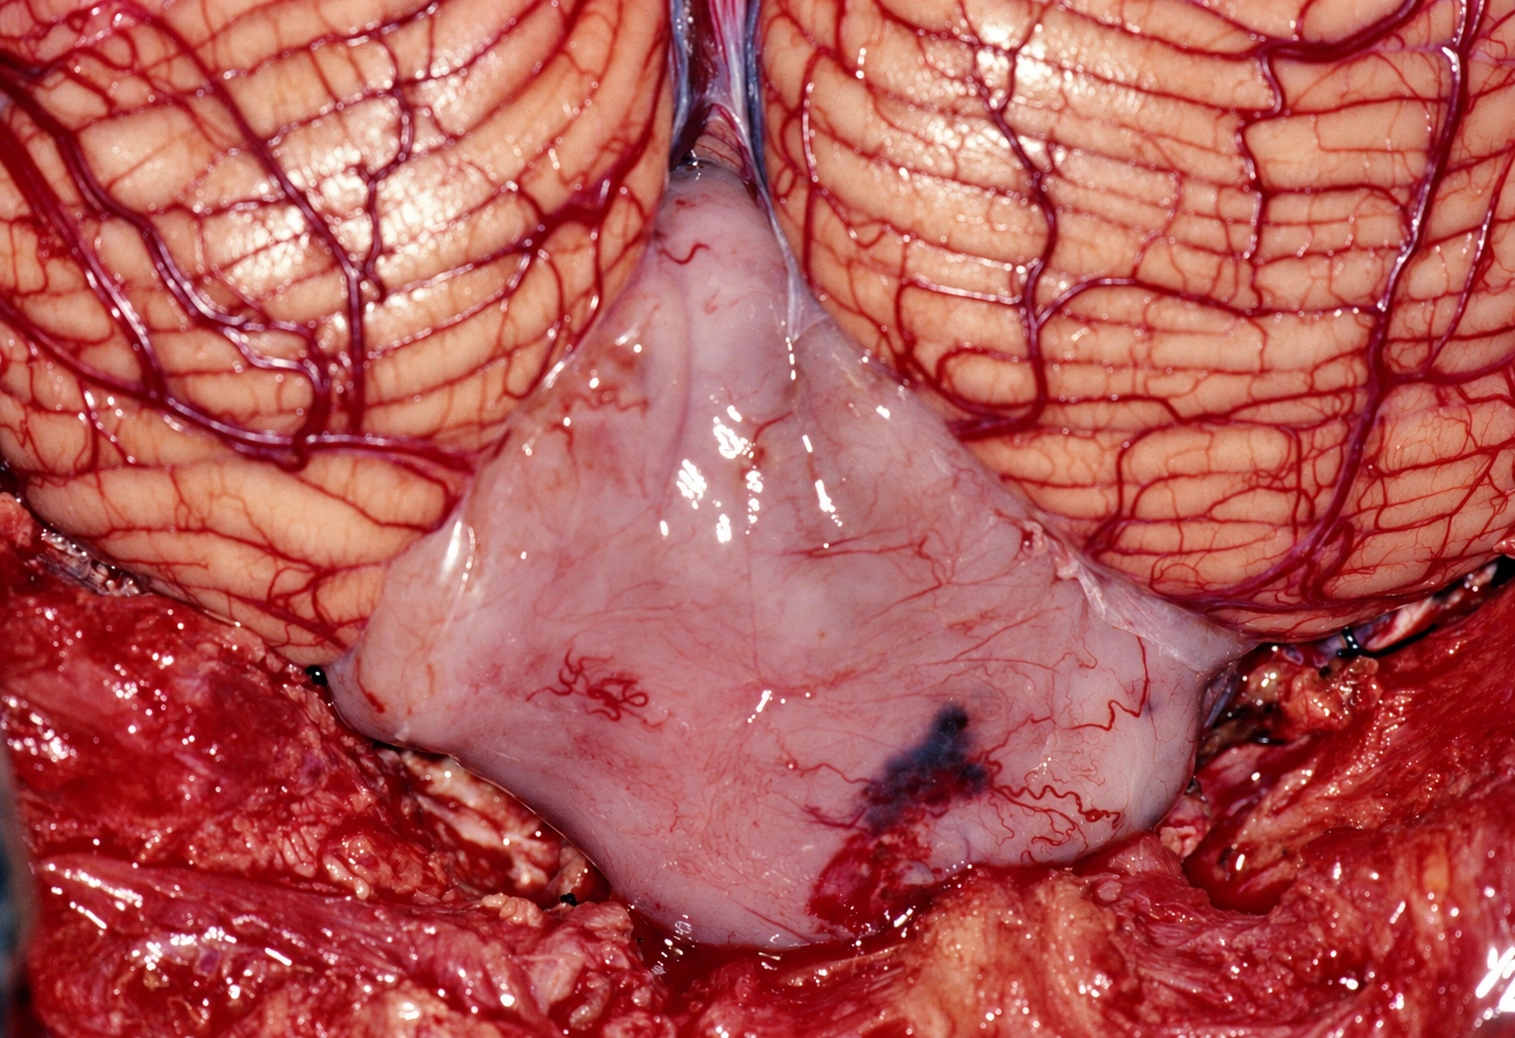
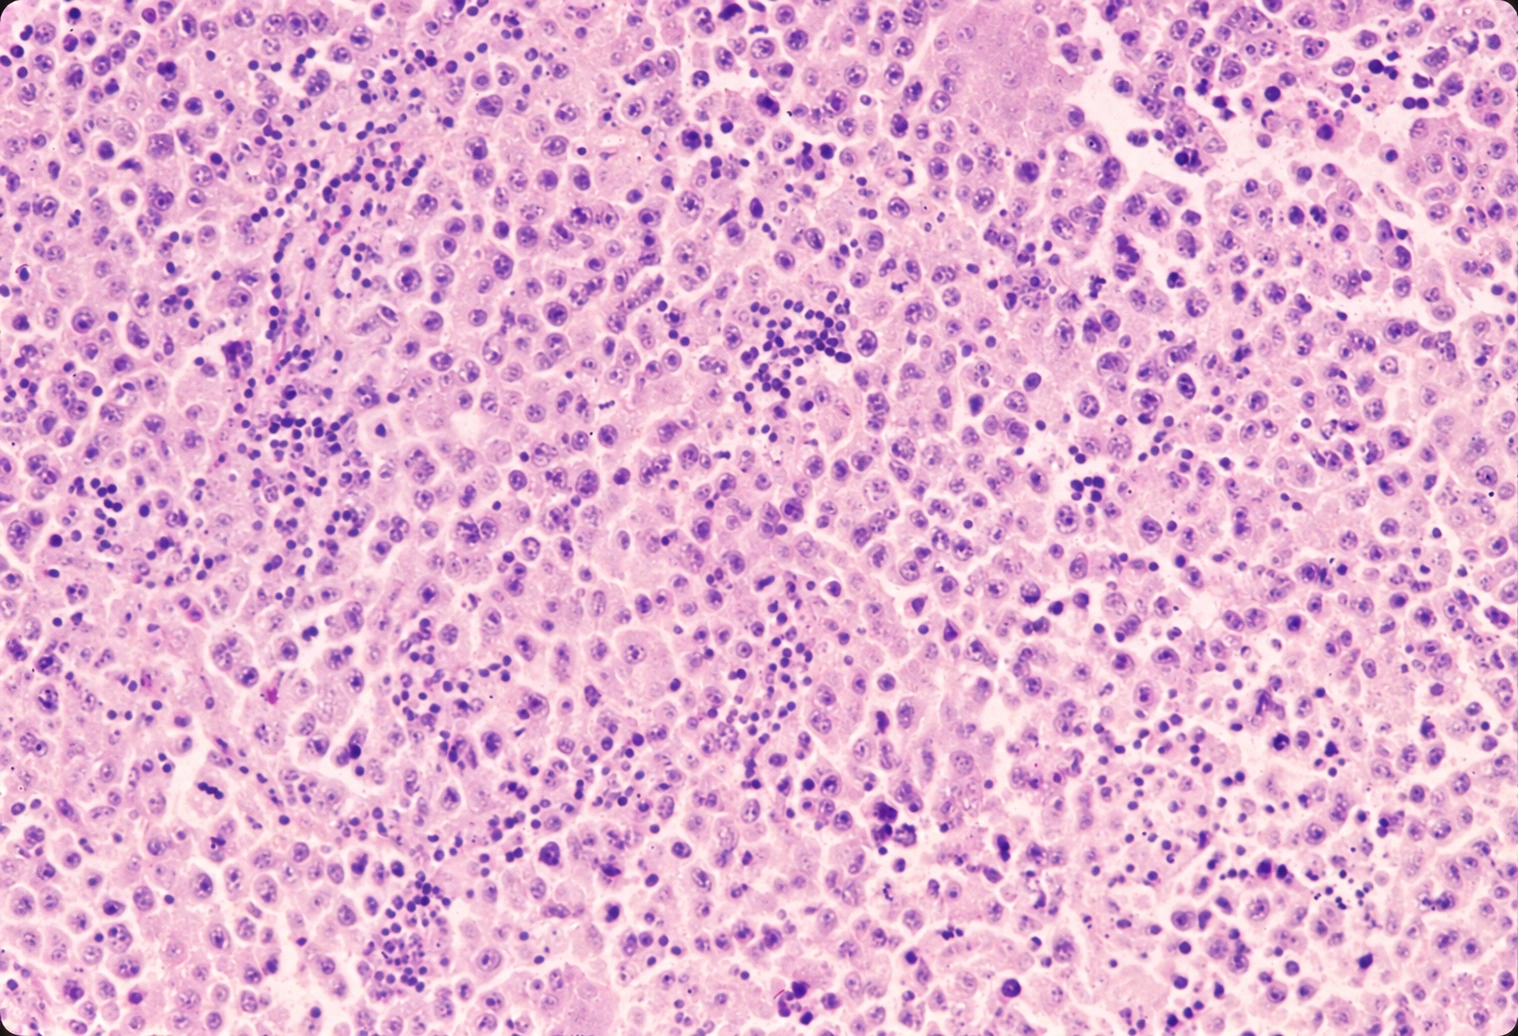
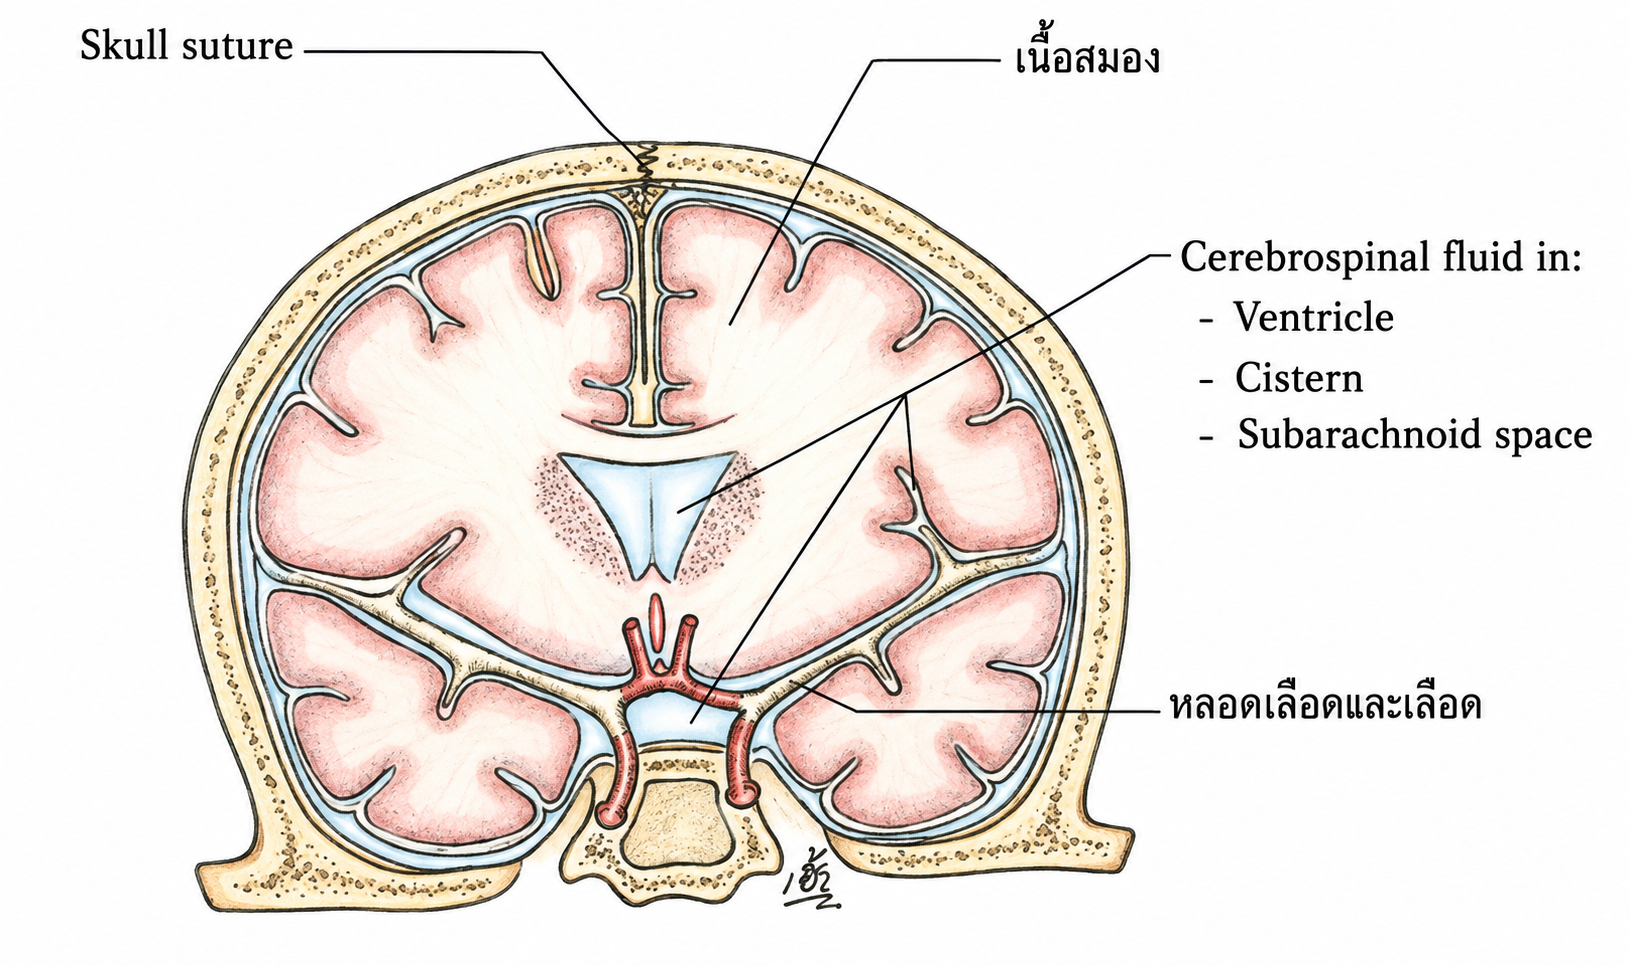
 Color added · Anatomical details based on the original image


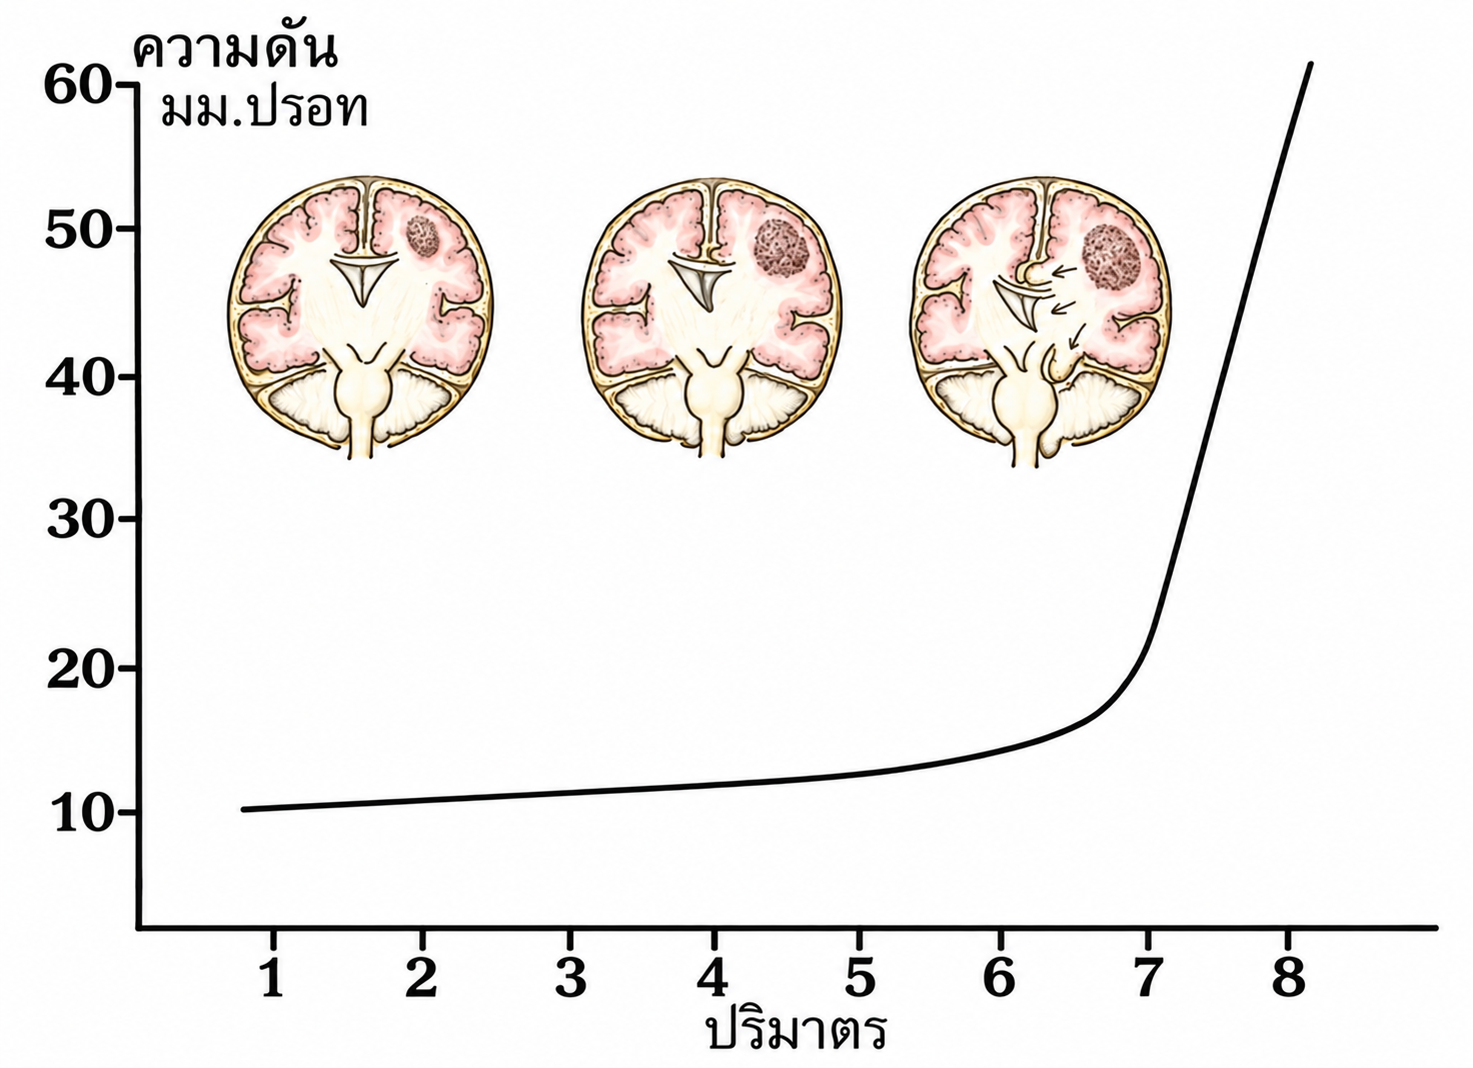
 Color added · Anatomical details based on the original image
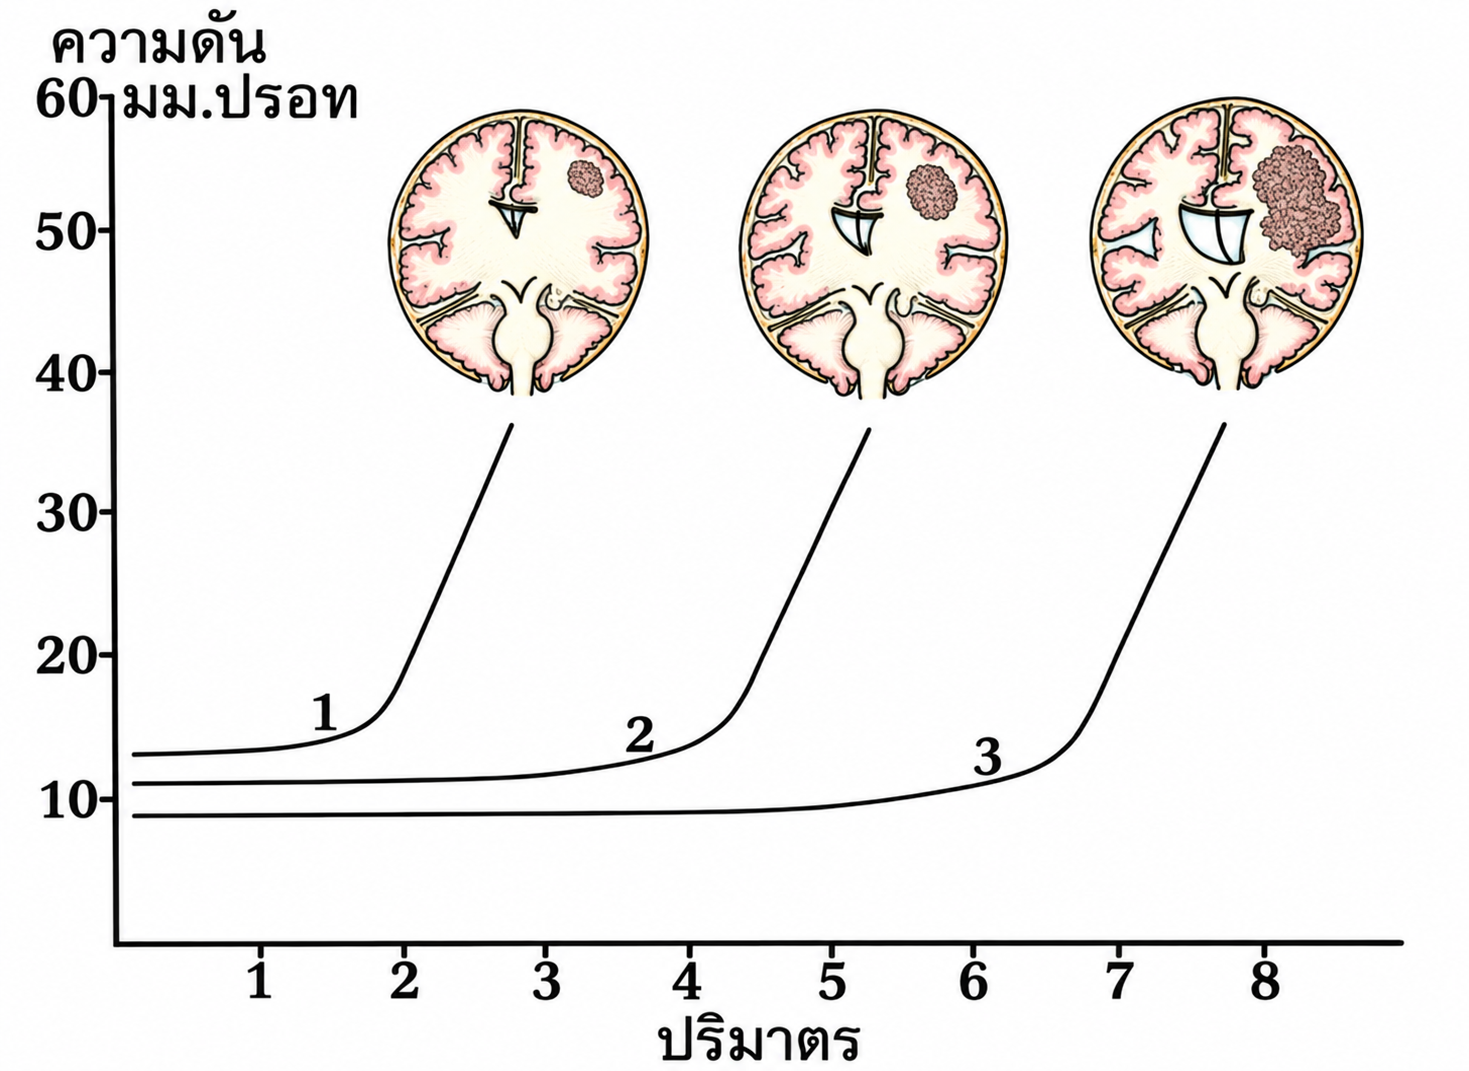
 Color added · Anatomical details based on the original image
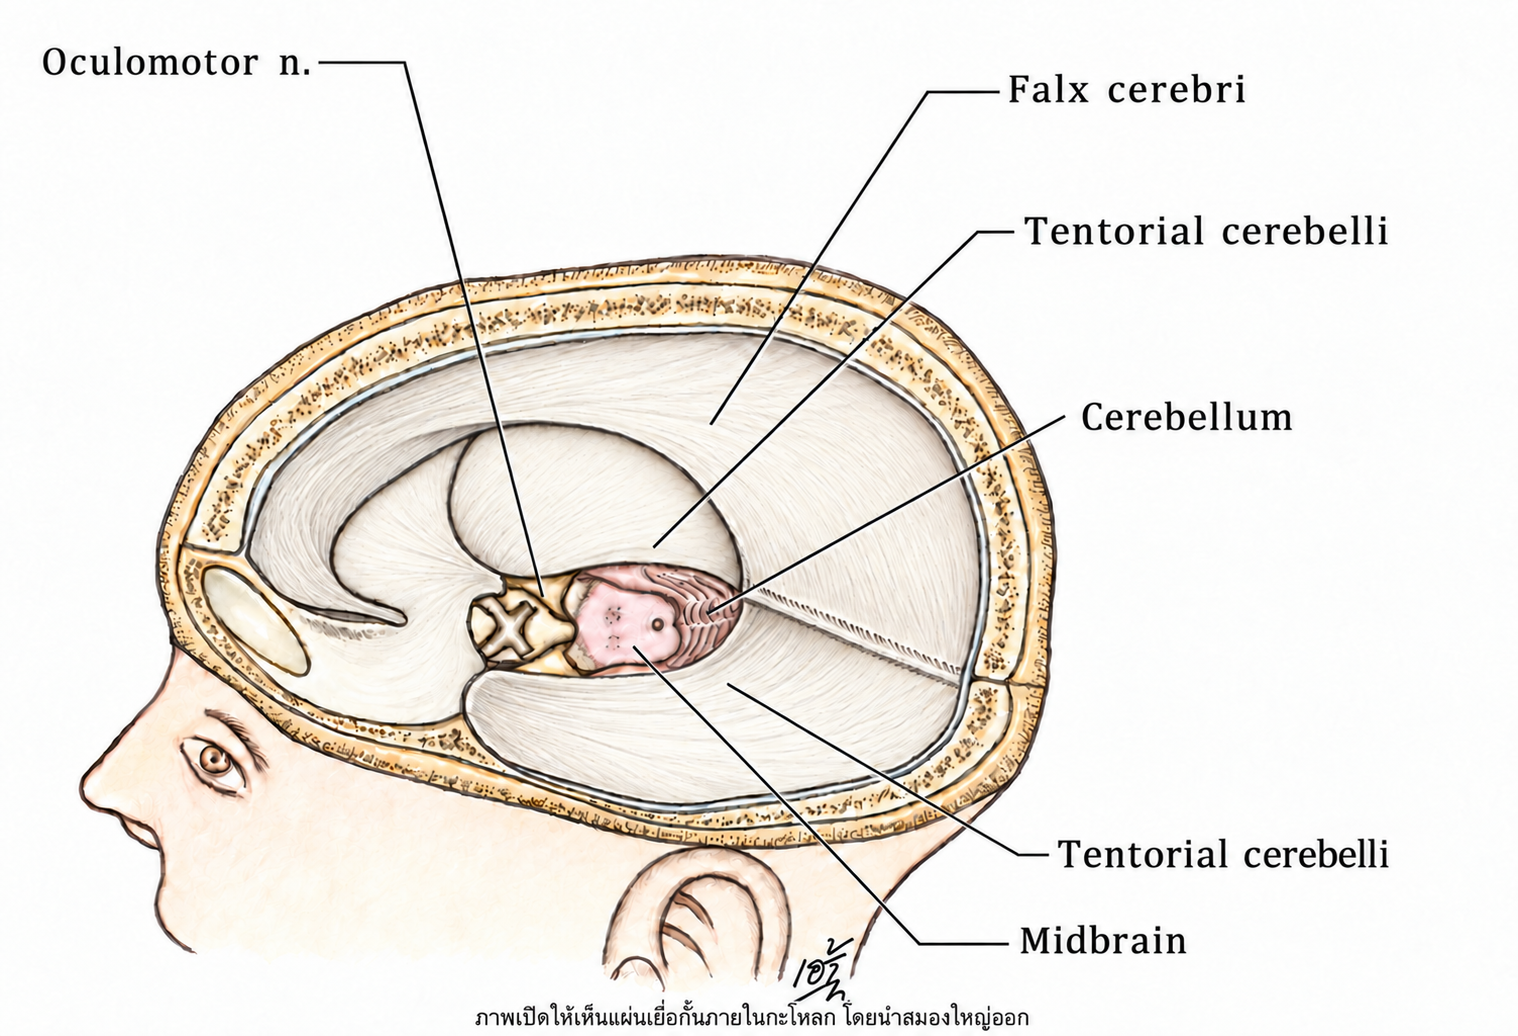
 Color added · Anatomical details based on the original image
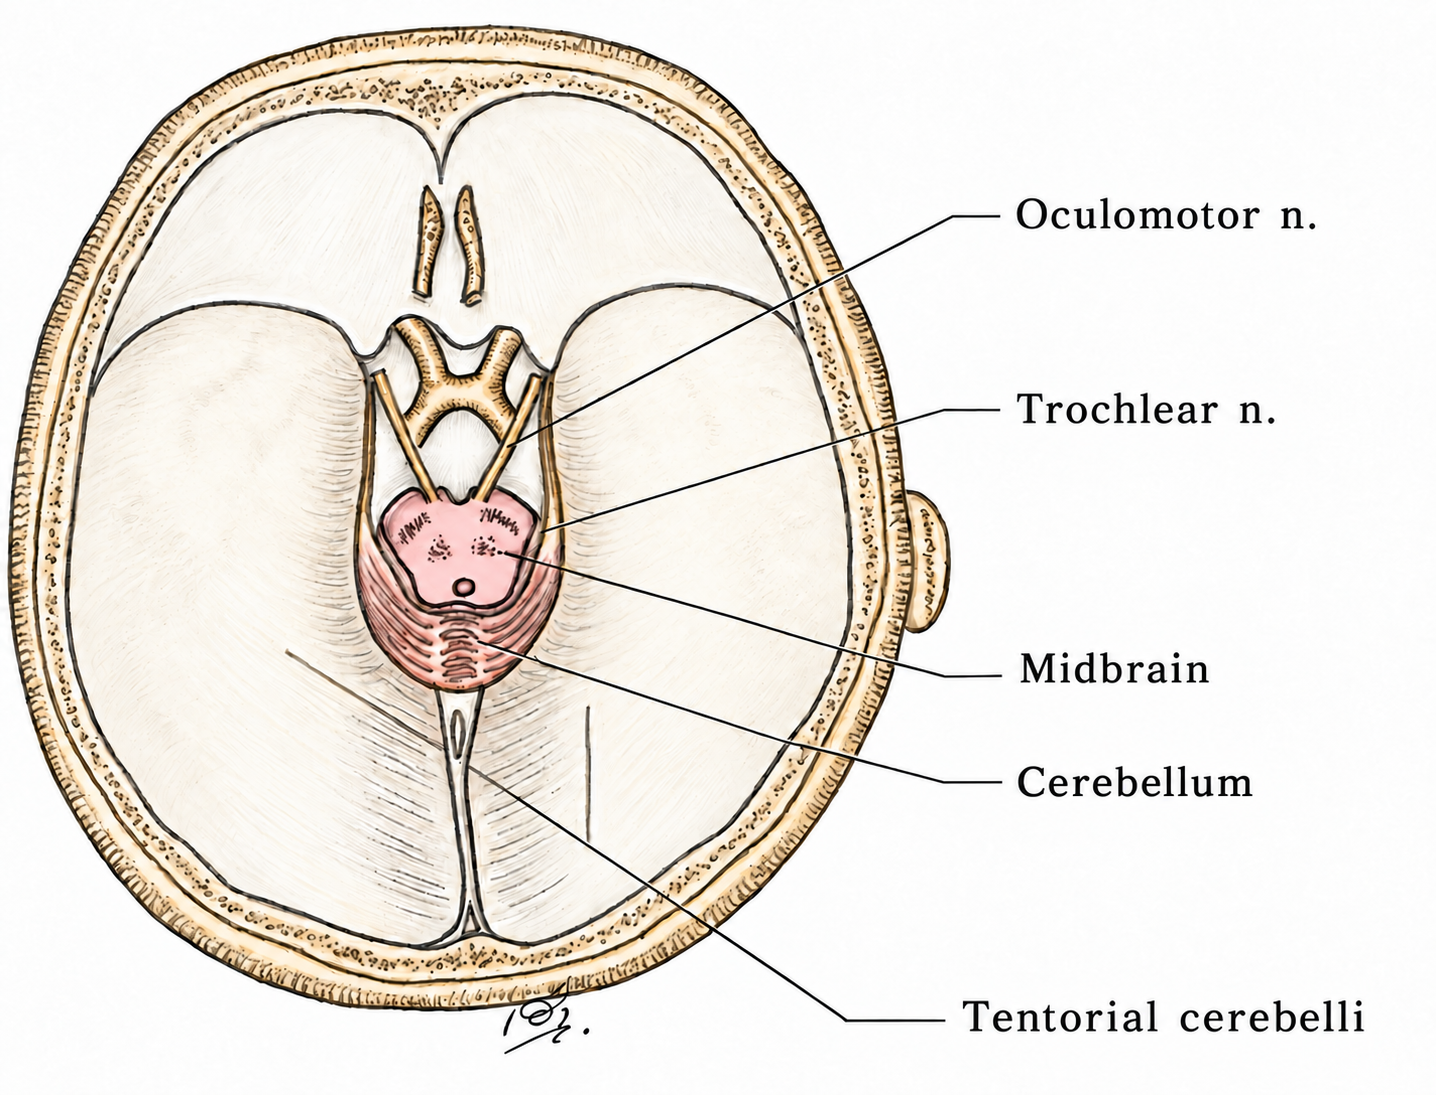
 Color added · Anatomical details based on the original image


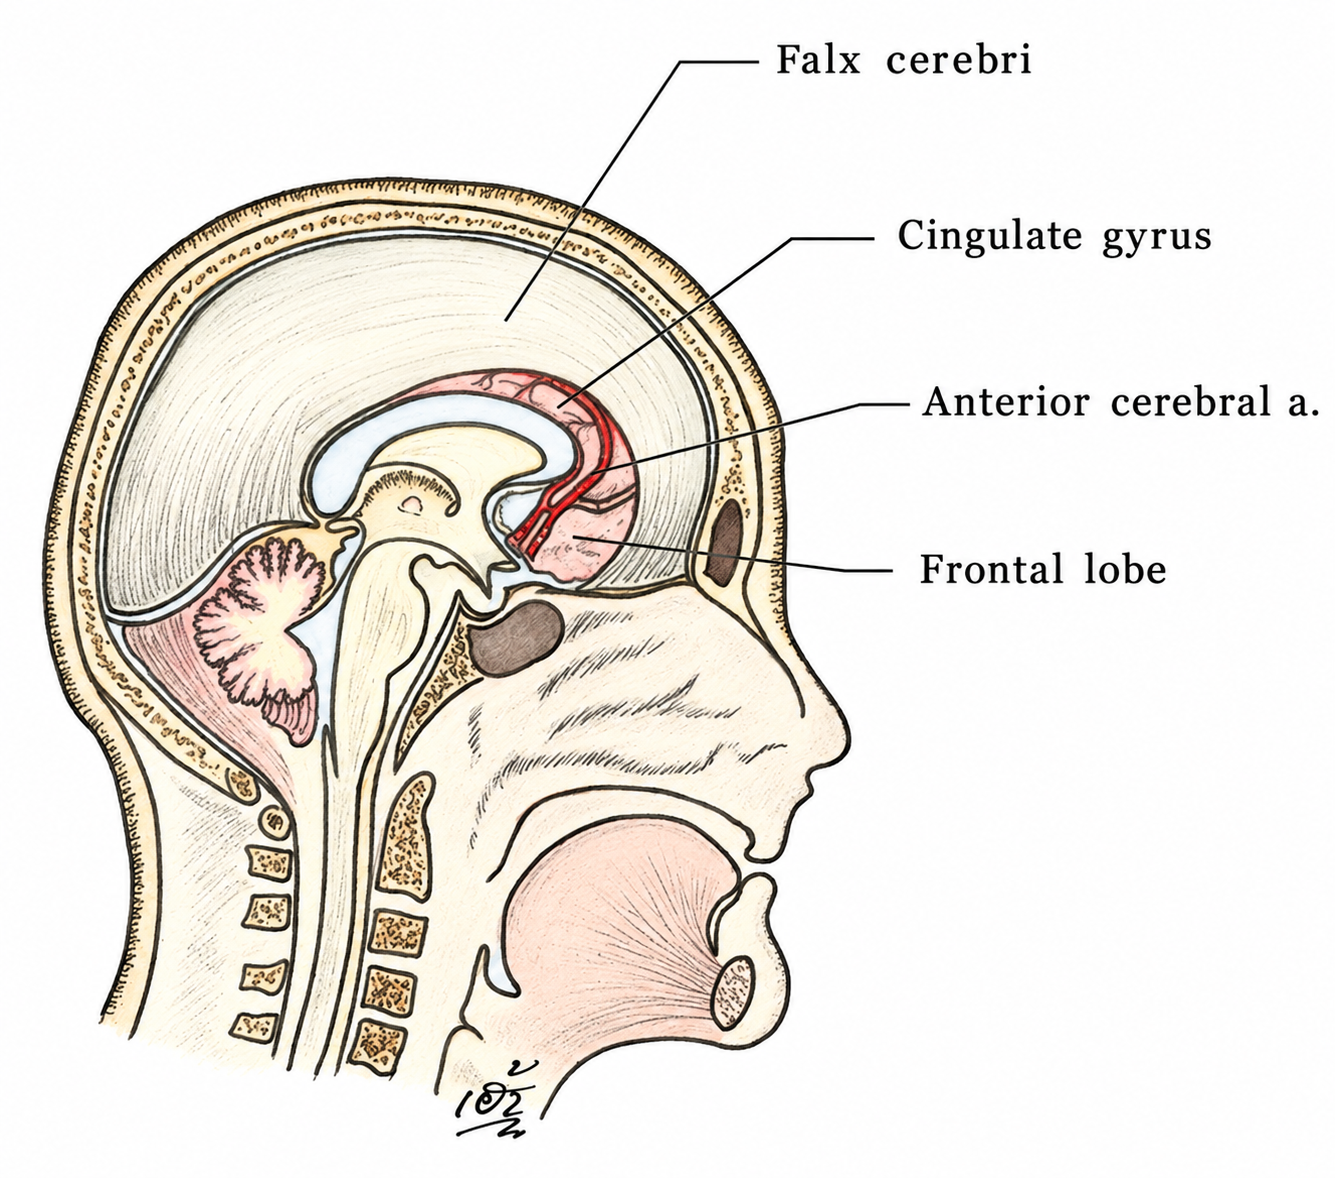
 Color added · Anatomical details based on the original image


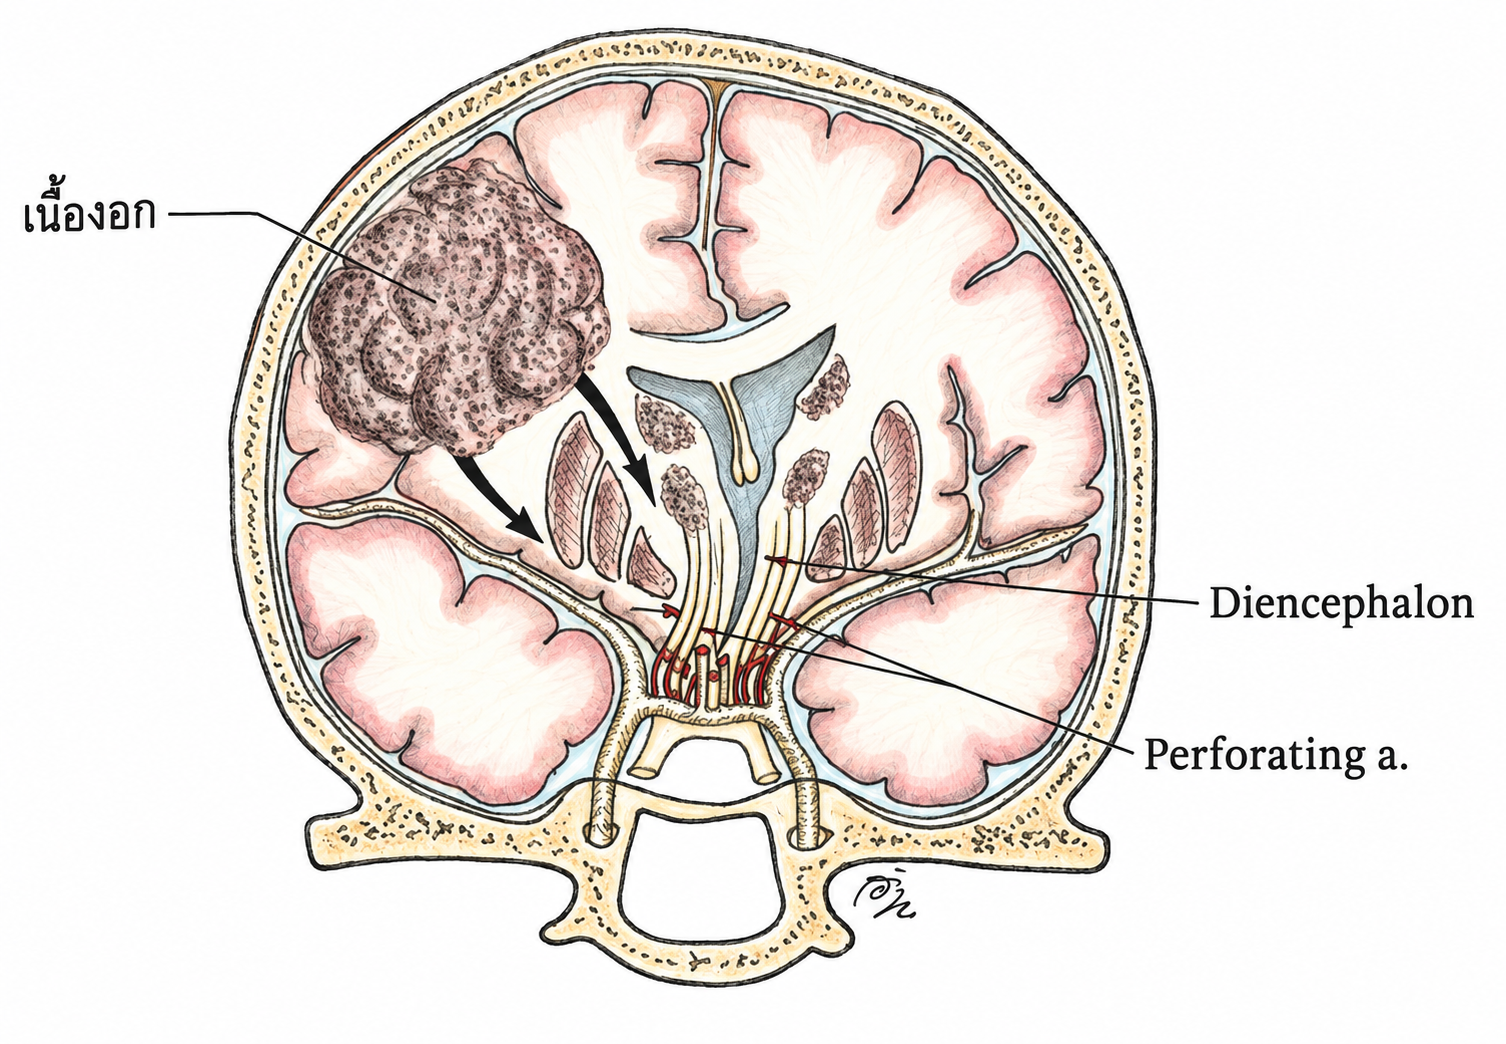
 Color added · Anatomical details based on the original illustration


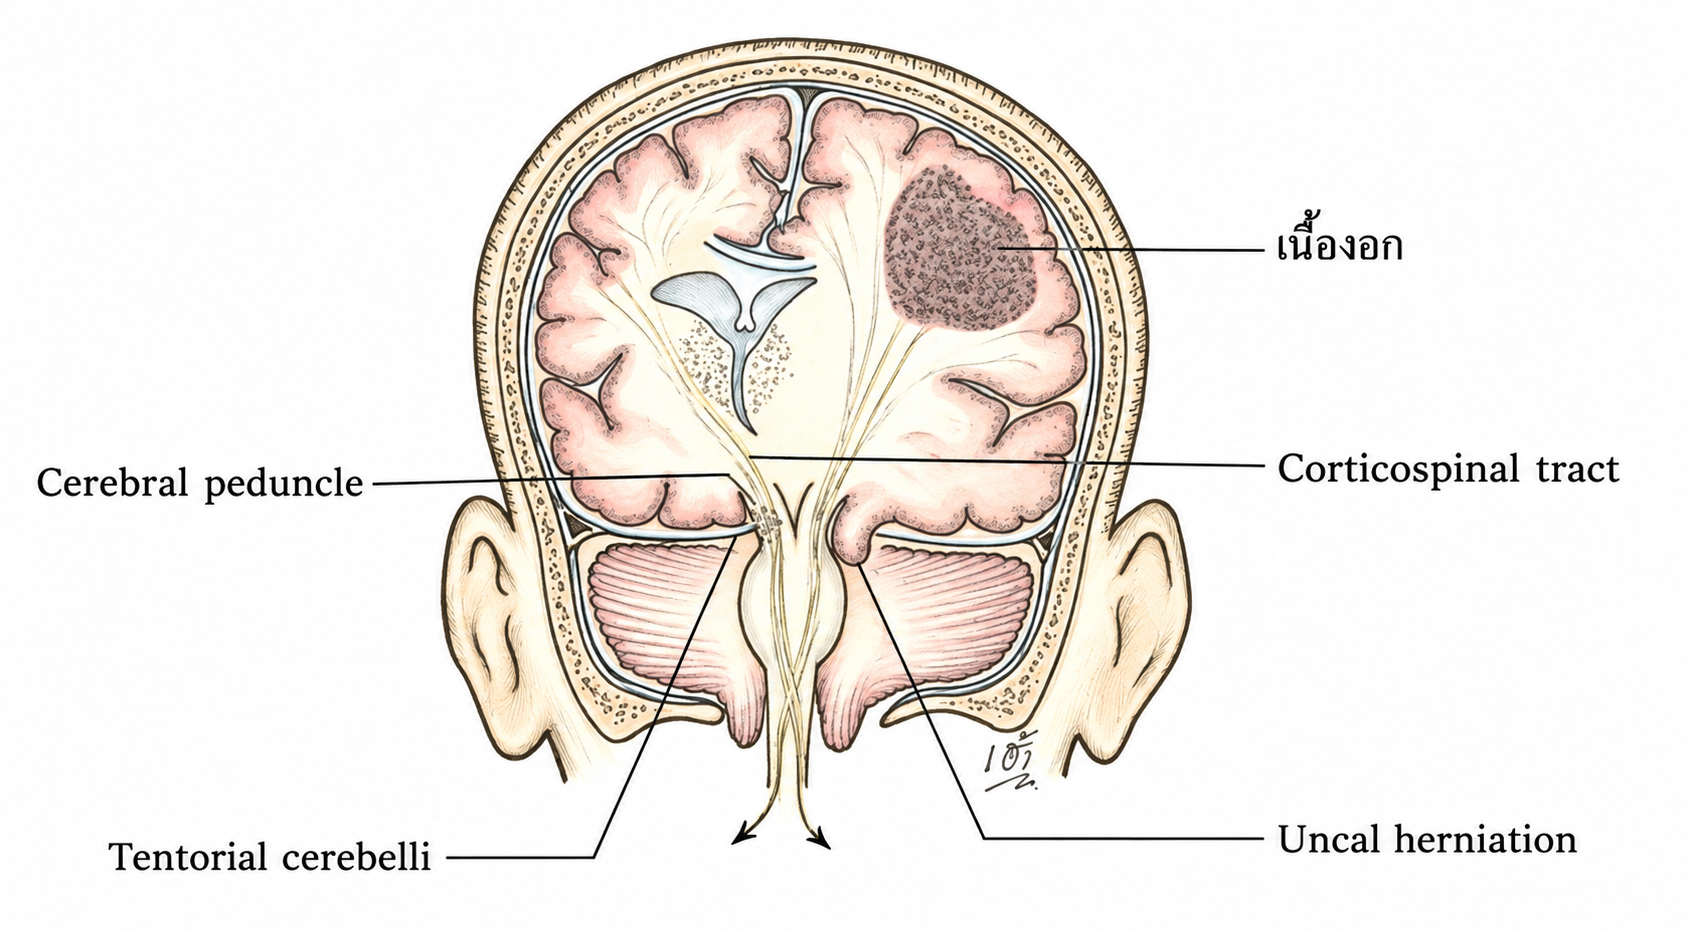
 Color added · Anatomical details based on the original illustration


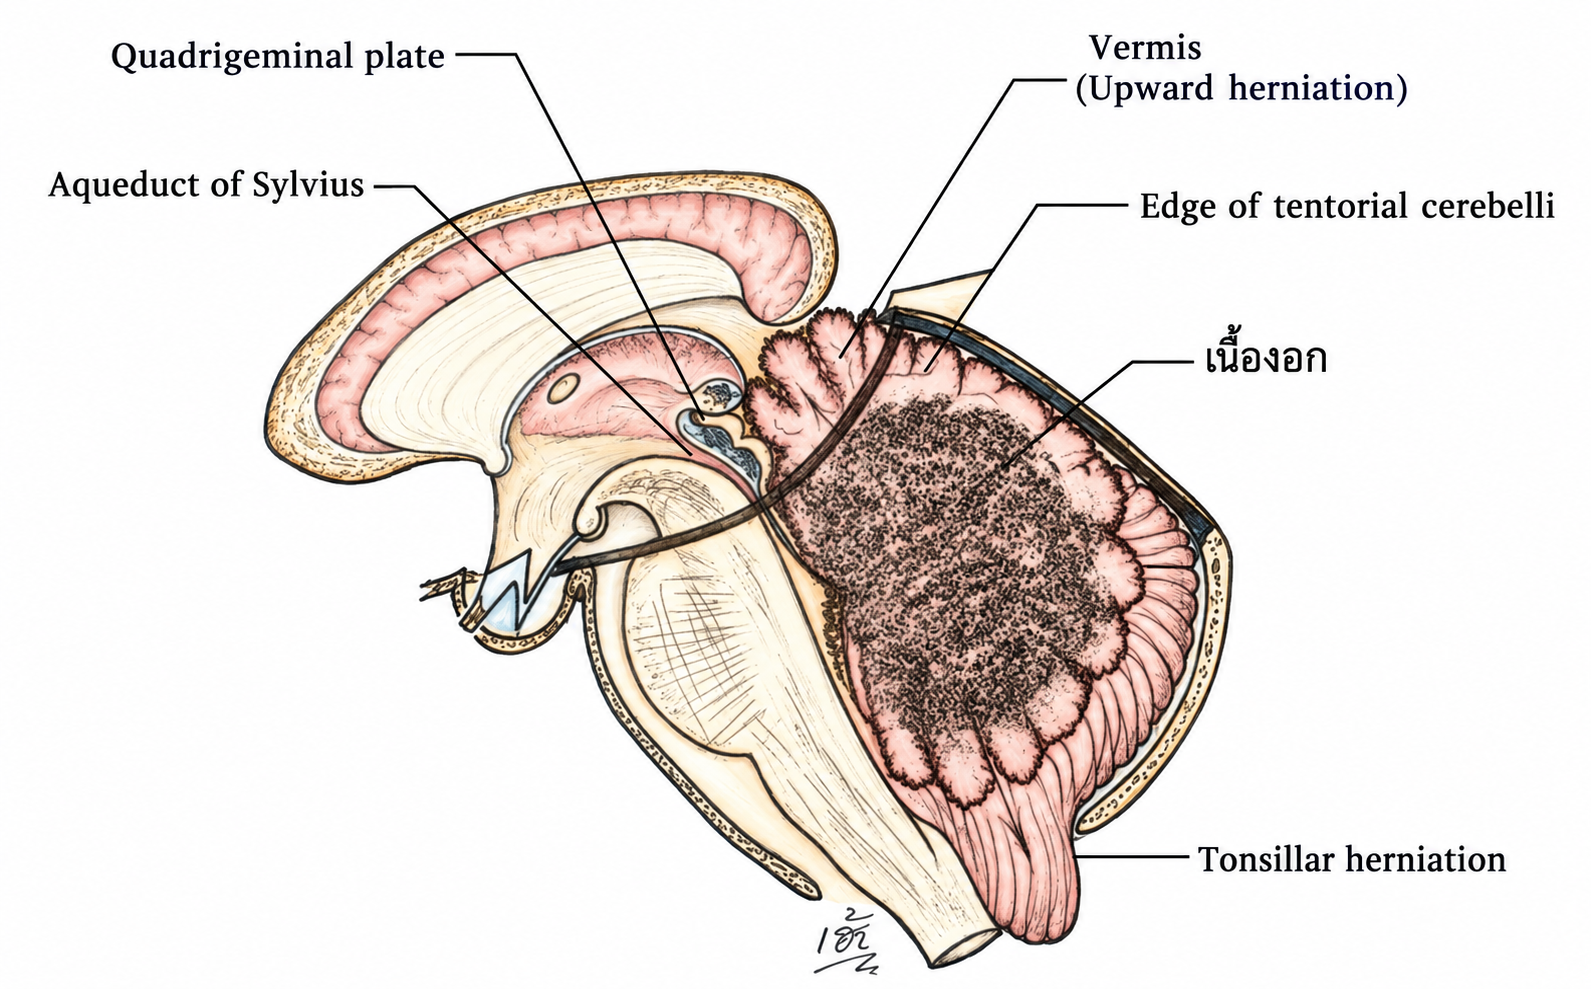
 Color added · Anatomical details based on the original illustration


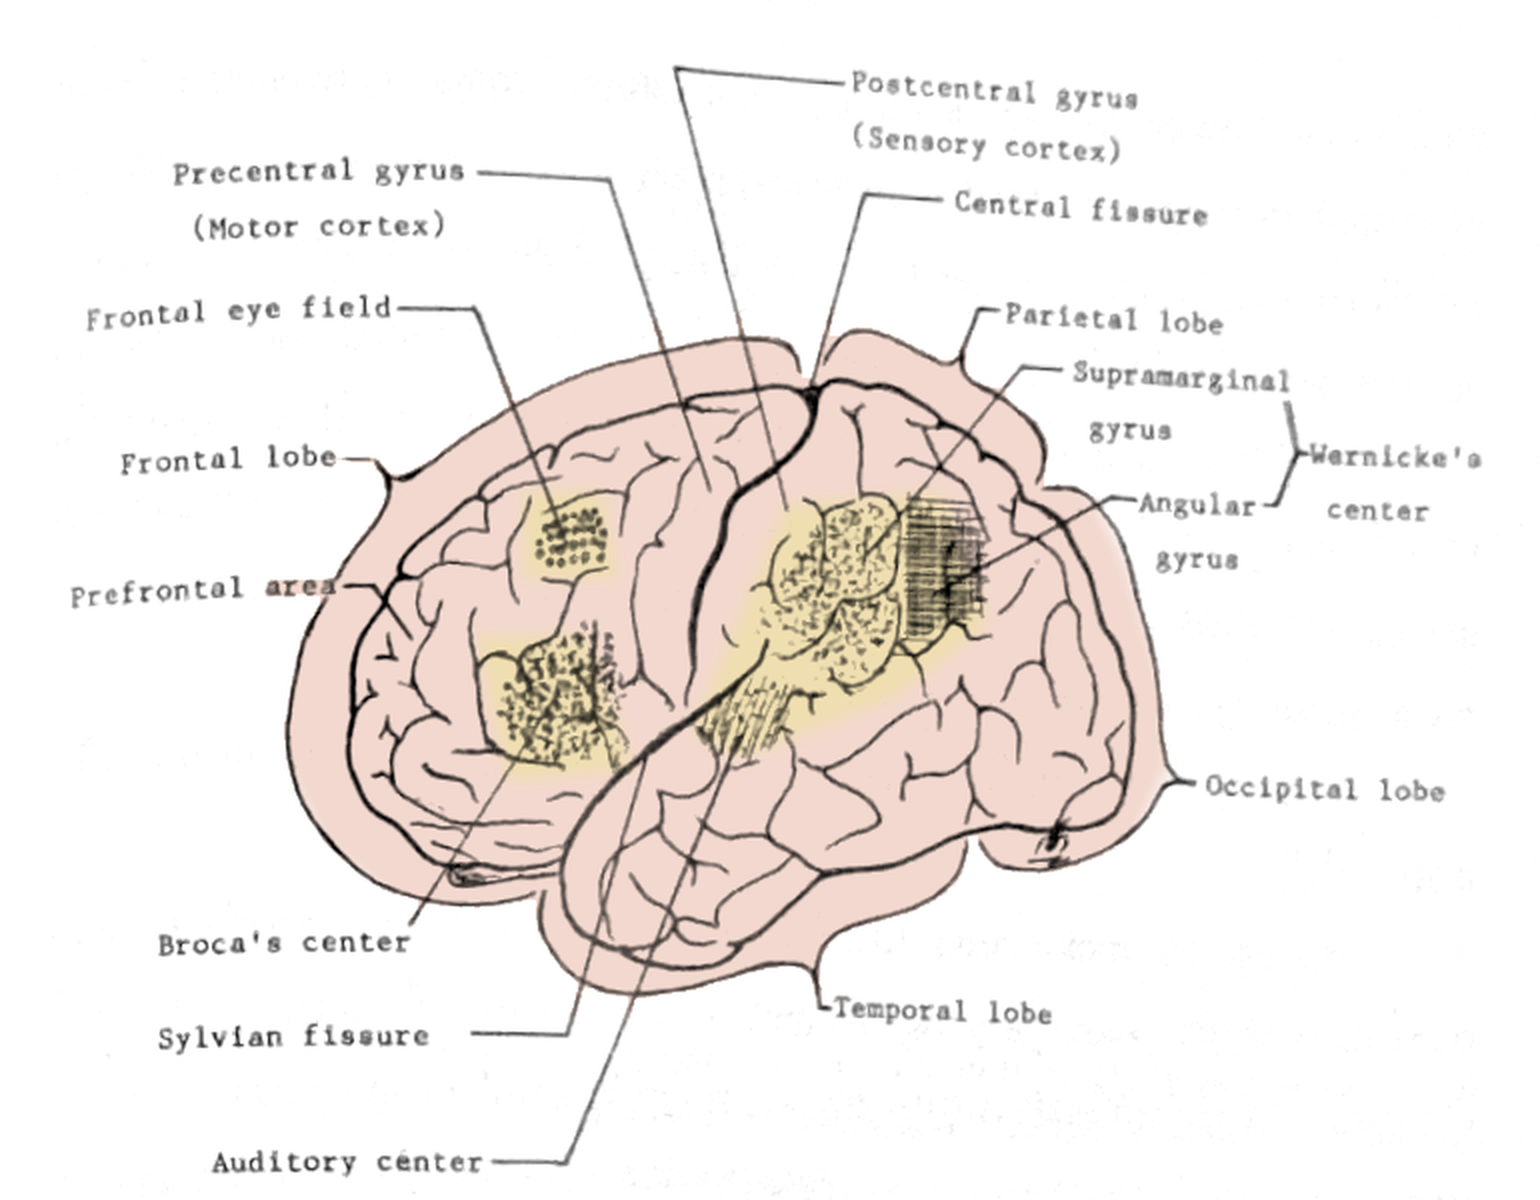
 Color added while retaining the original linework and lettering
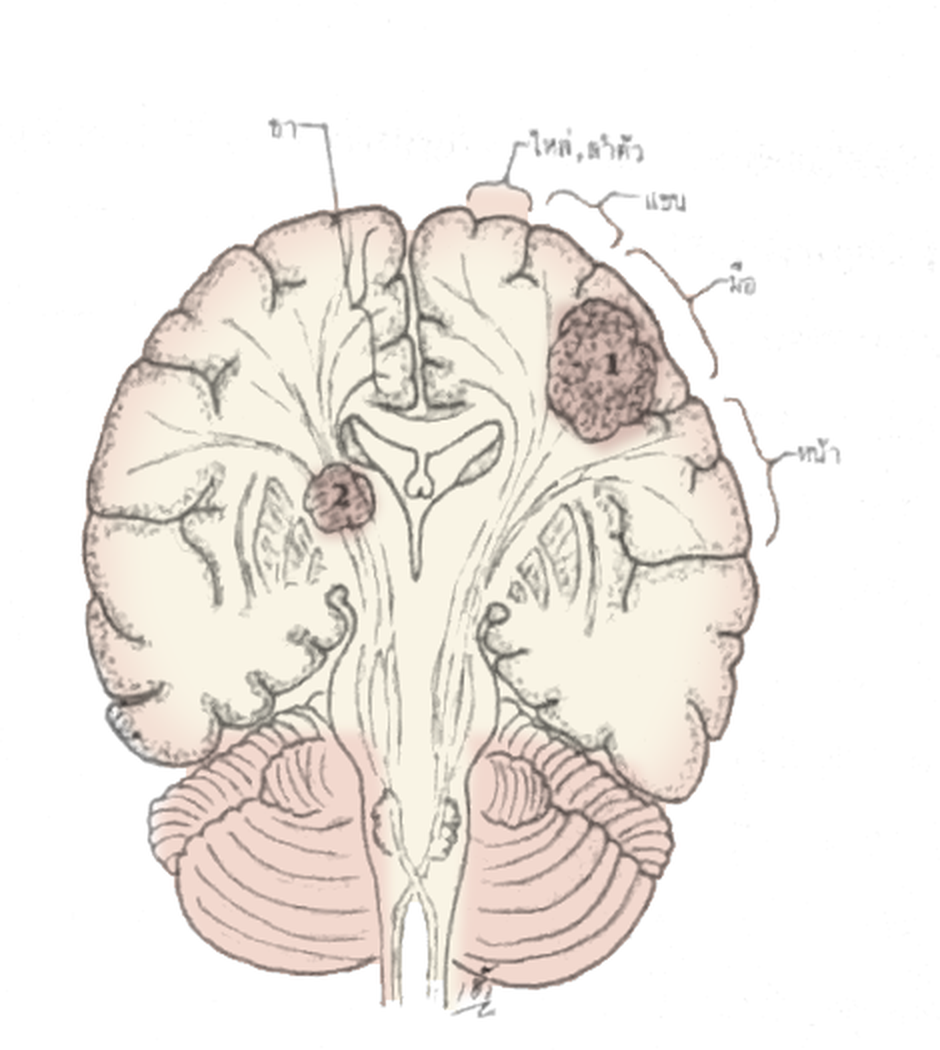
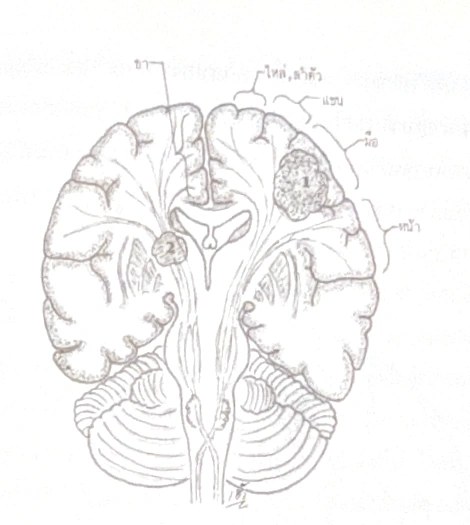 Color added while retaining the original linework and lettering
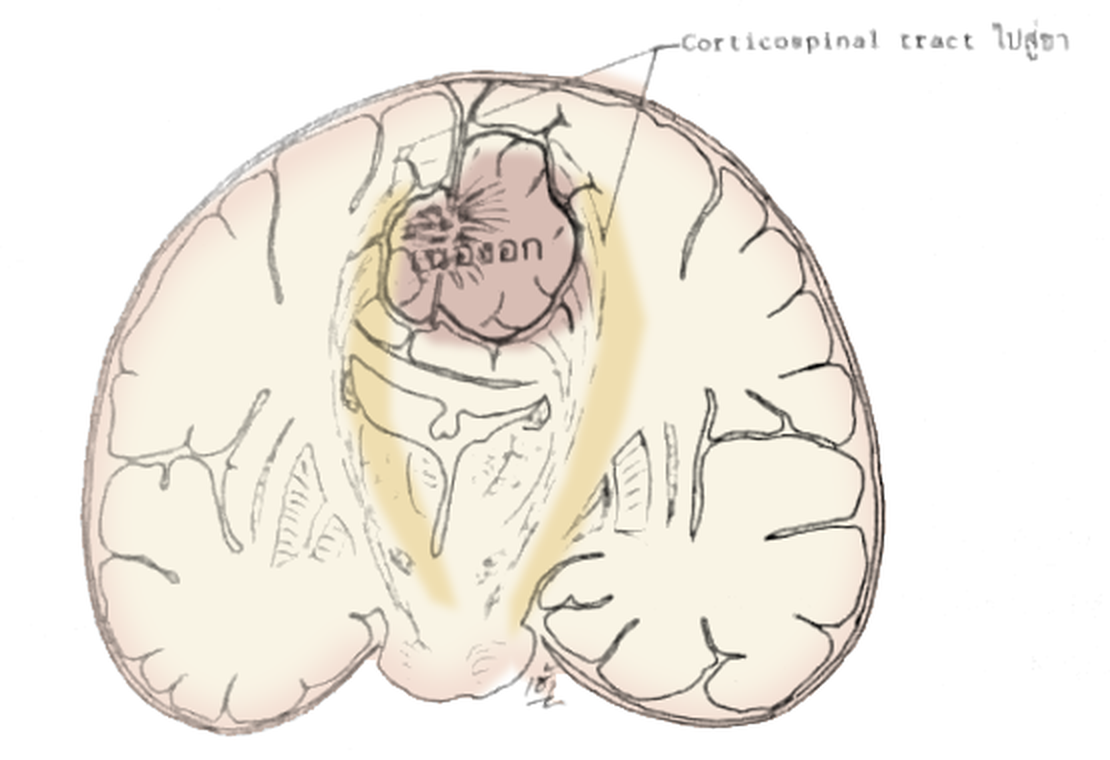
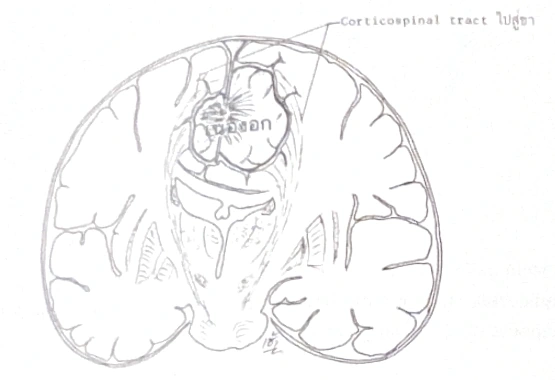 Color added while retaining the original linework and lettering
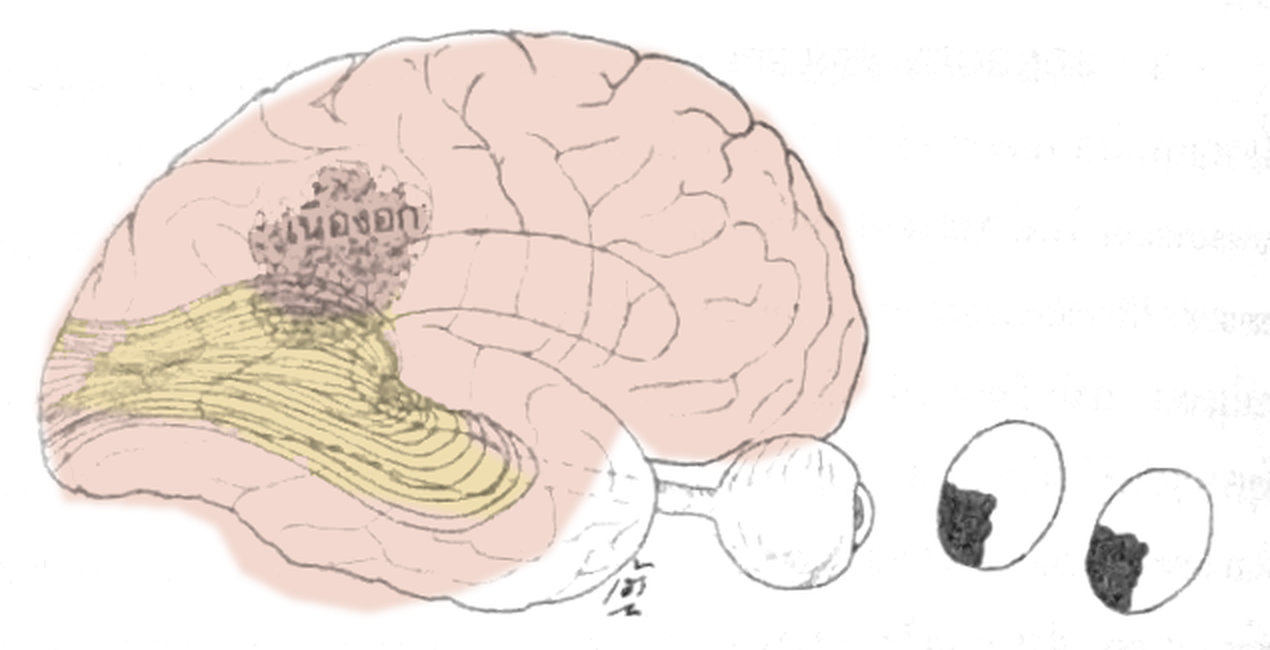
 Color added while retaining the original linework and lettering
 Color added while retaining the original linework and lettering
 Color added while retaining the original linework and lettering
 Color added while retaining the original linework and lettering
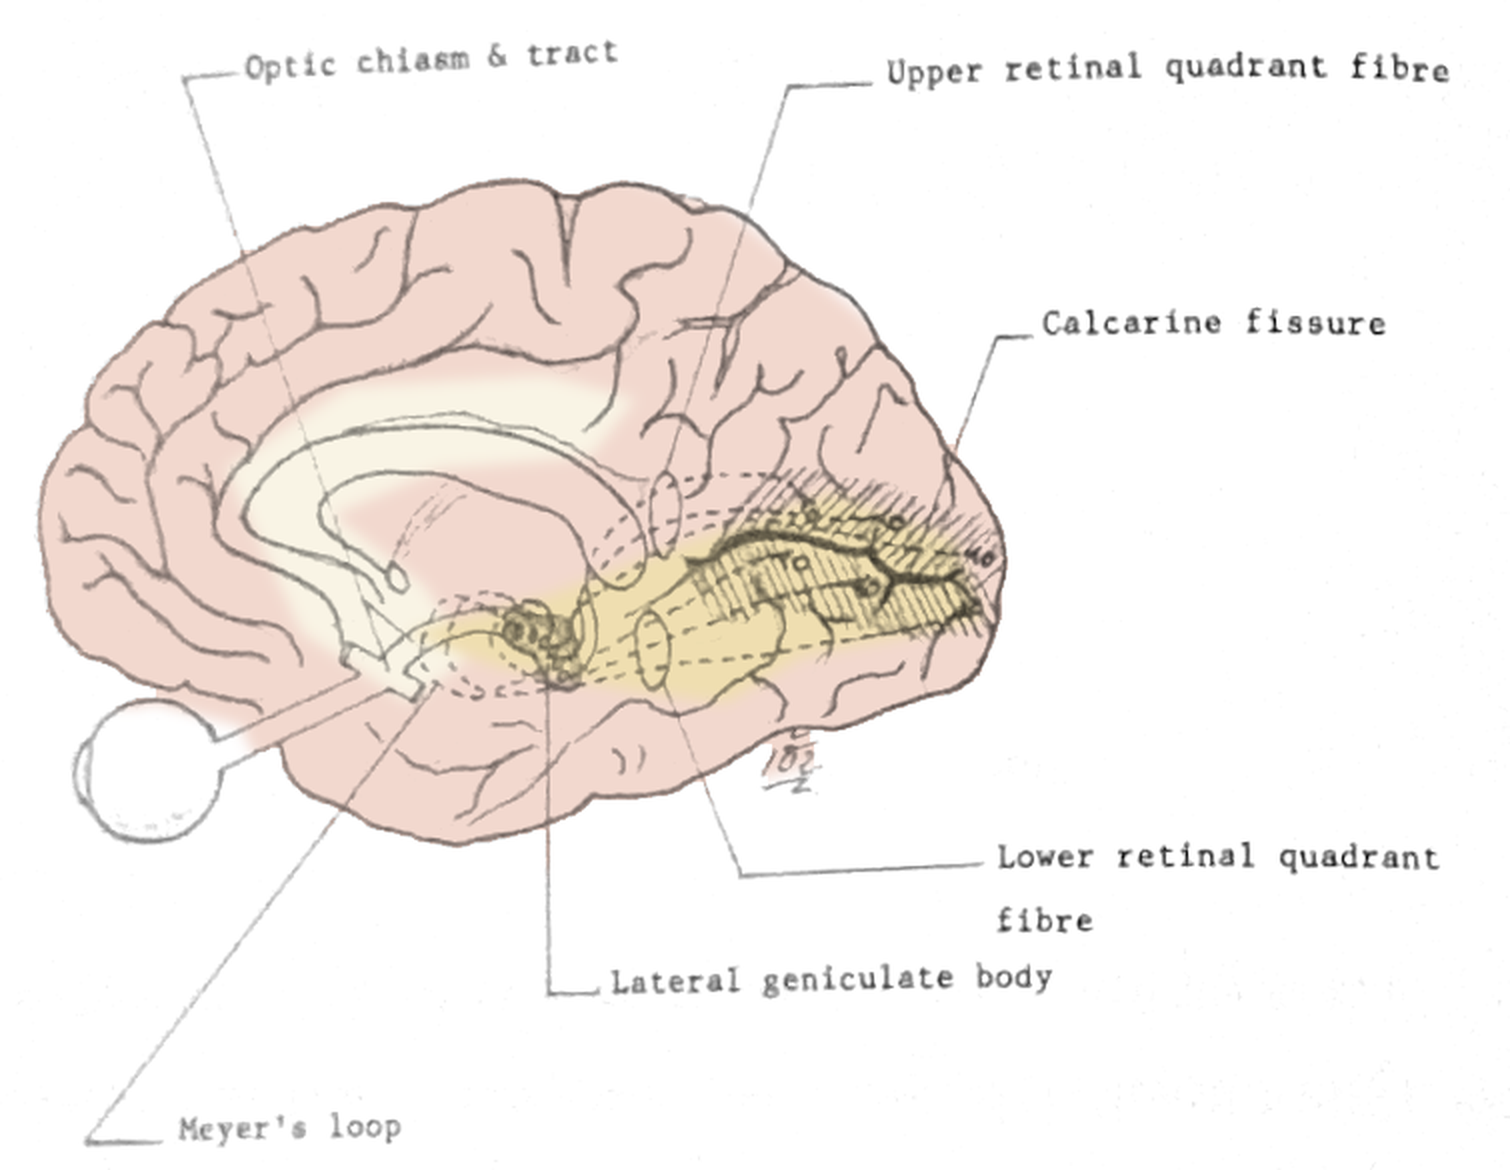
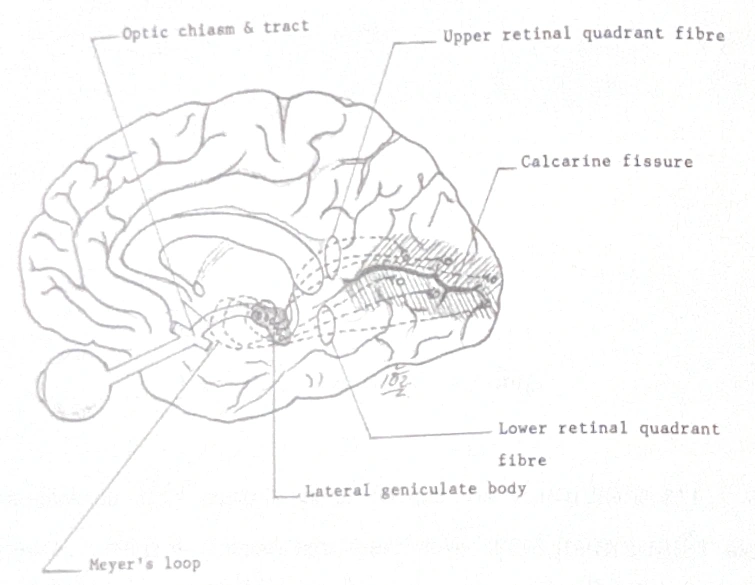 Color added while retaining the original linework and lettering
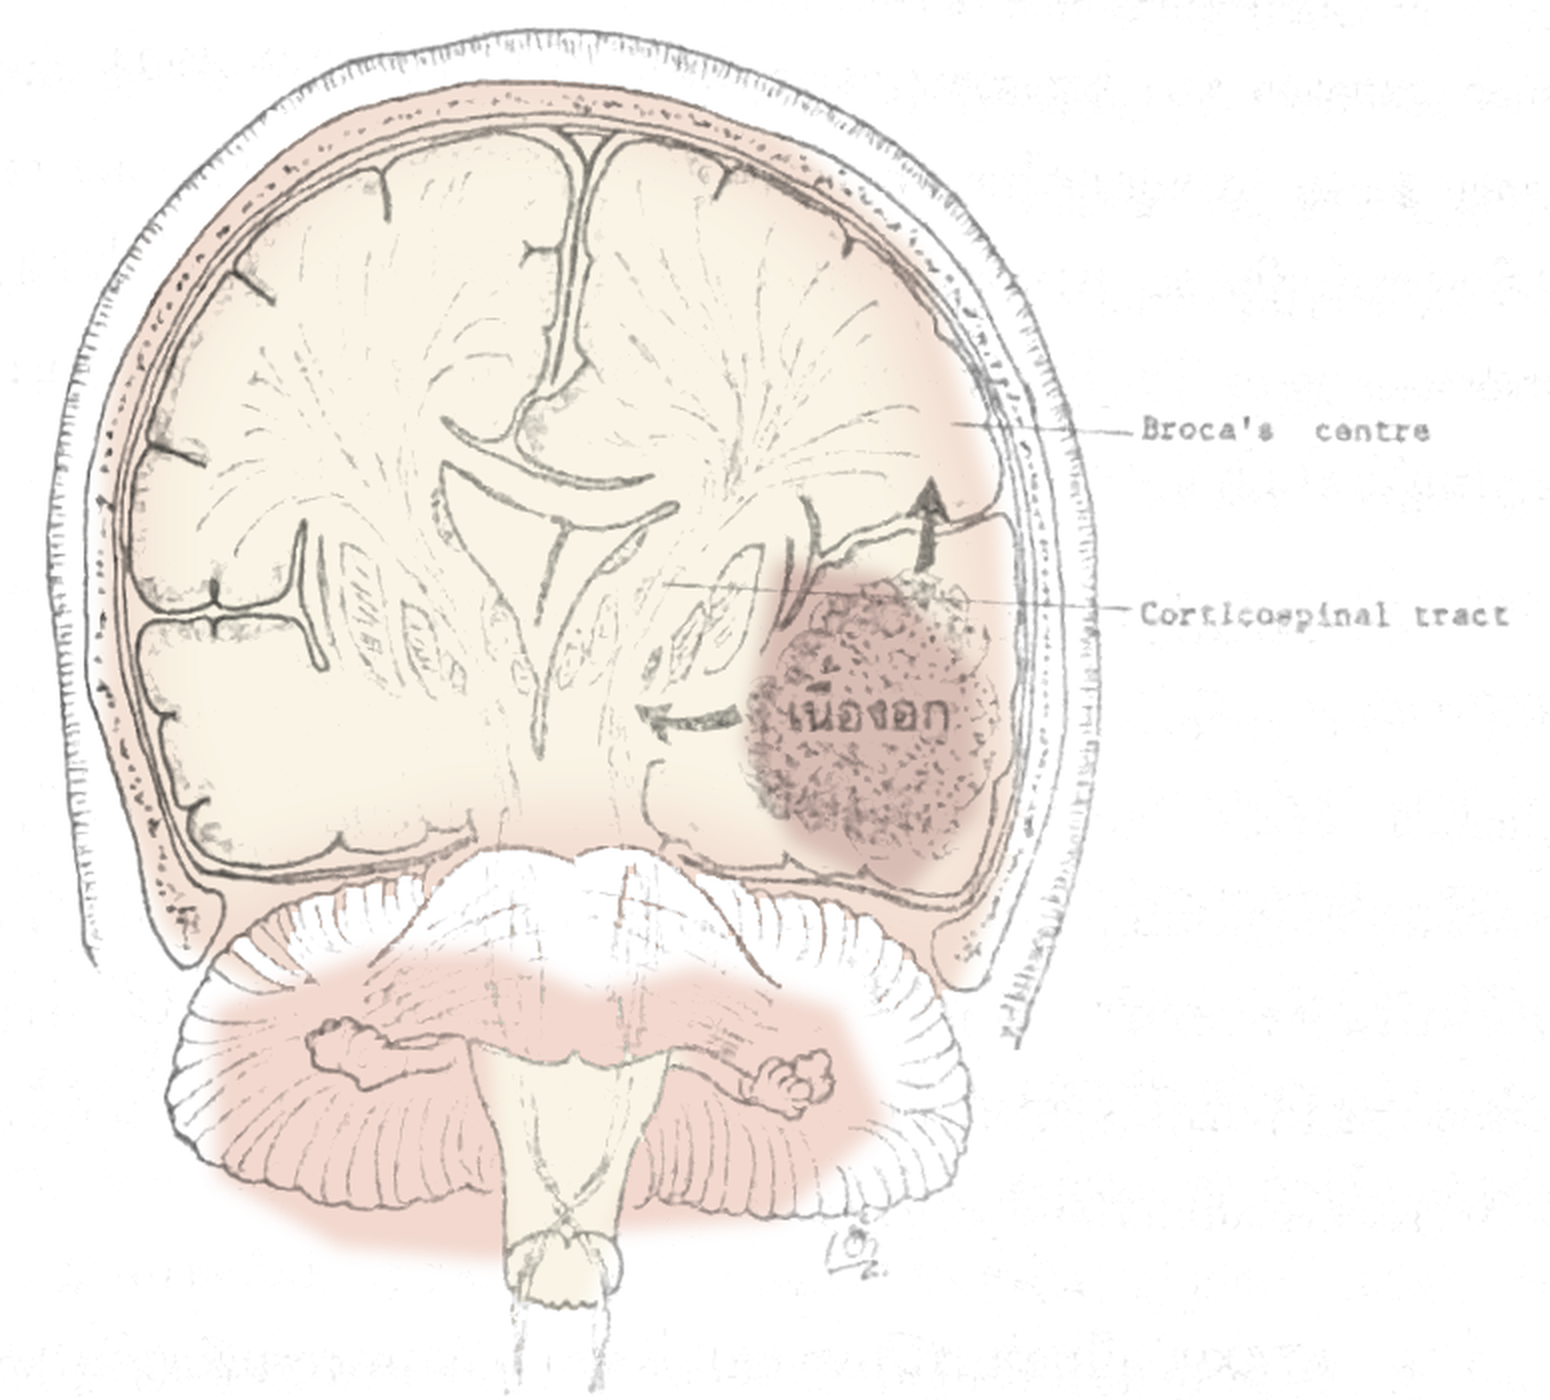
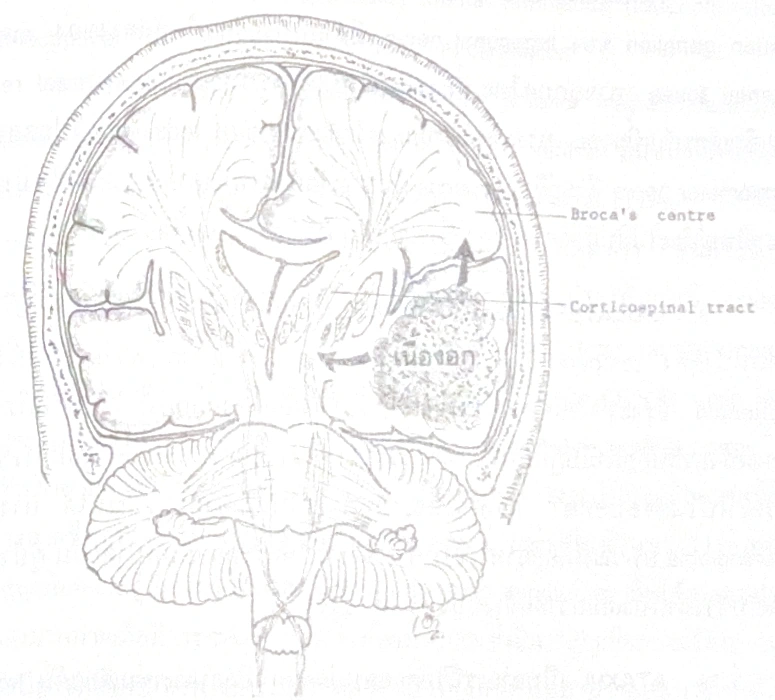 Color added while retaining the original linework and lettering
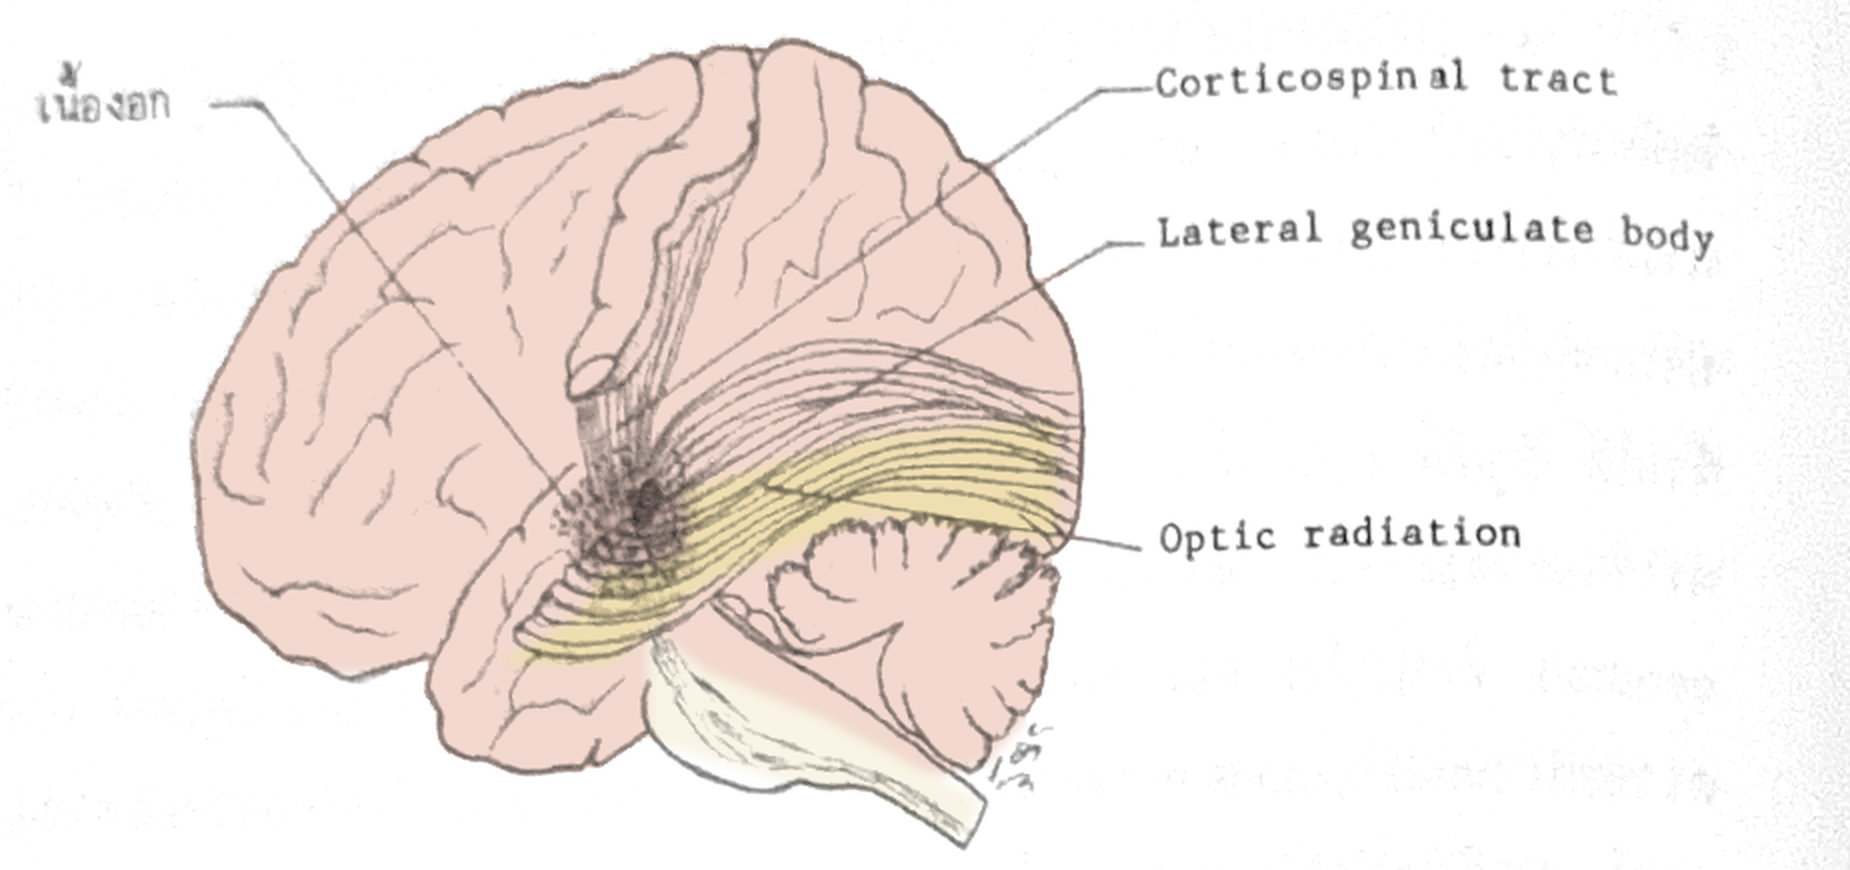
 Color added while retaining the original linework and lettering
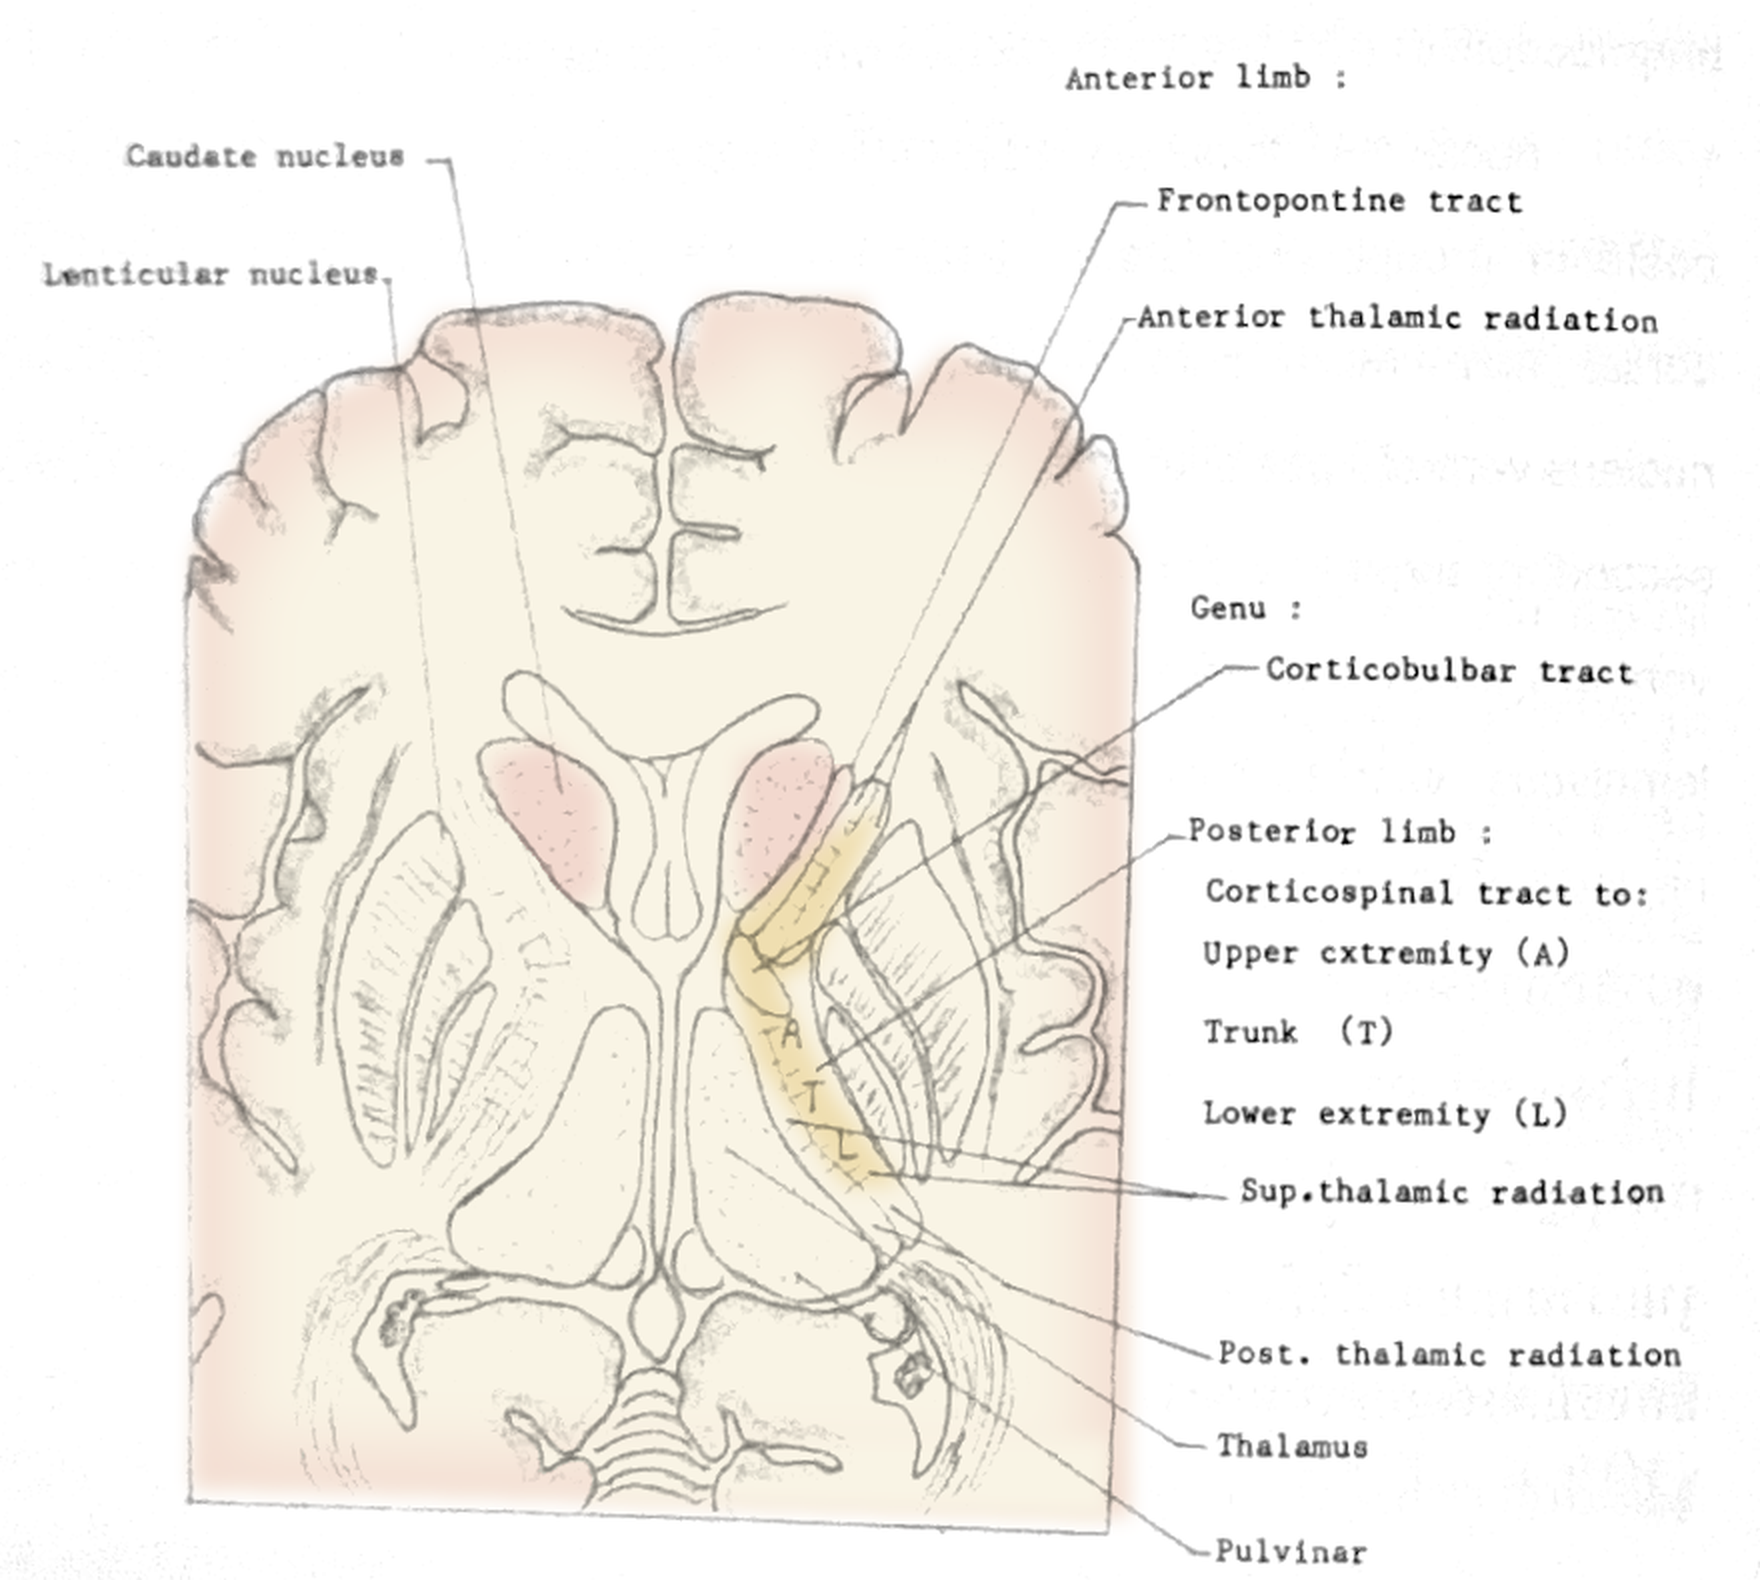
 Color added while retaining the original linework and lettering
 Color added while retaining the original linework and lettering
 Color added while retaining the original linework and lettering
 Color added while retaining the original linework and lettering
 Color added while retaining the original linework and lettering
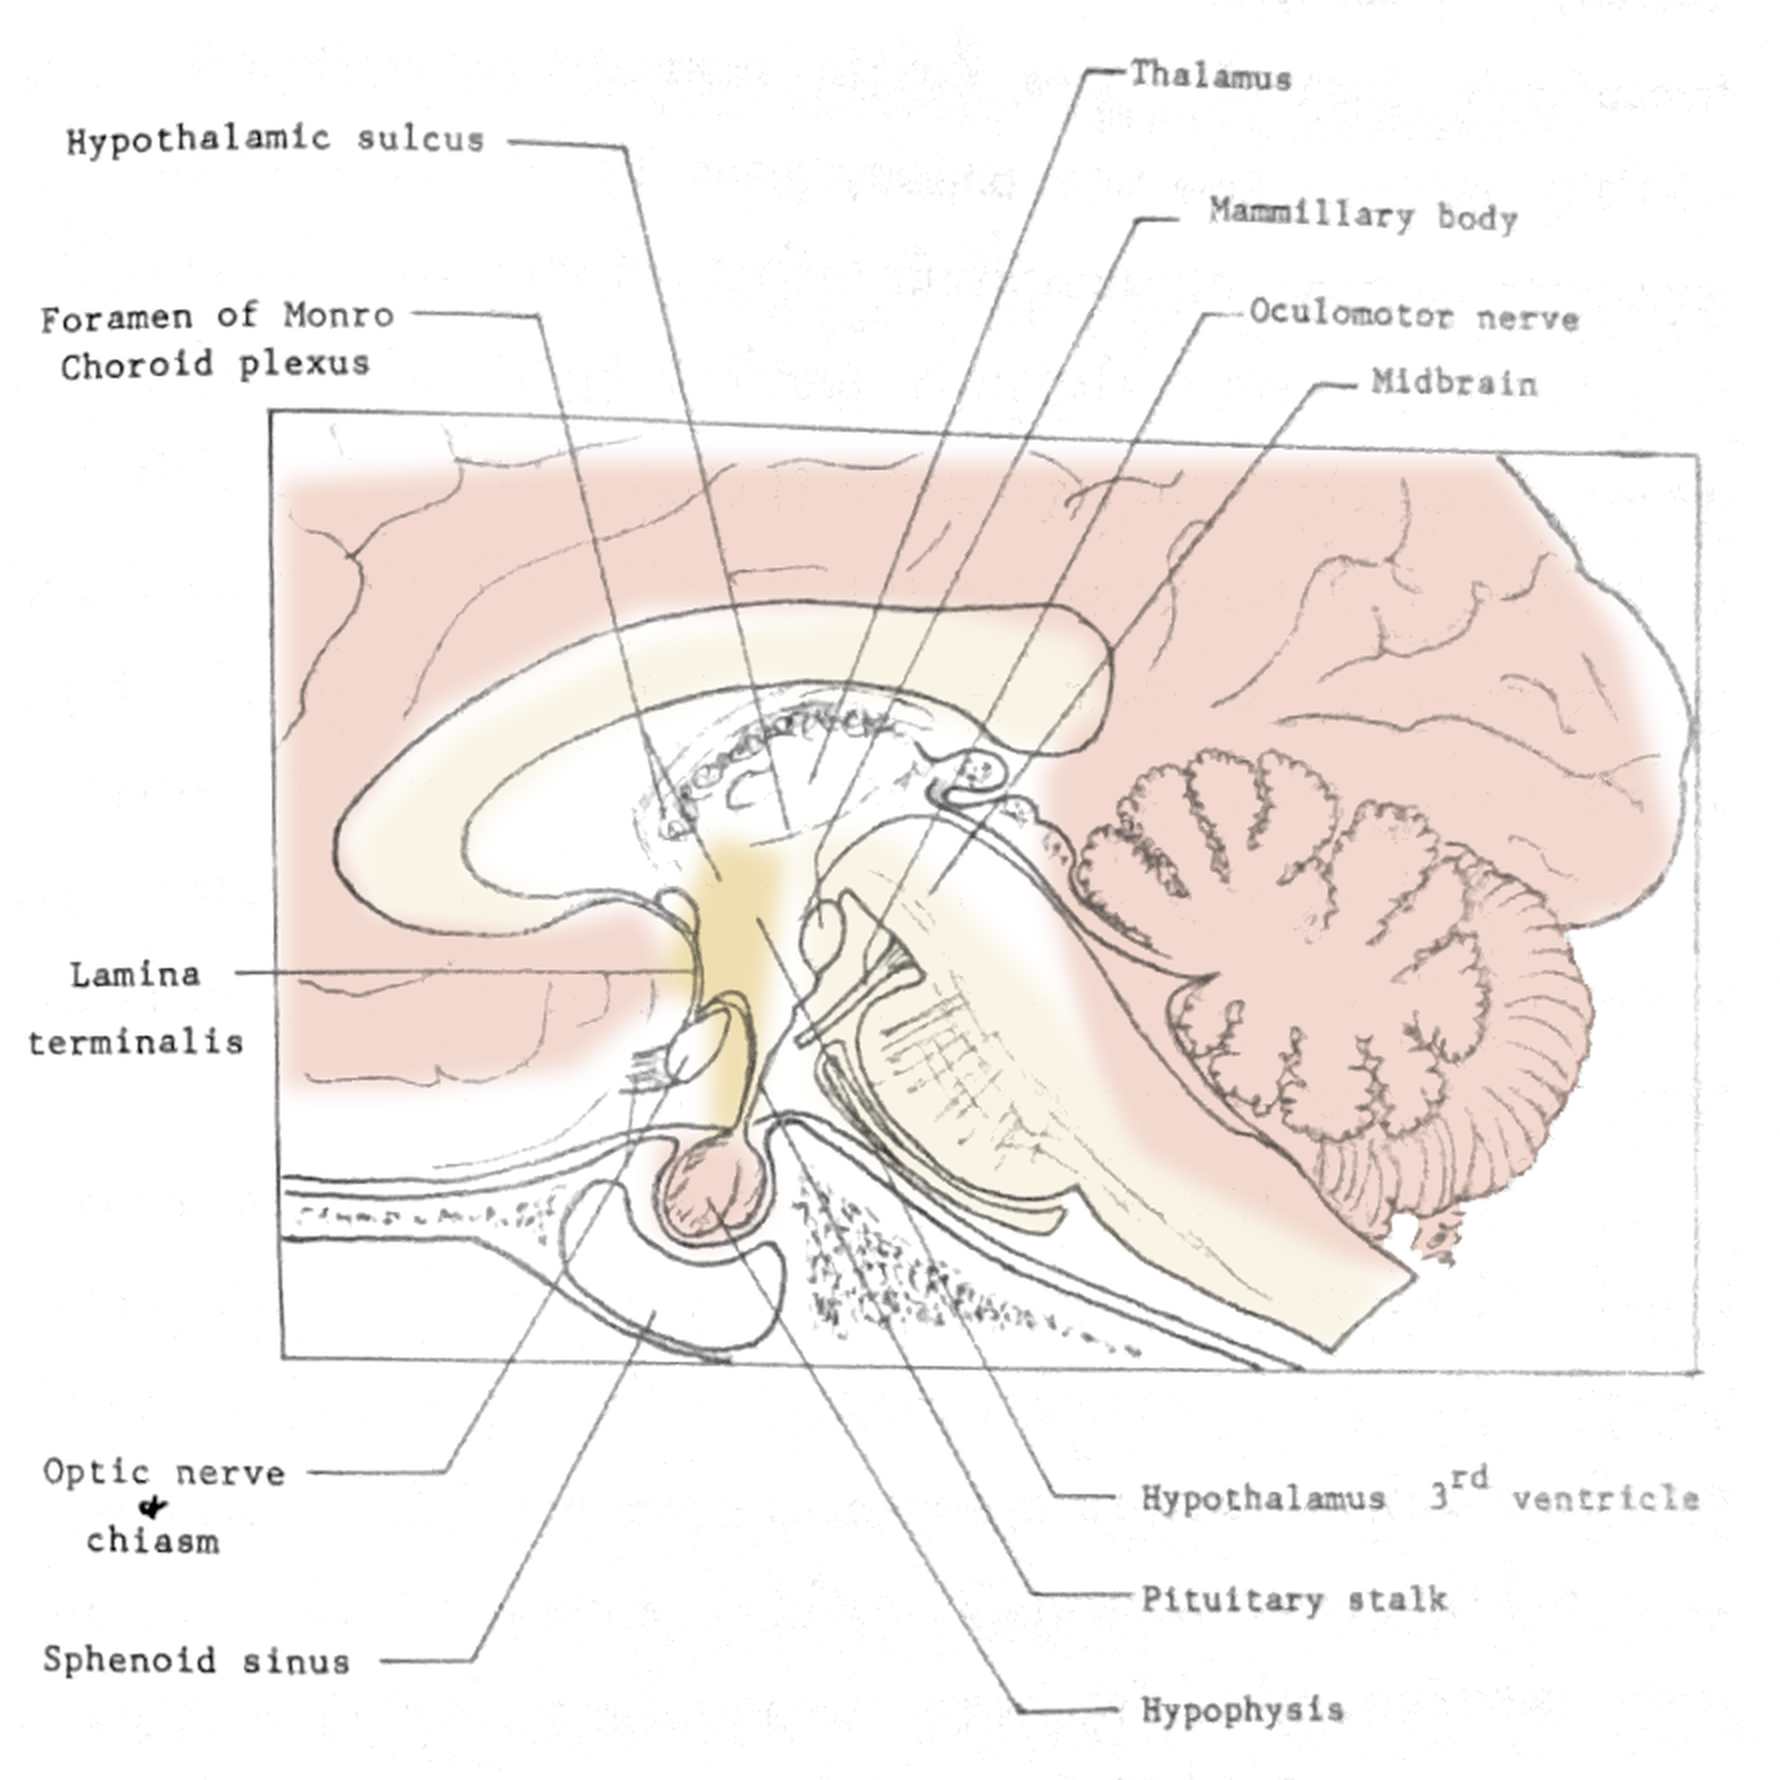
 Color added while retaining the original linework and lettering
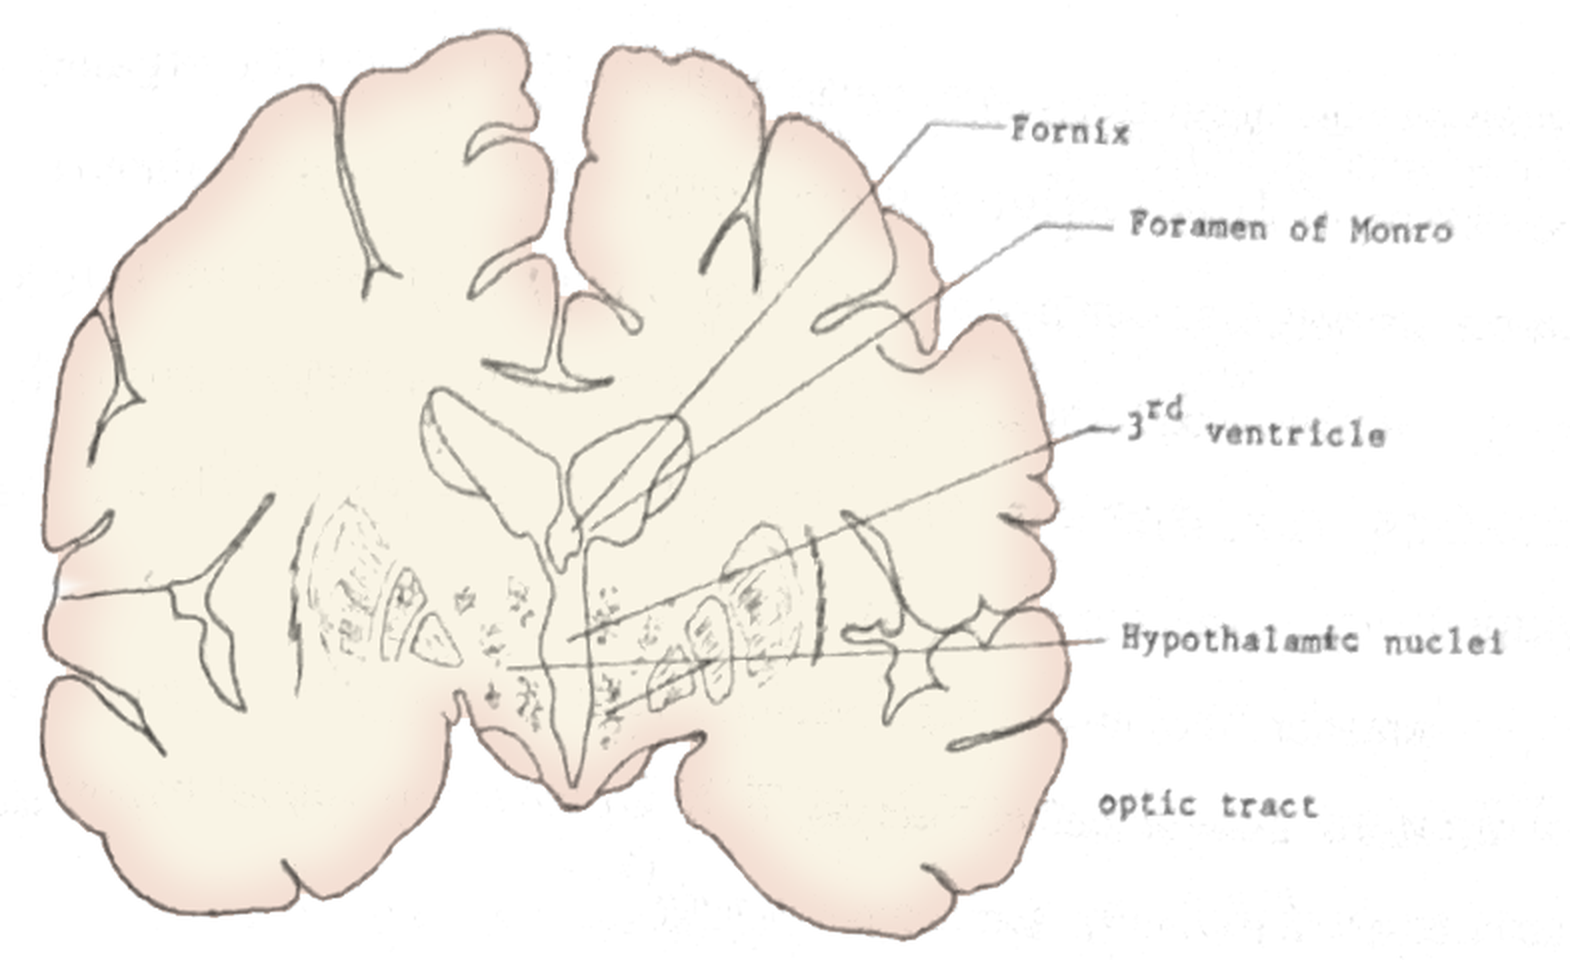
 Color added while retaining the original linework and lettering
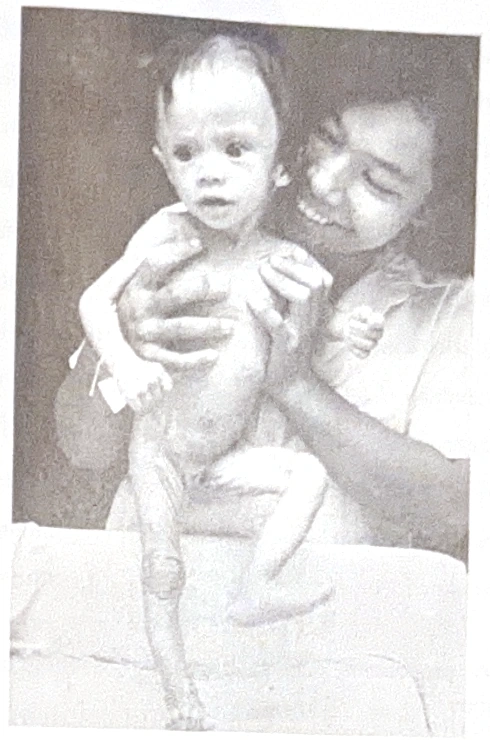
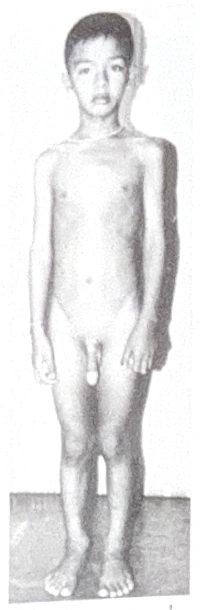
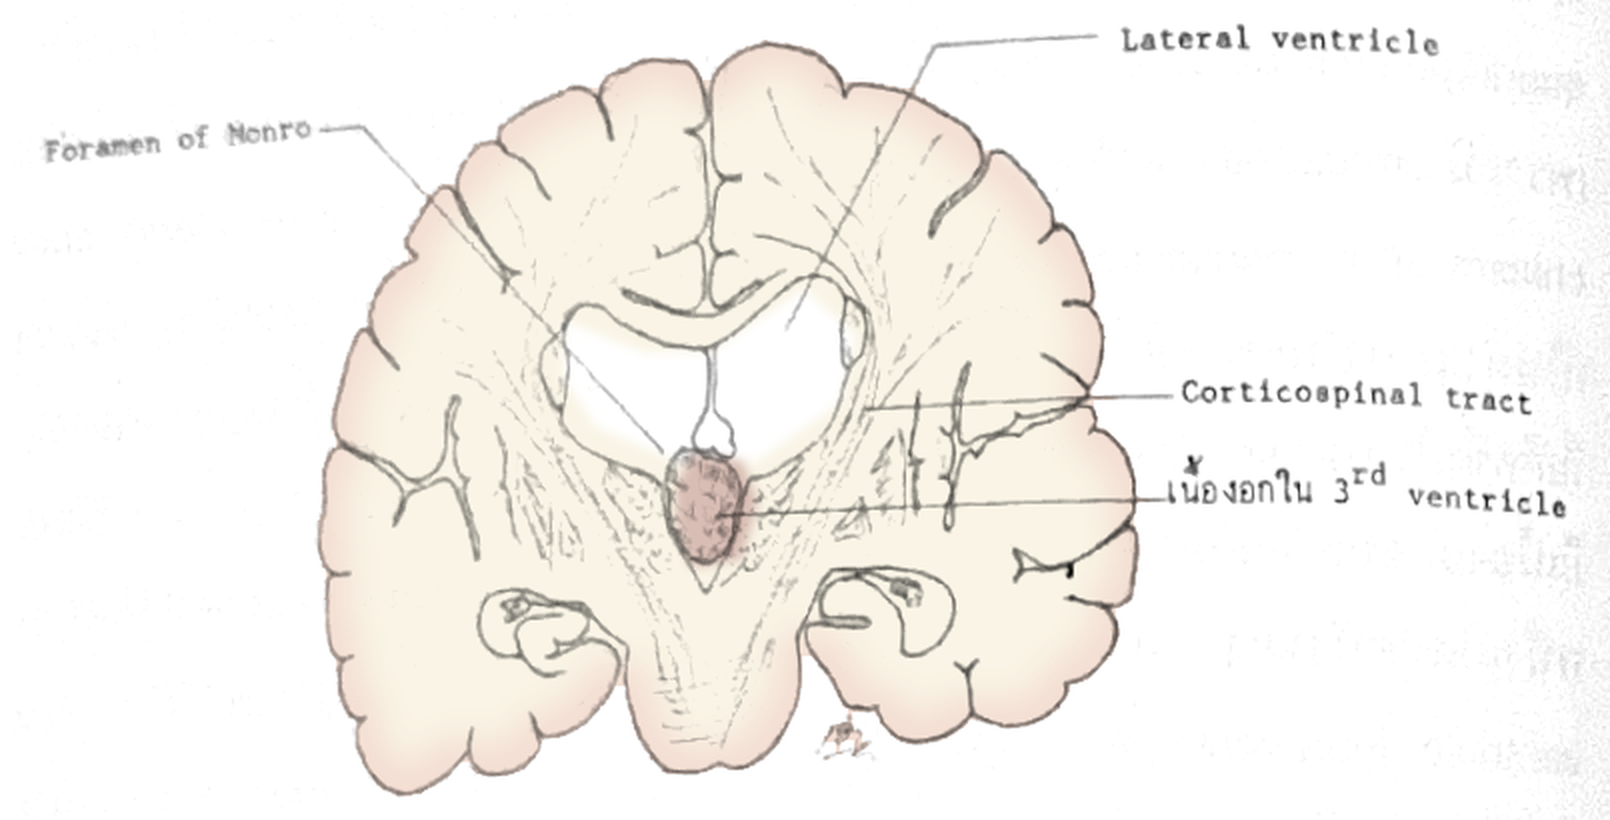
 Color added while retaining the original linework and lettering
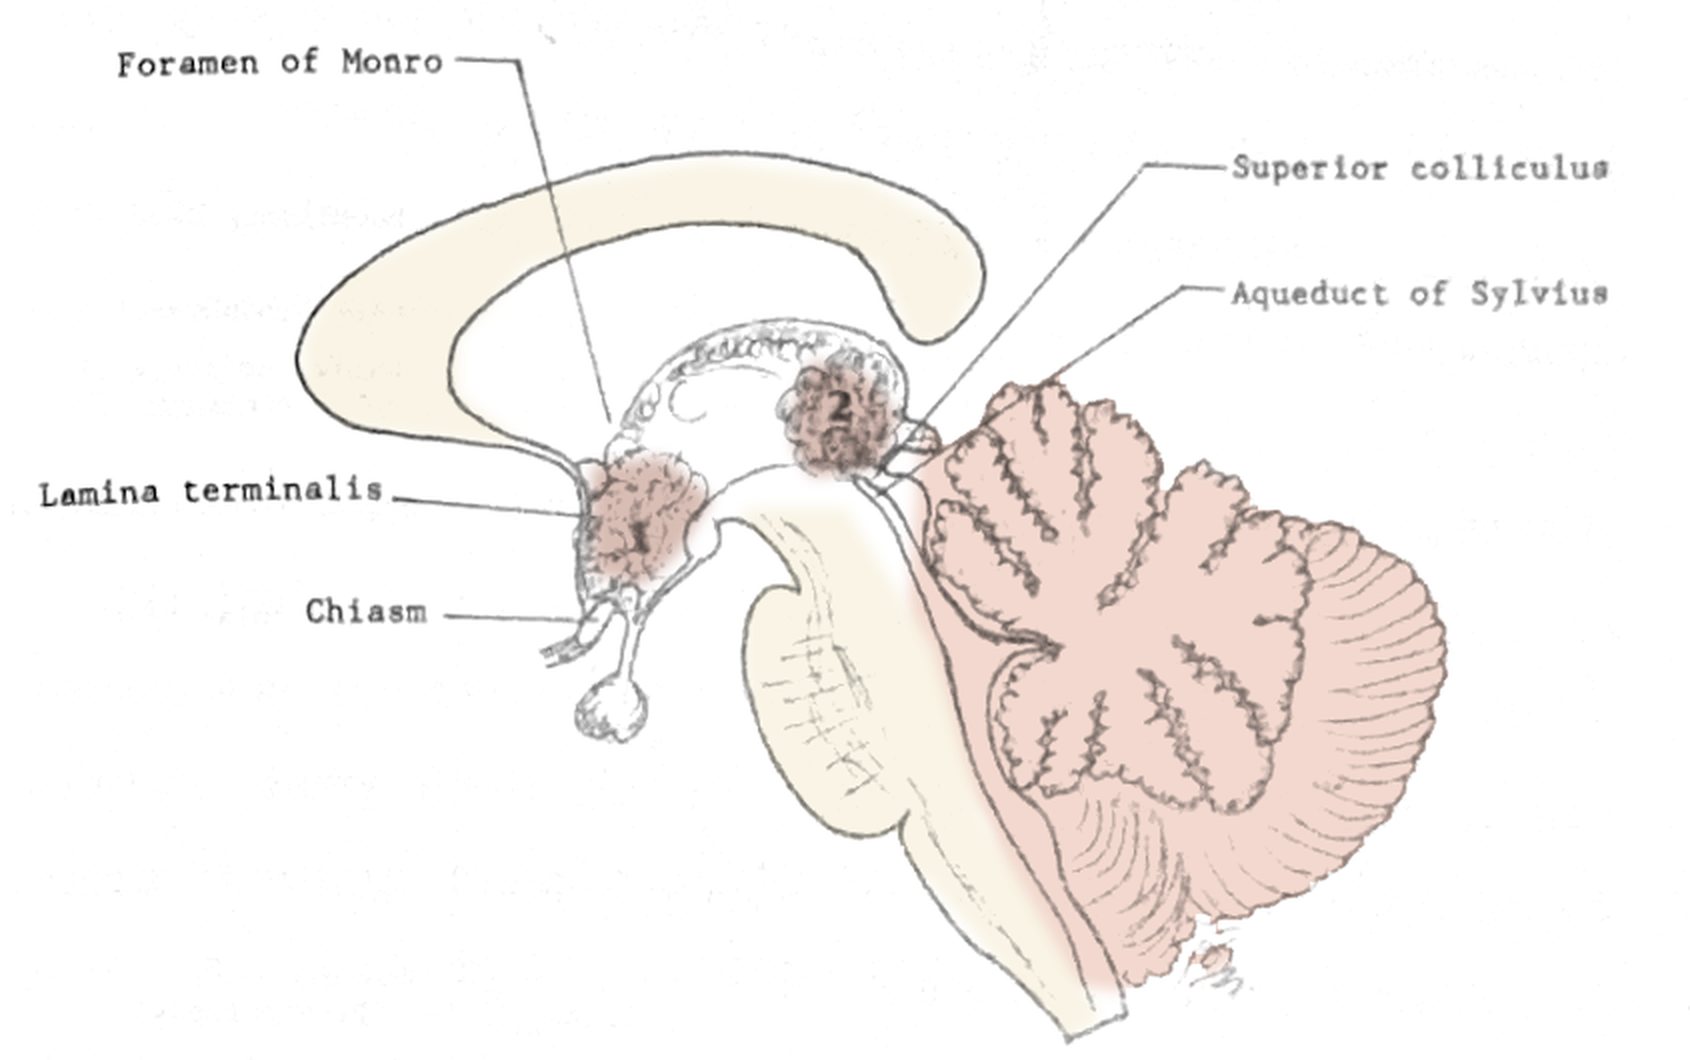
 Color added while retaining the original linework and lettering
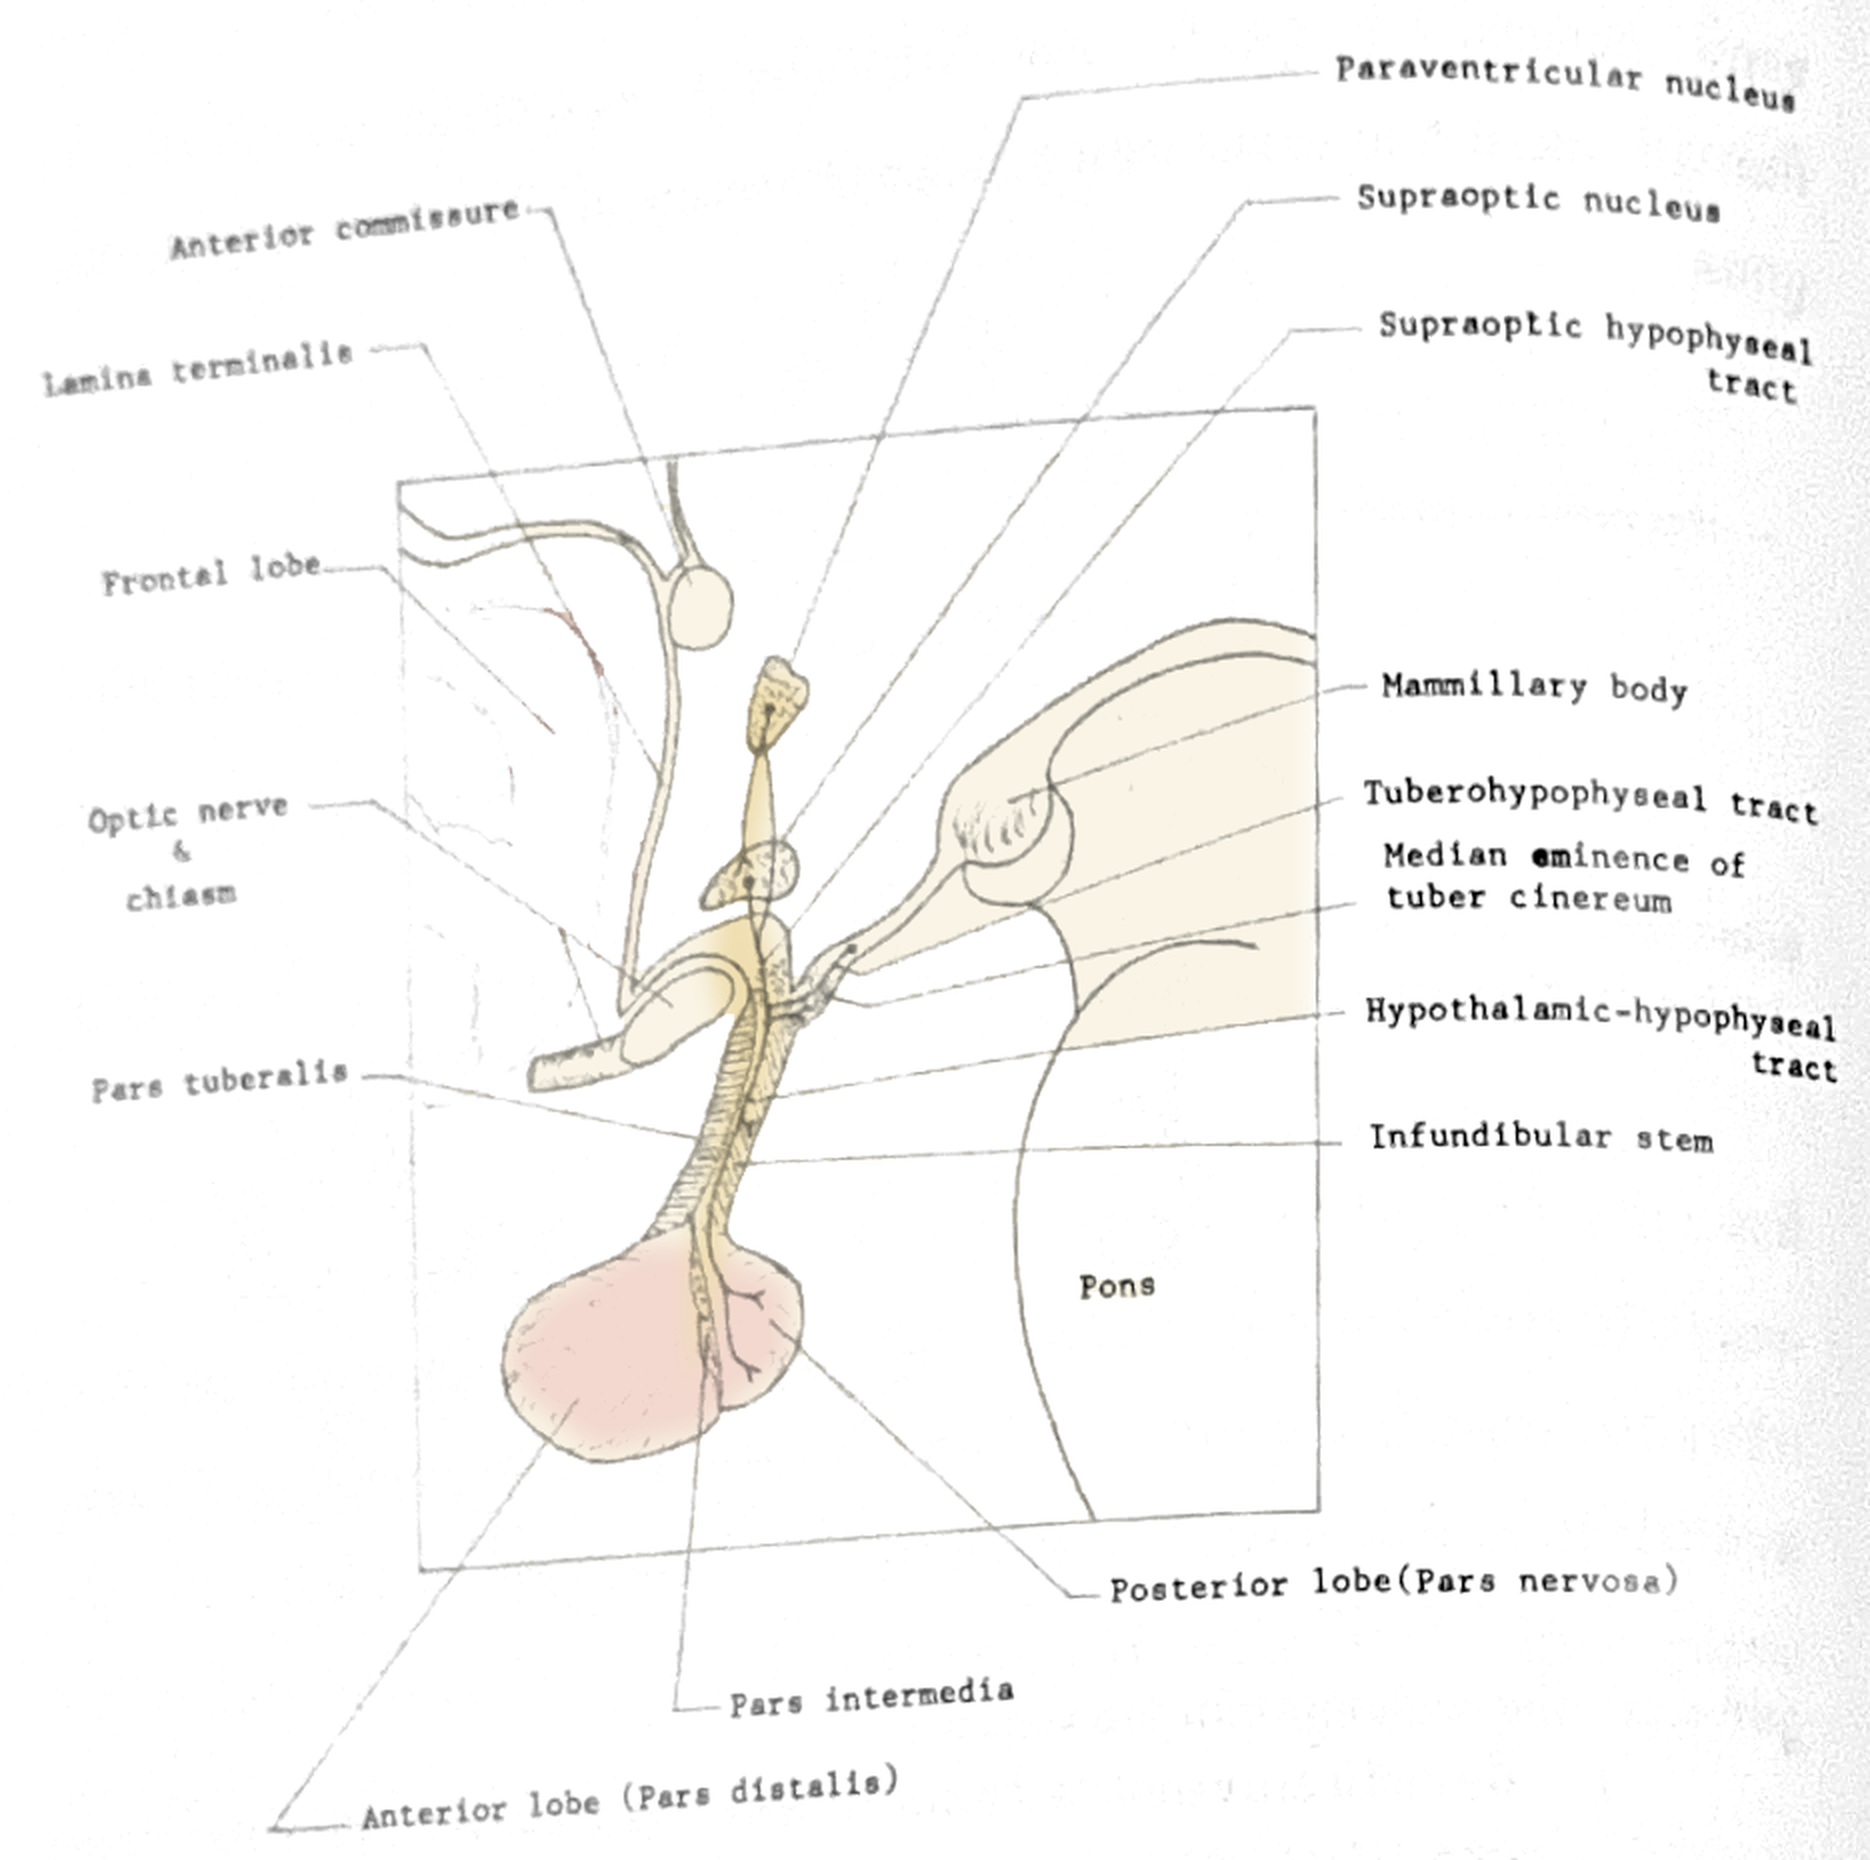
 Color added while retaining the original linework and lettering
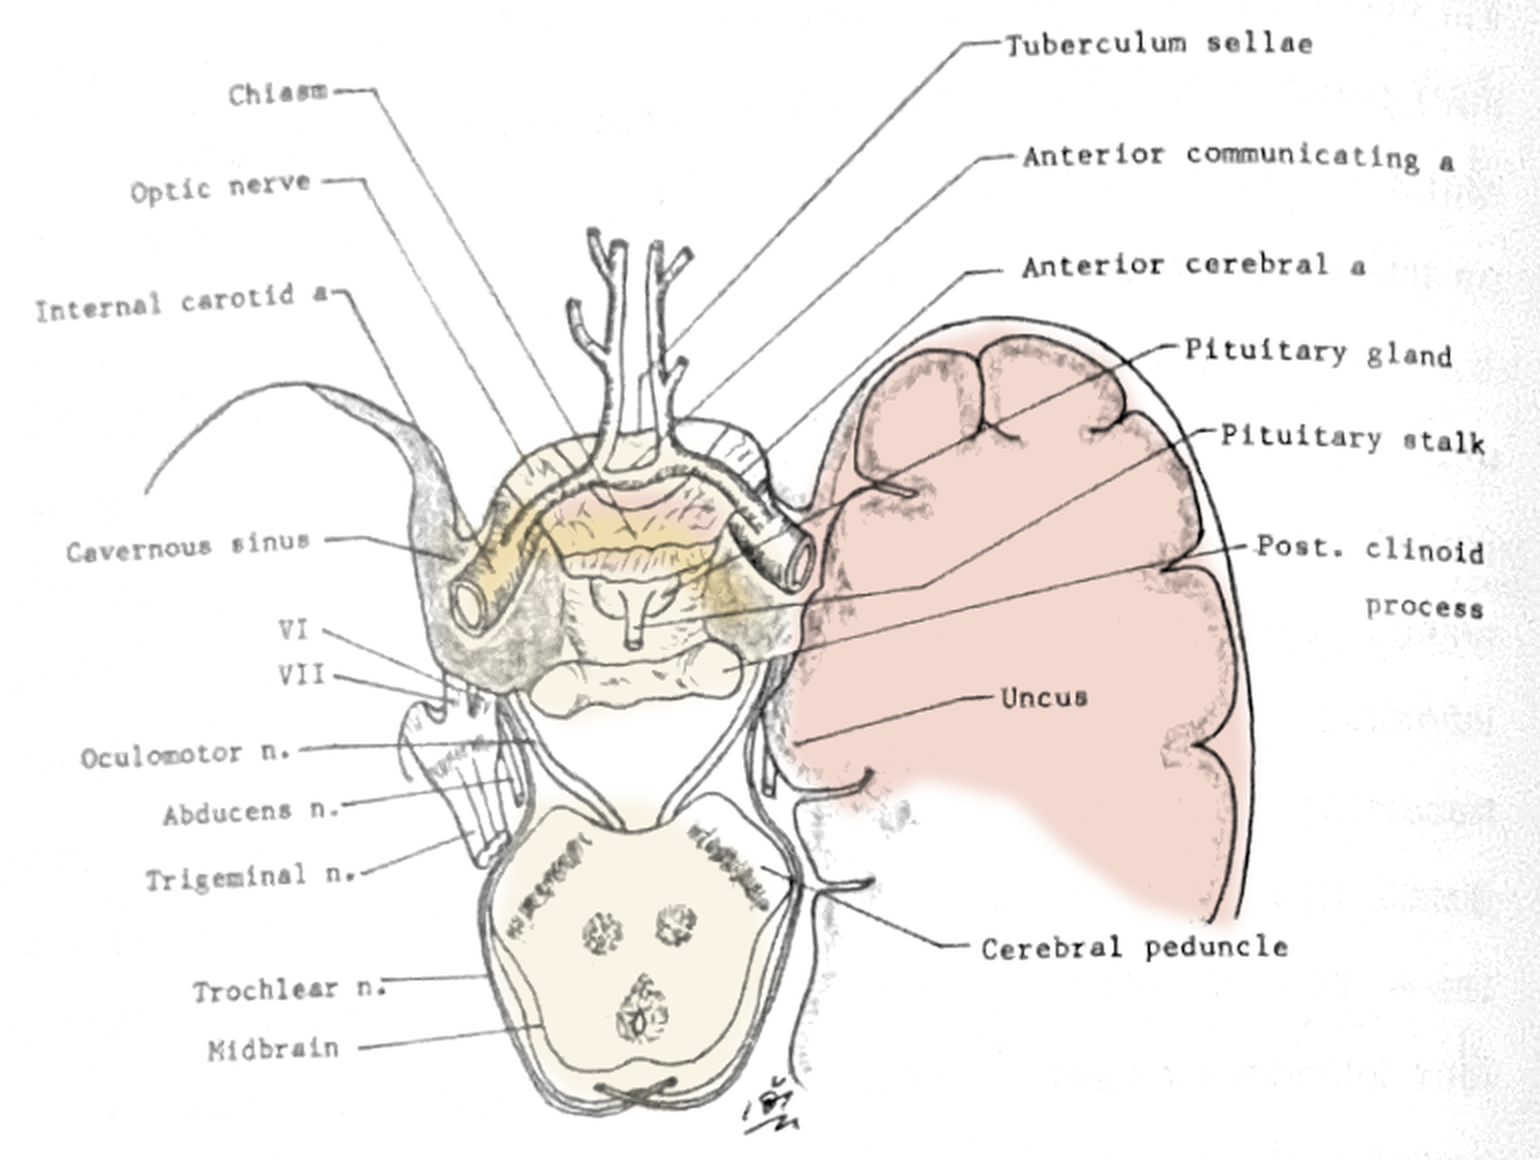
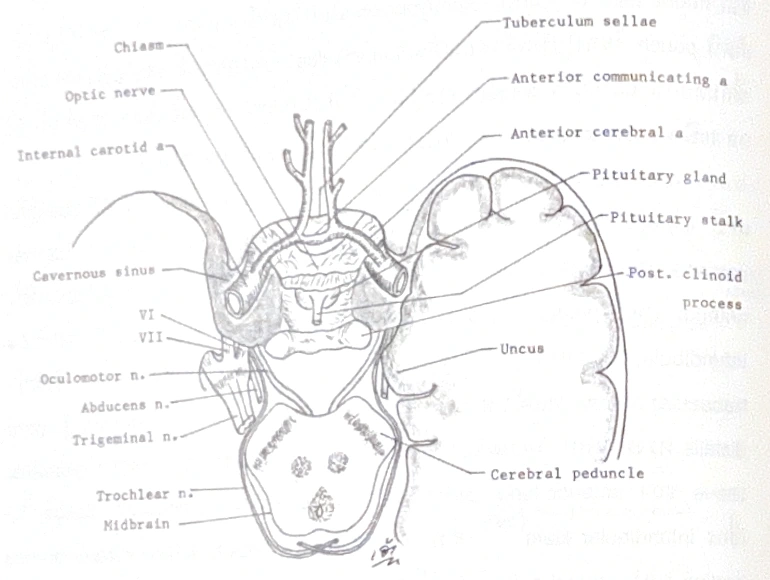 Color added while retaining the original linework and lettering
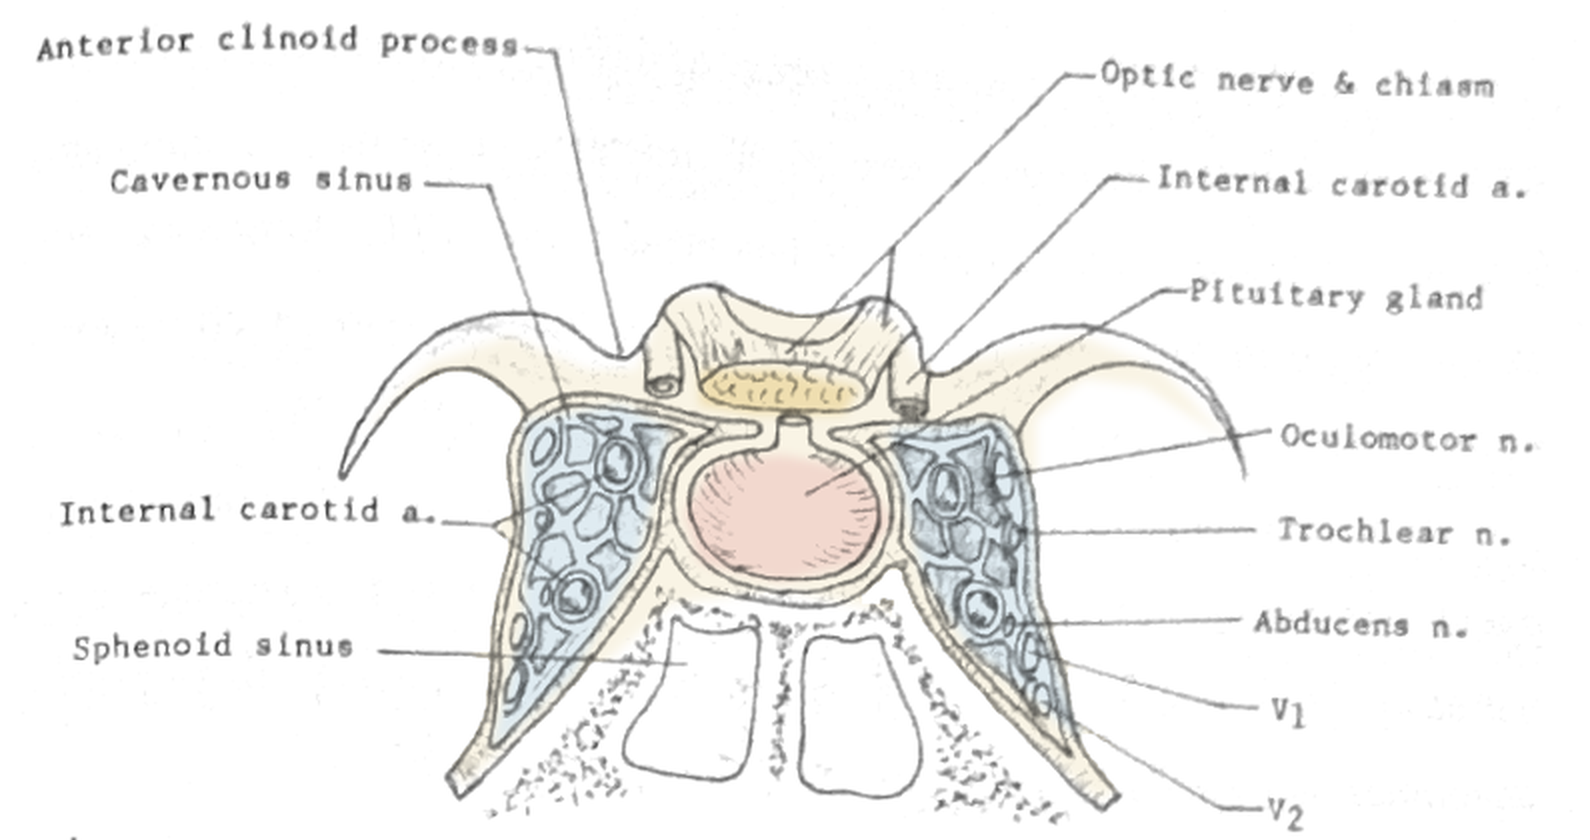
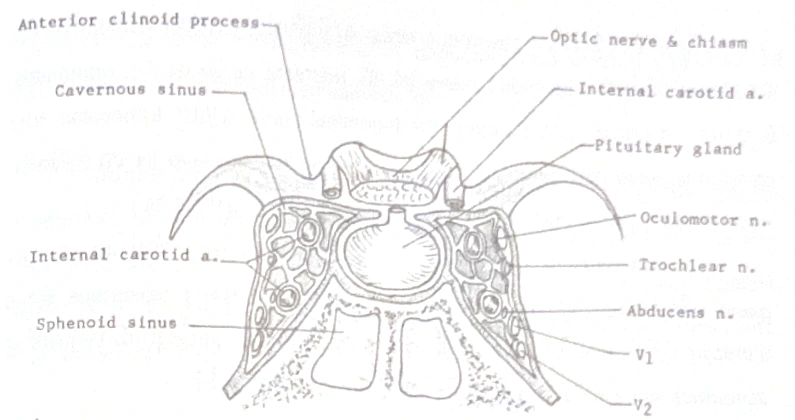 Color added while retaining the original linework and lettering
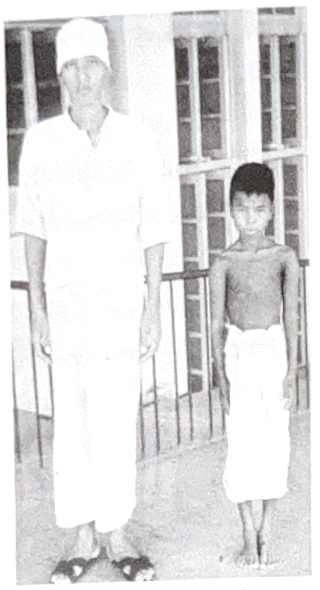
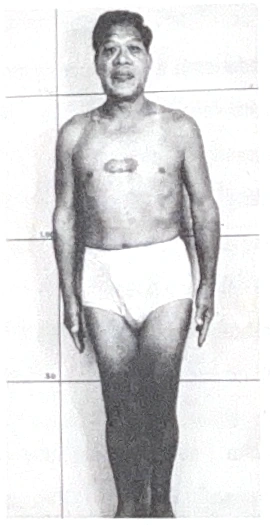
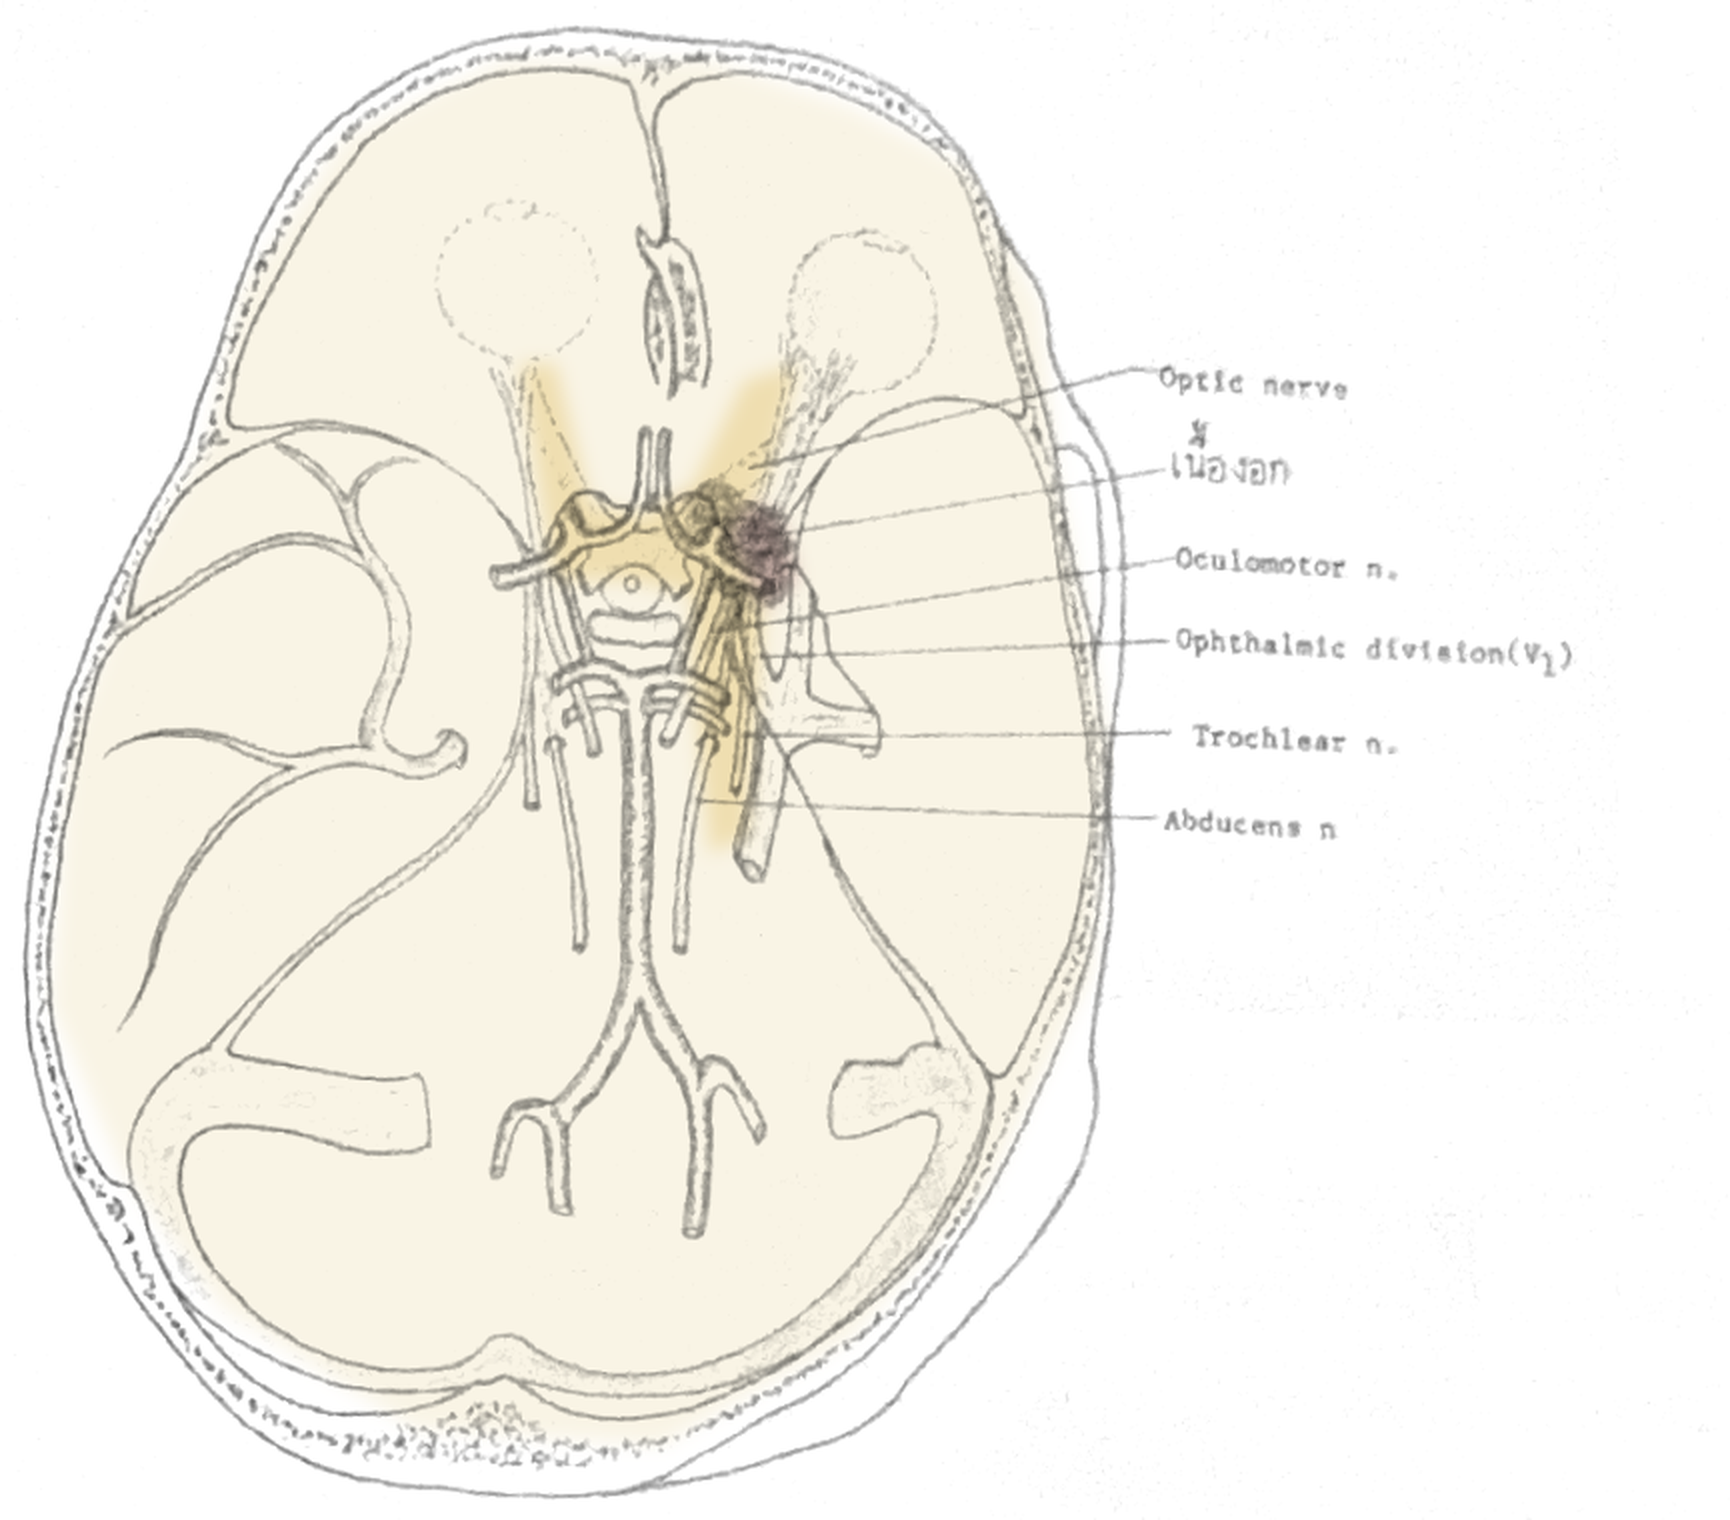
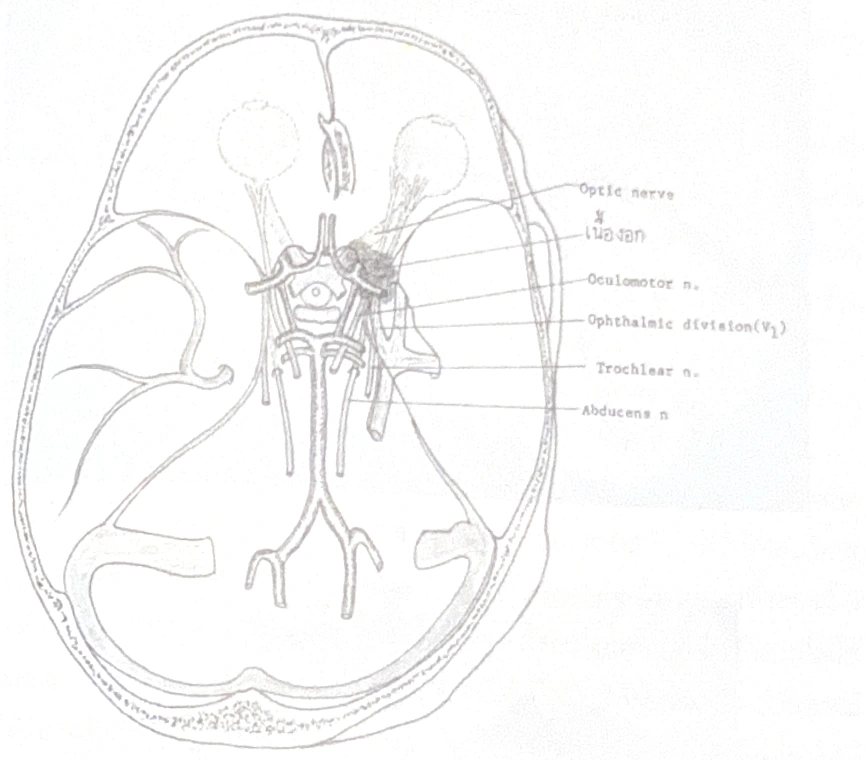 Color added while retaining the original linework and lettering
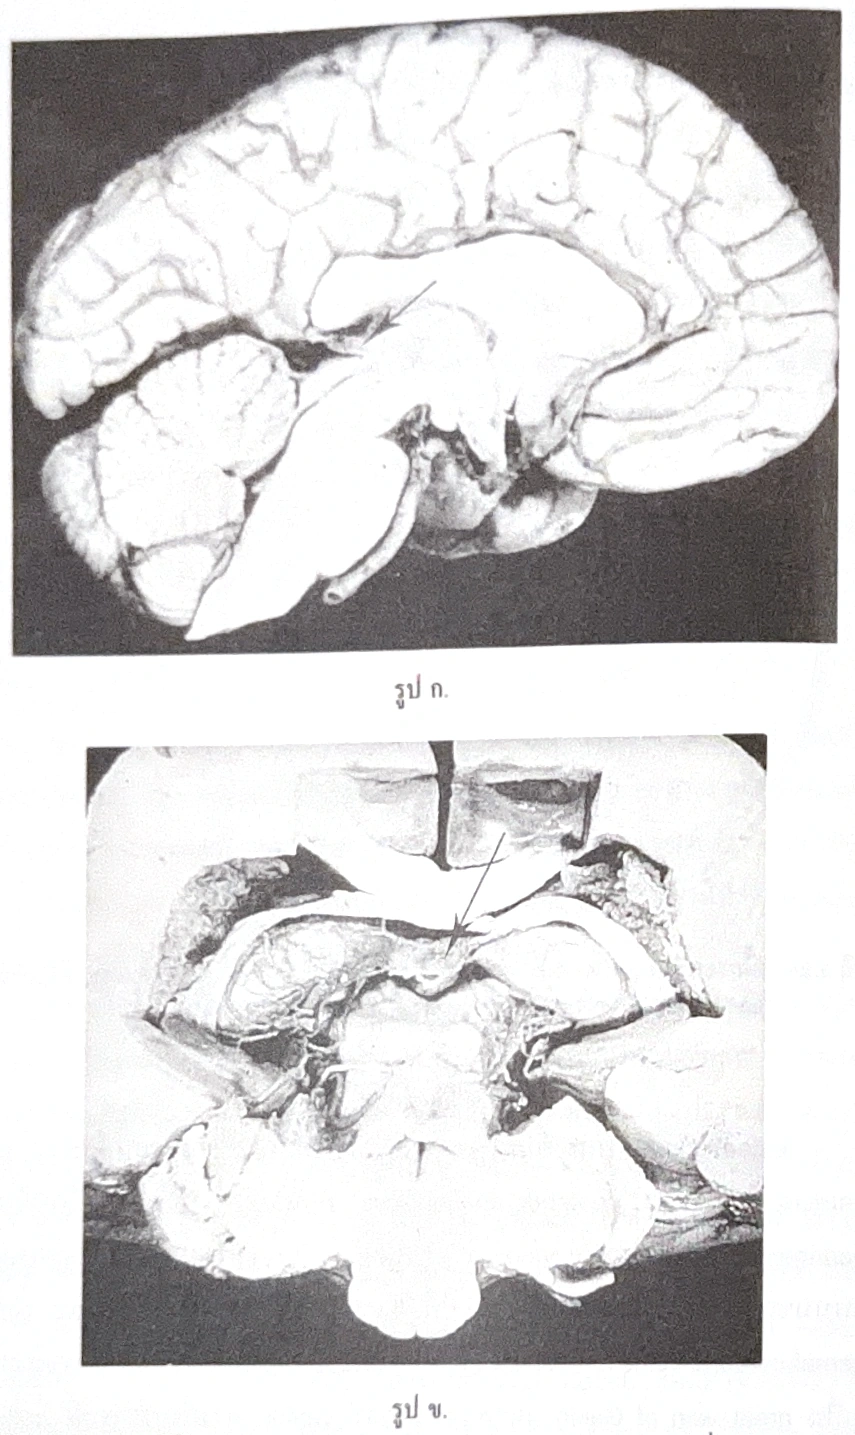
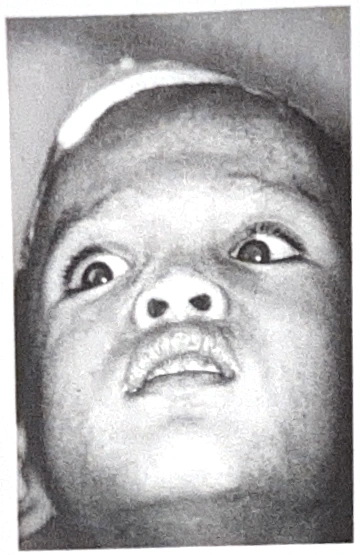
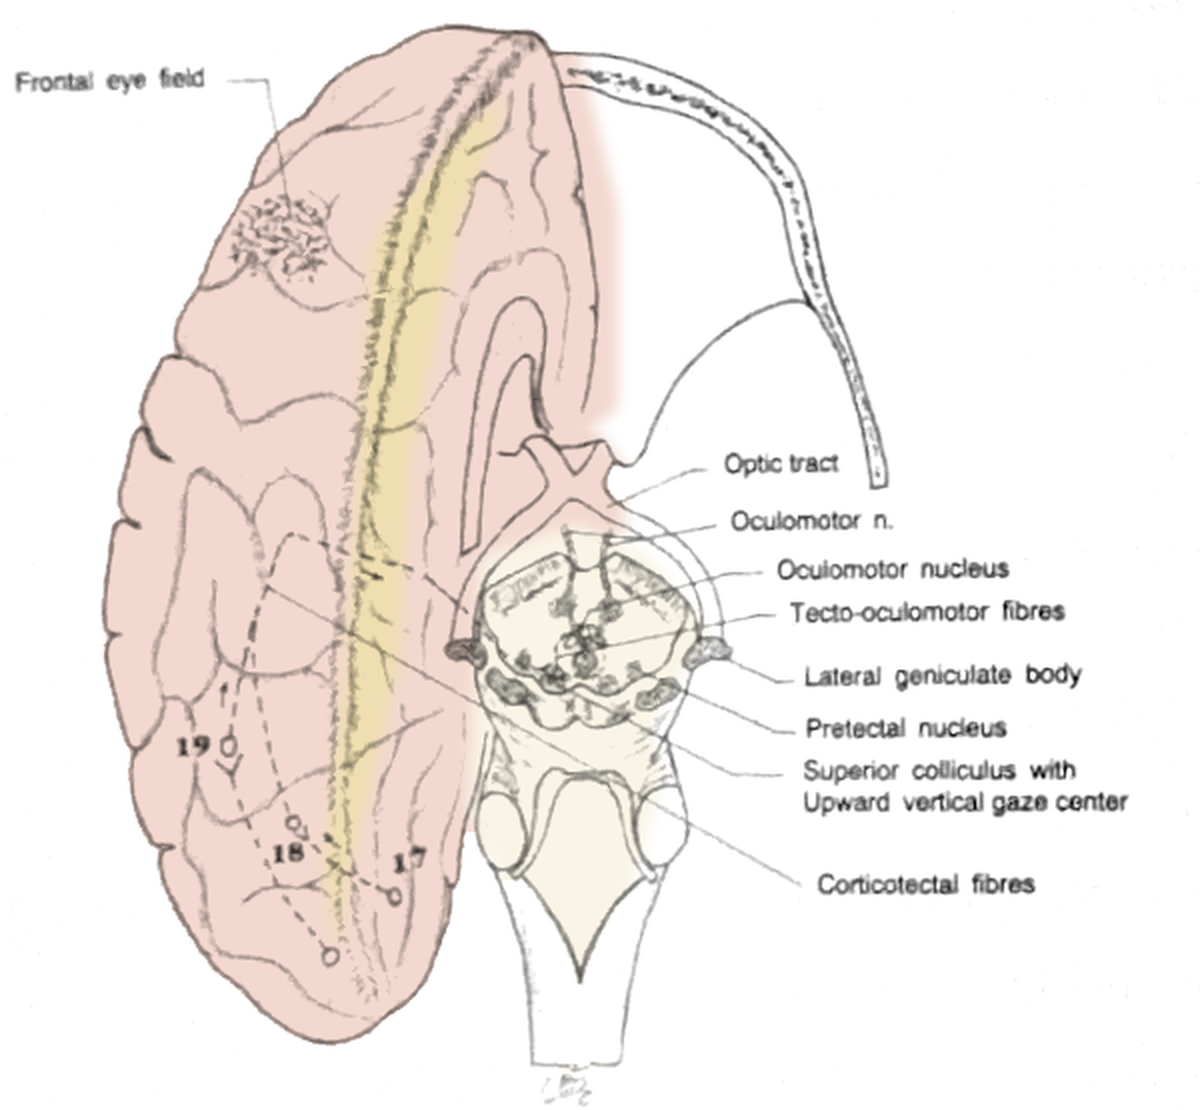
 Color added while retaining the original linework and lettering
 Color added while retaining the original linework and lettering
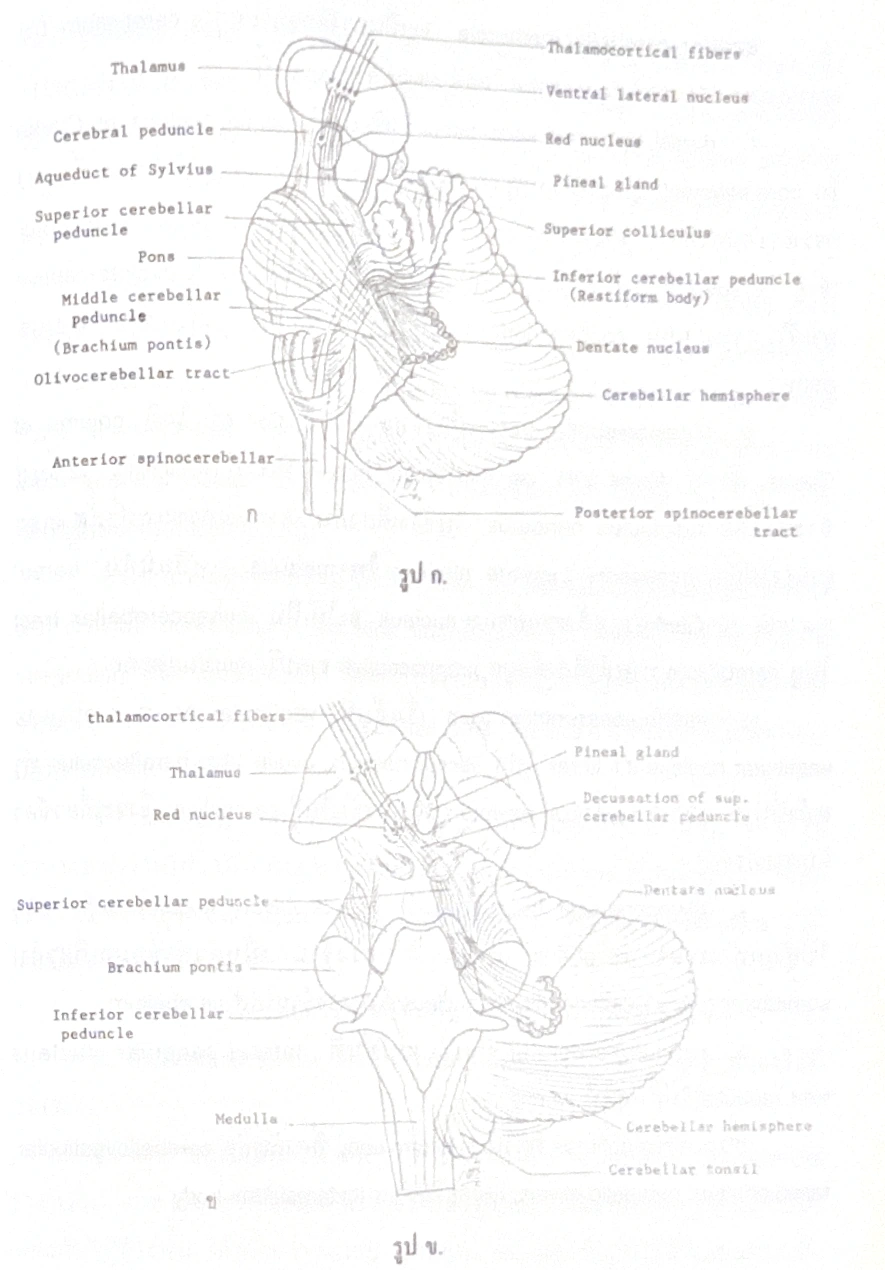 Color added while retaining the original linework and lettering
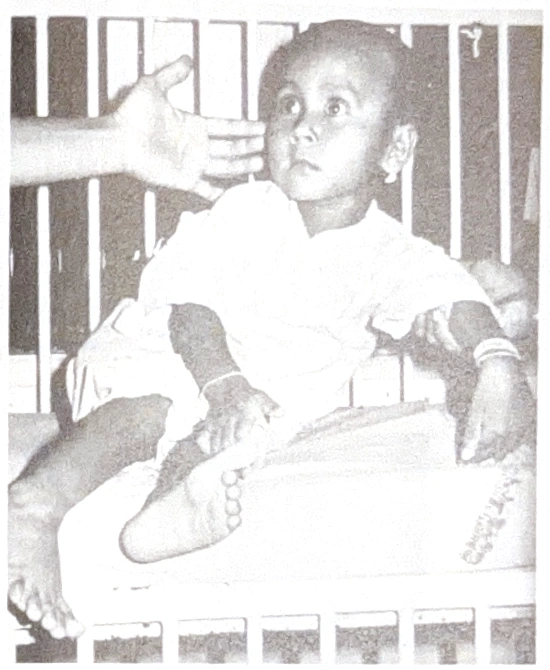

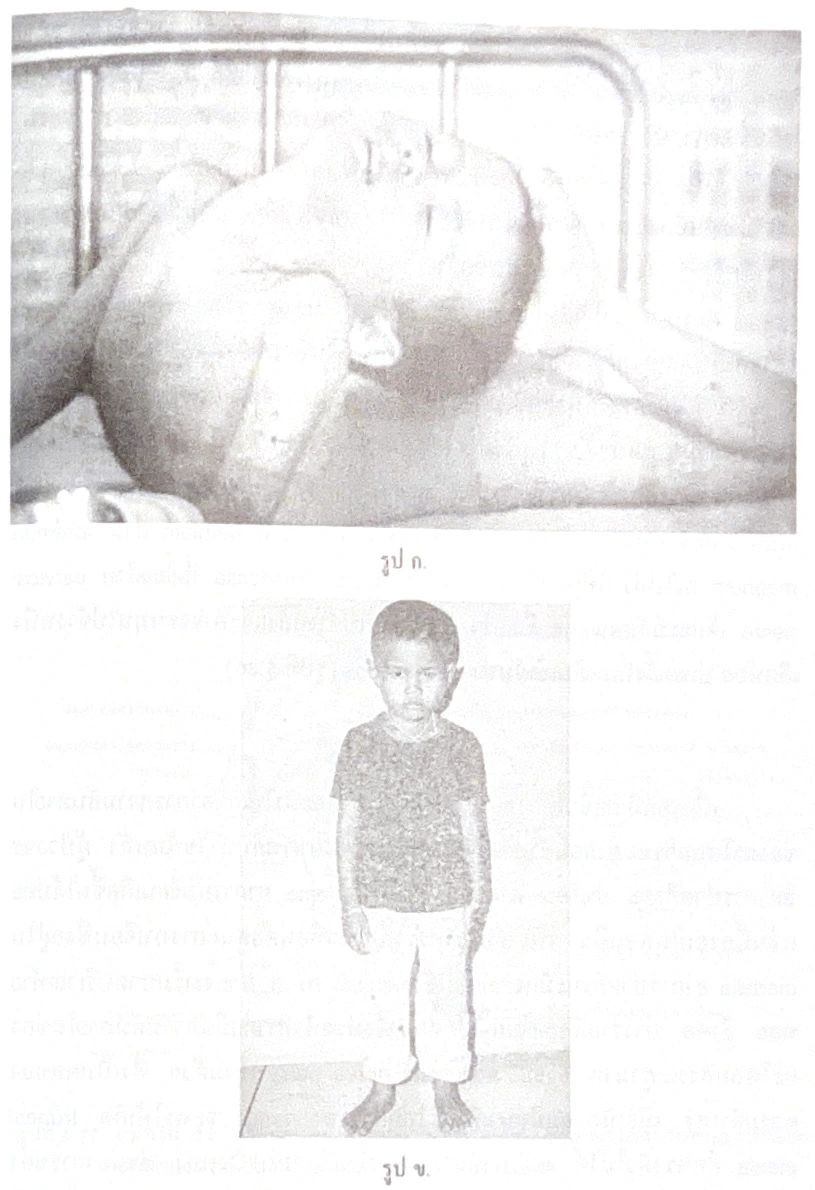
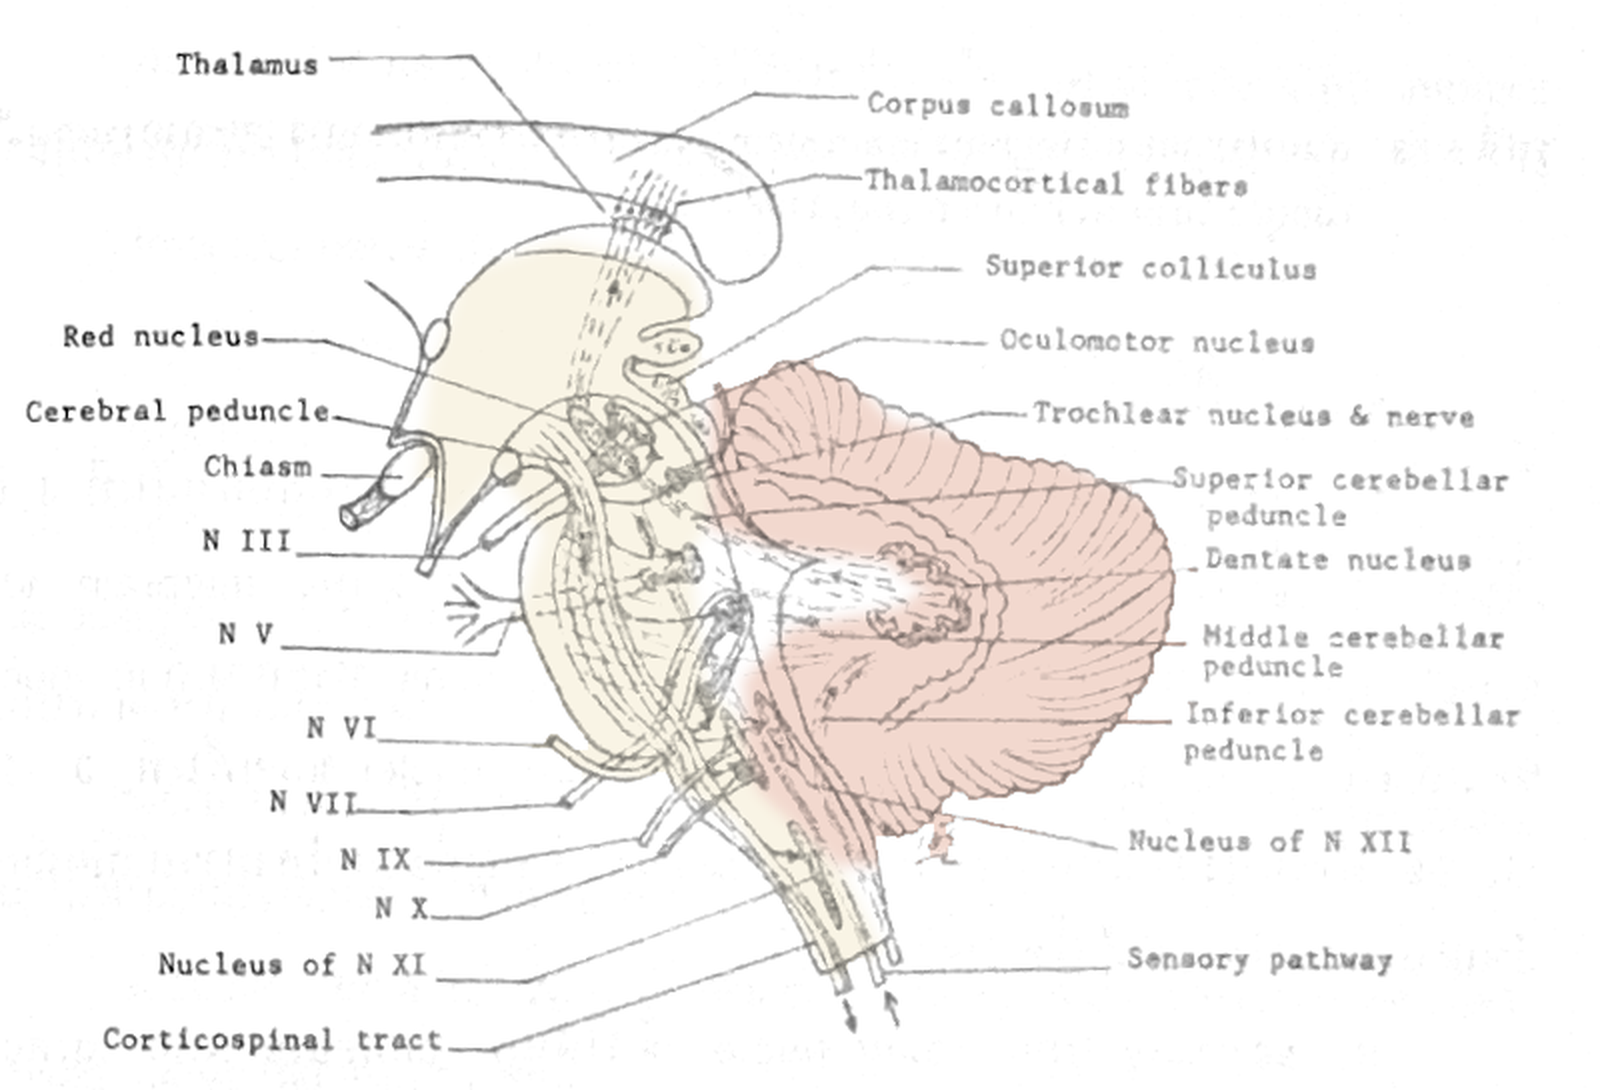
 Color added while retaining the original linework and lettering
 Color added while retaining the original linework and lettering
 Color added while retaining the original linework and lettering
 Color added while retaining the original linework and lettering
 Color added while retaining the original linework and lettering
 Color added while retaining the original linework and lettering




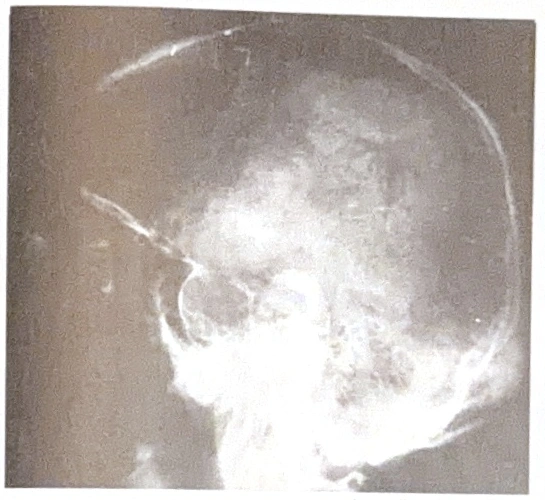
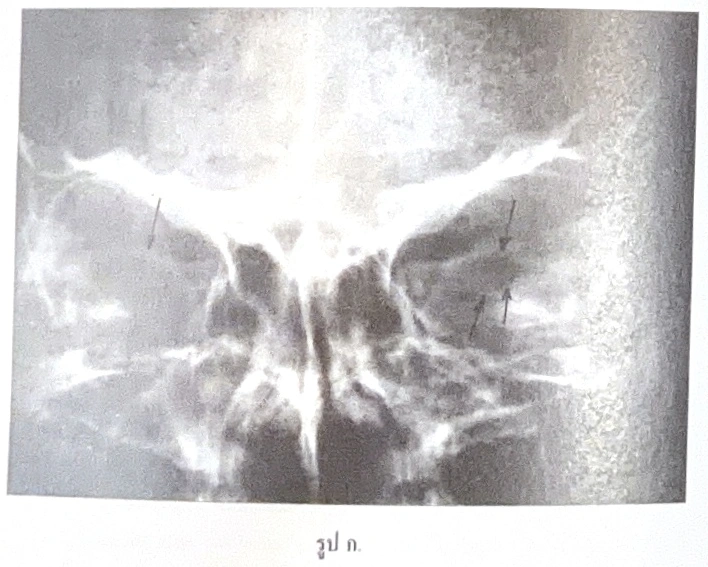
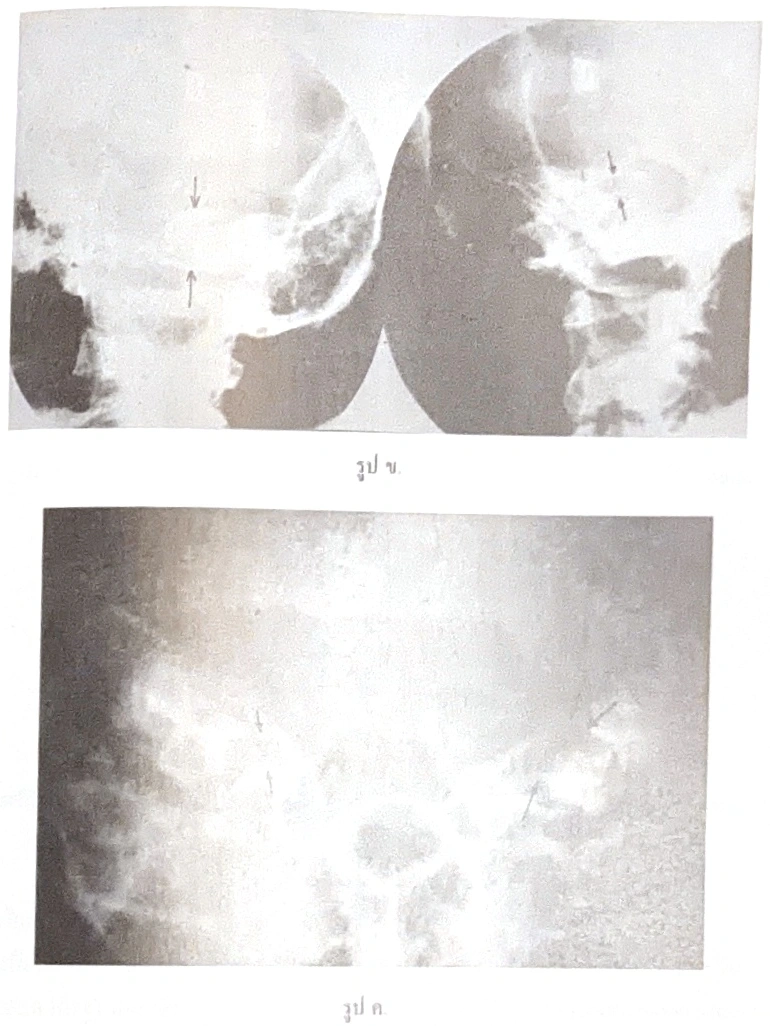

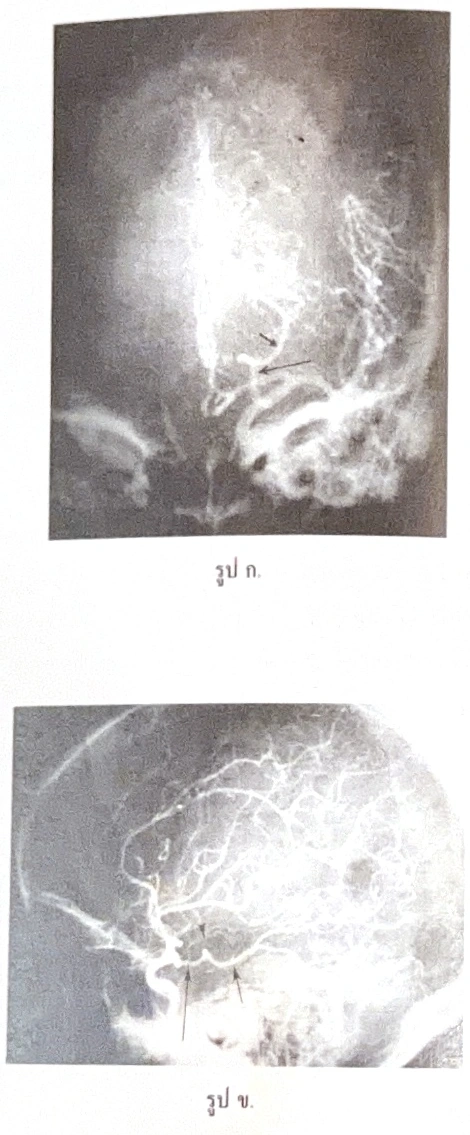
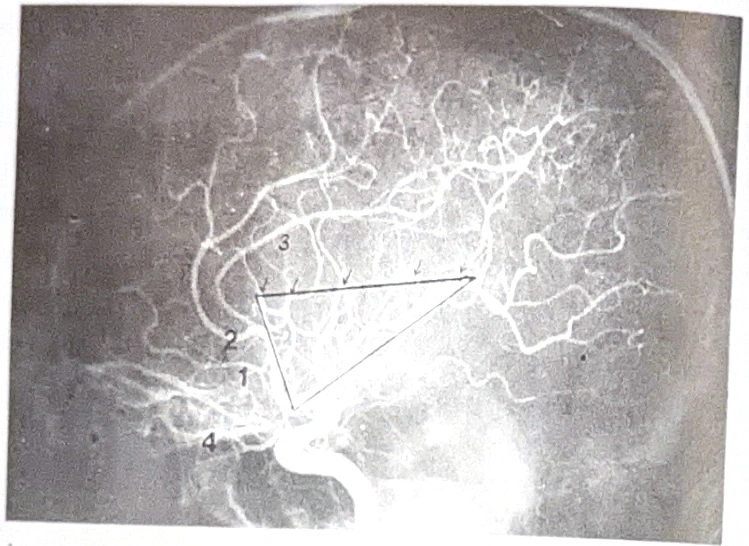
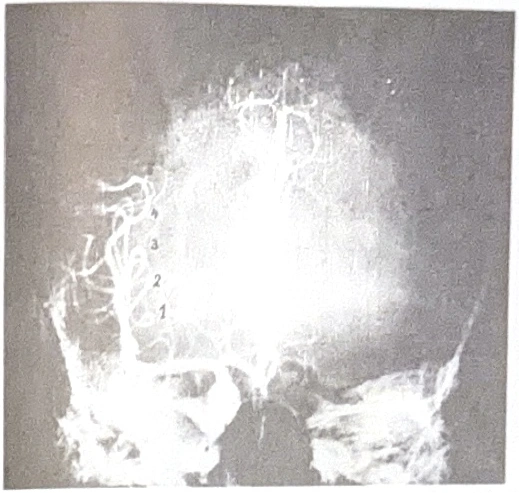
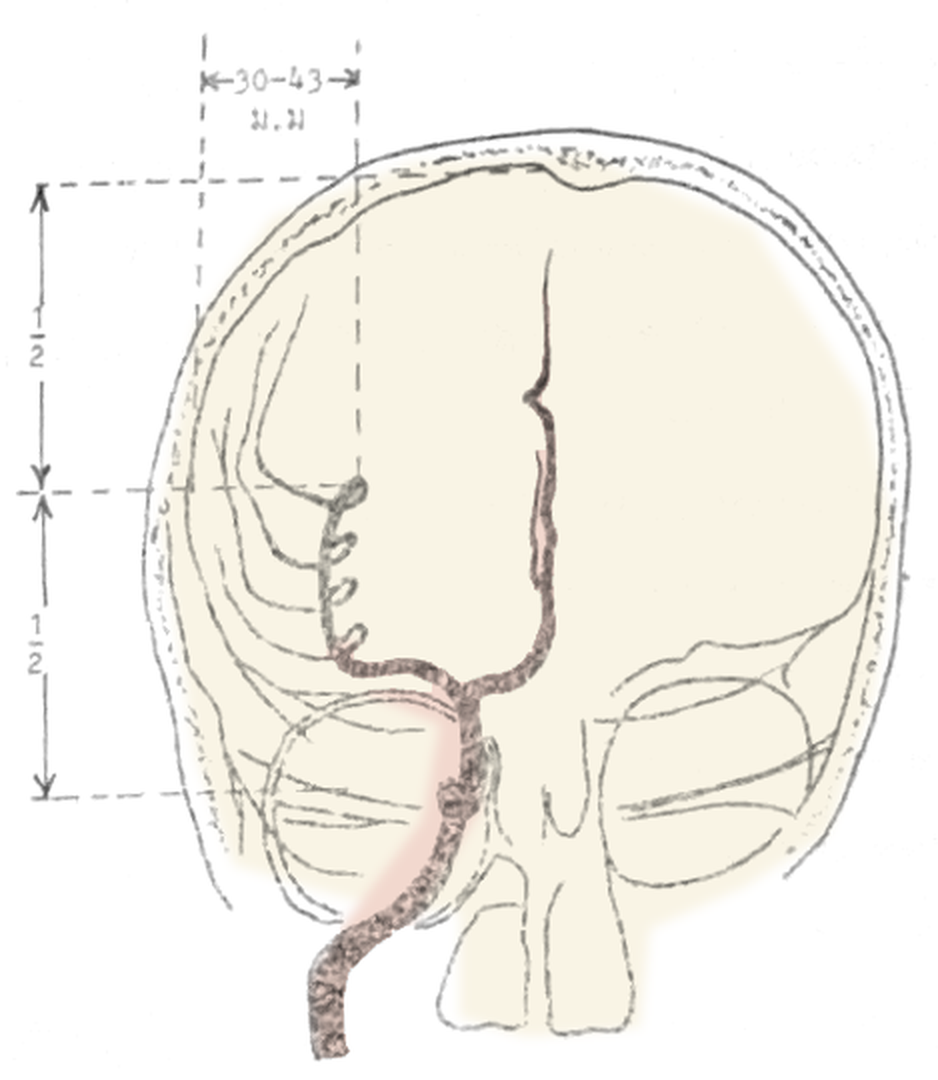
 Color added while retaining the original linework and lettering
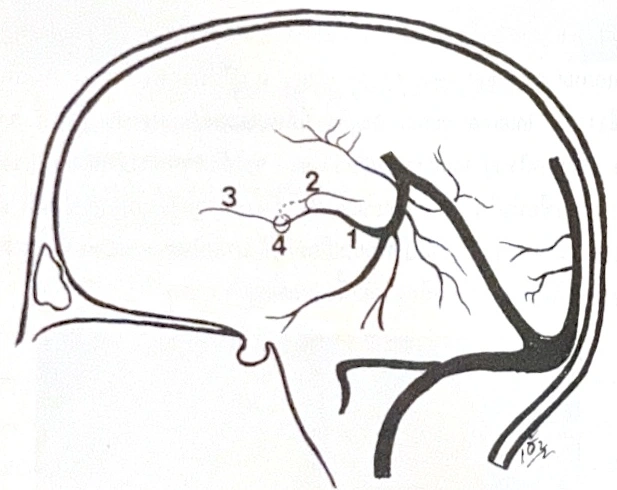 Color added while retaining the original linework and lettering

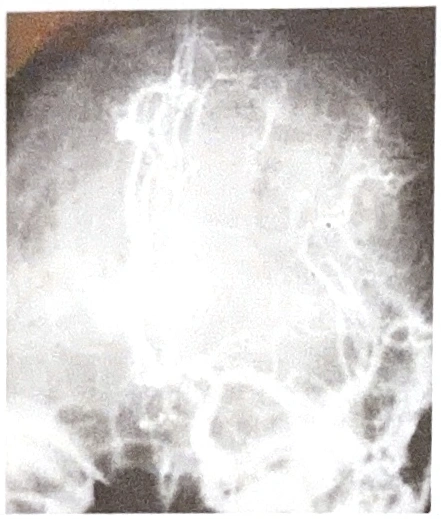
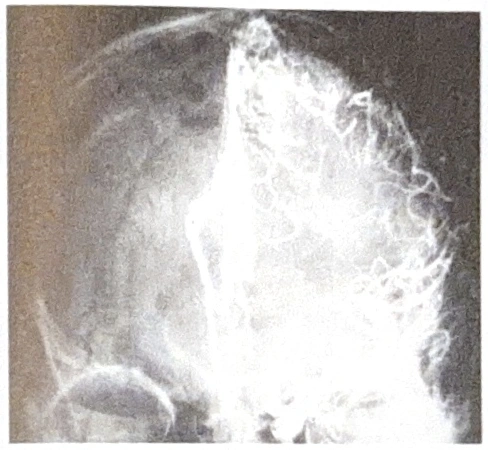
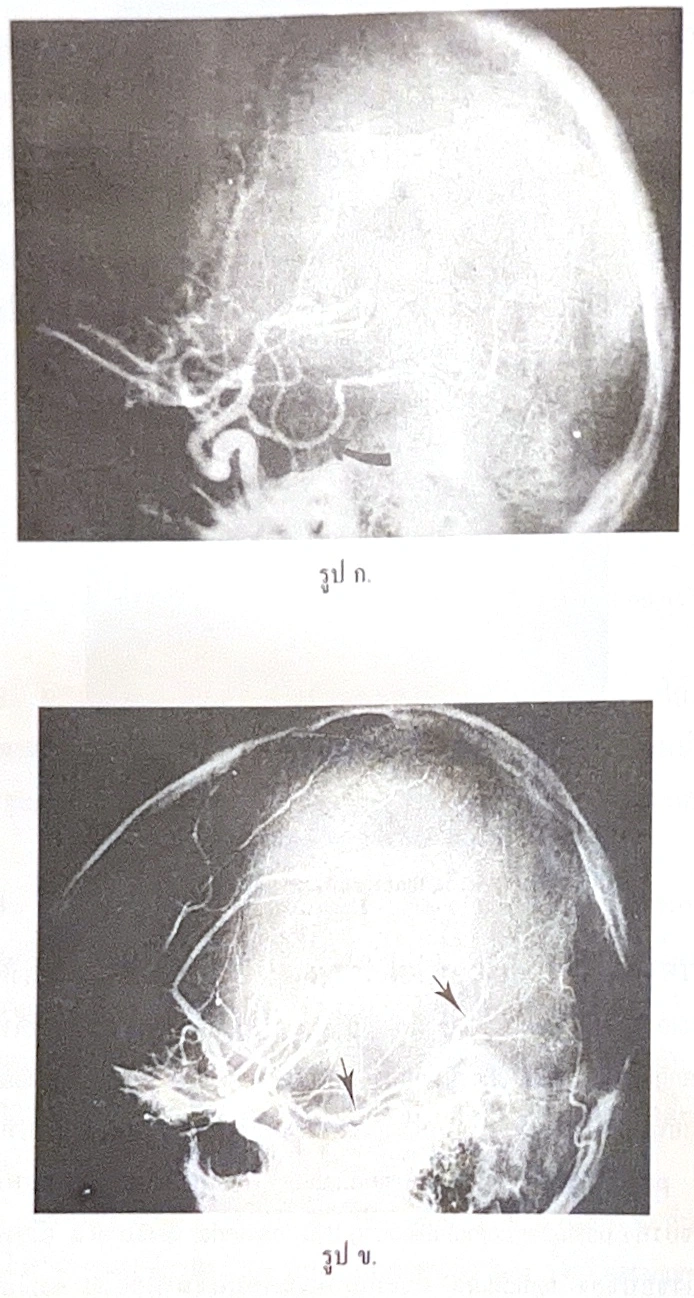
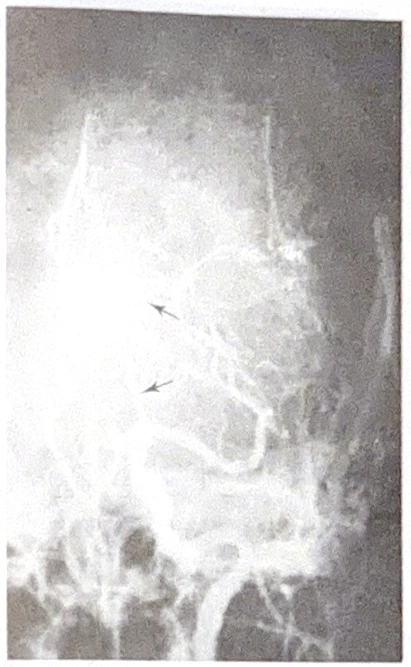
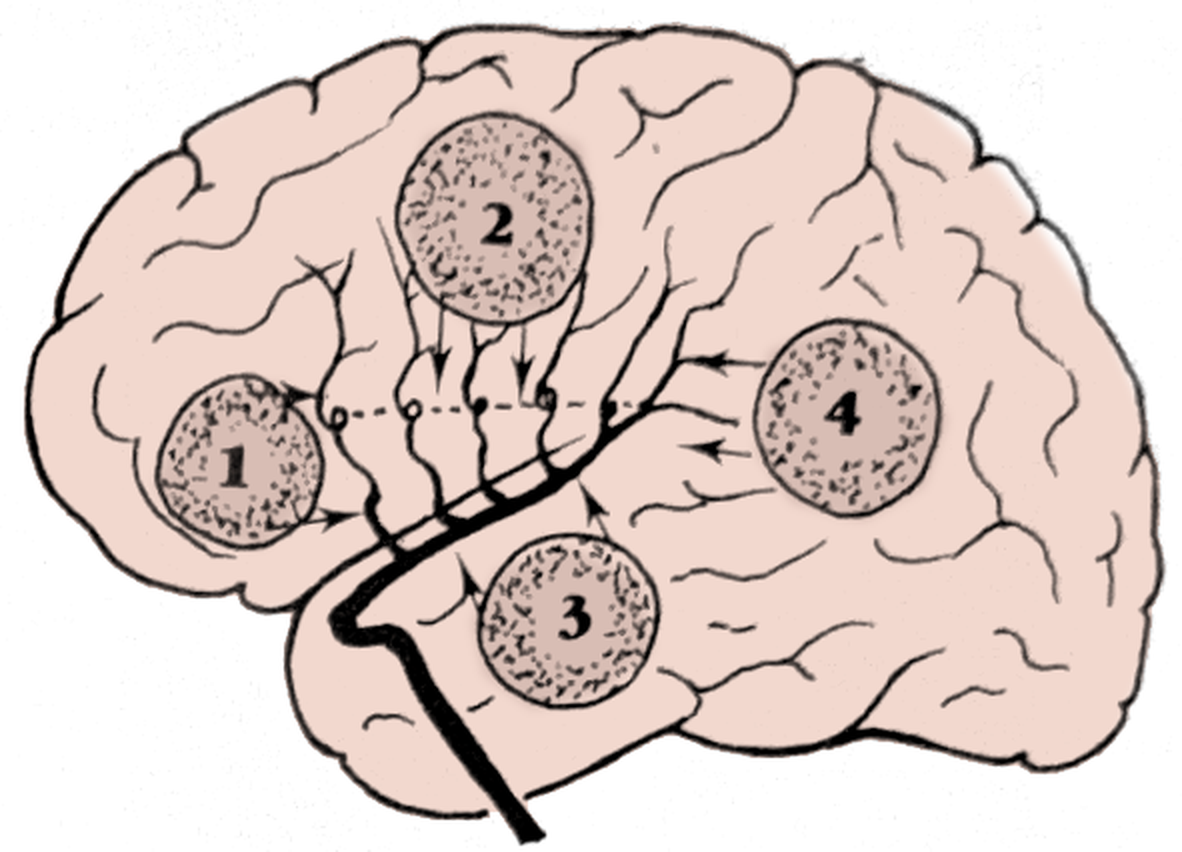
 Color added while retaining the original linework and lettering
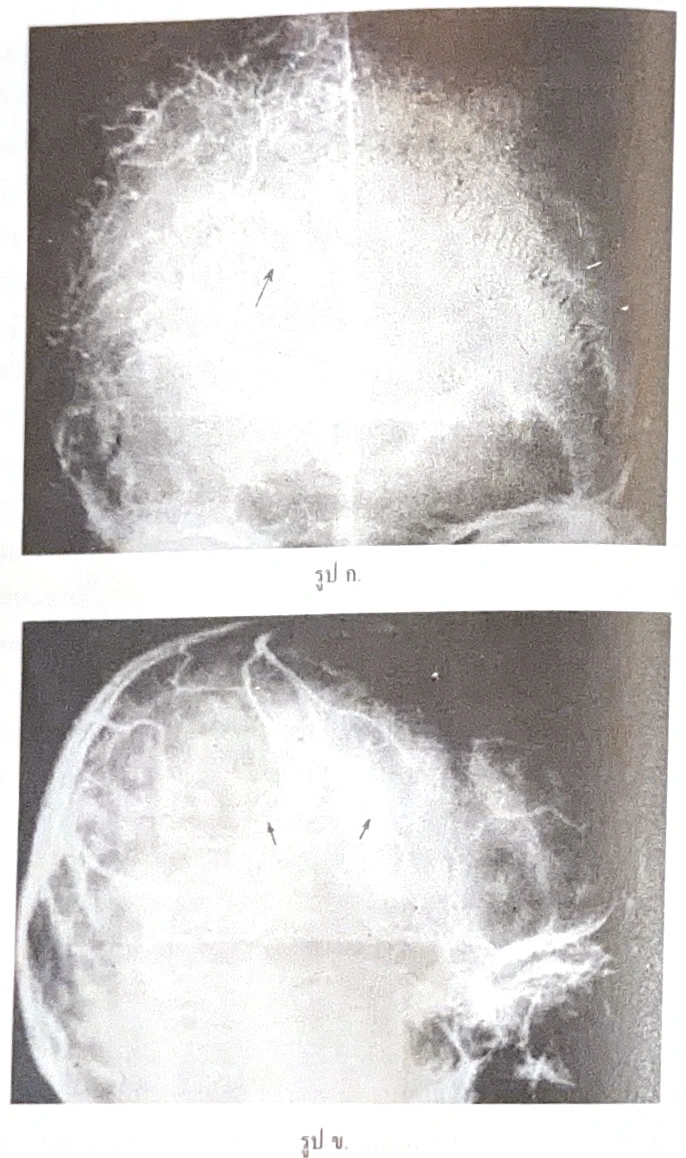
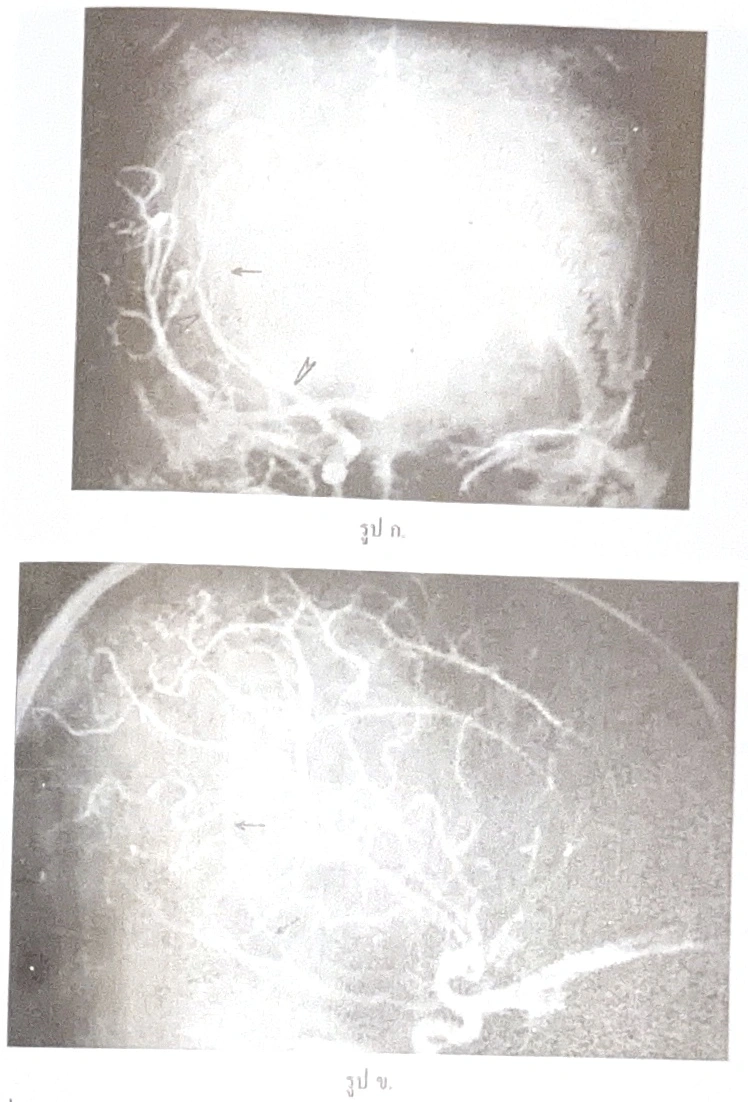
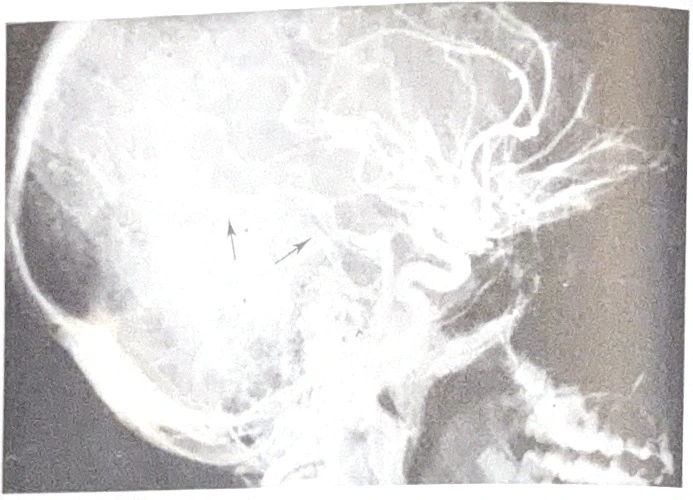
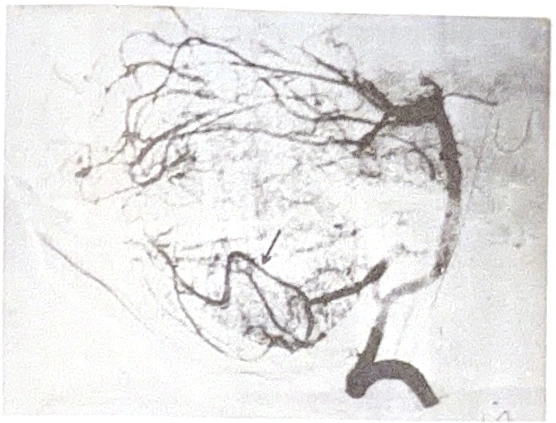
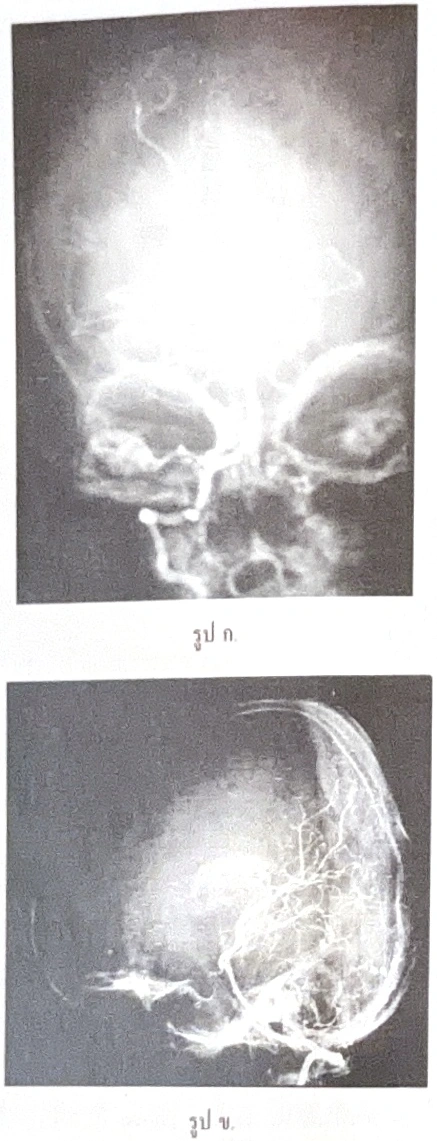
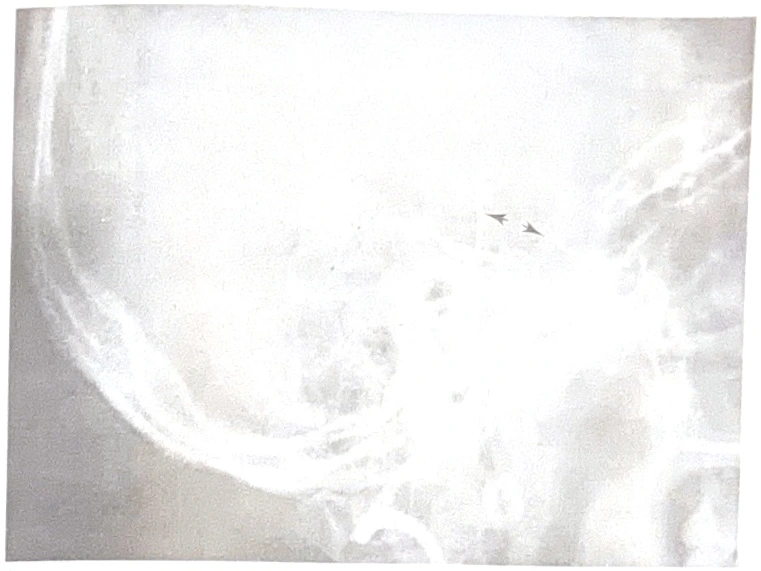

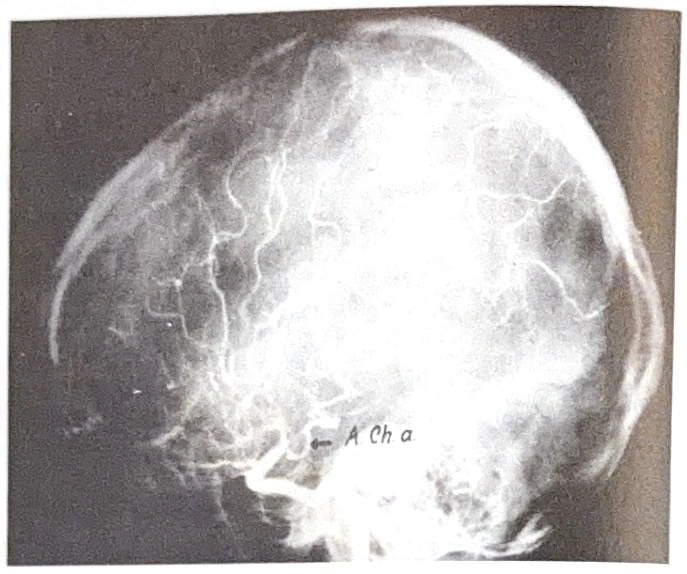
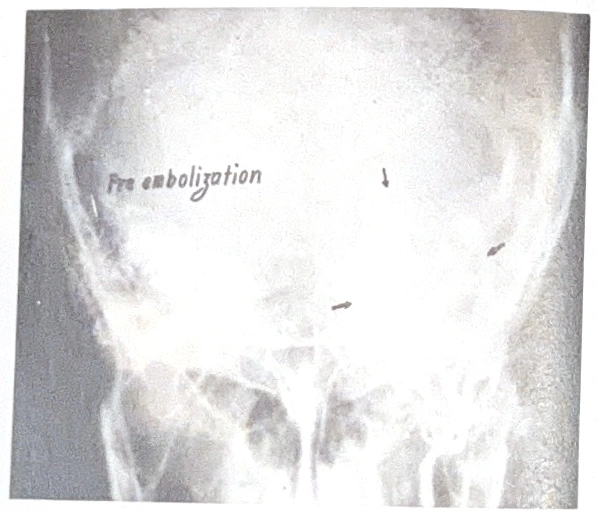
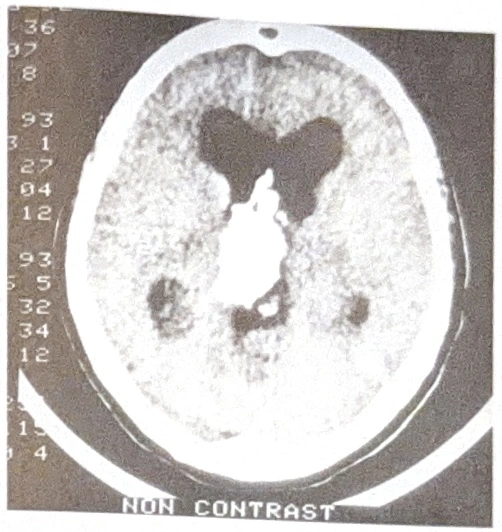
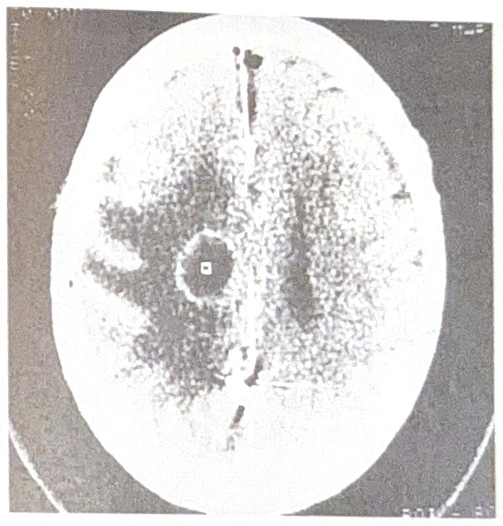
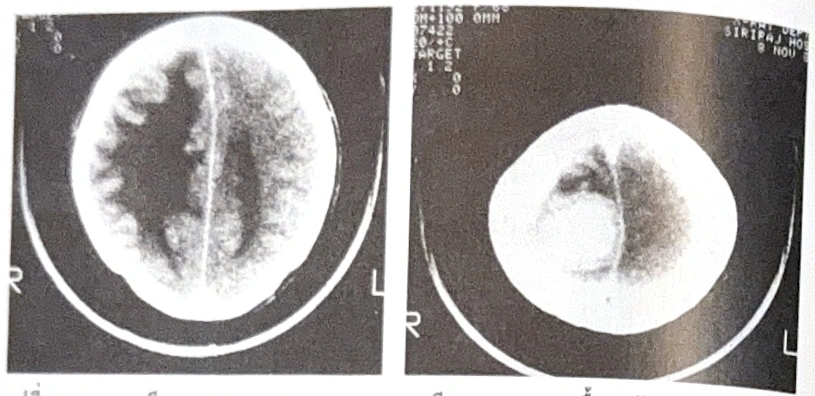
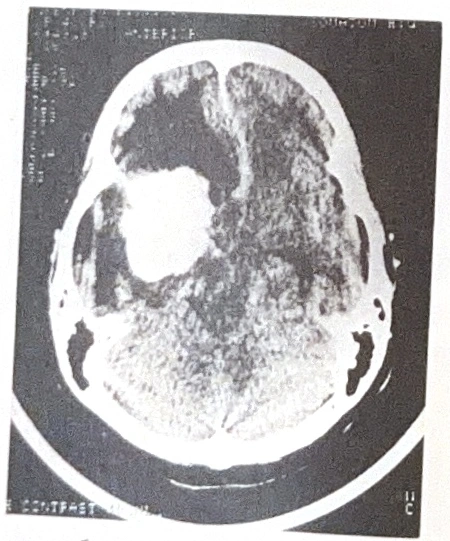
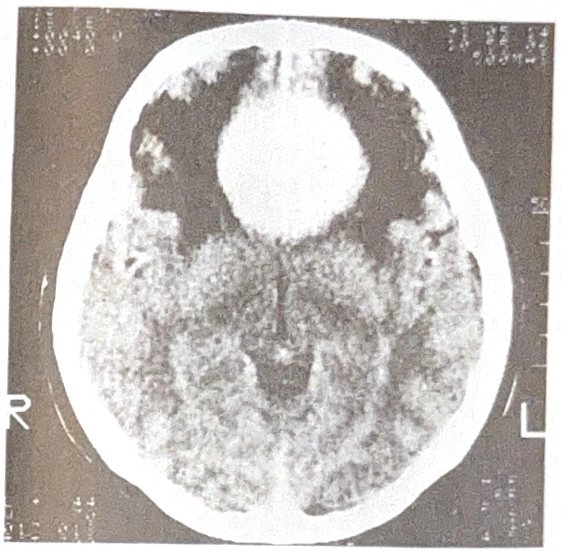
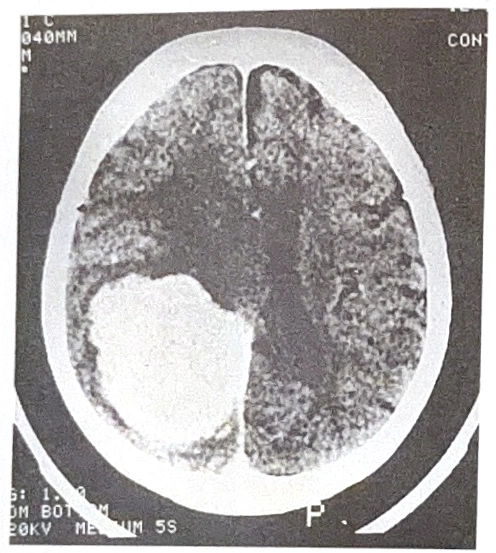
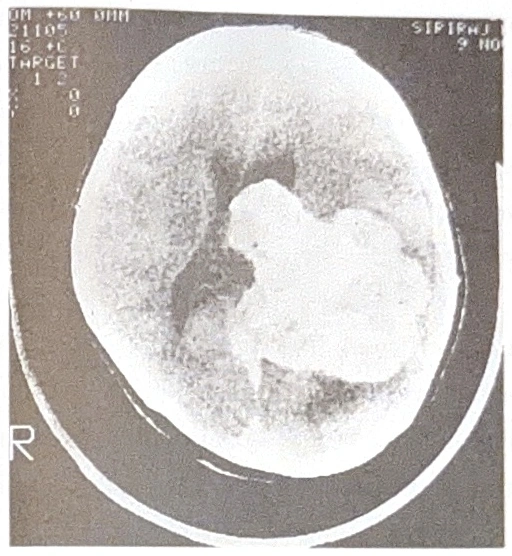
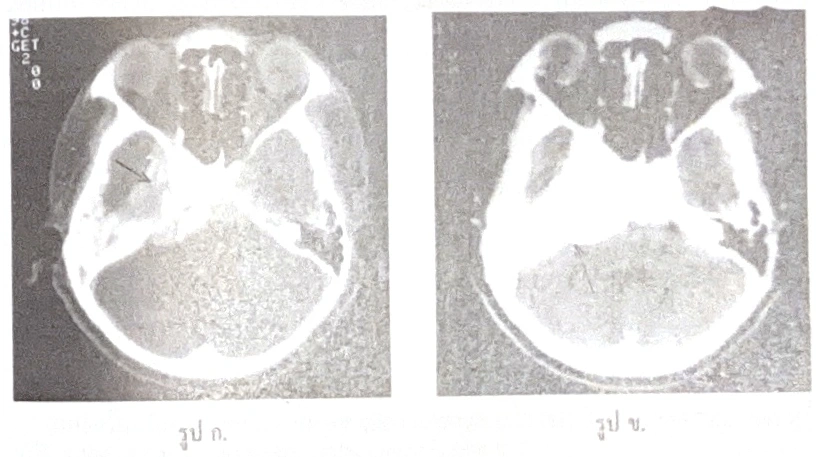
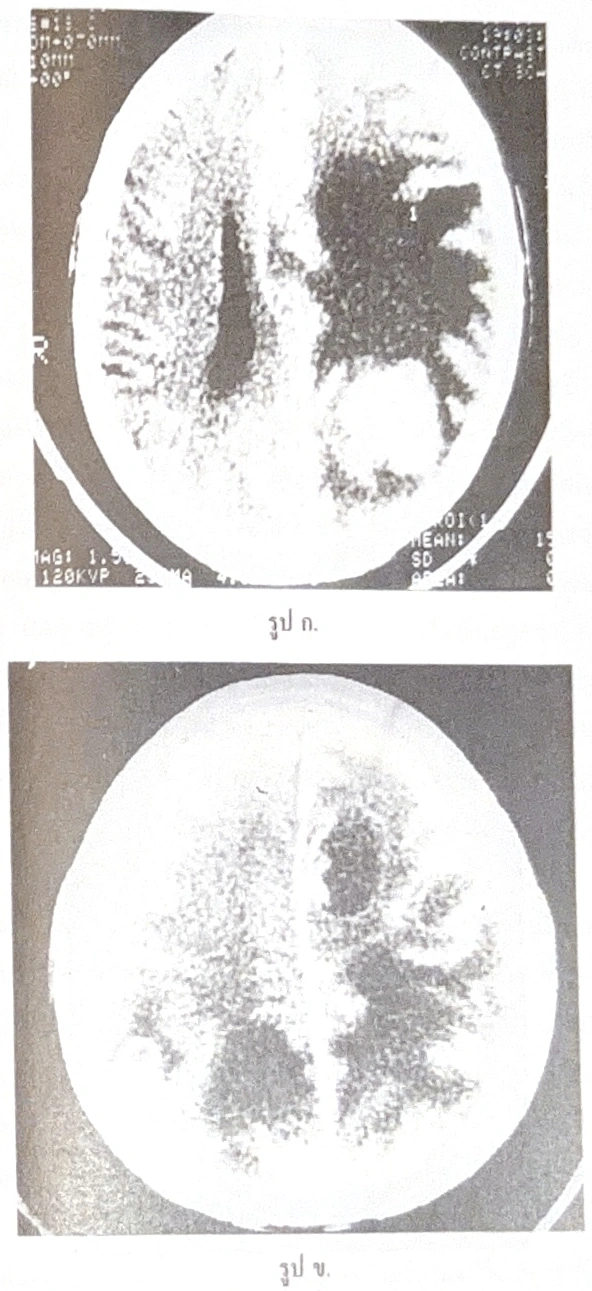
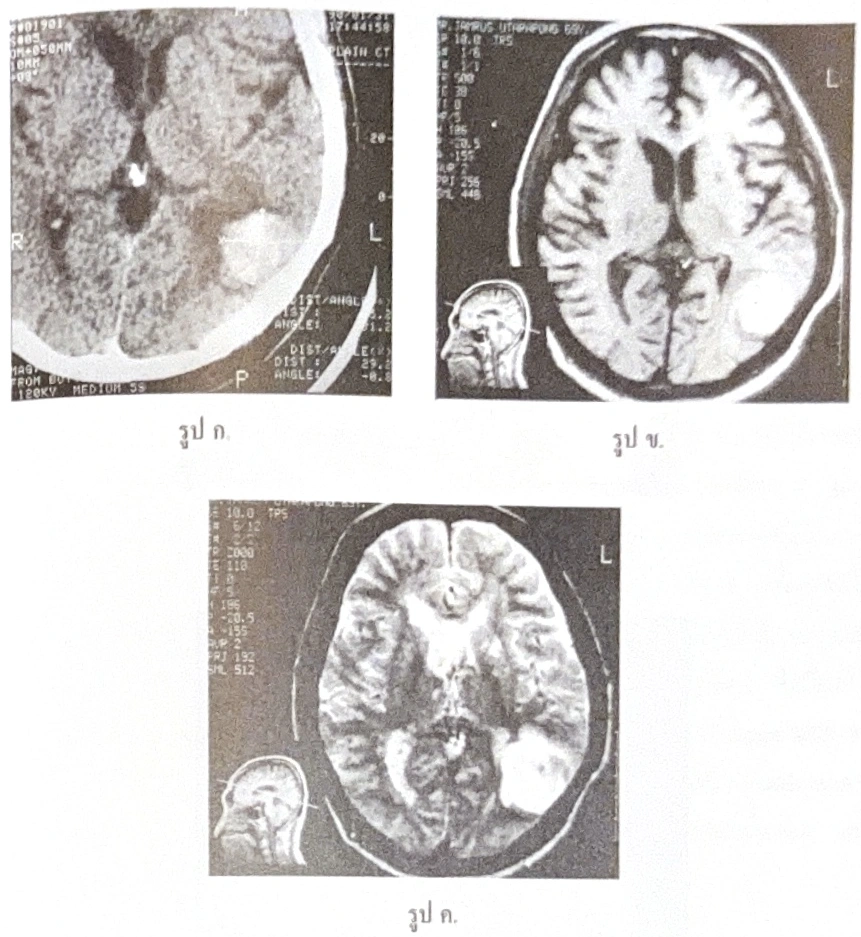
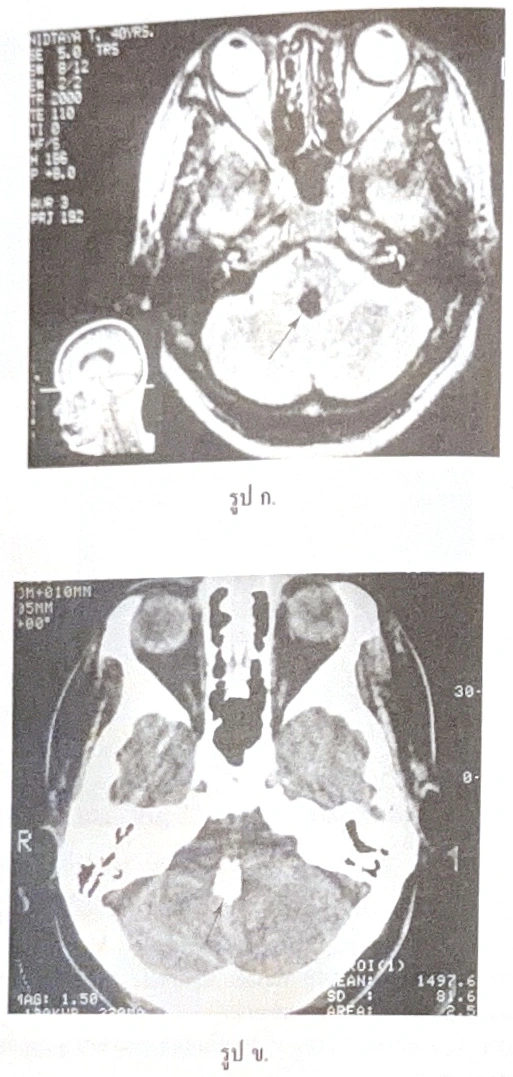
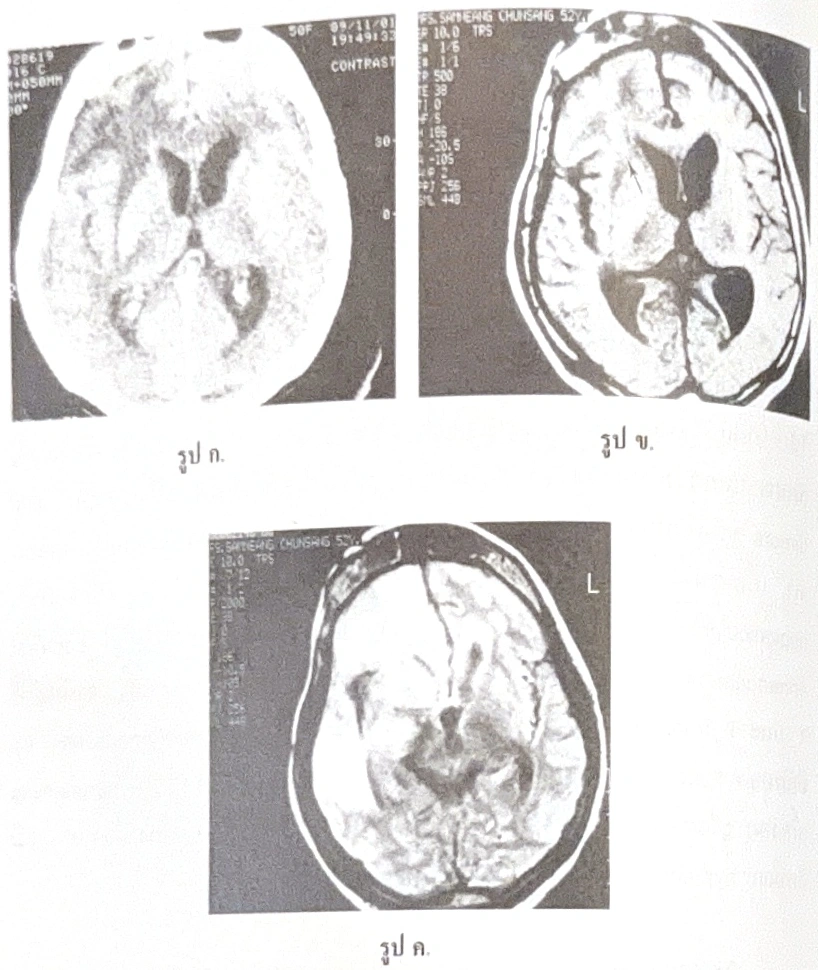
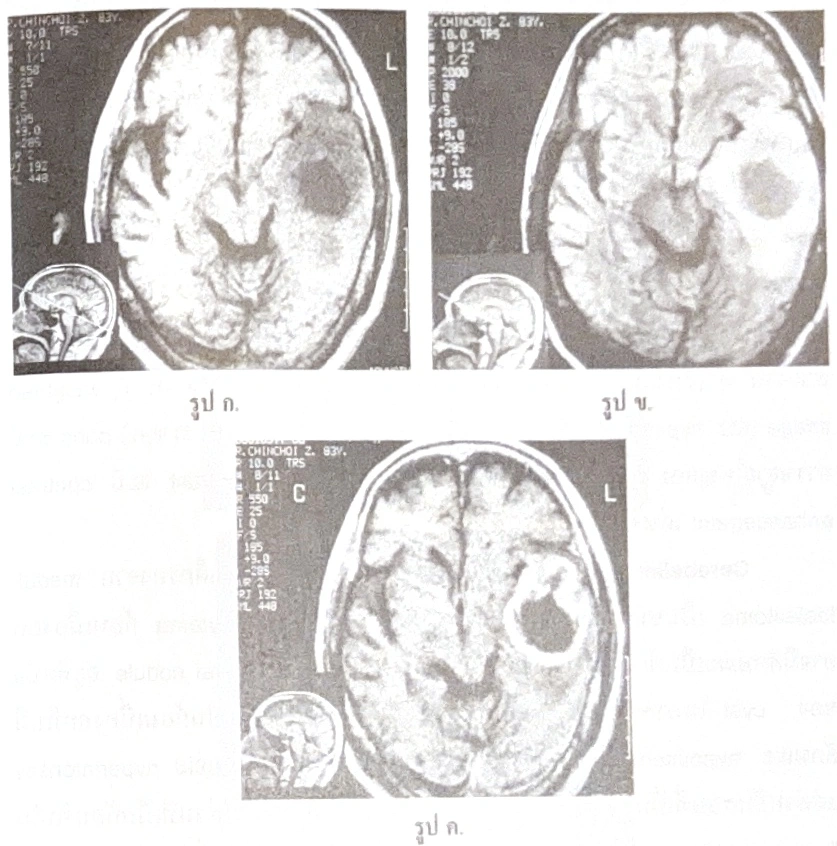
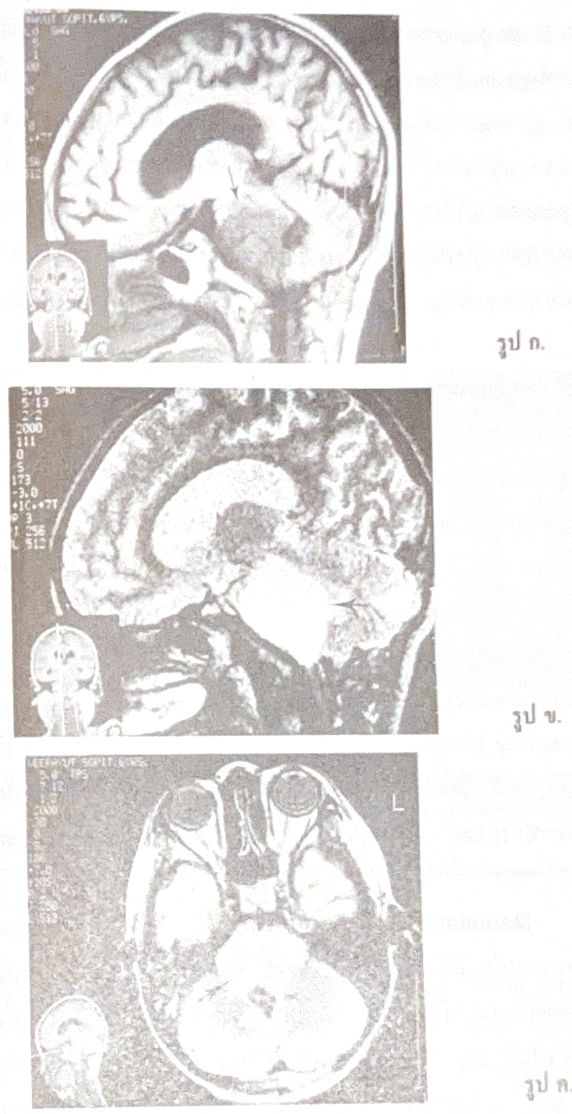
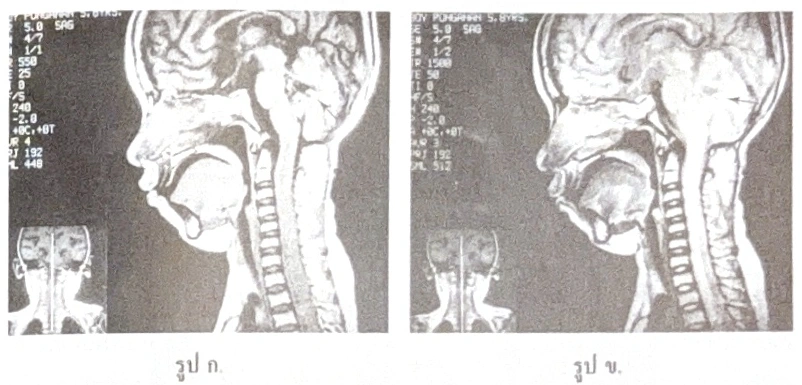
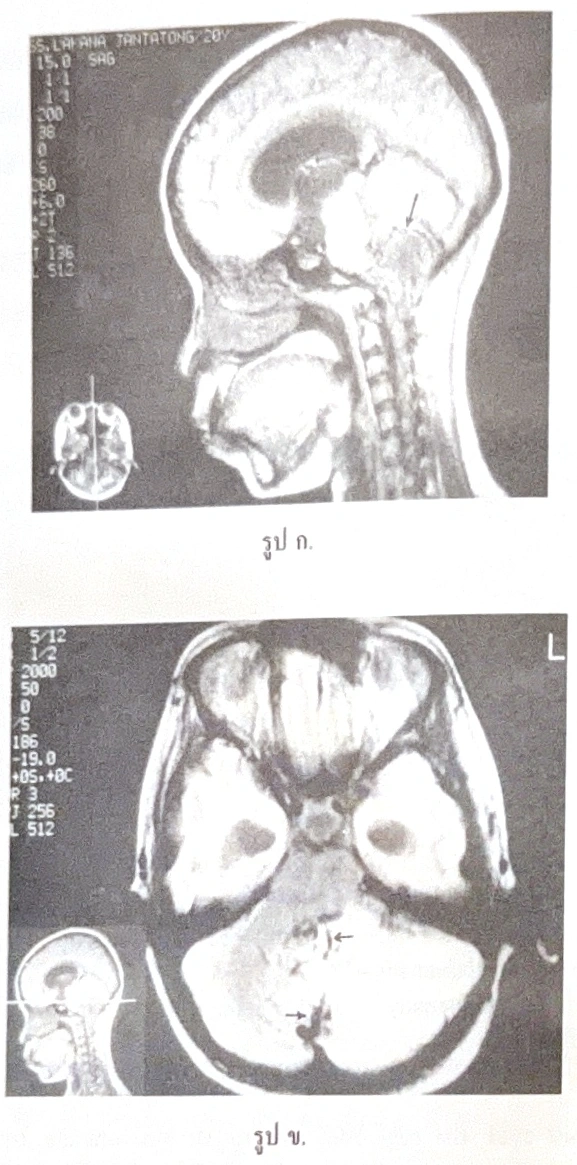
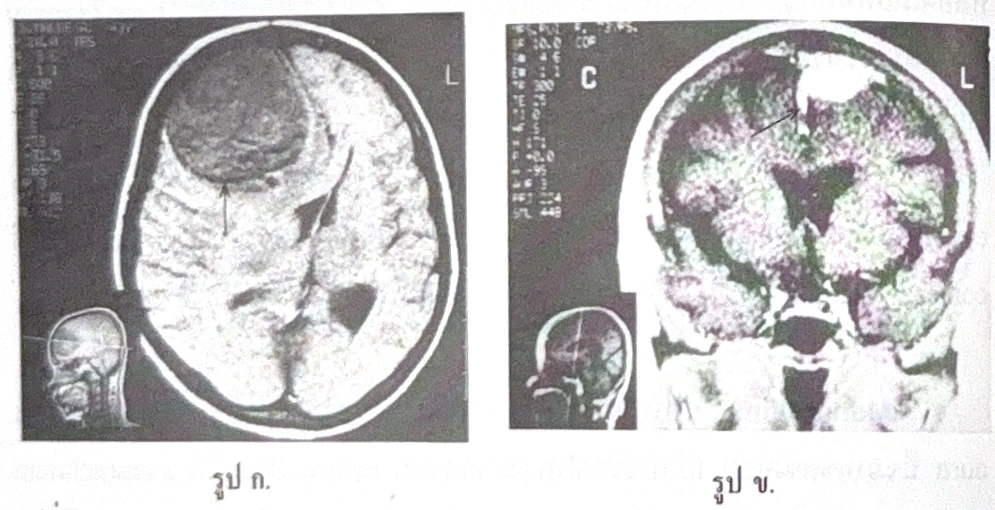
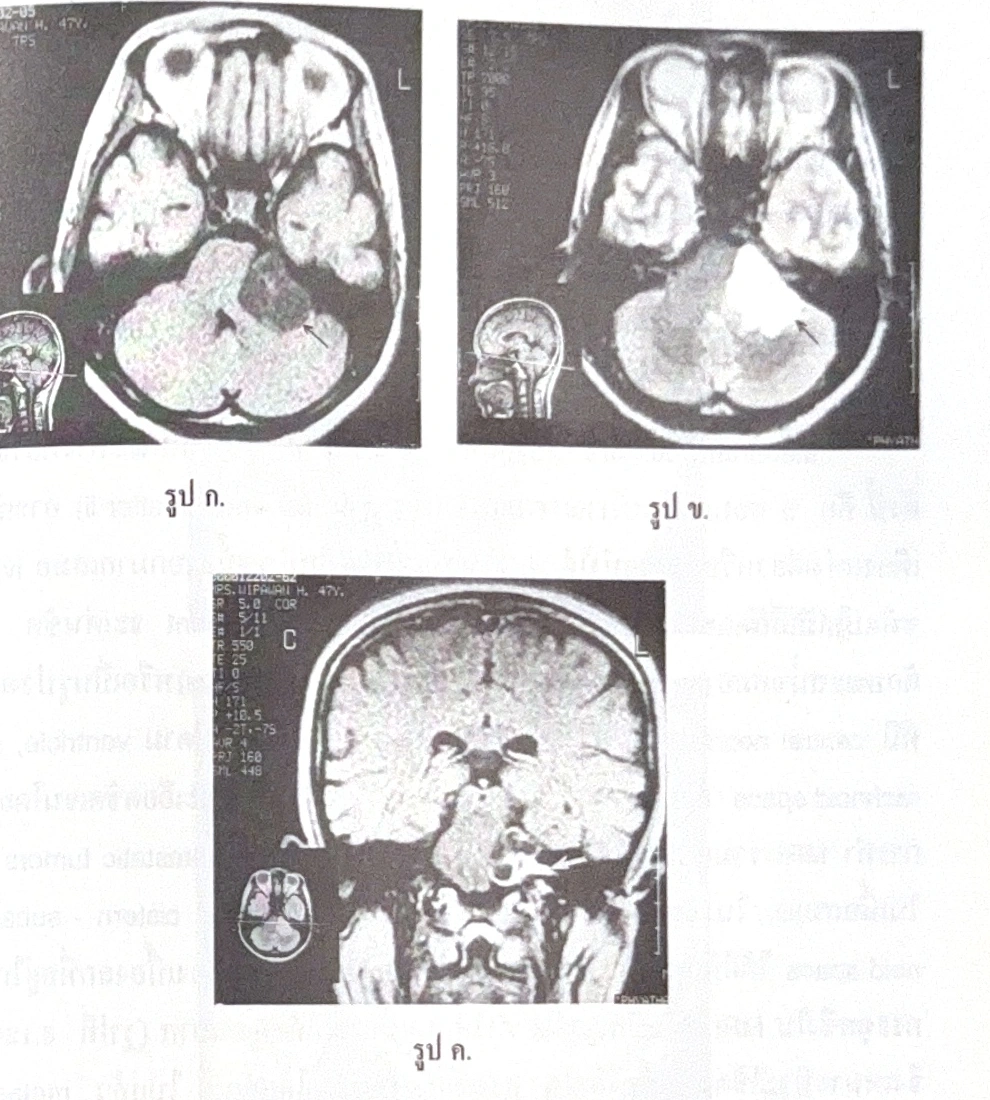
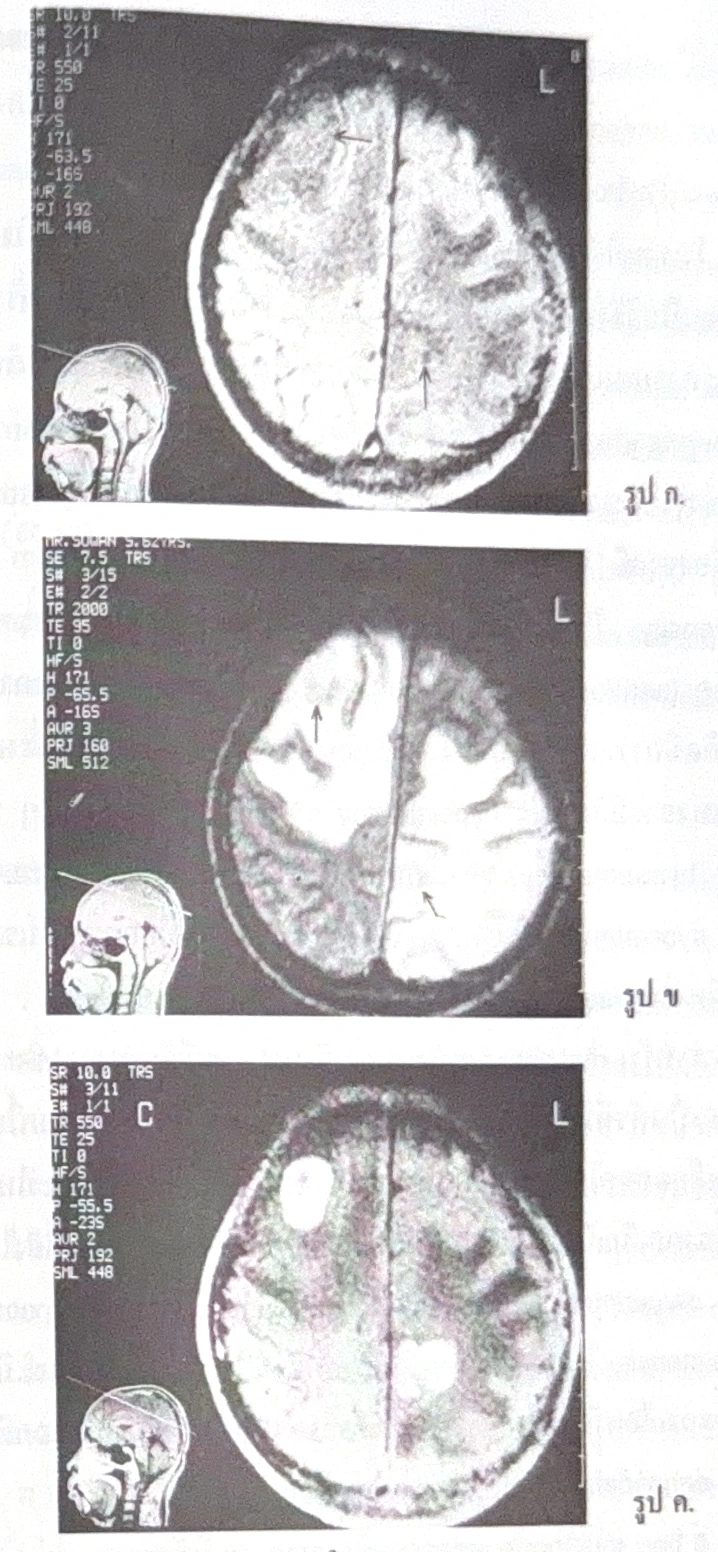
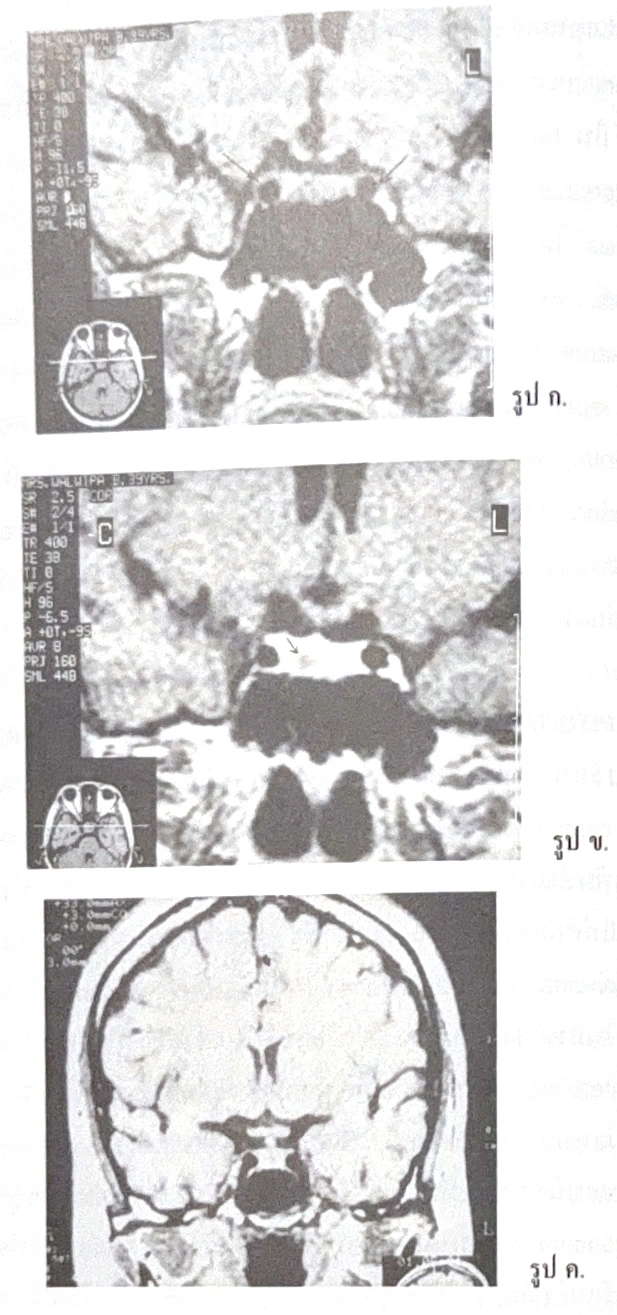
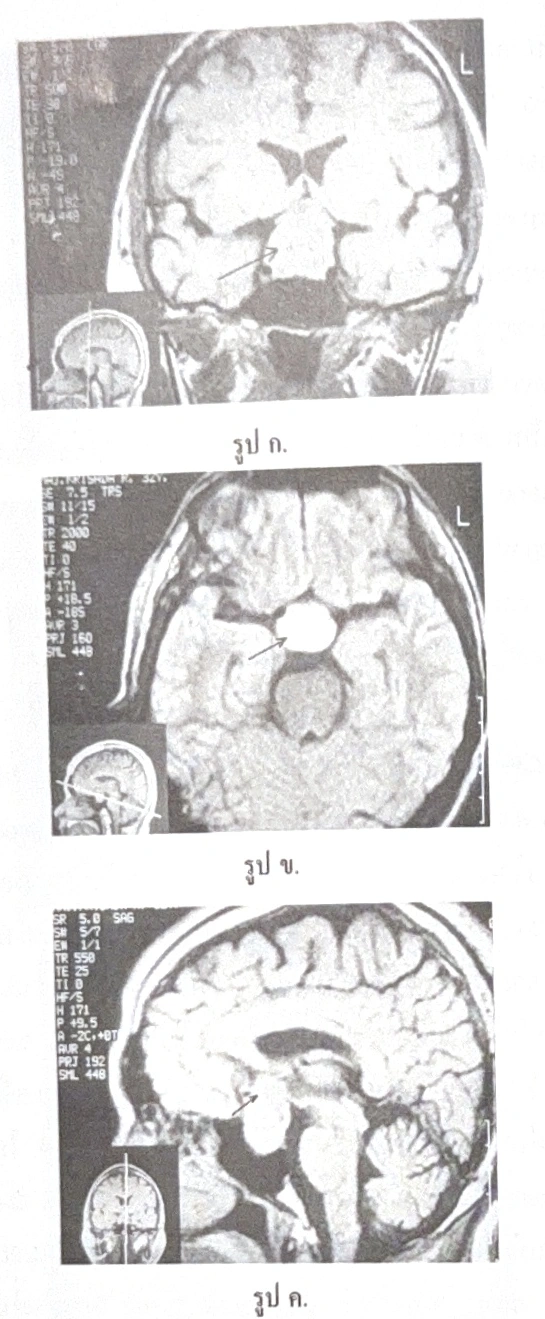
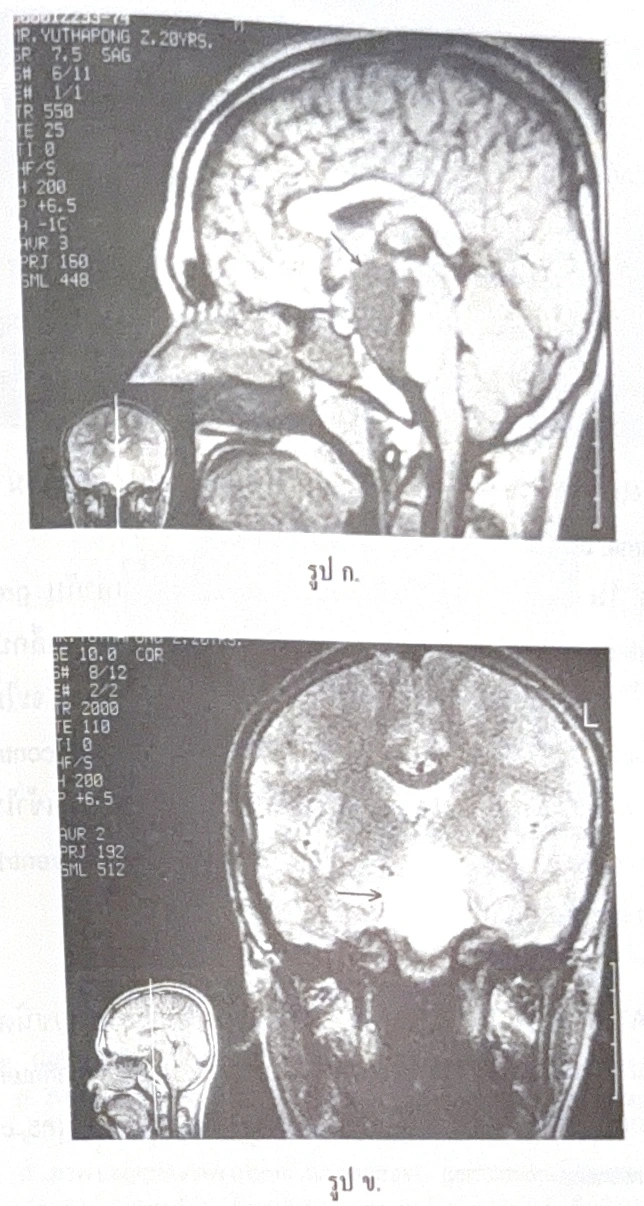
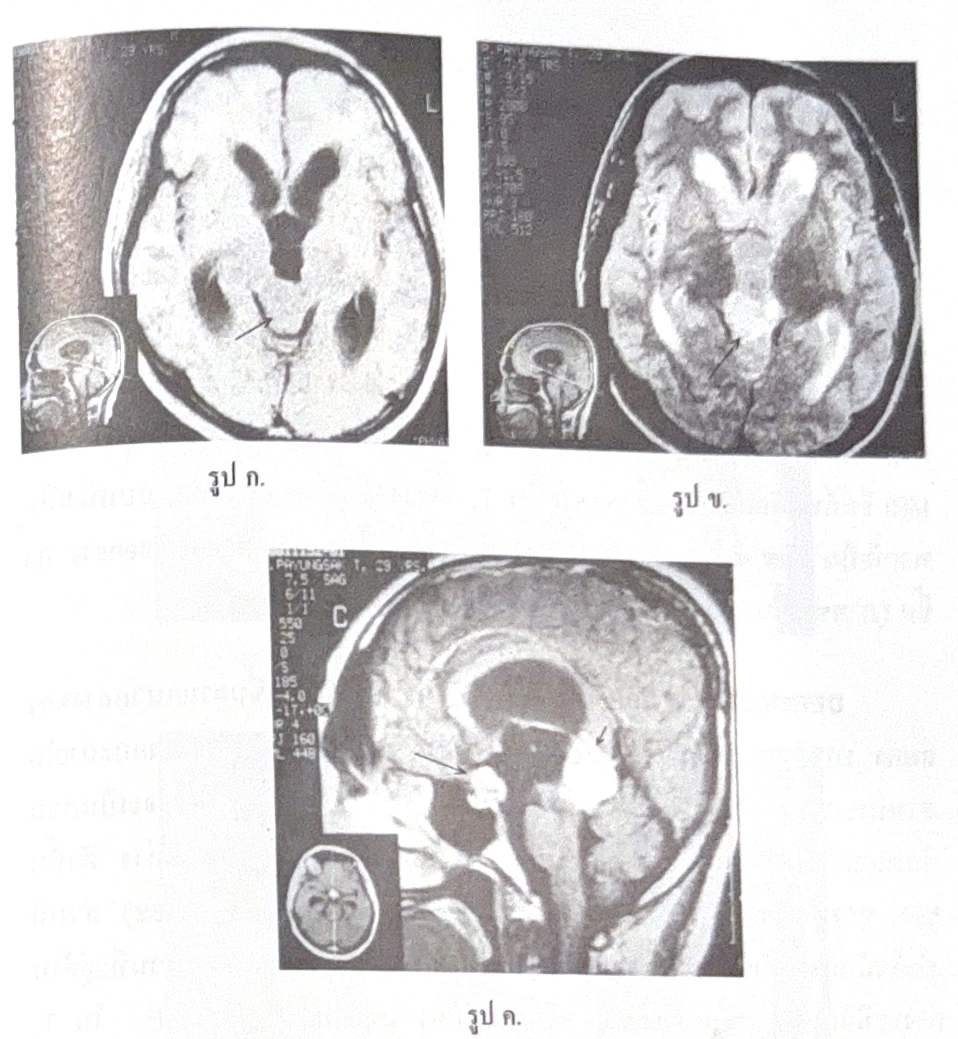
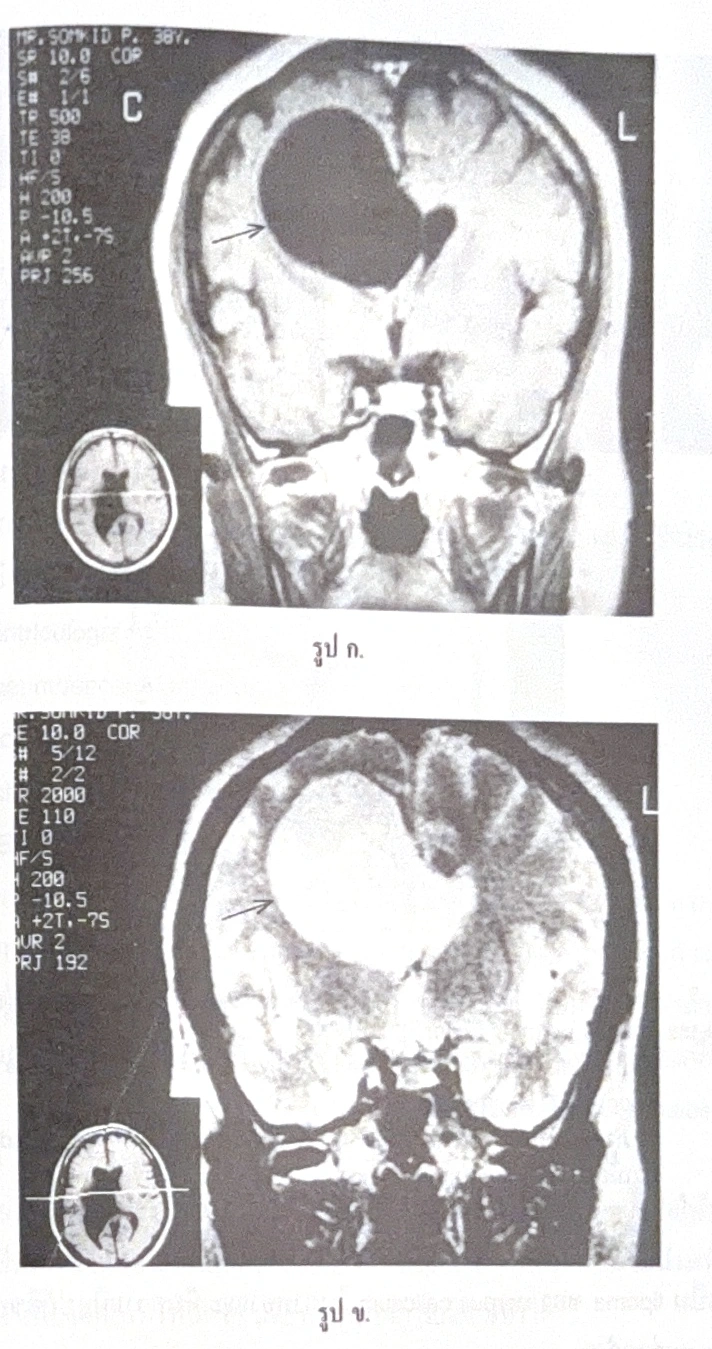
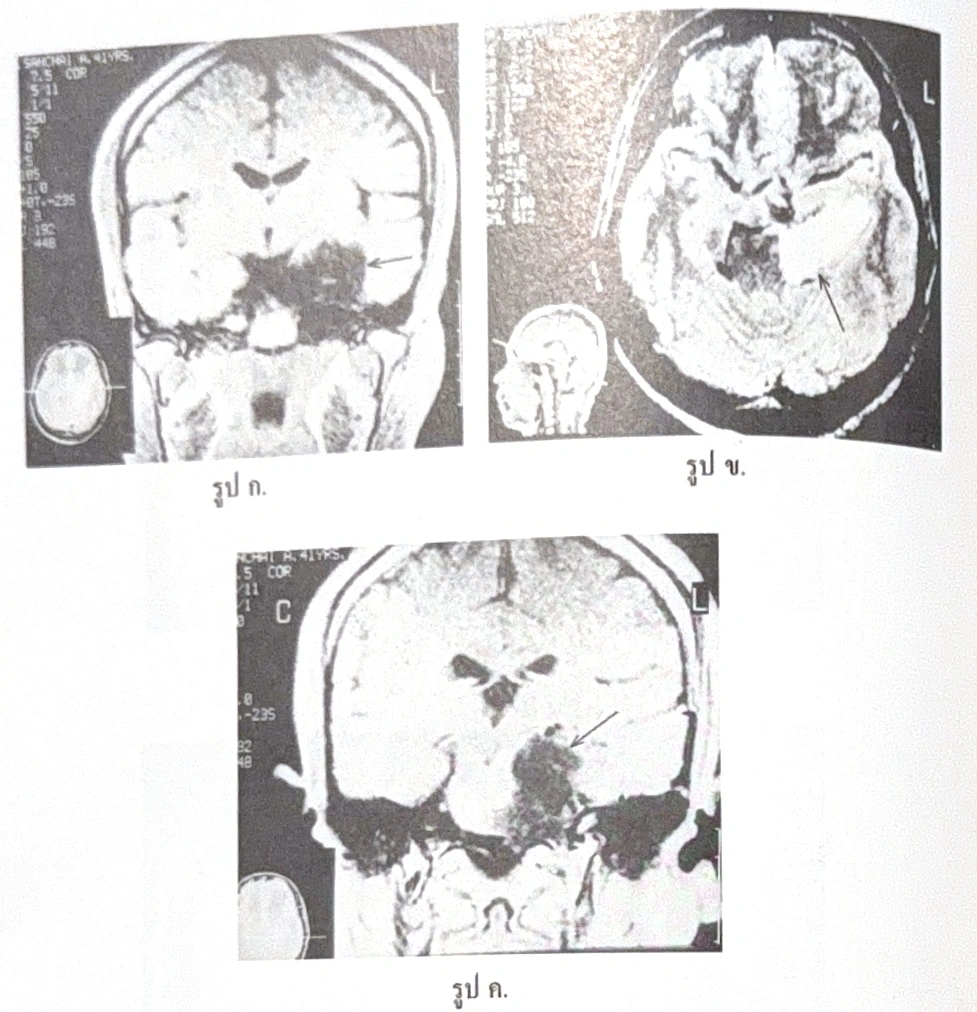
 AI-enhanced and colorized image · Switch to view the original
 AI-enhanced and colorized image · Switch to view the original
 AI-enhanced and colorized image · Switch to view the original
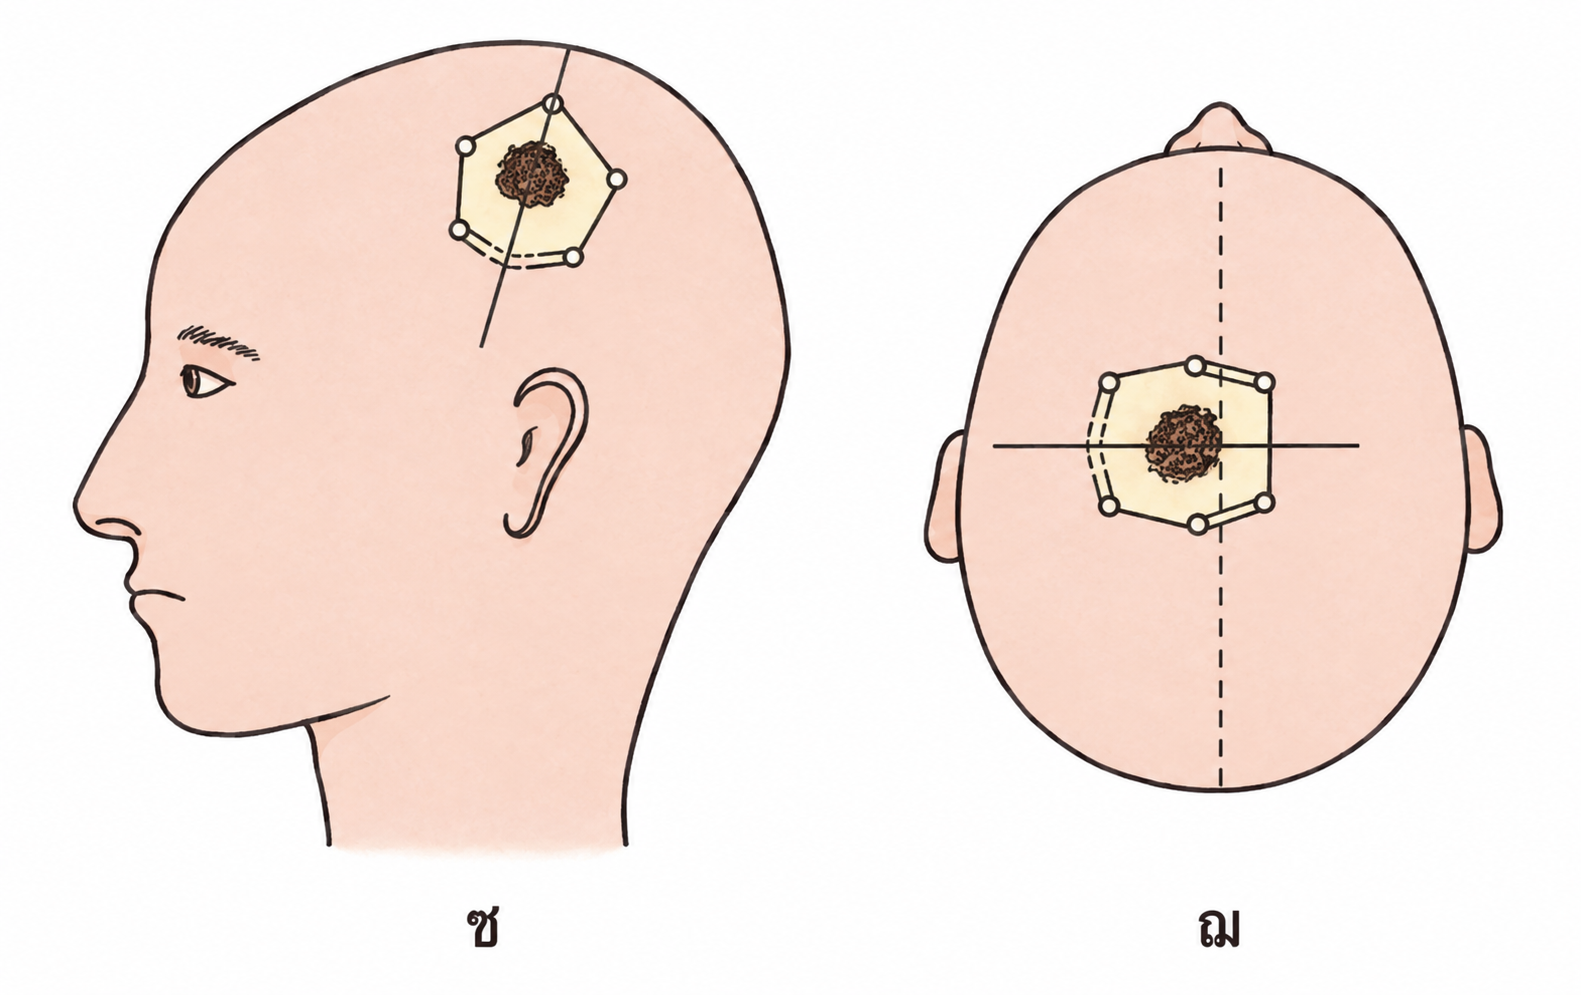
 AI-enhanced and colorized image · Switch to view the original
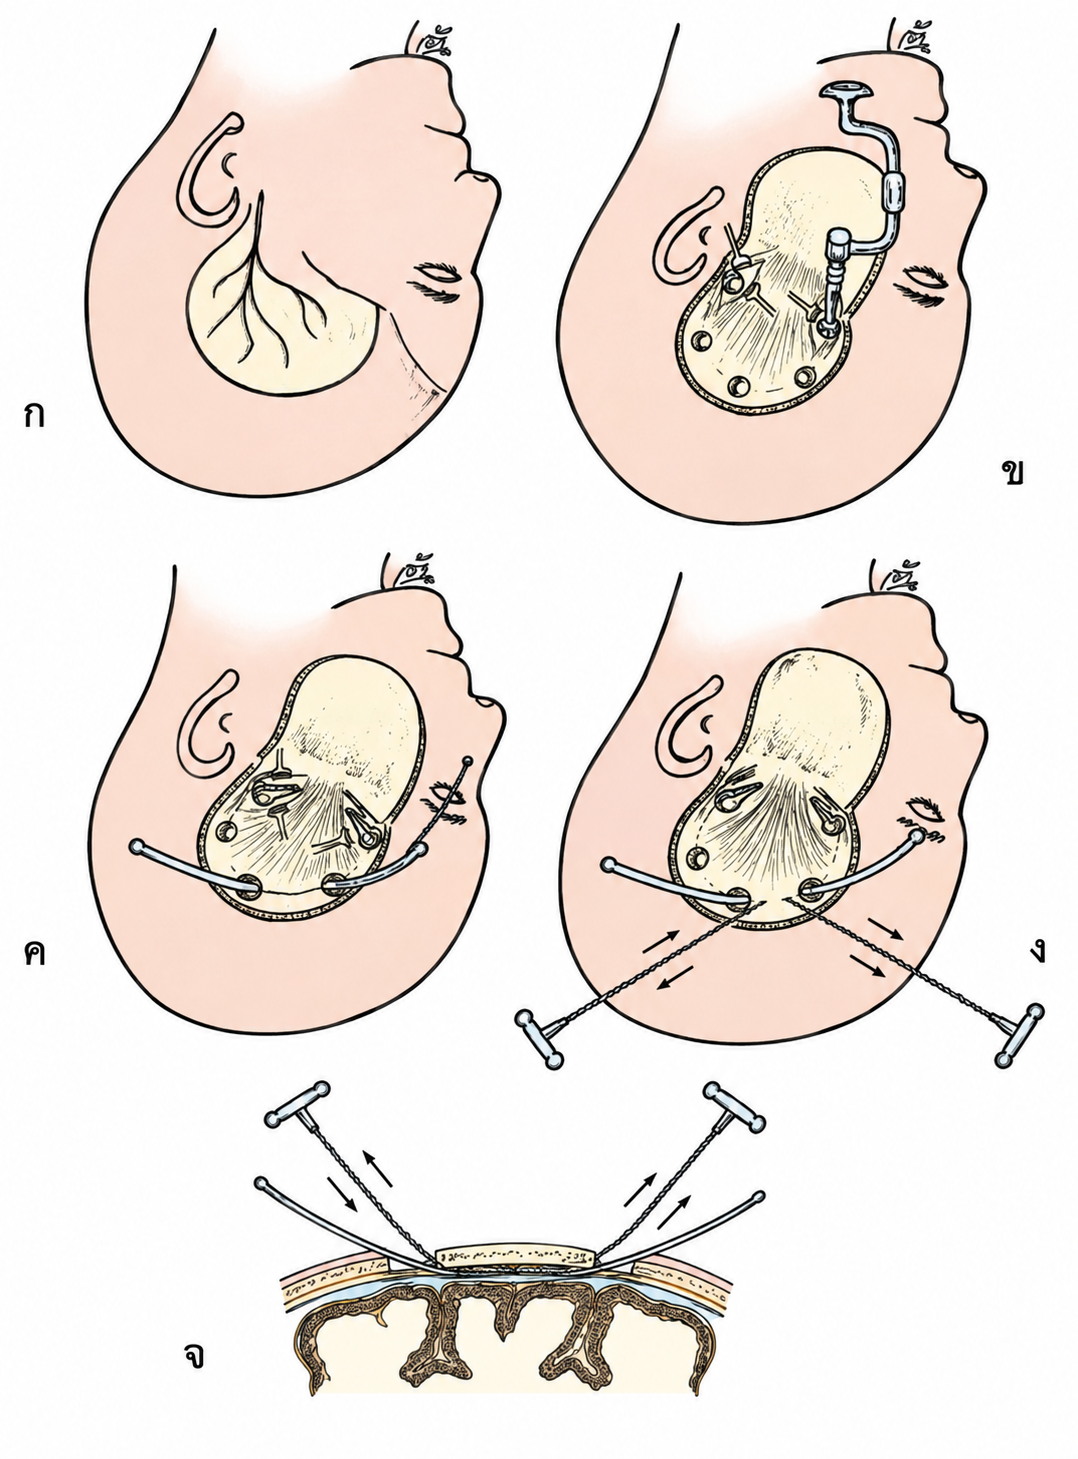
 AI-enhanced and colorized image · Switch to view the original
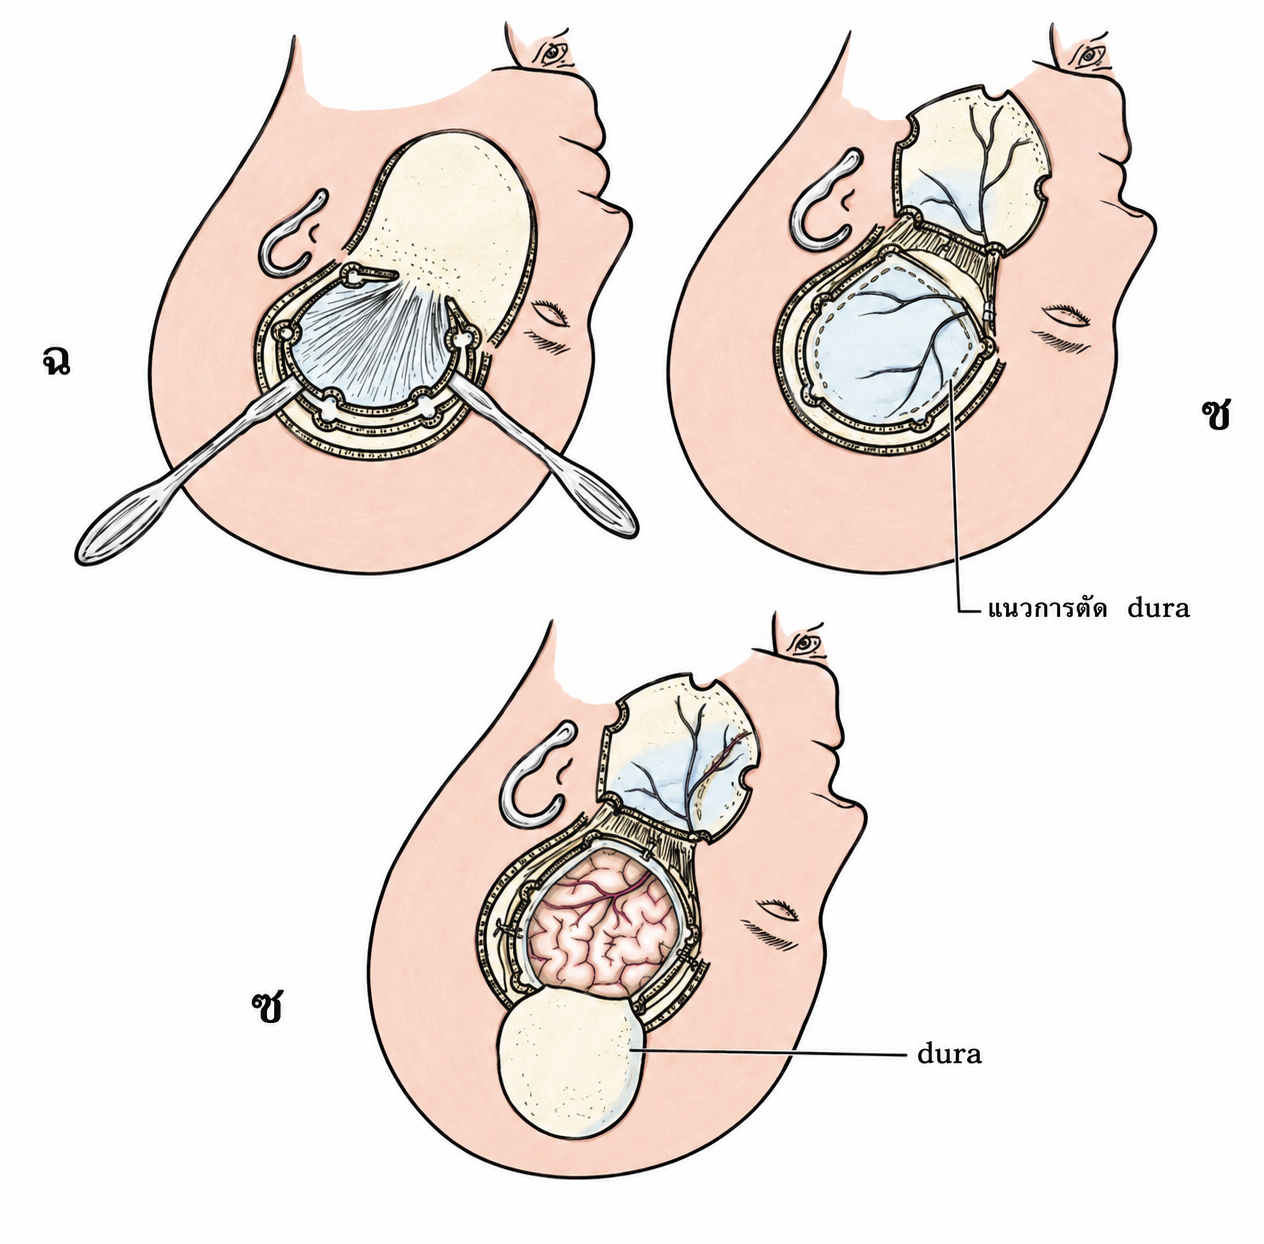
 AI-enhanced and colorized image · Switch to view the original
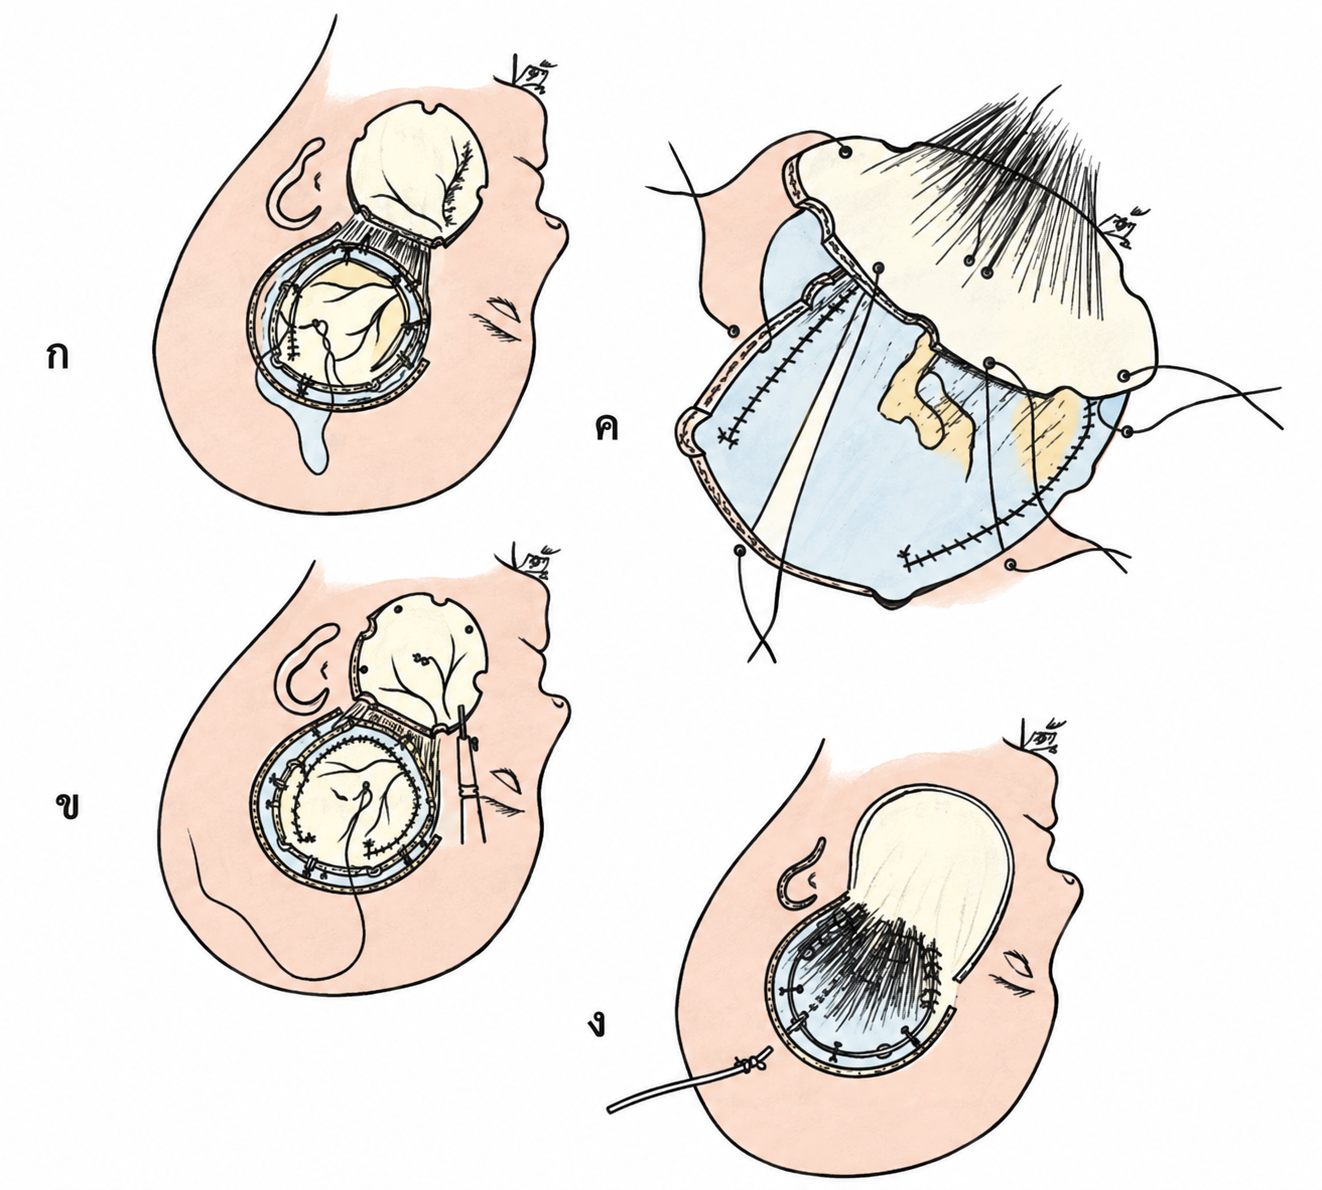
 AI-enhanced and colorized image · Switch to view the original
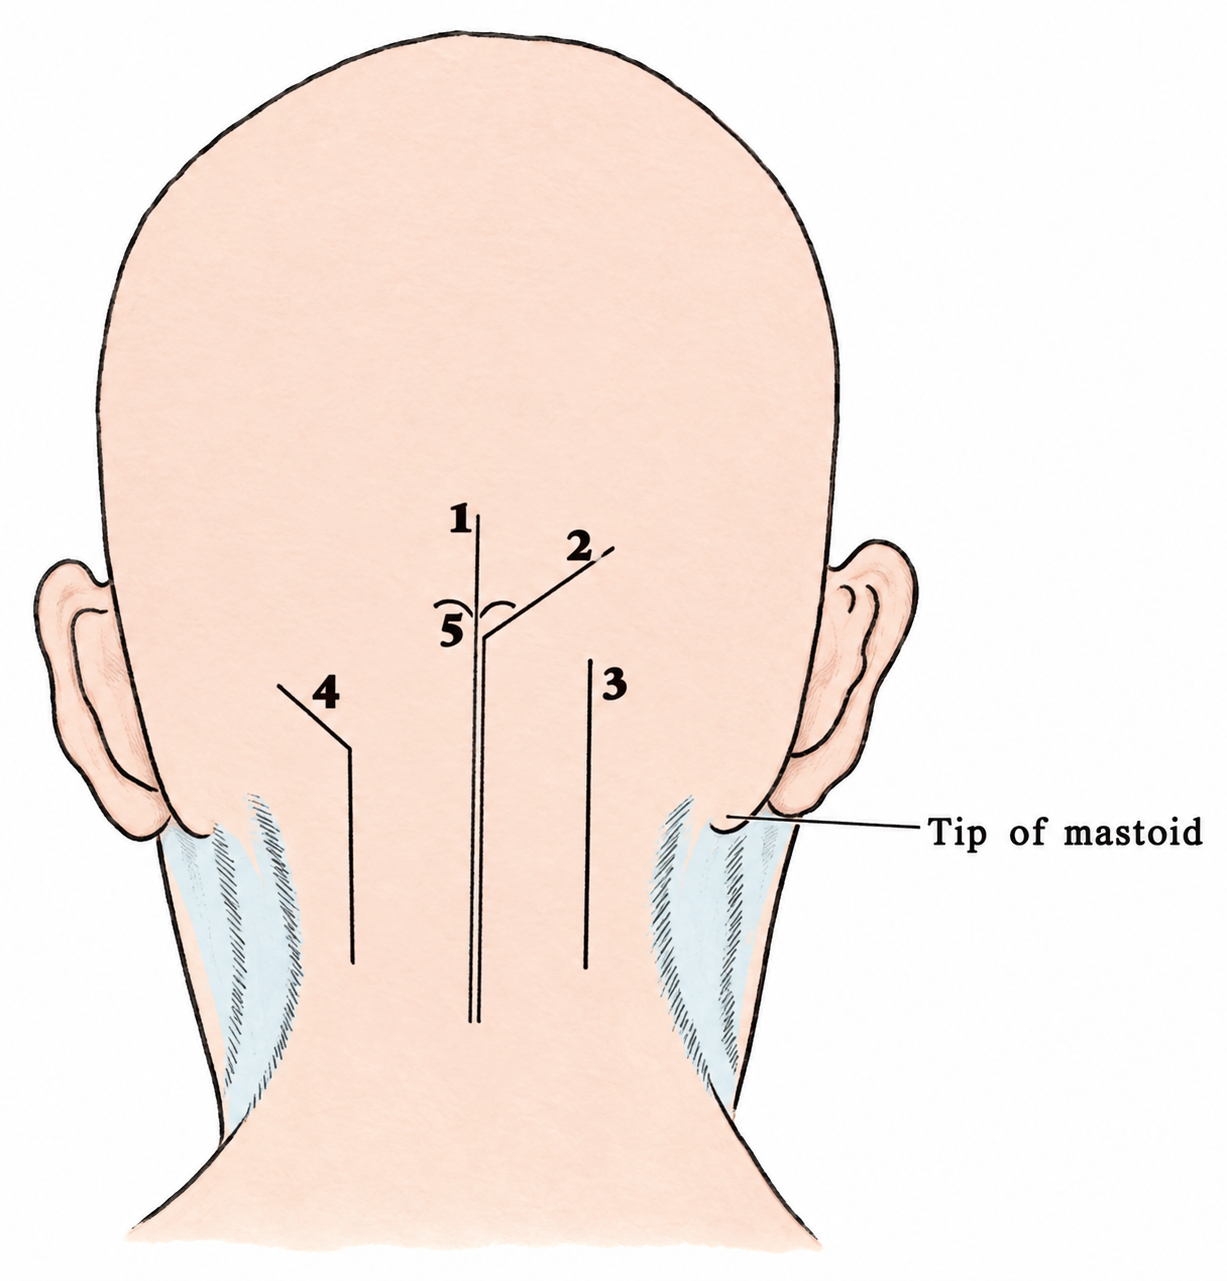
 AI-enhanced and colorized image · Switch to view the original
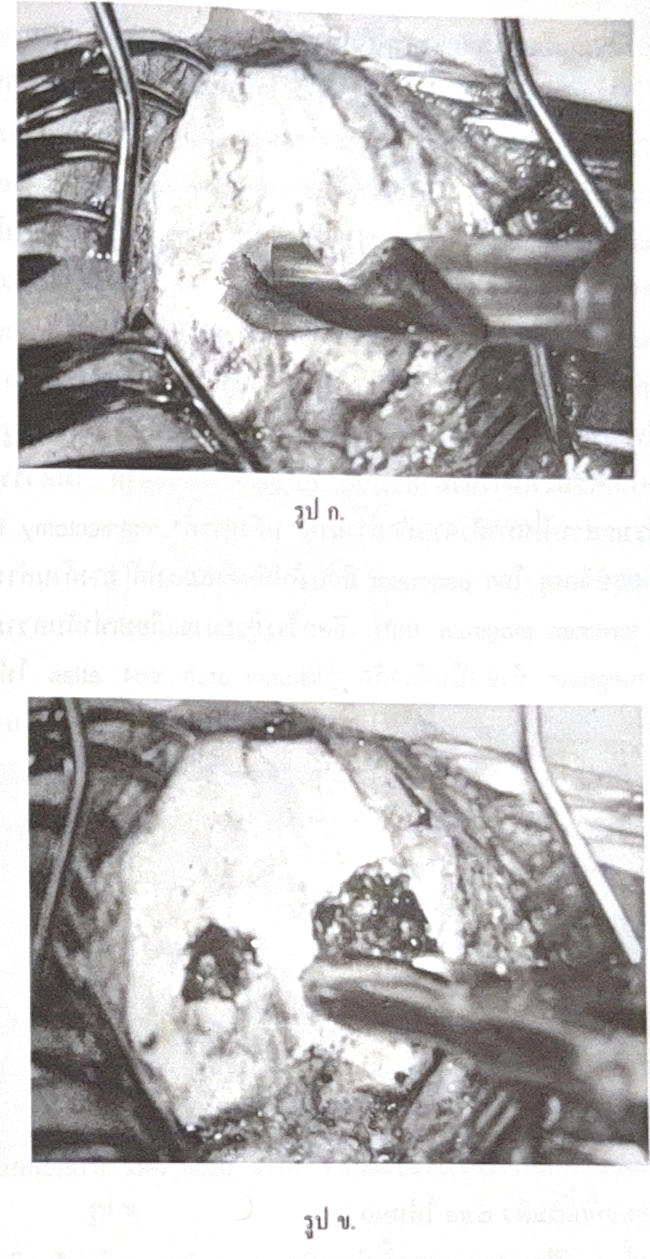
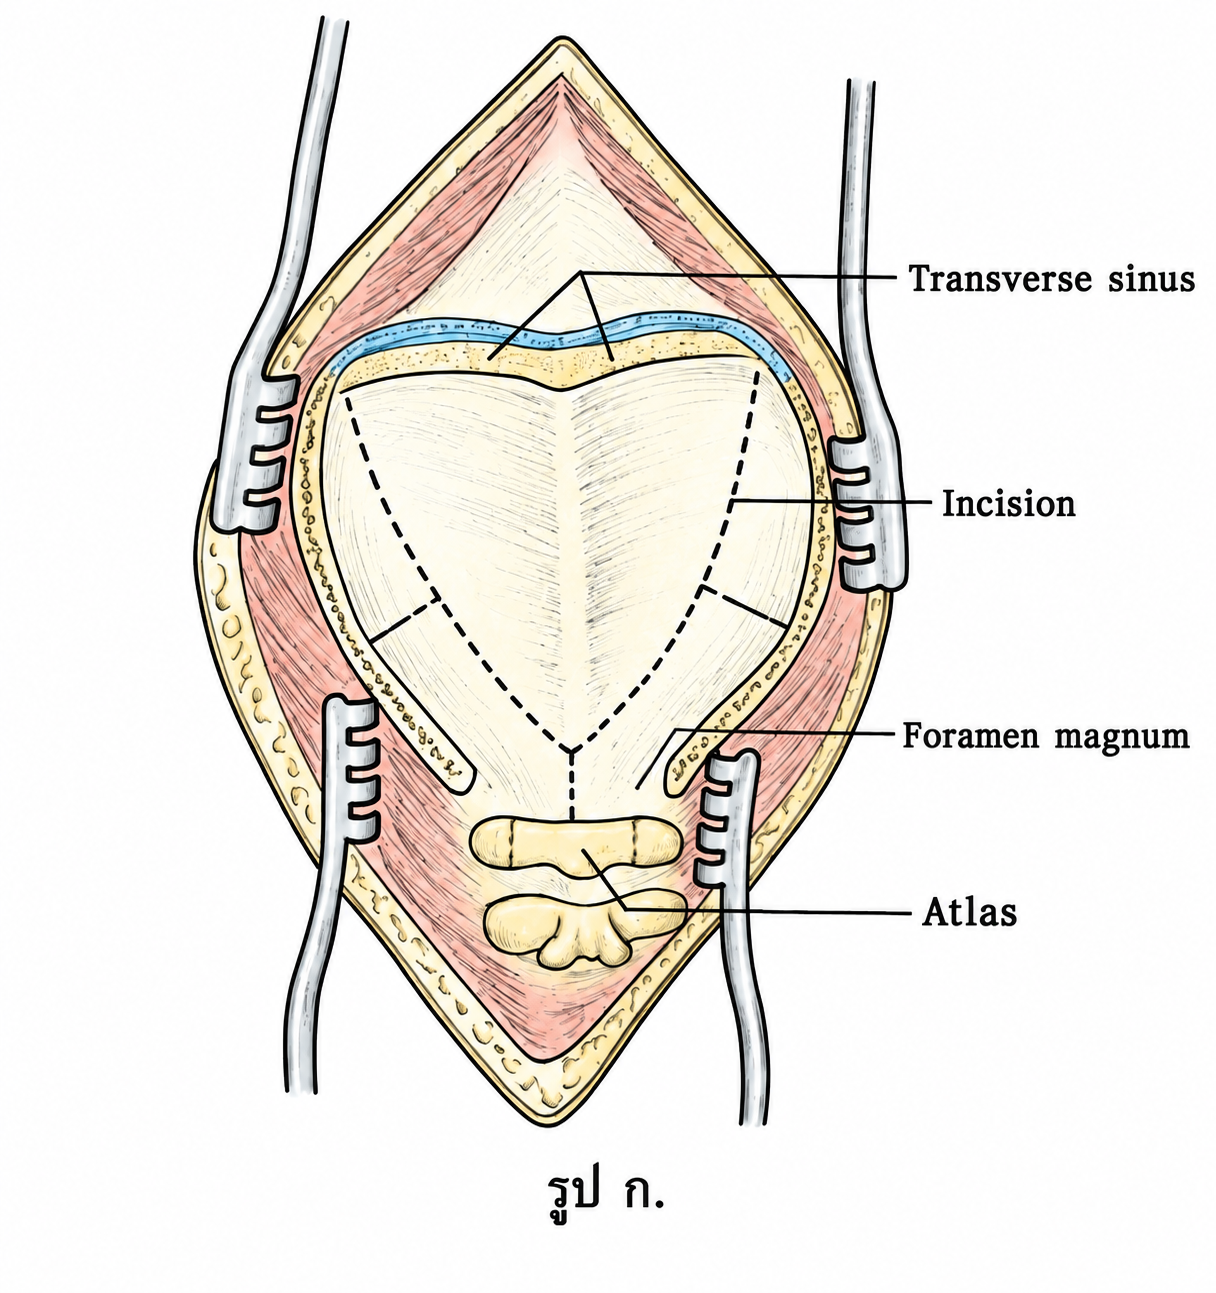
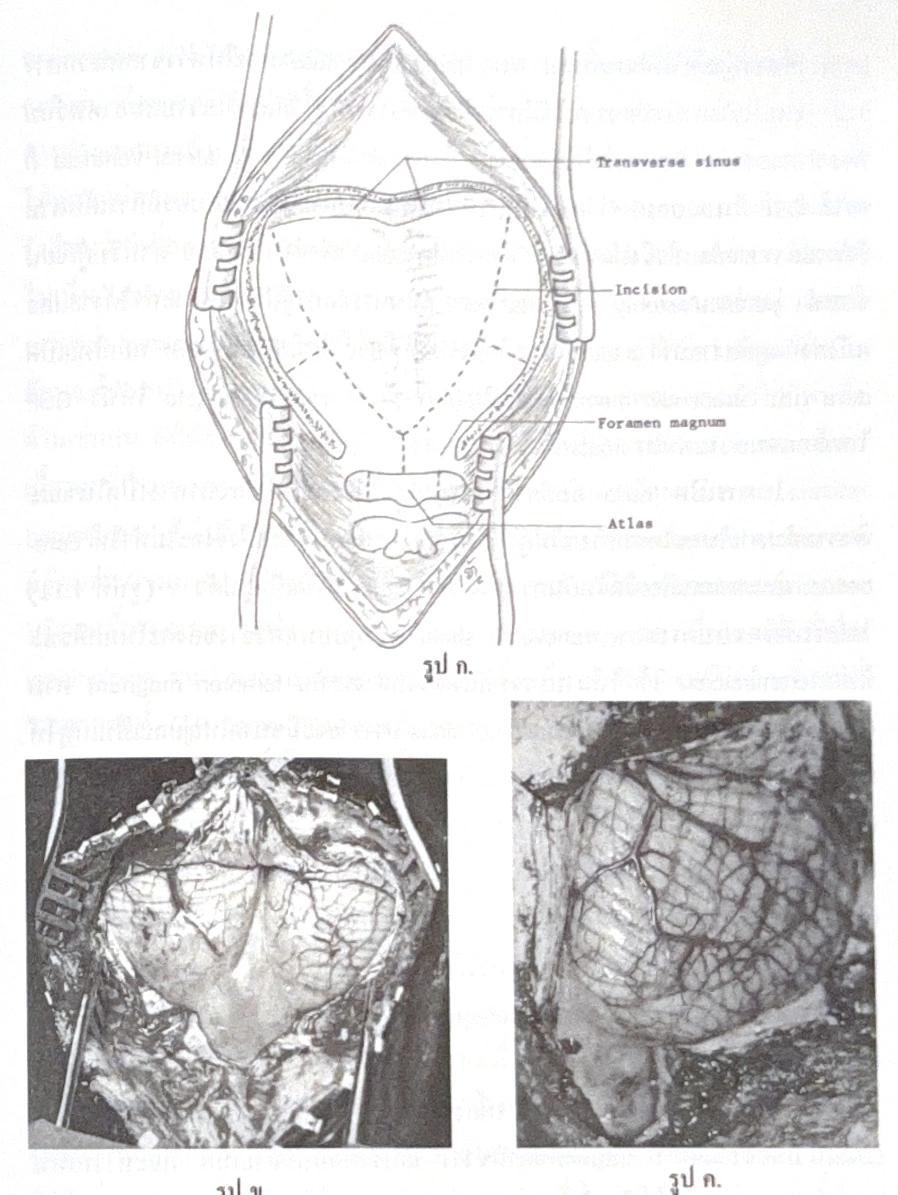
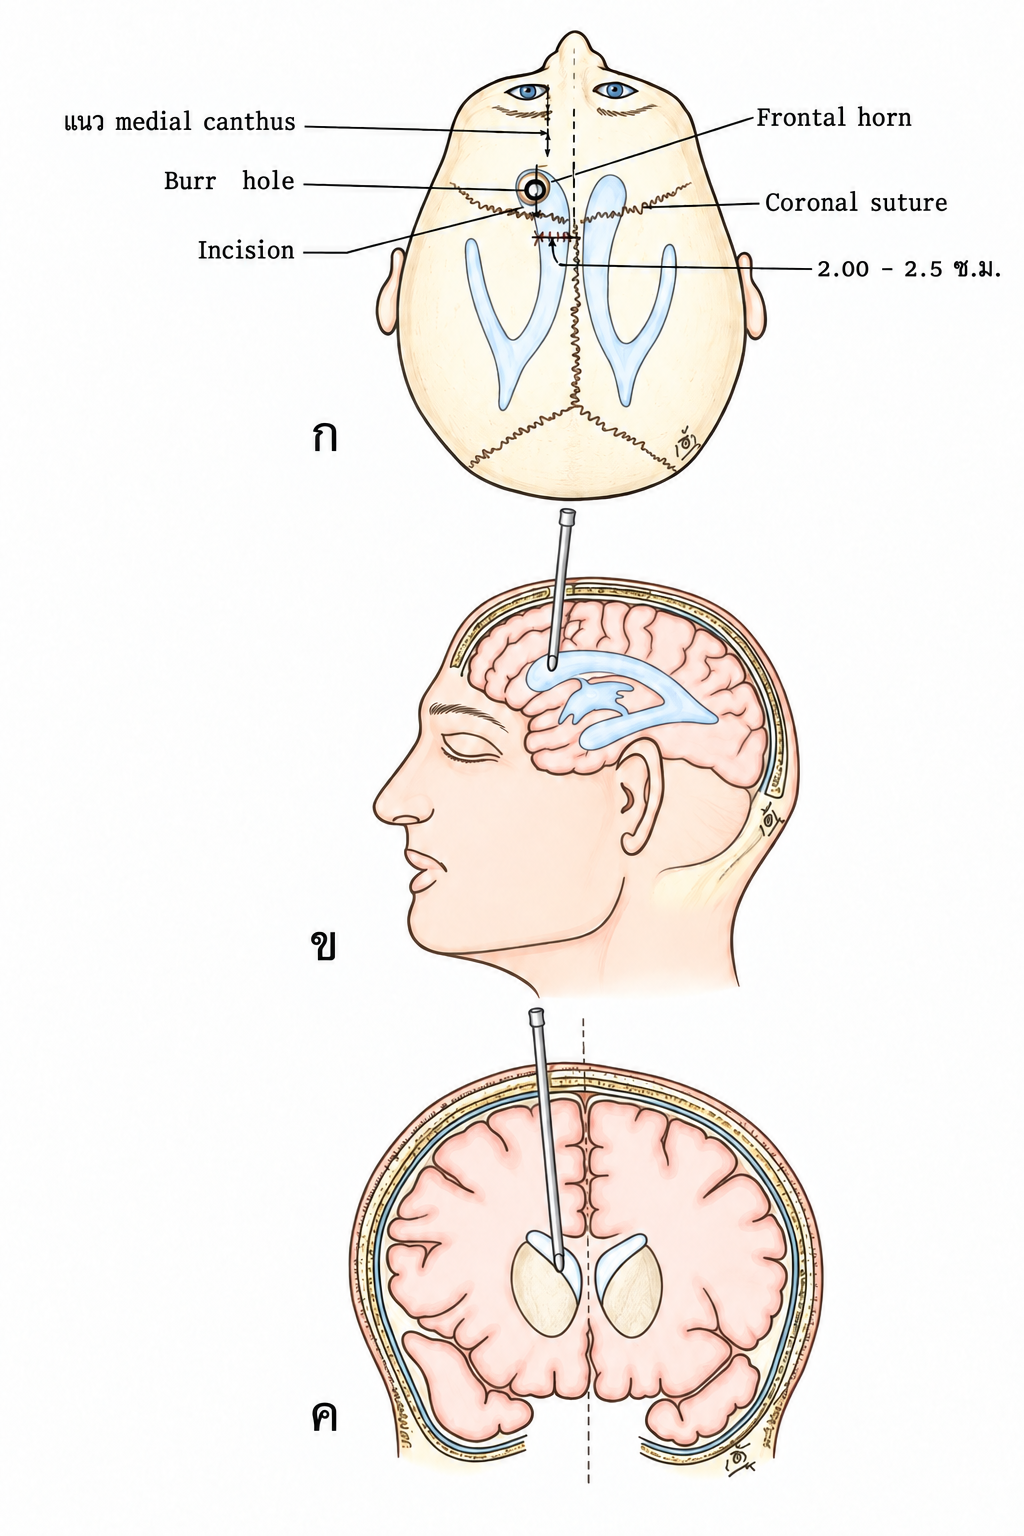
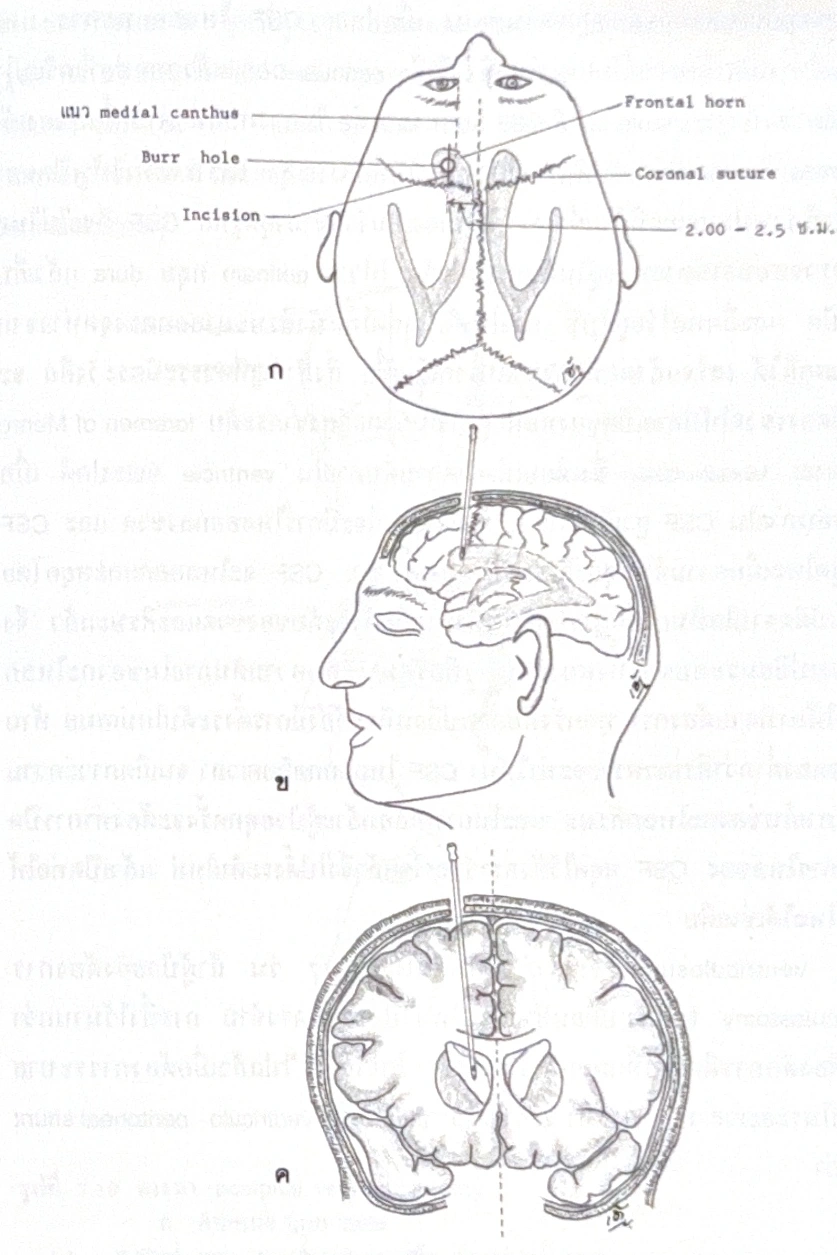 AI-enhanced and colorized image · Switch to view the original
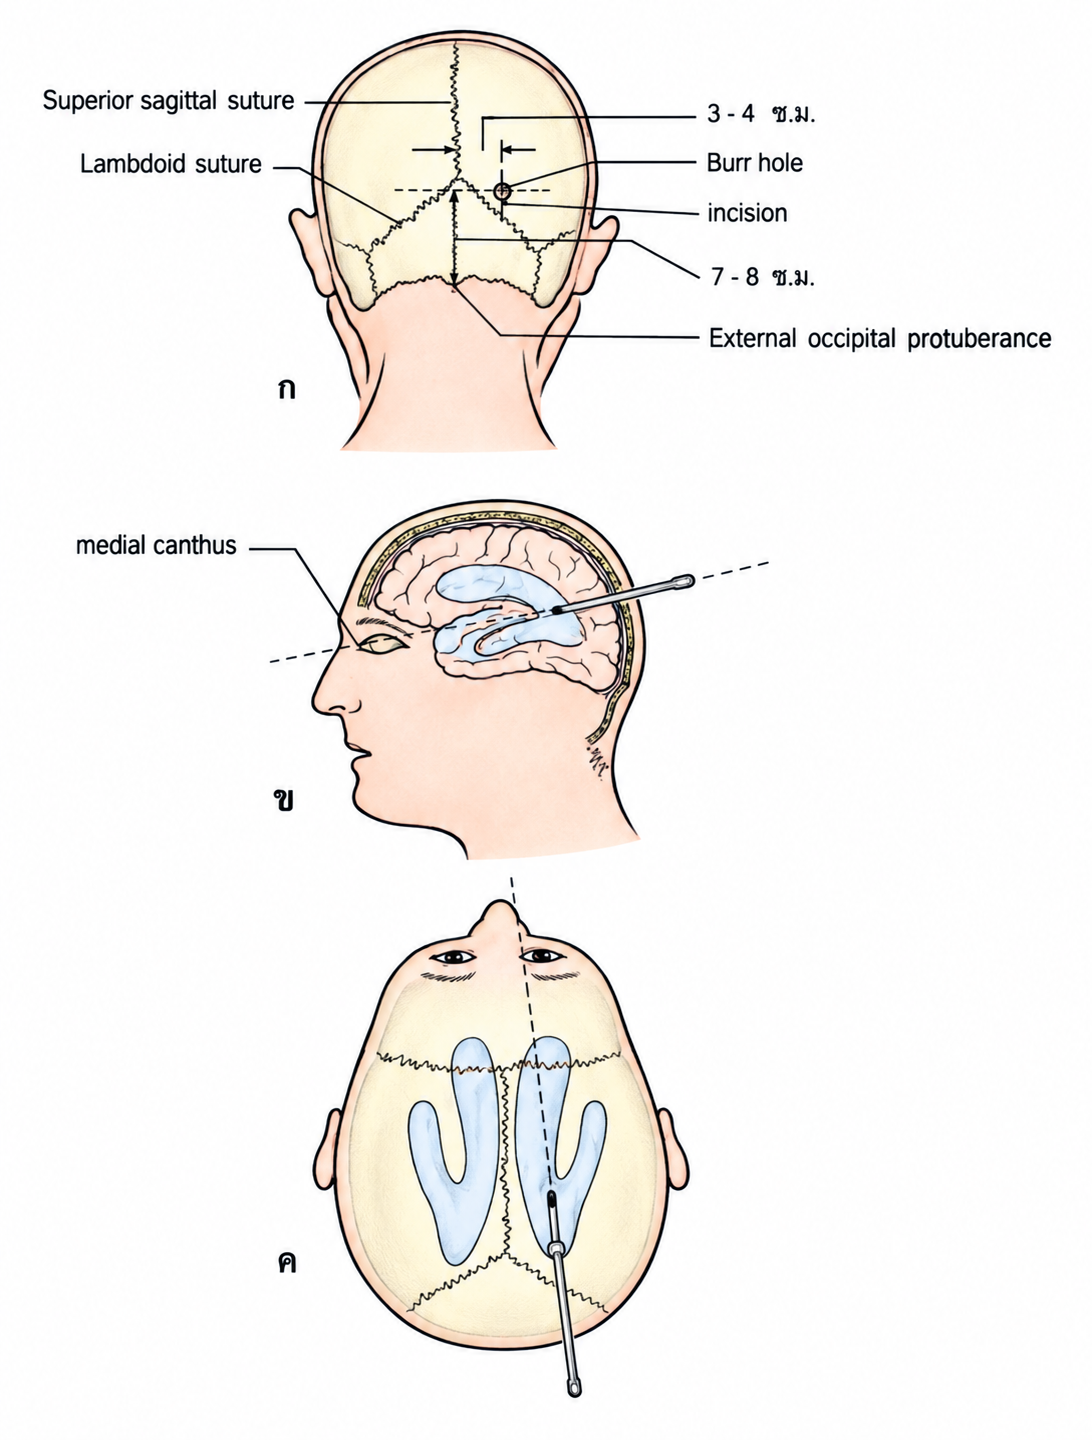
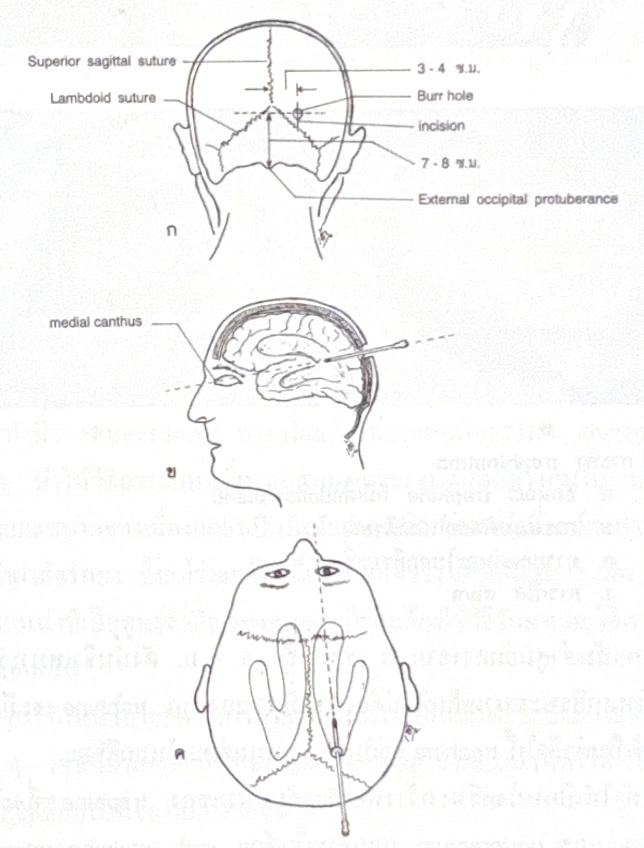 AI-enhanced and colorized image · Switch to view the original
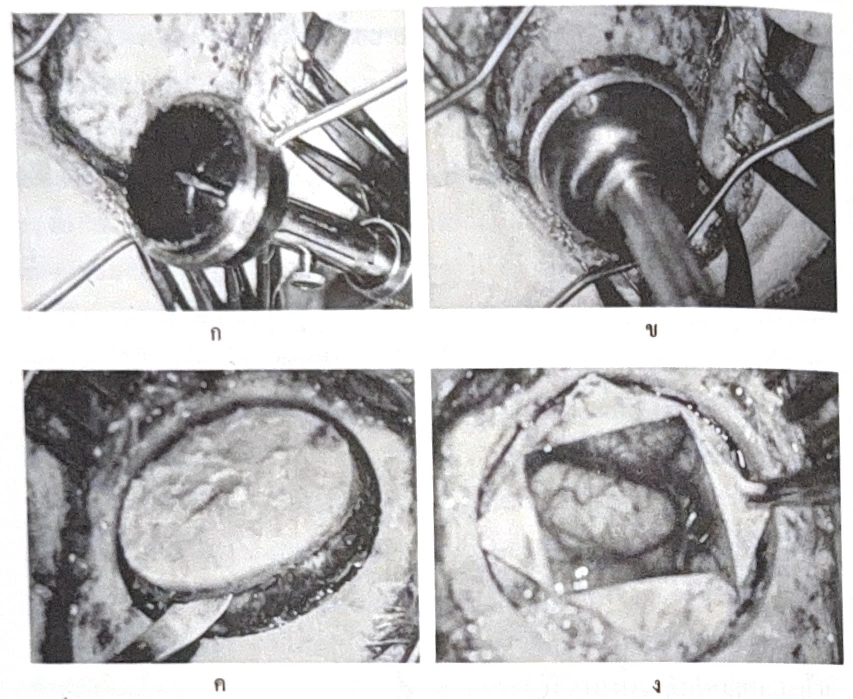
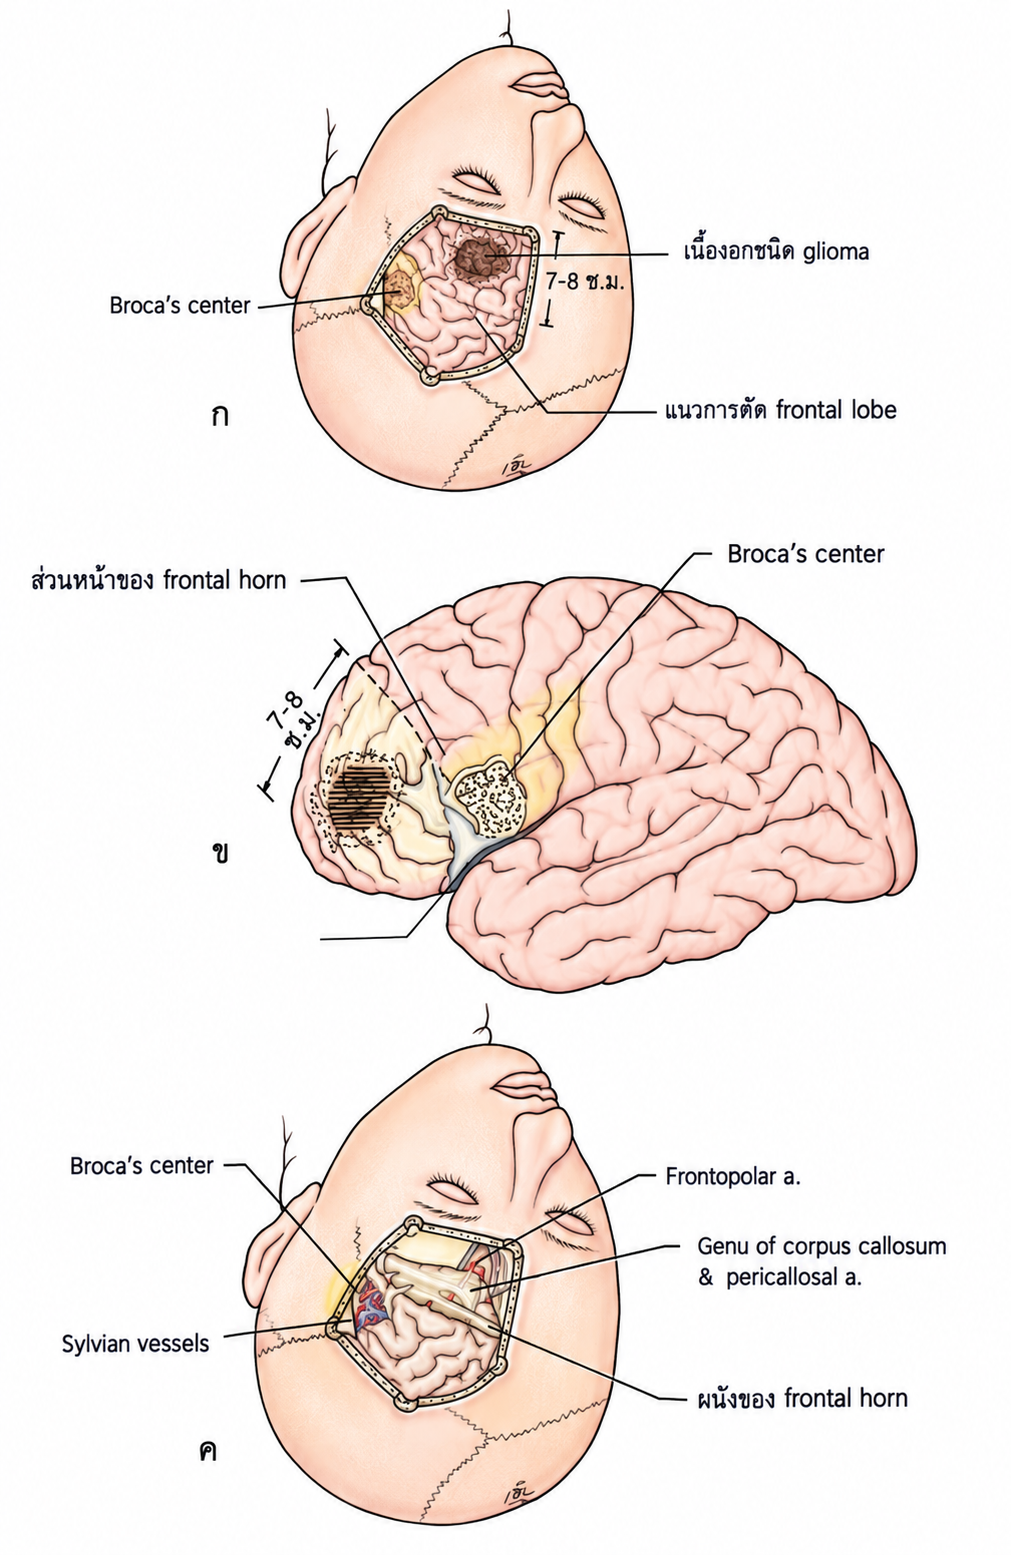
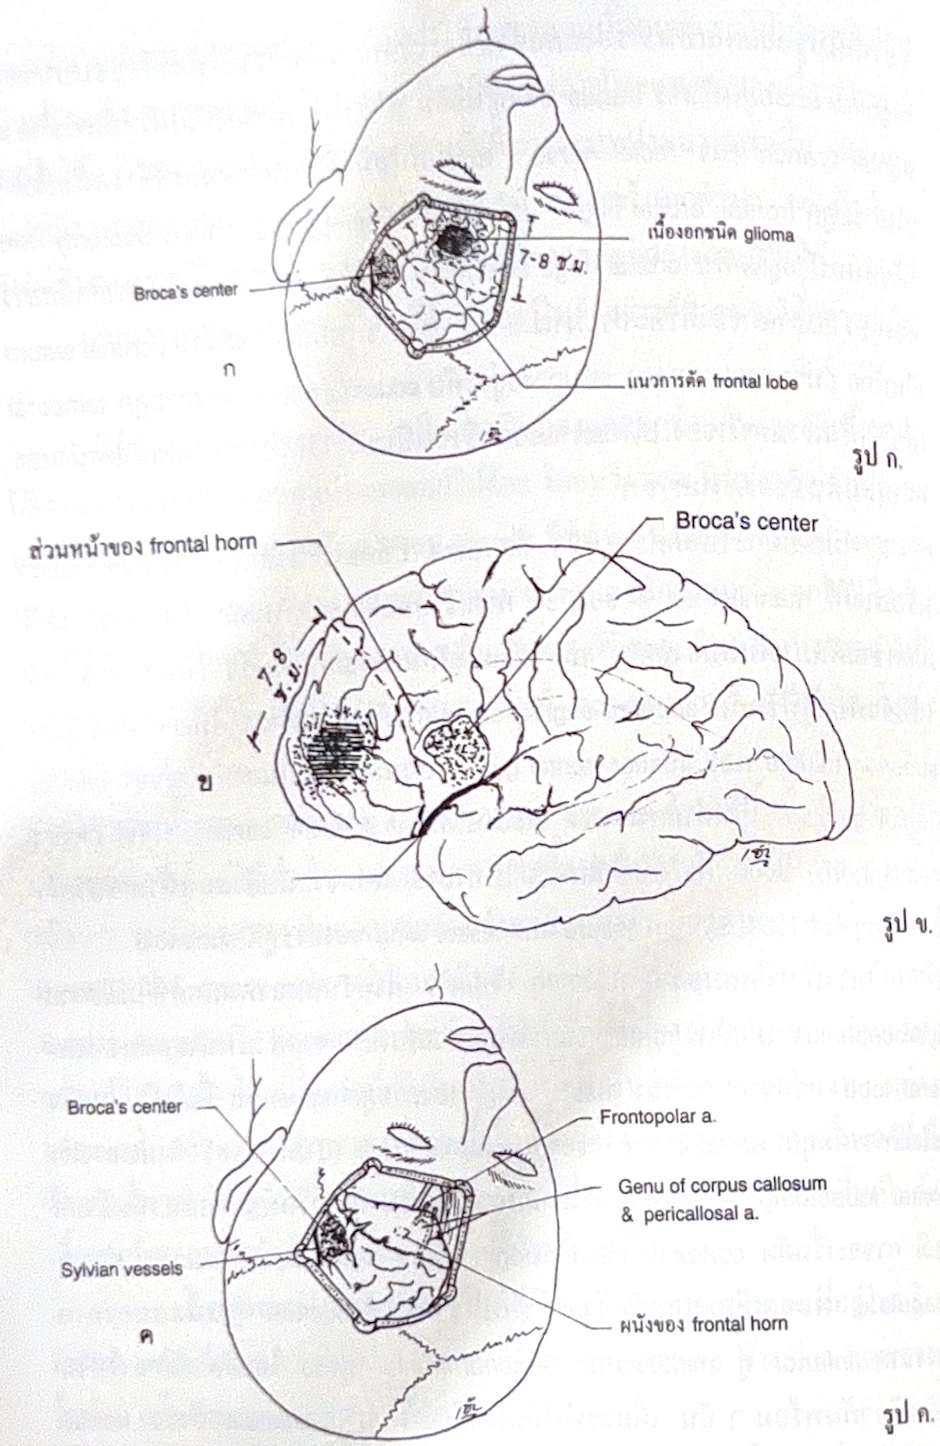 Image enhanced and colorized with AI · Switch to view the original image
 Image enhanced and colorized with AI · Switch to view the original image
 Image enhanced and colorized with AI · Switch to view the original image
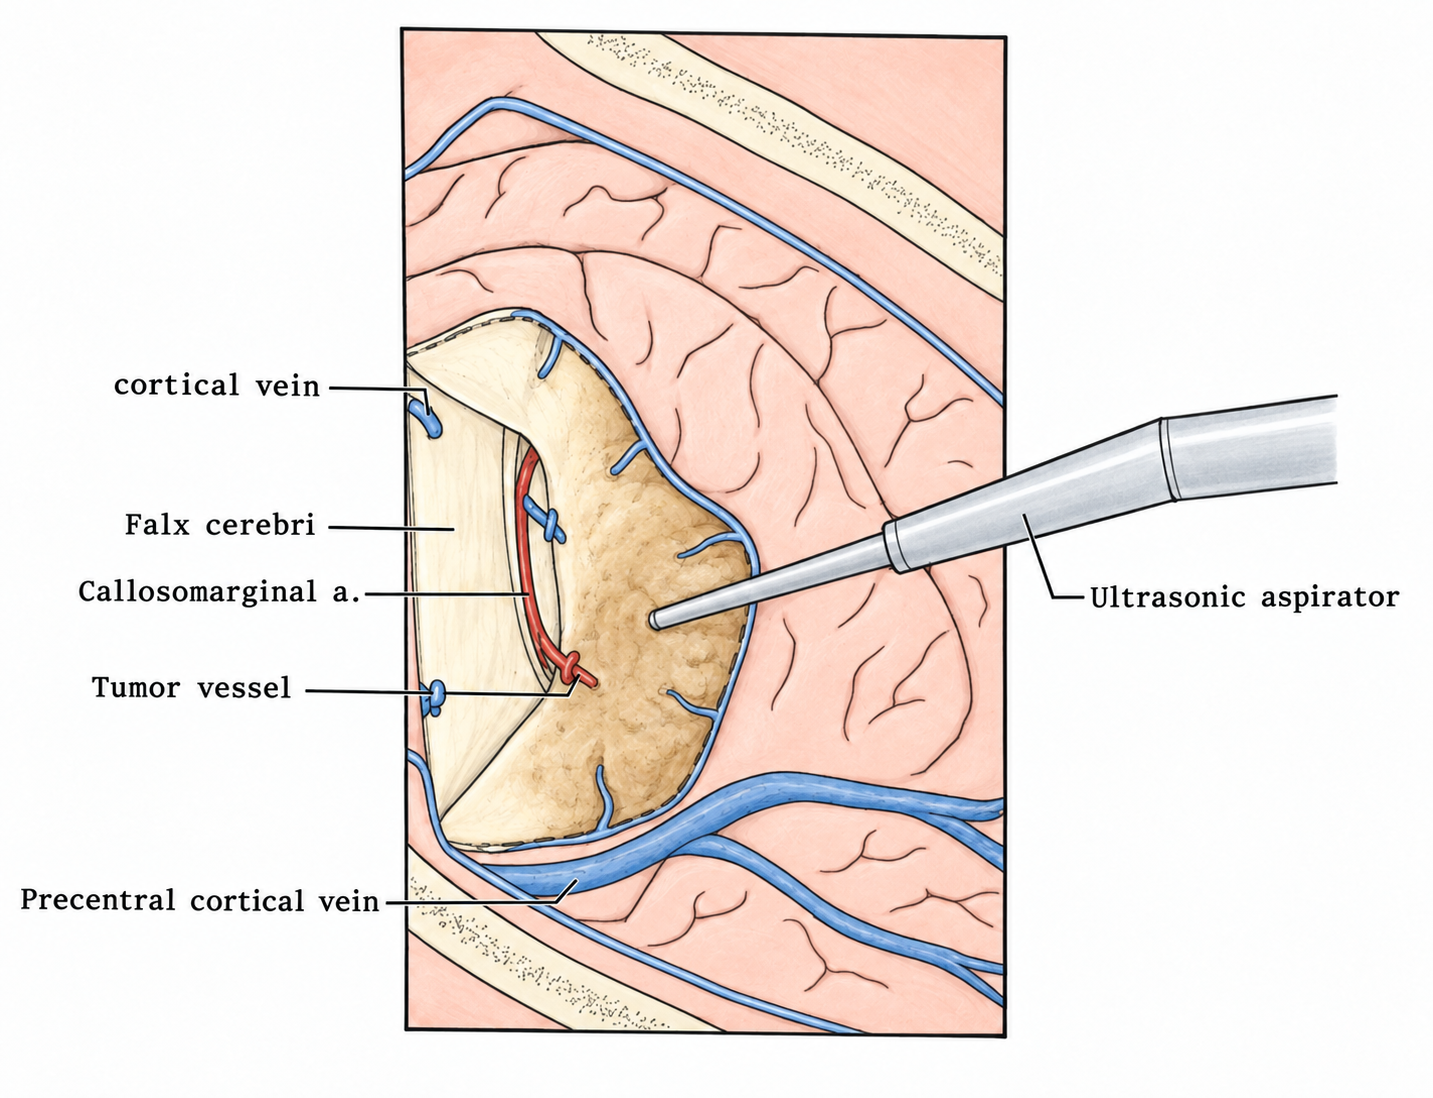
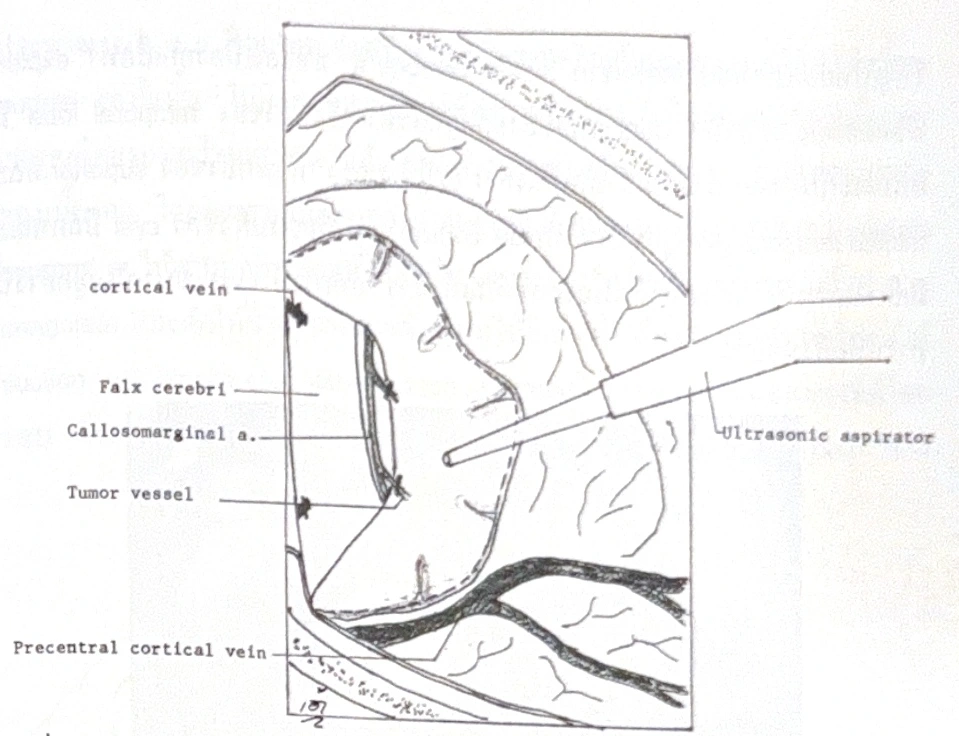 Image enhanced and colorized with AI · Switch to view the original image
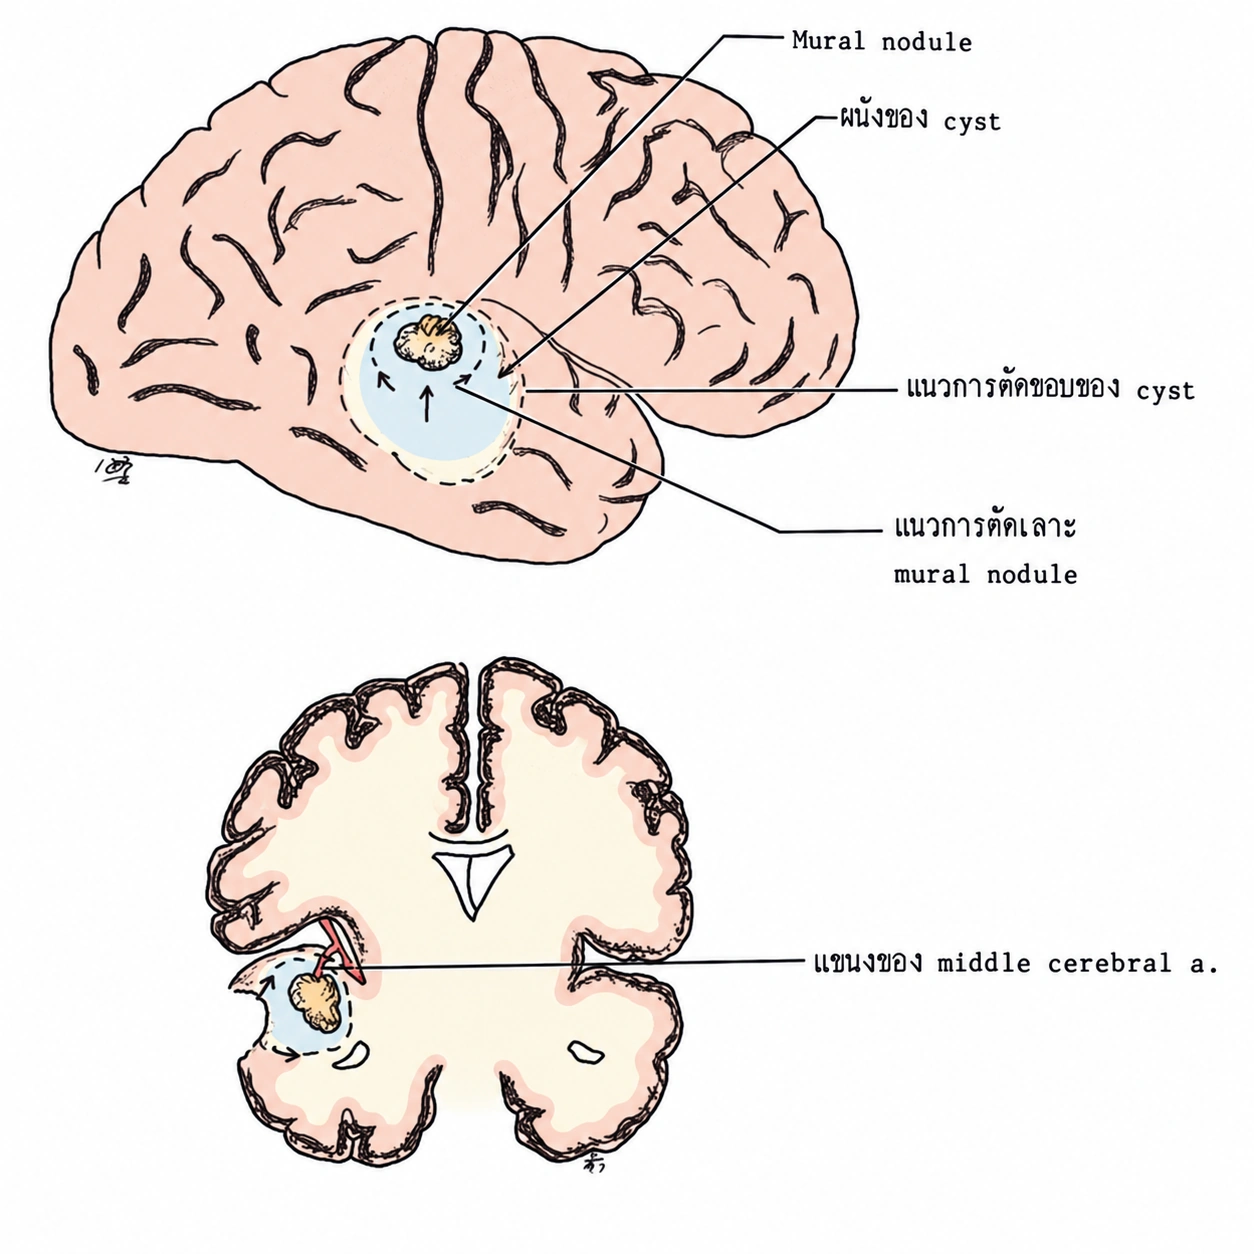
 Image enhanced and colorized with AI · Switch to view the original image
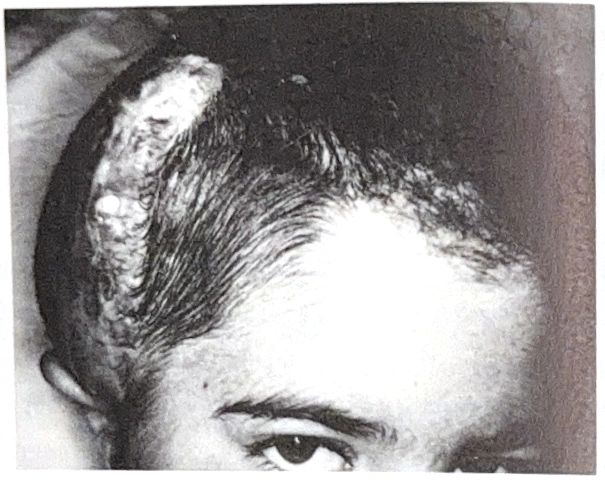
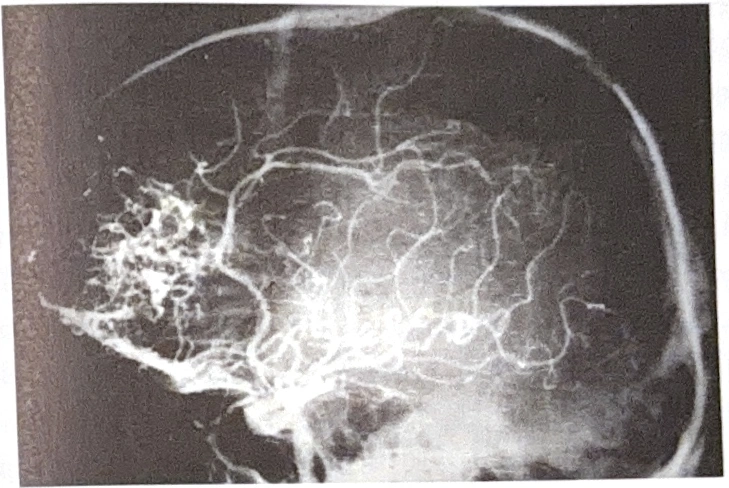
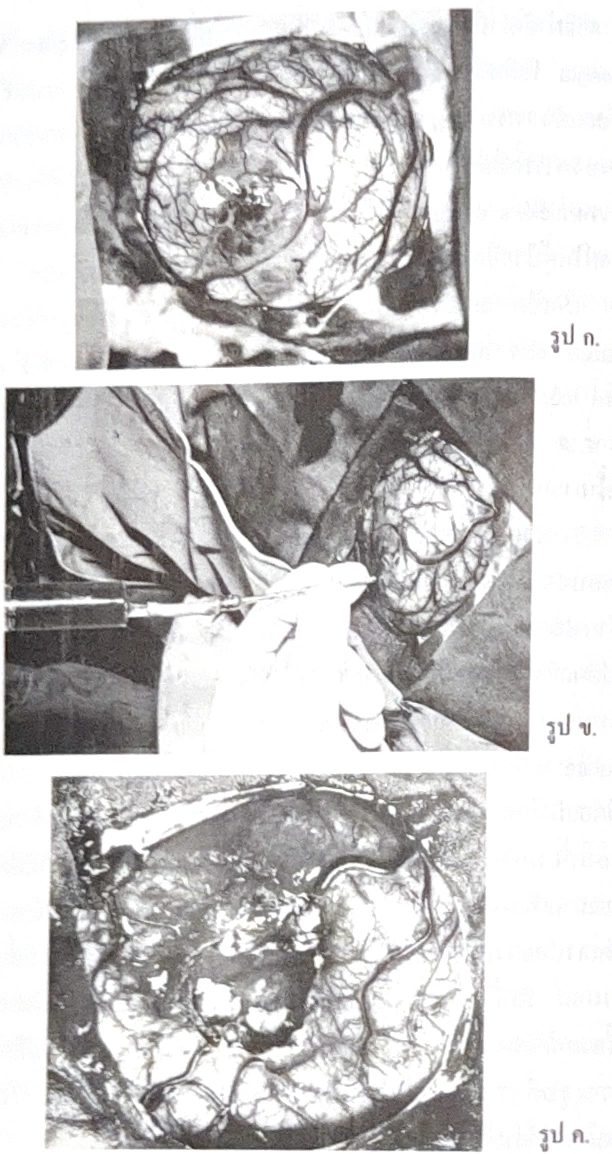
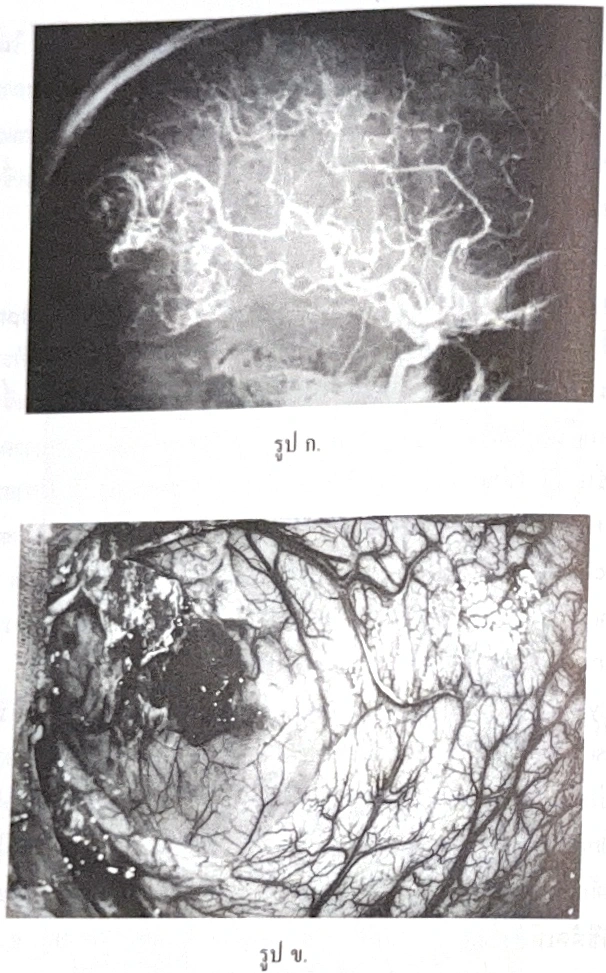
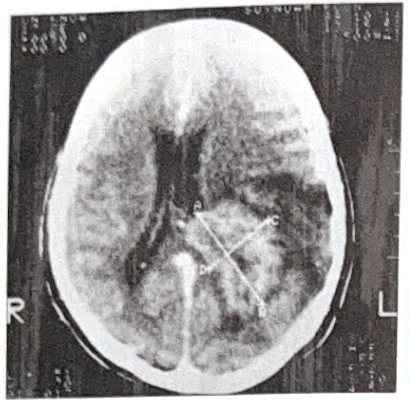
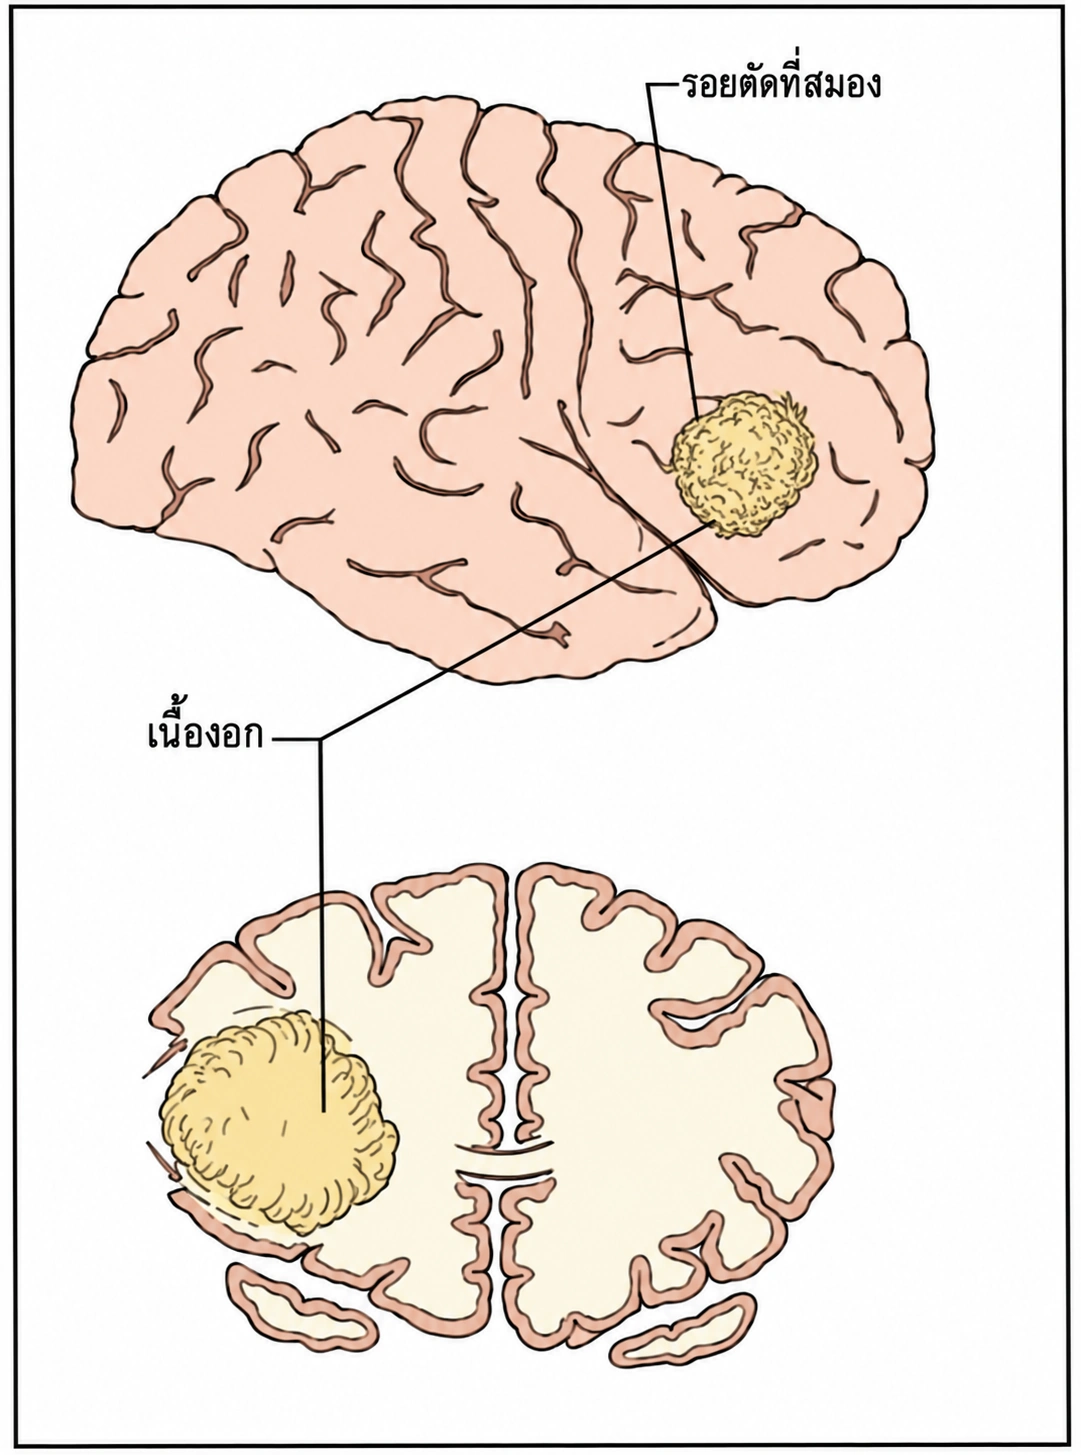
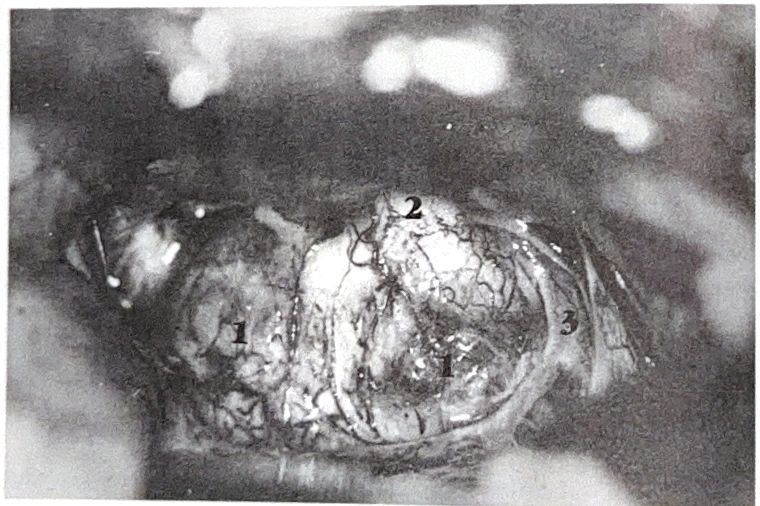
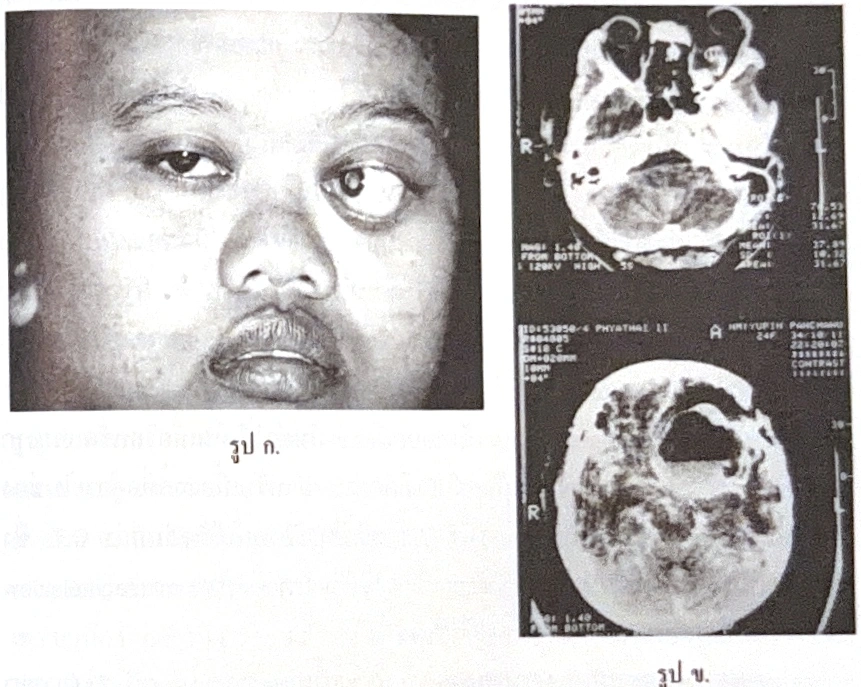
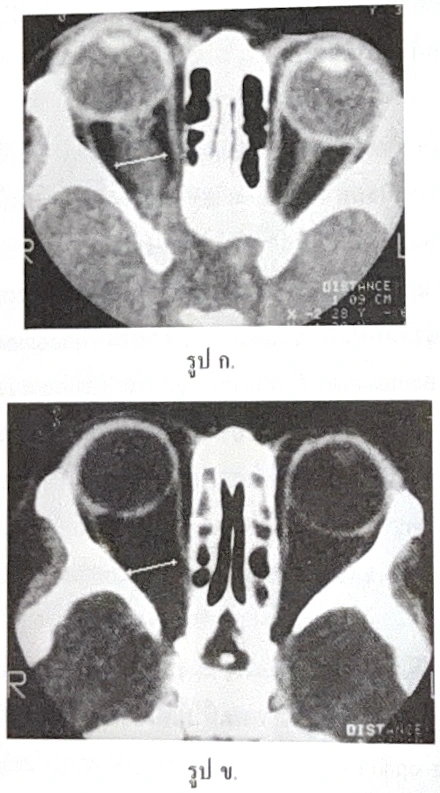
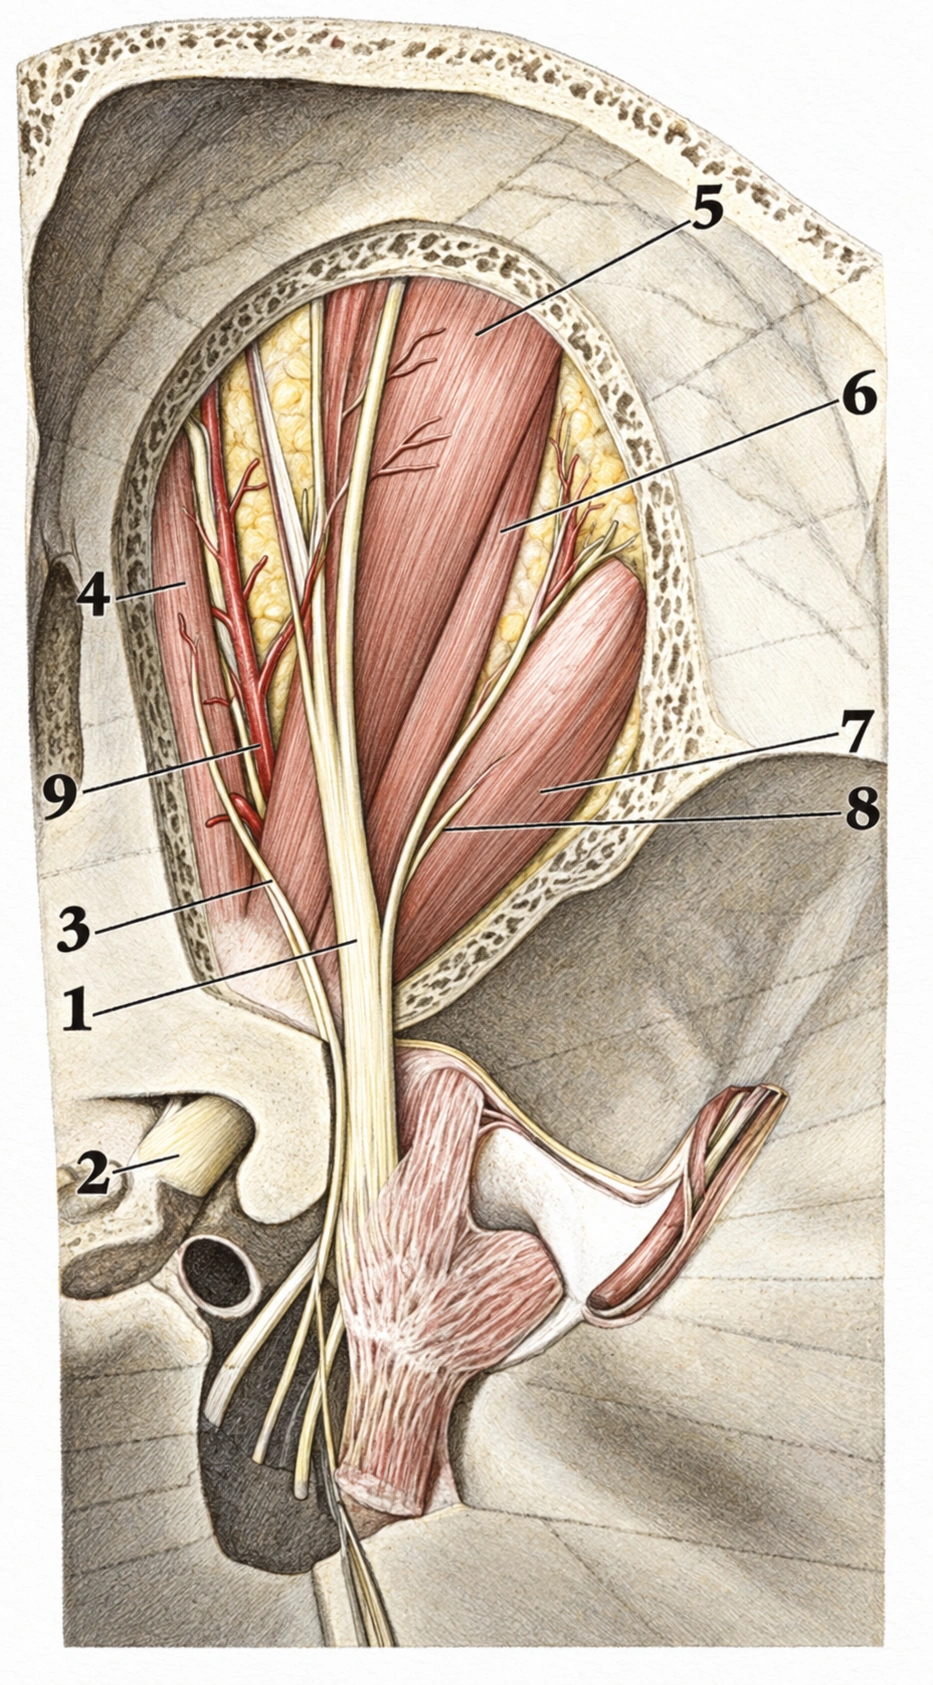
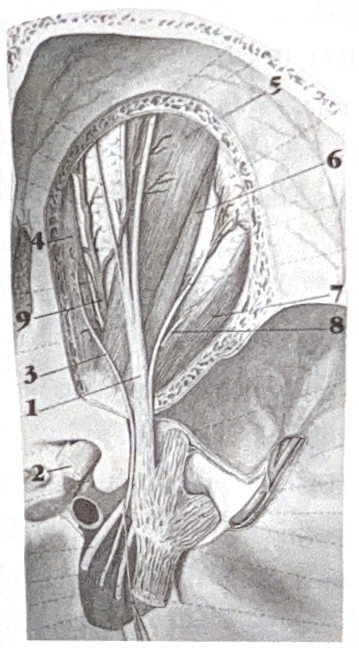 AI-enhanced and colorized image · Switch to view the original
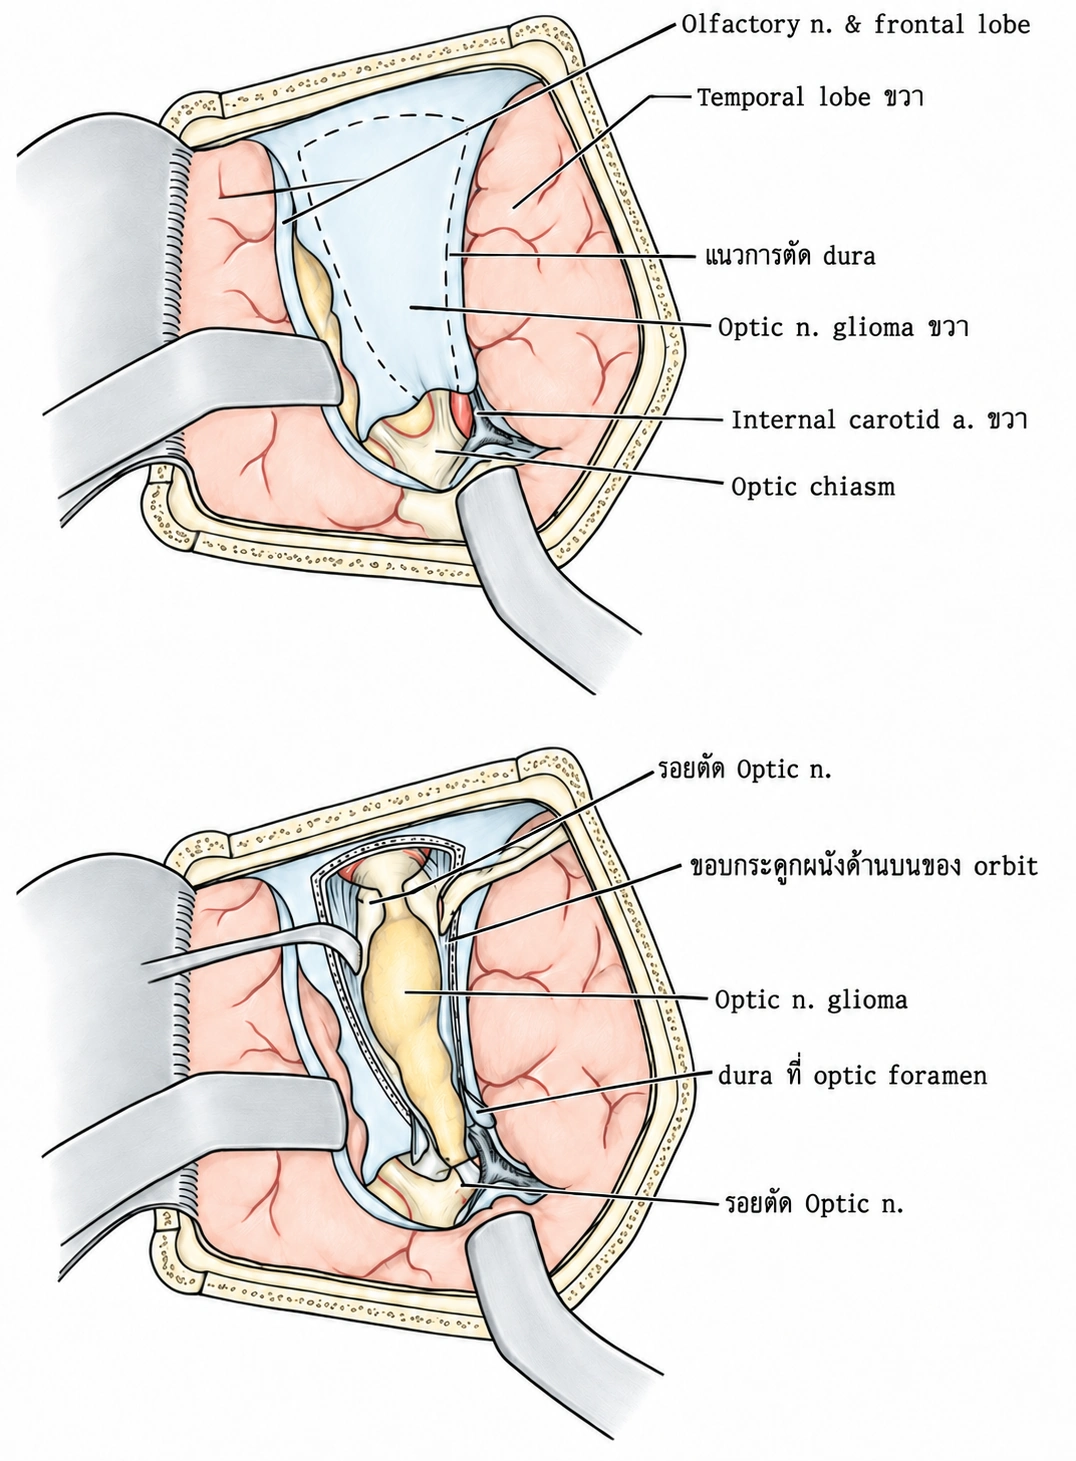
 AI-enhanced and colorized image · Switch to view the original
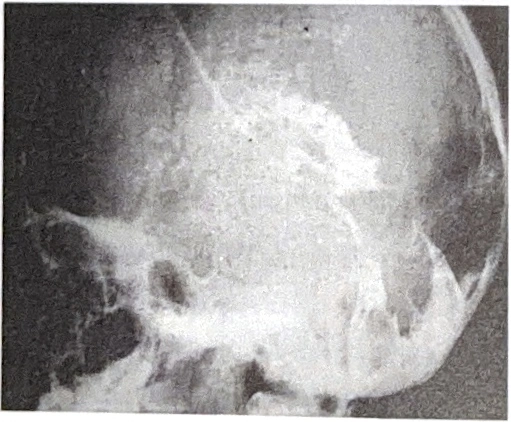
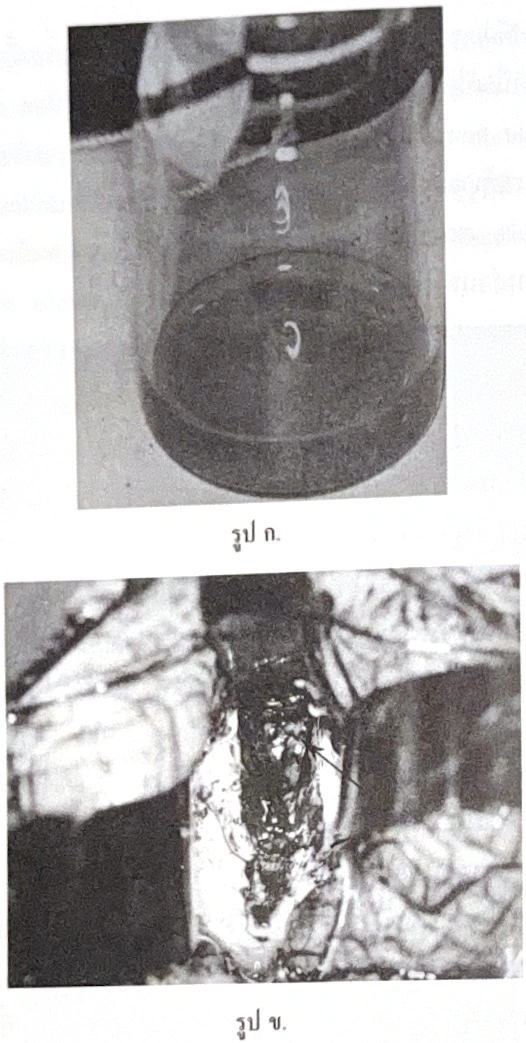
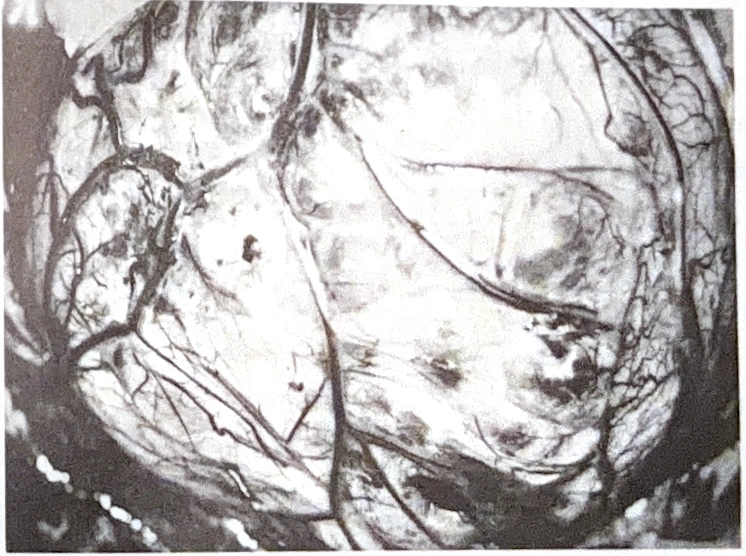
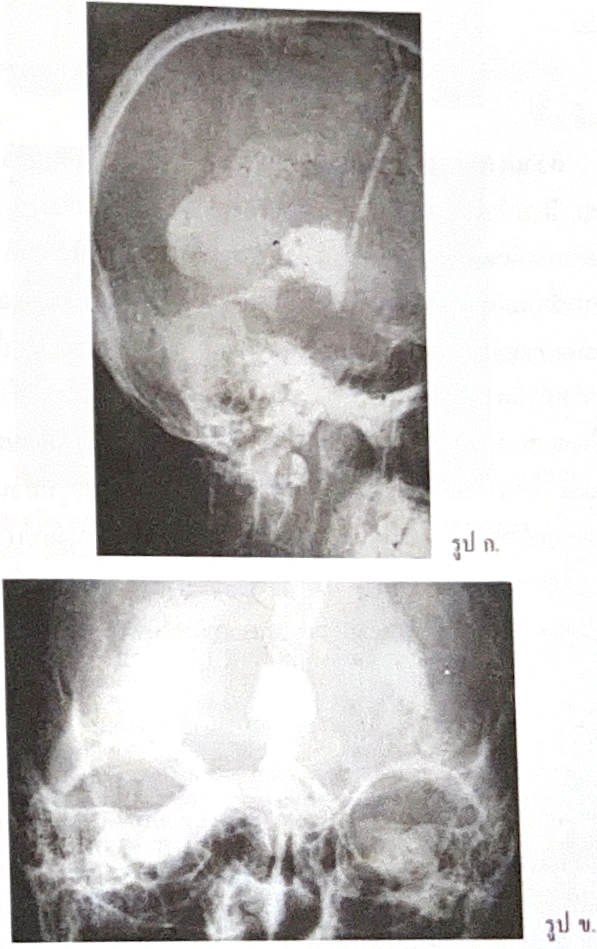
 AI-enhanced and colorized image · Switch to view the original
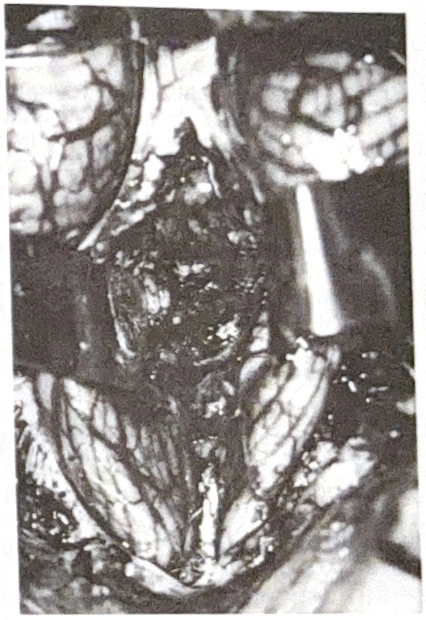
 AI-enhanced and colorized image · Switch to view the original
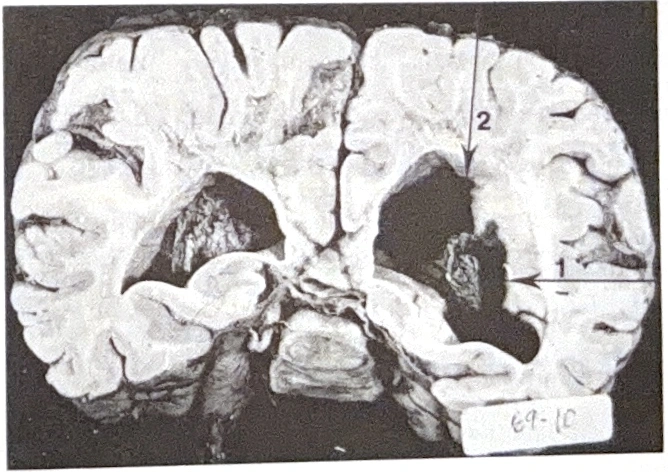
 AI-enhanced and colorized image · Switch to view the original
 AI-enhanced and colorized image · Switch to view the original
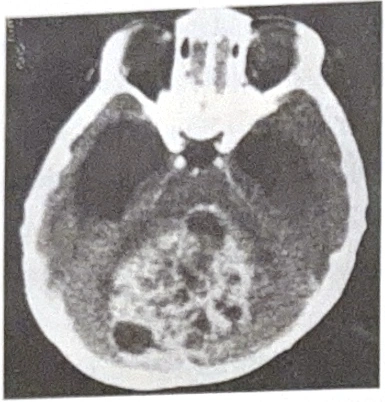
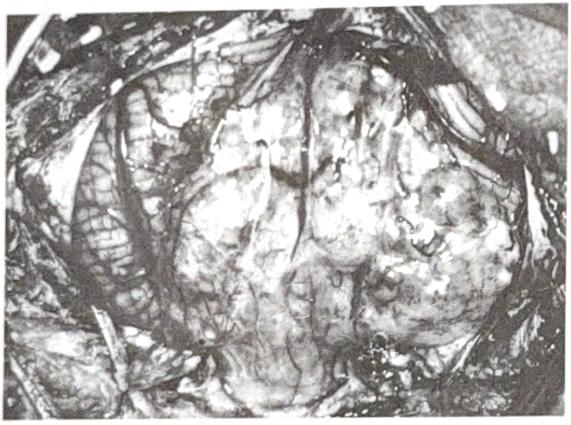
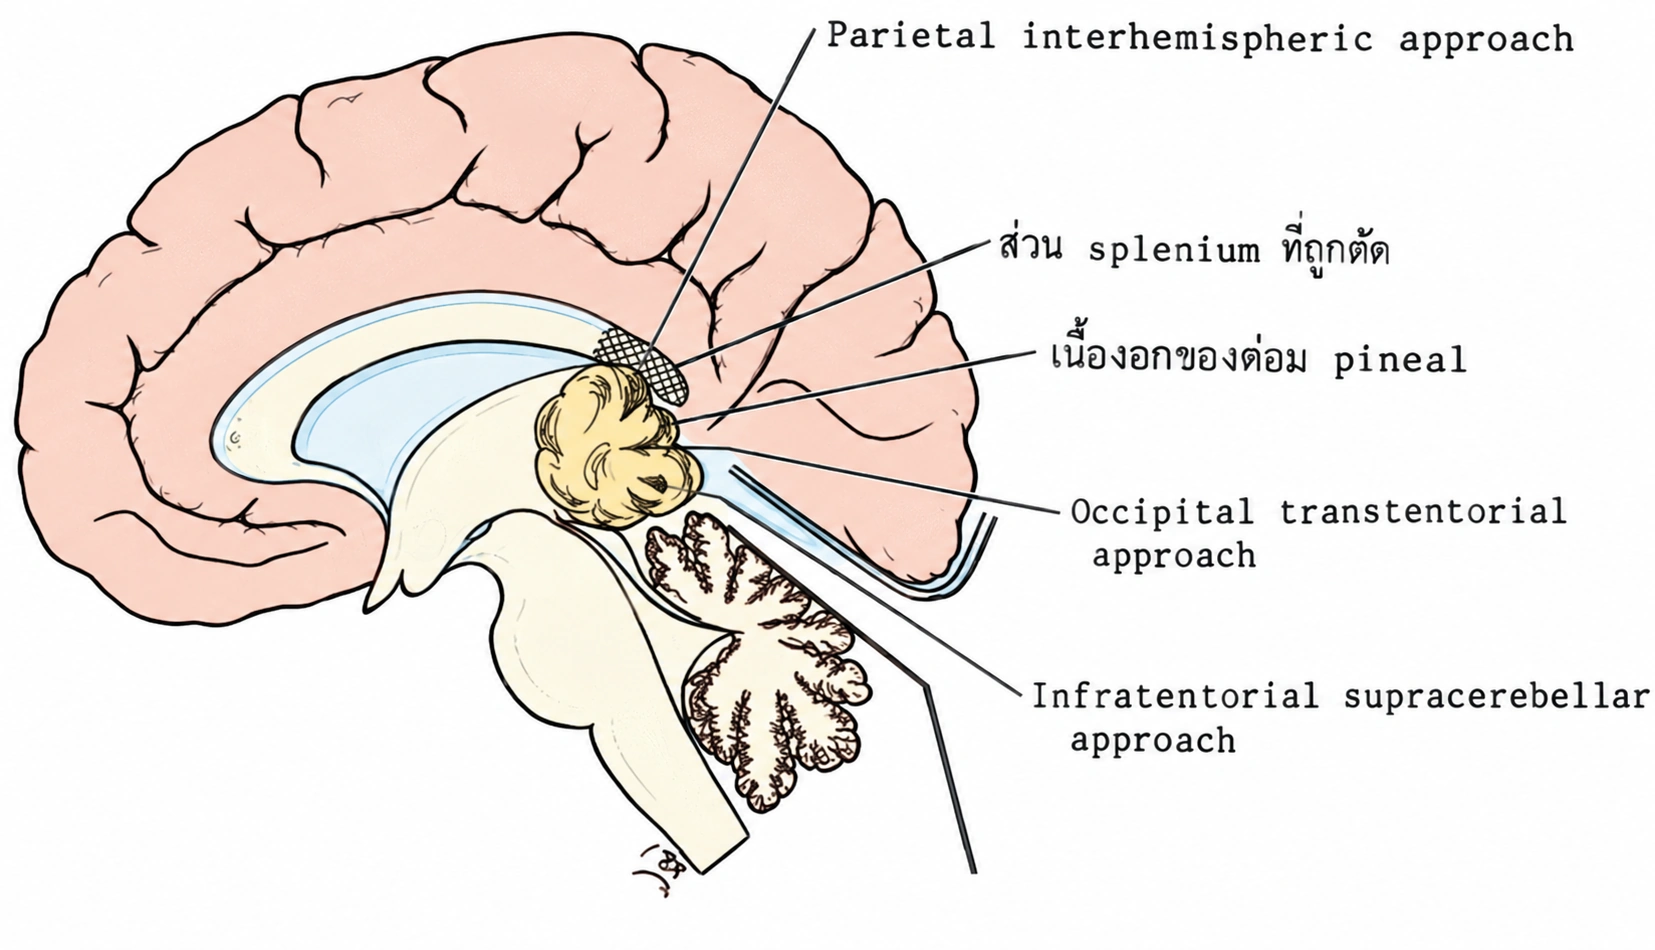
 AI-enhanced and colorized image · Switch to view the original
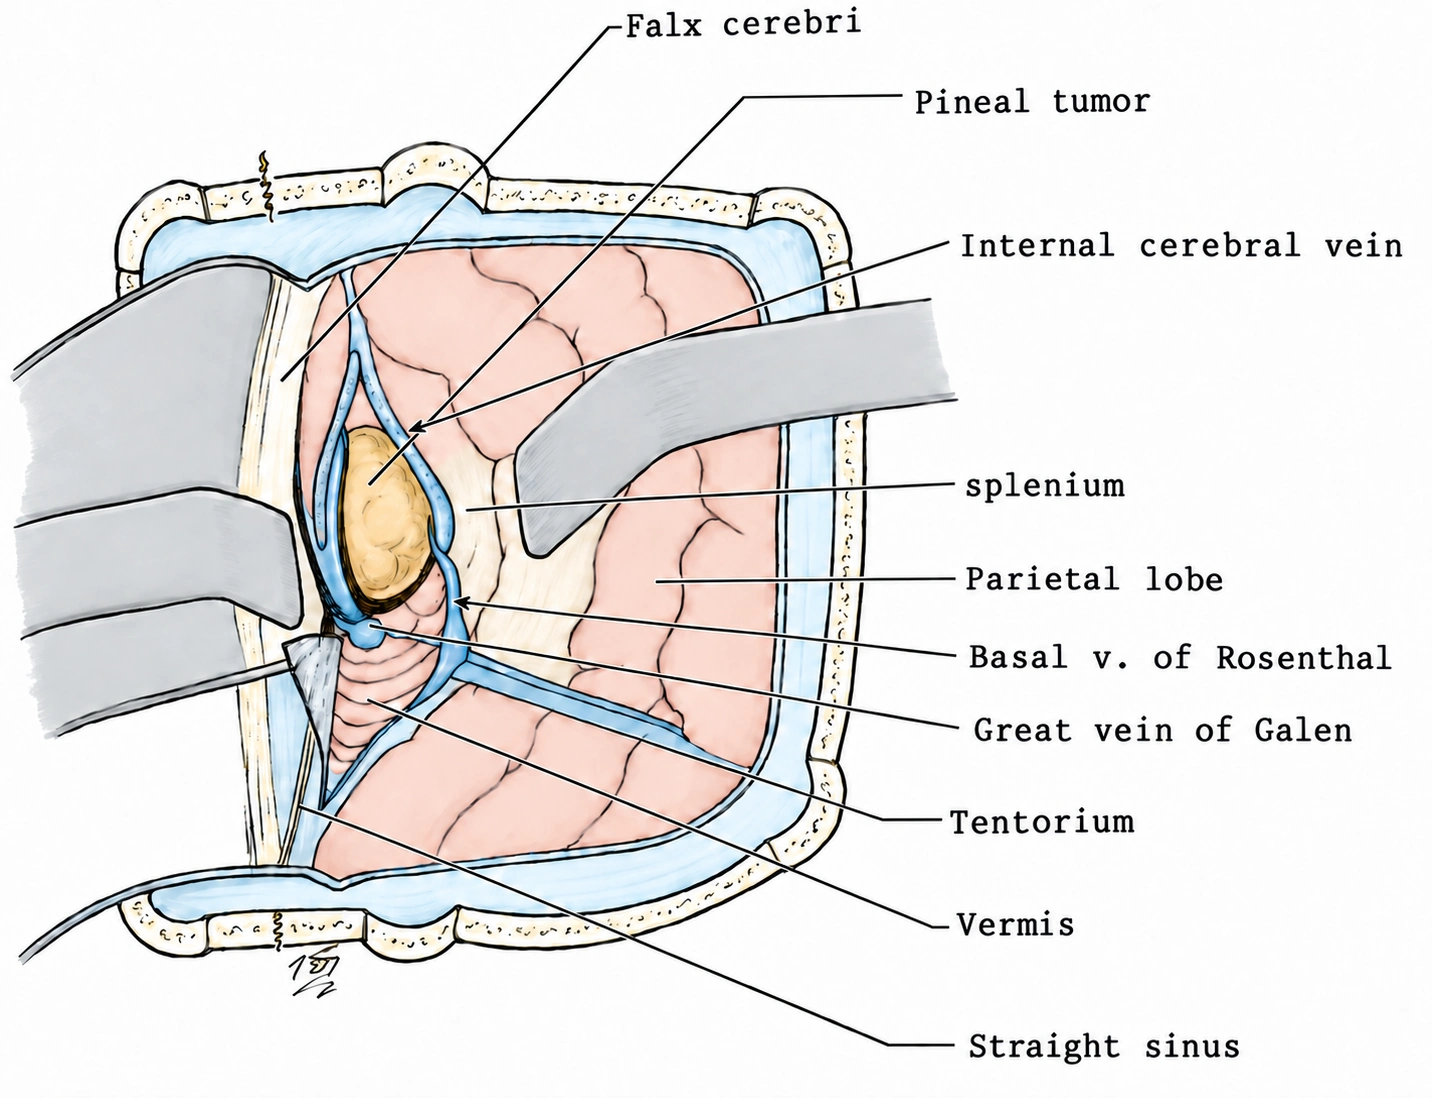
 AI-enhanced and colorized image · Switch to view the original
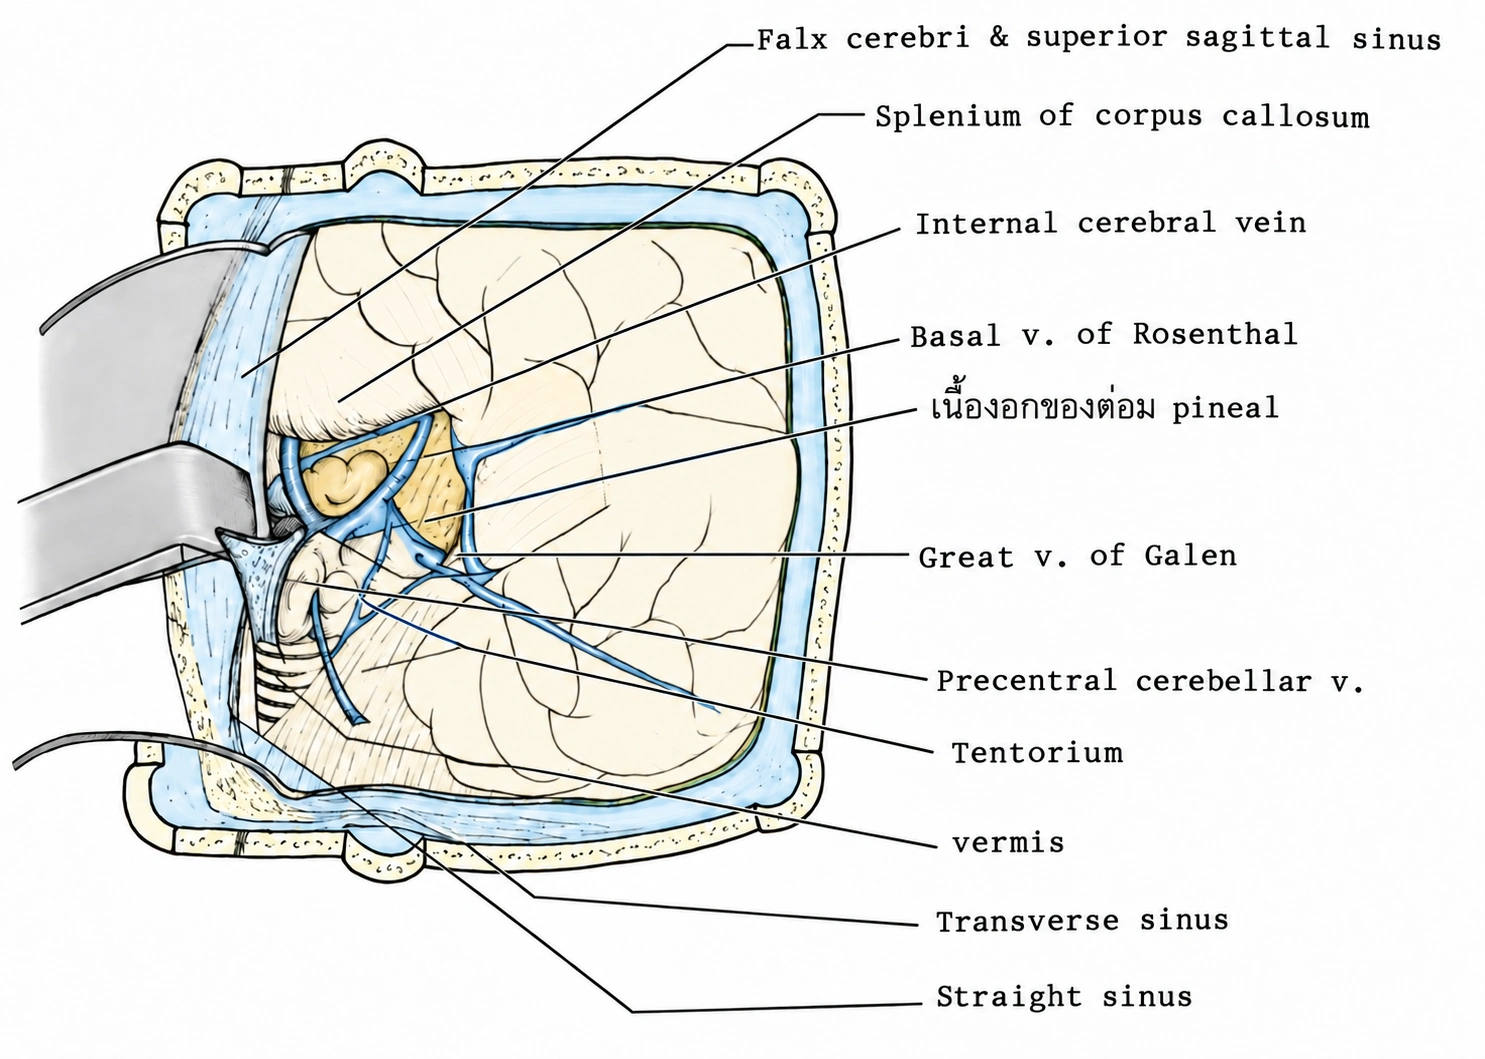
 AI-enhanced and colorized image · Switch to view the original
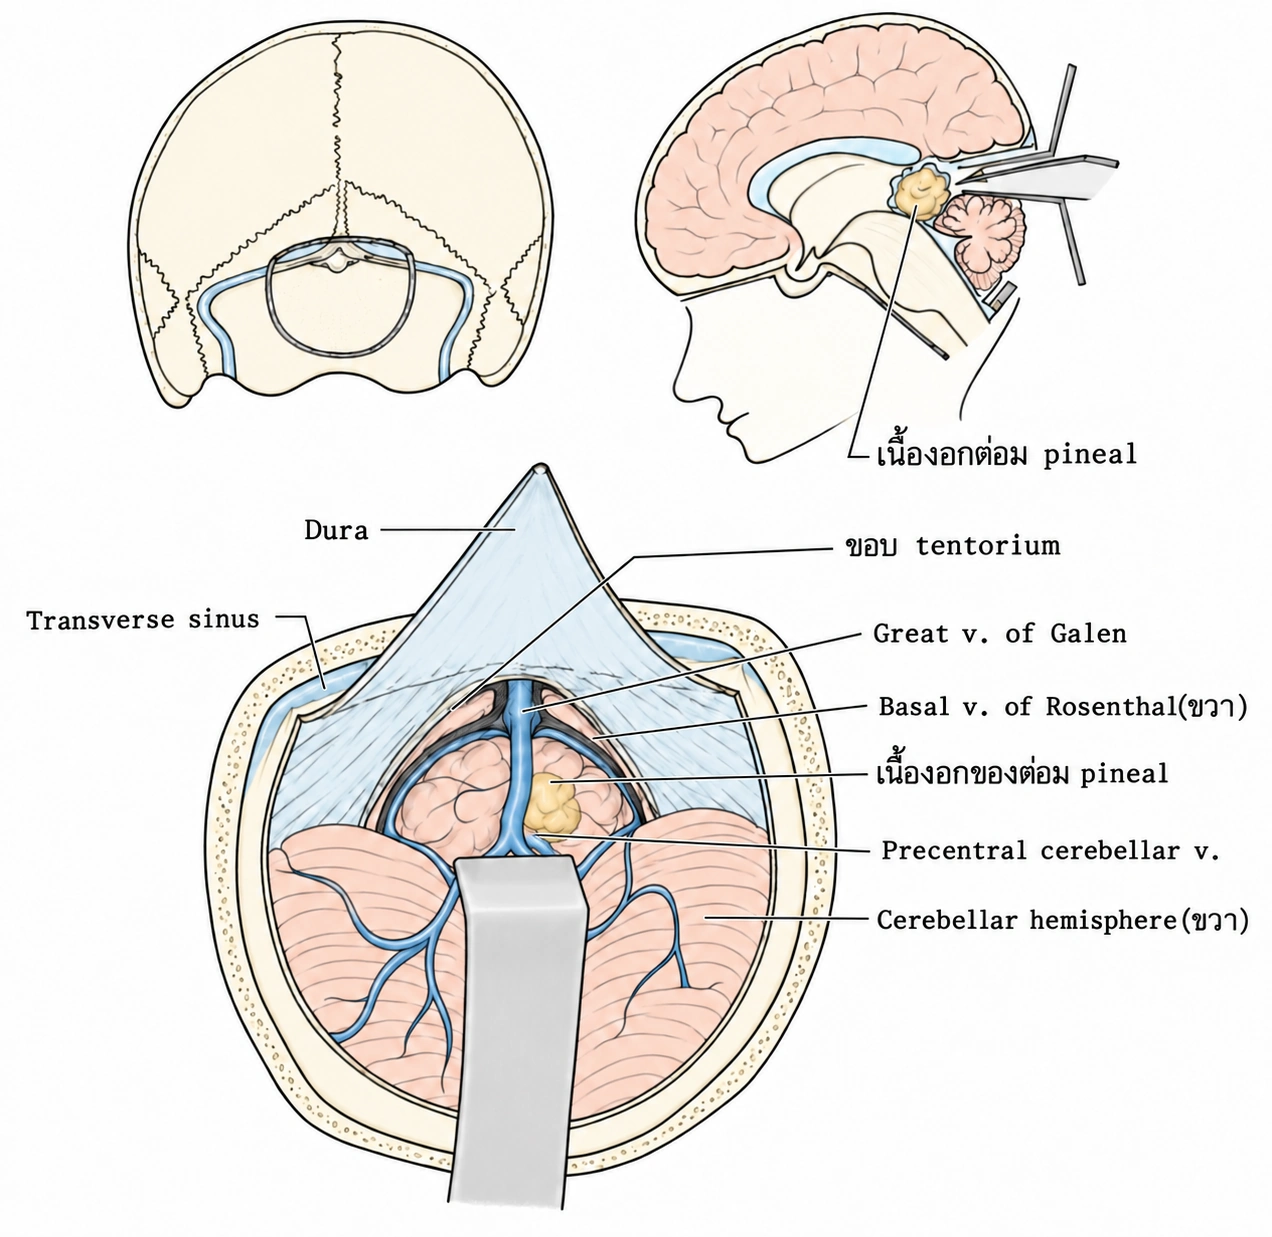
 AI-enhanced and colorized image · Switch to view the original
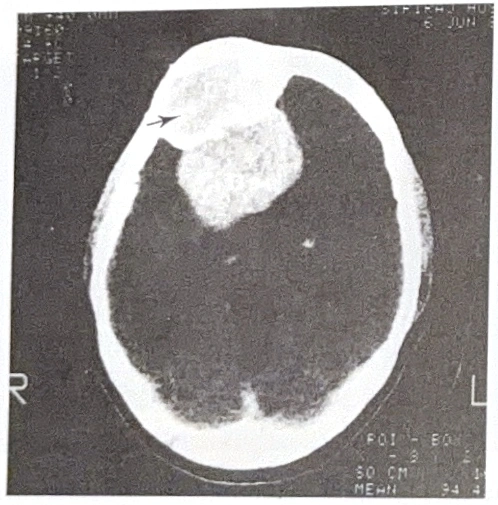
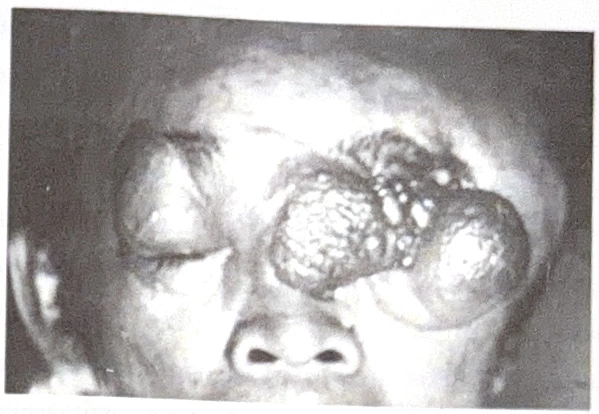
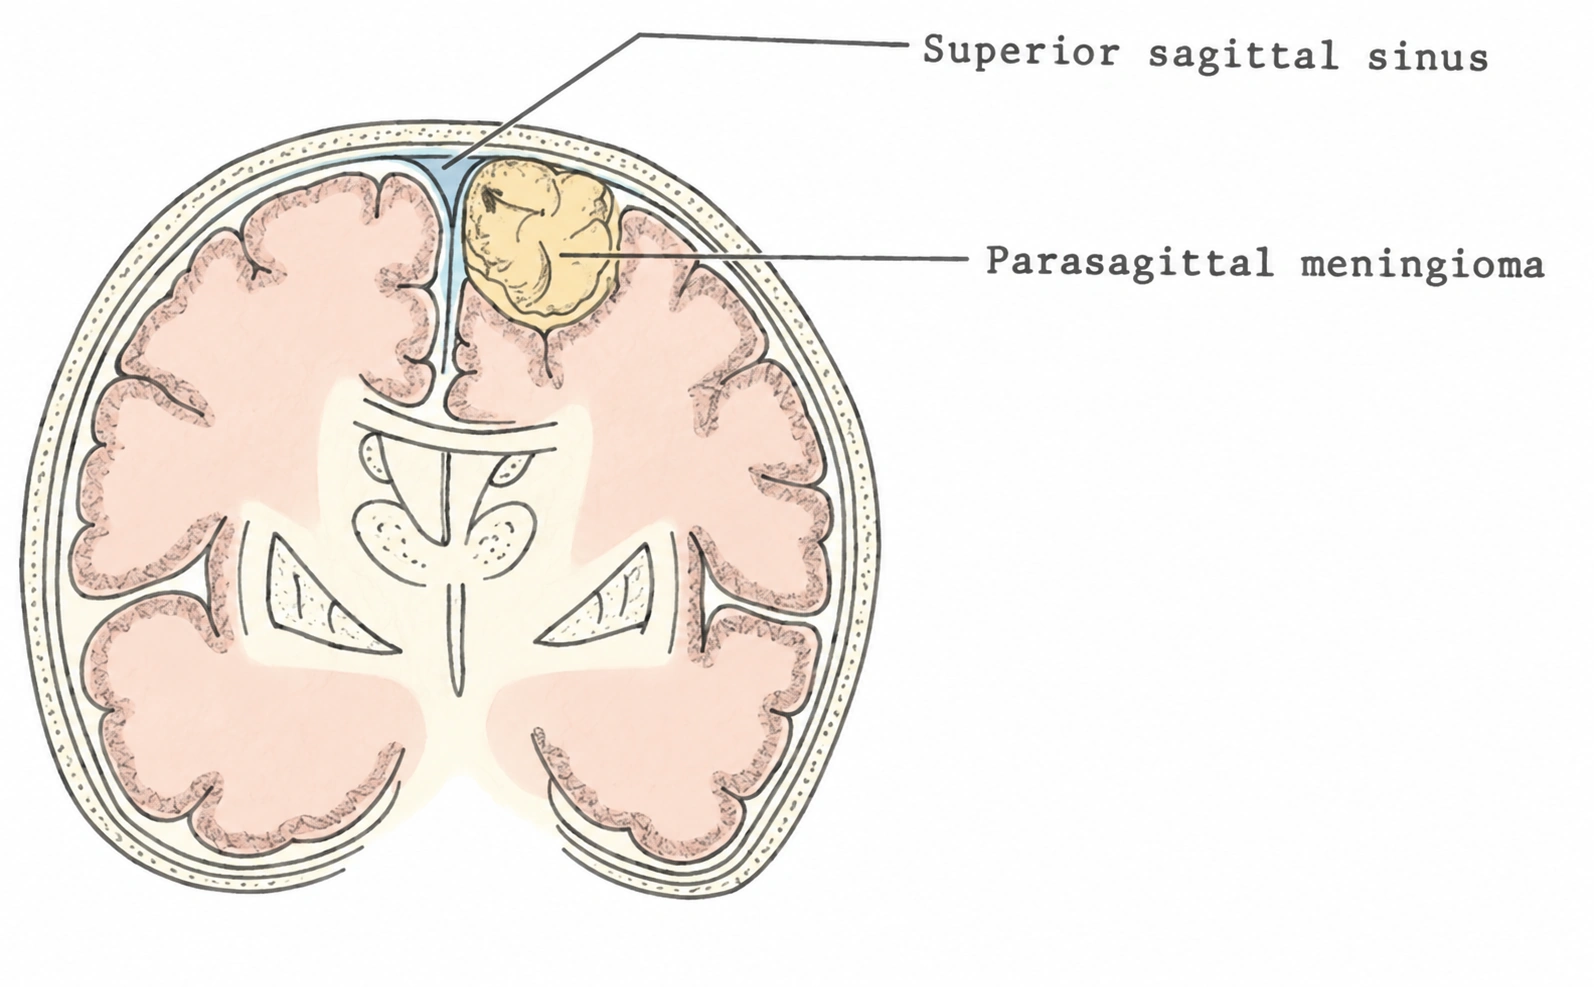
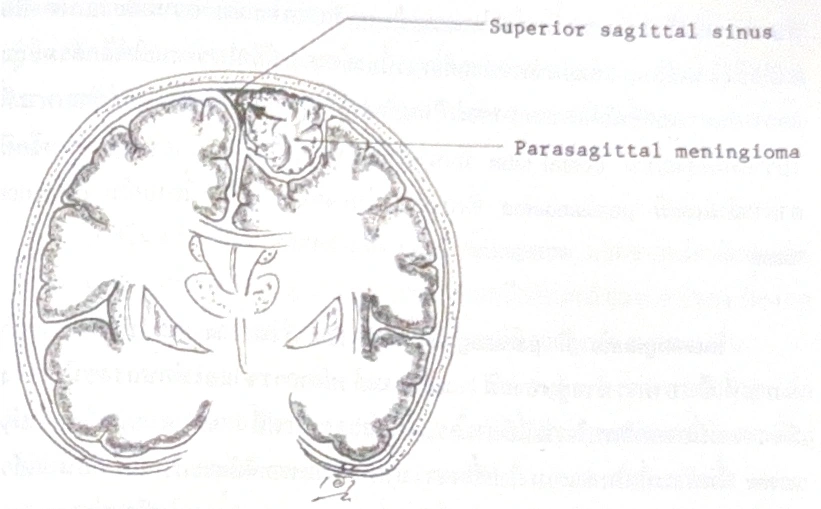 AI-enhanced and colorized image · Switch to view the original
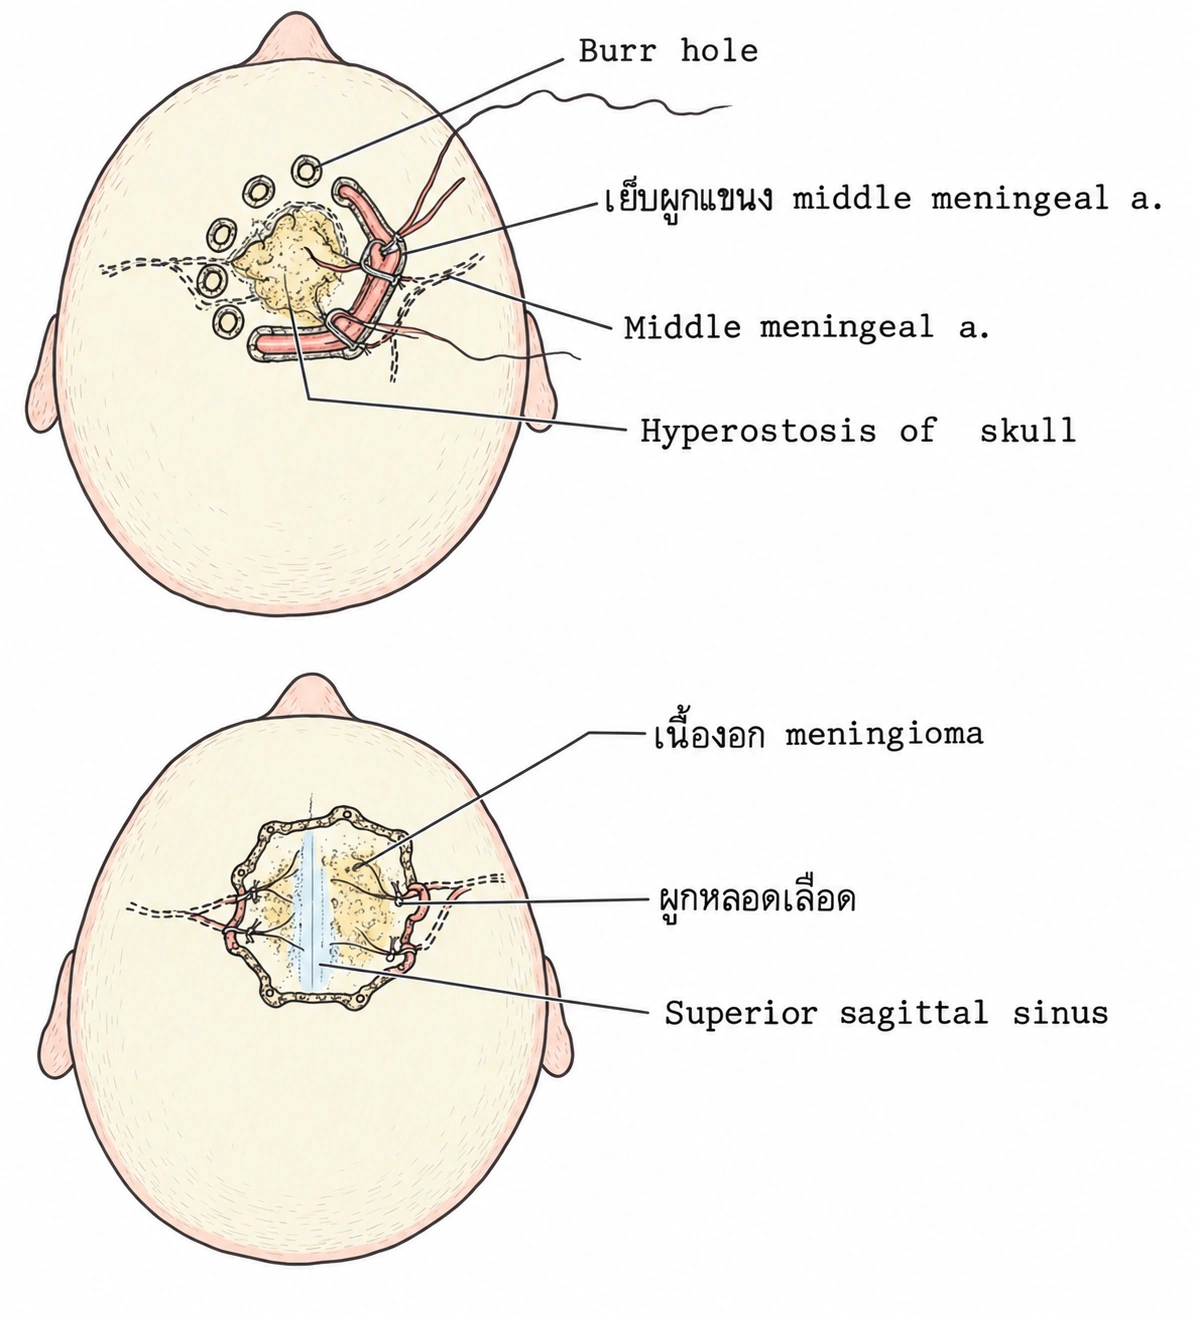
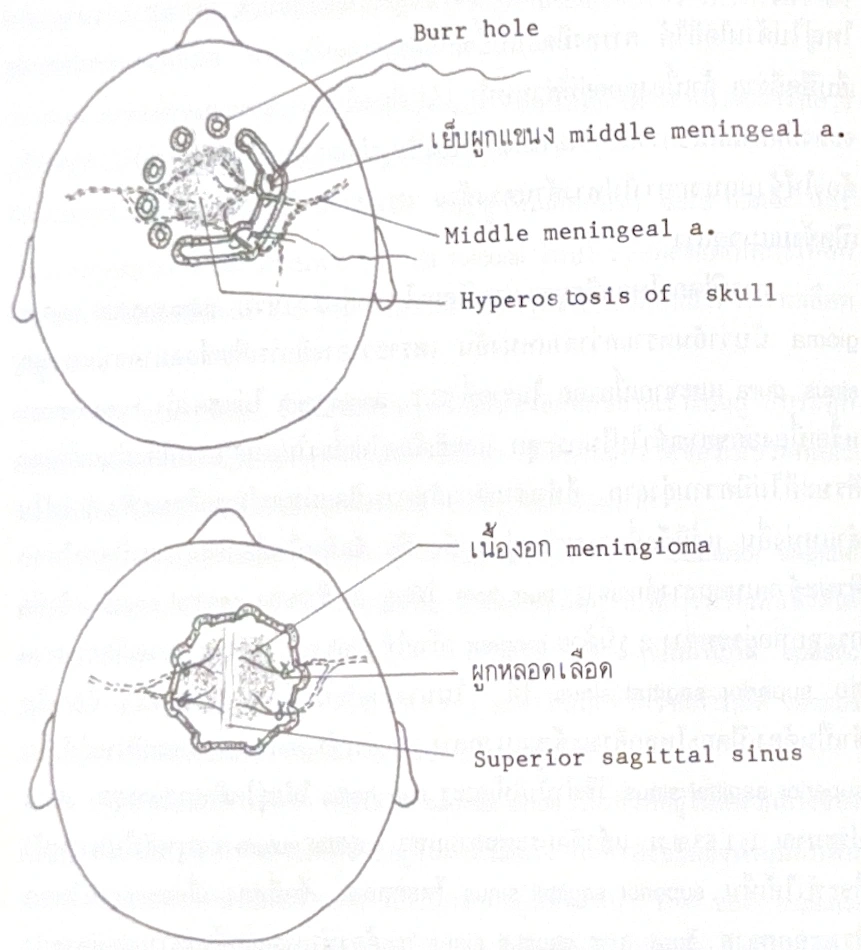 AI-enhanced and colorized image · Switch to view the original
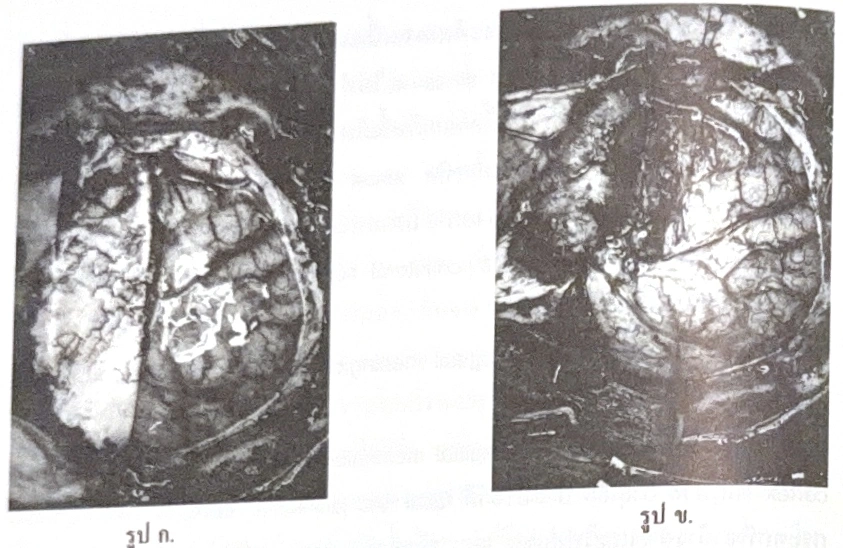
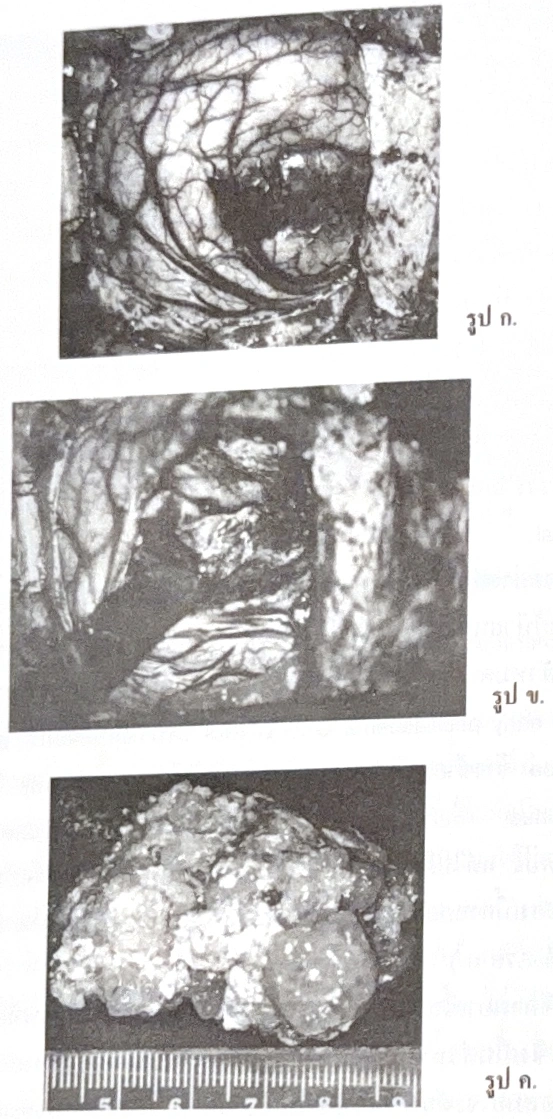
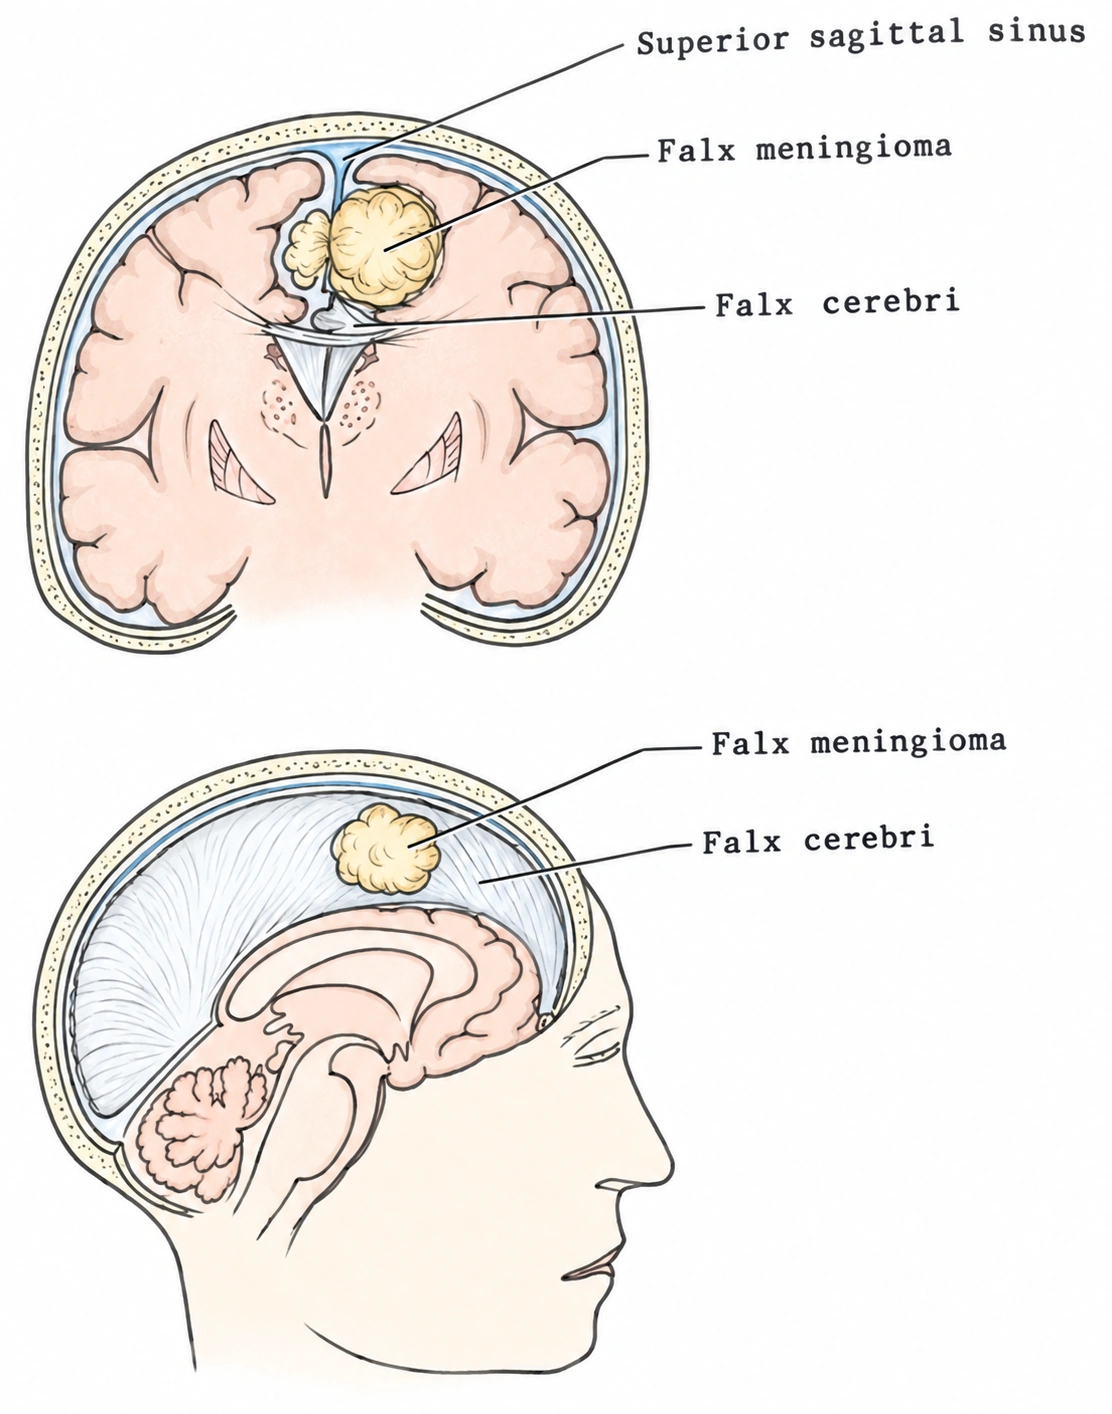
 AI-enhanced and colorized image · Switch to view the original
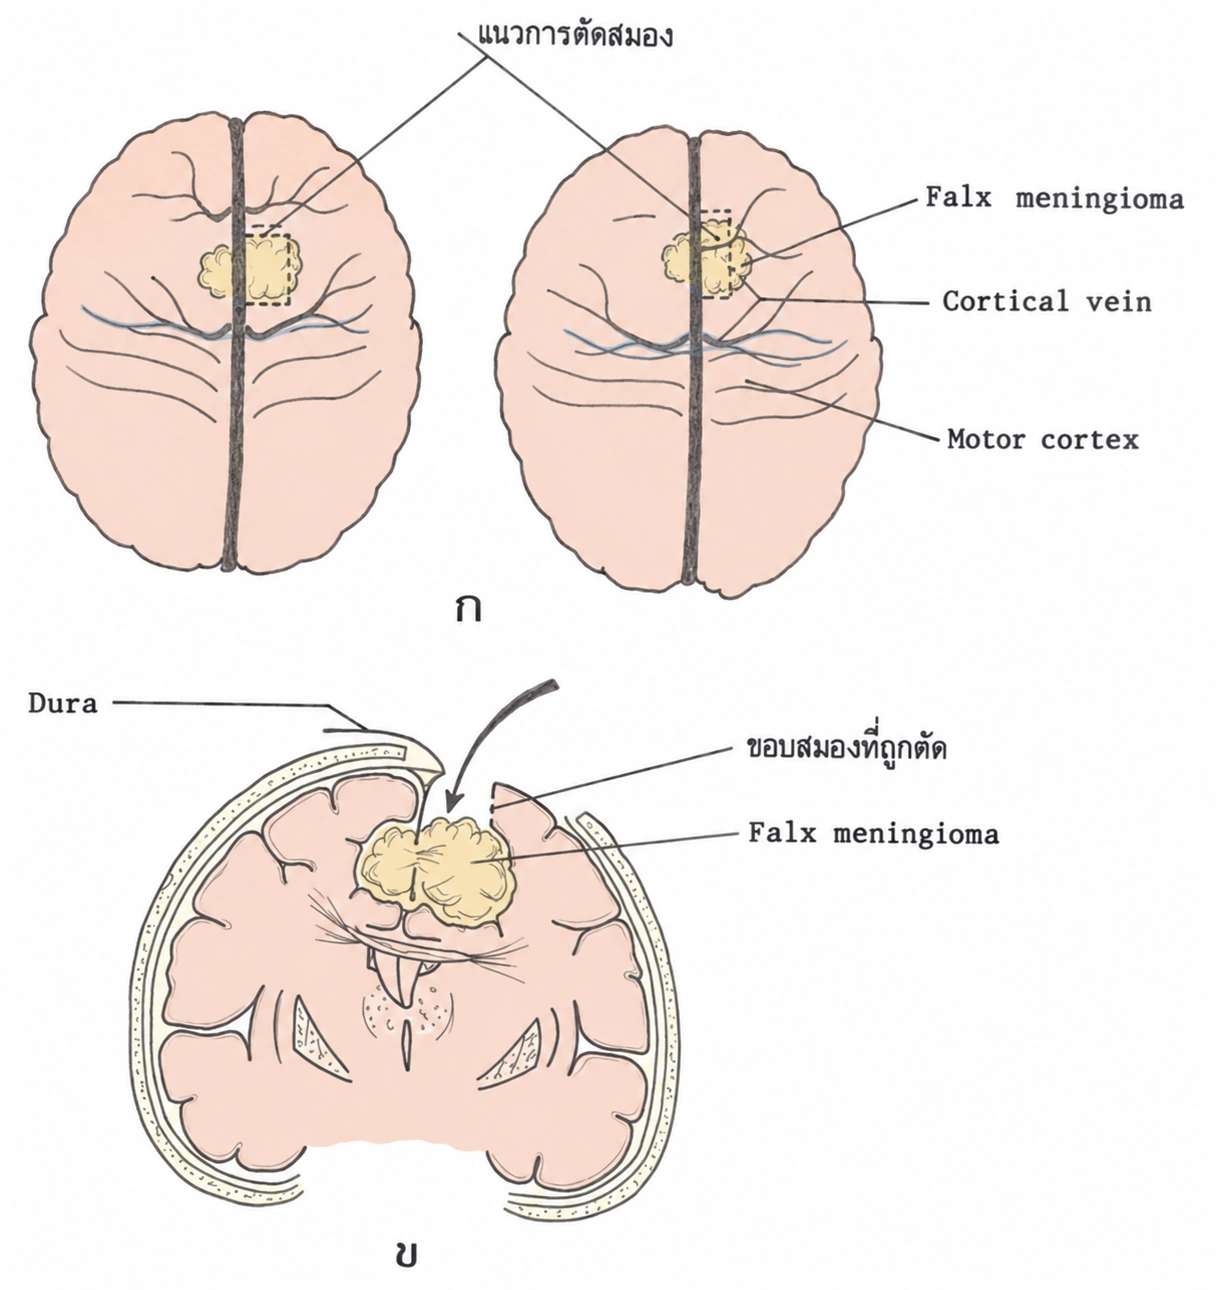
 AI-enhanced and colorized image · Switch to view the original
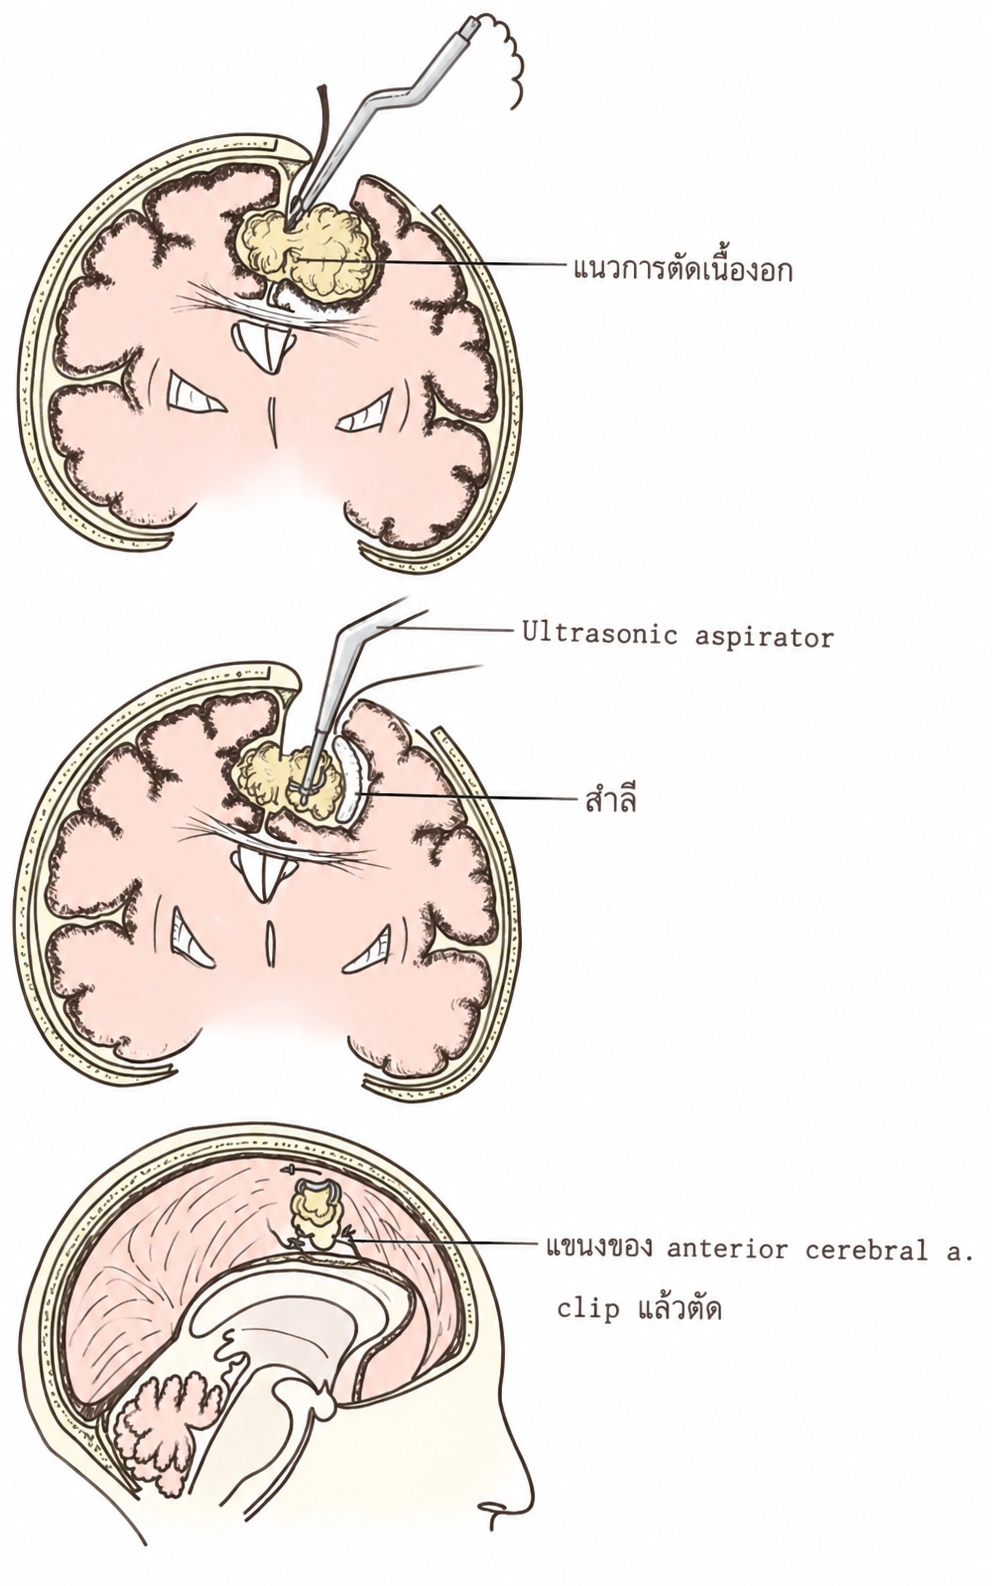
 AI-enhanced and colorized image · Switch to view the original
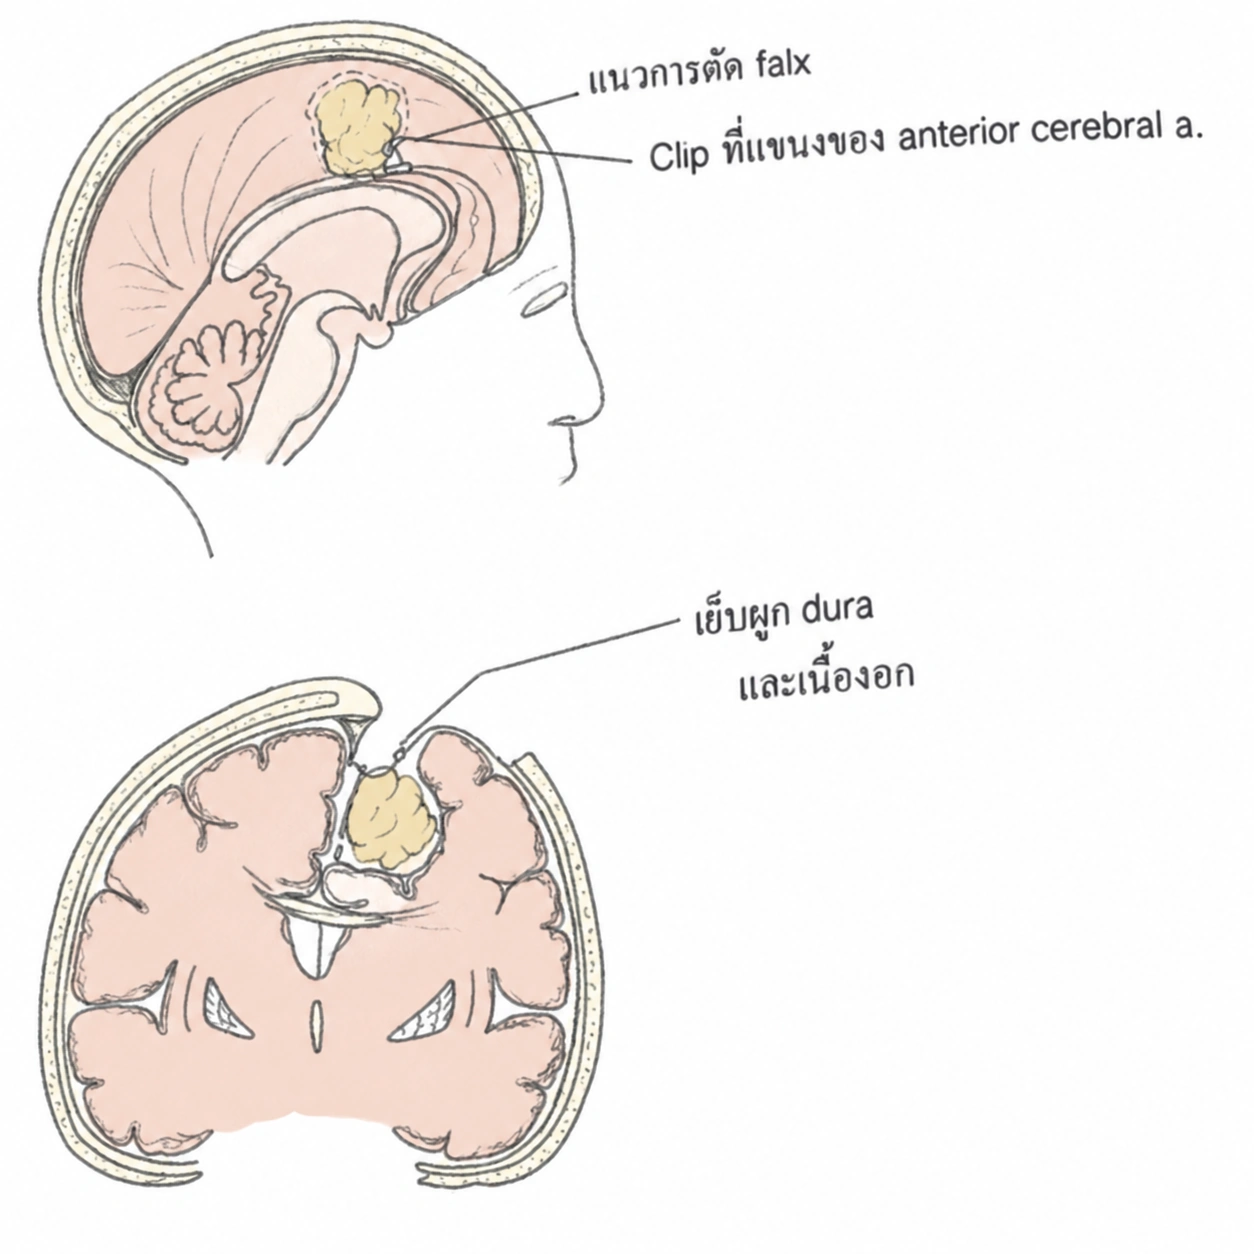
 AI-enhanced and colorized image · Switch to view the original
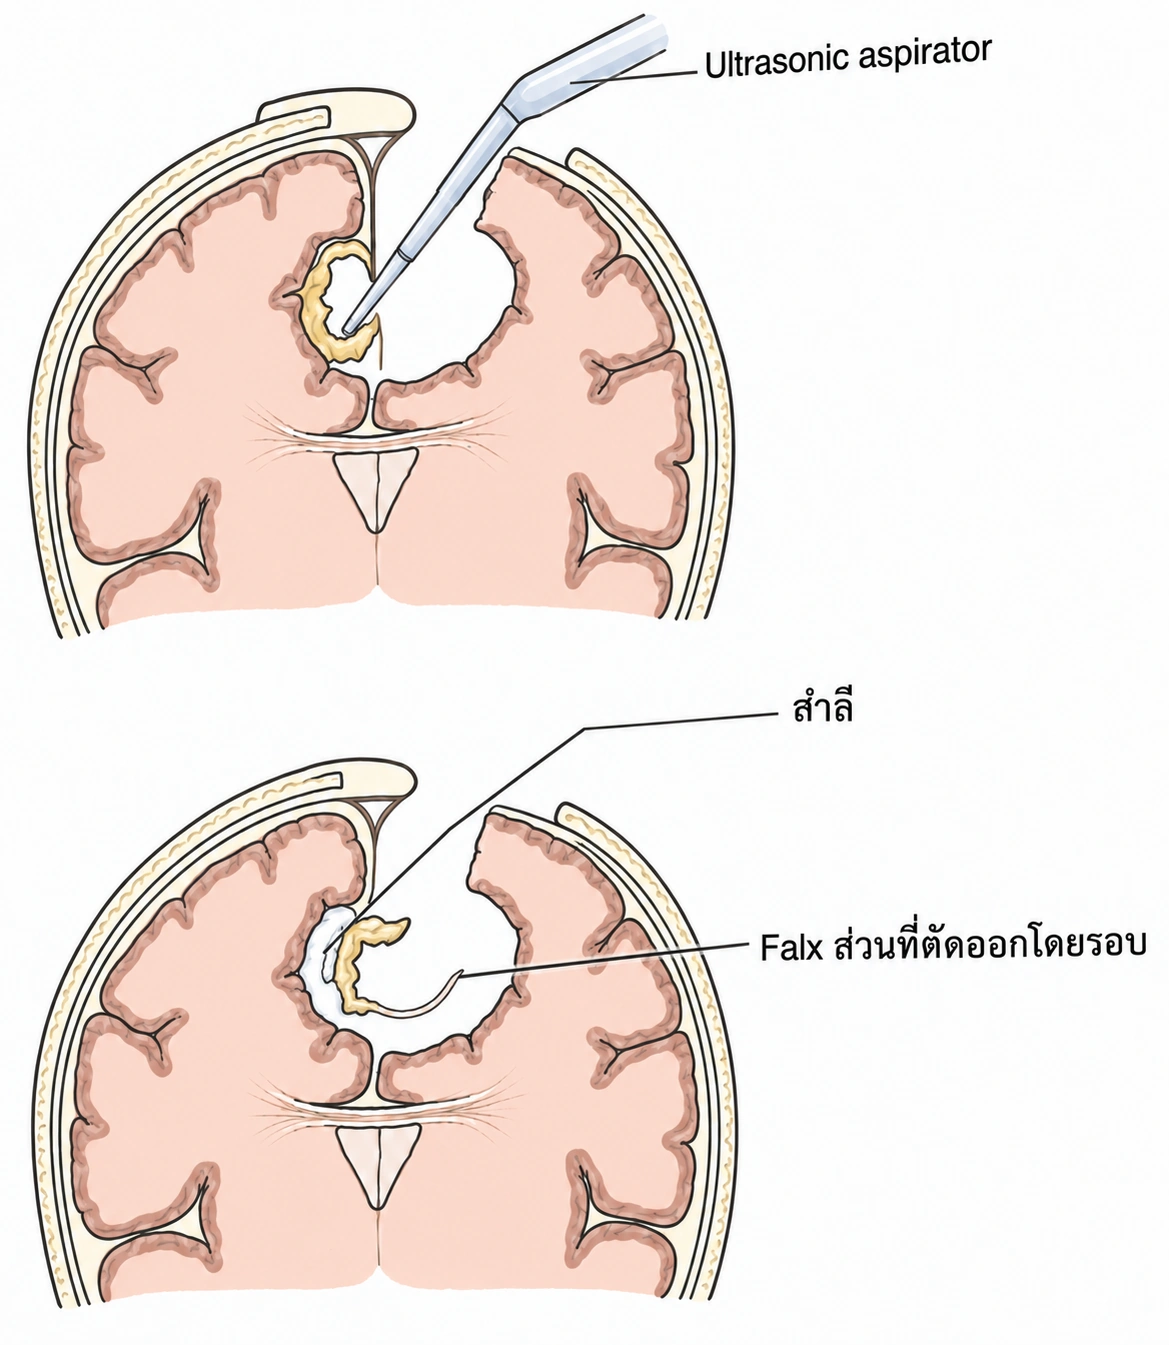
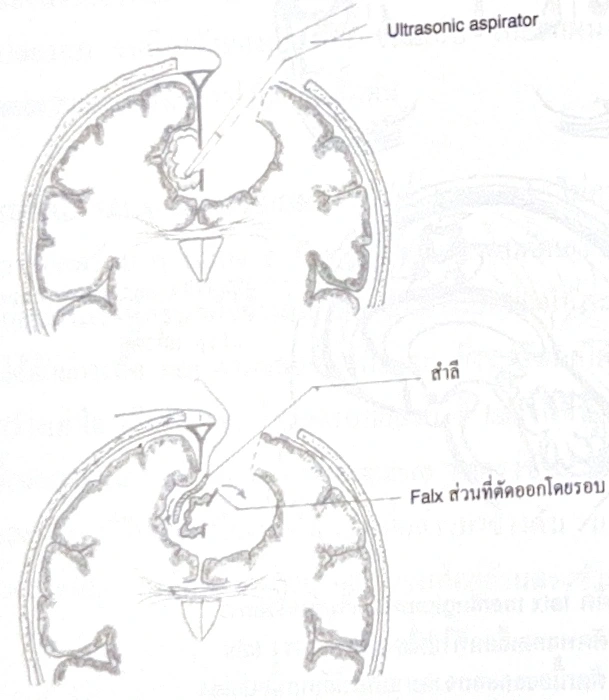 AI-enhanced and colorized image · Switch to view the original
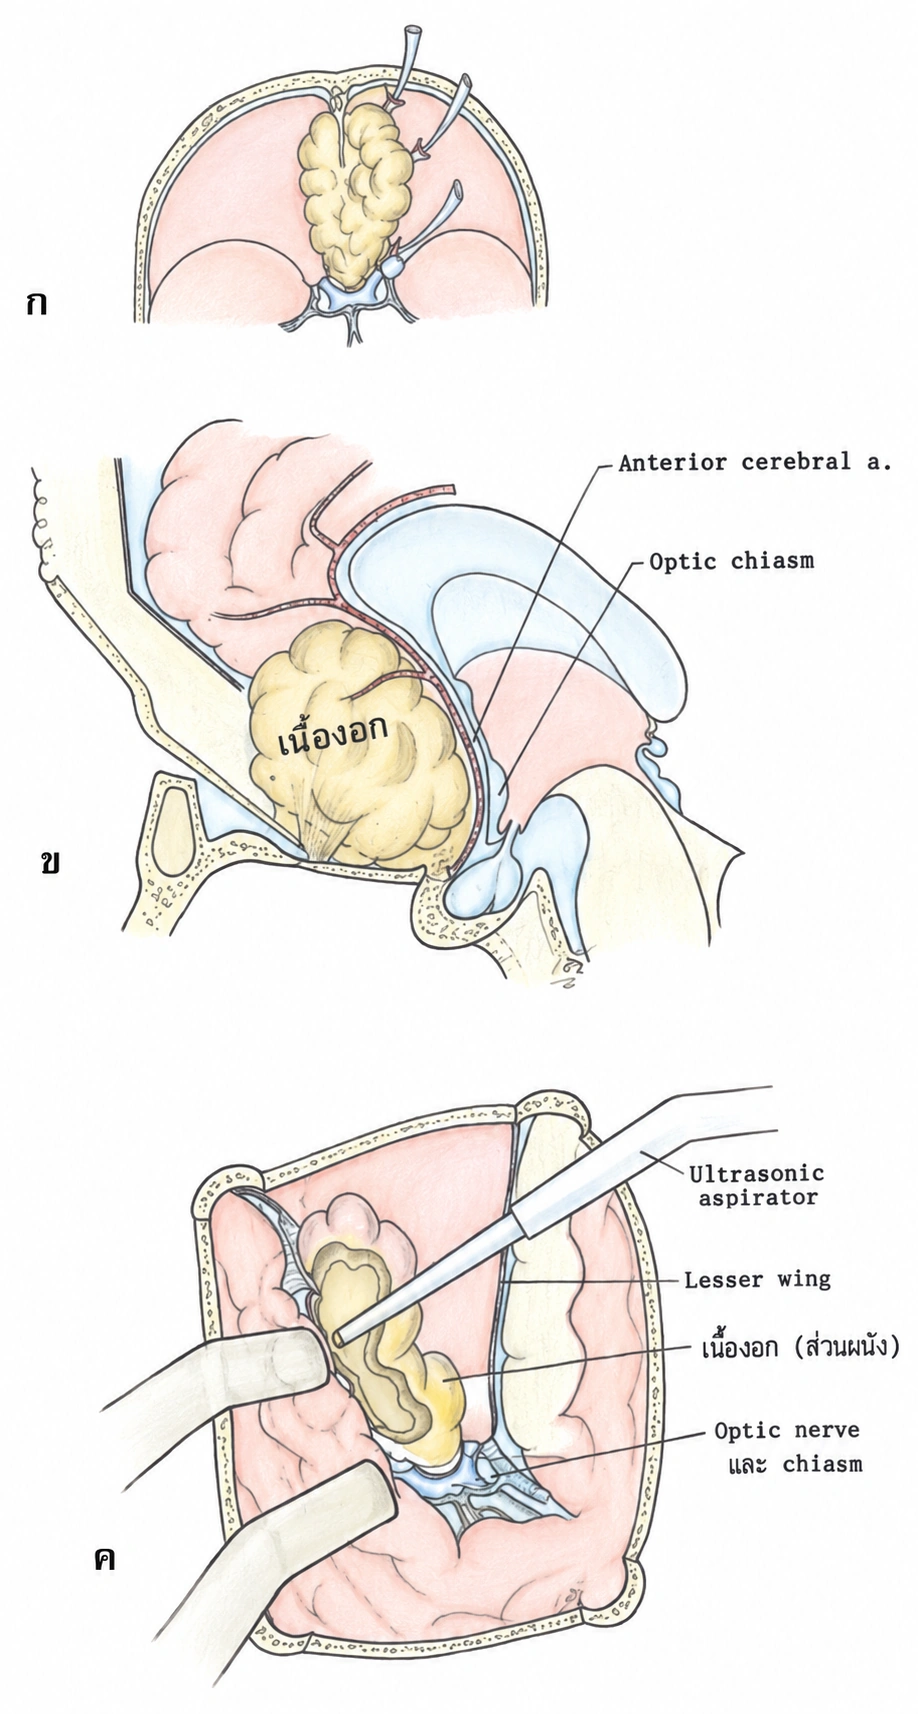
 AI-enhanced and colorized image · Switch to view the original
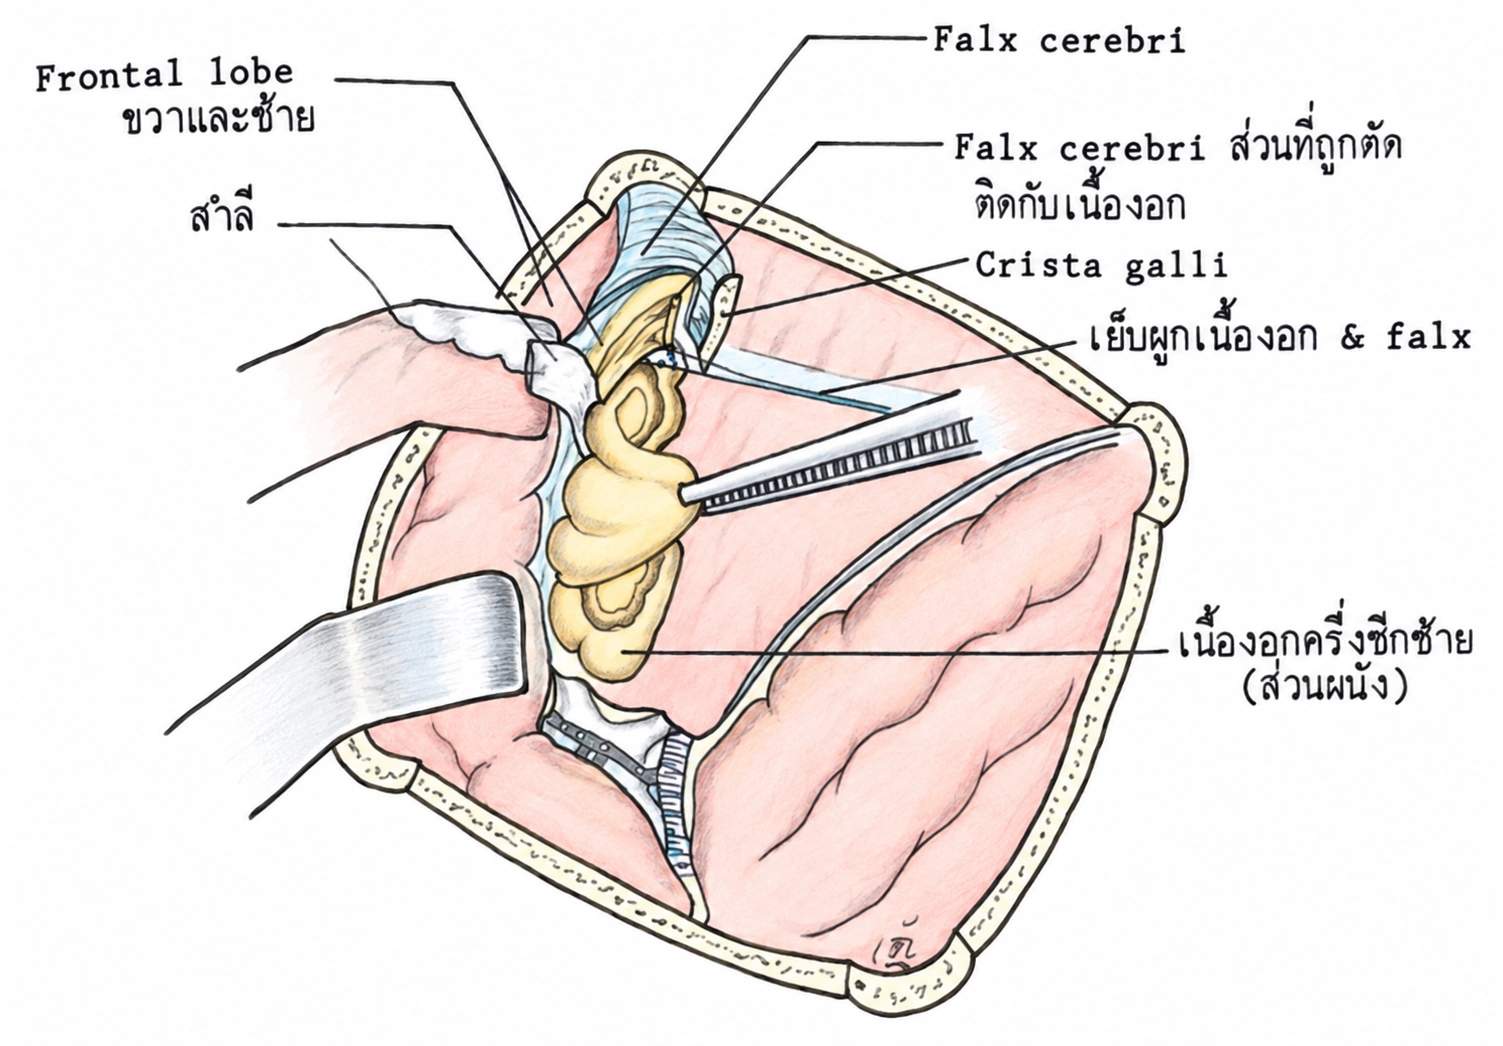
 AI-enhanced and colorized image · Switch to view the original
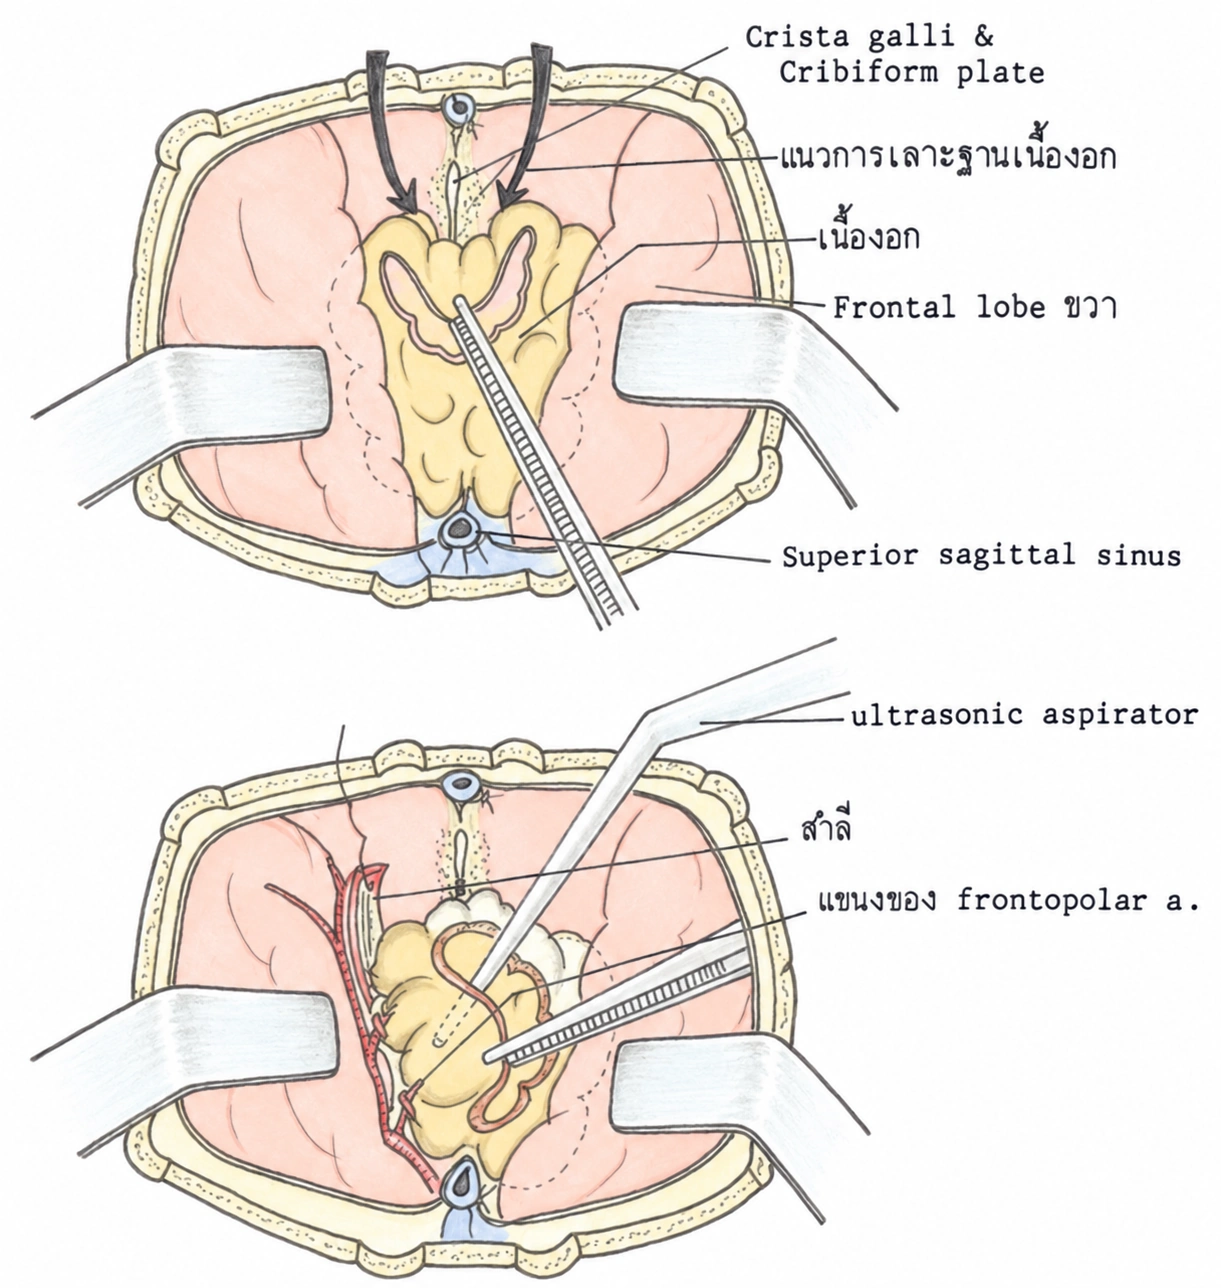
 AI-enhanced and colorized image · Switch to view the original
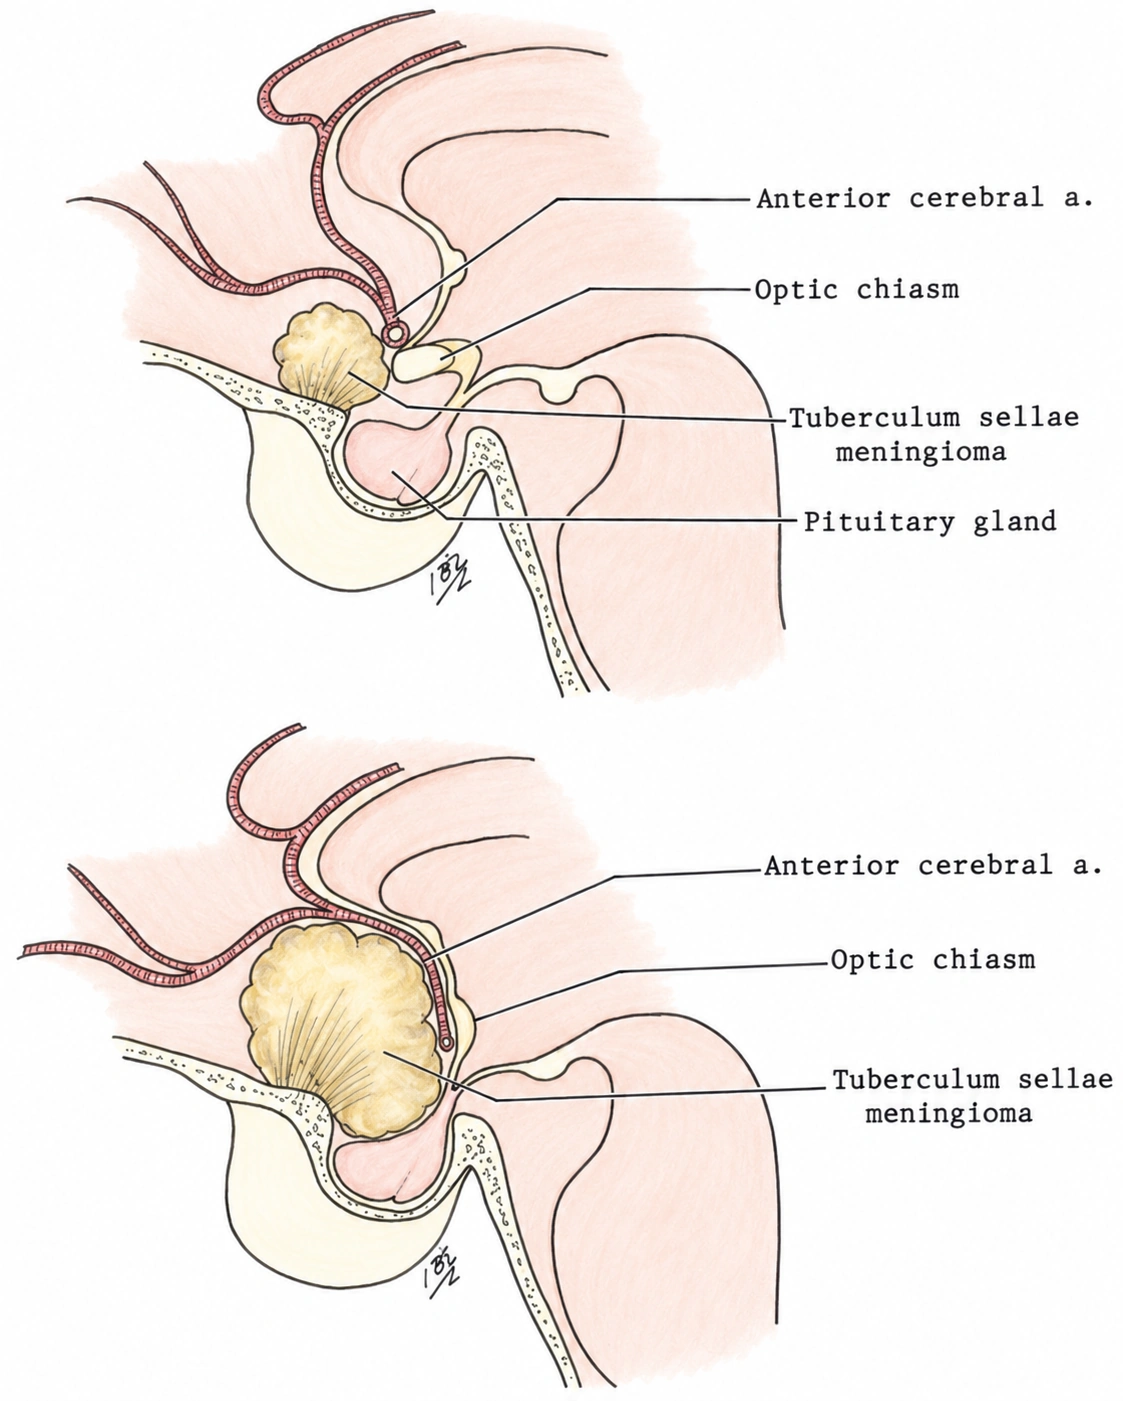
 AI-enhanced and colorized image · Switch to view the original
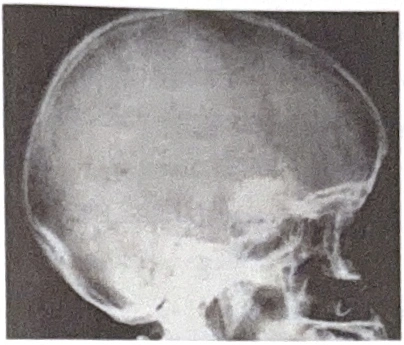
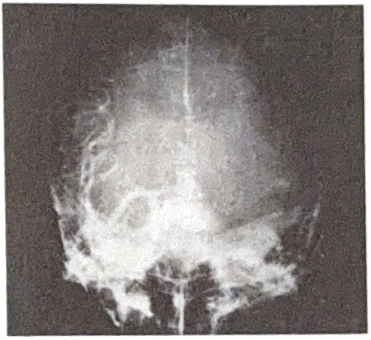
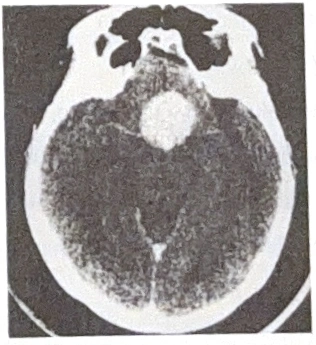
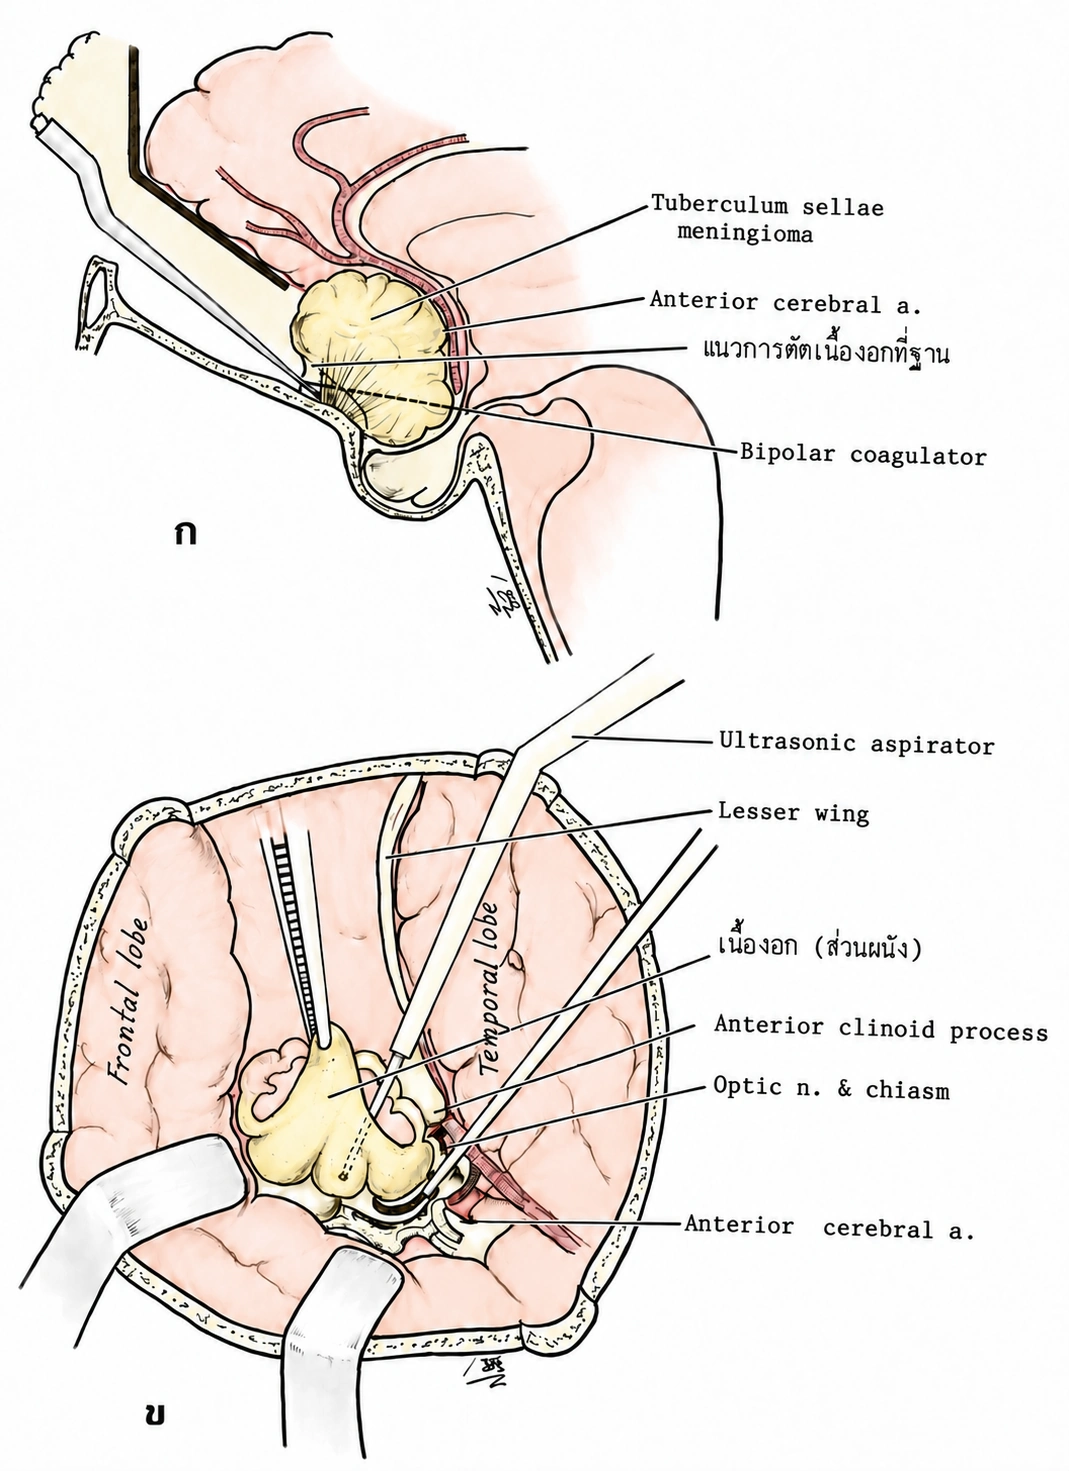
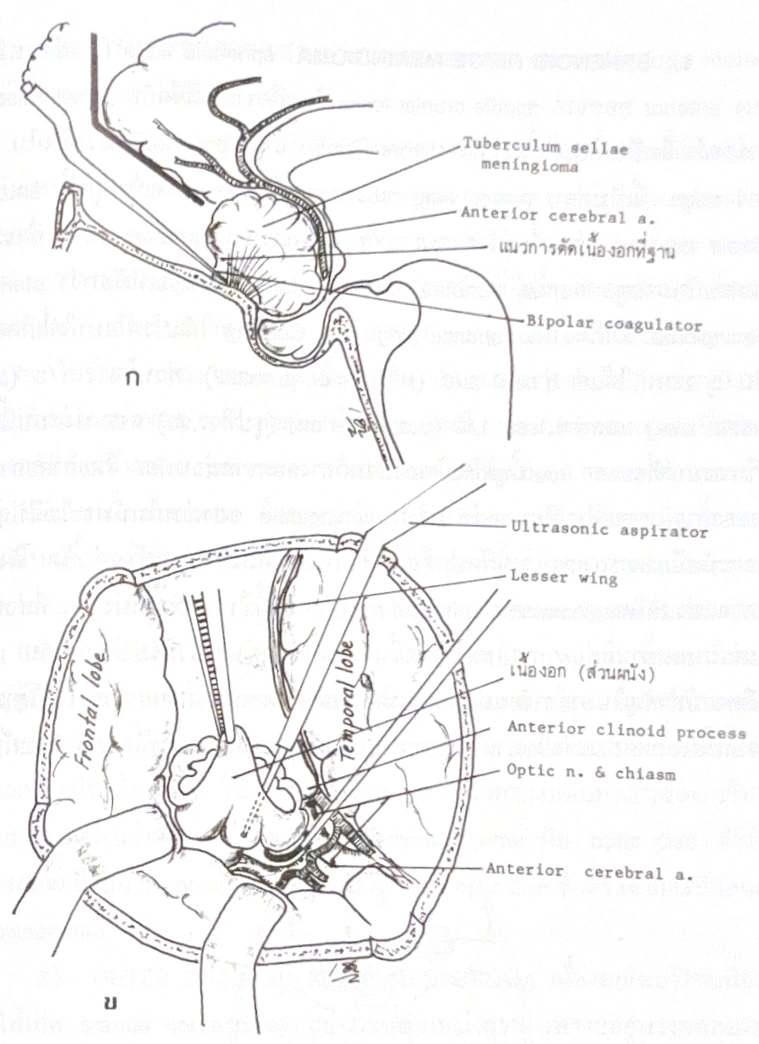 AI-enhanced and colorized image · Switch to view the original
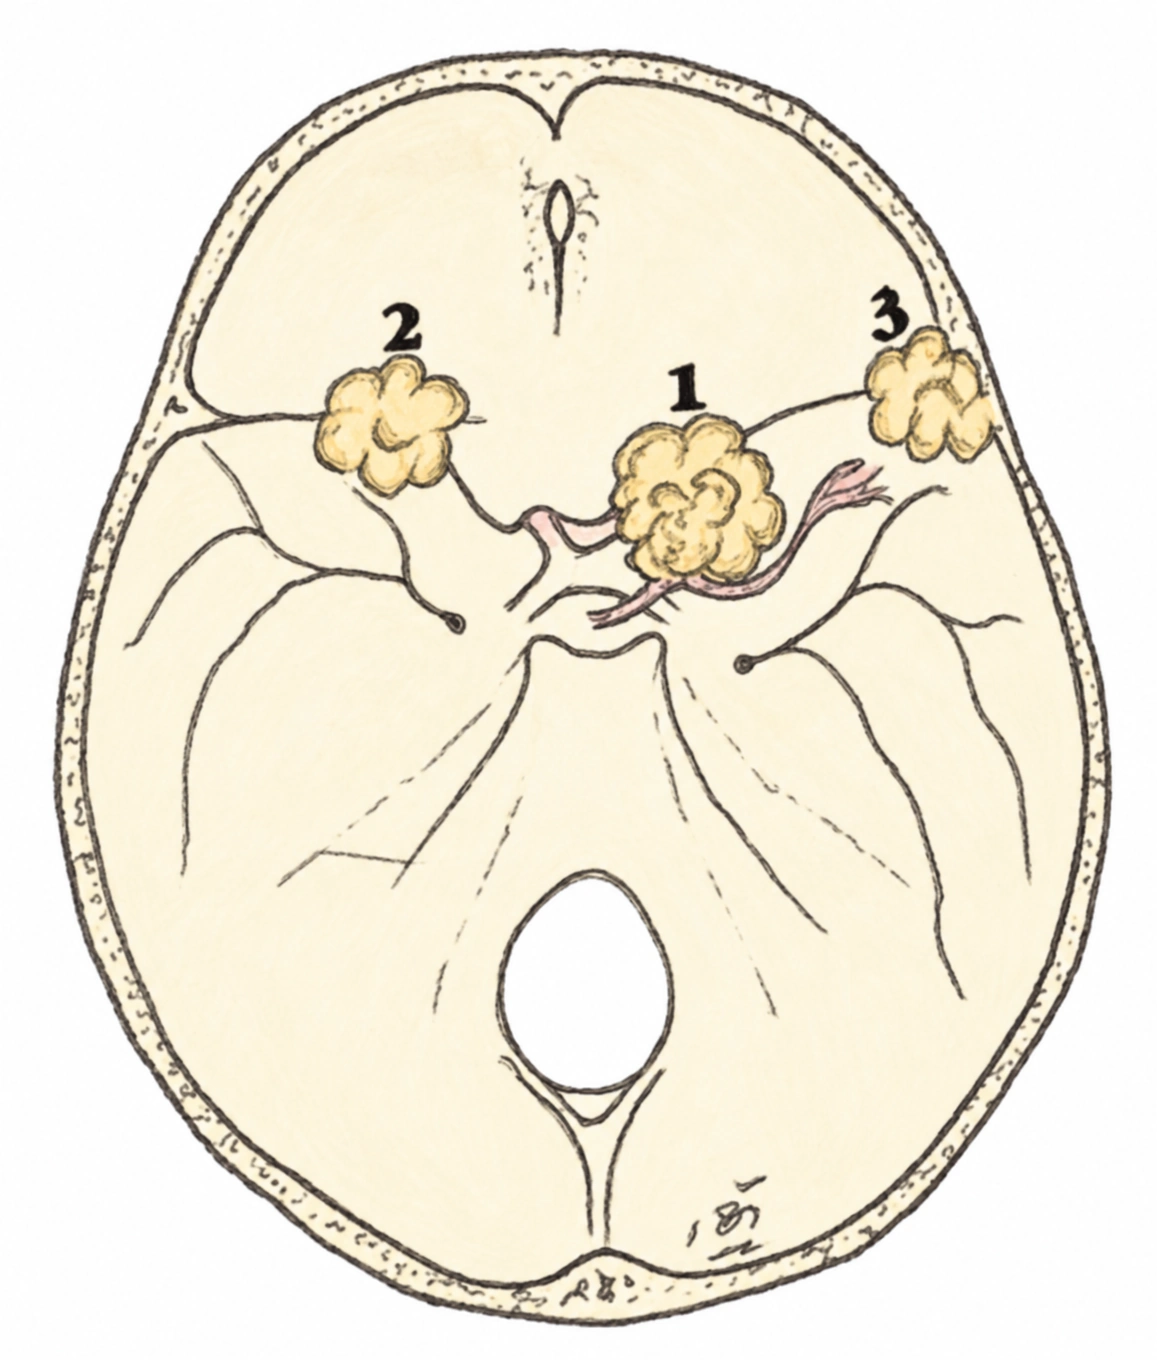
 AI-enhanced and colorized image · Switch to the original image
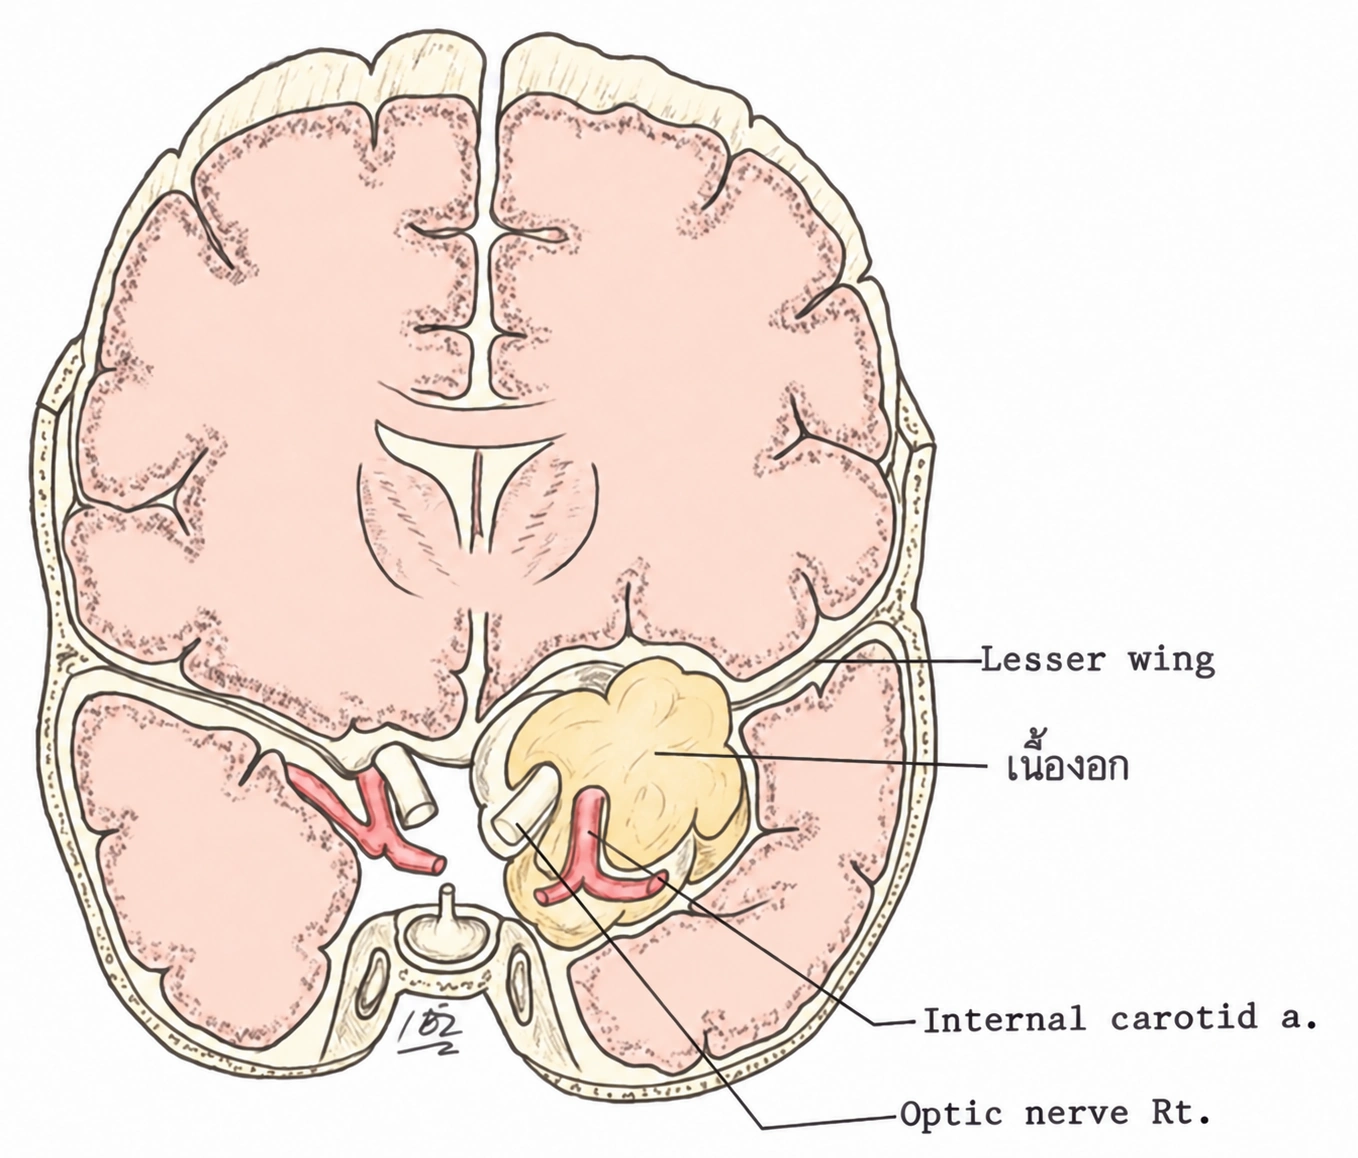
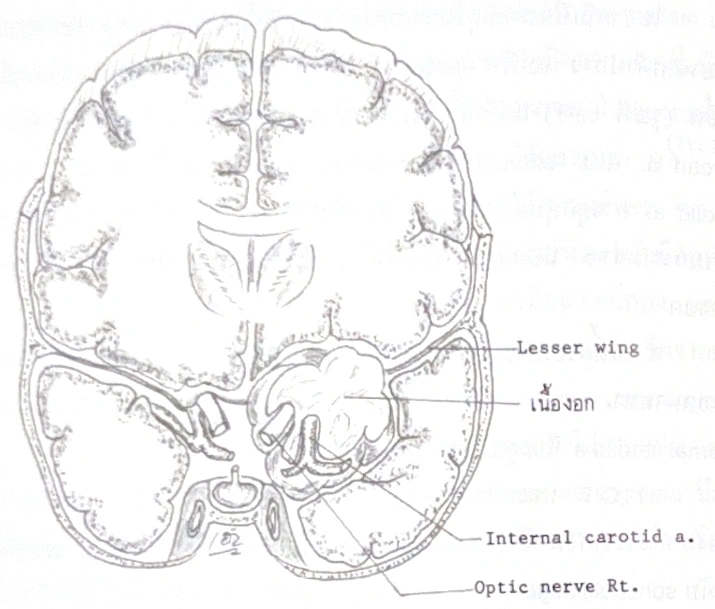 AI-enhanced and colorized image · Switch to the original image
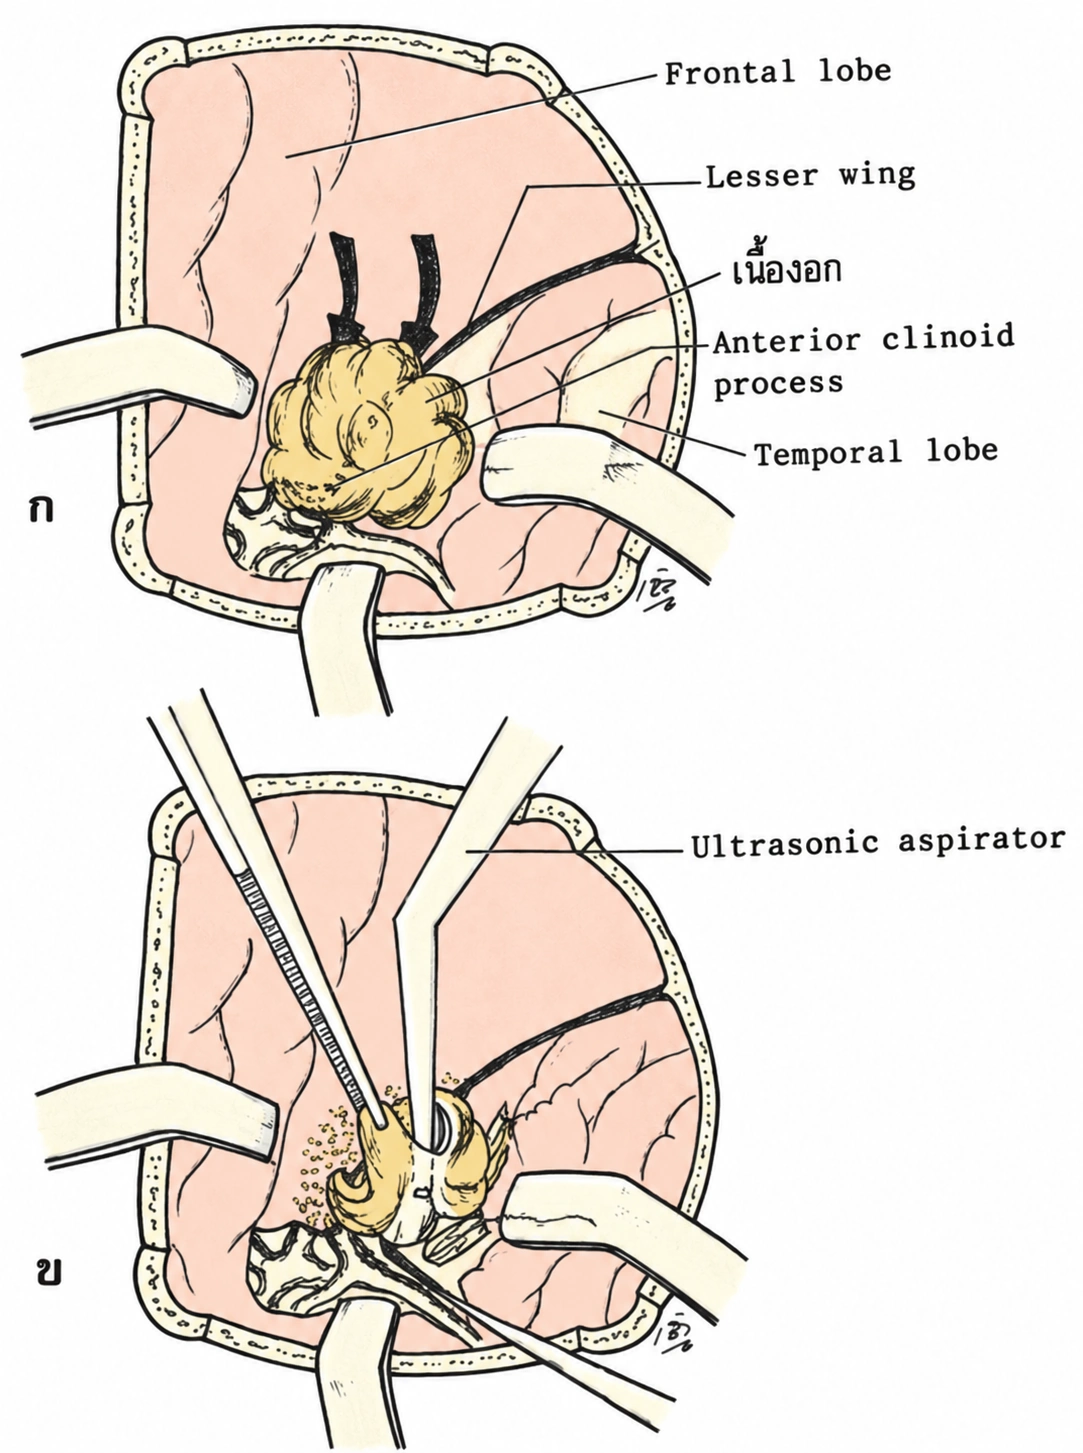
 AI-enhanced and colorized image · Switch to the original image
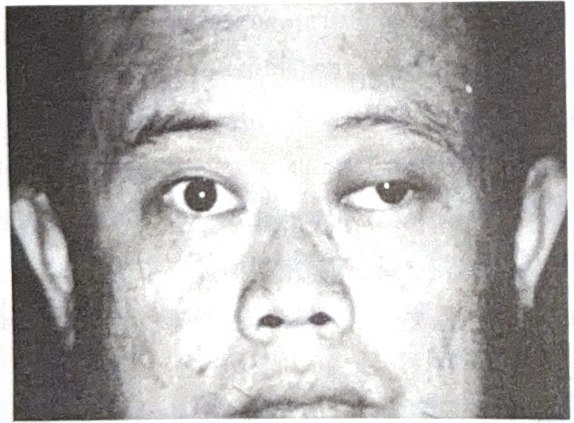
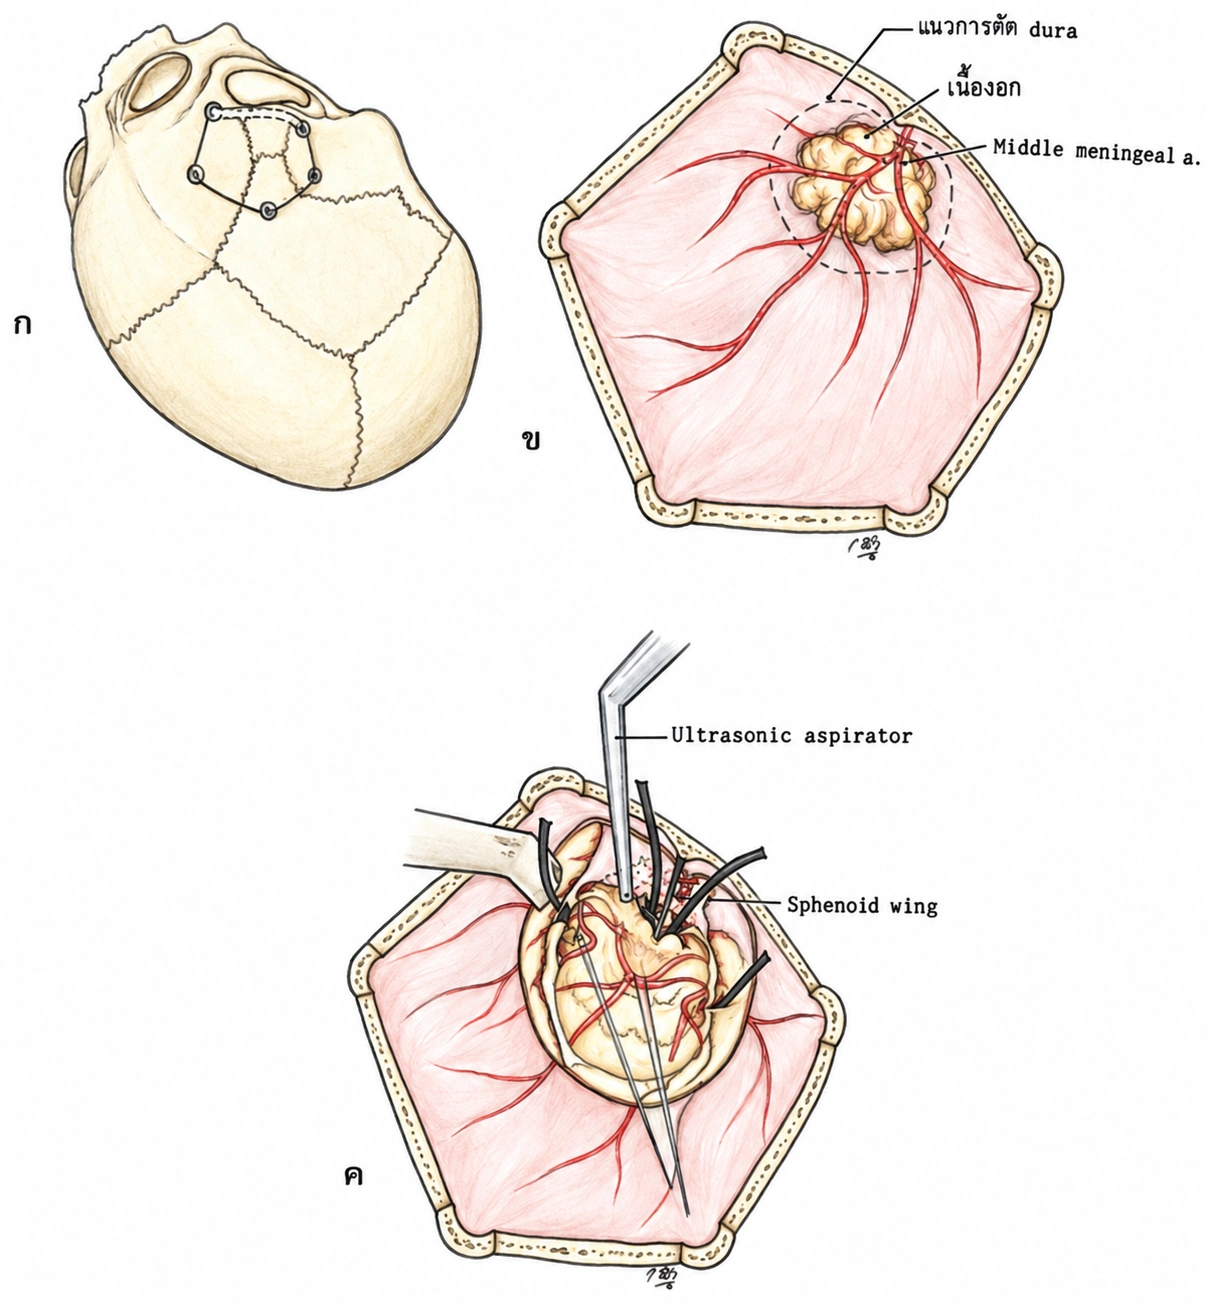
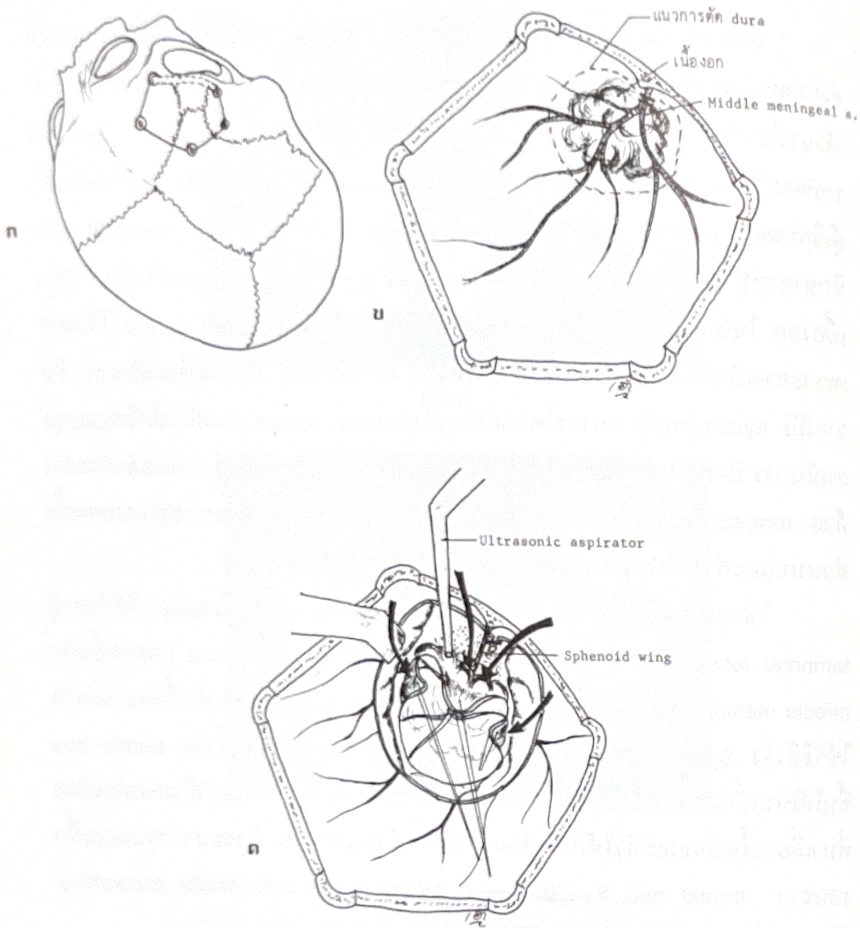 AI-enhanced and colorized image · Switch to the original image
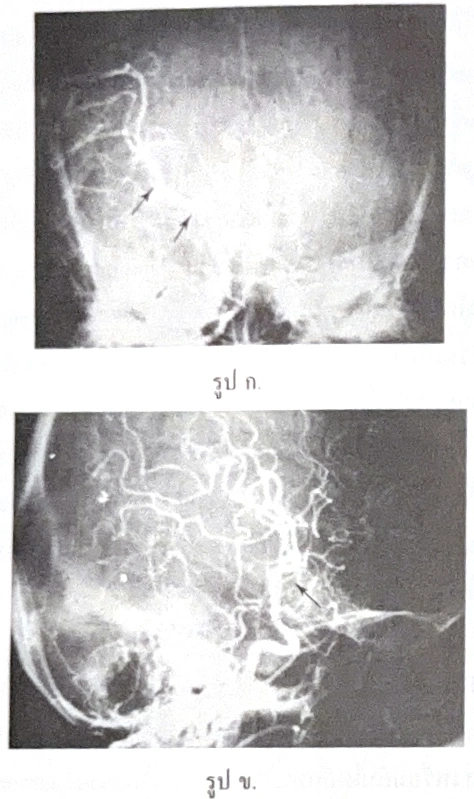
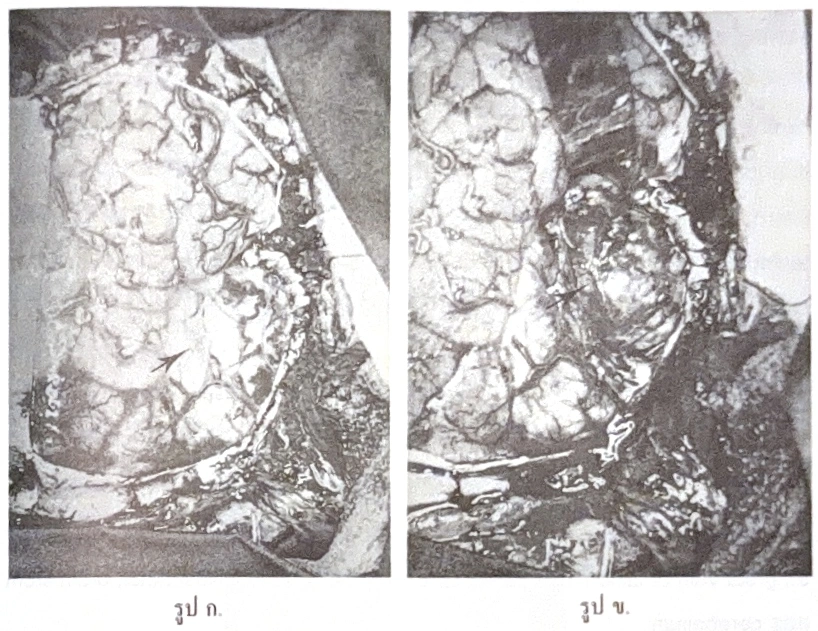
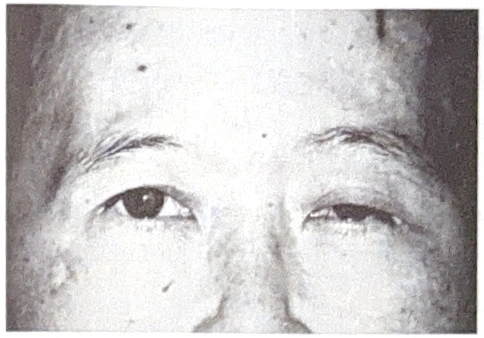
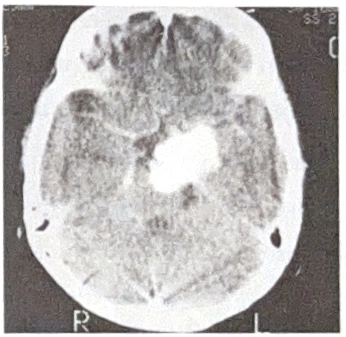
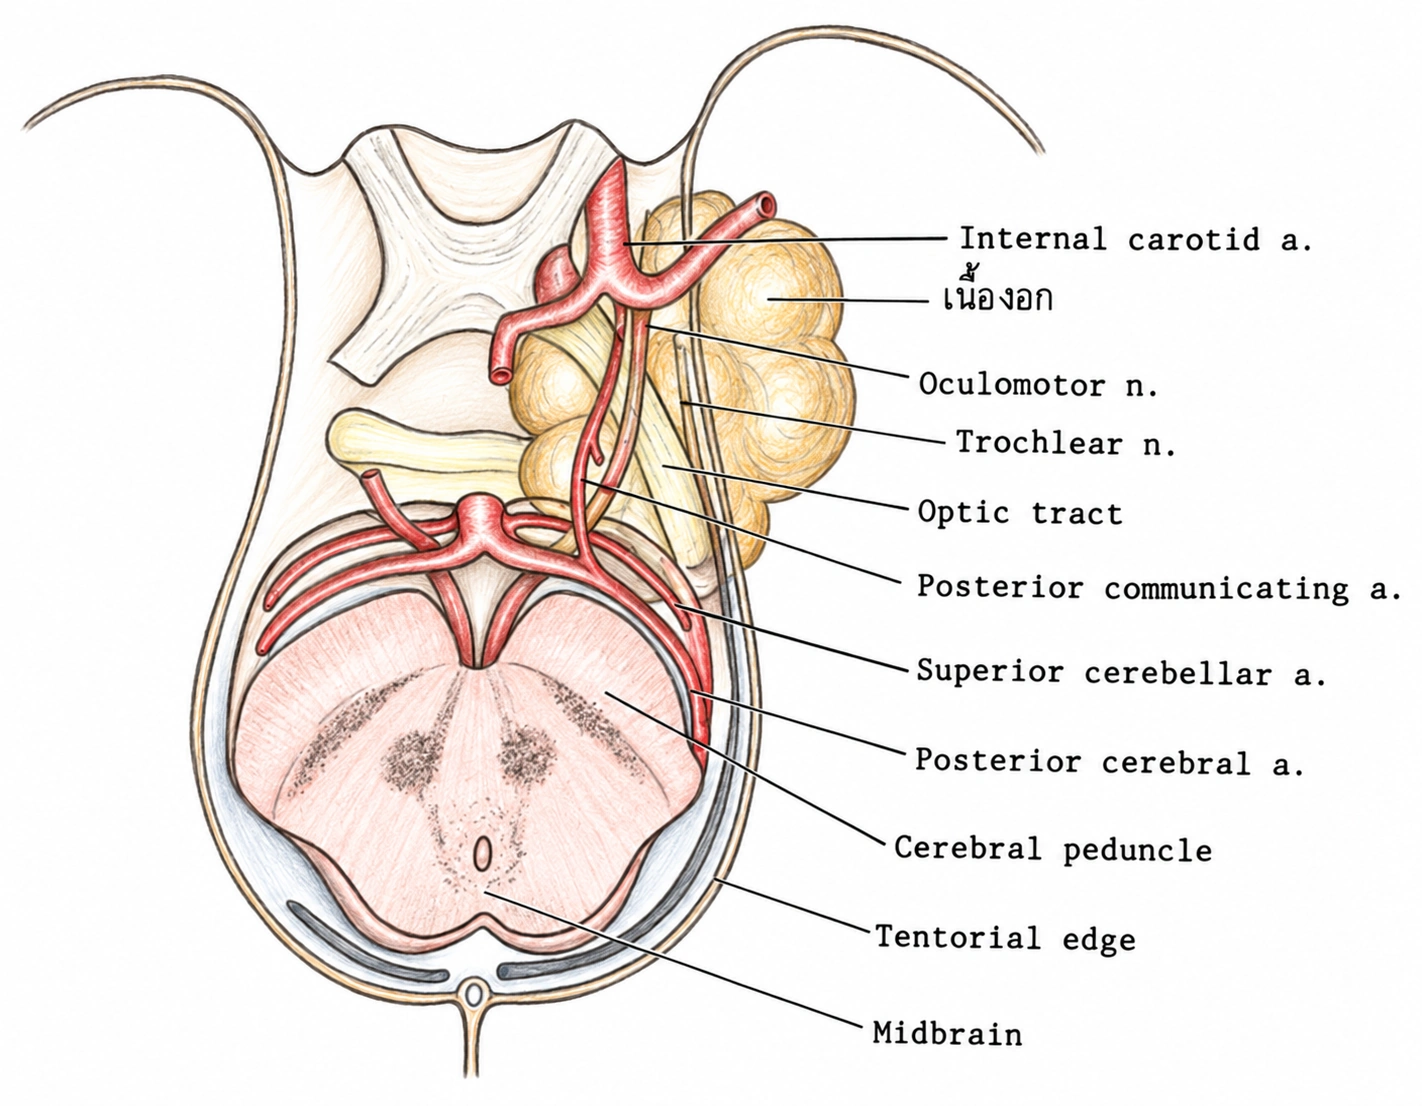
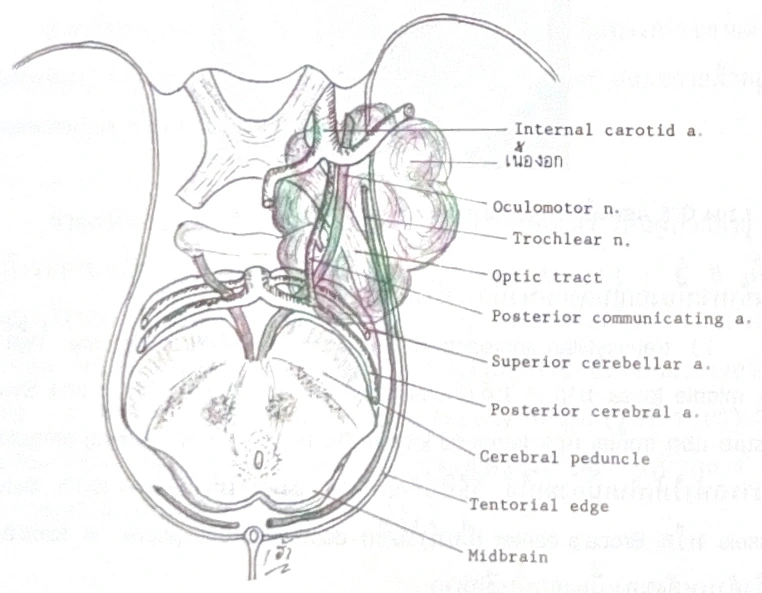 AI-enhanced and colorized image · Switch to the original image
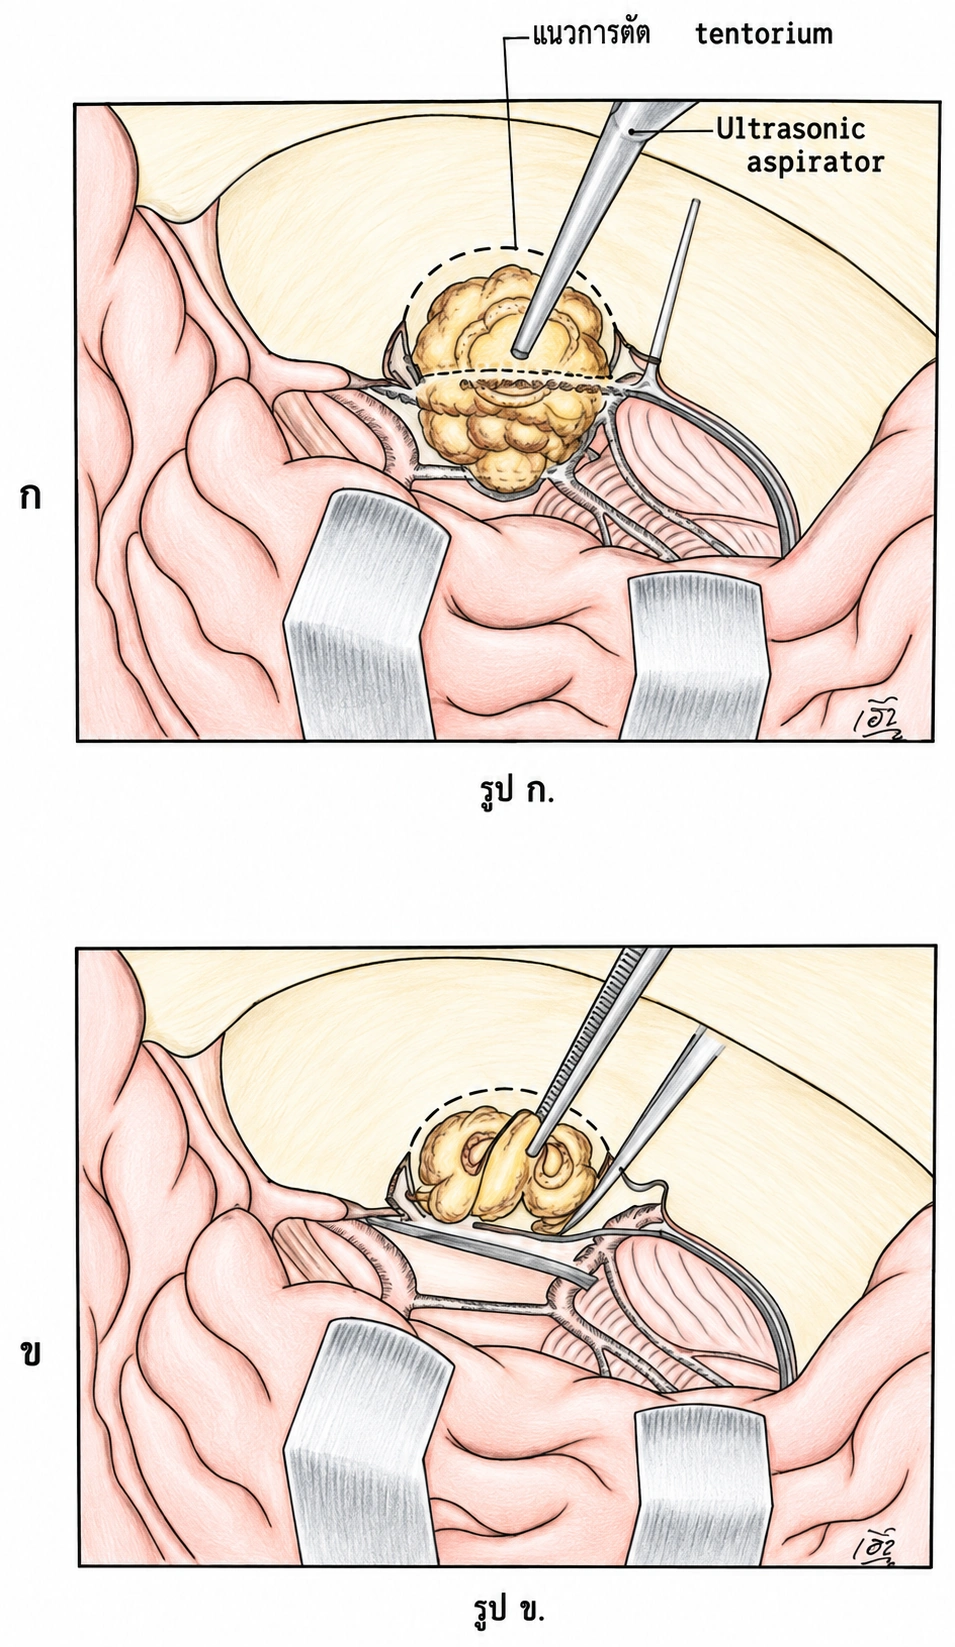
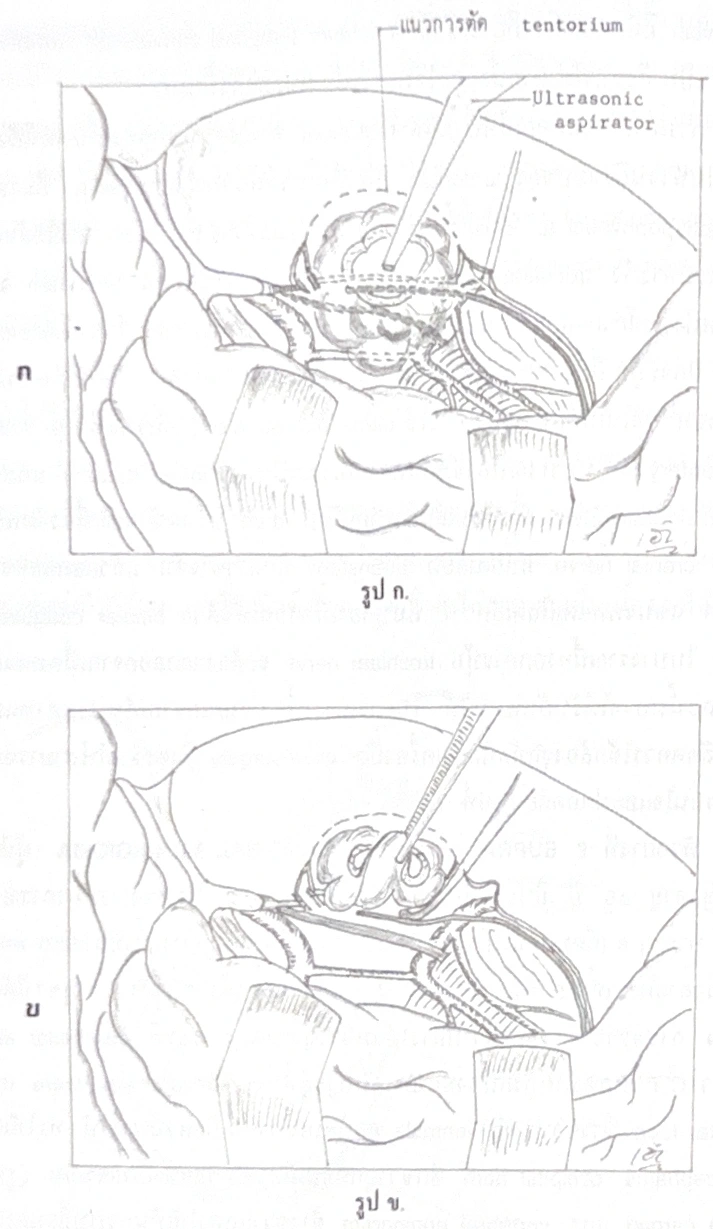 AI-enhanced and colorized image · Switch to the original image
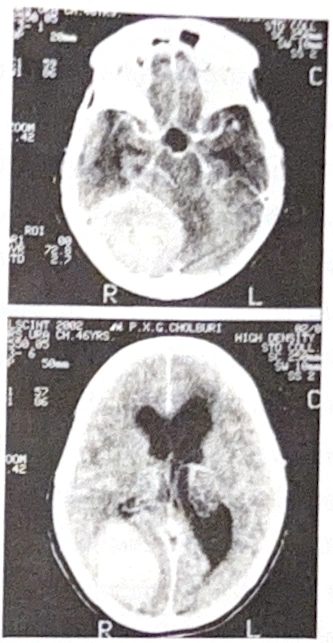
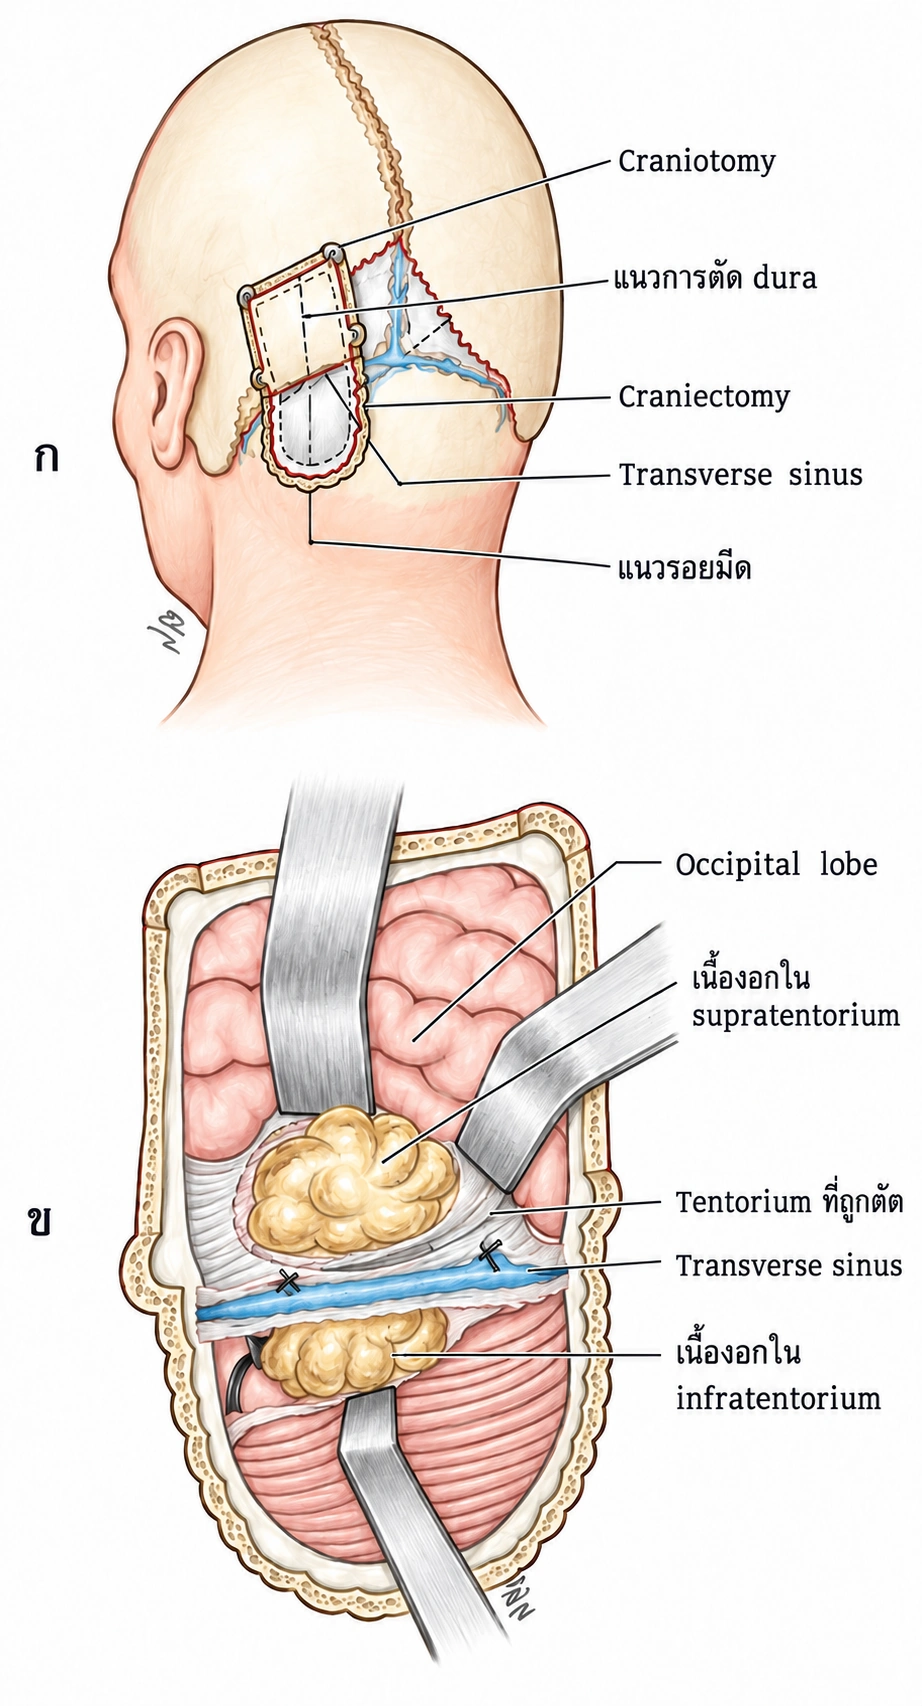
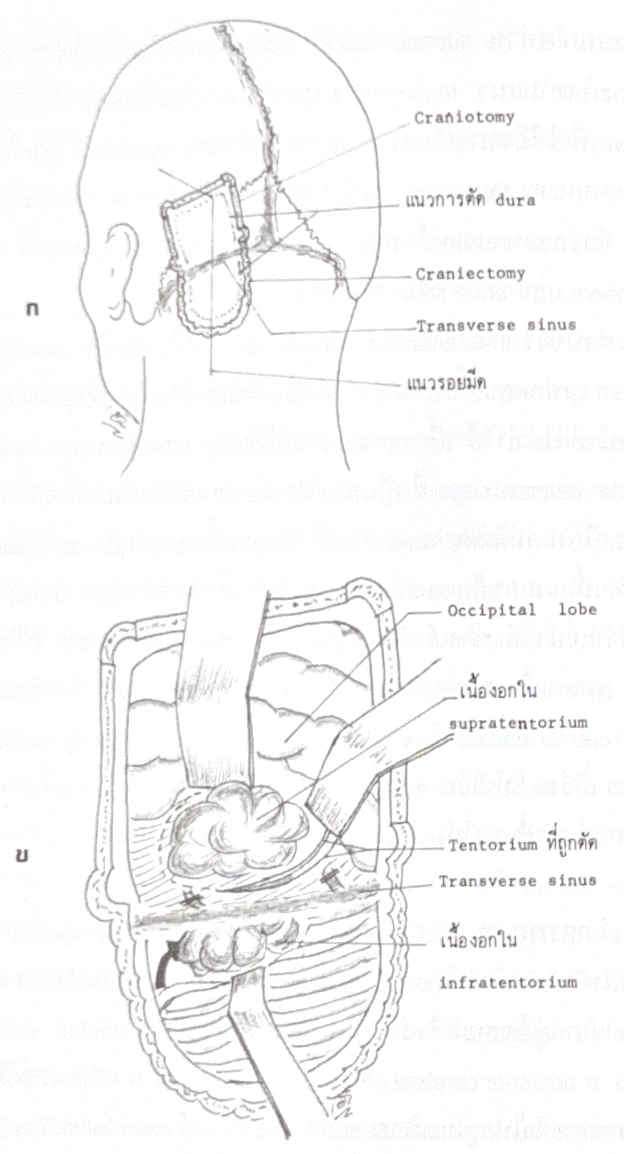 AI-enhanced and colorized image · Switch to the original image
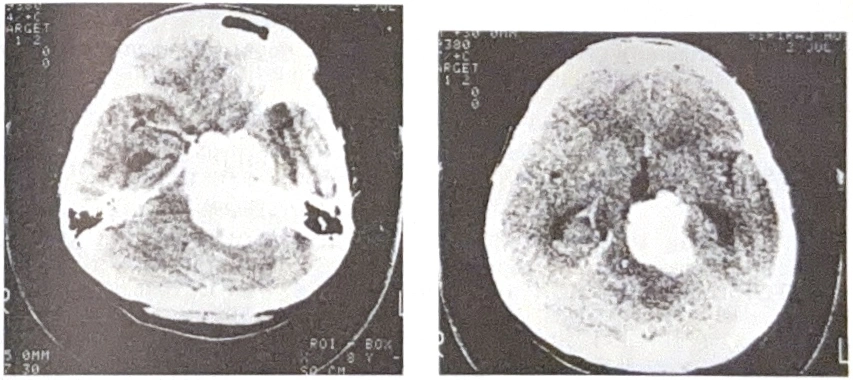
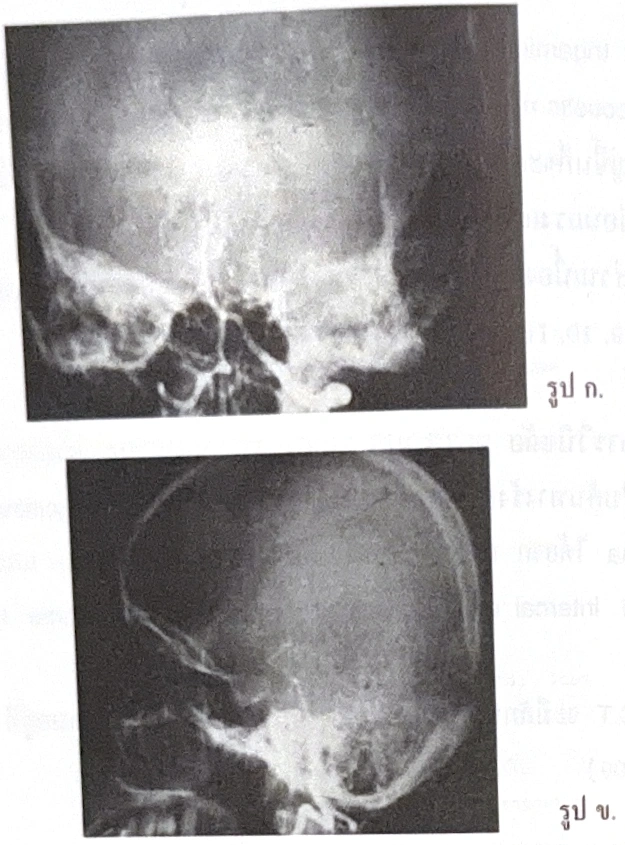
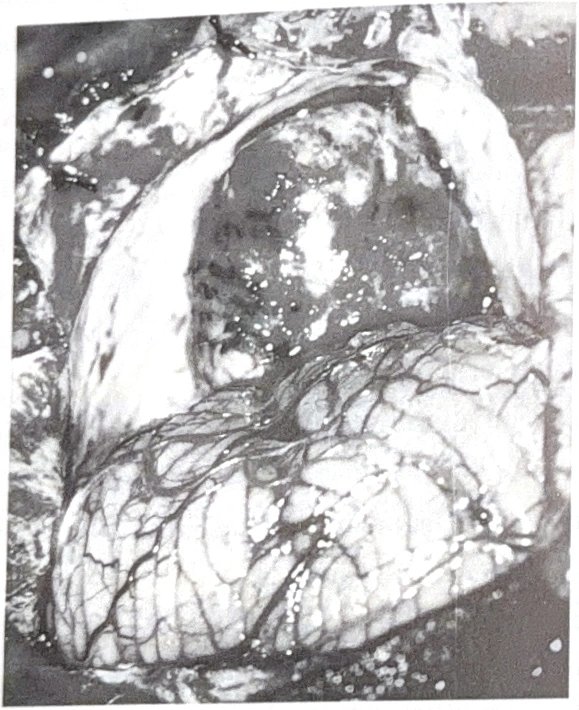
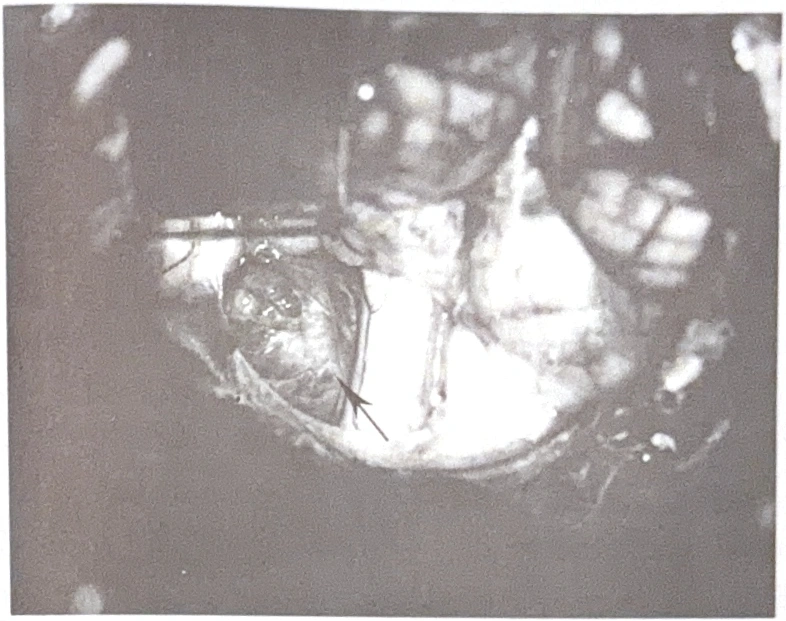
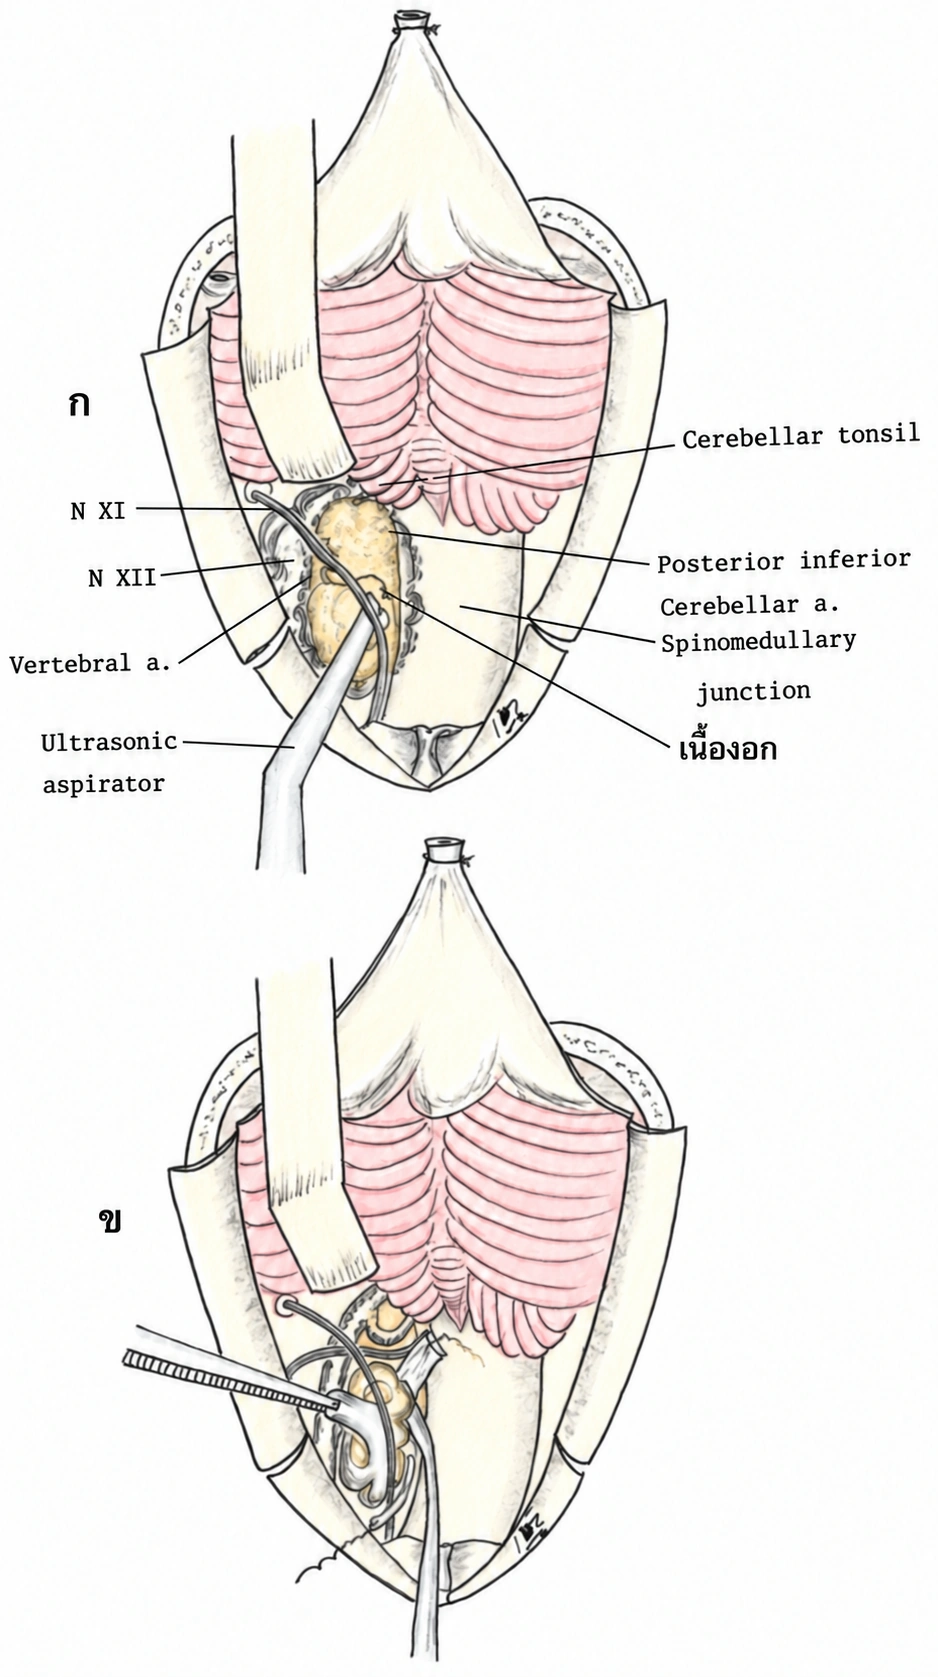
 AI-enhanced and colorized image · Switch to the original image
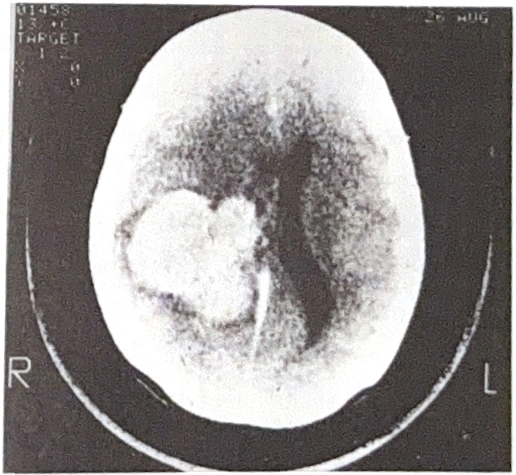
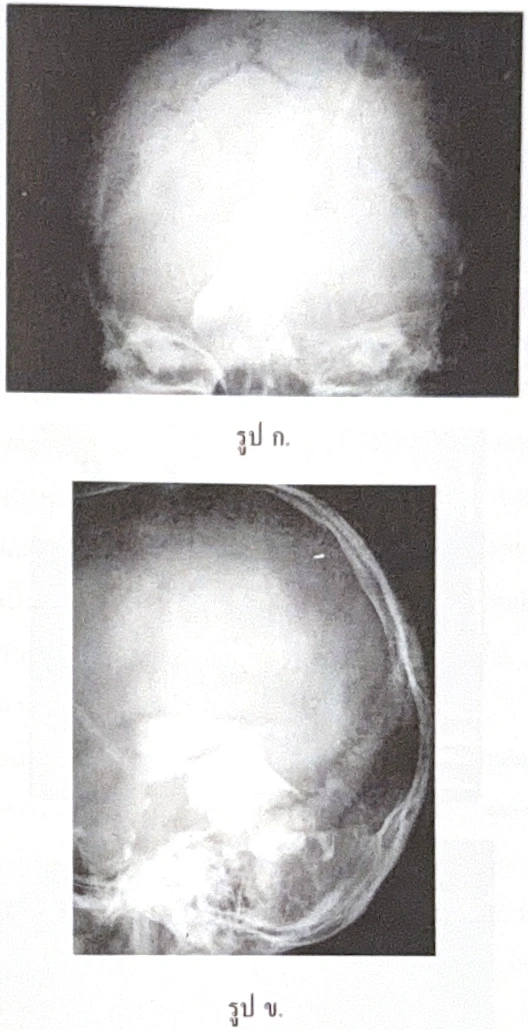
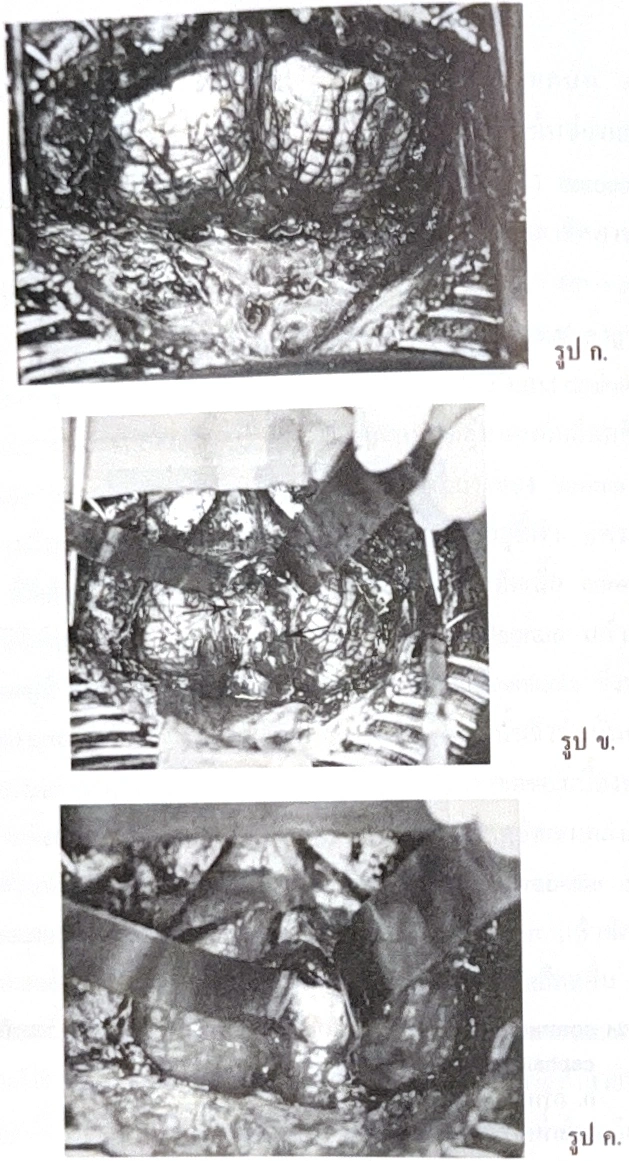
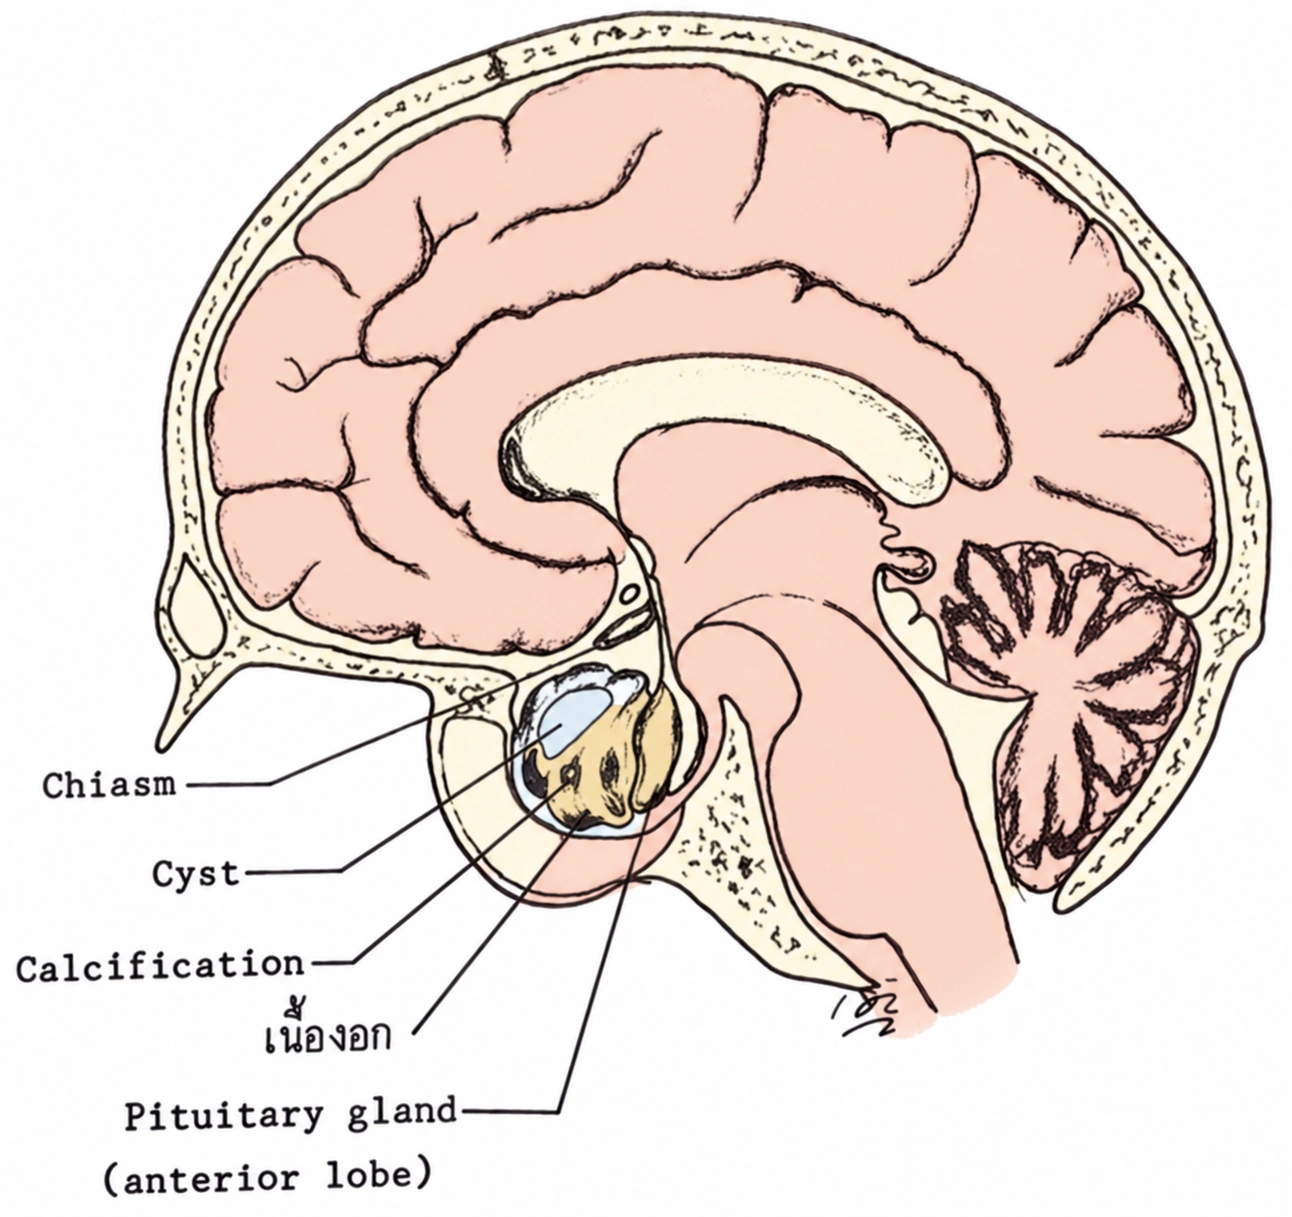
 Image enhanced and colorized with AI · Switch to the original image
 Image enhanced and colorized with AI · Switch to the original image
 Image enhanced and colorized with AI · Switch to the original image
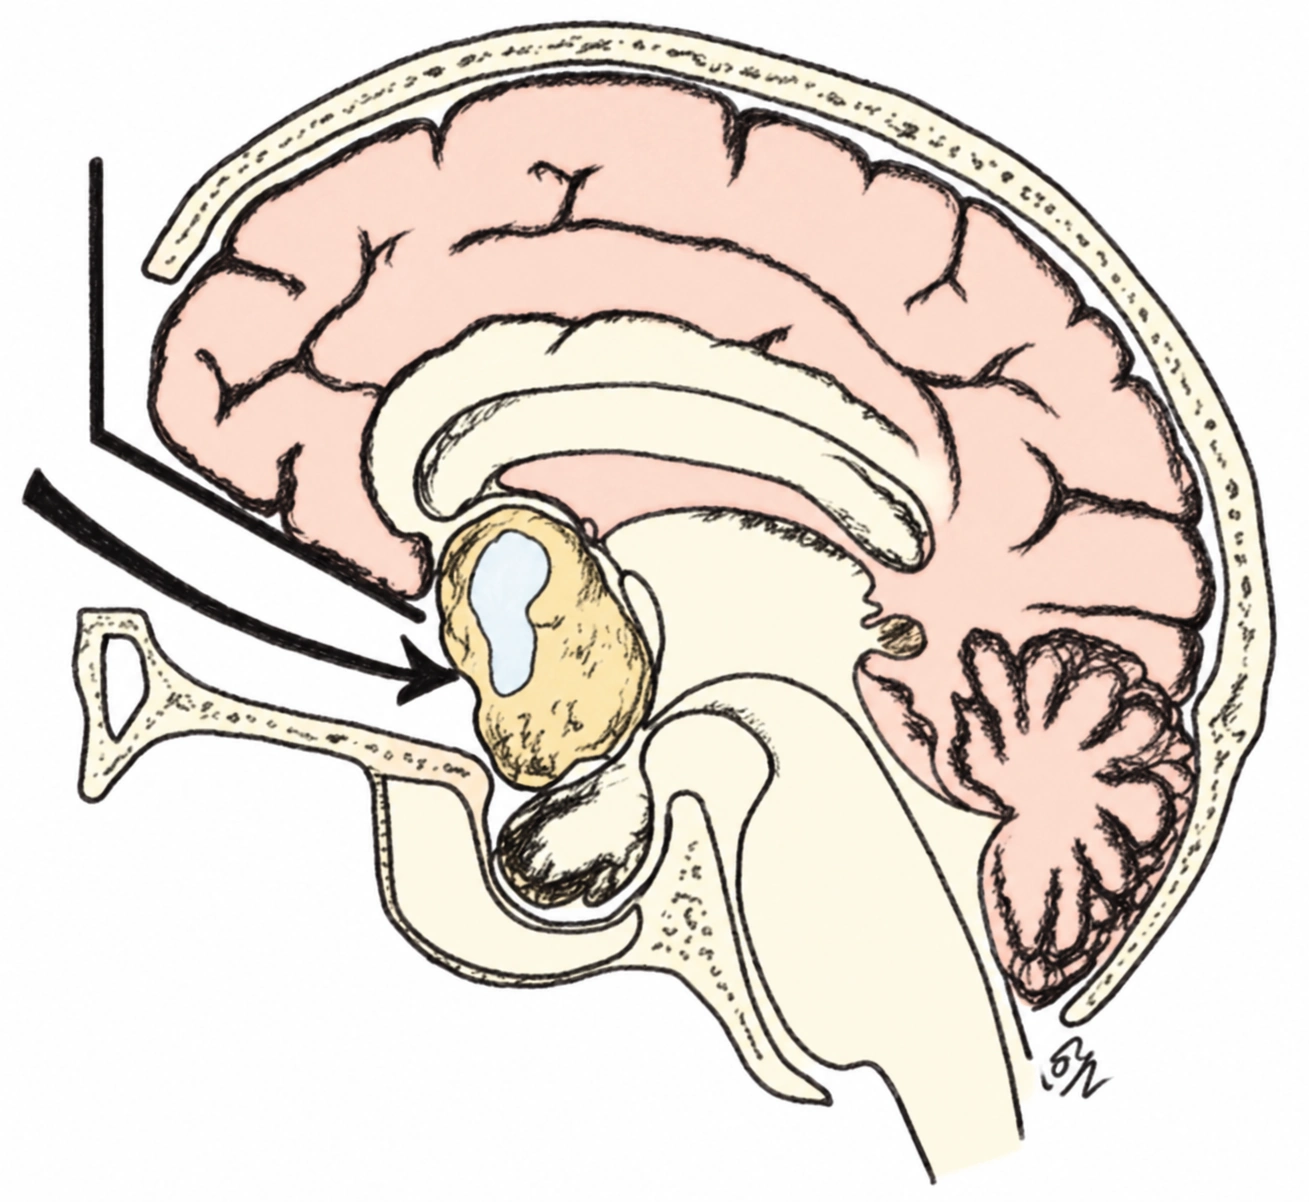
 Image enhanced and colorized with AI · Switch to the original image
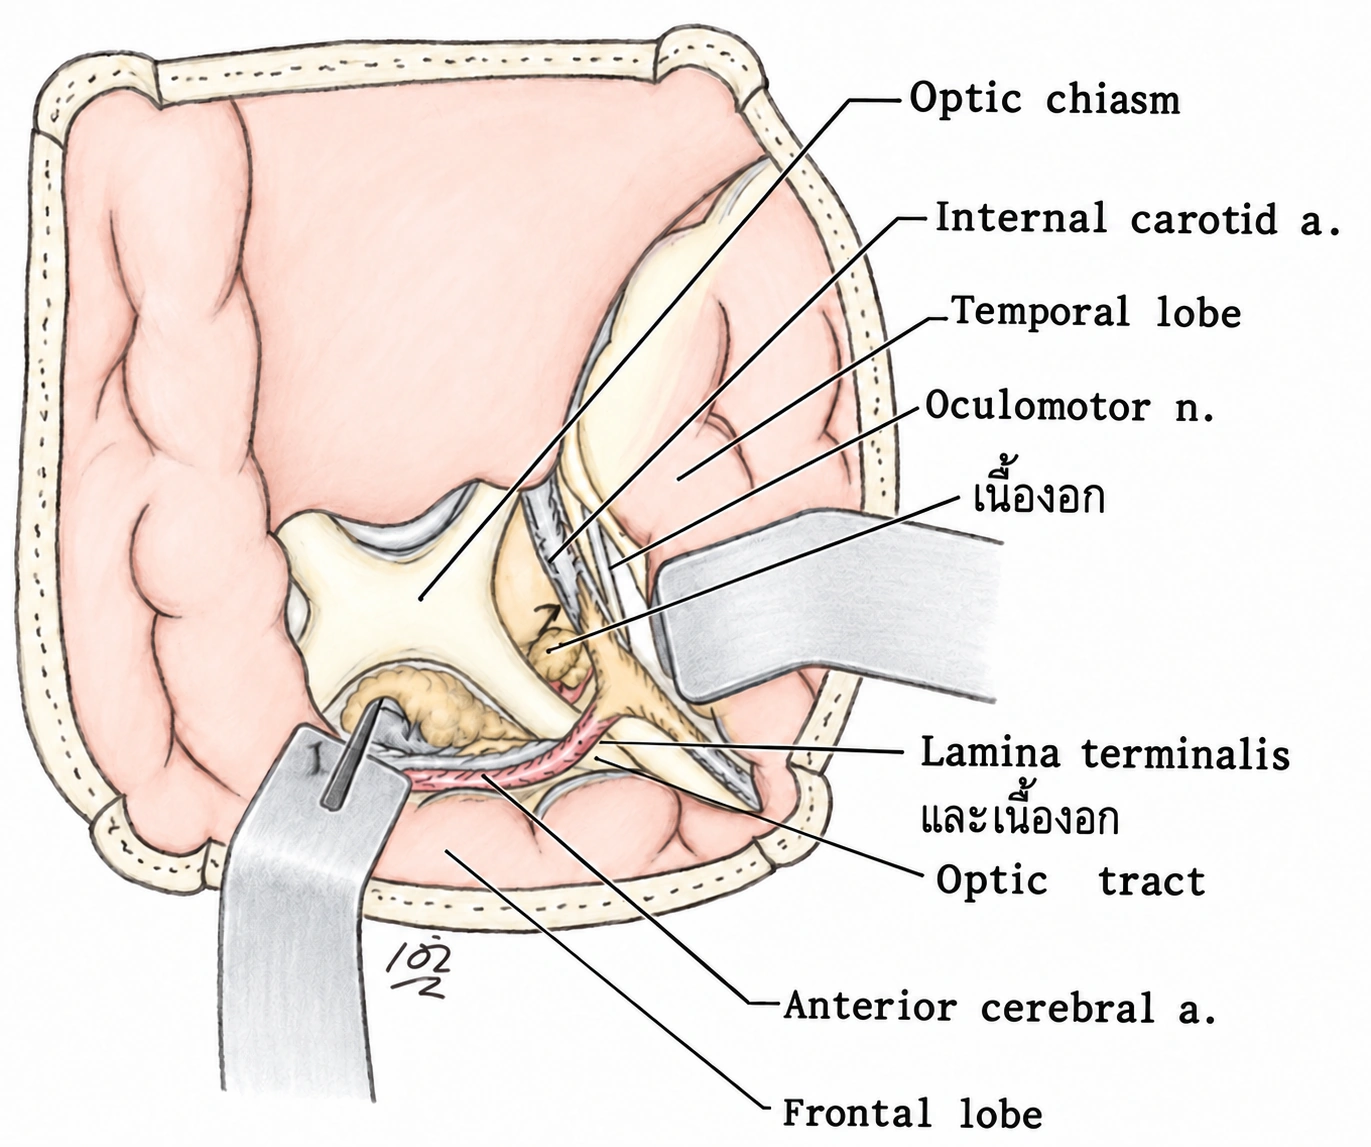
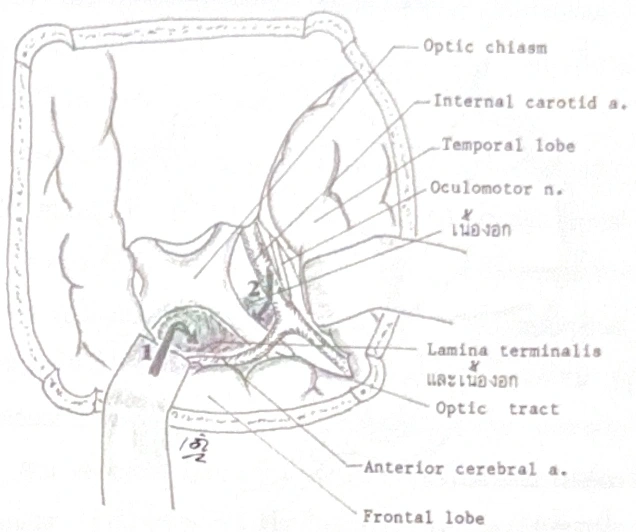 Image enhanced and colorized with AI · Switch to the original image
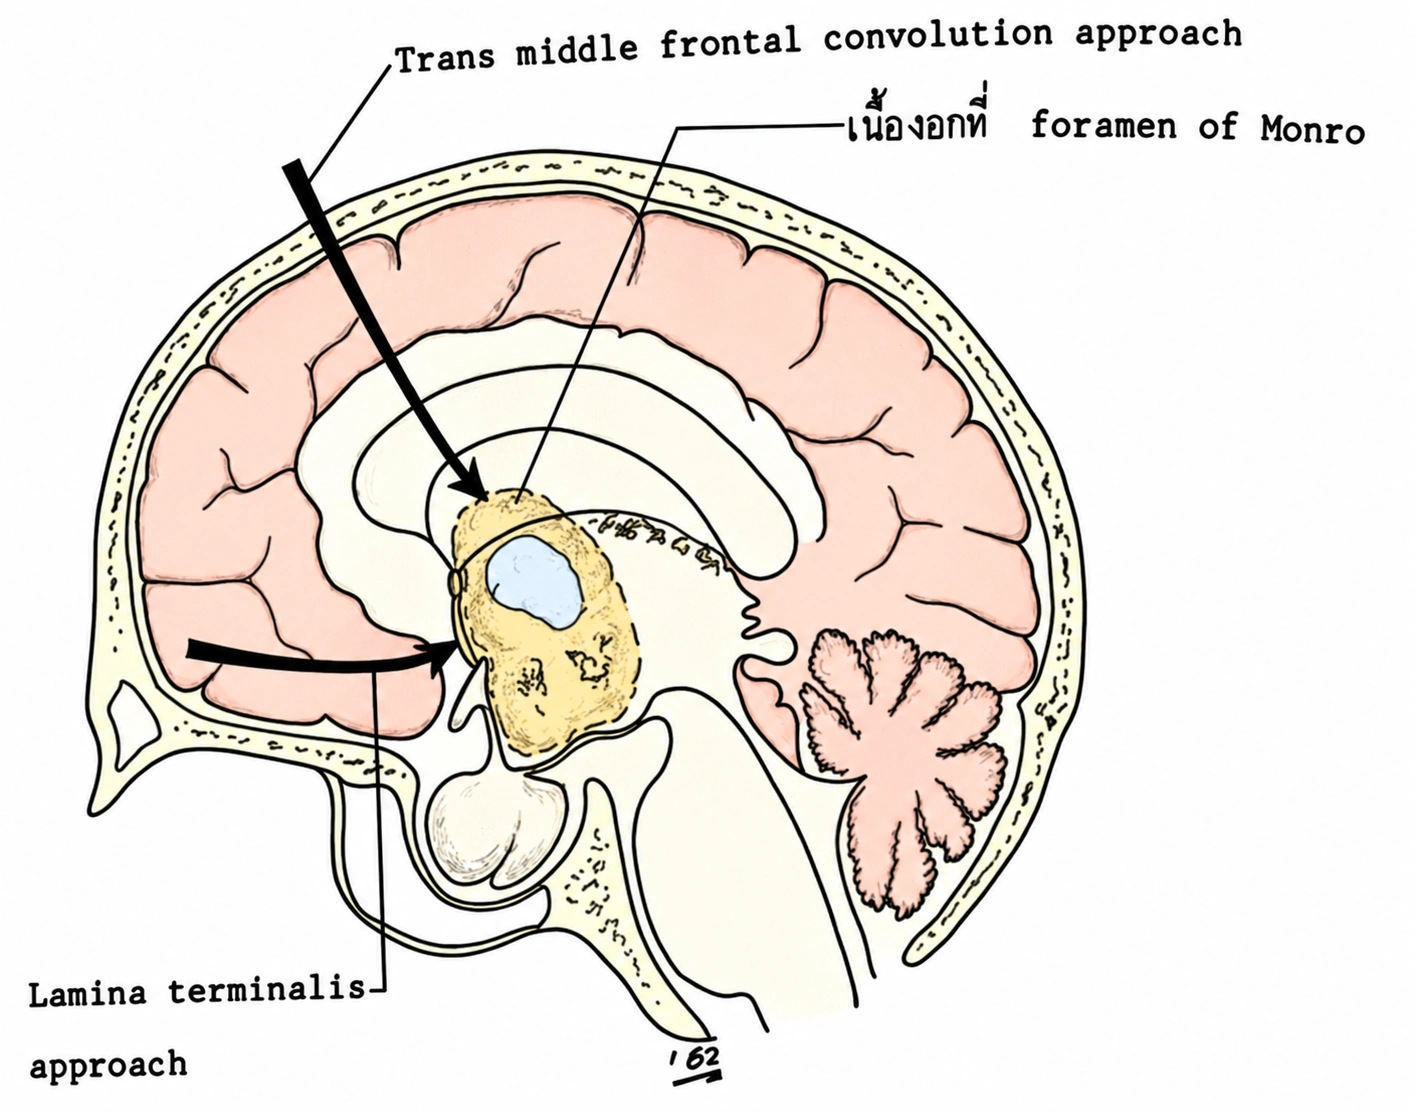
 Image enhanced and colorized with AI · Switch to the original image
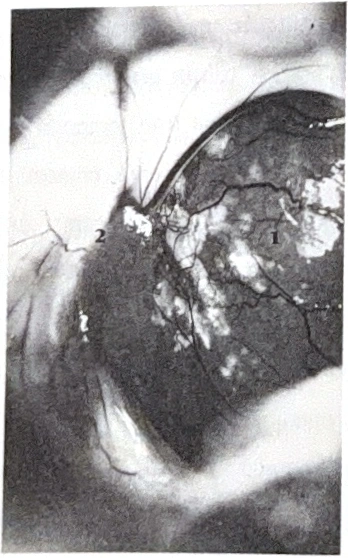
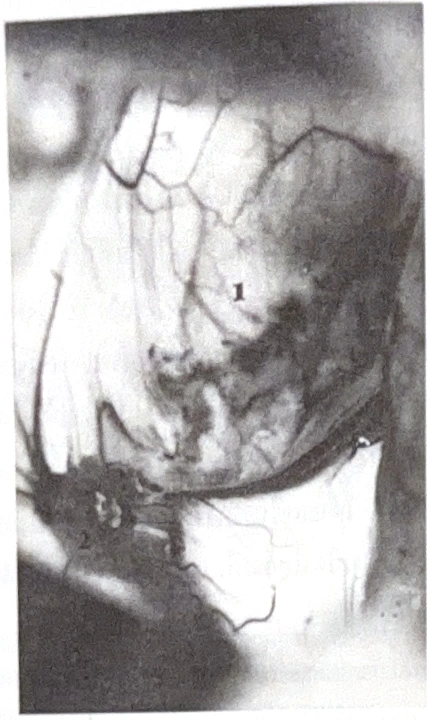
 Image enhanced and colorized with AI · Switch to the original image
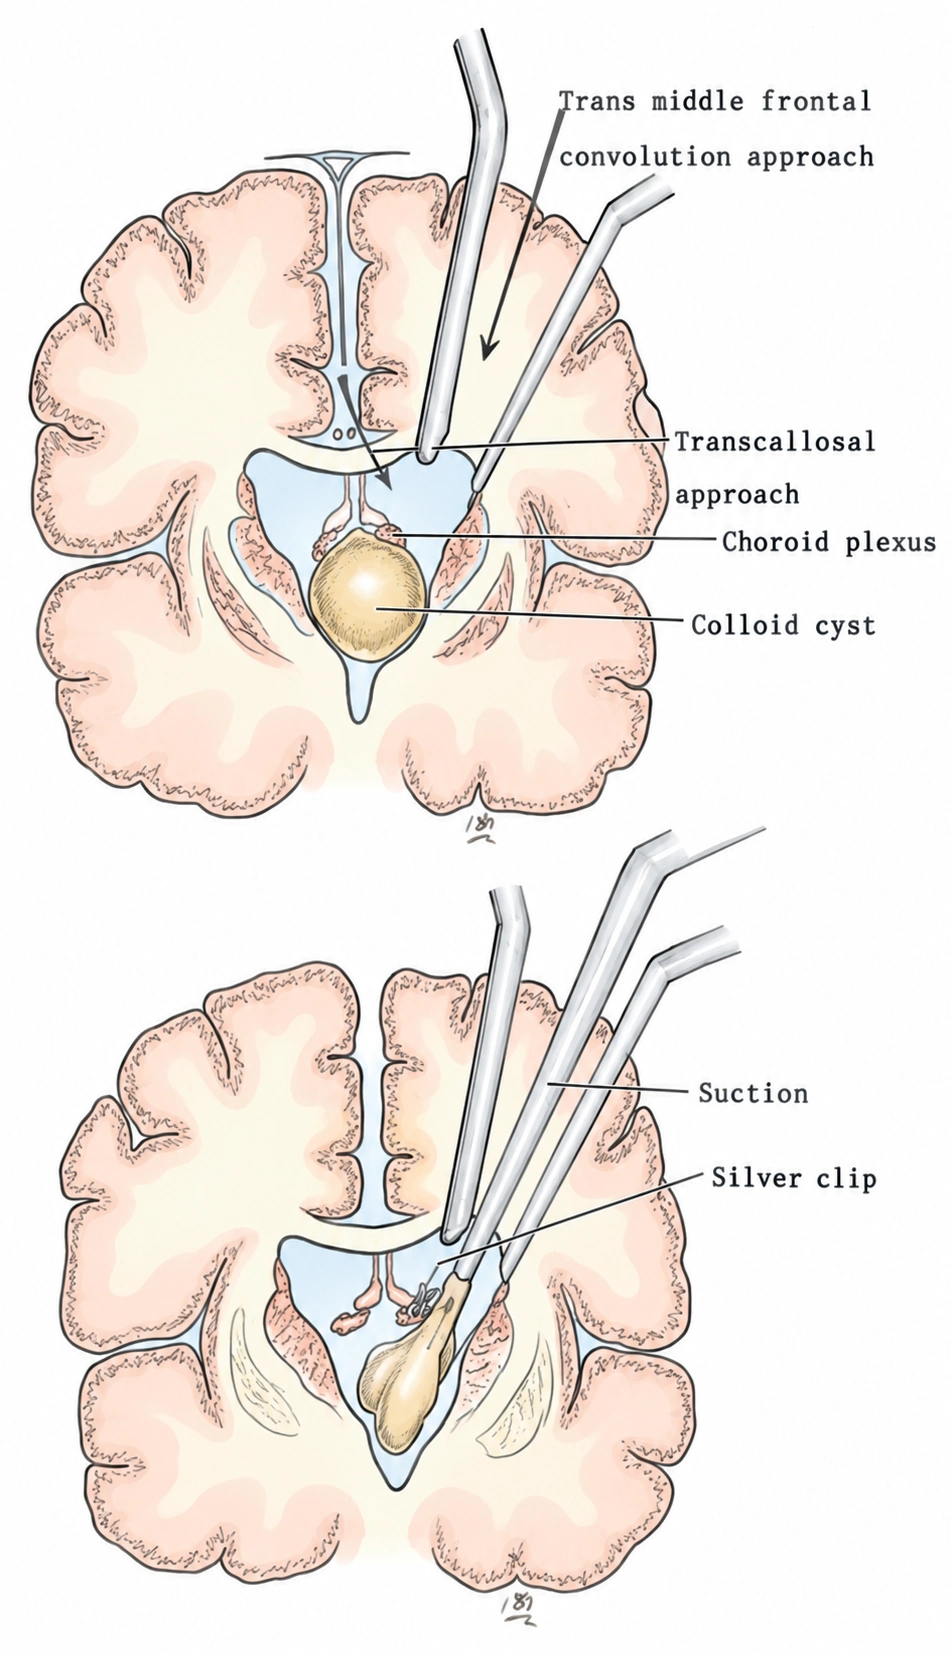
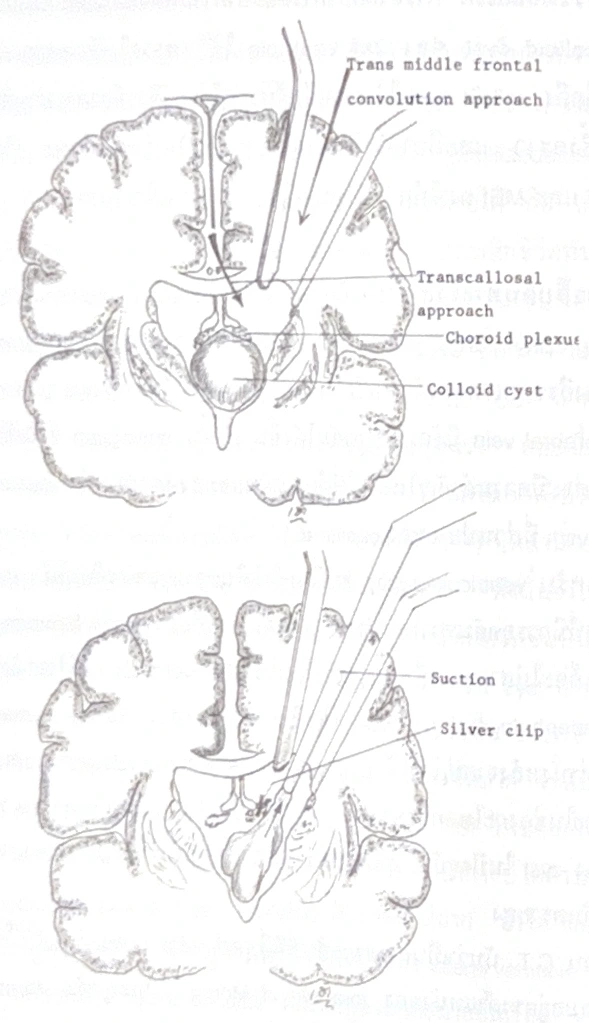 Image enhanced and colorized with AI · Switch to view the original
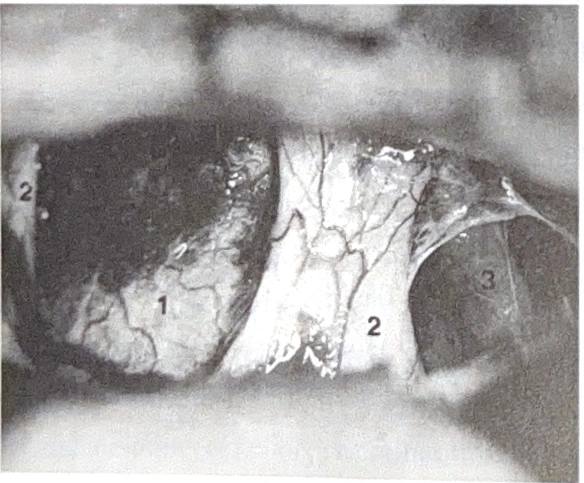
 Image enhanced and colorized with AI · Switch to view the original
 Image enhanced and colorized with AI · Switch to view the original
 Image enhanced and colorized with AI · Switch to view the original
 Image enhanced and colorized with AI · Switch to view the original
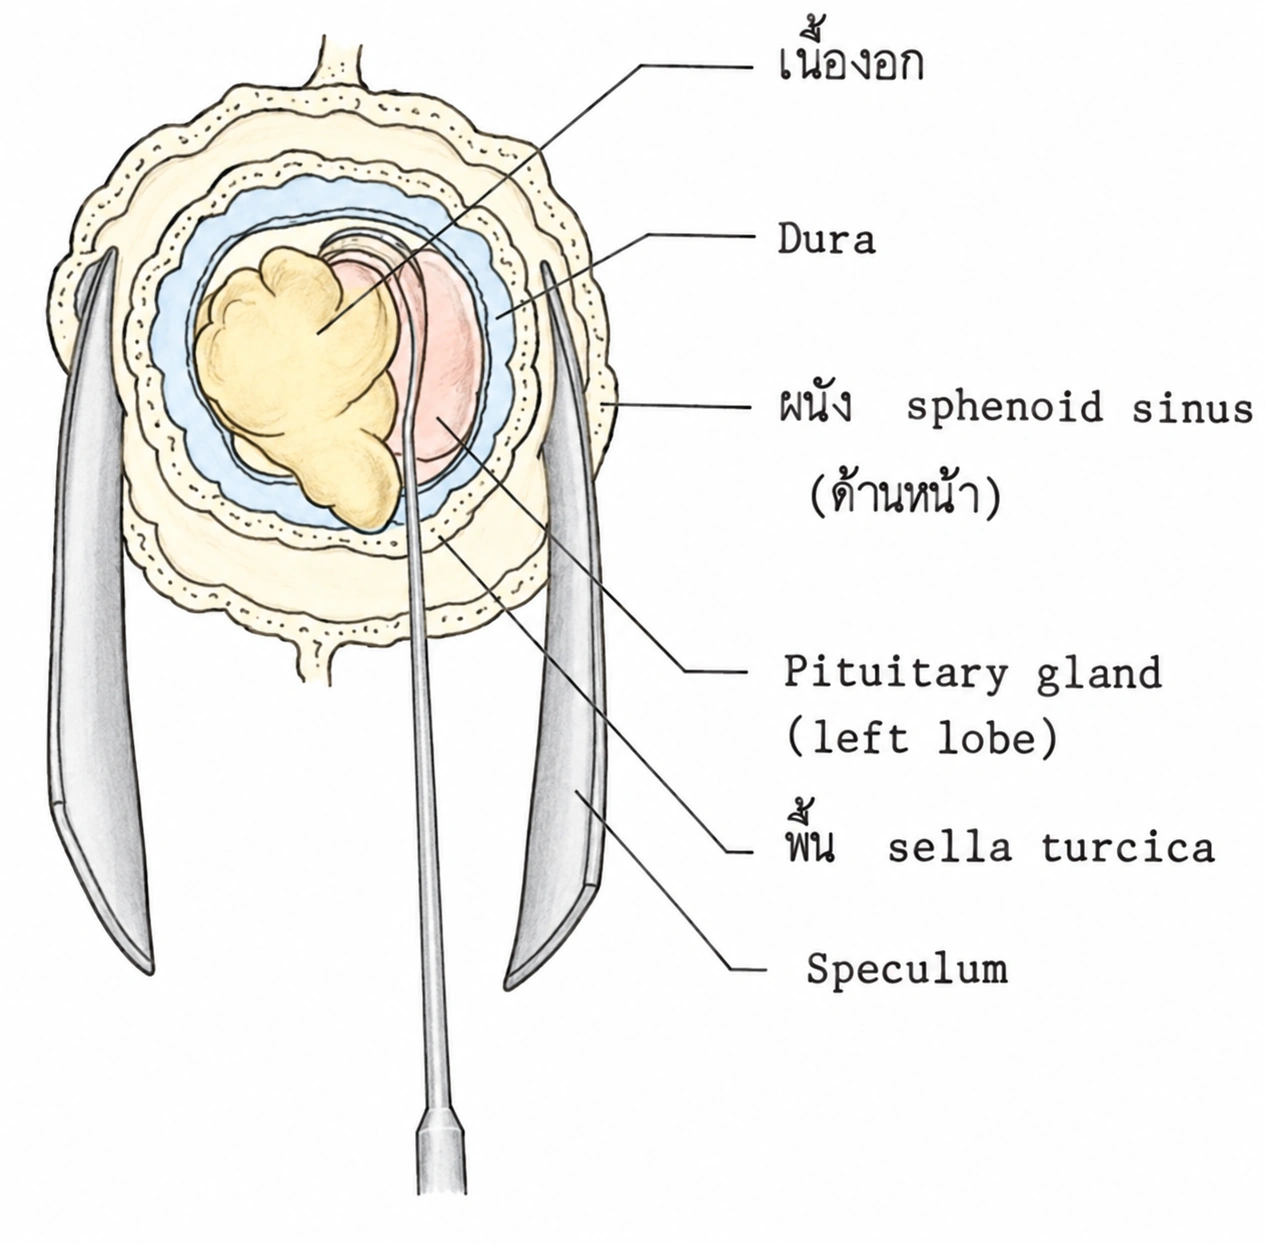
 Image enhanced and colorized with AI · Switch to view the original